
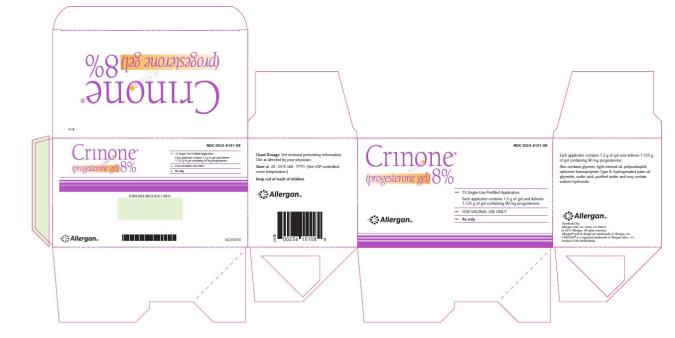
Crinone progesterone 90 mg/1.125g Gel, 15 applicators — NDC 0023-6151-08 (Billing 00023-6151-08)
This is a package of 15 applicators of Crinone progesterone 90 mg/1.125g Gel from Allergan, Inc., marketed since May 1997 and currently FDA-listed; retail pharmacies pay about $27.97 per g (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0023-6151-08 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0023 labeler · 6151 product · 08 package
- Package marketed since
- May 13, 1997
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0023615108 9
- Medicaid fills, this package
- 464 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Progesterone (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 031769
- GCN: 63011
- GPI-14 (Medi-Span): 55370060004020
- HICL (First Databank): 020653
- AHFS class code: 68:32.00.00
- RxCUI (RxNorm): 153579
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Progesterone class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Vaginal progesterone is used as part of assisted reproductive technology (ART; fertility treatment) in women experiencing infertility (not getting pregnant despite having carefully timed, unprotected sex). Vaginal progesterone is also used to bring on menstruation (periods) in women of childbearing age experiencing absence of menstruation who have had normal periods and then stopped. Progesterone is in a class of medications called progestins (female hormones). It works as a part of ART by increase embryo implantation and decrease the risk of miscarriage. It works to bring on menstruation by...
Read the full MedlinePlus article ↗- Progesterone vaginal products help with fertility treatment. Endometrin supports embryo implantation and early pregnancy in women under 35 in an ART program. Crinone is also used i...
- Both are placed in the vagina. How often depends on the product and why you use it, so follow your prescriber and the label. With Crinone, using more gel will not give you a bigger...
- With Crinone, common ones are breast tenderness, headache, nausea, cramps, bloating, sleepiness and mood changes. Call your doctor if they bother you or if depression worsens.
- Get help right away if you suspect a blood clot, stroke or heart attack. Hormone treatment can cause serious clots, and the medicine should be stopped if one is suspected.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Progesterone — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $27.973 | $472.04 / 16.88 g |
| Medicaid paysCMS SDUD · 12 mo | $28.79 | $485.89 / 16.88 g |
| Medicare drug plans payPart D · Q2 2026 | $30.55 | $515.53 / 16.88 g |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00023-6151-08 You're viewing this Main listing | 15 APPLICATOR in 1 CARTON / 1.125 g in 1 APPLICATOR | 1997-05-13 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Crinone 90 mg/1.125gthis 00023-6151-08 | Allergan, | 15 applicators | $27.973 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Allergan, Inc. labeler code 00023
- REFRESH Optive Mega-3 Carboxymethylcellulose sodium, Glycerin and Polysorbate 80 5 mg/mL; 10 mg/mL; 80 5 mg/mL Solution/ Drops NDC 0023-5773-05
- LILETTA Levonorgestrel 52 mg Intrauterine Device NDC 0023-5858-01
- Taytulla norethindrone acetate and ethinyl estradiol, and ferrous fumarate Kit NDC 0023-5862-29
- INFeD Iron Dextran 50 mg/mL Injection NDC 0023-6082-10
- Condylox podofilox 5 mg/g Gel NDC 0023-6118-03
- Crinone progesterone 45 mg/1.125g Gel NDC 0023-6150-04
- OXYTROL Oxybutynin 3.9 mg/d Patch NDC 0023-6153-08
- Ubrelvy ubrogepant 50 mg Tablet NDC 0023-6498-01
- ubrogepant 50 mg Tablet NDC 0023-6499-00
- Ubrelvy ubrogepant 100 mg Tablet NDC 0023-6501-01
- ubrogepant 100 mg Tablet NDC 0023-6502-00
- Refresh Relieva Carboxymethylcellulose sodium, Glycerin 5 mg/mL; 9 mg/mL Solution/ Drops NDC 0023-6630-03
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Assisted Reproductive Technology Crinone 8% is indicated for progesterone supplementation or replacement as part of an Assisted Reproductive Technology ("ART") treatment for infertile women with progesterone deficiency. Secondary Amenorrhea Crinone 4% is indicated for the treatment of secondary amenorrhea. Crinone 8% is indicated for use in women who have failed to respond to treatment with Crinone 4%.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Assisted Reproductive Technology Crinone 8% is administered vaginally at a dose of 90 mg once daily in women who require progesterone supplementation. Crinone 8% is administered vaginally at a dose of 90 mg twice daily in women with partial or complete ovarian failure who require progesterone replacement. If pregnancy occurs, treatment may be continued until placental autonomy is achieved, up to 10 to 12 weeks.
Secondary Amenorrhea Crinone 4% is administered vaginally every other day up to a total of six doses. For women who fail to respond, a trial of Crinone 8% every other day up to a total of six doses may be instituted. It is important to note that a dosage increase from the 4% gel can only be accomplished by using the 8% gel.
Increasing the volume of gel administered does not increase the amount of progesterone absorbed.
⛔ Contraindications ▾
CONTRAINDICATIONS Crinone should not be used in individuals with any of the following conditions: Known sensitivity to Crinone (progesterone or any of the other ingredients) Undiagnosed vaginal bleeding Liver dysfunction or disease Known or suspected malignancy of the breast or genital organs Missed abortion Active thrombophlebitis or thromboembolic disorders, or a history of hormone-associated thrombophlebitis or thromboembolic disorders
⚠️ Warnings ▾
WARNINGS The physician should be alert to the earliest manifestations of thrombotic disorders (thrombophlebitis, cerebrovascular disorders, pulmonary embolism, and retinal thrombosis). Should any of these occur or be suspected, the drug should be discontinued immediately. Progesterone and progestins have been used to prevent miscarriage in women with a history of recurrent spontaneous pregnancy losses.
No adequate evidence is available to show that they are effective for this purpose.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Assisted Reproductive Technology In a study of 61 women with ovarian failure undergoing a donor oocyte transfer procedure receiving Crinone 8% twice daily, treatment-emergent adverse events occurring in 5% or more of the women are shown in Table 3. TABLE 3 Treatment-Emergent Adverse Events in ≥ 5% of Women Receiving Crinone 8% Twice Daily Study COL1620-007US (n = 61) Body as a Whole Bloating 7% Cramps NOS 15% Pain 8% Central and Peripheral Nervous System Dizziness 5% Headache 13% Gastro-Intestinal System Nausea 7% Reproductive, Female Breast Pain 13% Moniliasis Genital 5% Vaginal Discharge 7% Skin and Appendages Pruritus Genital 5% In a second clinical study of 139 women using Crinone 8% once daily for luteal phase support while undergoing an in vitro fertilization procedure, treatment-emergent adverse events reported in ≥ 5% of the women are shown in Table 4.
TABLE 4 Treatment-Emergent Adverse Events in ≥ 5% of Women Receiving Crinone 8% Once Daily Study COL1620-F01 (n = 139) Body as a Whole Abdominal Pain 12% Perineal Pain Female 17% Central and Peripheral Nervous System Headache 17% Gastro-Intestinal System Constipation 27% Diarrhea 8% Nausea 22% Vomiting 5% Musculo-Skeletal System Arthralgia 8% Psychiatric Depression 11% Libido Decreased 10% Nervousness 16% Somnolence 27% Reproductive, Female Breast Enlargement 40% Dyspareunia 6% Urinary System Nocturia 13% Secondary Amenorrhea In three studies, 127 women with secondary amenorrhea received estrogen replacement therapy and Crinone 4% or 8% every other day for six doses.
Treatment-emergent adverse events during estrogen and Crinone treatment that occurred in 5% or more of women are shown in Table 5. TABLE 5 Treatment-Emergent Adverse Events in ≥ 5% of Women Receiving Estrogen Treatment and Crinone Every Other Day Studies COL1620-004US, COL1620-005US, COL1620-009US Estrogen + Crinone 4% n = 62 Estrogen + Crinone 8% n = 65 Body as a Whole Abdominal Pain 3 (5%) 6 (9%) Appetite Increased 3 (5%) 5 (8%) Bloating 8 (13%) 8 (12%) Cramps NOS 12 (19%) 17 (26%) Fatigue 13 (21%) 14 (22%) Central and Peripheral Nervous System Headache 12 (19%) 10 (15%) Gastro-Intestinal System Nausea 5 (8%) 4 (6%) Musculo-Skeletal System Back Pain 5 (8%) 2 (3%) Myalgia 5 (8%) 0 (0%) Psychiatric Depression 12 (19%) 10 (15%) Emotional Lability 14 (23%) 14 (22%) Sleep Disorder 11 (18%) 12 (18%) Reproductive, Female Vaginal Discharge 7 (11%) 2 (3%) Resistance Mechanism Upper Respiratory Tract Infection 3 (5%) 5 (8%) Skin and Appendages Pruritus Genital 1 (2%) 4 (6%)
🔄 Drug Interactions ▾
Drug Interactions No drug interactions have been assessed with Crinone.
🤰 Pregnancy ▾
Pregnancy [See CLINICAL STUDIES, Assisted Reproductive Technology ] Crinone 8% has been used to support embryo implantation and maintain pregnancies through its use as part of ART treatment regimens in two clinical studies (studies COL1620-007US and COL1620-F01). In the first study (COL1620-007US), 54 Crinone-treated women had donor oocyte transfer procedures, and clinical pregnancies occurred in 26 women (48%). The outcomes of these 26 pregnancies were as follows: one woman had an elective termination of pregnancy at 19 weeks due to congenital malformations (omphalocele) associated with a chromosomal abnormality; one woman pregnant with triplets had an elective termination of her pregnancy; seven women had spontaneous abortions; and 17 women delivered 25 apparently normal newborns.
In the second study (COL1620-F01), Crinone 8% was used in the luteal phase support of women undergoing in vitro fertilization ("IVF") procedures. In this multi-center, open-label study, 139 women received Crinone 8% once daily beginning within 24 hours of embryo transfer and continuing through Day 30 post-transfer. Clinical pregnancies assessed at Day 90 post-transfer were seen in 36 (26%) of women.
Thirty-two women (23%) delivered newborns and four women (3%) had spontaneous abortions. Of the 47 newborns delivered, one had a teratoma associated with a cleft palate; one had respiratory distress syndrome; 44 were apparently normal and one was lost to follow-up.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use The safety and effectiveness in geriatric patients (over age 65) have not been established.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of overdosage with Crinone. In the case of overdosage, however, discontinue Crinone, treat the patient symptomatically, and institute supportive measures. As with all prescription drugs, this medicine should be kept out of the reach of children.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Progesterone is a naturally occurring steroid that is secreted by the ovary, placenta, and adrenal gland. In the presence of adequate estrogen, progesterone transforms a proliferative endometrium into a secretory endometrium. Progesterone is essential for the development of decidual tissue, and the effect of progesterone on the differentiation of glandular epithelia and stroma has been extensively studied.
Progesterone is necessary to increase endometrial receptivity for implantation of an embryo. Once an embryo is implanted, progesterone acts to maintain the pregnancy. Normal or near-normal endometrial responses to oral estradiol and intramuscular progesterone have been noted in functionally agonadal women through the sixth decade of life.
Progesterone administration decreases the circulatory levels of gonadotropins. Pharmacokinetics Absorption Due to the sustained release properties of Crinone, progesterone absorption is prolonged with an absorption half-life of approximately 25 to 50 hours, and an elimination half-life of 5 to 20 minutes. Therefore, the pharmacokinetics of Crinone are rate-limited by absorption rather than by elimination.
The bioavailability of progesterone in Crinone was determined relative to progesterone administered intramuscularly. In a single dose crossover study, 20 healthy, estrogenized postmenopausal women received 45 mg or 90 mg progesterone vaginally in Crinone 4% or Crinone 8%, or 45 mg or 90 mg progesterone intramuscularly. The pharmacokinetic parameters (mean ± standard deviation) are shown in Table 1.
TABLE 1 Single Dose Relative Bioavailability Crinone 4% 45 mg Intramuscular Progesterone Crinone 8% 90 mg Intramuscular Progesterone C max (ng/mL) 13.15 ± 6.49 39.06 ± 13.68 14.87 ± 6.32 53.76 ±
14.9C avg 0-24 (ng/mL) 6.94 ± 4.24 22.41 ± 4.92 6.98 ± 3.21 28.98 ±
8.75AUC 0-96 (ng∙hr/mL) 288.63 ± 273.72 806.26 ± 102.75 296.78 ± 129.90 1378.91 ± 176.39 T max (hr) 5.6 ± 1.84 8.2 ± 6.43 6.8 ± 3.3 9.2 ± 2.7 t 1/2 (hr) 55.13 ± 28.04 28.05 ± 16.87 34.8 ± 11.3 19.6 ±
6.0F (%) 27.6
19.8C max - maximum progesterone serum concentration C avg 0-24 - average progesterone serum concentration over 24 hours AUC 0-96 - area under the drug concentration versus time curve from 0-96 hours post dose T max - time to maximum progesterone concentration t 1/2 - elimination half-life F - relative bioavailability The multiple dose pharmacokinetics of Crinone 4% and Crinone 8% administered every other day and Crinone 8% administered daily or twice daily for 12 days were studied in 10 healthy, estrogenized postmenopausal women in two separate studies.
Steady state was achieved within the first 24 hours after initiation of treatment. The pharmacokinetic parameters (mean ± standard deviation) after the last administration of Crinone 4% or 8% derived from these studies are shown in Table 2. TABLE 2 Multiple Dose Pharmacokinetics Assisted Reproductive Technology Secondary Amenorrhea Daily Dosing 8% Twice Daily Dosing 8% Every Other Day Dosing 4% Every Other Day Dosing 8% C max (ng/mL) 15.97± 5.05 14.57 ± 4.49 13.21± 9.46 13.67 ±
3.58C avg (ng/mL) 8.99 ± 3.53 11.6 ± 3.47 4.05 ± 2.85 6.75 ±
2.83T max (hr) 5.40 ± 0.97 3.55 ± 2.48 6.67 ± 3.16 7.00 ±
2.88AUC 0-t (ng∙hr/mL) 391.98 ±153.28 138.72 ± 41.58 242.15 ± 167.88 438.36 ± 223.36 t 1/2 (hr) 45.00 ± 34.70 25.91 ± 6.15 49.87 ± 31.20 39.08 ±
12.88C max -maximum progesterone serum concentration C avg -average progesterone serum concentration T max -time to maximum progesterone concentration AUC 0-t -area under the drug concentration versus time curve t 1/2 -elimination half-life Distribution Progesterone is extensively bound to serum proteins (~ 96-99%), primarily to serum albumin and corticosteroid binding globulin. Metabolism The major urinary metabolite of oral progesterone is 5β-pregnan-3α, 20α-diol glucuronide which is present in plasma in the conjugated form only.
Plasma metabolites also include 5β-pregnan-3α-ol-20-one (5β-pregnanolone) and 5α-preg… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Crinone is available in the following strengths: 4% gel (45 mg) in a single use, disposable, white polypropylene vaginal applicator with a teal twist-off cap. Each applicator contains 1.3 g of gel and delivers 1.125 g of gel. NDC 0023-6150-04 : 6 Single-use prefilled applicators.
8% gel (90 mg) in a single use, disposable, white polypropylene vaginal applicator with a teal twist-off cap. Each applicator contains 1.3 g of gel and delivers 1.125 g of gel. NDC 0023-6151-08 : 15 Single-use prefilled applicators.
Each applicator is wrapped and sealed in a foil overwrap. Store at 20-25ºC (68-77ºF). [See USP controlled room temperature.] Keep out of reach of children. Rx only For all medical inquiries contact: AbbVie Inc.
1-800-678-1605 Distributed by: AbbVie Inc. North Chicago, IL 60064 Content Updated: June 2017 © 2024 AbbVie. All rights reserved.
CRINONE and its design are trademarks of Allergan Sales, LLC, an AbbVie company.
📋 Description ▾
DESCRIPTION Crinone ® (progesterone gel) is a bioadhesive vaginal gel containing micronized progesterone in an emulsion system, which is contained in single use, polypropylene vaginal applicators. The carrier vehicle is an oil in water emulsion containing the water swellable, but insoluble polymer, polycarbophil. The progesterone is partially soluble in both the oil and water phase of the vehicle, with the majority of the progesterone existing as a suspension.
Physically, Crinone has the appearance of a soft, white to off-white gel. The active ingredient, progesterone, is present in either a 4% or an 8% concentration (w/w). The chemical name for progesterone is pregn-4-ene-3,20-dione.
It has an empirical formula of C 21 H 30 O 2 and a molecular weight of 314.5. The structural formula is: Progesterone exists in two polymorphic forms. Form 1, which is the form used in Crinone, exists as white orthorhombic prisms with a melting point of 127-131°C.
Each applicator delivers 1.125 grams of Crinone gel containing either 45 mg (4% gel) or 90 mg (8% gel) of progesterone in a base containing glycerin, light mineral oil, polycarbophil, carbomer homopolymer Type B, hydrogenated palm oil glyceride, sorbic acid, purified water and may contain sodium hydroxide. The structural formula
💬 Information for Patients ▾
Information for Patients The product should not be used concurrently with other local intravaginal therapy. If other local intravaginal therapy is to be used concurrently, there should be at least a 6-hour period before or after Crinone administration. Small, white globules may appear as a vaginal discharge possibly due to gel accumulation, even several days after usage.
⚠️ Precautions ▾
PRECAUTIONS General The pretreatment physical examination should include special reference to breast and pelvic organs, as well as Papanicolaou smear. In cases of breakthrough bleeding, as in all cases of irregular vaginal bleeding, nonfunctional causes should be considered. In cases of undiagnosed vaginal bleeding, adequate diagnostic measures should be undertaken.
Because progestogens may cause some degree of fluid retention, conditions which might be influenced by this factor (e.g., epilepsy, migraine, asthma, cardiac or renal dysfunction) require careful observation. The pathologist should be advised of progesterone therapy when relevant specimens are submitted. Patients who have a history of psychic depression should be carefully observed and the drug discontinued if the depression recurs to a serious degree.
A decrease in glucose tolerance has been observed in a small percentage of patients on estrogen-progestin combination drugs. The mechanism of this decrease is not known. For this reason, diabetic patients should be carefully observed while receiving progestin therapy.
Information for Patients The product should not be used concurrently with other local intravaginal therapy. If other local intravaginal therapy is to be used concurrently, there should be at least a 6-hour period before or after Crinone administration. Small, white globules may appear as a vaginal discharge possibly due to gel accumulation, even several days after usage.
Drug Interactions No drug interactions have been assessed with Crinone. Carcinogenesis, Mutagenesis, Impairment of Fertility Nonclinical toxicity studies to determine the potential of Crinone to cause carcinogenicity or mutagenicity have not been performed. The effect of Crinone on fertility has not been evaluated in animals.
Pregnancy [See CLINICAL STUDIES, Assisted Reproductive Technology ] Crinone 8% has been used to support embryo implantation and maintain pregnancies through its use as part of ART treatment regimens in two clinical studies (studies COL1620-007US and COL1620-F01). In the first study (COL1620-007US), 54 Crinone-treated women had donor oocyte transfer procedures, and clinical pregnancies occurred in 26 women (48%). The outcomes of these 26 pregnancies were as follows: one woman had an elective termination of pregnancy at 19 weeks due to congenital malformations (omphalocele) associated with a chromosomal abnormality; one woman pregnant with triplets had an elective termination of her pregnancy; seven women had spontaneous abortions; and 17 women delivered 25 apparently normal newborns.
In the second study (COL1620-F01), Crinone 8% was used in the luteal phase support of women undergoing in vitro fertilization ("IVF") procedures. In this multi-center, open-label study, 139 women received Crinone 8% once daily beginning within 24 hours of embryo transfer and continuing through Day 30 post-transfer. Clinical pregnancies assessed at Day 90 post-transfer were seen in 36 (26%) of women.
Thirty-two women (23%) delivered newborns and four women (3%) had spontaneous abortions. Of the 47 newborns delivered, one had a teratoma associated with a cleft palate; one had respiratory distress syndrome; 44 were apparently normal and one was lost to follow-up. Geriatric Use The safety and effectiveness in geriatric patients (over age 65) have not been established.
Pediatric Use Safety and effectiveness in pediatric patients have not been established. Nursing Mothers Detectable amounts of progestins have been identified in the milk of mothers receiving them. The effect of this on the nursing infant has not been determined.
🍼 Nursing Mothers ▾
Nursing Mothers Detectable amounts of progestins have been identified in the milk of mothers receiving them. The effect of this on the nursing infant has not been determined.
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption Due to the sustained release properties of Crinone, progesterone absorption is prolonged with an absorption half-life of approximately 25 to 50 hours, and an elimination half-life of 5 to 20 minutes. Therefore, the pharmacokinetics of Crinone are rate-limited by absorption rather than by elimination. The bioavailability of progesterone in Crinone was determined relative to progesterone administered intramuscularly.
In a single dose crossover study, 20 healthy, estrogenized postmenopausal women received 45 mg or 90 mg progesterone vaginally in Crinone 4% or Crinone 8%, or 45 mg or 90 mg progesterone intramuscularly. The pharmacokinetic parameters (mean ± standard deviation) are shown in Table 1. TABLE 1 Single Dose Relative Bioavailability Crinone 4% 45 mg Intramuscular Progesterone Crinone 8% 90 mg Intramuscular Progesterone C max (ng/mL) 13.15 ± 6.49 39.06 ± 13.68 14.87 ± 6.32 53.76 ±
14.9C avg 0-24 (ng/mL) 6.94 ± 4.24 22.41 ± 4.92 6.98 ± 3.21 28.98 ±
8.75AUC 0-96 (ng∙hr/mL) 288.63 ± 273.72 806.26 ± 102.75 296.78 ± 129.90 1378.91 ± 176.39 T max (hr) 5.6 ± 1.84 8.2 ± 6.43 6.8 ± 3.3 9.2 ± 2.7 t 1/2 (hr) 55.13 ± 28.04 28.05 ± 16.87 34.8 ± 11.3 19.6 ±
6.0F (%) 27.6
19.8C max - maximum progesterone serum concentration C avg 0-24 - average progesterone serum concentration over 24 hours AUC 0-96 - area under the drug concentration versus time curve from 0-96 hours post dose T max - time to maximum progesterone concentration t 1/2 - elimination half-life F - relative bioavailability The multiple dose pharmacokinetics of Crinone 4% and Crinone 8% administered every other day and Crinone 8% administered daily or twice daily for 12 days were studied in 10 healthy, estrogenized postmenopausal women in two separate studies.
Steady state was achieved within the first 24 hours after initiation of treatment. The pharmacokinetic parameters (mean ± standard deviation) after the last administration of Crinone 4% or 8% derived from these studies are shown in Table 2. TABLE 2 Multiple Dose Pharmacokinetics Assisted Reproductive Technology Secondary Amenorrhea Daily Dosing 8% Twice Daily Dosing 8% Every Other Day Dosing 4% Every Other Day Dosing 8% C max (ng/mL) 15.97± 5.05 14.57 ± 4.49 13.21± 9.46 13.67 ±
3.58C avg (ng/mL) 8.99 ± 3.53 11.6 ± 3.47 4.05 ± 2.85 6.75 ±
2.83T max (hr) 5.40 ± 0.97 3.55 ± 2.48 6.67 ± 3.16 7.00 ±
2.88AUC 0-t (ng∙hr/mL) 391.98 ±153.28 138.72 ± 41.58 242.15 ± 167.88 438.36 ± 223.36 t 1/2 (hr) 45.00 ± 34.70 25.91 ± 6.15 49.87 ± 31.20 39.08 ±
12.88C max -maximum progesterone serum concentration C avg -average progesterone serum concentration T max -time to maximum progesterone concentration AUC 0-t -area under the drug concentration versus time curve t 1/2 -elimination half-life Distribution Progesterone is extensively bound to serum proteins (~ 96-99%), primarily to serum albumin and corticosteroid binding globulin. Metabolism The major urinary metabolite of oral progesterone is 5β-pregnan-3α, 20α-diol glucuronide which is present in plasma in the conjugated form only.
Plasma metabolites also include 5β-pregnan-3α-ol-20-one (5β-pregnanolone) and 5α-pregnan-3α-ol-20-one (5α-pregnanolone). Excretion Progesterone undergoes both biliary and renal elimination. Following an injection of labeled progesterone, 50-60% of the excretion of progesterone metabolites occurs via the kidney; approximately 10% occurs via the bile and feces, the second major excretory pathway.
Overall recovery of labeled material accounts for 70% of an administered dose, with the remainder of the dose not characterized with respect to elimination. Only a small portion of unchanged progesterone is excreted in the bile.
🔬 Clinical Studies ▾
CLINICAL STUDIES Assisted Reproductive Technology In a single-center, open-label study (COL1620-007US), 99 women (aged 28-47 years) with either partial (n = 84) or premature ovarian failure (n = 15) who were candidates to receive a donor oocyte transfer as an Assisted Reproductive Technology ("ART") procedure were randomized to receive either Crinone 8% twice daily (n = 68) or intramuscular progesterone 100 mg daily (n = 31). The study was divided into three phases (Pilot, Donor Egg and Treatment). The first phase of the study consisted of a test Pilot Cycle to ensure that the administration of transdermal estradiol and progesterone would adequately prime the endometrium to receive the donor egg.
The second phase was the Donor Egg Cycle during which a fertilized oocyte was implanted. Crinone 8% was administered beginning the evening of Day 14 of the Pilot and Donor Egg cycles. Subjects with partial ovarian function also underwent a Pre-Pilot Cycle and a Pre-Donor Egg Cycle during which time they were administered only leuprolide acetate to suppress remaining ovarian function.
The Pre-Pilot Cycle, Pilot Cycle, Pre-Donor Egg Cycle, and Donor Egg Cycle each lasted approximately 34 days. The third phase of the study consisted of a 10-week treatment period to maintain a pregnancy until placental autonomy was achieved. Sixty-one women received Crinone 8% as part of the Pilot Cycle to determine their endometrial response.
Of the 55 evaluable endometrial biopsies in the Crinone 8% group performed on Day 25 to 27, all were histologically "in-phase", consistent with luteal phase biopsy specimens of menstruating women at comparable time intervals. Fifty-four women who received Crinone 8% and had a histologically "in-phase" biopsy received a donor oocyte transfer. Among these 54 Crinone-treated women, clinical pregnancies (assessed about week 10 after transfer by clinical examination, ultrasound and/or ß-hCG levels) occurred in 26 women (48%).
Seventeen women (31%) delivered a total of 25 newborns, seven women (13%) had spontaneous abortions and two women (4%) had elective abortions. In a second study (COL1620-F01), Crinone 8% was used in luteal phase support of women with tubal or idiopathic infertility due to endometriosis and normal ovulatory cycles, undergoing in vitro fertilization ("IVF") procedures. All women received a GnRH analog to suppress endogenous progesterone, human menopausal gonadotropins, and human chorionic gonadotropin.
In this multi-center, open-label study, 139 women (aged 22-38 years) received Crinone 8% once daily beginning within 24 hours of embryo transfer and continuing through Day 30 post-transfer. Clinical pregnancies assessed at Day 90 post-transfer were seen in 36 (26%) of women. Thirty-two women (23%) delivered newborns and four women (3%) had spontaneous abortions.
(See PRECAUTIONS, Pregnancy ) Secondary Amenorrhea In three parallel, open-label studies (COL1620-004US, COL1620-005US, COL1620-009US), 127 women (aged 18-44) with hypothalamic amenorrhea or premature ovarian failure were randomized to receive either Crinone 4% (n = 62) or Crinone 8% (n = 65). All women were treated with either conjugated estrogens 0.625 mg daily (n = 100) or transdermal estradiol (delivering 50 mcg/day) twice weekly (n = 27). Estrogen therapy was continuous for the entire three 28-day cycle studies.
At Day 15 of the second cycle (six weeks after initiating estrogen replacement), women who demonstrated adequate response to estrogen therapy (by ultrasound) and who continued to be amenorrheic received Crinone every other day for six doses (Day 15 through Day 25 of the cycle). In cycle 2, Crinone 4% induced bleeding in 79% of women and Crinone 8% induced bleeding in 77% of women. In the third cycle, estrogen was continued and Crinone was administered every other day beginning on Day 15 for six doses.
On Day 24 an endometrial biopsy was performed. In 53 women who received Crinone 4%, biopsy results were as follows: 7% proliferative,… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Nonclinical toxicity studies to determine the potential of Crinone to cause carcinogenicity or mutagenicity have not been performed. The effect of Crinone on fertility has not been evaluated in animals.
📄 Patient Package Insert ▾
PATIENT INFORMATION Crinone ® 4% and Crinone ® 8% (progesterone gel) For Vaginal Use Only Please read this information carefully before you start to use Crinone and each time your prescription is renewed, in case anything has changed. This leaflet does not take the place of discussions with your doctor. If you still have any questions, ask your doctor or healthcare provider.
What is Crinone? Crinone is medicine that contains the female hormone called progesterone. What is Crinone used for?
Crinone 4% and Crinone 8% are used to treat the absence of a menstrual period in a woman who has previously had a menstrual period. Progesterone is one of the hormones that allows women to have regular menstrual periods. When you do not produce enough progesterone, menstrual irregularities can occur.
Crinone may be prescribed to increase your progesterone. Crinone 8% is also used as part of a program for women who are undergoing fertility treatments to get pregnant. Progesterone is one of the hormones that helps to prepare the lining of your uterus so that it is ready to receive and nourish a fertilized egg and to continue a pregnancy.
If you are undergoing ART treatment and your doctor has determined your body does not produce enough progesterone on its own, Crinone may be prescribed to increase your progesterone. If pregnancy occurs, Crinone may be supplemented for 10 to 12 weeks until production of progesterone by the placenta is adequate. Who should not use Crinone?
Do not start using Crinone if you: Are allergic to progesterone, progesterone-like drugs, or any of the inactive ingredients in the gel (ask a pharmacist if you are not sure about the inactive ingredients in Crinone). Have unusual vaginal bleeding which has not been evaluated by a doctor. Have or have had a liver disease.
Have or have had cancer of the breast or genital organs. Have had a miscarriage and your physician suspects some tissue is still in the uterus. Have or have had blood clots in the legs, lungs, eyes, or elsewhere.
What are the possible side effects of Crinone? Serious side effects include: Blood clots. Progestational drug products may increase your chance of having blood clots in your blood vessels.
Blood clots can cause: ♦ blood vessel problems (thrombophlebitis) ♦ stroke ♦ loss of your arm or leg ♦ blood clot in your lungs (pulmonary embolus) ♦ heart attack ♦ death Birth defects. Abdominal wall defect and cleft palate have been reported with Crinone use in early pregnancy. It is not known if these defects were caused by Crinone.
Call your healthcare provider right away if you get any of the following warning signs or any other unusual symptoms that concern you: Pains in the calves or chest, a sudden shortness of breath or coughing blood indicating possible clots in the legs, heart, or lungs. Severe headache or vomiting, dizziness, faintness, or changes in vision or speech, weakness or numbness of an arm or leg indicating possible clots in the brain or eye. Common side effects include: abdominal pain perineal pain (the perineum is the area between the vagina and the rectum) cramps bloating headache fatigue increased appetite constipation diarrhea nausea joint pain depression mood swings sleep disorder nervousness decreased libido breast enlargement excessive urination at night vaginal discharge upper respiratory tract infection These are not all the possible side effects of Crinone.
For more information, ask your healthcare provider or pharmacist for advice about side effects. To report SUSPECTED ADVERSE REACTIONS, contact A bbVie at 1-800-678-1605 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . How should I use Crinone?
Use as directed by your healthcare provider. Read the Instructions for Use included in this leaflet for information on the right way to use Crinone. Additional information about Crinone You may see a small amount of white discharge that may look like a vaginal discharge.
This discharge may be caused by gel that can remain in your vagina,… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE Crinone ® 4% and Crinone ® 8% ("KRI-noan") (progesterone gel) For Vaginal Use Only You will need the following supplies: See Figure A. Step 1. Remove the applicator from the sealed wrapper.
Open the sealed wrapper and remove the applicator. Do not remove the twist-off cap at this time. See Figure B.
Step 2. Insert the plunger into the open end of the applicator. See Figure C.
Hold the applicator on each side and push the plunger into the applicator until the plunger snaps into place. You will see about 1 inch of the plunger outside of the applicator. Step 3.
Remove the cap. See Figures D and E. Remove the cap from the tip of the applicator by twisting it counterclockwise.
Do not push the plunger while you are removing the cap. This could cause some gel to come out. Step 4.
Prepare to insert the applicator. See Figure F. Choose the position that is most comfortable for you.
For example, lying down on your back with your knees bent. Step 5. Insert the applicator.
See Figure G. After you are in a comfortable position, gently insert the rounded tip of the applicator into your vagina. Step 6.
Push the plunger. See Figure H. While the applicator is inserted in your vagina, push the plunger to release the gel into your vagina.
Step 7. Remove the applicator from your vagina and throw it away in your household trash. It is normal for a small amount of gel to be left in the applicator.
You will still get the right dose of medicine. This Instructions for Use has been approved by the U.S. Food and Drug Administration.
Rx only For all medical inquiries contact: AbbVie Inc. 1-800-678-1605 Distributed by: AbbVie Inc. North Chicago, IL 60064 Content Updated: June 2017 © 2024 AbbVie.
All rights reserved. CRINONE and its design are trademarks of Allergan Sales, LLC, an AbbVie company. 225377-01 Figure A Figure B Figure C Figure D and Figure E Figure F Figure G Figure H
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0023-6150-04 Crinone ® (progesterone gel) 4% - 6 Single-Use Prefilled Applicators Each applicator contains 1.3 g of gel and delivers 1.125 g of gel containing 45 mg progesterone. - FOR VAGINAL USE ONLY - Rx only abbvie PRINCIPAL DISPLAY PANEL NDC 0023-6150-04 Crinone® (progesterone gel) 4% - 6 Single-Use Prefilled Applicators Each applicator contains 1.3 g of gel and delivers 1.125 g of gel containing 45 mg progesterone. - FOR VAGINAL USE ONLY - Rx only abbvie
PRINCIPAL DISPLAY PANEL NDC 0023-6151-08 Crinone ® (progesterone gel) 8% - 15 Single-Use Prefilled Applicators Each applicator contains 1.3 g of gel and delivers 1.125 g of gel containing 90 mg progesterone. - FOR VAGINAL USE ONLY - Rx only abbvie PRINCIPAL DISPLAY PANEL NDC 0023-6151-08 Crinone® (progesterone gel) 8% - 15 Single-Use Prefilled Applicators Each applicator contains 1.3 g of gel and delivers 1.125 g of gel containing 90 mg progesterone. - FOR VAGINAL USE ONLY - Rx only abbvie