
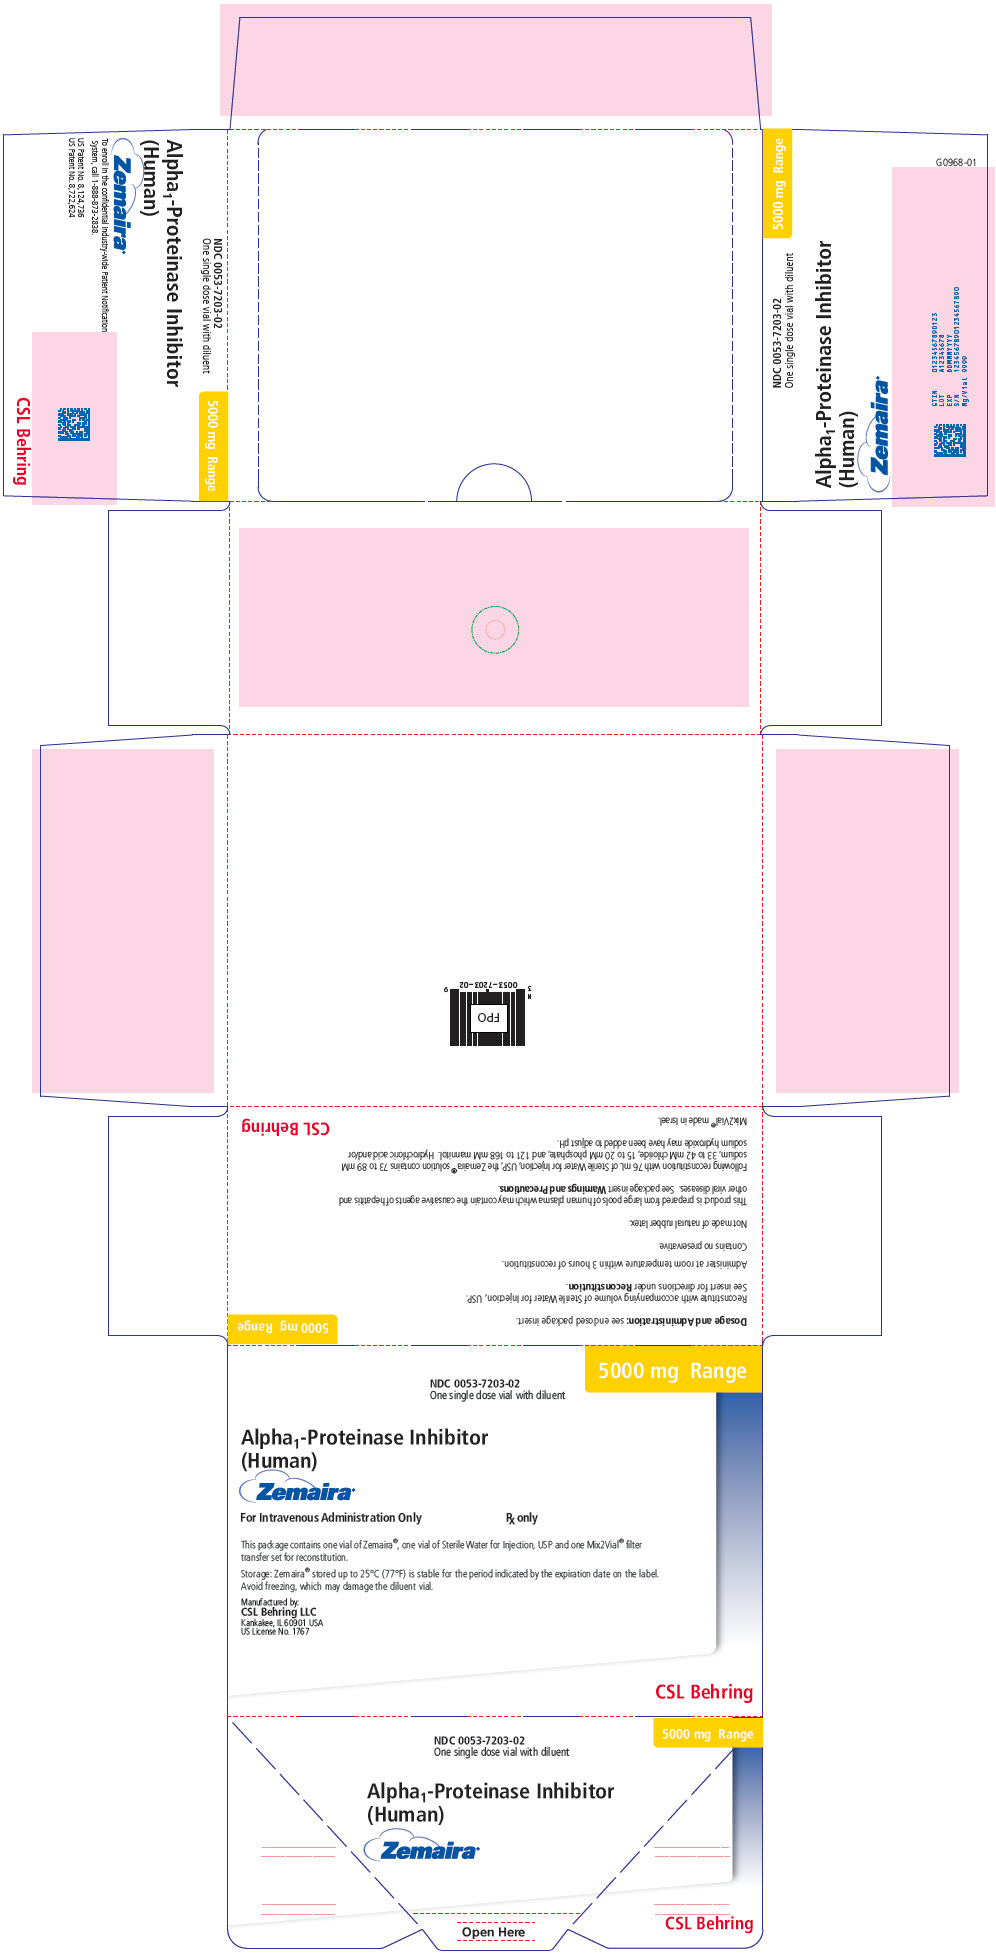
Zemaira .ALPHA.1-PROTEINASE Inhibitor Human Kit — NDC 0053-7202-02 (Billing 00053-7202-02)
This is a package of Zemaira .ALPHA.1-PROTEINASE Inhibitor Human Kit from CSL Behring LLC, marketed since Apr 2019 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0053-7202-02 alone.
- Record
- FDA NDC Directory package listing · Plasma derivative
- Code segments
- 0053 labeler · 7202 product · 02 package
- Package marketed since
- Apr 24, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0053720202 2
- Medicaid fills, this package
- 25 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085544
- GCN: 55052
- GPI-14 (Medi-Span): 45100010102140
- HICL (First Databank): 004529
- AHFS class code: 16:00.00.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 8, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
Clinical
Alpha-1-proteinase inhibitor is used in people with symptoms of emphysema (a lung disease) and alpha-1 antitrypsin deficiency (AATD). AATD is an inherited condition in which the body does not make enough of a protein (alpha-1 antitrypsin) needed to protect the lungs from smoke, dust, or pollution. Alpha-1-proteinase inhibitor is in a class of medications called blood derivatives. It works by increasing the levels of alpha-1 antitrypsin protein in your blood and lungs.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.1772 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0256 | $5.133 / J0256 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00053-7202-02 You're viewing this Main listing | 1 KIT in 1 CARTON * 76 mL in 1 VIAL, SINGLE-USE * 76 mL in 1 VIAL, SINGLE-USE | 2019-04-24 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Zemairathis 00053-7202-02 | CSL | 1 kit | — | — | FDA listed | — |
| Zemaira 00053-7203-02 | CSL | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from CSL Behring LLC labeler code 00053
- HEMGENIX etranacogene dezaparvovec Kit NDC 0053-0440-44
- HEMGENIX etranacogene dezaparvovec Kit NDC 0053-0450-45
- HEMGENIX etranacogene dezaparvovec Kit NDC 0053-0460-46
- HEMGENIX etranacogene dezaparvovec Kit NDC 0053-0470-47
- HEMGENIX etranacogene dezaparvovec Kit NDC 0053-0480-48
- Zemaira alpha-1-proteinase inhibitor human Kit NDC 0053-7201-02
- Zemaira .ALPHA.1-PROTEINASE Inhibitor Human Kit NDC 0053-7203-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full FDA label FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Zemaira ® is indicated for chronic augmentation and maintenance therapy in individuals with alpha 1 -proteinase inhibitor (A 1 -PI) deficiency and clinical evidence of emphysema. Zemaira ® increases antigenic and functional (ANEC) serum levels and lung epithelial lining fluid levels of A 1 -PI. Clinical data demonstrating the long-term effects of chronic augmentation therapy of individuals with Zemaira ® are not available.
Safety and effectiveness in pediatric patients have not been established. The effect of augmentation therapy with Zemaira ® or any A 1 -PI product on pulmonary exacerbations and on the progression of emphysema in A 1 -PI deficiency has not been demonstrated in randomized, controlled clinical trials. Zemaira ® is not indicated as therapy for lung disease patients in whom severe A 1 -PI deficiency has not been established.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Each vial of Zemaira ® contains the labeled amount of functionally active A 1 -PI in milligrams as stated on the vial label as determined by capacity to neutralize human neutrophil elastase. The recommended dose of Zemaira ® is 60 mg/kg body weight administered once weekly. Dose ranging studies using efficacy endpoints have not been performed with any A 1 -PI product.
When reconstituted as directed, Zemaira ® may be administered intravenously at a rate of approximately 0.08 mL/kg/min as determined by the response and comfort of the patient. The recommended dosage of 60 mg/kg body weight will take approximately 15 minutes to infuse. Preparation Each product package contains one Zemaira ® single use vial, one 20 mL vial of Sterile Water for Injection, USP (diluent) and one color-coded vented transfer device with air inlet filter.
Administer within three hours after reconstitution. Reconstitution 1. Bring both product (green cap) vial and diluent (white cap) vial to room temperature prior to reconstitution.
2. Remove the plastic flip-top caps from the vials. Aseptically cleanse the rubber stoppers with antiseptic solution and allow them to dry.
NOTE: The transfer device (Fig. 1) provided in the package is comprised of a white (diluent) end, which has a double orifice, and a green (product) end, which has a single orifice. Incorrect use of the transfer device will result in loss of vacuum and prevent transfer of the diluent, thereby preventing reconstitution of the product.
Fig. 1 The transfer device is sterile. Do not touch the exposed ends of the spike after removing the protective covers.
3. Remove the protective cover from the white (diluent) end of the transfer device. Insert the white end of the transfer device into the center of the stopper of the upright diluent vial first.
(Fig. 2) 4. Remove the protective cover from the green (product) end of the transfer device.
Invert the diluent vial with the attached transfer device and, using minimum force, insert the green end of the transfer device into the center of the rubber stopper of the upright Zemaira ® vial (green top). (Fig. 3) The flange of the transfer device should rest on the surface of the stopper so that the diluent flows into the Zemaira ® vial.
5. Allow the vacuum in the Zemaira ® vial to pull the diluent into the Zemaira ® vial. 6.
During diluent transfer, wet the lyophilized cake completely by gently tilting the Zemaira ® vial. (Fig. 4) Do not allow the air inlet filter to face downward.
Care should be taken not to lose the vacuum, as this will prolong reconstitution of the product. 7. After diluent transfer is complete, the transfer device will allow filtered air into the Zemaira ® vial through the air filter.
Additional venting of the product vial after diluent transfer is complete is not required. When diluent transfer is complete, withdraw the transfer device and diluent vial and properly discard in accordance with biohazard procedures. 8.
Gently swirl the Zemaira ® vial until the powder is completely dissolved. (Fig. 5) DO NOT SHAKE .
9. Inspect parenteral drug products visually for particulate matter and discoloration prior to administration. Administer at room temperature within three hours after reconstitution.
Fig. 2 Fig. 3 Fig.
4 Fig. 5 Figure 1 Figure 2 Figure 3 Figure 4 Figure 5 Pooling Reconstituted Vials If more than one vial of Zemaira ® is needed to achieve the required dose, use an aseptic technique to transfer the reconstituted solution from the vials into the administration container (e.g., empty I.V. bag or glass bottle). Administration Parenteral drug preparations should be inspected visually for particulate matter and discoloration prior to administration.
Administer at room temperature within three hours after reconstitution. Filter the reconstituted solution during administration. To ensure proper filtration of Zemaira ® , use an I.V. administration set with a suitable 5 micron infusion filter (not supplied).
Fol… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Zemaira ® is contraindicated in individuals with a known hypersensitivity to any of its components. Zemaira ® is also contraindicated in individuals with a history of anaphylaxis or severe systemic response to A 1 -PI products. Zemaira ® is contraindicated in IgA deficient patients with antibodies against IgA, due to the risk of severe hypersensitivity.
⚠️ Warnings ▾
WARNINGS Zemaira ® may contain trace amounts of IgA. Patients with known antibodies to IgA, which can be present in patients with selective or severe IgA deficiency, have a greater risk of developing potentially severe hypersensitivity and anaphylactic reactions. Zemaira ® is contraindicated in patients with antibodies against IgA due to risk of severe hypersensitivity.
Zemaira ® is made from human plasma. Products made from human plasma may contain infectious agents, such as viruses, that can cause disease. Because Zemaira ® is made from human blood, it may carry a risk of transmitting infectious agents, e.g., viruses, and theoretically the Creutzfeldt-Jakob disease (CJD) agent.
The risk that such products will transmit an infectious agent has been reduced by screening plasma donors for prior exposure to certain viruses, by testing for the presence of certain current virus infections, and by inactivating and/or removing certain viruses during manufacture. (See DESCRIPTION section for viral reduction measures.) The manufacturing procedure for Zemaira ® includes processing steps designed to reduce further the risk of viral transmission. Stringent procedures utilized at plasma collection centers, plasma testing laboratories, and fractionation facilities are designed to reduce the risk of viral transmission.
The primary viral reduction steps of the Zemaira ® manufacturing process are pasteurization (60°C for 10 hours) and nanofiltration. Additional purification procedures used in the manufacture of Zemaira ® also potentially provide viral reduction. Despite these measures, such products may still potentially contain human pathogenic agents, including those not yet known or identified.
Thus, the risk of transmission of infectious agents can not be totally eliminated. Any infections thought by a physician possibly to have been transmitted by this product should be reported by the physician or other healthcare provider to CSL Behring at 1-866-915-6958. The physician should discuss the risks and benefits of this product with the patient.
Individuals who receive infusions of blood or plasma products may develop signs and/or symptoms of some viral infections (see Information For Patients ). During clinical studies, no cases of hepatitis A, B, C, or HIV viral infections were reported with the use of Zemaira ® .
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In clinical studies, the following adverse reactions considered treatment-related by the investigator were reported following intravenous administration of Zemaira ® , 60 mg/kg weekly: asthenia, injection site pain, dizziness, headache, paresthesia, and pruritus. Each of these related adverse events was observed in 1 of 89 subjects (1%). The adverse reactions were mild.
Should evidence of an acute hypersensitivity reaction be observed, the infusion should be stopped promptly and appropriate countermeasures and supportive therapy should be administered. Table 3 summarizes the adverse event data obtained with single and multiple doses during clinical trials with Zemaira ® and Prolastin ® . No clinically significant differences were detected between the two treatment groups.
Table 3: Summary of Adverse Events Zemaira ® Prolastin ® No. of subjects treated 89 32 No. of subjects with adverse events regardless of causality (%) 69 (78%) 20 (63%) No. of subjects with related adverse events (%) 5 (6%) 4 (13%) No. of subjects with related serious adverse events 0 0 No. of infusions 1296 160 No. of adverse events regardless of causality (rates per infusion) 298 (0.230) 83 (0.519) No. of related adverse events (rates per infusion) 6 (0.005) 5 (0.031) The frequencies of adverse events per infusion that were ≥0.4% in Zemaira ® -treated subjects, regardless of causality, were: headache (33 events per 1296 infusions, 2.5%), upper respiratory infection (1.6%), sinusitis (1.5%), injection site hemorrhage (0.9%), sore throat (0.9%), bronchitis (0.8%), asthenia (0.6%), fever (0.6%), pain (0.5%), rhinitis (0.5%), bronchospasm (0.5%), chest pain (0.5%), increased cough (0.4%), rash (0.4%), and infection (0.4%).
The following adverse events, regardless of causality, occurred at a rate of 0.2% to <0.4% per infusion: abdominal pain, diarrhea, dizziness, ecchymosis, myalgia, pruritus, vasodilation, accidental injury, back pain, dyspepsia, dyspnea, hemorrhage, injection site reaction, lung disorder, migraine, nausea, and paresthesia. Diffuse interstitial lung disease was noted on a routine chest x-ray of one subject at Week 24. Causality could not be determined.
In a retrospective analysis, during the 10-week blinded portion of the 24-week clinical study, 6 subjects (20%) of the 30 treated with Zemaira ® had a total of 7 exacerbations of their chronic obstructive pulmonary disease (COPD). Nine subjects (64%) of the 14 treated with Prolastin ® had a total of 11 exacerbations of their COPD. The observed difference between groups was 44% (95% confidence interval from 8% to 70%).
Over the entire 24-week treatment period, of the 30 subjects in the Zemaira ® treatment group, 7 subjects (23%) had a total of 11 exacerbations of their COPD.
🤰 Pregnancy ▾
Pregnancy Category C Animal reproduction studies have not been conducted with Zemaira ® . It is also not known whether Zemaira ® can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Zemaira ® should be given to a pregnant woman only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in the pediatric population have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of Zemaira ® did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. As for all patients, dosing for geriatric patients should be appropriate to their overall situation.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Alpha 1 -proteinase inhibitor (A 1 -PI) deficiency is a chronic, hereditary, autosomal, co-dominant disorder that is usually fatal in its severe form. Low blood levels of A 1 -PI (i.e., below 11 µM) are most commonly associated with progressive, severe emphysema that becomes clinically apparent by the third to fourth decade of life. In addition, PiSZ individuals, whose serum A 1 -PI levels range from approximately 9 to 23 µM are considered to have moderately increased risk for developing emphysema, regardless of whether their serum A 1 -PI levels are above or below 11 µM.
1 Not all individuals with severe genetic variants of A 1 -PI deficiency have emphysema. Augmentation therapy with Alpha 1 -Proteinase Inhibitor (Human) is indicated only in patients with severe congenital A 1 -PI deficiency who have clinically evident emphysema. A recent registry study showed 54% of A 1 -PI deficient subjects had emphysema.
2 Another registry study showed 72% of A 1 -PI deficient subjects had pulmonary symptoms. 3 Smoking is an important risk factor for the development of emphysema in patients with A 1 -PI deficiency. Approximately 100 genetic variants of A 1 -PI deficiency can be identified electrophoretically, only some of which are associated with the clinical disease.
4,5 Ninety-five percent of A 1 -PI deficient individuals are of the severe PiZZ phenotype. Up to 39% of A 1 -PI deficient patients may have an asthmatic component to their lung disease, as evidenced by symptoms and/or bronchial hyperreactivity. 2 Pulmonary infections, including pneumonia and acute bronchitis, are common in A 1 -PI deficient patients and contribute significantly to the morbidity of the disease.
Augmenting the levels of functional protease inhibitor by intravenous infusion is an approach to therapy for patients with A 1 -PI deficiency. However, the efficacy of augmentation therapy in affecting the progression of emphysema has not been demonstrated in randomized, controlled clinical trials. The intended theoretical goal is to provide protection to the lower respiratory tract by correcting the imbalance between neutrophil elastase and protease inhibitors.
Whether augmentation therapy with Zemaira ® or any A 1 -PI product actually protects the lower respiratory tract from progressive emphysematous changes has not been evaluated. Individuals with endogenous levels of A 1 -PI below 11 µM, in general, manifest a significantly increased risk for development of emphysema above the general population background risk. 5,6,7,8 Although the maintenance of blood serum levels of A 1 -PI (antigenically measured) above 11 µM has been historically postulated to provide therapeutically relevant anti-neutrophil elastase protection 9 , this has not been proven.
Individuals with severe A 1 -PI deficiency have been shown to have increased neutrophil and neutrophil elastase concentrations in lung epithelial lining fluid compared to normal PiMM individuals, and some PiSZ individuals with A 1 -PI above 11 µM have emphysema attributed to A 1 -PI deficiency. 1 These observations underscore the uncertainty regarding the appropriate therapeutic target serum level of A 1 -PI during augmentation therapy. Mechanism of Action Pulmonary disease, particularly emphysema, is the most frequent manifestation of A 1 -PI deficiency.
5 The pathogenesis of emphysema is understood to evolve as described in the "protease-antiprotease imbalance" model. A 1 -PI is now understood to be the primary antiprotease in the lower respiratory tract, where it inhibits neutrophil elastase (NE). 10 Normal healthy individuals produce sufficient A 1 -PI to control the NE produced by activated neutrophils and are thus able to prevent inappropriate proteolysis of lung tissue by NE.
Conditions that increase neutrophil accumulation and activation in the lung, such as respiratory infection and smoking, will in turn increase levels of NE. However, individuals who are severely deficient in endogenous A 1… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action Pulmonary disease, particularly emphysema, is the most frequent manifestation of A 1 -PI deficiency. 5 The pathogenesis of emphysema is understood to evolve as described in the "protease-antiprotease imbalance" model. A 1 -PI is now understood to be the primary antiprotease in the lower respiratory tract, where it inhibits neutrophil elastase (NE).
10 Normal healthy individuals produce sufficient A 1 -PI to control the NE produced by activated neutrophils and are thus able to prevent inappropriate proteolysis of lung tissue by NE. Conditions that increase neutrophil accumulation and activation in the lung, such as respiratory infection and smoking, will in turn increase levels of NE. However, individuals who are severely deficient in endogenous A 1 -PI are unable to maintain an appropriate antiprotease defense and are thereby subject to more rapid proteolysis of the alveolar walls leading to chronic lung disease.
Zemaira ® serves as A 1 -PI augmentation therapy in this patient population, acting to increase and maintain serum levels and lung epithelial lining fluid (ELF) levels of A 1 -PI. In 18 subjects treated with a single dose (60 mg/kg) of Zemaira ® , the mean area under the curve (AUC) and standard deviation (SD) were 144 µM × day (SD 27), maximum serum concentration was 44.1 µM (SD 10.8), clearance was 603 mL per day (SD 129), and terminal half-life was 5.1 days (SD 2.4). Weekly repeated infusions of A 1 -PI at a dose of 60 mg/kg lead to serum A 1 -PI levels above the historical target threshold of 11 µM.
The clinical benefit of the increased blood levels of A 1 -PI at the recommended dose for any A 1 -PI product has not been established.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Zemaira ® is supplied in a single use vial containing the labeled amount of functionally active A 1 -PI, as stated on the label. Each carton contains one single use vial of Zemaira ® , one 20 mL vial of Sterile Water for Injection, USP (diluent) and one vented transfer device. Each product package consists of the following: NDC Number Component 0053-7201-02 Carton (kit) containing one vial of Zemaira ® [NDC 0053-7211-01], one 20 mL vial of Sterile Water for Injection, USP (diluent) [NDC 0053-7653-20] and one vented transfer device.
STORAGE When stored up to 25°C (77°F), Zemaira ® is stable for the period indicated by the expiration date on its label. Avoid freezing which may damage container for the diluent.
📦 Storage and Handling ▾
STORAGE When stored up to 25°C (77°F), Zemaira ® is stable for the period indicated by the expiration date on its label. Avoid freezing which may damage container for the diluent.
📋 Description ▾
DESCRIPTION Alpha 1 -Proteinase Inhibitor (Human), Zemaira ® , is a sterile, stable, lyophilized preparation of highly purified human alpha 1 -proteinase inhibitor (A 1 -PI), also known as alpha 1 -antitrypsin, derived from human plasma. Zemaira ® is manufactured from large pools of human plasma by cold ethanol fractionation according to a modified Cohn process followed by additional purification steps. Zemaira ® is supplied as a sterile, white, lyophilized powder to be administered by the intravenous route.
The specific activity of Zemaira ® is ≥0.7 mg of functional A 1 -PI per milligram of total protein. The purity is ≥90% A 1 -PI. Following reconstitution with 20 mL of Sterile Water for Injection, USP, each vial contains approximately 1000 mg of functionally active A 1 -PI, 81 mM sodium, 38 mM chloride, 17 mM phosphate, and 144 mM mannitol.
Hydrochloric acid and/or sodium hydroxide may have been added to adjust the pH. Zemaira ® contains no preservatives. Each vial of Zemaira ® contains the labeled amount of functionally active A 1 -PI in milligrams as stated on the vial label as determined by its capacity to neutralize human neutrophil elastase.
All Source Plasma used in the manufacture of this product was tested by FDA-licensed Nucleic Acid Tests (NAT) for HCV and HIV-1 and found to be nonreactive (negative). An investigational NAT for HBV was also performed on all Source Plasma used in the manufacture of this product and found to be nonreactive (negative). The aim of the HBV test is to detect low levels of viral material, however, the significance of a nonreactive (negative) result has not been established.
Two viral reduction steps are employed in the manufacture of Zemaira ® : pasteurization at 60°C for 10 hours in an aqueous solution with stabilizers and nanofiltration. These viral reduction steps have been validated in a series of in vitro experiments for their capacity to inactivate/remove a wide range of viruses of diverse physicochemical characteristics including: Human Immunodeficiency Virus (HIV), West Nile Virus (WNV), Hepatitis A Virus (HAV), Parvovirus B19, and the following model viruses: Bovine Viral Diarrhea Virus (BVDV) as a model virus for HCV, Pseudorabies Virus (PRV) as a non-specific model virus for large DNA viruses, e.g. herpes, and Canine Parvovirus (CPV) as a model virus for Parvovirus B19.
Total log 10 reductions range from ≥ 6.4 to ≥ 16.7 log 10 as shown in Table 1. Table 1: Virus Reduction Factors Reduction Factor Pasteurization In addition, virus clearance of human parvovirus B19 by the pasteurization step was investigated. The estimated log 10 reduction factor was 1.9. [log 10 ] Reduction Factor Nanofiltration [log 10 ] Cumulative Reduction Factor [log 10 ] N.A. : Not applicable HIV-1 ≥ 6.8 ≥ 5.5 ≥
12.3WNV ≥ 8.3 ≥ 8.4 ≥
16.7BVDV ≥ 5.2 ≥ 5.4 ≥
10.6PRV 4.4 ≥ 6.3 ≥
10.7HAV ≥ 5.4 ≥ 5.3 ≥
10.7CPV N.A. ≥ 6.4 ≥ 6.4
💬 Information for Patients ▾
Information For Patients Patients should be informed of the early signs of hypersensitivity reactions including hives, generalized urticaria, tightness of the chest, dyspnea, wheezing, faintness, hypotension, and anaphylaxis. Patients should be advised to discontinue use of the product and contact their physician and/or seek immediate emergency care, depending on the severity of the reaction, if these symptoms occur. As with all plasma-derived products, some viruses, such as parvovirus B19, are particularly difficult to remove or inactivate at this time.
Parvovirus B19 may most seriously affect pregnant women and immune-compromised individuals. Symptoms of parvovirus B19 include fever, drowsiness, chills, and runny nose followed two weeks later by a rash and joint pain. Patients should be encouraged to consult their physician if such symptoms occur.
Inform patients that administration of Zemaira ® has been demonstrated to raise the plasma level of A 1 -PI, but that the effect of this augmentation on the frequency of pulmonary exacerbations and on the rate of progression of emphysema has not been established by clinical trials.
⚠️ Precautions ▾
PRECAUTIONS General Infusion rates and the patient's clinical state should be monitored closely during infusion. The patient should be observed for signs of infusion-related reactions. As with any colloid solution, there may be an increase in plasma volume following intravenous administration of Zemaira ® .
Use caution in patients at risk for circulatory overload. Information For Patients Patients should be informed of the early signs of hypersensitivity reactions including hives, generalized urticaria, tightness of the chest, dyspnea, wheezing, faintness, hypotension, and anaphylaxis. Patients should be advised to discontinue use of the product and contact their physician and/or seek immediate emergency care, depending on the severity of the reaction, if these symptoms occur.
As with all plasma-derived products, some viruses, such as parvovirus B19, are particularly difficult to remove or inactivate at this time. Parvovirus B19 may most seriously affect pregnant women and immune-compromised individuals. Symptoms of parvovirus B19 include fever, drowsiness, chills, and runny nose followed two weeks later by a rash and joint pain.
Patients should be encouraged to consult their physician if such symptoms occur. Inform patients that administration of Zemaira ® has been demonstrated to raise the plasma level of A 1 -PI, but that the effect of this augmentation on the frequency of pulmonary exacerbations and on the rate of progression of emphysema has not been established by clinical trials. Pregnancy Category C Animal reproduction studies have not been conducted with Zemaira ® .
It is also not known whether Zemaira ® can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Zemaira ® should be given to a pregnant woman only if clearly needed. Nursing Mothers It is not known whether Zemaira ® is excreted in human milk.
Because many drugs are excreted in human milk, caution should be exercised when Zemaira ® is administered to a nursing woman. Pediatric Use Safety and effectiveness in the pediatric population have not been established. Geriatric Use Clinical studies of Zemaira ® did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
As for all patients, dosing for geriatric patients should be appropriate to their overall situation.
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether Zemaira ® is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when Zemaira ® is administered to a nursing woman.
🔬 Clinical Studies ▾
CLINICAL STUDIES Clinical studies were conducted with Zemaira ® in 89 subjects (59 males and 30 females). The subjects ranged in age from 29 to 68 years (median age 49 years). Ninety-seven percent of the treated subjects had the PiZZ phenotype of A 1 -PI deficiency, and 3% had the M MALTON phenotype.
At screening, serum A 1 -PI levels were between 3.2 and 10.1 µM (mean of 5.6 µM). The objectives of the clinical studies were to demonstrate that Zemaira ® augments and maintains serum levels of A 1 -PI above 11 µM and increases A 1 -PI levels in ELF of the lower lung. In a double-blind, controlled clinical study to evaluate the safety and efficacy of Zemaira ® , 44 subjects were randomized to receive 60 mg/kg of either Zemaira ® or Prolastin ® (a commercially available Alpha 1 -Proteinase Inhibitor [Human] product) once weekly for 10 weeks.
After 10 weeks, all subjects received Zemaira ® for an additional 14 weeks. All subjects were followed for a total of 24 weeks to complete the safety evaluation. The mean trough serum A 1 -PI levels at steady state (Weeks 7-11) in the Zemaira ® -treated subjects were statistically equivalent to those in the Prolastin ® -treated subjects.
Both groups were maintained above 11 µM (80 mg/dL). The mean (range and standard deviation) of the steady state trough serum antigenic A 1 -PI level for Zemaira ® -treated subjects was 17.7 µM (range 13.9 to 23.2, SD 2.5) and for Prolastin ® -treated subjects was 19.1 µM (range 14.7 to 23.1, SD 2.2). The difference between the Zemaira ® and the Prolastin ® groups was not considered clinically significant and may be related to the higher specific activity of Zemaira ® .
In a subgroup of subjects enrolled in the study (10 Zemaira ® -treated subjects and 5 Prolastin ® -treated subjects), bronchoalveolar lavage was performed at baseline and at Week 11. Four A 1 -PI related analytes in ELF were measured: antigenic A 1 -PI, A 1 -PI:NE complexes, free NE, and functional A 1 -PI (anti-neutrophil elastase capacity, ANEC). A blinded retrospective analysis, which revised the prospectively established acceptance criteria showed that within each treatment group, ELF levels of antigenic A 1 -PI and A 1 -PI:NE complexes increased from baseline to Week 11.
Free elastase was immeasurably low in all samples. The post-treatment ANEC values in ELF were not significantly different between the Zemaira ® -treated and Prolastin ® -treated subjects (mean 1725 nM vs. 1418 nM).
No conclusions can be drawn about changes of ANEC values in ELF during the study period as baseline values in the Zemaira ® -treated subjects were unexpectedly high. No A 1 -PI analytes showed any clinically significant differences between the Zemaira ® and Prolastin ® treatment groups. Table 2: ELF Analytes - change from baseline Analyte Treatment Mean change from baseline 90% CI A 1 -PI (nM) Zemaira ® 1358.3 822.6 to 1894.0 Prolastin ® 949.9 460.0 to 1439.7 ANEC (nM) Zemaira ® -588.1 -2032.3 to 856.1 Prolastin ® 497.5 -392.3 to 1387.2 A 1 -PI:NE Complexes (nM) Zemaira ® 118.0 39.9 to 196.1 Prolastin ® 287.1 49.8 to 524.5 The clinical efficacy of Zemaira ® or any A 1 -PI product in influencing the course of pulmonary emphysema or pulmonary exacerbations has not been demonstrated in adequately powered, randomized, controlled clinical trials.
Subjects were also monitored for the presence of antibodies to HIV and markers for viral hepatitis (HAV, HBV, and HCV). Subjects who were negative for Hepatitis B surface antigen (HBsAg) at screening were vaccinated against Hepatitis B. Zemaira ® -treated subjects were tested six months after the end of treatment for HAV, HBV, HCV, HIV, and Parvovirus B19, and no evidence of viral transmission was observed.
No subjects developed detectable antibodies to Zemaira ® .
📚 References ▾
REFERENCES Turino GM, Barker AF, Brantly ML, et al: Clinical Features of Individuals with PI*SZ Phenotype of α 1 -Antitrypsin Deficiency. Am J Respir Crit Care Med 154:1718-1725, 1996. Stoller JK, Brantly M, et al .
Formation and current results of a patient-organized registry for α 1 -antitrypsin deficiency. Chest 118(3):843-848, 2000. McElvaney NG, Stoller JK, et al .
Baseline Characteristics of Enrollees in the National Heart, Lung, and Blood Institute Registry of α 1 -Antitrypsin Deficiency. Chest 111:394-403, 1997. Crystal RG. α 1 -Antitrypsin Deficiency, Emphysema, and Liver Disease; Genetic Basis and Strategies for Therapy.
J Clin Invest 85:1343-1352, 1990. World Health Organization. Alpha-1-Antitrypsin Deficiency; Report of a WHO Meeting.
Geneva. 18-20 March 1996. Eriksson S.
Pulmonary Emphysema and Alpha 1 -Antitrypsin Deficiency. ACTA Med Scand 175(2):197-205, 1964. Eriksson S.
Studies in α 1 -antitrypsin deficiency. ACTA Med Scan Suppl. 432:1-85, 1965.
Gadek JE, Crystal RG. α 1 -Antitrypsin Deficiency. In: The Metabolic Basis of Inherited Disease 5th ed. Stanbury JB, Wyngaarden JB, Frederickson DS, et al. , eds: New York, McGraw-Hill.
1983; pp. 1450-1467. American Thoracic Society.
Guidelines for the Approach to the Patient with Severe Hereditary Alpha-1-Antitrypsin Deficiency. Am Rev Respir Dis 140:1494-1497, 1989. Gadek JE, Fells GA, Zimmerman RL, Rennard SI, Crystal RG.
Antielastases of the Human Alveolar Structures; Implications for the Protease-Antiprotease Theory of Emphysema. J Clin Invest 68:889-898, 1981.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - Vial Label NDC 0053-7211-01 Alpha 1 -Proteinase Inhibitor (Human) Zemaira ® Store up to 25°C (77°F). Rx only I.V. use only Manufactured by: CSL Behring LLC Kankakee, IL 60901 USA US License No. 1767 PRINCIPAL DISPLAY PANEL - Vial Label
PRINCIPAL DISPLAY PANEL - Carton NDC 0053-7201-02 One single dose vial with diluent Alpha 1 -Proteinase Inhibitor (Human) Zemaira ® For Intravenous Administration Only. This package contains one vial of Zemaira ® , one vial of Sterile Water for Injection, USP and one vented transfer device for reconstitution. Rx only Storage: Zemaira ® stored up to 25°C (77°F) is stable for the period indicated by the expiration date on the label.
Avoid freezing. Manufactured by: CSL Behring LLC Kankakee, IL 60901 USA US License No. 1767 CSL Behring PRINCIPAL DISPLAY PANEL - Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |