
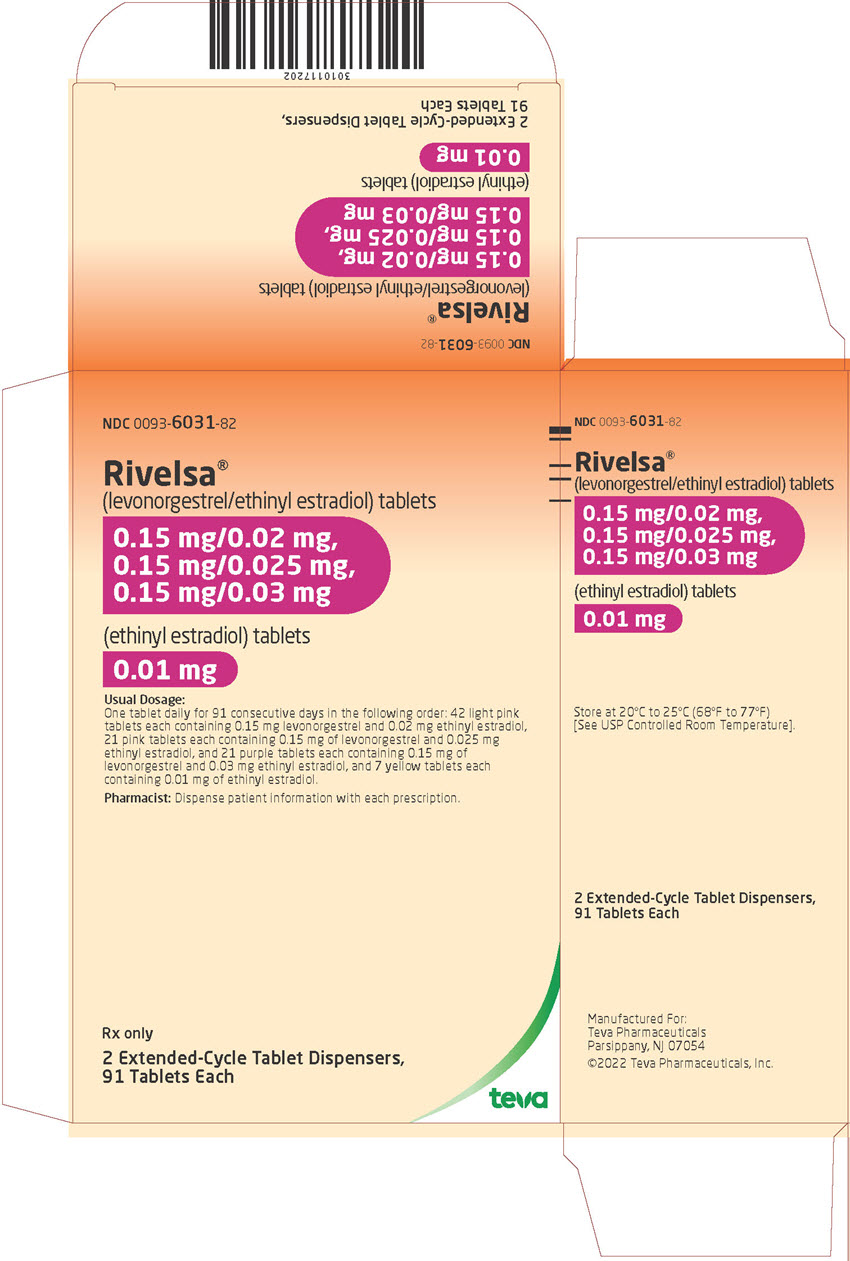
Rivelsa Levonorgestrel/Ethinyl Estradiol and Ethinyl Kit, 2 pouches
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and levonorgestrel (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗- It prevents pregnancy mainly by stopping your ovaries from releasing an egg. It also thickens the cervical mucus so sperm can't easily get through, and changes the uterine lining a...
- What exactly does this medication do, and how well does it work?
- The most common ones in the first few months are headaches, nausea, irregular bleeding or spotting, breast tenderness, and mood changes. Most of these tend to settle down after you...
- Are there any side effects I should expect when I first start?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.438 | $2.88 / 2 kit |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $2.38 | $4.76 / 2 kit |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| camrese Lo 00093-6148-82 | Teva | 2 pouches | $0.239 | AB | Availability likely | save 83% |
| LoJaimiess 70700-0124-87 | Xiromed, | 1 kit | $0.239 | AB | Availability likely | save 83% |
| Rivelsathis 00093-6031-82 | Teva | 2 pouches | $1.438 | AB | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8415332 ↗ | Drug product | — | Mar 11, 2029 |
Is there a generic version of RIVELSA TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00093-6031-82 You're viewing this | 2 POUCH in 1 CARTON (0093-6031-82) / 1 KIT in 1 POUCH (0093-6031-91) | 2017-04-03 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptives (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs, including RIVELSA, are contraindicated in women who are over 35 years of age and smoke [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )] .
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS See full prescribing information for complete boxed warning. RIVELSA is contraindicated in women over 35 years old who smoke. ( 4 ) Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use.
( 4 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE RIVELSA ® is indicated for use by females of reproductive age to prevent pregnancy. RIVELSA is a combination of levonorgestrel, a progestin, and ethinyl estradiol, an estrogen, indicated for use by females of reproductive potential to prevent pregnancy. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take one tablet daily by mouth at the same time every day for 91 days in the order directed on the blister pack. ( 2 )
2.1How to Start and Take RIVELSA Begin RIVELSA on the first Sunday after the onset of menstruation. If menstruation begins on a Sunday, take the first light pink tablet that day. For each 91-day course, take in the following order: Start the first light pink tablet on the first Sunday after the onset of menstruation.
If menstruation begins on a Sunday, take the tablet on that day. Then take one light pink tablet once daily for a total of 42 consecutive days. Use a non-hormonal backup method of contraception (such as condoms and spermicide) for the first 7 days of treatment.
One pink tablet once daily for 21 consecutive days. One purple tablet once daily for 21 days. One yellow tablet once daily for 7 days.
Bleeding should occur during yellow tablet use. Begin the next and all subsequent 91-day courses of RIVELSA without interruption on the same day of the week (Sunday) on which the first dose of RIVELSA was taken. Follow the same schedule as the initial 91-day course: light pink tablet once daily for 42 days, pink tablet once daily for 21 days, purple tablet once daily for 21 days, and yellow tablet once daily for 7 days.
If the next pill pack is not started immediately, use a non-hormonal backup method of contraception until a light pink tablet has been taken once daily for 7 consecutive days. Switching to RIVELSA from another oral hormonal contraceptive or from another contraceptive method (transdermal patch, vaginal ring, injection, intrauterine contraceptive, implant) Start on the Sunday after the patient’s next period starts. Use additional non-hormonal contraceptive (such as condoms and spermicide) until the patient has taken 7 light pink pills (7 days).
Starting RIVELSA after Abortion or Miscarriage First-trimester RIVELSA may be started on the Sunday after an abortion or miscarriage. The patient must use additional non-hormonal contraception (such as condoms and spermicide) until the patient has taken a light pink tablet for 7 days. Second-trimester Do not start until 4 weeks after a second-trimester abortion or miscarriage, due to the increased risk of thromboembolic disease.
Start contraceptive therapy with RIVELSA following the instructions for women not currently using hormonal contraception. Use additional non-hormonal contraception (such as condoms and spermicide) until the patient has taken a light pink tablet for 7 days [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )]. Starting RIVELSA after Childbirth Do not start until 4 weeks after delivery, due to the increased risk of thromboembolic disease.
Start contraceptive therapy with RIVELSA following the instructions for women not currently using hormonal contraception. Use additional non-hormonal contraception (such as condoms and spermicide) until the patient has taken a light pink tablet for 7 days [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )]. RIVELSA is not recommended for use in lactating women [see Use in Specific Populations ( 8.2 )] .
If the woman has not yet had a period postpartum, consider the possibility of ovulation and conception occurring prior to use of RIVELSA [see Warnings and Precautions ( 5.1 ), Use in Specific Populations ( 8.1 )].
2.2Dosing RIVELSA Take one tablet by mouth at the same time every day. The dosage of RIVELSA is one light pink tablet once daily for 42 days, one pink tablet once daily for 21 days, one purple tablet once daily for 21 days, and one yellow tablet once daily for 7 days. To achieve maximum contraceptive effectiveness, take RIVELSA exactly as directed, in the order directed, and at intervals not exceeding 24 hours.
The failure rate may increase when pills are missed or taken incorrectly.
2.3Missed Doses Table 1. Instructions for Missed RIVELSA Tablets If one light pink, pink or purple tablet is missed Take the missed tablet as soon as…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS RIVELSA (levonorgestrel/ethinyl estradiol and ethinyl estradiol) tablets are available as round, film-coated, biconvex tablets debossed with TV on one side, packaged in Extended-Cycle Tablet Dispensers, each containing a 13-week supply of tablets in the following order: 42 light pink tablets, each containing 0.15 mg of levonorgestrel and 0.02 mg ethinyl estradiol: debossed with 076 on the other side 21 pink tablets containing 0.15 mg of levonorgestrel and 0.025 mg ethinyl estradiol: debossed with 075 on the other side 21 purple tablets containing 0.15 mg of levonorgestrel and 0.03 mg ethinyl estradiol: debossed with 074 on the other side and 7 yellow tablets containing 0.01 mg of ethinyl estradiol: debossed with 077 on the other side RIVELSA consists of 91 tablets in the following order ( 3 ): 42 light pink tablets containing 0.15 mg levonorgestrel and 0.02 mg ethinyl estradiol, 21 pink tablets containing 0.15 mg of levonorgestrel and 0.025 mg ethinyl estradiol, and 21 purple tablets containing 0.15 mg of levonorgestrel and 0.03 mg ethinyl estradiol, and 7 yellow tablets containing 0.01 mg of ethinyl estradiol.
⛔ Contraindications ▾
4 CONTRAINDICATIONS RIVELSA is contraindicated in females who are known to have or develop the following conditions: A high risk of arterial or venous thrombotic diseases. Examples include females who are known to: Smoke, if over age 35 [see Boxed Warning and Warnings and Precautions ( 5.1 )]. Have current or history of deep vein thrombosis or pulmonary embolism [see Warnings and Precautions ( 5.1 )].
Have cerebrovascular disease [see Warnings and Precautions ( 5.1 )]. Have coronary artery disease [see Warnings and Precautions ( 5.1 )]. Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see Warnings and Precautions ( 5.1 )].
Have inherited or acquired hypercoagulopathies [see Warnings and Precautions ( 5.1 )]. Have uncontrolled hypertension or hypertension with vascular disease [see Warnings and Precautions ( 5.5 )]. Have diabetes mellitus and are over age 35, diabetes mellitus with hypertension or with vascular disease or other end-organ damage, or diabetes mellitus of > 20 years duration [see Warnings and Precautions ( 5.7 )].
Have headaches with focal neurological symptoms, migraine headaches with aura, or over age 35 with any migraine headaches [see Warnings and Precautions ( 5.8 )]. Current diagnosis of, or history of, breast cancer, which may be hormone sensitive [see Warnings and Precautions ( 5.11 )] . Liver tumors, acute viral hepatitis, or severe (decompensated) cirrhosis [see Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.6 )].
Undiagnosed abnormal uterine bleeding [see Warnings and Precautions ( 5.9 )]. Use of Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations [see Warnings and Precautions ( 5.4 )]. A high risk of arterial or venous thrombotic diseases ( 4 ) Undiagnosed abnormal uterine bleeding ( 4 ) Breast cancer ( 4 ) Liver tumors or liver disease ( 4 ) Co-administration with Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Vascular risks: Stop if a thrombotic or thromboembolic event occurs. Stop at least 4 weeks before and through 2 weeks after major surgery. Start no earlier than 4 weeks after delivery, in women who are not breastfeeding.
Consider cardiovascular risk factors before initiating in all females, particularly those over 35 years. ( 5.1 , 5.5 ) Liver disease: Discontinue if jaundice occurs. ( 5.2 ) Hypertension: If used in females with well-controlled hypertension, monitor blood pressure and stop use if blood pressure rises significantly.
( 5.3 ) Gallbladder disease: May cause or worsen gallbladder disease. ( 5.6 ) Carbohydrate and lipid metabolic effects: Monitor glucose in prediabetic and diabetic women taking RIVELSA. Consider an alternate contraceptive method for women with uncontrolled dyslipidemias.
( 5.7 ) Headache: Evaluate significant change in headaches and discontinue if indicated. ( 5.8 ) Uterine bleeding: May cause irregular bleeding or amenorrhea. Evaluate for other causes if symptoms persist.
( 5.9 )
5.1Thromboembolic Disorders and Other Vascular Conditions Stop RIVELSA if an arterial or deep venous thromboembolic event occurs. Stop RIVELSA if there is unexplained loss of vision, proptosis, diplopia, papilledema, or retinal vascular lesions. Evaluate for retinal vein thrombosis immediately.
Discontinue RIVELSA during prolonged immobilization. If feasible, stop RIVELSA at least 4 weeks before and through 2 weeks after major surgery or other surgeries known to have an elevated risk of thromboembolism. Start RIVELSA no earlier than 4 weeks after delivery, in females who are not breastfeeding.
The risk of postpartum thromboembolism decreases after the third postpartum week, whereas the risk of ovulation increases after the third postpartum week. Before starting RIVELSA evaluate any past medical history or family history of thrombotic or thromboembolic disorders and consider whether the history suggests an inherited or acquired hypercoagulopathy. RIVELSA is contraindicated in females with a high risk of arterial or venous/thromboembolic diseases [see Contraindications ( 4 )] .
Arterial Events COCs increase the risk of cardiovascular events and cerebrovascular events, such as myocardial infarction and stroke. The risk is greater among older women (> 35 years of age), smokers, and females with hypertension, dyslipidemia, diabetes, or obesity. RIVELSA is contraindicated in women over 35 years of age who smoke [see Contraindications (4)] .
Cigarette smoking increases the risk of serious cardiovascular events from COC use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. Venous Events Use of COCs increases the risk of venous thromboembolic events (VTEs), such as deep vein thrombosis and pulmonary embolism.
Risk factors for VTEs include smoking, obesity, and family history of VTE, in addition to other factors that contraindicate use of COCs [see Contraindications (4)] . While the increased risk of VTE associated with use of COCs is well-established, the rates of VTE are even greater during pregnancy, and especially during the postpartum period (see Figure 1). The rate of VTE in females using COCs has been estimated to be 3 to 9 cases per 10,000 woman years.
The risk of VTE is highest during the first year of use of a COC and when restarting hormonal contraception after a break of four weeks or longer. The risk of thromboembolic disease due to COCs gradually disappears after COC use is discontinued. Figure 1 shows the risk of developing a VTE for females who are not pregnant and do not use oral contraceptives, for females who use oral contraceptives, and for females in the postpartum period.
To put the risk of developing a VTE into perspective: If 10,000 females who are not pregnant and do not use oral contraceptives are followed for one year, between 1 and 5 of these females will develop a VTE. Use of RIVELSA provides women with more ho…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions with the use of COCs are discussed elsewhere in the labeling: Serious cardiovascular events [see Boxed Warning and Warnings and Precautions ( 5.1 )] Vascular events [see Warnings and Precautions ( 5.1 )] Liver disease [see Warnings and Precautions ( 5.2 )] The most common adverse reactions (≥2%) in clinical trials for RIVELSA were headaches, heavy/irregular vaginal bleeding, nausea/vomiting, acne, dysmenorrhea, weight increased, mood changes, anxiety/panic attack, breast pain and migraines.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva Pharmaceuticals at 1-888-483-8279 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to the rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety data described below are from a 12-month, US, open-label study, which enrolled women aged 18-40, of whom 3,597 took at least one dose of RIVELSA (2,661 woman-years of exposure) [see Clinical Studies ( 14 )] . Adverse Reactions Leading to Study Discontinuation : 13.3% of the women discontinued from the clinical trial due to an adverse reaction; the most common adverse reactions (≥1% of women) leading to discontinuation were heavy/irregular bleeding (5.0%), mood swings/alteration/affect lability (1.4%), headaches/migraines (1.3%), weight increased (1.3%) and acne (1.0%).
Common Adverse Reactions (≥2% of women) : headaches (12.2%), heavy/irregular vaginal bleeding (9.7%), nausea/vomiting (8.8%), acne (5.4%), dysmenorrhea (5.4%), weight increased (4.6%), mood changes (depression, depressed mood, crying, major depression, affective disorder, depression suicidal, dysthymic disorder) (2.9%), anxiety/panic attack (2.4%), breast tenderness/pain/discomfort (2.2%), migraine (2.0%). Serious Adverse Reactions (≥2 women): abortion spontaneous, suicide attempt, cholecystitis/cholelithiasis, deep vein thrombosis, ectopic pregnancy.
6.2Postmarketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 - 1.12 (Figure 3). Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 2). One of these studies reported no association between breast cancer risk and COC use.
The other two studies found an increased relative risk of 1.19 - 1.33 with current or recent use. Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8-10 years of COC use. Figure 3: Relevant Studies of Risk of Breast Cancer with Combined Oral Contraceptives RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs.
The following adverse reactions have been identified during post-approval use of extended-cycle COCs containing levonorgestrel and ethinyl estradiol. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Gastrointestinal disorders: abdominal distension, vomiting General disorders and administration site conditions: chest pain, fatigue, malaise, edema peripheral, pain Immune system disorders: hypersensitivity reaction Investigations: blood pressure increased Musculoskeletal and connective tissue disorders: muscle spasms, pain in extremity Nervous system disorders: dizziness, loss of consciousness Psychiatric disorders: ins…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The sections below provide information on substances for which data on drug interactions with COCs are available. There is little information available about the clinical effect of most drug interactions that may affect COCs. However, based on the known pharmacokinetic effects of these drugs, clinical strategies to minimize any potential adverse effect on contraceptive effectiveness or safety are suggested.
Consult the approved product labeling of all concurrently used drugs to obtain further information about interactions with COCs or the potential for metabolic enzyme or transporter system alterations. No drug-drug interaction studies were conducted with RIVELSA. Enzyme inducers (e.g., CYP3A4): May decrease the effectiveness of RIVELSA or increase breakthrough bleeding.
Counsel patients to use a backup or alternative method of contraception when enzyme inducers are used with RIVELSA. ( 7.1 )
7.1Effects of Other Drugs on Combined Oral Contraceptives Substances Decreasing the Plasma Concentrations of COCs and Potentially Diminishing the Efficacy of COCs: Table 3 includes substances that demonstrated an important drug interaction with RIVELSA. Table 3: Significant Drug Interactions Involving Substances That Affect COCs Metabolic Enzyme Inducers Clinical effect Concomitant use of COCs with metabolic enzyme inducers may decrease the plasma concentrations of the estrogen and/or progestin component of COCs. Decreased exposure of the estrogen and/or progestin component of COCs may potentially diminish the effectiveness of COCs and may lead to contraceptive failure or an increase in breakthrough bleeding.
Prevention or management Counsel females to use an alternative method of contraception or a backup method when enzyme inducers are used with COCs. Continue backup contraception for 28 days after discontinuing the enzyme inducer to maintain contraceptive reliability. Examples Aprepitant, barbiturates, bosentan, carbamazepine, efavirenz, felbamate, griseofulvin, oxcarbazepine, phenytoin, rifampin, rifabutin, rufinamide, topiramate, products containing St.
John’s wort a , and certain protease inhibitors (see separate section on protease inhibitors below). Colesevelam Clinical effect Concomitant use of COCs with colesevelam significantly decreases systemic exposure of ethinyl estradiol. Decreased exposure of the estrogen component of COCs may potentially reduce contraceptive efficacy or result in an increase in breakthrough bleeding, depending on the strength of ethinyl estradiol in the COC.
Prevention or management Administer 4 or more hours apart to attenuate this drug interaction. a Induction potency of St. John’s wort may vary widely based on preparation. Substances increasing the systemic exposure of COCs: Co-administration of atorvastatin or rosuvastatin and COCs containing ethinyl estradiol increase systemic exposure of ethinyl estradiol by approximately 20 to 25 percent.
Ascorbic acid and acetaminophen may increase systemic exposure of ethinyl estradiol, possibly by inhibition of conjugation. CYP3A4 inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, or ketoconazole may increase systemic exposure of the estrogen and/or progestin component of COCs. Human immunodeficiency virus (HIV)/hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors: Significant decreases in systemic exposure of the estrogen and/or progestin have been noted when COCs are co-administered with some HIV protease inhibitors (e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos)amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir), some HCV protease inhibitors (e.g., boceprevir and telaprevir), and some non-nucleoside reverse transcriptase inhibitors (e.g., nevirapine).
In contrast, significant increases in systemic exposure of the estrogen and/or progestin have been noted when COCs are co-administered with certain other HIV protease inhibitors (e.g., indinavir…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Discontinue use if pregnancy occurs. ( 8.1 ) Lactation: Advise use of another method. RIVELSA is not recommended for nursing mothers; may decrease milk production. ( 8.2 )
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy; therefore, RIVELSA should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively.
8.2Lactation Risk Summary Contraceptive hormones and/or metabolites are present in human milk. CHCs can reduce milk production in breastfeeding females. This reduction can occur at any time but is less likely to occur once breastfeeding is well-established.
When possible, advise the nursing female to use other methods of contraception until she discontinues breastfeeding [See Dosage and Administration ( 2.1 )]. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for RIVELSA and any potential adverse effects on the breastfed child from RIVELSA or the underlying maternal condition.
8.4Pediatric Use Safety and efficacy of RIVELSA have been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 as for users 18 years and older. Use of RIVELSA before menarche is not indicated.
8.6Hepatic Impairment No studies have been conducted to evaluate the effect of hepatic impairment on the disposition of RIVELSA. However, steroid hormones may be poorly metabolized in patients with hepatic impairment. RIVELSA is contraindicated in females with acute hepatitis or severe decompensated cirrhosis. [See Contraindications ( 4 ) and Warnings and Precautions ( 5.2 )]
8.6Hepatic Impairment No studies have been conducted to evaluate the effect of hepatic impairment on the disposition of RIVELSA. However, steroid hormones may be poorly metabolized in patients with hepatic impairment. RIVELSA is contraindicated in females with acute hepatitis or severe decompensated cirrhosis. [See Contraindications ( 4 ) and Warnings and Precautions ( 5.2 )]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy; therefore, RIVELSA should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of RIVELSA have been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 as for users 18 years and older. Use of RIVELSA before menarche is not indicated.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of serious ill effects from overdose of oral contraceptives, including ingestion by children. Overdosage may cause withdrawal bleeding in females and nausea.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action CHCs prevent pregnancy primarily by suppressing ovulation.
12.2Pharmacodynamics No pharmacodynamic studies were conducted with RIVELSA.
12.3Pharmacokinetics Absorption Ethinyl estradiol and levonorgestrel are absorbed with maximum plasma concentrations occurring within 2 hours after RIVELSA administration. Levonorgestrel is completely absorbed after oral administration (bioavailability nearly 100%) and is not subject to first-pass metabolism. Ethinyl estradiol is absorbed from the gastrointestinal tract but, due to first-pass metabolism in gut mucosa and liver, the bioavailability of ethinyl estradiol is approximately 40%.
The effect of food on the rate and the extent of levonorgestrel and ethinyl estradiol absorption following oral administration of RIVELSA has not been evaluated. The mean plasma pharmacokinetic parameters of levonorgestrel following administration of another levonorgestrel/ethinyl estradiol combination tablet with an equal dose of levonorgestrel for 84 days, in healthy women are reported in Table 5. Table 5: Mean Pharmacokinetic Parameters for 150 mcg Levonorgestrel Following Administration of a Levonorgestrel/Ethinyl Estradiol Combination Tablet Once Daily for 84 Days AUC 0-24 hr (mean ± SD) C max (mean ± SD) T max (mean ± SD) Day 1 18.2 ± 6.1 ng•hr/mL 3.0 ± 1.0 ng/mL 1.3 ± 0.4 hours Day 21 64.4 ± 25.1 ng•hr/mL 6.2 ± 1.6 ng/mL 1.3 ± 0.4 hours Day 84 60.2 ± 24.6 ng•hr/mL 5.5 ± 1.6 ng/mL 1.3 ± 0.3 hours Following repeated daily dosing of levonorgestrel/ethinyl estradiol oral contraceptives, levonorgestrel plasma concentrations accumulate more than predicted based on single-dose pharmacokinetics, due in part, to increased sex hormone binding globulin (SHBG) levels that are induced by ethinyl estradiol, and a possible reduction in hepatic metabolic capacity.
Systemic exposure to ethinyl estradiol following administration of a levonorgestrel/ethinyl estradiol combination tablet increases linearly in an approximate dose-proportional manner over the range of doses of 20 mcg to 30 mcg within this product. Systemic exposure to ethinyl estradiol (as assessed by AUC) at steady state following administration of levonorgestrel/ethinyl estradiol oral contraceptives is approximately 20% higher than expected based on single-dose data for the dose range of 20-30 mcg. Distribution The apparent volume of distribution of levonorgestrel is reported to be approximately
1.8L/kg. Levonorgestrel is about 97.5 - 99% protein-bound, principally to SHBG and, to a lesser extent, serum albumin. The apparent volume of distribution of ethinyl estradiol is reported to be approximately
4.3L/kg. Ethinyl estradiol is about 95-97% bound to serum albumin. Ethinyl estradiol does not bind to SHBG, but induces SHBG synthesis, which leads to decreased levonorgestrel clearance.
Metabolism Following absorption, levonorgestrel is conjugated at the 17β-OH position to form sulfate and to a lesser extent, glucuronide conjugates in plasma. Significant amounts of conjugated and unconjugated 3α,5β-tetrahydrolevonorgestrel are also present in plasma, along with much smaller amounts of 3α,5α-tetrahydrolevonorgestrel and 16β-hydroxylevonorgestrel. Levonorgestrel and its phase I metabolites are excreted primarily as glucuronide conjugates.
Metabolic clearance rates may differ among individuals by several-fold, and this may account in part for the wide variation observed in levonorgestrel concentrations among users. First-pass metabolism of ethinyl estradiol involves formation of ethinyl estradiol-3-sulfate in the gut wall, followed by 2-hydroxylation of a portion of the remaining untransformed ethinyl estradiol by hepatic cytochrome P-450 3A4 (CYP3A4). Levels of CYP3A4 vary widely among individuals and can explain the variation in rates of ethinyl estradiol hydroxylation.
Hydroxylation at the 4-, 6-, and 16- positions may also occur, although to a much lesser extent than 2-hydroxylation. The various hydroxyla…
🧬 Mechanism of Action ▾
12.1Mechanism of Action CHCs prevent pregnancy primarily by suppressing ovulation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied RIVELSA (levonorgestrel/ethinyl estradiol and ethinyl estradiol) tablets are available as round, film-coated, unscored, biconvex tablets debossed with TV on one side, packaged in an Extended-Cycle Tablet Dispenser, each containing a 13-week supply of the tablets in the following order: 42 light pink tablets, each containing 0.15 mg of levonorgestrel and 0.02 mg ethinyl estradiol: debossed with 076 on the other side 21 pink tablets containing 0.15 mg of levonorgestrel and 0.025 mg ethinyl estradiol: debossed with 075 on the other side 21 purple tablets containing 0.15 mg of levonorgestrel and 0.03 mg ethinyl estradiol: debossed with 074 on the other side and 7 yellow tablets containing 0.01 mg of ethinyl estradiol: debossed with 077 on the other side Box of 2 Extended-Cycle Tablet Dispensers NDC 0093-6031-82 Storage and Handling Store at 20°C to 25°C (68°F to 77°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION RIVELSA (levonorgestrel/ethinyl estradiol and ethinyl estradiol) tablets is an extended-cycle oral contraceptive. RIVELSA consists of 42 light pink tablets containing 0.15 mg levonorgestrel and 0.02 mg ethinyl estradiol, 21 pink tablets containing 0.15 mg levonorgestrel and 0.025 mg ethinyl estradiol, and 21 purple tablets containing 0.15 mg levonorgestrel and 0.03 mg ethinyl estradiol, and 7 yellow tablets containing 0.01 mg ethinyl estradiol. Levonorgestrel is a progestin and ethinyl estradiol is an estrogen.
The structural formulas, molecular formulas, molecular weights, and chemical names for the active components are shown below: Levonorgestrel C 21 H 28 O 2 MW: 312.4 Levonorgestrel is chemically 18,19-Dinorpregn-4-en-20-yn-3-one, 13-ethyl-17-hydroxy-(17α)-(-)-. Ethinyl Estradiol C 20 H 24 O 2 MW: 296.4 Ethinyl Estradiol is 19-Norpregna-1,3,5(10)-trien-20-yne-3,17-diol, (17α)-. Each light pink tablet contains the following inactive ingredients: anhydrous lactose, D&C Red no.
27/phloxine aluminum lake, FD&C Blue no. 2/Indigo Carmine aluminum lake, FD&C Yellow no. 6/Sunset Yellow FCF aluminum lake, hypromellose, lactose monohydrate, microcrystalline cellulose, magnesium stearate, polyethylene glycol/macrogol, titanium dioxide, and triacetin.
Each pink tablet contains the following inactive ingredients: anhydrous lactose, D&C Red no. 27/phloxine aluminum lake, FD&C Blue no. 2/Indigo Carmine aluminum lake, hypromellose, lactose monohydrate, microcrystalline cellulose, magnesium stearate, polyethylene glycol/macrogol, titanium dioxide and triacetin.
Each purple tablet contains the following inactive ingredients: anhydrous lactose, D&C Red no. 27/phloxine aluminum lake, FD&C Blue no. 1/Brilliant Blue FCF aluminum lake, hypromellose, lactose monohydrate, microcrystalline cellulose, magnesium stearate, polyethylene glycol/macrogol, titanium dioxide and triacetin.
Each yellow tablet contains the following inactive ingredients: anhydrous lactose, D&C Yellow no. 10 aluminum lake, FD&C Yellow no. 6/Sunset Yellow FCF aluminum lake, hypromellose, magnesium stearate, microcrystalline cellulose, polacrilin potassium, polyethylene glycol/macrogol, polysorbate 80 and titanium dioxide. levonorgestril structure ethinyl estradiol structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Counsel patients about the following information: Cigarette Smoking Cigarette smoking increases the risk of serious cardiovascular events from COC use, Women who are over 35 years old and smoke should not use RIVELSA [see Boxed Warning and Warnings and Precautions ( 5.1 )] . Venous Thromboembolism Increased risk of VTE compared to non-users of COCs is greatest after initially starting a COC or restarting (following a 4-week or greater pill-free interval) the same or a different COC [see Warnings and Precautions ( 5.1 )] .
Use during Pregnancy Instruct females to stop RIVELSA if pregnancy is confirmed during treatment. Sexually Transmitted Infections RIVELSA does not protect against HIV infection and other sexually transmitted infections. Dosing and Missed Pill Instructions Patients should take one tablet daily by mouth at the same time every day.
Instruct patients what to do in the event pills are missed. See [see Dosage and Administration ( 2.3 )] . Instruct patients to see, “What to do if you miss pills” section of the FDA-Approved Instructions for Use.
Need for Additional Contraception Postpartum females who have not yet had a period when they start RIVELSA need to use an additional method of contraception until they have taken a light pink tablet for 7 consecutive days [see Dosage and Administration ( 2.2 )] . There is a need for a backup or alternative method of contraception when enzyme inducers are used with RIVELSA [see Drug Interactions ( 7.1 )] . Lactation RIVELSA may reduce breast milk production.
This is less likely to occur if breastfeeding is well established. When possible, nursing women should use other methods of contraception until they have discontinued breastfeeding [see Use in Specific Populations ( 8.2 )] . Amenorrhea and Possible Symptoms of Pregnancy Amenorrhea may occur [see Warnings and Precautions (5.9)] .
Advise the patient to contact a healthcare provider in the event of amenorrhea with symptoms of pregnancy, such as morning sickness or unusual breast tenderness [see Use in Specific Populations ( 8.1 ] . Depression Depressed mood and depression may occur. Women should contact their healthcare provider if mood changes and depressive symptoms occur, including shortly after initiating the treatment [see Warnings and Precautions ( 5.10 )] .
Manufactured for: Teva Pharmaceuticals Parsippany, NJ 07054 Rev. 10/2024 RIV-005 ©2024 Teva Pharmaceuticals, Inc.