
Magnesium Sulfate 500 mg/mL Injection, Solution — NDC 0409-1754-10 (Billing 00409-1754-10)
This is a package of Magnesium Sulfate 500 mg/mL Injection, Solution from Hospira, Inc., marketed since Nov 2006 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0409-1754-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0409 labeler · 1754 product · 10 package
- Package marketed since
- Nov 28, 2006
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0409175410 2
- Medicaid fills, this package
- 205 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 001413
- GCN: 04120
- GPI-14 (Medi-Span): 79400010402020
- HICL (First Databank): 000610
- AHFS class code: 24:04.04.92
- RxCUI (RxNorm): 829762
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Osmotically acting laxatives class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. The IV injection is used in hospitals to prevent and control seizures in preeclampsia and eclampsia. Epsom salt products by mouth are for occasional cons...
- Follow your package directions. They generally say to dissolve the dose in a full glass of water and then drink more liquid. It usually works in about 30 minutes to 6 hours. Don't...
- How do I take Epsom salt for constipation?
- Flushing, sweating, low blood pressure, and drowsiness are common. Your team also checks your reflexes, breathing and magnesium levels to catch problems early.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Magnesium Sulfate (prescription drug) — tap one for details:
Magnesium Sulfate (prescription drug) may be associated with lower levels of 6 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1.24 | $124.09 / 100 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J3475 | $0.446 / J3475 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00409-1754-10 You're viewing this Main listing | 10 CARTON in 1 PACKAGE / 1 SYRINGE, PLASTIC in 1 CARTON / 10 mL in 1 SYRINGE, PLASTIC | 2006-11-28 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Magnesium Sulfate 500 mg/mL 00404-9903-10 | Henry | 1 syringe | — | AP | FDA listed | — |
| Magnesium Sulfate 500 mg/mLthis 00409-1754-10 | Hospira, | 1 syringe | — | AP | FDA listed | — |
| 50% Magnesium Sulfate 500 mg/mL 51662-1235-01 | HF | 1 syringe | — | AP | FDA listed | — |
| Magnesium Sulfate 500 mg/mL 51662-1372-01 | HF | 20 ml | — | AP | FDA listed | — |
| Magnesium Sulfate 500 mg/mL 51662-1390-01 | HF | 2 ml | — | AP | FDA listed | — |
| Magnesium Sulfate 500 mg/mL 00404-9904-02 | Henry | 1 vial | — | AP | FDA listed | — |
| Magnesium Sulfate 500 mg/mL 00409-2168-77 | Hospira, | 25 vials | — | AP | FDA listed | — |
| Magnesium Sulfate 500 mg/mL 00404-9902-20 | Henry | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Magnesium Sulfate inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII O40UQP6WCF
A strong acid used in small amounts to adjust and maintain the pH balance of a medicine, helping ensure stability and proper dissolution of the active ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Hospira, Inc. labeler code 00409
- Bortezomib 2.5 mg Injection, Powder, Lyophilized, For Solution NDC 0409-1703-01
- Bortezomib 1 mg Injection, Powder, Lyophilized, For Solution NDC 0409-1704-01
- Docetaxel 10 mg/mL Injection, Solution NDC 0409-1732-01
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 2.5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1746-10
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1749-10
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 2.5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1752-50
- Marcaine with Epinephrine BUPIVACAINE HYDROCHLORIDE AND EPINEPHRINE BITARTRATE 5 mg/mL; .0091 mg/mL Injection, Solution NDC 0409-1755-50
- Marcaine Spinal Bupivacaine Hydrochloride in Dextrose 7.5 mg/mL Injection, Solution NDC 0409-1761-02
- Dextrose 250 mg/mL Injection, Solution NDC 0409-1775-10
- Metoprolol Tartrate 1 mg/mL Injection, Solution NDC 0409-1778-05
- Naloxone Hydrochloride .4 mg/mL Injection, Solution NDC 0409-1782-69
- Hydromorphone Hydrochloride .25 mg/.5mL Injection, Solution NDC 0409-1805-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Magnesium Sulfate Injection, USP is suitable for replacement therapy in magnesium deficiency, especially in acute hypomagnesemia accompanied by signs of tetany similar to those observed in hypocalcemia. In such cases, the serum magnesium (Mg ++ ) level is usually below the lower limit of normal (1.5 to 2.5 mEq/liter) and the serum calcium (Ca ++ ) level is normal (4.3 to 5.3 mEq/liter) or elevated. In total parenteral nutrition (TPN), magnesium sulfate may be added to the nutrient admixture to correct or prevent hypomagnesemia which can arise during the course of therapy.
Magnesium Sulfate Injection, USP is also indicated for the prevention and control of seizures (convulsions) in pre-eclampsia and eclampsia, respectively.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Dosage of magnesium sulfate must be carefully adjusted according to individual requirements and response, and administration of the drug should be discontinued as soon as the desired effect is obtained. Both intravenous and intramuscular administration are appropriate. Intramuscular administration of the undiluted 50% solution results in therapeutic plasma levels in 60 minutes, whereas intravenous doses will provide a therapeutic level almost immediately.
The rate of intravenous injection should generally not exceed 150 mg/minute (1.5 mL of a 10% concentration or its equivalent), except in severe eclampsia with seizures (see below). Continuous maternal administration of magnesium sulfate in pregnancy beyond 5 to 7 days can cause fetal abnormalities. Solutions for intravenous infusion must be diluted to a concentration of 20% or less prior to administration.
The diluents commonly used are 5% Dextrose Injection, USP and 0.9% Sodium Chloride Injection, USP. Deep intramuscular injection of the undiluted (50%) solution is appropriate for adults, but the solution should be diluted to a 20% or less concentration prior to such injection in children. In Magnesium Deficiency In the treatment of mild magnesium deficiency, the usual adult dose is 1 gram, equivalent to 8.12 mEq of magnesium (2 mL of the 50% solution) injected intramuscularly every six hours for four doses (equivalent to a total of 32.5 mEq of magnesium per 24 hours).
For severe hypomagnesemia, as much as 250 mg (approximately 2 mEq) per kg of body weight (0.5 mL of the 50% solution) may be given intramuscularly within a period of four hours if necessary. Alternatively, 5 grams, (approximately 40 mEq) can be added to one liter of 5% Dextrose Injection, USP or 0.9% Sodium Chloride Injection, USP for slow intravenous infusion over a three-hour period. In the treatment of deficiency states, caution must be observed to prevent exceeding the renal excretory capacity.
In Hyperalimentation In TPN, maintenance requirements for magnesium are not precisely known. The maintenance dose used in adults ranges from 8 to 24 mEq (1 gram to 3 grams) daily; for infants, the range is 2 to 10 mEq (0.25 gram to 1.25 grams) daily. In Pre-eclampsia or Eclampsia In severe pre-eclampsia or eclampsia, the total initial dose is 10 grams to 14 grams of magnesium sulfate.
Intravenously, a dose of 4 grams to 5 grams in 250 mL of 5% Dextrose Injection, USP or 0.9% Sodium Chloride Injection, USP may be infused. Simultaneously, intramuscular doses of up to 10 grams (5 grams or 10 mL of the undiluted 50% solution in each buttock) are given. Alternatively, the initial intravenous dose of 4 grams may be given by diluting the 50% solution to a 10 or 20% concentration; the diluted fluid (40 mL of a 10% solution or 20 mL of a 20% solution) may then be injected intravenously over a period of three to four minutes.
Subsequently, 4 grams to 5 grams (8 to 10 mL of the 50% solution) are injected intramuscularly into alternate buttocks every four hours as needed, depending on the continuing presence of the patellar reflex and adequate respiratory function. Alternatively, after the initial intravenous dose, some clinicians administer 1 gram to 2 grams/hour by constant intravenous infusion. Therapy should continue until paroxysms cease.
A serum magnesium level of 6 mg/100 mL is considered optimal for control of seizures. A total daily (24 hr) dose of 30 grams to 40 grams should not be exceeded. In the presence of severe renal insufficiency, the maximum dosage of magnesium sulfate is 20 grams/48 hours and frequent serum magnesium concentrations must be obtained.
Continuous use of magnesium sulfate in pregnancy beyond 5 to 7 days can cause fetal abnormalities. Other Uses In counteracting the muscle-stimulating effects of barium poisoning, the usual dose of magnesium sulfate is 1 gram to 2 grams given intravenously. For controlling seizures associated with epilepsy, glomerulonephritis or hypothyroi… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Parenteral administration of the drug is contraindicated in patients with heart block or myocardial damage.
⚠️ Warnings ▾
WARNINGS FETAL HARM: Continuous administration of magnesium sulfate beyond 5 to 7 days to pregnant women can lead to hypocalcemia and bone abnormalities in the developing fetus. These bone abnormalities include skeletal demineralization and osteopenia. In addition, cases of neonatal fracture have been reported.
The shortest duration of treatment that can lead to fetal harm is not known. Magnesium sulfate should be used during pregnancy only if clearly needed. If magnesium sulfate is given for treatment of preterm labor, the woman should be informed that the efficacy and safety of such use have not been established and that use of magnesium sulfate beyond 5 to 7 days may cause fetal abnormalities.
ALUMINUM TOXICITY: This product contains aluminum that may be toxic. Aluminum may reach toxic levels with prolonged parenteral administration if kidney function is impaired. Premature neonates are particularly at risk because their kidneys are immature, and they require large amounts of calcium and phosphate solutions, which contain aluminum.
Research indicates that patients with impaired kidney function, including premature neonates, who receive parenteral levels of aluminum at greater than 4 to 5 mcg/kg/day accumulate aluminum at levels associated with central nervous system and bone toxicity. Tissue loading may occur at even lower rates of administration. Parenteral use in the presence of renal insufficiency may lead to magnesium intoxication.
Intravenous use in the eclampsia should be reserved for immediate control of life-threatening convulsions.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The adverse effects of parenterally administered magnesium usually are the result of magnesium intoxication. These include flushing, sweating, hypotension, depressed reflexes, flaccid paralysis, hypothermia, circulatory collapse, cardiac and central nervous system depression proceeding to respiratory paralysis. Hypocalcemia with signs of tetany secondary to magnesium sulfate therapy for eclampsia has been reported.
🆘 Overdosage ▾
OVERDOSAGE Magnesium intoxication is manifested by a sharp drop in blood pressure and respiratory paralysis. Disappearance of the patellar reflex is a useful clinical sign to detect the onset of magnesium intoxication. In the event of overdosage, artificial ventilation must be provided until a calcium salt can be injected intravenously to antagonize the effects of magnesium.
For Treatment of Overdose Artificial respiration is often required. Intravenous calcium, 10 to 20 mL of a 5% solution (diluted if desirable with isotonic sodium chloride for injection) is used to counteract effects of hypermagnesemia. Subcutaneous physostigmine, 0.5 to 1 mg may be helpful.
Hypermagnesemia in the newborn may require resuscitation and assisted ventilation via endotracheal intubation or intermittent positive pressure ventilation as well as intravenous calcium.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Magnesium (Mg ++ ) is an important cofactor for enzymatic reactions and plays an important role in neurochemical transmission and muscular excitability. As a nutritional adjunct in hyperalimentation, the precise mechanism of action for magnesium is uncertain. Early symptoms of hypomagnesemia (less than 1.5 mEq/liter) may develop as early as three to four days or within weeks.
Predominant deficiency effects are neurological, e.g., muscle irritability, clonic twitching and tremors. Hypocalcemia and hypokalemia often follow low serum levels of magnesium. While there are large stores of magnesium present intracellularly and in the bones of adults, these stores often are not mobilized sufficiently to maintain plasma levels.
Parenteral magnesium therapy repairs the plasma deficit and causes deficiency symptoms and signs to cease. Magnesium prevents or controls convulsions by blocking neuromuscular transmission and decreasing the amount of acetylcholine liberated at the end plate by the motor nerve impulse. Magnesium is said to have a depressant effect on the central nervous system (CNS), but it does not adversely affect the woman, fetus or neonate when used as directed in eclampsia or pre-eclampsia.
Normal plasma magnesium levels range from 1.5 to 2.5 mEq/liter. As plasma magnesium rises above 4 mEq/liter, the deep tendon reflexes are first decreased and then disappear as the plasma level approaches 10 mEq/liter. At this level respiratory paralysis may occur.
Heart block also may occur at this or lower plasma levels of magnesium. Serum magnesium concentrations in excess of 12 mEq/L may be fatal. Magnesium acts peripherally to produce vasodilation.
With low doses only flushing and sweating occur, but larger doses cause lowering of blood pressure. The central and peripheral effects of magnesium poisoning are antagonized to some extent by intravenous administration of calcium. Pharmacokinetics With intravenous administration the onset of anticonvulsant action is immediate and lasts about 30 minutes.
Following intramuscular administration the onset of action occurs in about one hour and persists for three to four hours. Effective anticonvulsant serum levels range from 2.5 to 7.5 mEq/liter. Magnesium is excreted solely by the kidneys at a rate proportional to the plasma concentration and glomerular filtration.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Magnesium Sulfate Injection, USP is supplied in single-dose containers as follows: NDC No. Container Total Amount Concentration mEq Mg ++ /mL 0409-1754-10 Ansyr™ Plastic Syringe 5 g/10 mL 50% 4 mEq/mL Do not administer unless solution is clear and container is undamaged. Discard unused portion. Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F). [See USP Controlled Room Temperature.]
📋 Description ▾
DESCRIPTION Magnesium Sulfate Injection, USP 50% is a sterile solution of magnesium sulfate heptahydrate in Water for Injection, USP administered by the intravenous or intramuscular routes as an electrolyte replenisher or anticonvulsant. Must be diluted before intravenous use. May contain sulfuric acid and/or sodium hydroxide for pH adjustment.
The pH is 5.5 to 7.0. The 50% concentration has an osmolarity of 4.06 mOsmol/mL (calc.). The solution contains no bacteriostat, antimicrobial agent or added buffer (except for pH adjustment) and is intended only for use as a single-dose injection.
When smaller doses are required the unused portion should be discarded with the entire unit. Magnesium Sulfate, USP heptahydrate is chemically designated MgSO 4 • 7H 2 O with molecular weight of 246.48 and occurs as colorless crystals or white powder freely soluble in water. The plastic syringe is molded from a specially formulated polypropylene.
Water permeates from inside the container at an extremely slow rate which will have an insignificant effect on solution concentration over the expected shelf life. Solutions in contact with the plastic container may leach out certain chemical components from the plastic in very small amounts; however, biological testing was supportive of the safety of the syringe material.
⚠️ Precautions ▾
PRECAUTIONS General Administer with caution if flushing and sweating occurs. When barbiturates, narcotics or other hypnotics (or systemic anesthetics) are to be given in conjunction with magnesium, their dosage should be adjusted with caution because of additive CNS depressant effects of magnesium. Because magnesium is removed from the body solely by the kidneys, the drug should be used with caution in patients with renal impairment.
Urine output should be maintained at a level of 100 mL or more during the four hours preceding each dose. Monitoring serum magnesium levels and the patient's clinical status is essential to avoid the consequences of overdosage in toxemia. Clinical indications of a safe dosage regimen include the presence of the patellar reflex (knee jerk) and absence of respiratory depression (approximately 16 breaths or more/minute).
When repeated doses of the drug are given parenterally, knee jerk reflexes should be tested before each dose and if they are absent, no additional magnesium should be given until they return. Serum magnesium levels usually sufficient to control convulsions range from 3 to 6 mg/100 mL (2.5 to 5 mEq/liter). The strength of the deep tendon reflexes begins to diminish when magnesium levels exceed 4 mEq/liter.
Reflexes may be absent at 10 mEq magnesium/liter, where respiratory paralysis is a potential hazard. An injectable calcium salt should be immediately available to counteract the potential hazards of magnesium intoxication in eclampsia. 50% Magnesium Sulfate Injection, USP must be diluted to a concentration of 20% or less prior to intravenous infusion.
Rate of administration should be slow and cautious, to avoid producing hypermagnesemia. The 50% solution also should be diluted to 20% or less for intramuscular injection in infants and children. Laboratory Tests Magnesium sulfate injection should not be given unless hypomagnesemia has been confirmed and the serum concentration of magnesium is monitored.
The normal serum level is 1.5 to 2.5 mEq/L. Drug Interactions CNS Depressants — When barbiturates, narcotics or other hypnotics (or systemic anesthetics), or other CNS depressants are to be given in conjunction with magnesium, their dosage should be adjusted with caution because of additive CNS depressant effects of magnesium. CNS depression and peripheral transmission defects produced by magnesium may be antagonized by calcium.
Neuromuscular Blocking Agents — Excessive neuromuscular block has occurred in patients receiving parenteral magnesium sulfate and a neuromuscular blocking agent; these drugs should be administered concomitantly with caution. Cardiac Glycosides — Magnesium sulfate should be administered with extreme caution in digitalized patients, because serious changes in cardiac conduction which can result in heart block may occur if administration of calcium is required to treat magnesium toxicity. Pregnancy (See WARNINGS and PRECAUTIONS ) Teratogenic Effects Magnesium sulfate can cause fetal abnormalities when administered beyond 5 to 7 days to pregnant women.
There are retrospective epidemiological studies and case reports documenting fetal abnormalities such as hypocalcemia, skeletal demineralization, osteopenia and other skeletal abnormalities with continuous maternal administration of magnesium sulfate for more than 5 to 7 days. 1-10 Magnesium sulfate injection should be used during pregnancy only if clearly needed. If this drug is used during pregnancy, the woman should be apprised of the potential harm to the fetus.
Nonteratogenic Effects When administered by continuous intravenous infusion (especially for more than 24 hours preceding delivery) to control convulsions in a toxemic woman, the newborn may show signs of magnesium toxicity, including neuromuscular or respiratory depression (See OVERDOSAGE ). Labor and Delivery Continuous administration of magnesium sulfate is an unapproved treatment for preterm labor. The safety and efficacy of such use have not been esta… [Excerpted — this section continues on DailyMed.]
📚 References ▾
REFERENCES 1. Yokoyama K, Takahashi N, Yada Y. Prolonged maternal magnesium administration and bone metabolism in neonates.
Early Hum Dev . 2010;86(3):187-91. Epub 2010 Mar 12.
2. Wedig KE, Kogan J, Schorry EK et al. Skeletal demineralization and fractures caused by fetal magnesium toxicity.
J. Perinatol . 2006; 26(6):371-4.
3. Nassar AH, Sakhel K, Maarouf H, et al. Adverse maternal and neonatal outcome of prolonged course of magnesium sulfate tocolysis.
Acta Obstet Gynecol Scan . 2006;85(9):1099-103. 4.
Malaeb SN, Rassi A, Haddad MC. Bone mineralization in newborns whose mothers received magnesium sulphate for tocolysis of premature labor. Pediatr Radiol .
2004;34(5):384-6. Epub 2004 Feb 18. 5.
Matsuda Y, Maeda Y, Ito M, et al. Effect of magnesium sulfate treatment on neonatal bone abnormalities. Gynecol Obstet Invest .
1997;44(2):82-8. 6. Schanler RJ, Smith LG, Burns PA.
Effects of long-term maternal intravenous magnesium sulfate therapy on neonatal calcium metabolism and bone mineral content. Gynecol Obstet Invest . 1997;43(4):236-41.
7. Santi MD, Henry GW, Douglas GL. Magnesium sulfate treatment of preterm labor as a cause of abnormal neonatal bone mineralization.
J Pediatr Orthrop . 1994;14(2):249-53. 8.
Holcomb WL, Shackelford GD, Petrie RH. Magnesium tocolysis and neonatal bone abnormalities; a controlled study. Obstet Gynecol .
1991; 78(4):611-4. 9. Cumming WA, Thomas VJ.
Hypermagnesemia: a cause of abnormal metaphyses in the neonate. Am J Roentgenol . 1989; 152(5):1071-2.
10. Lamm CL, Norton KL, Murphy RJ. Congenital rickets associated with magnesium sulfate infusion for tocolysis.
J Pediatr . 1988; 113(6):1078-82. 11.
McGuinness GA, Weinstein MM, Cruikshank DP, et al. Effects of magnesium sulfate treatment on perinatal calcium metabolism. II.
Neonatal responses. Obstet Gynecol . 1980; 56(5): 595-600.
12. Riaz M, Porat R, Brodsky NL, et al. The effects of maternal magnesium sulfate treatment on newborns: a prospective controlled study.
J. Perinatol . 1998;18(6 pt 1):449-54.
Distributed by Hospira, Inc., Lake Forest, IL 60045 USA LAB-1024-4.0 Revised: 05/2020 Hospira Logo
📄 Package Label / Principal Display Panel ▾
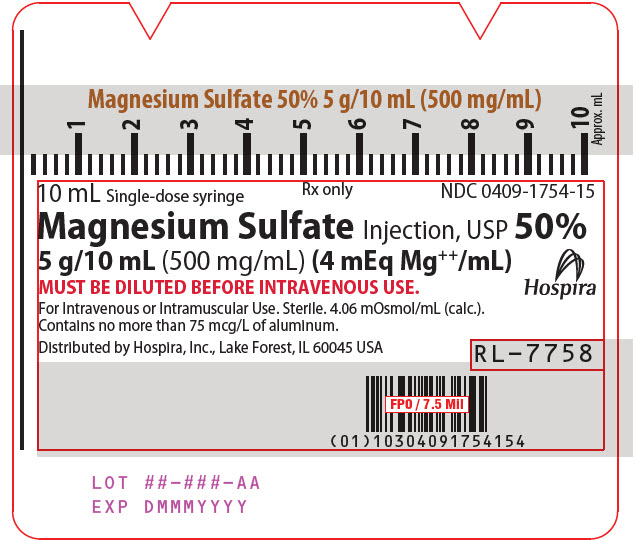
PRINCIPAL DISPLAY PANEL - 10 mL Syringe Label Magnesium Sulfate 50% 5 g/10 mL (500 mg/mL) 10 mL Single-dose syringe Rx only NDC 0409-1754-15 Magnesium Sulfate Injection, USP 50% 5 g/10 mL (500 mg/mL) (4 mEq Mg ++ /mL) MUST BE DILUTED BEFORE INTRAVENOUS USE. For Intravenous or Intramuscular Use. Sterile.
4.06mOsmol/mL (calc.). Contains no more than 75 mcg/L of aluminum. Distributed by Hospira, Inc., Lake Forest, IL 60045 USA Hospira RL–7758 LOT ##–###–AA EXP DMMMYYYY PRINCIPAL DISPLAY PANEL - 10 mL Syringe Label
PRINCIPAL DISPLAY PANEL - 10 mL Syringe Carton 10 mL NDC 0409-1754-15 Rx only Single-dose syringe Magnesium Sulfate Injection, USP 50% 5 g/10 mL (500 mg/mL) (4 mEq Mg ++ /mL) For intravenous or intramuscular use Ansyr™ Single-dose syringe CAUTION: Must be diluted before intravenous use. Hospira LOT #####AA EXP DMMMYYYY ◀ PRESS AND PULL TO OPEN ▶ PRINCIPAL DISPLAY PANEL - 10 mL Syringe Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |