
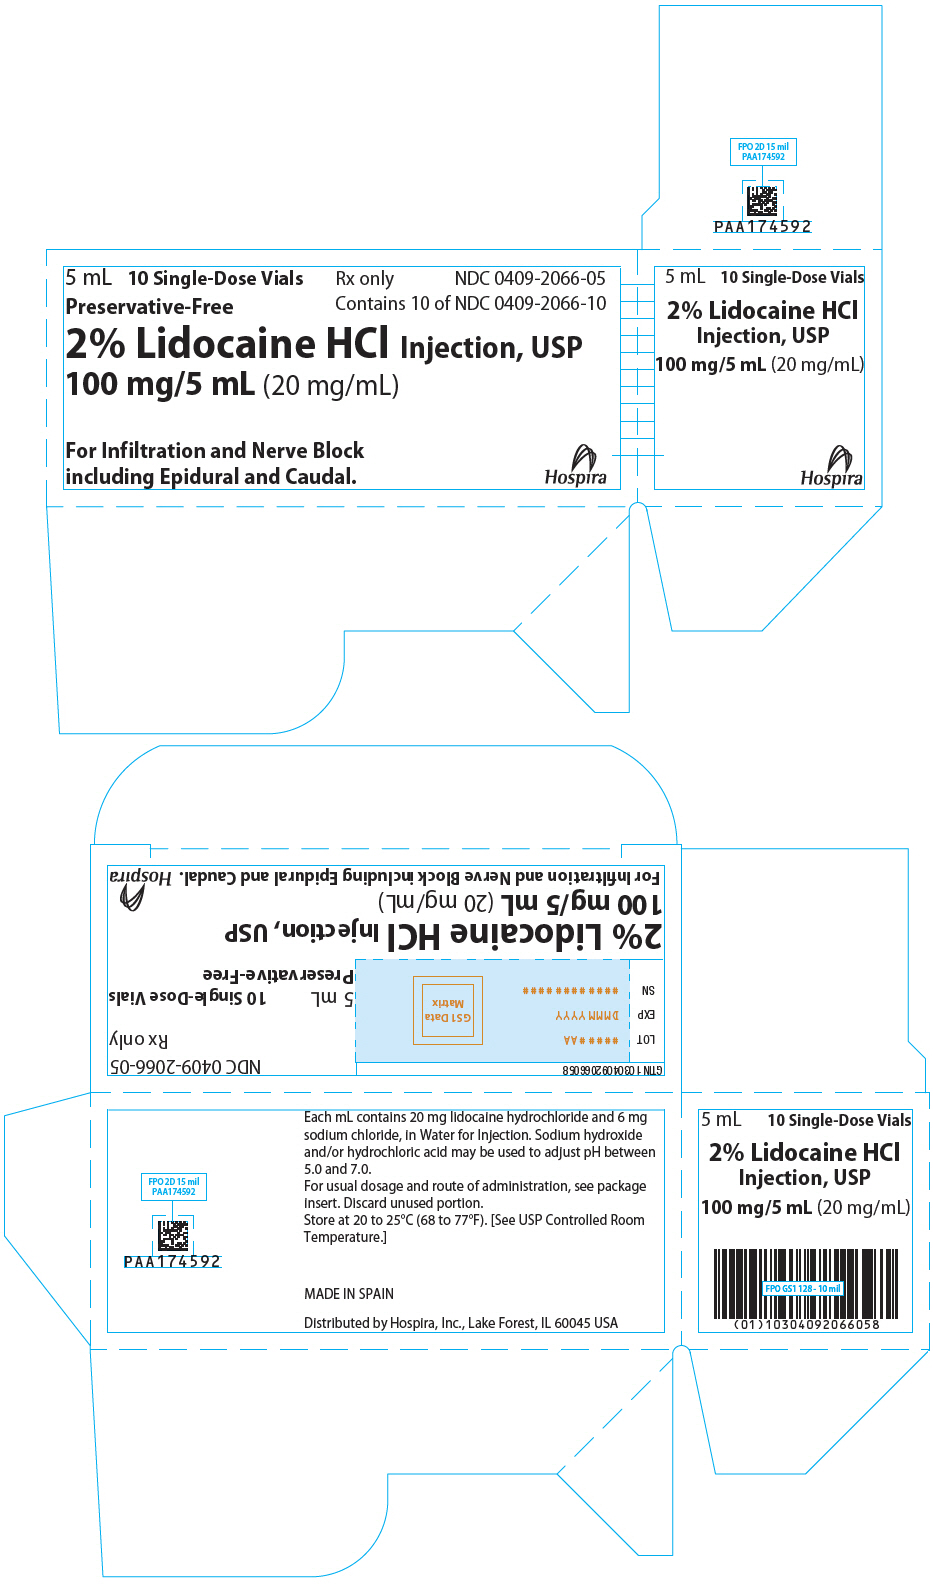
Lidocaine Hydrochloride 20 mg/mL Injection, Solution — NDC 0409-2066-05 (Billing 00409-2066-05)
This is a package of Lidocaine Hydrochloride 20 mg/mL Injection, Solution from Hospira, Inc., marketed since Sep 2005 and currently FDA-listed; retail pharmacies pay about $0.3487 per mL (NADAC). It is this product's only package size.
Other active recalls for Lidocaine Hydrochloride (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 060674
- GCN: 26885
- HICL (First Databank): 033592
- AHFS class code: 24:04.04.08
- RxCUI (RxNorm): 1737761
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Antiarrhythmic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Lidocaine numbs the area where it is used. Clinicians inject it for procedures. Skin products are used for pain, itching, minor burns, insect bites, hemorrhoid discomfort, and in s...
- Clean and dry the skin first, then apply as your product’s directions say. Wash your hands afterward. Don’t exceed the number of uses on the label. Ask a doctor before using a prod...
- No. Heat can increase how much lidocaine your body absorbs. Don’t bandage tightly either. Also avoid using other topical pain products at the same time.
- Can I use a heating pad with a lidocaine patch?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.349 | $17.44 / 50 ml |
| Medicaid paysCMS SDUD · 12 mo | $5.27 | $263.54 / 50 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2003 | No ASP payment limit on file for J2003 this quarter. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00409-2066-05 You're viewing this Main listing | 10 VIAL, SINGLE-DOSE in 1 CARTON / 5 mL in 1 VIAL, SINGLE-DOSE | 2005-09-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lidocaine Hydrochloride 20 mg/mLthis 00409-2066-05 | Hospira, | 10 vials | $0.349 | AP | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mL 31722-0118-31 | Camber | 25 vials | $0.349 | AP | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mL 55150-0165-05 | Eugia | 10 vials | $0.349 | AP | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mL 72603-0505-10 | NorthStar | 10 vials | $0.349 | AP | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mL 72603-0410-25 | NorthStar | 25 vials | $0.349 | AP | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mL 00143-9594-25 | Hikma | 25 vials | $0.363 | AP | Availability likely | +4% |
| Lidocaine Hydrochloride 20 mg/mL 68094-0081-25 | Precision | 25 vials | $0.363 | AP | Availability likely | +4% |
| Lidocaine Hydrochloride 20 mg/mL 72572-0372-25 | Civica, | 25 vials | $0.363 | AP | Availability likely | +4% |
| Lidocaine Hydrochloride 20 mg/mL 00404-9897-05 | Henry | 1 vial | — | AP | FDA listed | — |
| Lidocaine Hci 20 mg/mL 51662-1233-01 | HF | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hci 20 mg/mL 51662-1364-01 | HF | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hci 20 mg/mL 51662-1422-01 | HF | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hci 20 mg/mL 51662-1543-01 | HF | 5 ml | — | AP | FDA listed | — |
| XYLOCAINE- MPF (LIDOCAINE HCl ) 20 mg/mL 51662-1604-03 | HF | 25 pouches | — | AP | FDA listed | — |
| Lidocaine 20 mg/mL 63323-0208-05 | Fresenius | 25 vials | — | AP | FDA listed | — |
| Xylocaine MPF 20 mg/mL 63323-0495-26 | Fresenius | 25 vials | — | AP | FDA listed | — |
| Xylocaine MPF 20 mg/mL 65219-0814-05 | Fresenius | 25 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 70756-0643-10 | Lifestar | 10 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 71351-0023-10 | Brookfield | 10 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 71872-7144-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 71872-7161-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 71872-7357-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 73293-0003-02 | Huons | 10 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 76420-0078-05 | Asclemed | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 76420-0540-05 | Asclemed | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 83854-0012-25 | Anthea | 25 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 84549-0005-25 | ProPharma | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 84549-0066-05 | ProPharma | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 84549-0323-05 | ProPharma | 5 ml | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 84769-0002-02 | Novagenix | 10 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 76420-0079-01 | Asclemed | 2 ml | — | — | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 55150-0164-02 | Eugia | 10 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 00409-4282-01 | Hospira, | 5 cellos | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 55150-0160-72 | Eugia | 10 ampules | — | — | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 70756-0642-10 | Lifestar | 10 vials | — | AP | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 00781-3539-35 | Sandoz | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lidocaine Hydrochloride Injection is indicated in adult and pediatric patients for the production of local or regional anesthesia or analgesia for surgery, dental, and oral surgery procedures, diagnostic and therapeutic procedures, and for obstetrical procedures. Specific concentrations and presentations of Lidocaine Hydrochloride Injection are recommended for each type of block indicated to produce local or regional anesthesia or analgesia [see Dosage and Administration (2.2) ] . Lidocaine Hydrochloride Injection contains lidocaine, an amide local anesthetic.
Lidocaine Hydrochloride Injection is indicated in adult and pediatric patients for the production of local or regional anesthesia or analgesia for surgery, dental, and oral surgery procedures, diagnostic and therapeutic procedures, and for obstetrical procedures. For each type of block indicated to produce local or regional anesthesia or analgesia, specific concentrations and presentations are recommended. ( 1 , 2.2 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION See Full Prescribing Information for recommended dosages and administration information for adult and pediatric patients. ( 2 )
2.1Important Dosage and Administration Information • Lidocaine Hydrochloride Injection is not recommended for intrathecal use. • Discard unused portions of solution not containing preservatives, i.e., those supplied in single-dose vials, following initial use. • Visually inspect this product for particulate matter and discoloration prior to administration whenever solution and container permit. Lidocaine Hydrochloride Injection is a clear, colorless solution. Do not administer solutions which are discolored or contain particulate matter. • Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever the solution and container permit.
Solutions which are discolored (e.g., pinkish or darker than slightly yellow) or which contain particulate matter or precipitate should not be administered. • Mixing or the prior or intercurrent use of any other local anesthetic with Lidocaine Hydrochloride Injection is not recommended because of insufficient data on the clinical use of such mixtures. Administration Precautions • Lidocaine Hydrochloride Injection is to be administered in carefully adjusted dosages by or under the supervision of experienced clinicians who are well versed in the diagnosis and management of dose‑related toxicity and other acute emergencies which might arise from the block to be employed. • Use Lidocaine Hydrochloride Injection only if the following are immediately available: oxygen, cardiopulmonary resuscitative equipment and drugs, and the personnel resources needed for proper management of toxic reactions and related emergencies [see Warnings and Precautions (5.1) , Adverse Reactions (6) , Overdosage (10) ] . • The toxic effects of local anesthetics are additive.
Monitor for neurologic and cardiovascular effects related to local anesthetic systemic toxicity when additional local anesthetics are administered with Lidocaine Hydrochloride Injection [see Warnings and Precautions (5.1) , Drug Interactions (7.1) , Overdosage (10) ] . • Aspirate for blood or cerebrospinal fluid (where applicable) prior to injecting Lidocaine Hydrochloride Injection, both the initial dose and all subsequent doses, to avoid intravascular or intrathecal injection. However, a negative aspiration for blood or cerebrospinal fluid does not ensure against an intravascular or intrathecal injection [see Warnings and Precautions (5.7) ] . • Avoid rapid injection of a large volume of Lidocaine Hydrochloride Injection and use fractional (incremental) doses when feasible. • During major regional nerve blocks, such as those of the brachial plexus or lower extremity, the patient should have an indwelling intravenous catheter to assure adequate intravenous access.
The lowest dosage of Lidocaine Hydrochloride Injection that results in effective anesthesia should be used to avoid high plasma levels and serious adverse reactions. • Perform careful and constant monitoring of cardiovascular and respiratory (adequacy of oxygenation and ventilation) vital signs and the patient’s level of consciousness after each local anesthetic injection. • Use Lidocaine Hydrochloride Injection in carefully restricted quantities in areas of the body supplied by end arteries or having otherwise compromised blood supply such as digits, nose, external ear, or penis [see Warnings and Precautions (5.10) ] .
2.2Recommended Concentrations and Dosages of Lidocaine Hydrochloride Injection in Adults The dosage of Lidocaine Hydrochloride Injection administered varies with the anesthetic procedure, the area to be anesthetized, the vascularity of the tissues, the number of neuronal segments to be blocked, the depth of anesthesia and degree of muscle relaxation required, the duration of anesthesia desired, individual tolerance, and the physical condition of the patient.… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lidocaine Hydrochloride Injection, USP is a clear, colorless solution available as: • 2% (100 mg per 5 mL) (20 mg per mL), 5 mL single-dose vials • Lidocaine Hydrochloride Injection, USP single-dose vials: 2% ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lidocaine Hydrochloride Injection is contraindicated in patients with a known hypersensitivity to lidocaine or to any local anesthetics of the amide-type or to other components of Lidocaine Hydrochloride Injection. • Known hypersensitivity to any local anesthetic agent of the amide-type or to other components of Lidocaine Hydrochloride Injection. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Dose-Related Toxicity : Monitor cardiovascular and respiratory vital signs and patient’s state of consciousness after injection of Lidocaine Hydrochloride Injection. ( 5.1 ) • Methemoglobinemia : Cases of methemoglobinemia have been reported in association with local anesthetics use. See full prescribing information for more details on managing these risks.
( 5.2 ) • Chondrolysis with Intra-Articular Infusion : Avoid intra-articular infusions as there have been post-marketing reports of chondrolysis in patients receiving such infusion. ( 5.4 ) • Risk of Systemic Toxicities with Unintended Intravascular or Intrathecal Injection : Unintended intravascular or intrathecal injection may be associated with systemic toxicities, including CNS or cardiorespiratory depression and coma, progression ultimately to respiratory arrest. Aspirate for blood or cerebrospinal fluid (where applicable) prior to each dose and consider using a test dose of a lidocaine solution containing epinephrine.
( 5.7 )
5.1Dose-Related Toxicity The safety and effectiveness of Lidocaine Hydrochloride Injection depend on proper dosage, correct technique, adequate precautions, and readiness for emergencies. Careful and constant monitoring of cardiovascular and respiratory (adequacy of ventilation) vital signs and the patient’s state of consciousness should be performed after injection of Lidocaine Hydrochloride Injection solutions. Possible early warning signs of central nervous system (CNS) toxicity are restlessness, anxiety, incoherent speech, lightheadedness, numbness and tingling of the mouth and lips, metallic taste, tinnitus, dizziness, blurred vision, tremors, twitching, CNS depression, or drowsiness.
Delay in proper management of dose-related toxicity, underventilation from any cause and/or altered sensitivity may lead to the development of acidosis, cardiac arrest, and, possibly, death. During major regional nerve blocks, such as those of the brachial plexus or lower extremity, the patient should have an indwelling intravenous catheter to assure adequate intravenous access. Use the lowest dosage of Lidocaine Hydrochloride Injection that results in effective anesthesia to avoid high plasma levels and serious adverse effects.
Avoid rapid injection of a large volume of Lidocaine Hydrochloride Injection solution and administer fractional (incremental) doses when feasible. Injection of repeated doses of Lidocaine Hydrochloride Injection may cause significant increases in plasma levels with each repeated dose due to slow accumulation of the drug or its metabolites, or to slow metabolic degradation. Tolerance to elevated blood levels varies with the status of the patient.
Debilitated, elderly patients and acutely ill patients should be given reduced doses commensurate with their age and physical status.
5.2Methemoglobinemia Cases of methemoglobinemia have been reported in association with local anesthetic use. Although all patients are at risk for methemoglobinemia, patients with glucose-6-phosphate dehydrogenase deficiency, congenital or idiopathic methemoglobinemia, cardiac or pulmonary compromise, infants under 6 months of age, and concurrent exposure to oxidizing agents or their metabolites are more susceptible to developing clinical manifestations of the condition [see Drug Interactions (7.5) ] . If local anesthetics must be used in these patients, close monitoring for symptoms and signs of methemoglobinemia is recommended.
Signs of methemoglobinemia may occur immediately or may be delayed some hours after exposure and are characterized by a cyanotic skin discoloration and abnormal coloration of the blood. Methemoglobin levels may continue to rise; therefore, immediate treatment is required to avert more serious central nervous system and cardiovascular adverse effects, including seizures, coma, arrhythmias, and death. Discontinue Lidocaine Hydrochloride Injection and any other oxidizing agents.
Depending on the severity of the… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions have been reported and described in the Warnings and Precautions section of the labeling: • Dose-Related Toxicity [see Warnings and Precautions (5.1) ] • Methemoglobinemia [see Warnings and Precautions (5.2) ] • Chondrolysis with Intra-Articular Infusion [see Warnings and Precautions (5.4) ] • Severe, Persistent Hypertension, Cerebrovascular Accidents, and Bradycardia Due to Drug Interactions [see Warnings and Precautions (5.5) ] • Allergic-Type Reactions [see Warnings and Precautions (5.6) ] • Systemic Toxicities with Unintended Intravascular or Intrathecal Injection [see Warnings and Precautions (5.7) ] • Respiratory Arrest Following Retrobulbar Block [see Warnings and Precautions (5.14) ] The following adverse reactions from voluntary reports or clinical studies have been reported with lidocaine or lidocaine and epinephrine.
Because many of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Adverse reactions to Lidocaine Hydrochloride Injection are characteristic of those associated with other amide‑type local anesthetics. A major cause of adverse reactions to this group of drugs is excessive plasma levels, which may be due to overdosage, unintentional intravascular injection, or slow metabolic degradation.
The most commonly encountered acute adverse reactions that demand immediate counter measures were related to the CNS and the cardiovascular system. These adverse reactions were generally dose-related and due to high plasma levels which may have resulted from overdosage, rapid absorption from the injection site, diminished tolerance, or from unintentional intravascular injection of the local anesthetic solution. In addition to systemic dose-related toxicity, unintentional intrathecal injection of drug during the intended performance of caudal or lumbar epidural block or nerve blocks near the vertebral column (especially in the head and neck region) has resulted in underventilation or apnea (“Total or High Spinal”).
Also, hypertension due to loss of sympathetic tone and respiratory paralysis or underventilation due to cephalad extension of the motor level of anesthesia have occurred. This has led to secondary cardiac arrest when untreated. When used for dental injections, paresthesia of the lips, tongue, and oral tissues have been reported.
Persistent paresthesia lasting weeks to months and, in some instances, lasting greater than one year, have also been reported. Nervous System Disorders Adverse reactions were characterized by excitation and/or depression of the central nervous system and included lightheadedness, nervousness, apprehension, euphoria, confusion, dizziness, drowsiness, tinnitus, blurred or double vision, vomiting, sensations of heat, cold or numbness, twitching, tremors, convulsions, unconsciousness, respiratory depression and arrest. The incidences of adverse reactions associated with the use of local anesthetics may be related to the total dose of local anesthetic administered and are also dependent upon the particular drug used, the route of administration and the physical status of the patient.
In a prospective review of 10,440 patients who received lidocaine hydrochloride for spinal anesthesia, the incidences of adverse reactions were reported to be about 3 percent each for positional headaches, hypotension and backache; 2 percent for shivering; and less than 1 percent each for peripheral nerve symptoms, nausea, respiratory inadequacy and double vision. Persistent motor, sensory and/or autonomic (sphincter control) deficit of some lower spinal segments with slow recovery (several months) or incomplete recovery have been reported in rare instances when caudal or lumbar epidural block has been attempted.
Backache and headache have also been noted following use of these anesthetic procedur… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Local Anesthetics : The toxic effects of local anesthetics are additive. Monitor for neurologic and cardiovascular effects when additional local anesthetics are administered. ( 7.1 ) • Monoamine Oxidase Inhibitors and Tricyclic Antidepressants : Administration of lidocaine solutions containing epinephrine to patients receiving monoamine oxidase inhibitors or tricyclic antidepressants may produce severe, prolonged hypertension.
Concurrent use of these agents should generally be avoided. ( 5.5 , 7.2 ) • Ergot-type Oxytocic drugs : Concurrent administration of lidocaine solutions containing epinephrine and ergot-type oxytocic drugs may cause severe, persistent hypertension or cerebrovascular accidents. ( 5.5 , 7.3 ) • Nonselective Beta-Adrenergic Antagonists : Administration of lidocaine solutions containing epinephrine in patients receiving nonselective beta-adrenergic antagonist may cause severe hypertension and bradycardia.
Concurrent use of these agents should generally be avoided. ( 5.5 , 7.4 ) • Drugs Associated with Methemoglobinemia : Patients are at increased risk of developing methemoglobinemia when concurrently exposed to nitrates, nitrites, local anesthetics, antineoplastic agents, antibiotics, antimalarials, anticonvulsants and other drugs. ( 7.5 ) • Potent Inhalation Anesthetics : Serious dose-related cardiac arrhythmias may occur if lidocaine solutions containing epinephrine are used in patients during or following the administration of potent inhalation anesthetics.
( 5.11 , 7.6 )
7.1Local Anesthetics The toxic effects of local anesthetics are additive. If coadministration of other local anesthetics with Lidocaine Hydrochloride Injection cannot be avoided, monitor patients for neurologic and cardiovascular effects related to local anesthetic systemic toxicity [see Warnings and Precautions (5.1) ] .
7.2Monoamine Oxidase Inhibitors and Tricyclic Antidepressants The administration of lidocaine solutions containing epinephrine to patients receiving monoamine oxidase inhibitors or tricyclic antidepressants may produce severe, prolonged hypertension. Concurrent use of these agents should generally be avoided. In situations when concurrent therapy is necessary, careful monitoring of the patient’s hemodynamic status is essential [see Warnings and Precautions (5.5) ] .
7.3Ergot-Type Oxytocic Drugs Concurrent administration of vasopressor drugs (for the treatment of hypotension related to obstetric blocks) and ergot-type oxytocic drugs may cause severe, persistent hypertension or cerebrovascular accidents. Avoid use of lidocaine solutions containing epinephrine concomitantly with ergot-type oxytocic drugs [see Warnings and Precautions (5.5) ] .
7.4Nonselective Beta-Adrenergic Antagonists Administration of lidocaine solutions containing epinephrine in patients receiving nonselective beta-adrenergic antagonists may cause severe hypertension and bradycardia. Concurrent use of these agents should generally be avoided. In situations when concurrent therapy is necessary, careful monitoring of the patient's blood pressure and heart rate is essential [see Warnings and Precautions (5.5) ] .
7.5Drugs Associated with Methemoglobinemia Patients that are administered local anesthetics may be at increased risk of developing methemoglobinemia when concurrently exposed to the following oxidizing agents: Class Examples Nitrates/Nitrites nitroglycerin, nitroprusside, nitric oxide, nitrous oxide Local anesthetics articaine, benzocaine, bupivacaine, lidocaine, mepivacaine, prilocaine, procaine, ropivacaine, tetracaine Antineoplastic agents cyclophosphamide, flutamide, rasburicase, ifosfamide, hydroxyurea Antibiotics dapsone, sulfonamides, nitrofurantoin, para-aminosalicylic acid Antimalarials chloroquine, primaquine Anticonvulsants phenytoin, sodium valproate, phenobarbital Other drugs acetaminophen, metoclopramide, quinine, sulfasalazine
7.6Potent Inhalation Anesthetics Serious dose-related cardiac arrhythmias may… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Geriatric Use : Elderly patients should be given reduced doses commensurate with their age and physical condition. ( 8.5 ) • Hepatic Impairment : Consider reduced dosing and increased monitoring for local anesthetic systemic toxicity in patients with hepatic impairment. ( 8.6 )
8.1Pregnancy Risk Summary Available published data and decades of clinical use with lidocaine hydrochloride in pregnant women have not identified any drug-associated risk for major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Local anesthetics may cause varying degrees of toxicity to the mother and fetus and adverse reactions include alterations of the central nervous system, peripheral vascular tone and cardiac function (see Clinical Considerations ) . In a published animal reproduction study, pregnant rats administered lidocaine by continuous subcutaneous infusion at a dose approximately 9.6 times the maximum recommended human dose (MRHD) of 500 mg of lidocaine hydrochloride during the period of organogenesis resulted in lower fetal body weights [see Data ] .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the United States general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Maternal Adverse Reactions Maternal hypotension has resulted from regional anesthesia. Local anesthetics produce vasodilation by blocking sympathetic nerves. Therefore, during treatment of systemic toxicity, maternal hypotension or fetal bradycardia following regional block, the parturient should be maintained in the left lateral decubitus position if possible or manual displacement of the uterus off the great vessels be accomplished.
Elevating the patient’s legs will also help prevent decreases in blood pressure. The fetal heart rate also should be monitored continuously, and electronic fetal monitoring is highly advisable. Labor or Delivery Local anesthetics rapidly cross the placenta, and when used for epidural, paracervical, pudendal or caudal block anesthesia, can cause varying degrees of maternal, fetal and neonatal toxicity [see Clinical Pharmacology (12.3) ] .
The incidence and degree of toxicity depend upon the procedure performed, the type and amount of drug used, and the technique of drug administration. Adverse reactions in the parturient, fetus and neonate involve alterations of the central nervous system, peripheral vascular tone and cardiac function. However, dosage recommendations for spinal anesthesia are much lower than dosage recommendations for other major blocks.
Spinal anesthesia may alter the forces of parturition through changes in uterine contractility or maternal expulsive efforts. Spinal anesthesia has also been reported to prolong the second stage of labor by removing the parturient’s reflex urge to bear down or by interfering with motor function. The use of obstetrical anesthesia may increase the need for forceps assistance.
The use of some local anesthetic drug products during labor and delivery may be followed by diminished muscle strength and tone for the first day or two of life. Data Animal Data Reproduction studies have been performed in rats at doses up to 6.6 times the human dose and have revealed no evidence of harm to the fetus caused by lidocaine hydrochloride. In a published study, lidocaine administered to pregnant rats by continuous subcutaneous infusion during the period of organogenesis at 100, 250, and 500 mg/kg/day, did not produce any structural abnormalities, but did result in lower fetal weights at 500 mg/kg/day dose (approximately 9.6 times the maximum recommended human dose [MRHD] of 500 mg lidocaine on a mg/m 2 basis) in the absence of maternal toxicity.
8.2Lactation Risk Summa… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available published data and decades of clinical use with lidocaine hydrochloride in pregnant women have not identified any drug-associated risk for major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Local anesthetics may cause varying degrees of toxicity to the mother and fetus and adverse reactions include alterations of the central nervous system, peripheral vascular tone and cardiac function (see Clinical Considerations ) . In a published animal reproduction study, pregnant rats administered lidocaine by continuous subcutaneous infusion at a dose approximately 9.6 times the maximum recommended human dose (MRHD) of 500 mg of lidocaine hydrochloride during the period of organogenesis resulted in lower fetal body weights [see Data ] .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the United States general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Maternal Adverse Reactions Maternal hypotension has resulted from regional anesthesia. Local anesthetics produce vasodilation by blocking sympathetic nerves. Therefore, during treatment of systemic toxicity, maternal hypotension or fetal bradycardia following regional block, the parturient should be maintained in the left lateral decubitus position if possible or manual displacement of the uterus off the great vessels be accomplished.
Elevating the patient’s legs will also help prevent decreases in blood pressure. The fetal heart rate also should be monitored continuously, and electronic fetal monitoring is highly advisable. Labor or Delivery Local anesthetics rapidly cross the placenta, and when used for epidural, paracervical, pudendal or caudal block anesthesia, can cause varying degrees of maternal, fetal and neonatal toxicity [see Clinical Pharmacology (12.3) ] .
The incidence and degree of toxicity depend upon the procedure performed, the type and amount of drug used, and the technique of drug administration. Adverse reactions in the parturient, fetus and neonate involve alterations of the central nervous system, peripheral vascular tone and cardiac function. However, dosage recommendations for spinal anesthesia are much lower than dosage recommendations for other major blocks.
Spinal anesthesia may alter the forces of parturition through changes in uterine contractility or maternal expulsive efforts. Spinal anesthesia has also been reported to prolong the second stage of labor by removing the parturient’s reflex urge to bear down or by interfering with motor function. The use of obstetrical anesthesia may increase the need for forceps assistance.
The use of some local anesthetic drug products during labor and delivery may be followed by diminished muscle strength and tone for the first day or two of life. Data Animal Data Reproduction studies have been performed in rats at doses up to 6.6 times the human dose and have revealed no evidence of harm to the fetus caused by lidocaine hydrochloride. In a published study, lidocaine administered to pregnant rats by continuous subcutaneous infusion during the period of organogenesis at 100, 250, and 500 mg/kg/day, did not produce any structural abnormalities, but did result in lower fetal weights at 500 mg/kg/day dose (approximately 9.6 times the maximum recommended human dose [MRHD] of 500 mg lidocaine on a mg/m 2 basis) in the absence of maternal toxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use Dosages in children should be reduced, commensurate with age, body weight and physical condition [see Dosage and Administration (2.6) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Elderly patients should be given reduced doses commensurate with their age and physical condition [see Dosage and Administration (2.6) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute emergencies from local anesthetics are generally related to high plasma levels encountered during therapeutic use of local anesthetics or to unintended subarachnoid injection of local anesthetic solution [see Warnings and Precautions (5.1) , Adverse Reactions (6) ] . Management The first consideration is prevention, best accomplished by careful and constant monitoring of cardiovascular and respiratory vital signs and the patient’s state of consciousness after each local anesthetic injection.
At the first sign of change, oxygen should be administered. The first step in the management of convulsions, as well as underventilation or apnea due to unintended subarachnoid injection of drug solution, consists of immediate attention to the maintenance of a patent airway and assisted or controlled ventilation with oxygen and a delivery system capable of permitting immediate positive airway pressure by mask. Immediately after the institution of these ventilatory measures, the adequacy of the circulation should be evaluated, keeping in mind that drugs used to treat convulsions sometimes depress the circulation when administered intravenously.
Should convulsions persist despite adequate respiratory support, and if the status of the circulation permits, a benzodiazepine (such as diazepam) may be administered intravenously. The clinician should be familiar, prior to the use of local anesthetics, with these anticonvulsant drugs. Supportive treatment of circulatory depression may require administration of intravenous fluids and, when appropriate, a vasopressor as directed by the clinical situation (e.g., ephedrine).
If not treated immediately, both convulsions and cardiovascular depression can result in hypoxia, acidosis, bradycardia, arrhythmias and cardiac arrest. Underventilation or apnea due to unintentional subarachnoid injection of local anesthetic solution may produce these same signs and also lead to cardiac arrest if ventilatory support is not instituted. If cardiac arrest should occur, standard cardiopulmonary resuscitative measures should be instituted.
Endotracheal intubation, employing drugs and techniques familiar to the clinician, may be indicated, after initial administration of oxygen by mask, if difficulty is encountered in the maintenance of a patent airway or if prolonged ventilatory support (assisted or controlled) is indicated. Dialysis is of negligible value in the treatment of acute overdosage with lidocaine hydrochloride.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lidocaine hydrochloride stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses thereby effecting local anesthetic action.
12.2Pharmacodynamics Excessive blood levels may cause changes in cardiac output, total peripheral resistance, and mean arterial pressure. With central neural blockade these changes may be attributable to block of autonomic fibers, a direct depressant effect of the local anesthetic agent on various components of the cardiovascular system, and/or the beta-adrenergic receptor stimulating action of epinephrine when present. The net effect is normally a modest hypotension when the recommended dosages are not exceeded.
Factors such as acidosis and the use of CNS stimulants and depressants affect the CNS levels of lidocaine hydrochloride required to produce overt systemic effects. Objective adverse manifestations become increasingly apparent with increasing venous plasma levels above 6 mcg free base per mL.
12.3Pharmacokinetics Systemic plasma levels of lidocaine following Lidocaine Hydrochloride Injection do not correlate with local efficacy. Absorption Information derived from diverse formulations, concentrations and usages reveals that lidocaine hydrochloride is completely absorbed following parenteral administration, its rate of absorption depending, for example, upon various factors such as the site of administration and the presence or absence of a vasoconstrictor agent. Except for intravascular administration, the highest blood levels are obtained following intercostal nerve block and the lowest after subcutaneous administration.
Distribution The plasma binding of lidocaine hydrochloride is dependent on drug concentration, and the fraction bound decreases with increasing concentration. At concentrations of 1 to 4 mcg of free base per mL 60 to 80 percent of lidocaine hydrochloride is protein bound. Binding is also dependent on the plasma concentration of the alpha-1‑acid glycoprotein.
Lidocaine hydrochloride crosses the blood-brain and placental barriers, presumably by passive diffusion. Elimination The elimination half-life of lidocaine hydrochloride following an intravenous bolus injection is typically 1.5 to 2 hours. Metabolism Lidocaine hydrochloride is metabolized rapidly by the liver, and biotransformation includes oxidative N‑dealkylation, ring hydroxylation, cleavage of the amide linkage, and conjugation.
N-dealkylation, a major pathway of biotransformation, yields the metabolites monoethylglycinexylidide and glycinexylidide. The pharmacological/toxicological actions of these metabolites are similar to, but less potent than, those of lidocaine hydrochloride. Excretion Approximately 90% of lidocaine hydrochloride administered is excreted in the form of various metabolites, and less than 10% is excreted unchanged by the kidneys.
The primary metabolite in urine is a conjugate of 4‑hydroxy-2,6-dimethylaniline. Specific Populations Patients with Hepatic Impairment Because of the rapid rate at which lidocaine hydrochloride is metabolized, any condition that affects liver function may alter lidocaine hydrochloride kinetics. The half-life may be prolonged two-fold or more in patients with liver dysfunction.
Patients with Renal Impairment Renal dysfunction does not affect lidocaine hydrochloride kinetics but may increase the accumulation of metabolites.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lidocaine hydrochloride stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses thereby effecting local anesthetic action.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Discard unused portion after initial use. 2% Lidocaine Hydrochloride Injection, USP. This product is clear and colorless. Unit of Sale Concentration NDC 0409-2066-05 Carton of 10 Single-dose Vials 2% 100 mg/5 mL (20 mg/mL)
📋 Description ▾
11 DESCRIPTION Lidocaine Hydrochloride Injection, USP contains lidocaine hydrochloride, an amide local anesthetic, as the active pharmaceutical ingredient. The route of administration for Lidocaine Hydrochloride Injection is by injection, for infiltration, nerve block, epidural and caudal use. Lidocaine hydrochloride is chemically designated as acetamide, 2-(diethylamino)-N-(2,6-dimethylphenyl)-, monohydrochloride monohydrate and has the molecular weight of 288.8 g/mol.
Lidocaine hydrochloride molecular formula is C 14 H 22 N 2 O • HCl•H 2 O, and has the following structural formula: Each single-dose vial contains Lidocaine Hydrochloride Injection, USP, which is a sterile, nonpyrogenic, clear, colorless aqueous solution intended for parenteral administration [see Indications and Usage (1) ] for special uses. Each mL contains 20 mg lidocaine hydrochloride and 6 mg sodium chloride, in Water for Injection. Sodium hydroxide and/or hydrochloric acid may be used to adjust pH between 5.0 and 7.0.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Allergic-Type Reactions Assess if the patient has had allergic-type reactions to amide-type local anesthetics or to other formulation ingredients [see Contraindications (4) , Warnings and Precautions (5.6) , Adverse Reactions (6) ] .
17.2Temporary Loss of Sensation and Motor Activity After Caudal or Epidural Anesthesia When appropriate, patients should be informed in advance that they may experience temporary loss of sensation and motor activity, usually in the lower half of the body, following proper administration of caudal or epidural anesthesia. Instructions After Dental Injection of Lidocaine Hydrochloride Injection Advise patients receiving dental injections of Lidocaine Hydrochloride Injection not to chew solid foods or to test the anesthetized area by biting or probing until anesthesia has worn off (up to 7 hours) [see Warnings and Precautions (5.15) ] .
17.3Methemoglobinemia Inform patients that use of local anesthetics may cause methemoglobinemia, a serious condition that must be treated promptly. Advise patients or caregivers to stop use and seek immediate medical attention if they or someone in their care experience the following signs or symptoms: pale, gray, or blue colored skin (cyanosis); headache; rapid heart rate; shortness of breath; lightheadedness; or fatigue [see Warnings and Precautions (5.2) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Systemic plasma levels of lidocaine following Lidocaine Hydrochloride Injection do not correlate with local efficacy. Absorption Information derived from diverse formulations, concentrations and usages reveals that lidocaine hydrochloride is completely absorbed following parenteral administration, its rate of absorption depending, for example, upon various factors such as the site of administration and the presence or absence of a vasoconstrictor agent. Except for intravascular administration, the highest blood levels are obtained following intercostal nerve block and the lowest after subcutaneous administration.
Distribution The plasma binding of lidocaine hydrochloride is dependent on drug concentration, and the fraction bound decreases with increasing concentration. At concentrations of 1 to 4 mcg of free base per mL 60 to 80 percent of lidocaine hydrochloride is protein bound. Binding is also dependent on the plasma concentration of the alpha-1‑acid glycoprotein.
Lidocaine hydrochloride crosses the blood-brain and placental barriers, presumably by passive diffusion. Elimination The elimination half-life of lidocaine hydrochloride following an intravenous bolus injection is typically 1.5 to 2 hours. Metabolism Lidocaine hydrochloride is metabolized rapidly by the liver, and biotransformation includes oxidative N‑dealkylation, ring hydroxylation, cleavage of the amide linkage, and conjugation.
N-dealkylation, a major pathway of biotransformation, yields the metabolites monoethylglycinexylidide and glycinexylidide. The pharmacological/toxicological actions of these metabolites are similar to, but less potent than, those of lidocaine hydrochloride. Excretion Approximately 90% of lidocaine hydrochloride administered is excreted in the form of various metabolites, and less than 10% is excreted unchanged by the kidneys.
The primary metabolite in urine is a conjugate of 4‑hydroxy-2,6-dimethylaniline. Specific Populations Patients with Hepatic Impairment Because of the rapid rate at which lidocaine hydrochloride is metabolized, any condition that affects liver function may alter lidocaine hydrochloride kinetics. The half-life may be prolonged two-fold or more in patients with liver dysfunction.
Patients with Renal Impairment Renal dysfunction does not affect lidocaine hydrochloride kinetics but may increase the accumulation of metabolites.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Excessive blood levels may cause changes in cardiac output, total peripheral resistance, and mean arterial pressure. With central neural blockade these changes may be attributable to block of autonomic fibers, a direct depressant effect of the local anesthetic agent on various components of the cardiovascular system, and/or the beta-adrenergic receptor stimulating action of epinephrine when present. The net effect is normally a modest hypotension when the recommended dosages are not exceeded.
Factors such as acidosis and the use of CNS stimulants and depressants affect the CNS levels of lidocaine hydrochloride required to produce overt systemic effects. Objective adverse manifestations become increasingly apparent with increasing venous plasma levels above 6 mcg free base per mL.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Studies of lidocaine hydrochloride in animals to evaluate the carcinogenic potential have not been conducted. Mutagenesis Studies of lidocaine hydrochloride in animals to evaluate the mutagenic potential have not been conducted. Impairment of Fertility In a published study, female Sprague-Dawley rats were treated subcutaneously with lidocaine via osmotic pumps starting two weeks prior to mating, and reproductive effects were assessed.
Rats dosed up to the high dose of 500 mg/kg/day (approximately 45 times the MRDD on a mg/m 2 basis) showed no effects on copulatory rate, pregnancy rate, numbers of corpora lutea, or implantations.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Studies of lidocaine hydrochloride in animals to evaluate the carcinogenic potential have not been conducted. Mutagenesis Studies of lidocaine hydrochloride in animals to evaluate the mutagenic potential have not been conducted. Impairment of Fertility In a published study, female Sprague-Dawley rats were treated subcutaneously with lidocaine via osmotic pumps starting two weeks prior to mating, and reproductive effects were assessed.
Rats dosed up to the high dose of 500 mg/kg/day (approximately 45 times the MRDD on a mg/m 2 basis) showed no effects on copulatory rate, pregnancy rate, numbers of corpora lutea, or implantations.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 5 mL Vial Label 5 mL Single-Dose Vial NDC 0409-2066-10 Preservative-Free Rx only 2% Lidocaine HCl Injection, USP 100 mg/5 mL (20 mg/mL) For Infiltration and Nerve Block including Epidural and Caudal. Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Discard unused portion. Distributed by Hospira, Inc., Lake Forest, IL 60045 USA PRINCIPAL DISPLAY PANEL - 5 mL Vial Label
PRINCIPAL DISPLAY PANEL - 5 mL Vial Carton 5 mL 10 Single-Dose Vials Rx only NDC 0409-2066-05 Contains 10 of NDC 0409-2066-10 Preservative-Free 2% Lidocaine HCl Injection, USP 100 mg/5 mL (20 mg/mL) For Infiltration and Nerve Block including Epidural and Caudal. Hospira PRINCIPAL DISPLAY PANEL - 5 mL Vial Carton