
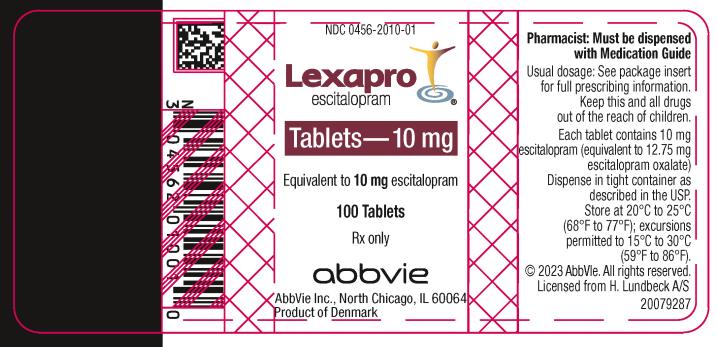
Lexapro ESCITALOPRAM 10 mg Tablet, Film Coated
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin Reuptake Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Antidepressants like escitalopram don't work overnight. Most people don't notice a real difference in mood or anxiety for several weeks, and it can take a few months to feel the fu...
- How long will it take before I start feeling better on escitalopram?
- Please don't stop on your own, even if you're feeling great — that's actually a sign the medication is working. Stopping escitalopram suddenly can cause uncomfortable withdrawal-li...
- Is it okay to stop taking escitalopram if I feel better?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Escitalopram — tap one for details:
Escitalopram may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| escitalopram 10 mg 00904-6426-61 | Major | 100 tablets | $0.039 | AB | Availability likely | — |
| escitalopram 10 mg 13668-0136-01 | Torrent | 100 tablets | $0.039 | AB | Availability likely | — |
| escitalopram 10 mg 16571-0756-01 | Rising | 100 tablets | $0.039 | AB | Availability likely | — |
| Escitalopram 10 mg 43547-0281-10 | SOLCO | 100 tablets | $0.039 | AB | Availability likely | — |
| Escitalopram 10 mg 65862-0374-01 | Aurobindo | 100 tablets | $0.039 | AB | Availability likely | — |
| Escitalopram 10 mg 68001-0592-00 | BluePoint | 100 tablets | $0.039 | AB | Availability likely | — |
| Escitalopram 10 mg 68084-0617-01 | American | 1 tablet | $0.039 | AB | Availability likely | — |
| Escitalopram Oxalate 10 mg 68645-0519-54 | Legacy | 30 tablets | $0.039 | AB | Availability likely | — |
| Escitalopram Oxalate 10 mg/21 72603-0150-01 | NorthStar | 1000 tablets | $0.039 | AB | Availability likely | — |
| escitalopram oxalate 10 mg 82009-0036-10 | Quallent | 1000 tablets | $0.039 | AB | Availability likely | — |
| Escitalopram 10 mg 59746-0280-01 | Jubilant | 100 tablets | $0.046 | AB | FDA listed | — |
| Escitalopram 10 mg 16729-0169-01 | Accord | 100 tablets | $0.048 | AB | FDA listed | — |
| Escitalopram Oxalate 10 mg/21 33342-0037-11 | Macleods | 100 tablets | $0.048 | AB | FDA listed | — |
| Lexapro 10 mgthis 00456-2010-63 | Allergan, | 10 tablets | — | AB | Discontinued | — |
| Escitalopram 10 mg 00615-8476-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 42708-0077-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 42708-0155-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| escitalopram oxalate 10 mg 43063-0761-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 10 mg 43602-0474-10 | Ascent | 1000 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 50090-4915-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 50090-6190-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 50090-6191-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 50090-6496-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 51655-0149-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 51655-0277-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 51655-0449-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 10 mg 53746-0020-05 | Amneal | 500 tablets | — | AB | FDA listed | — |
| escitalopram 10 mg 55154-6893-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 55700-0847-30 | Quality | 30 tablets | — | AB | Discontinued | — |
| escitalopram 10 mg 60760-0895-30 | St. | 30 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 10 mg 65162-0020-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 67046-0355-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| escitalopram oxalate 10 mg 68788-8371-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| escitalopram 10 mg 68788-8569-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 10 mg 69097-0848-02 | Cipla | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 70518-2472-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| escitalopram 10 mg 70518-3923-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 70518-4567-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 71205-0168-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 71205-0344-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 71205-0782-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| escitalopram oxalate 10 mg 71205-0792-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| escitalopram oxalate 10 mg 71335-0322-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 71335-1030-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Escitalopram 10 mg 71335-1187-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| escitalopram 10 mg 71335-2903-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| escitalopram 10 mg 71335-3094-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| escitalopram 10 mg 72162-2241-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 72189-0424-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 72789-0194-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Escitalopram oxalate 10 mg 76282-0250-01 | Exelan | 100 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 76420-0722-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 80425-0320-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 10 mg 80425-0375-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| escitalopram oxalate 10 mg 82982-0065-60 | Pharmasource | 60 tablets | — | AB | Discontinued | — |
| Escitalopram Oxalate 10 mg 70518-4703-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | May 12, 2026 |
| NPP | New Patient Population | May 12, 2026 |
| NPP | New Patient Population | May 12, 2026 |
Is there a generic version of LEXAPRO 10 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00456-2010-01 | 100 TABLET, FILM COATED in 1 BOTTLE (0456-2010-01) | $15.42 / ea | $1,541.93 | 2002-08-14 | Active |
| 00456-2010-63 You're viewing this | 10 BLISTER PACK in 1 BOX, UNIT-DOSE (0456-2010-63) / 10 TABLET, FILM COATED in 1 BLISTER PACK (0456-2010-11) | — | — | 2002-08-14 | Discontinued by firm |
This pack shows little to no recent Medicaid volume — the 100 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 00456-2010-63?
What NDC number is used to bill for this package of Lexapro ESCITALOPRAM 10 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behavior s in pediatric and young adult patients in short-term studies . Closely monitor all antidepressant-treated patients for clinical worsening, and for emergence of suicidal thoughts and behaviors [see Warnings and Precautions ( 5.1 )] . Lexapro is not approved for use in pediatric patients less than 7 years of age [ s ee Use in Specific Populations ( 8.4 )] .
WARNING: SUICIDAL THOUGHTS AN D BEHAVIORS See full prescribing information for complete boxed warning. Increased risk of suicidal thoughts and behavior in pediatric and you ng adult patients taking antidepressants . Closely monitor all antidepressant-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors ( 5.1 ).
Lexapro is not approved for use in pediatric patients less than 7 years of age ( 8.4 ) .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lexapro is indicated for the treatment of: • major depressive disorder (MDD) in adults and pediatric patients 12 years of age and older. • generalized anxiety disorder (GAD) in adults and pediatric patients 7 years of age and older. Lexapro is a selective serotonin reuptake inhibitor (SSRI) indicated for the: treatment of major depressive disorder (MDD) in adults and pediatric patients 12 years of age and older ( 1 ) treatment of generalized anxiety disorder (GAD) in adults and pediatric patients 7 years and older ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Indication and Population Recommended Dosage MDD in Adults ( 2.1 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily MDD in Pediatric Patients 12 years and older ( 2.1 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily GAD in Adults ( 2.2 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily GAD in Pediatric Patients 7 years and older ( 2.2 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily No additional benefits were seen at 20 mg once daily ( 2.1 ) Administer once daily, morning or evening, with or without food ( 2.3 ) Elderly patients: recommended dosage is 10 mg once daily ( 2.4 ) Hepatic impairment: recommended dosage is 10 mg once daily ( 2.4 , 8.6 ) When discontinuing Lexapro, reduce dose gradually whenever possible ( 2.5 )
2.1Major Depressive Disorder Adults The recommended dosage of Lexapro in adults is 10 mg once daily. A fixed-dose trial of Lexapro demonstrated the effectiveness of both 10 mg and 20 mg of Lexapro, but failed to demonstrate a greater benefit of 20 mg over 10 mg [see Clinical Studies ( 14.1 )] . Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 1 week.
Pediatric Patients 12 years of age and older The recommended dosage of Lexapro in pediatric patients 12 years of age and older is 10 mg once daily. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 3 weeks.
2.2Generalized Anxiety Disorder Adults The recommended starting dosage of Lexapro in adults is 10 mg once daily. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 1 week. Pediatric Patients 7 years of age and older The recommended starting dosage of Lexapro for pediatric patients ages 7 years of age and older is 10 mg once daily.
Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 2 weeks.
2.3Administration Information Administer Lexapro orally once daily, in the morning or evening, with or without food. 2. 4 Screen for Bipolar Disorder Prior to Starting Lexapro Prior to initiating treatment with Lexapro or another antidepressant, screen patients for a personal family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions ( 5.5 )] .
2. 5 Recommended Dosage for Specific Populations The recommended dosage for most elderly patients and patients with hepatic impairment is 10 mg once daily [see Use in Specific Populations ( 8.5 , 8.6 )] . The recommended dosage for Lexapro in adults with a creatinine clearance less than 20 mL/minute has not been determined.
No dosage adjustment is necessary for patients with mild or moderate renal impairment [see Use in Specific Populations ( 8.7 )] . 2. 6 Discontinuation of Treatment with Lexapro Symptoms associated with discontinuation of Lexapro and other SSRIs and SNRIs have been reported [see Warnings and Precautions ( 5.3 )] .
Patients should be monitored for these symptoms when discontinuing treatment. A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, then resuming the previously prescribed dose may be considered.
Subsequently, the physician may continue decreasing the dose but at a more gradual rate. 2. 7 Switching Patients to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with Lexapro.
Conversely, at least 14 days should be al…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets 5 mg: White to off-white, round, non-scored, film-coated. Imprint "FL" on one side of the tablet and "5" on the other side. 10 mg: White to off-white, round, scored, film-coated.
Imprint on scored side with "F" on the left side and "L" on the right side. Imprint on the non-scored side with "10". 20 mg: White to off-white, round, scored, film-coated.
Imprint on scored side with "F" on the left side and "L" on the right side. Imprint on the non-scored side with "20". Oral Solution 1 mg/mL: Clear, colorless to opalescent liquid, peppermint flavor (not currently being marketed).
Tablets: 5 mg, 10 mg (scored), and 20 mg (scored) Oral solution: 1 mg per mL (not currently being marketed)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lexapro is contraindicated in patients: taking MAOIs with Lexapro or within 14 days of stopping treatment with Lexapro because of an increased risk of serotonin syndrome. The use of Lexapro within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated [see Dosage and Administration ( 2.7 ) and Warnings and Precautions ( 5.2 )] . Starting Lexapro in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome [ see Dosage and Administration ( 2.6 ) and Warnings and Precautions ( 5.2 ) ]. taking pimozide [see Drug Interactions ( 7 ) ] . with a hypersensitivity to escitalopram or citalopram or any of the inactive ingredients in Lexapro.
Do not use MAOIs intended to treat psychiatric disorders with Lexapro or within 14 days of stopping treatment with Lexapro. Do not use Lexapro within 14 days of stopping an MAOI intended to treat psychiatric disorders. In addition, do not start Lexapro in a patient who is being treated with linezolid or intravenous methylene blue ( 4 ) Concomitant use of pimozide ( 4 ) Known hypersensitivity to escitalopram or citalopram or any of the inactive ingredients ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome: Increased risk when co-administered with other serotonergic agents but also when taken alone. If it occurs, discontinue Lexapro and serotonergic agents and initiate supportive treatment ( 4 , 5.2 ) Discontinuation syndrome: When discontinuing Lexapro, reduce dosage gradually whenever possible, and monitor for discontinuation symptoms ( 5.3 ) Seizures: Use with caution in patients with a history of seizure ( 5.4 ) Activation of Mania/Hypomania: Screen patients for bipolar disorder ( 5.5 ) Hyponatremia: Can occur in association with syndrome of inappropriate antidiuretic hormone secretion ( 5.6 ) Increased Risk of Bleeding: Concomitant use of nonsteroidal anti-inflammatory drugs, aspirin, other antiplatelet drugs, warfarin and other drugs that affect coagulation may increase risk ( 5.7 ) Interference with Cognitive and Motor Performance: Use caution when operating machinery ( 5.8 ) Angle Closure Glaucoma: Angle closure glaucoma has occurred in patients with untreated anatomically narrow angles treated with antidepressants ( 5.9 ) Use in Patients with Concomitant Illness: Use caution in patients with diseases or conditions that produce altered metabolism or hemodynamic responses ( 5.10 ) Sexual Dysfunction: Lexapro may cause symptoms of sexual dysfunction ( 5.11 )
5.1Suicidal Thoughts and Behaviors in Adolescents and Young Adults In pooled analyses of placebo-controlled trials of antidepressant drugs (SSRIs and other antidepressant classes) that included approximately 77,000 adult patients and 4,500 pediatric patients, the incidence of suicidal thoughts and behaviors in the antidepressant-treated patients age 24 years and younger was greater than in placebo-treated patients. There was considerable variation in risk of suicidal thoughts and behaviors among drugs, but there was an increased risk identified in young patients for most drugs studied.
There were differences in absolute risk of suicidal thoughts and behaviors across the different indications, with the highest incidence in patients with MDD. The drug-placebo differences in the number of cases of suicidal thoughts and behaviors per 1000 patients treated are provided in Table 1 . Table 1: Risk Differences of the Number of Patients of Suicidal Thoughts and Behaviors in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range Drug-Placebo Difference in Number of Patients of Suicidal Thoughts and Behaviors per 1000 Patients Treated Increases Compared to Placebo <18 years old 14 additional patients 18 to 24 years old 5 additional patients Decreases Compared to Placebo 25 to 64 years old 1 fewer patient ≥65 years old 6 fewer patients It is unknown whether the risk of suicidal thoughts and behaviors in children, adolescents, and young adults extends to longer-term use, i.e., beyond four months.
However, there is substantial evidence from placebo-controlled maintenance trials in adults with MDD that antidepressants delay the recurrence of depression and that depression itself is a risk factor for suicidal thoughts and behaviors. Monitor all antidepressant-treated patients for any indication for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes. Counsel family members or caregivers of patients to monitor for changes in behavior and to alert the healthcare provider.
Consider changing the therapeutic regimen, including possibly discontinuing Lexapro, in patients whose depression is persistently worse, or who are experiencing emergent suicidal thoughts or behaviors.
5.2Serotonin Syndrome SSRIs, including Lexapro, can precipitate serotonin syndrome, a potentially life-threatening condition. The risk is increased with concomitant use of other serotonergic drugs (including triptans, tricyclic antidepressants, fentanyl, meperidine, methadone, lithium, tramadol, tryptophan, buspirone, amphetami…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Suicidal thoughts and behaviors in adolescents and young adults [see Warnings and Precautions ( 5.1 )] Serotonin syndrome [see Warnings and Precautions ( 5.2 )] Discontinuation syndrome [see Warnings and Precautions ( 5.3 )] Seizures [see Warnings and Precautions ( 5.4 )] Activation of mania or hypomania [see Warnings and Precautions ( 5.5 )] Hyponatremia [see Warnings and Precautions ( 5.6 )] Increased Risk of Bleeding [see Warnings and Precautions ( 5.7 )] Interference with Cognitive and Motor Performance [see Warnings and Precautions ( 5.8 )] Angle-closure glaucoma [see Warnings and Precautions ( 5.9 )] Use in Patients with Concomitant Illness [see Warnings and Precautions ( 5.10 )] Sexual Dysfunction [see Warnings and Precautions ( 5.11 )] Most commonly observed adverse reactions (incidence ≥ 5% and at least twice the incidence of placebo patients) are: insomnia, ejaculation disorder (primarily ejaculatory delay), nausea, sweating increased, fatigue and somnolence, decreased libido, and anorgasmia ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AbbVie at 1-800- 678-1605, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Clinical Trial Data Sources Adults Adverse reactions information for Lexapro was collected from 715 patients with major depressive disorder who were exposed to escitalopram and from 592 patients who were exposed to placebo in double-blind, placebo-controlled trials.
An additional 284 patients with major depressive disorder were newly exposed to escitalopram in open-label trials. The adverse reaction information for Lexapro in patients with GAD was collected from 429 patients exposed to escitalopram and from 427 patients exposed to placebo in double-blind, placebo-controlled trials. Adverse reactions during exposure were obtained primarily by general inquiry and recorded by clinical investigators using terminology of their own choosing.
Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse reactions without first grouping similar types of reactions into a smaller number of standardized event categories. In the tables and tabulations that follow, standard World Health Organization (WHO) terminology has been used to classify reported adverse reactions. The stated frequencies of adverse reactions represent the proportion of individuals who experienced, at least once, a treatment emergent adverse event of the type listed.
An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation. Pediatric Patients Adverse reaction information for pediatric patients was collected in double-blind placebo-controlled studies in 576 pediatric patients 6 to 17 years of age, (286 Lexapro, 290 placebo) with major depressive disorder and in 273 pediatric patients 7 to 17 years of age (137 Lexapro, 136 placebo) with generalized anxiety disorder. The safety and effectiveness of Lexapro have not been established in pediatric patients less than 12 years of age with MDD or less than 7 years of age with GAD.
Adverse Reactions Associated with Discontinuation of Treatment Major Depressive Disorder Adults Among the 715 depressed patients who received Lexapro in placebo-controlled trials, 6% discontinued treatment due to an adverse event, as compared to 2% of 592 patients receiving placebo. In two fixed-dose studies, the rate of discontinuation for adverse reactions in patients receiving 10 mg/day Lexapro was not significantly different from the rate of discontinuation for adverse r…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 6 presents clinically important drug interactions with Lexapro. TABLE 6 Clinically Important Drug Interactions with Lexapro Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact : Concomitant use of SSRIs, including Lexapro, and MAOIs increases the risk of serotonin syndrome. Intervention: Lexapro is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Dosage and Administration ( 2.7 ), Contraindications ( 4 ), and Warnings and Precautions ( 5.2 )] .
Pimozide Clinical Impact: Concomitant use of racemic citalopram with pimozide increases plasma concentrations of pimozide, a drug with a narrow therapeutic index, and may increase the risk of QT prolongation and/or ventricular arrhythmias compared to use of racemic citalopram alone [see Clinical Pharmacology ( 12.3 )]. Intervention: Lexapro is contraindicated in patients taking pimozide [see Contraindications ( 4 )]. Other Serotonergic Drugs Clinical Impact: Concomitant use of Lexapro and other serotonergic drugs (including other SSRIs, SNRIs, triptans, tricyclic antidepressants, opioids, lithium, buspirone, amphetamines, tryptophan, and St.
John's Wort) increases the risk of serotonin syndrome. Intervention: Monitor patients for signs and symptoms of serotonin syndrome, particularly during Lexapro initiation and dosage increases. If serotonin syndrome occurs, consider discontinuation of Lexapro and/or concomitant serotonergic drugs [see Warning and Precautions ( 5.2 )] .
Drugs That Interfere With Hemostasis (NSAIDs, Aspirin, Warfarin, etc.) Clinical Impact: Concomitant use of Lexapro and an antiplatelet or anticoagulant may potentiate the risk of bleeding. Intervention: Inform patients of the increased risk of bleeding associated with the concomitant use of Lexapro and antiplatelet agents and anticoagulants. For patients taking warfarin, carefully monitor the international normalized ratio [see Warning and Precautions ( 5.7 )] .
Sumatriptan Clinical Impact: There have been postmarketing reports describing patients with weakness, hyperreflexia, and incoordination following the use of an SSRI and sumatriptan. Intervention: If concomitant treatment with sumatriptan and an SSRI is clinically warranted, appropriate observation of the patient is advised [see Warning and Precautions ( 5.2 )] . Carbamazepine Clinical Impact: Combined administration of racemic citalopram (40 mg/day for 14 days) and carbamazepine (titrated to 400 mg/day for 35 days) did not significantly affect the pharmacokinetics of carbamazepine, a CYP3A4 substrate.
Intervention: Although trough citalopram plasma levels were unaffected, given the enzyme-inducing properties of carbamazepine, the possibility that carbamazepine might increase the clearance of escitalopram should be considered if the two drugs are coadministered. Drugs Metabolized by CYP2D6 Clinical Impact: Coadministration of escitalopram (20 mg/day for 21 days) with the tricyclic antidepressant desipramine (single dose of 50 mg), a substrate for CYP2D6, resulted in a 40% increase in Cmax and a 100% increase in AUC of desipramine.
Intervention: The clinical significance of this finding is unknown. Exercise caution during coadministration of escitalopram and drugs metabolized by CYP2D6. Concomitant use with SSRIs, SNRIs or Tryptophan is not recommended ( 7 ) Use caution when concomitant use with drugs that affect Hemostasis (NSAIDs, Aspirin, Warfarin) ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: SSRI use, particularly later in pregnancy, may increase the risk for persistent pulmonary hypertension and symptoms of poor adaptation (respiratory distress, temperature instability, feeding difficulties, hypotonia, tremor, irritability) in the neonate ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to advise patients to register by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185 or visiting online at https://womensmentalhealth.org/research/pregnancyregistry/antidepressants . Risk Summary Based on data from published observational studies, exposure to SSRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions ( 5.7 ) and Clinical Considerations].
Available data from published epidemiologic studies and postmarketing reports have not established an increased risk of major birth defects or miscarriage. There are risks of persistent pulmonary hypertension of the newborn (PPHN) (see Data) and poor neonatal adaptation (see Clinical Considerations) with exposure to selective serotonin reuptake inhibitors (SSRIs), including LEXAPRO, during pregnancy. There are risks associated with untreated depression in pregnancy (see Clinical Considerations).
In animal reproduction studies, both escitalopram and racemic citalopram have been shown to have adverse effects on embryo/fetal and postnatal development, including fetal structural abnormalities, when administered at doses greater than human therapeutic doses (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal risk and/or embryo/fetal risk Women who discontinue antidepressants are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective longitudinal study of 201 pregnant women with a history of major depression, who were euthymic and taking antidepressants at the beginning of pregnancy.
Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Maternal Adverse Reactions Use of Lexapro in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions ( 5.7 )] . Fetal/Neonatal adverse reactions Neonates exposed to SSRIs or SNRIs, including Lexapro, late in third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and SNRIs or, possibly, a drug discontinuation syndrome.
It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [see Warnings and Precautions ( 5.2 )] . Data Human Data Exposure to SSRIs, particularly later in pregnancy, may increase the risk for PPHN. PPHN occurs in 1-2 per 1000 live births in the general populations and is associated with substantial neonatal morbidity and mortality.
Animal Data In a rat embryo/fetal development study, oral administration of…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to advise patients to register by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185 or visiting online at https://womensmentalhealth.org/research/pregnancyregistry/antidepressants . Risk Summary Based on data from published observational studies, exposure to SSRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions ( 5.7 ) and Clinical Considerations].
Available data from published epidemiologic studies and postmarketing reports have not established an increased risk of major birth defects or miscarriage. There are risks of persistent pulmonary hypertension of the newborn (PPHN) (see Data) and poor neonatal adaptation (see Clinical Considerations) with exposure to selective serotonin reuptake inhibitors (SSRIs), including LEXAPRO, during pregnancy. There are risks associated with untreated depression in pregnancy (see Clinical Considerations).
In animal reproduction studies, both escitalopram and racemic citalopram have been shown to have adverse effects on embryo/fetal and postnatal development, including fetal structural abnormalities, when administered at doses greater than human therapeutic doses (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal risk and/or embryo/fetal risk Women who discontinue antidepressants are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective longitudinal study of 201 pregnant women with a history of major depression, who were euthymic and taking antidepressants at the beginning of pregnancy.
Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Maternal Adverse Reactions Use of Lexapro in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions ( 5.7 )] . Fetal/Neonatal adverse reactions Neonates exposed to SSRIs or SNRIs, including Lexapro, late in third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and SNRIs or, possibly, a drug discontinuation syndrome.
It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [see Warnings and Precautions ( 5.2 )] . Data Human Data Exposure to SSRIs, particularly later in pregnancy, may increase the risk for PPHN. PPHN occurs in 1-2 per 1000 live births in the general populations and is associated with substantial neonatal morbidity and mortality.
Animal Data In a rat embryo/fetal development study, oral administration of escitalopram (56, 112, or 150 mg/kg/day) to pregnant animals during the period of organogenesis resulted in decreased fetal body weight and associated delays in ossification at the two higher doses [approximately ≥ 55 times the maximum recommended human dose (MRHD) of 20 mg/day on a mg/m 2 basis]. Mat…
🧒 Pediatric Use ▾
8.4Pediatric Use Major Depressive Disorder The safety and effectiveness of Lexapro for the treatment of major depressive disorder have been established in pediatric patients 12 years of age and older. Use of Lexapro for this indication is supported by evidence from adequate and well-controlled studies in adults with additional evidence from an 8-week, flexible-dose, placebo-controlled study that compared Lexapro 10 mg to 20 mg once daily to placebo in pediatric patients 12 to 17 years of age with major depressive disorder [see Clinical Studies ( 14.1 )] .
The safety of Lexapro was similar to adult patients with MDD [see Adverse Reactions ( 6.1 )] . The safety and effectiveness of Lexapro for the treatment of major depressive disorder have not been established in pediatric patients younger than 12 years of age. In a 24-week, open- label safety study in 118 pediatric patients aged 7 to 11 years who had major depressive disorder, the safety findings were consistent with the known safety and tolerability profile for Lexapro.
Generalized Anxiety Disorder The safety and effectiveness of Lexapro for the treatment of generalized anxiety disorder have been established in pediatric patients 7 years of age and older. Use of Lexapro for this indication is supported by evidence from adequate and well-controlled studies in adults with additional evidence from an 8-week, flexible-dose, placebo-controlled study that compared Lexapro 10 mg to 20 mg once daily to placebo in pediatric patients 7 to 17 years of age with GAD [see Clinical Studies ( 14.2 )].
The safety of Lexapro was similar to adult patients with GAD [see Adverse Reactions ( 6.1 )] . The safety and effectiveness of Lexapro for the treatment of generalized anxiety disorder have not been established in pediatric patients younger than 7 years of age. Antidepressants increase the risk of suicidal thoughts and behaviors in pediatric patients [see Warnings and Precautions ( 5.1 )] .
Decreased appetite and weight loss have been observed in association with the use of SSRIs. Consequently, regular monitoring of weight and growth should be performed in children and adolescents treated with an SSRI such as Lexapro. Juvenile Animal Toxicity Data In a juvenile animal study, male and female rats were administered escitalopram at 5, 40, or 80 mg/kg/day by oral gavage from postnatal day (PND) 21 to PND 69.
A delay in sexual maturation was observed in both males and females at ≥ 40 mg/kg/day with a No Observed Adverse Effect Level (NOAEL) of 5 mg/kg/day. This NOAEL was associated with plasma AUC levels less than those measured at the maximum recommended dose (MRHD) in pediatrics (20 mg). However, there was no effect on reproductive function.
Increased motor activity (both ambulatory and fine movements) was observed in females prior to daily dosing at ≥ 40 mg/kg/day (3.5 times the MRHD based on AUC levels). A reversible disruption of learning and memory function was observed in males at 80 mg/kg/day with a NOAEL of 40 mg/kg/day, which was associated with an AUC level 3.5 times those measured at the MRHD in pediatrics. There was no effect on learning and memory function in treated female rats.
🧓 Geriatric Use ▾
8.5Geriatric Use Approximately 69 patients (6%) of the 1,144 patients receiving escitalopram in controlled trials of Lexapro in major depressive disorder and GAD were 60 years of age or older [see Clinical Studies ( 14.1 , 14.2 )] . The number of elderly patients in these trials was insufficient to adequately assess for possible differential efficacy and safety measures on the basis of age. Nevertheless, greater sensitivity of some elderly individuals to effects of Lexapro cannot be ruled out.
In two pharmacokinetic studies, escitalopram half-life was increased by approximately 50% in subjects 65 years and older as compared to young subjects and C max was unchanged [see Clinical Pharmacology ( 12.3 )] . The recommended dosage of LEXAPRO for elderly patients is 10 mg daily [see Dosage and Administration ( 2.5 )] . SSRIs, including Lexapro, have been associated with cases of clinically significant hyponatremia in elderly patients, who may be at greater risk for this adverse reaction [ see Warnings and Precautions ( 5.6 )] .
Of 4,422 patients in clinical studies of racemic citalopram, 1,357 were 60 and over, 1,034 were 65 and over, and 457 were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the geriatric and younger patients, but again, greater sensitivity of some elderly individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE The following have been reported with Lexapro tablet overdosage: Seizures, which may be delayed, and altered mental status including coma. Cardiovascular toxicity, which may be delayed, including QRS and QTc interval prolongation, wide complex tachyarrhythmias, and torsade de pointes. Hypertension most commonly seen, but rarely can see hypotension alone or with co-ingestants including alcohol.
Serotonin syndrome (patients with a multiple drug overdosage with other proserotonergic drugs may have a higher risk). Prolonged cardiac monitoring is recommended in Lexapro overdosage ingestions due to the arrhythmia risk. Gastrointestinal decontamination with activated charcoal should be considered in patients who present early after a Lexapro overdose.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of antidepressant action of escitalopram, the S-enantiomer of racemic citalopram, is presumed to be linked to potentiation of serotonergic activity in the central nervous system (CNS) resulting from its inhibition of CNS neuronal reuptake of serotonin (5-HT).
12.2Pharmacodynamics In vitro and in vivo studies in animals suggest that escitalopram is a highly selective serotonin reuptake inhibitor (SSRI) with minimal effects on norepinephrine and dopamine neuronal reuptake. Escitalopram is at least 100-fold more potent than the R-enantiomer with respect to inhibition of 5-HT reuptake and inhibition of 5-HT neuronal firing rate. Tolerance to a model of antidepressant effect in rats was not induced by long-term (up to 5 weeks) treatment with escitalopram.
Escitalopram has no or very low affinity for serotonergic (5-HT 1-7 ) or other receptors including alpha- and beta-adrenergic, dopamine (D 1-5 ), histamine (H 1-3 ), muscarinic (M 1-5 ), and benzodiazepine receptors. Escitalopram also does not bind to, or has low affinity for, various ion channels including Na + , K + , Cl - , and Ca ++ channels. Antagonism of muscarinic, histaminergic, and adrenergic receptors has been hypothesized to be associated with various anticholinergic, sedative, and cardiovascular side effects of other psychotropic drugs.
12.3Pharmacokinetics The single- and multiple-dose pharmacokinetics of escitalopram are linear and dose-proportional in a dose range of 10 to 30 mg/day. With once-daily dosing, steady state plasma concentrations are achieved within approximately one week. At steady state, the extent of accumulation of escitalopram in plasma in young healthy subjects was 2.2-2.5 times the plasma concentrations observed after a single dose.
Absorption The absolute bioavailability of citalopram is about 80% relative to an intravenous dose. The tablet and the oral solution dosage forms of escitalopram oxalate are bioequivalent. Following a single oral dose (20 mg tablet or solution) of escitalopram, peak blood levels occur at about 5 hours.
Absorption of escitalopram is not affected by food. Distribution The binding of escitalopram to human plasma proteins is approximately 56%. The volume of distribution of citalopram is about 12 L/kg.
Data specific on escitalopram are unavailable. Elimination Biotransformation of escitalopram is mainly hepatic, with a mean terminal half-life of about 27-32 hours. The oral clearance of escitalopram is 600 mL/min, with approximately 7% of that due to renal clearance.
Metabolism Escitalopram is metabolized to S-DCT and S-didemethylcitalopram (S-DDCT). In humans, unchanged escitalopram is the predominant compound in plasma. At steady state, the concentration of the escitalopram metabolite S-DCT in plasma is approximately one-third that of escitalopram.
The level of S-DDCT was not detectable in most subjects. In vitro studies show that escitalopram is at least 7 and 27 times more potent than S-DCT and S-DDCT, respectively, in the inhibition of serotonin reuptake, suggesting that the metabolites of escitalopram do not contribute significantly to the antidepressant actions of escitalopram. S-DCT and S-DDCT also have no or very low affinity for serotonergic (5-HT 1-7 ) or other receptors including alpha- and beta-adrenergic, dopamine (D 1-5 ), histamine (H 1-3 ), muscarinic (M 1-5 ), and benzodiazepine receptors.
S-DCT and S-DDCT also do not bind to various ion channels including Na + , K + , Cl - , and Ca ++ channels. In vitro studies using human liver microsomes indicated that CYP3A4 and CYP2C19 are the primary isozymes involved in the N-demethylation of escitalopram. Excretion Following oral administrations of escitalopram, the fraction of drug recovered in the urine as escitalopram and S-demethylcitalopram (S-DCT) is about 8% and 10%, respectively.
Specific Populations Pediatric Patients Pediatric patients 7 to 11 years of age: Based on population PK simulations…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of antidepressant action of escitalopram, the S-enantiomer of racemic citalopram, is presumed to be linked to potentiation of serotonergic activity in the central nervous system (CNS) resulting from its inhibition of CNS neuronal reuptake of serotonin (5-HT).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Tablets 5 mg Tablets: Bottle of 100 NDC # 0456-2005-01 White to off-white, round, non-scored, film-coated. Imprint "FL" on one side of the tablet and "5" on the other side. 10 mg Tablets: Bottle of 100 NDC # 0456-2010-01 10 x 10 Unit Dose NDC # 0456-2010-63 White to off-white, round, scored, film-coated.
Imprint on scored side with "F" on the left side and "L" on the right side. Imprint on the non-scored side with "10". 20 mg Tablets: Bottle of 100 NDC # 0456-2020-01 10 x 10 Unit Dose NDC # 0456-2020-63 White to off-white, round, scored, film-coated.
Imprint on scored side with "F" on the left side and "L" on the right side. Imprint on the non-scored side with "20". Oral Solution 5 mg/5 mL, peppermint flavor (240 mL) NDC # 0456-2101-08.
The oral solution is not currently being marketed. Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15 to 30°C (59° to 86°F).
📋 Description ▾
11 DESCRIPTION Lexapro contains escitalopram, a selective serotonin reuptake inhibitor (SSRI), present as escitalopram oxalate salt. Escitalopram is the pure S- enantiomer (single isomer) of the racemic bicyclic phthalane derivative citalopram. Escitalopram oxalate is designated S-(+)-1-[3(dimethyl-amino)propyl]-1-( p -fluorophenyl)-5-phthalancarbonitrile oxalate with the following structural formula: The molecular formula is C 20 H 21 FN 2 O • C 2 H 2 O 4 and the molecular weight is 414.40.
Escitalopram oxalate occurs as a fine, white to slightly-yellow powder and is freely soluble in methanol and dimethyl sulfoxide (DMSO), soluble in isotonic saline solution, sparingly soluble in water and ethanol, slightly soluble in ethyl acetate, and insoluble in heptane. Lexapro tablets, for oral use, are film-coated, round tablets containing 6.38 mg, 12.75 mg, 25.5 mg escitalopram oxalate in strengths equivalent to 5 mg, 10 mg, and 20 mg, respectively, of escitalopram base. The 10 and 20 mg tablets are scored.
The tablets also contain the following inactive ingredients: talc, croscarmellose sodium, microcrystalline cellulose/colloidal silicon dioxide, and magnesium stearate. The film coating contains hypromellose, titanium dioxide, and polyethylene glycol. Lexapro oral solution contains 1.29 mg/ml escitalopram oxalate equivalent to 1 mg/mL escitalopram base.
It also contains the following inactive ingredients: sorbitol, purified water, citric acid, sodium citrate, malic acid, glycerin, propylene glycol, methylparaben, propylparaben, and natural peppermint flavor. The oral solution is not currently marketed. The following structural formula for Lexapro® (escitalopram oxalate) is an orally administered selective serotonin reuptake inhibitor (SSRI).
Escitalopram is the pure S-enantiomer (single isomer) of the racemic bicyclic phthalane derivative citalopram. Escitalopram oxalate is designated S-(+)-1-[3-(dimethyl-amino)propyl]-1-(p-fluorophenyl)-5-phthalancarbonitrile oxalate.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Suicidal Thoughts and Behaviors Advise patients, their families and caregivers to look for the emergence of suicidal ideation and behavior, especially during treatment and when the dose is adjusted up or down, and instruct them to report such symptoms to their healthcare provider [see Boxed Warning and Warnings and Precautions ( 5.1 )] . Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the with the concomitant use of Lexapro with other serotonergic drugs including triptans, tricyclic antidepressants, opioids, lithium, tryptophan, buspirone, amphetamines, and St.
John’s Wort, and with drugs that impair metabolism of serotonin (in particular, MAOIs, both those intended to treat psychiatric disorders and also others, such as linezolid). Instruct patients to contact their health care provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome [see Warnings and Precautions ( 5.2 ), Drug Interactions ( 7 )] . Discontinuation Syndrome Advise patients not to abruptly discontinue Lexapro and to discuss any tapering regimen with their healthcare provider.
Inform patients that adverse reactions can occur when Lexapro is discontinued [see Warnings and Precautions ( 5.3 )] . Activation of Mania or Hypomania Advise patients and their caregivers to observe for signs of activation of mania/hypomania and instruct them to report such symptoms to the healthcare provider [see Warnings and Precautions ( 5.5 )]. Increased Risk of Bleeding Inform patients about the concomitant use of Lexapro with NSAIDs, aspirin, warfarin, other antiplatelet drugs, or other anticoagulants because the combined use has been associated with an increased risk of bleeding.
Advise patients to inform their healthcare providers if they are taking or planning to take any prescription or over-the-counter medications that increase the risk of bleeding [see Warnings and Precautions ( 5.7 )] . Angle Closure Glaucoma Advise patients that taking Lexapro can cause mild pupillary dilation, which in susceptible individuals, can lead to an episode of angle closure glaucoma. Pre-existing glaucoma is almost always open-angle glaucoma because angle closure glaucoma, when diagnosed, can be treated definitively with iridectomy.
Open-angle glaucoma is not a risk factor for angle closure glaucoma. Patients may wish to be examined to determine whether they are susceptible to angle closure, and have a prophylactic procedure (e.g., iridectomy), if they are susceptible [see Warnings and Precautions ( 5.9 )] . Sexual Dysfunction Advise patients that use of Lexapro may cause symptoms of sexual dysfunction in both male and female patients.
Inform patients that they should discuss any changes in sexual function and potential management strategies with their healthcare provider [see Warnings and Precautions ( 5.11 )] . Concomitant Medications Since escitalopram is the active isomer of racemic citalopram (Celexa), the two agents should not be coadministered. Patients should be advised to inform their physician if they are taking, or plan to take, any prescription or over-the-counter drugs, as there is a potential for interactions.
Interference with Psychomotor Performance Because psychoactive drugs may impair judgment, thinking, or motor skills, patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that Lexapro therapy does not affect their ability to engage in such activities. Alcohol Patients should be told that, although Lexapro has not been shown in experiments with normal subjects to increase the mental and motor skill impairments caused by alcohol, the concomitant use of Lexapro and alcohol in depressed patients is not advised.
Pregnan c y Advise pregnant women to notify their healthcare providers if they become pregnant or intend…
💬 Medication Guide ▾
MEDICATION GUIDE Lexapro ® (leks-a-pro) (escitalopram) tablets oral solution What is the most important information I should know about Lexapro? Lexapro may cause serious side effects, including: Increased risk of suicidal thoughts or actions. Lexapro and other antidepressant medicines increase the risk of suicidal thoughts and actions in people 24 years of age and younger, especially within the first few months of treatment or when the dose is changed. ○ Depression or other mental illnesses are the most important causes of suicidal thoughts or actions.
How can I watch for and try to prevent suicidal thoughts and actions? ○ Pay close attention to any changes, especially sudden changes in mood, behavior, thoughts, or feelings, or if you or your child develop suicidal thoughts or actions. This is very important when an antidepressant medicine is started or when the dose is changed. ○ Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings or if you or your child develop suicidal thoughts or actions. ○ Keep all follow-up visits with your healthcare provider as scheduled and call your healthcare provider between visits if you are worried about symptoms.
Call your healthcare provider or get emergency medical help right away if you or your child have any of the following symptoms, especially if they are new, worse, or worry you: attempts to commit suicide acting on dangerous impulses acting aggressive, being angry or violent thoughts about suicide or dying new or worse depression new or worsening anxiety panic attacks feeling very agitated or restless new or worse irritability trouble sleeping an extreme increase in activity or talking (mania) other unusual changes in behavior or mood What is Lexapro?
Lexapro is a prescription medicine used to treat: a certain type of depression called Major Depressive Disorder (MDD) in adults and children 12 years of age and older Generalized Anxiety Disorder (GAD) in adults and children 7 years of age and older It is not known if Lexapro is safe and effective for use in children under 12 years of age with MDD or children under 7 years of age with GAD. Do not take Lexapro if you or your child: are taking, or have stopped taking within the last 14 days, a medicine called a monoamine oxidase inhibitor (MAOI), including the antibiotic linezolid or intravenous methylene blue are taking the antipsychotic medicine pimozide are allergic to escitalopram or citalopram or any of the ingredients in Lexapro.
See the end of this Medication Guide for a complete list of ingredients in Lexapro. Ask your healthcare provider or pharmacist if you are not sure if you or your child take an MAOI, including the antibiotic linezolid or intravenous methylene blue. Do not start taking an MAOI for at least 14 days after you or your child have stopped treatment with Lexapro.
Before taking Lexapro, tell your healthcare provider about all your medical conditions, including if you or your child : have or had seizures or convulsions have, or have a family history of bipolar disorder, mania, or hypomania have low blood sodium levels have or had bleeding problems have high pressure in the eye (glaucoma) have heart, liver, or kidney problems are pregnant or plan to become pregnant. Lexapro may harm the unborn baby. Taking Lexapro during the third trimester of pregnancy may cause the baby to have withdrawal symptoms, or breathing, temperature control, feeding, or other problems after birth.
Talk to your healthcare provider about the risks to the baby if you or your child take Lexapro during pregnancy. ○ Tell your healthcare provider right away if you or your child become pregnant or think you may be pregnant during treatment with Lexapro. ○ There is a pregnancy registry for females who are exposed to Lexapro during pregnancy. The purpose of the registry is to collect information about the health of females exposed to Lexapro and their baby. If you or your child become pregnant…