
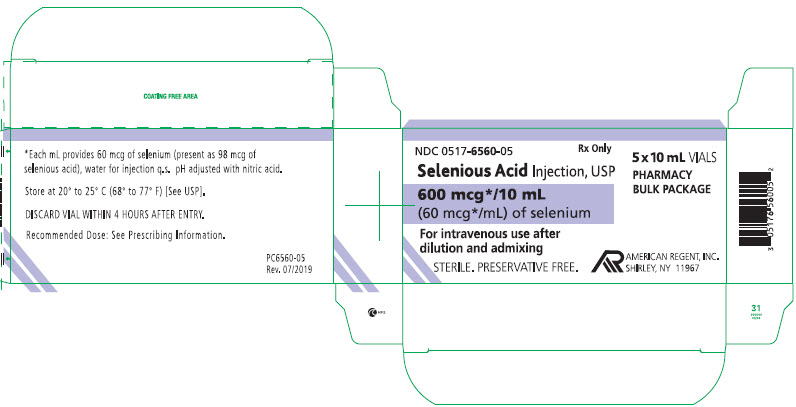
Selenious Acid 60 ug/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 411VRN1TV4
Nitric acid is a strong chemical used in small amounts during drug manufacturing to adjust and maintain the proper acid-base balance of a medicine, ensuring stability and correct formulation.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $91.07 | $4,553.52 / 50 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Selenious Acid 60 ug/mLthis 00517-6560-05 | American | 5 vials | — | AP | FDA listed | — |
| Selenious Acid 60 ug/mL 68083-0660-05 | Gland | 5 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12150957 ↗ | Method of use | U-4039 | Jul 1, 2041 |
| US 12150957 ↗ | Method of use | U-4039 | Jul 1, 2041 |
| US 12150957 ↗ | Method of use | U-4039 | Jul 1, 2041 |
| US 11998565 ↗ | Drug product | — | Jul 1, 2041 |
| US 11998565 ↗ | Drug product | — | Jul 1, 2041 |
| US 11998565 ↗ | Drug product | — | Jul 1, 2041 |
Is there a generic version of SELENIOUS ACID 600 MCG/10 ML?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00517-6560-05 You're viewing this | 5 VIAL, PHARMACY BULK PACKAGE in 1 BOX (0517-6560-05) / 10 mL in 1 VIAL, PHARMACY BULK PACKAGE (0517-6560-01) | 2019-07-01 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Selenious Acid Injection is indicated in adult and pediatric patients as a source of selenium for parenteral nutrition when oral or enteral nutrition is not possible, insufficient, or contraindicated. Selenious Acid Injectionis a trace element indicated in adult and pediatric patients as a source of selenium for parenteral nutrition when oral or enteral nutrition is not possible, insufficient, or contraindicated. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Pharmacy Bulk Package or Single-Dose Vial: Not for direct intravenous infusion. ( 2.1 ) • See full prescribing information for information on preparation, administration, and general dosing considerations. ( 2.1 , 2.2 , 2.3 , 2.4 ) Recommended Dosage ( 2.5) • Selenious Acid Injection provides 60 mcg/mL of selenium. • Selenious Acid Injection in a concentration of 6 mcg/mL is recommended for use in pediatric patients, particularly those weighing 7 kg or less. • Individualize the dosage based upon the patient’s clinical condition, nutritional requirements, and the contribution of oral or enteral selenium intake.
The following dosages are general recommendations intended for most patients. However, based upon clinical requirements, some patients may require a higher dosage: ○ Adults: 60 mcg/day ○ Pediatric Patients 7 kg and above: 2 mcg/kg/day (up to 60 mcg/day) ○ Pediatric Patients less than 7 kg: 2 to 4 mcg/kg/day • Monitor selenium concentrations during treatment.
2.1Important Administration Information Selenious Acid Injection is supplied as a pharmacy bulk package or single-dose vial for admixing use only. It is not for direct intravenous infusion . Prior to administration, Selenious Acid Injection must be transferred to a separate parenteral nutrition container, prepared and used as an admixture in parenteral nutrition solutions.
The Pharmacy Bulk Package vial of Selenious Acid Injection is intended for dispensing of single doses to multiple patients in a pharmacy admixture program. The final parenteral nutrition solution is for intravenous infusion into a central or peripheral vein. The choice of a central or peripheral venous route should depend on the osmolarity of the final infusate.
Solutions with osmolarity of 900 mOsmol/L or greater must be infused through a central venous catheter [see Warnings and Precautions ( 5.2 )] .
2.2Preparation and Administration Instructions • Selenious Acid Injection is not for direct intravenous infusion . Prior to administration, Selenious Acid Injection must be prepared and used as an admixture inparenteral nutrition solutions. • Selenious Acid Injection is to be prepared only in a suitable work area such as a laminar flow hood (or an equivalent clean air compounding area). The key factor in the preparation is careful aseptic technique to avoid inadvertent touch contamination during mixing of solutions and addition of other nutrients. • Visually inspect the prepared parenteral nutrition solution containing Selenious Acid Injection for particulate matter before admixing, after admixing, and prior to administration.
2.3Preparation Instructions for Admixing Using a Parenteral Nutrition Container Inspect Selenious Acid Injection vials for particulate matter. Transfer Selenious Acid Injection to the parenteral nutrition solution following the admixture of amino acids, dextrose, lipid (if added), and electrolytes solutions. Because additives may be incompatible, evaluate all additions to the parenteral nutrition container for compatibility and stability of the resulting preparation.
Consult with pharmacist, if available. Questions about compatibility may be directed to America Regent. If it is deemed advisable to introduce additives to the parenteral nutrition container, use aseptic technique.
Inspect the final parenteral nutrition containing Selenious Acid Injection to ensure that: Precipitates have not formed during mixing or addition of additives. The admixed emulsion has not separated, if a lipid emulsion has been added. Separation of the admixed emulsion can be visibly identified by a yellowish streaking of the accumulation of yellowish droplets.
Discard if any precipitates are observed. Stability and Storage Single-dose vial (2 mL): Discard unused portion. Pharmacy Bulk Package vial (10 mL): Penetrate vial closure only one time with a suitable sterile transfer device or dispensing set that allows measured dispensing of the content.
Use Selenious Acid Inj…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Selenious Acid Injection, USP is a clear colorless solution available in the following: Pharmacy Bulk Package: 600 mcg/10mL (60 mcg/mL) of selenium Single-Dose Vial: 12 mcg/2 mL (6 mcg/mL) of selenium Selenious Acid Injection, USP: ( 3 ) Pharmacy Bulk Package: 600 mcg/10 mL (60 mcg/mL) of selenium Single-Dose Vial: 12 mcg/2 mL (6 mcg/mL) of selenium
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Pulmonary Embolism due to Pulmonary Vascular Precipitates : If signs of pulmonary distress occur, stop the infusion and initiate a medical evaluation. (5.1) Vein Damage and Thrombosis: Solutions with osmolarity of 900 mOsmol/L or more must be infused through a central venous catheter. ( 2.1 , 5.2 ) Aluminum Toxicity : Increased risk in patients with renal impairment, including preterm infants.
( 5.3, 5.4 ) Monitoring and Laboratory Tests : Monitor selenium concentrations, fluid and electrolyte status, serum osmolarity, blood glucose, liver and kidney function, blood count and coagulation parameters throughout treatment. ( 5.4 , 2.4 )
5.1Pulmonary Embolism due to Pulmonary Vascular Precipitates Pulmonary vascular precipitates causing pulmonary vascular emboli and pulmonary distress have been reported in patients receiving parenteral nutrition. The cause of precipitate formation has not been determined in all cases; however, in some fatal cases, pulmonary emboli occurred as a result of calcium phosphate precipitates. Precipitation has occurred following passage through an in-line filter; in vivo precipitate formation may also have occurred.
If signs of pulmonary distress occur, stop the parenteral nutrition infusion and initiate a medical evaluation. In addition to inspection of the solution [see Dosage and Administration ( 2.2 , 2.3 )] , the infusion set and catheter should also periodically be checked for precipitates.
5.2Vein Damage and Thrombosis Selenious Acid Injection has a low pH and must be prepared and used as an admixture in parenteral nutrition solutions. It is not for direct intravenous infusion. In addition, consider the osmolarity of the final parenteral nutrition solution in determining peripheral versus central administration.
Solutions with an osmolarity of 900 mOsmol/L or greater must be infused through a central catheter [see Dosage and Administration ( 2.1 )] . The infusion of hypertonic nutrient injections into a peripheral vein may result in vein irritation, vein damage, and/or thrombosis. The primary complication of peripheral access is venous thrombophlebitis, which manifests as pain, erythema, tenderness or a palpable cord.
Remove the catheter as soon as possible, if thrombophlebitis develops.
5.3Aluminum Toxicity Selenious Acid Injection contains aluminum that may be toxic. Aluminum may reach toxic levels with prolonged parenteral administration if kidney function is impaired. Preterm infants are particularly at risk for aluminum toxicity because their kidneys are immature, and they require large amounts of calcium and phosphate solutions, which also contain aluminum.
Patients with impaired kidney function, including preterm neonates, who receive greater than 4 to 5 mcg/kg/day of parenteral aluminum can accumulate aluminum to levels associated with central nervous system and bone toxicity. Tissue loading may occur at even lower rates of administration. Exposure to aluminum from Selenious Acid Injection is not more than 0.6 mcg/kg/day.
When prescribing Selenious Acid Injection for use in parenteral nutrition containing other small volume parenteral products, the total daily patient exposure to aluminum from the admixture should be considered and maintained at no more than 5 mcg/kg/day [see Use in Specific Populations ( 8.4 )] .
5.4Monitoring and Laboratory Tests Monitor selenium concentrations, fluid and electrolyte status, serum osmolarity, blood glucose, liver and kidney function, blood count and coagulation parameters during treatment [see Dosage and Administration ( 2.5 )] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS No selenium-related adverse reactions have been reported in clinical studies or postmarketing reports in patients receiving intravenously administered parenteral nutrition solutions containing selenious acid within the recommended dosage range. The following adverse reactions associated with use of other components of parenteral nutrition solutions were identified in clinical studies or postmarketing reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: Pulmonary embolism due to pulmonary vascular precipitates [see Warnings and Precautions ( 5.1 )] Vein damage and thrombosis [see Warnings and Precautions ( 5.2 )] Aluminum toxicity [see Warnings and Precautions ( 5.3 )] No selenium-related adverse reactions in patients receiving intravenously administered parenteral nutrition solutions containing selenious acid within the recommended dosage range.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact American Regent Inc. at 1-800-734-9236 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Administration of the recommended dose of Selenious Acid Injection in parenteral nutrition is not expected to cause major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal reproduction studies have not been conducted with intravenous selenious acid. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. n the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo-Fetal Risk Deficiency of trace elements, including selenium, is associated with adverse pregnancy and fetal outcomes. Pregnant women have an increased metabolic demand for trace elements, including selenium.
Parenteral nutrition with selenium should be considered if a pregnant woman’s nutritional requirements cannot be fulfilled by oral or enteral intake.
8.2Lactation Risk Summary Selenium is present in human milk. Administration of the approved recommended dose of Selenious Acid Injection in parenteral nutrition is not expected to cause harm to a breastfed infant. There is no information on the effects of selenious acid on milk production.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for Selenious Acid Injection and any potential adverse effects on the breastfed infant from Selenious Acid Injection or from the underlying maternal condition.
8.4Pediatric Use Selenious Acid Injection is approved for use in the pediatric population, including neonates, as a source of selenium for parenteral nutrition when oral or enteral nutrition is not possible, insufficient, or contraindicated. Safety and dosing recommendations in pediatric patients are based on clinical experience [see Dosage and Administration ( 2.5 )] . Because of immature renal function, preterm infants receiving prolonged parenteral nutrition treatment with Selenious Acid Injection may be at higher risk of aluminum toxicity [see Warnings and Precautions ( 5.3 )].
8.5Geriatric Use Reported clinical experience with intravenous selenious acid has not identified a difference in selenium requirements between elderly and younger patients. In general, dose selection should be individualized based on the patient’s clinical condition, nutritional requirements, and additional nutritional intake provided orally or enterally to the patient.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Administration of the recommended dose of Selenious Acid Injection in parenteral nutrition is not expected to cause major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal reproduction studies have not been conducted with intravenous selenious acid. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. n the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo-Fetal Risk Deficiency of trace elements, including selenium, is associated with adverse pregnancy and fetal outcomes. Pregnant women have an increased metabolic demand for trace elements, including selenium.
Parenteral nutrition with selenium should be considered if a pregnant woman’s nutritional requirements cannot be fulfilled by oral or enteral intake.
🧒 Pediatric Use ▾
8.4Pediatric Use Selenious Acid Injection is approved for use in the pediatric population, including neonates, as a source of selenium for parenteral nutrition when oral or enteral nutrition is not possible, insufficient, or contraindicated. Safety and dosing recommendations in pediatric patients are based on clinical experience [see Dosage and Administration ( 2.5 )] . Because of immature renal function, preterm infants receiving prolonged parenteral nutrition treatment with Selenious Acid Injection may be at higher risk of aluminum toxicity [see Warnings and Precautions ( 5.3 )].
🧓 Geriatric Use ▾
8.5Geriatric Use Reported clinical experience with intravenous selenious acid has not identified a difference in selenium requirements between elderly and younger patients. In general, dose selection should be individualized based on the patient’s clinical condition, nutritional requirements, and additional nutritional intake provided orally or enterally to the patient.
🆘 Overdosage ▾
10 OVERDOSAGE There are no known cases of overdosage with intravenous selenious acid in parenteral nutrition. Overdosage has been reported with oral selenium. Available selenium concentrations in these subjects have been reported using various assays and laboratory-based reference ranges over a period of time.
Interpret results in the context of current reported ranges. For oral selenium, the Tolerable Upper Limit (UL) is 400 mcg/day and the No Observed Adverse Effect Level (NOAEL) is 800 mcg/day. The estimated oral bioavailability of selenium is approximately 70%.
Acute Oral Toxicity Effects Serious adverse events and deaths have been reported with acute oral toxicity, however, there is no clear correlation between the amount ingested, signs and symptoms of toxicity, or selenium blood concentrations. With severe toxicity, the most common presenting symptoms within a few hours post-ingestion of oral doses greater than 1 gram/day of selenium are gastrointestinal (nausea, vomiting, diarrhea, and abdominal pain), altered mental status, and “garlic” breath odor. Death from circulatory collapse has been reported after oral ingestion of 5 to 10 grams of selenium.
Selenium serum or blood concentrations in fatal cases have been reported in the range of 190 mcg/dL to 3,800 mcg/dL. Mild to moderate intoxication (myalgia, muscle spasms, and irritability) has been reported in patients with selenium serum or blood concentrations in the range of 41 to 750 mcg/dL. Chronic Selenosis Chronic daily exposure to selenium from dietary sources (0.003 to 0.007 grams/day) or oral supplements (0.0016 to 0.25 grams/day) may result in alopecia and nail brittleness.
Other signs include gastrointestinal disturbances, skin rash, garlic breath, fatigue, irritability, and nervous system abnormalities including paresthesia and ataxia. Selenium serum or blood concentrations in patients in China exposed through oral (non-dietary) supplementation were in the range of 32 to 150 mcg/dL. Management There is no known antidote for acute selenium toxicity.
Management of selenium overdosage is supportive care based on presenting signs and symptoms.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Selenious acid is converted in vivo to hydrogen selenide via glutathione-involved electron reductions. Hydrogen selenide acts as a selenium pool to form selenoproteins which include, but are not limited to, glutathione peroxidase, iodothyronine deiodinase, peroxidase and thioredoxins.
12.2Pharmacodynamics Selenious acid exposure-response relationships and the time course of pharmacodynamic responses is unknown.
12.3Pharmacokinetics Distribution In humans 85% of intravenous administered 75 Se-sodium selenite was protein-bound within 4 to 6 hours and 95% by 24 hours. Elimination Selenium is primarily eliminated in urine.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Selenious acid is converted in vivo to hydrogen selenide via glutathione-involved electron reductions. Hydrogen selenide acts as a selenium pool to form selenoproteins which include, but are not limited to, glutathione peroxidase, iodothyronine deiodinase, peroxidase and thioredoxins.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED Selenious Acid Injection, USP is a clear, colorless solution available as: 600 mcg/10mL (60 mcg/mL) of selenium in a 10 mL pharmacy bulk package. Carton of 5 vials (NDC 0517-6560-05). 12 mcg/2 mL (6 mcg/mL) of selenium in a 2 mL single-dose vial.
Carton of 10 vials (NDC 0517-6502-10). The vial closure for both presentation is not made with natural rubber latex. Store at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature] For storage of admixed solution, see Dosage and Administration ( 2.3 ).
📋 Description ▾
11 DESCRIPTION Selenious Acid Injection, USP is a sterile, non-pyrogenic, clear, colorless solution intended for use as a trace element and additive to intravenous solutions for parenteral nutrition. Each 600 mcg/10 mL Pharmacy Bulk Package vial contains 10 mL of selenious acid solution. Each 6 mcg/mL single-dose vial contains 2 mL of selenious acid solution.
None of the presentations contain preservatives. Each mL of the 60 mcg/mL strength contains 60 mcg of selenium present as 98 mcg of selenious acid, nitric acid for pH adjustment (1.8 to 2.4), and water for injection q.s. Each mL of the 6 mcg/mL strength contains 6 mcg of selenium present as 9.8 mcg of selenious acid, nitric acid for pH adjustment (1.8 to 2.4), and water for injection q.s.
Selenious Acid Injection 60 mcg/mL contains no more than 2,500 mcg/L of aluminum and has a calculated osmolarity of 16 mOsmol/L. Selenious Acid Injection 6 mcg/mL contains no more than 900 mcg/L of aluminum and has a calculated osmolarity of 13 mOsmol/L. Selenious acid has a molecular weight of 128.97 g/mol and a formula of H 2 SeO 3 .
The structural formula is: Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients, caregivers or home healthcare providers of the following risks of Selenious Acid Injection: Pulmonary embolism due to pulmonary vascular precipitates [see Warnings and Precautions ( 5.1 )] Vein damage and thrombosis [see Warnings and Precautions ( 5.2 )] Aluminum toxicity [see Warnings and Precautions ( 5.3 )] AMERICAN REGENT, INC. SHIRLEY, NY 11967 IN6560 Rev. 8/2021