
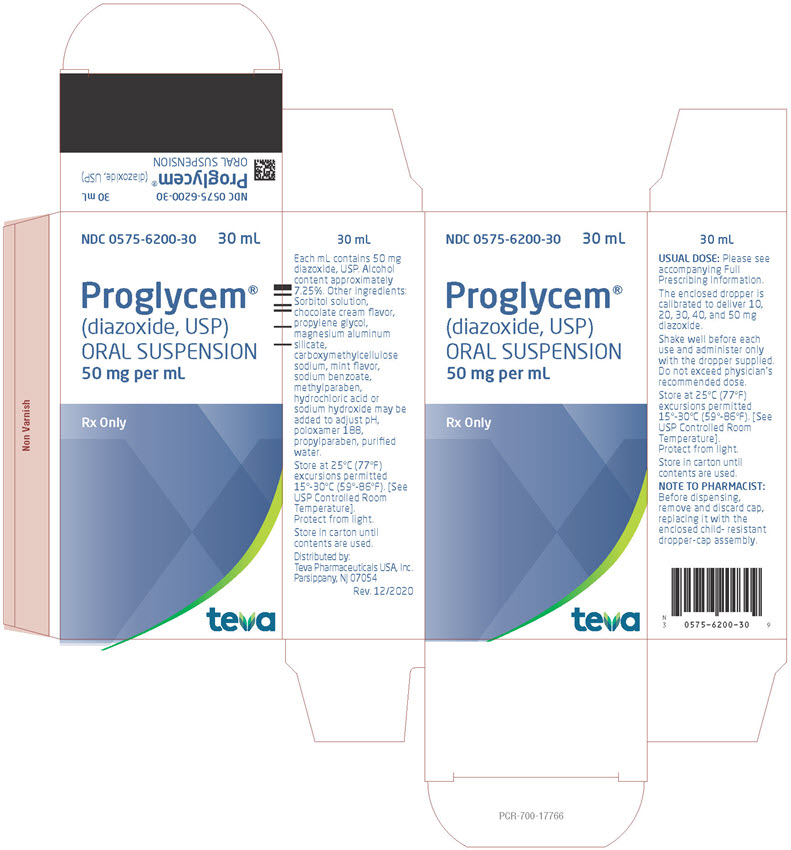
Proglycem diazoxide 50 mg/mL Suspension — NDC 0575-6200-30 (Billing 00575-6200-30)
This is a package of Proglycem diazoxide 50 mg/mL Suspension from Teva Pharmaceuticals USA, Inc., marketed since Sep 1990 and currently FDA-listed; retail pharmacies pay about $16.48 per mL (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0575-6200-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0575 labeler · 6200 product · 30 package
- Package marketed since
- Sep 30, 1990
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0575620030 9
- Medicaid fills, this package
- 1,592 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 000298
- GCN: 01280
- GPI-14 (Medi-Span): 27300020001810
- HICL (First Databank): 000092
- AHFS class code: 68:22.92.00
- RxCUI (RxNorm): 197593
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Thiazide derivatives class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Diazoxide — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $16.483 | $494.48 / 30 ml |
| Medicaid paysCMS SDUD · 12 mo | $15.65 | $469.48 / 30 ml |
| Medicare drug plans payPart D · Q2 2026 | $17.46 | $523.82 / 30 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00575-6200-30 You're viewing this Main listing | 1 BOTTLE, DROPPER in 1 BOX / 30 mL in 1 BOTTLE, DROPPER | 1990-09-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diazoxide 50 mg/mL 00254-1010-19 | Par | 1 bottle | $7.376 | AB | Availability likely | save 55% |
| Diazoxide 50 mg/mL 13517-0100-30 | e5 | 1 bottle | $7.376 | AB | Availability likely | save 55% |
| Proglycem 50 mg/mLthis 00575-6200-30 | Teva | 1 bottle | $16.483 | AB | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 6M3P64V0NC
A fine powder made from magnesium, aluminum, and silicon compounds. It absorbs moisture and helps keep medicine ingredients from clumping or separating, so the product stays stable and flows smoothly during manufacturing.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE PROGLYCEM is indicated for the management of hypoglycemia due to hyperinsulinism associated with the following conditions: Adults: Inoperable islet cell adenoma or carcinoma, or extrapancreatic malignancy. Infants and children: Leucine sensitivity, islet cell hyperplasia, nesidioblastosis, extrapancreatic malignancy, islet cell adenoma, or adenomatosis. PROGLYCEM may be used preoperatively as a temporary measure, and postoperatively, if hypoglycemia persists.
PROGLYCEM should be used only after a diagnosis of hypoglycemia due to one of the above conditions has been definitely established. When other specific medical therapy or surgical management either has been unsuccessful or is not feasible, treatment with PROGLYCEM should be considered.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Patients should be under close clinical observation when treatment with PROGLYCEM is initiated. Carefully monitor the clinical response and blood glucose until the patient’s condition has stabilized satisfactory; in most instances, this may be accomplished in several days. If administration of PROGLYCEM is not effective after 2 or 3 weeks, discontinue PROGLYCEM.
Individualize the dosage of PROGLYCEM based on the severity of the hypoglycemic condition and the blood glucose level and clinical response of the patient. Adjust the dosage until the desired clinical and laboratory effects are produced with the least amount of PROGLYCEM. Take special care to ensure the accuracy of the dosage in infants and young children.
Adults and children: The recommended starting dosage is 3 mg/kg/day, administered orally, divided into 3 equal doses every 8 hours or 2 equal doses every 12 hours. The dosage may be titrated to a maximum of 8 mg/kg/day. Patients with refractory hypoglycemia may require higher dosages.
Infants and newborns: The recommended starting dosage is 8 mg/kg/day, administered orally, divided into 3 equal doses every 8 hours or 2 equal doses every 12 hours. The dosage may be titrated to a maximum of 15 mg/kg/day.
⛔ Contraindications ▾
CONTRAINDICATIONS PROGLYCEM is contraindicated in patients with: Functional hypoglycemia Hypersensitivity to diazoxide, any of the excipients in PROGLYCEM, or other thiazides
⚠️ Warnings ▾
WARNINGS The antidiuretic property of diazoxide may lead to significant fluid retention. In patients with compromised cardiac reserve, fluid retention may precipitate congestive heart failure. If fluid retention develops, manage according to standards of care.
Co-administration of PROGLYCEM with thiazides may potentiate the hyperglycemic and hyperuricemic actions of diazoxide (see DRUG INTERACTIONS and ANIMAL PHARMACOLOGY AND/OR TOXICOLOGY ). Ketoacidosis and nonketotic hyperosmolar coma have been reported in patients treated with PROGLYCEM, usually during intercurrent illness. Prompt recognition and treatment are essential (see OVERDOSAGE ), and prolonged surveillance following the acute episode is necessary because of the long drug half-life of approximately 30 hours.
Advise patients to monitor urine glucose and ketones and to promptly report abnormal findings and symptoms of ketoacidosis to their healthcare provider. Transient cataracts occurred in association with hyperosmolar coma in an infant, and subsided on correction of the hyper-osmolarity. Cataracts have been observed in several animals receiving daily dosages of intravenous or oral diazoxide.
The development of abnormal facial features in four children treated chronically (>4 years) with PROGLYCEM for hypoglycemia hyperinsulinism in the same clinic has been reported. Pulmonary Hypertension in Neonates and Infants There have been postmarketing reports of pulmonary hypertension occurring in infants and neonates treated with diazoxide. The cases were reversible upon discontinuation of diazoxide.
Monitor patients, especially those with risk factors for pulmonary hypertension, for respiratory distress and discontinue PROGLYCEM if pulmonary hypertension is suspected.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Frequent and Serious: Sodium and fluid retention is most common in young infants and in adults and may precipitate congestive heart failure in patients with compromised cardiac reserve (see DRUG INTERACTIONS ). Infrequent but Serious: Diabetic ketoacidosis and hyperosmolar nonketotic coma may develop very rapidly. Monitor patients for up to 7 days due to the long half-life of PROGLYCEM (see OVERDOSAGE ).
Other frequent adverse reactions: Hirsutism of the lanugo type, mainly on the forehead, back and limbs, occurs most commonly in children and women and may be cosmetically unacceptable. It subsides on discontinuation of PROGLYCEM. Hyperglycemia or glycosuria may require reduction in dosage in order to avoid progression to ketoacidosis or hyperosmolar coma.
Gastrointestinal intolerance may include anorexia, nausea, vomiting, abdominal pain, ileus, diarrhea, transient loss of taste. Tachycardia, palpitations, increased levels of serum uric acid are common. Thrombocytopenia with or without purpura may require discontinuation of PROGLYCEM.
Neutropenia is transient, is not associated with increased susceptibility to infection, and ordinarily does not require discontinuation of PROGLYCEM. Skin rash, headache, weakness, and malaise may also occur. Other adverse reactions: Cardiovascular: Hypotension occurs occasionally, which may be augmented by thiazide diuretics given concurrently.
A few cases of transient hypertension, for which no explanation is apparent, have been noted. Chest pain has been reported rarely. Pulmonary hypertension has been reported in neonates and young infants (see WARNINGS ).
There have been postmarketing reports of pericardial effusion in patients without structural heart disease; the majority of cases occurred in pediatric patients and infants. Gastrointestinal: There have been postmarketing reports of necrotizing enterocolitis; the majority of cases occurred in infants with underlying co-morbid conditions. Hematologic: eosinophilia; decreased hemoglobin / hematocrit; excessive bleeding, decreased IgG.
Hepato-renal: increased AST, alkaline phosphatase; azotemia, decreased creatinine clearance, reversible nephrotic syndrome, decreased urinary output, hematuria, albuminuria. Neurologic: anxiety, dizziness, insomnia, polyneuritis, paresthesia, pruritus, extrapyramidal signs. Ophthalmologic: transient cataracts, subconjunctival hemorrhage, ring scotoma, blurred vision, diplopia, lacrimation.
Skeletal, integumentary; monilial dermatitis, herpes, advance in bone age; loss of scalp hair. Systemic: fever, lymphadenopathy. Other; gout acute pancreatitis/pancreatic necrosis, galactorrhea, enlargement of lump in breast.
🔄 Drug Interactions ▾
Drug Interactions Since diazoxide is highly bound to serum proteins, it may displace other substances which are also bound to protein, such as bilirubin or coumarin and its derivatives, resulting in higher blood levels of these substances. Concomitant administration of PROGLYCEM and diphenylhydantoin may result in a loss of seizure control. Consider these potential interactions when administering PROGLYCEM.
The concomitant administration of thiazides or other diuretics may potentiate the hyperglycemic and hyperuricemic effects of PROGLYCEM.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions The hyperglycemic and hyperuricemic effects of diazoxide preclude proper assessment of these metabolic states. Increased renin secretion, IgG concentrations and decreased cortisol secretions have also been noted. Diazoxide inhibits glucagon-stimulated insulin release and causes a false-negative insulin response to glucagon.
🧒 Pediatric Use ▾
Pediatric Use See INDICATIONS AND USAGE .
🆘 Overdosage ▾
OVERDOSAGE An overdosage of PROGLYCEM causes marked hyperglycemia which may be associated with ketoacidosis. Because of the diazoxide’s long half-life (approximately 30 hours), the symptoms of overdosage require prolonged surveillance for periods up to 7 days until the blood glucose level stabilizes within the normal range. One investigator reported successful lowering of diazoxide blood levels by peritoneal dialysis in one patient and by hemodialysis in another.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY PROGLYCEM produces a dose-related increase in blood glucose, due primarily to an inhibition of insulin release from the pancreas, and also to an extrapancreatic effect. The hyperglycemic effect of PROGLYCEM begins within an hour and generally lasts no more than 8 hours in the presence of normal renal function. PROGLYCEM decreases the excretion of sodium and water, resulting in fluid retention which may be clinically significant.
The hypotensive effect of PROGLYCEM is usually not marked (see ADVERSE REACTIONS ). Other pharmacologic actions of PROGLYCEM include increased pulse rate; increased serum uric acid levels due to decreased excretion; increased serum levels of free fatty acids’ decreased chloride excretion; decreased para-aminohippuric acid; (PAH) clearance with no appreciable effect on glomerular filtration rate. The concomitant administration of a benzothiazide diuretic may intensify the hyperglycemic and hyperuricemic effects of PROGLYCEM.
In the presence of hypokalemia, hyperglycemic effects are also potentiated. PROGLYCEM-induced hyperglycemia is reversed by the administration of insulin or tolbutamide. The inhibition of insulin release by PROGLYCEM is antagonized by alpha-adrenergic blocking agents.
PROGLYCEM is extensively bound (more than 90%) to serum proteins and is excreted in the kidneys. The plasma half-life following intravenous administration is 28 ± 8.3 hours. Limited data on oral administration revealed a half-life of 24 and 36 hours in two adults.
In four children aged 4 months to 6 years, the plasma half-life varied from 9.5 to 24 hours on long-term oral administration. The half-life may be prolonged following overdosage, and in patients with impaired renal function.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED PROGLYCEM (diazoxide) oral suspension, 50 mg/mL, a chocolate-mint flavored suspension; bottle of 30 ml (NDC 0575-6200-30), with dropper calibrated to deliver 10, 20, 30, 40 and 50 mg diazoxide. Shake well before each use. Protect from light.
Store in carton until contents are used. Store in light resistant container as defined in the USP. Store PROGLYCEM at 25°C (77°F) excursions permitted to 15°C to 30°C (59°F to 86°F).
See USP Controlled Room Temperature. Manufactured for: Teva Pharmaceuticals Parsippany, NJ 07054 ©2024 Teva Pharmaceuticals USA, Inc. Rev.
7/2024 PRGM-003
📋 Description ▾
DESCRIPTION PROGLYCEM ® (diazoxide) oral suspension is a nondiuretic benzothiadiazine derivative taken orally for the management of symptomatic hypoglycemia. PROGLYCEM oral suspension contains 50 mg of diazoxide in each milliliter and has a chocolate-mint flavor; alcohol content is approximately 7.25%. Other ingredients include sorbitol solution, chocolate cream flavor, propylene glycol, magnesium aluminum silicate, carboxymethylcellulose sodium, mint flavor, sodium benzoate, methylparaben, poloxamer 188, propylparaben, and purified water.
Hydrochloric acid or sodium hydroxide may be added to adjust pH. Diazoxide has the following structural formula: Diazoxide is 7-chloro-3-methyl-2 H -1,2,4-benzothiadiazine 1,1-dioxide with the empirical formula C 8 H 7 ClN 2 O 2 S and the molecular weight 230.7. It is a white powder practically insoluble to sparingly soluble in water.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Advise patients of the need for periodic laboratory testing during treatment with PROGLYCEM. In addition, advise patients to: take PROGLYCEM on a regular schedule as prescribed, not to skip doses, not to take extra doses consult their healthcare provider before starting any new medications not allow anyone else to take this medication follow dietary instructions report any adverse reactions (i.e., increased urinary frequency, increased thirst, fruity breath odor) promptly to their healthcare provider report pregnancy or to discuss plans for pregnancy with their healthcare provider
⚠️ Precautions ▾
PRECAUTIONS General Treatment with PROGLYCEM should be initiated under close clinical supervision, with careful monitoring of blood glucose and clinical response until the patient’s condition has stabilized. This usually requires several days. If not effective in 2 to 3 weeks, discontinue PROGLYCEM.
Prolonged treatment requires regular monitoring of urine glucose and ketones, especially under stress conditions. Advise patients to promptly report any abnormalities to their healthcare provider. Periodically monitor blood glucose to determine the need for dosage adjustment.
Consider the effects of PROGLYCEM on the hematopoietic system and the level of serum uric acid; the latter should be considered particularly in patients with hyperuricemia or a history of gout. Since the plasma half-life of diazoxide is prolonged in patients with impaired renal function, a reduced dosage should be considered. Serum electrolyte levels should also be evaluated for such patients.
The antihypertensive effect of other drugs may be enhanced by PROGLYCEM, and this should be kept in mind when administering it concomitantly with antihypertensive agents. Because of the protein binding, administration of PROGLYCEM with coumarin anticoagulants or its derivatives may require reduction in the dosage of the anticoagulant, although there has been no reported evidence of excessive anticoagulant effect. In addition, PROGLYCEM may displace bilirubin from albumin; consider this when treating newborns with increased bilirubinemia.
Pulmonary hypertension has been reported in neonates and young infants treated with diazoxide (see WARNINGS ). Information for Patients Advise patients of the need for periodic laboratory testing during treatment with PROGLYCEM. In addition, advise patients to: take PROGLYCEM on a regular schedule as prescribed, not to skip doses, not to take extra doses consult their healthcare provider before starting any new medications not allow anyone else to take this medication follow dietary instructions report any adverse reactions (i.e., increased urinary frequency, increased thirst, fruity breath odor) promptly to their healthcare provider report pregnancy or to discuss plans for pregnancy with their healthcare provider Laboratory Tests Consider monitoring the following laboratory tests during treatment with PROGLYCEM (not all-inclusive): blood glucose (recommended at periodic intervals in patients taking diazoxide orally for treatment of hypoglycemia, until stabilized) blood urea nitrogen (BUN) and creatinine clearance hematocrit, platelet count, total and differential leukocyte counts serum aspartate aminotransferase (AST) serum uric acid level urine testing for glucose and ketones Drug Interactions Since diazoxide is highly bound to serum proteins, it may displace other substances which are also bound to protein, such as bilirubin or coumarin and its derivatives, resulting in higher blood levels of these substances.
Concomitant administration of PROGLYCEM and diphenylhydantoin may result in a loss of seizure control. Consider these potential interactions when administering PROGLYCEM. The concomitant administration of thiazides or other diuretics may potentiate the hyperglycemic and hyperuricemic effects of PROGLYCEM.
Drug/Laboratory Test Interactions The hyperglycemic and hyperuricemic effects of diazoxide preclude proper assessment of these metabolic states. Increased renin secretion, IgG concentrations and decreased cortisol secretions have also been noted. Diazoxide inhibits glucagon-stimulated insulin release and causes a false-negative insulin response to glucagon.
Carcinogenesis, Mutagenesis, Impairment of Fertility No long-term animal dosing study has been done to evaluate the carcinogenic potential of diazoxide. No laboratory study of mutagenic potential or animal study of effects on fertility has been done. Reproduction studies using the oral preparation in rats have revealed increased fetal resorptions and delayed parturition, as… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Information is not available concerning the passage of diazoxide in breast milk. Because many drugs are excreted in human milk and because of the potential for adverse reactions from diazoxide in nursing infants, a decision should be made whether to discontinue nursing or to discontinue PROGLYCEM, taking into account the importance of the use of PROGLYCEM in the mother.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility No long-term animal dosing study has been done to evaluate the carcinogenic potential of diazoxide. No laboratory study of mutagenic potential or animal study of effects on fertility has been done. Reproduction studies using the oral preparation in rats have revealed increased fetal resorptions and delayed parturition, as well as fetal skeletal anomalies; evidence of skeletal and cardiac teratogenic effects in rabbits has been noted with intravenous administration.
Diazoxide has also been demonstrated to cross the placental barrier in animals and to cause degeneration of the fetal pancreatic beta cells (see ANIMAL PHARMACOLOGY AND/OR TOXICOLOGY ). Since there are no adequate data on fetal effects of this drug when given to pregnant women, safety in pregnancy has not been established. When the use of PROGLYCEM is considered, the indications should be limited to those specified above for adults (see INDICATIONS AND USAGE ), and the potential benefits to the mother must be weighed against possible harmful effects to the fetus.
📄 Package Label / Principal Display Panel ▾
Package/Label Display Panel NDC 0575-6200-30 30 mL Proglycem (diazoxide, USP) ORAL SUSPENSION 50 mg per mL Rx Only TEVA Proglycem Carton