
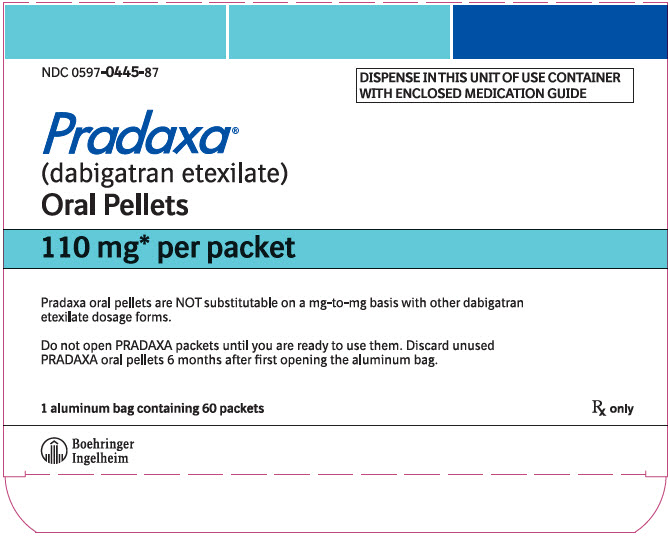
Pradaxa dabigatran etexilate 110 mg Pellet, 60-count
Other active recalls for Dabigatran Etexilate (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Direct thrombin inhibitors class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's a blood thinner — its main jobs are to reduce your risk of stroke if you have atrial fibrillation (an irregular heartbeat), to treat or prevent dangerous blood clots in your v...
- What exactly is dabigatran etexilate used for?
- No — please don't. Opening, breaking, or chewing the capsule releases the pellets inside in a way the body absorbs about 75% more drug than it should. That raises your risk of seri...
- Can I open or crush the capsule if I have trouble swallowing it?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5C5403N26O
Acacia is a natural gum derived from acacia tree sap. It serves as a binder, thickener, and emulsifier to help hold ingredients together, improve texture, and stabilize the medicine.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII W4888I119H
Tartaric acid is a natural organic acid found in grapes and tamarinds. In medicines, it works as a buffer to control acidity, an antioxidant to prevent spoilage, and sometimes a flavoring or binding agent.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Pradaxa 110 mgthis 00597-0445-87 | Boehringer | 60 pellets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7932273 ↗ | Drug substance | — | Sep 7, 2025 |
| US 7932273 ↗ | Drug substance | — | Sep 7, 2025 |
| US 7932273 ↗ | Drug substance | — | Sep 7, 2025 |
| US 7932273 ↗ | Drug substance | — | Sep 7, 2025 |
| US 7932273 ↗ | Drug substance | — | Sep 7, 2025 |
| US 7932273 ↗ | Drug substance | — | Sep 7, 2025 |
| US 7932273*PED ↗ | Drug product | — | Mar 7, 2026 |
| US 7932273*PED ↗ | Drug product | — | Mar 7, 2026 |
| US 7932273*PED ↗ | Drug product | — | Mar 7, 2026 |
| US 7932273*PED ↗ | Drug product | — | Mar 7, 2026 |
| US 7932273*PED ↗ | Drug product | — | Mar 7, 2026 |
| US 7932273*PED ↗ | Drug product | — | Mar 7, 2026 |
Is there a generic version of PRADAXA 110 MG PELLET PACK?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00597-0445-87 You're viewing this | 1 BAG in 1 CARTON (0597-0445-87) / 60 PELLET in 1 BAG | 2022-03-16 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: (A) PREMATURE DISCONTINUATION OF PRADAXA INCREASES THE RISK OF THROMBOTIC EVENTS, and (B) SPINAL/EPIDURAL HEMATOMA WARNING: (A) PREMATURE DISCONTINUATION OF PRADAXA INCREASES THE RISK OF THROMBOTIC EVENTS, and (B) SPINAL/EPIDURAL HEMATOMA See full prescribing information for complete boxed warning (A) PREMATURE DISCONTINUATION OF PRADAXA INCREASES THE RISK OF THROMBOTIC EVENTS: Premature discontinuation of any oral anticoagulant, including PRADAXA, increases the risk of thrombotic events. To reduce this risk, consider coverage with another anticoagulant if PRADAXA is discontinued for a reason other than pathological bleeding or completion of a course of therapy ( 2.5 , 2.6 , 2.7 , 5.1 ).
(B) SPINAL/EPIDURAL HEMATOMA: Epidural or spinal hematomas may occur in patients treated with PRADAXA who are receiving neuraxial anesthesia or undergoing spinal puncture. These hematomas may result in long-term or permanent paralysis ( 5.3 ). Monitor patients frequently for signs and symptoms of neurological impairment and if observed, treat urgently.
Consider the benefits and risks before neuraxial intervention in patients who are or who need to be anticoagulated ( 5.3 ). (A) PREMATURE DISCONTINUATION OF PRADAXA INCREASES THE RISK OF THROMBOTIC EVENTS Premature discontinuation of any oral anticoagulant, including PRADAXA, increases the risk of thrombotic events. If anticoagulation with PRADAXA is discontinued for a reason other than pathological bleeding or completion of a course of therapy, consider coverage with another anticoagulant [see Dosage and Administration (2.5 , 2.6 , 2.7) and Warnings and Precautions (5.1) ].
(B) SPINAL/EPIDURAL HEMATOMA Epidural or spinal hematomas may occur in patients treated with PRADAXA who are receiving neuraxial anesthesia or undergoing spinal puncture. These hematomas may result in long-term or permanent paralysis. Consider these risks when scheduling patients for spinal procedures.
Factors that can increase the risk of developing epidural or spinal hematomas in these patients include: use of indwelling epidural catheters concomitant use of other drugs that affect hemostasis, such as non-steroidal anti-inflammatory drugs (NSAIDs), platelet inhibitors, other anticoagulants a history of traumatic or repeated epidural or spinal punctures a history of spinal deformity or spinal surgery optimal timing between the administration of PRADAXA and neuraxial procedures is not known [see Warnings and Precautions (5.3) ].
Monitor patients frequently for signs and symptoms of neurological impairment. If neurological compromise is noted, urgent treatment is necessary [see Warnings and Precautions (5.3) ]. Consider the benefits and risks before neuraxial intervention in patients anticoagulated or to be anticoagulated [see Warnings and Precautions (5.3) ].
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE PRADAXA Oral Pellets are a direct thrombin inhibitor indicated: For the treatment of venous thromboembolic events (VTE) in pediatric patients aged 3 months to less than 12 years of age who have been treated with a parenteral anticoagulant for at least 5 days ( 1.1 ) To reduce the risk of recurrence of VTE in pediatric patients aged 3 months to less than 12 years of age who have been previously treated ( 1.2 )
1.1Treatment of Venous Thromboembolic Events in Pediatric Patients PRADAXA Oral Pellets are indicated for the treatment of venous thromboembolic events (VTE) in pediatric patients aged 3 months to less than 12 years of age who have been treated with a parenteral anticoagulant for at least 5 days.
1.2Reduction in the Risk of Recurrence of Venous Thromboembolic Events in Pediatric Patients PRADAXA Oral Pellets are indicated to reduce the risk of recurrence of VTE in pediatric patients aged 3 months to less than 12 years of age who have been previously treated.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Treatment of Pediatric Venous Thromboembolic Events (VTE): For pediatric patients aged 3 months to less than 2 years: age- and weight-based dosage, twice daily after at least 5 days of parenteral anticoagulant ( 2.2 ) For pediatric patients 2 years to less than 12 years: weight-based dosage, twice daily after at least 5 days of parenteral anticoagulant ( 2.2 ) Reduction in the Risk of Recurrence of Pediatric VTE: For pediatric patients aged 3 months to less than 2 years: age- and weight-based dosage, twice daily after previous treatment ( 2.2 ) For pediatric patients aged 2 years to less than 12 years: weight-based dosage, twice daily after previous treatment ( 2.2 ) Pradaxa Oral Pellets are NOT substitutable on a milligram-to-milligram basis with other dabigatran etexilate dosage forms ( 2.1 ) Review recommendations for converting to or from other oral or parenteral anticoagulants ( 2.5 , 2.6 ) Temporarily discontinue PRADAXA before invasive or surgical procedures when possible, then restart promptly ( 2.7 )
2.1Important Dosage Information Dabigatran etexilate is available in different dosage forms and not all dosage forms are approved for the same indications and age groups. In addition, there are differences between the dosage forms with respect to dosing due to differences in bioavailability. Do not substitute different dosage forms (for example, capsules) for oral pellets on a milligram-to-milligram basis and do not combine more than one dosage form to achieve the total dose [see Clinical Pharmacology (12.3) ] .
2.2Recommended PRADAXA Oral Pellets Dosage for Pediatric Patients PRADAXA Oral Pellets can be used in pediatric patients aged 3 months to less than 12 years as soon as they are able to swallow soft food. For the treatment of VTE in pediatric patients, treatment should be initiated following treatment with a parenteral anticoagulant for at least 5 days. For reduction in risk of recurrence of VTE, treatment should be initiated following previous treatment.
The recommended dosage of PRADAXA Oral Pellets is based on the patient's age and actual weight as shown in the tables below. PRADAXA Oral Pellets is administered twice daily. Adjust the dosage according to age and actual weight as treatment progresses.
Table 1 Age- and Weight-Based Dosage for PRADAXA Oral Pellets for Pediatric Patients less than 2 Years Old Actual Weight (kg) Age (in months) Dosage (mg) twice daily Number of Packets Needed 3 kg to less than 4 kg 3 to less than 6 months 30 mg one 30 mg packet twice daily 4 kg to less than 5 kg 3 to less than 10 months 40 mg one 40 mg packet twice daily 5 kg to less than 7 kg 3 to less than 5 months 40 mg one 40 mg packet twice daily 5 to less than 24 months 50 mg one 50 mg packet twice daily 7 kg to less than 9 kg 3 to less than 4 months 50 mg one 50 mg packet twice daily 4 to less than 9 months 60 mg two 30 mg packets twice daily 9 to less than 24 months 70 mg one 30 mg packet plus one 40 mg packet twice daily 9 kg to less than 11 kg 5 to less than 6 months 60 mg two 30 mg packets twice daily 6 to less than 11 months 80 mg two 40 mg packets twice daily 11 to less than 24 months 90 mg one 40 mg packet plus one 50 mg packet twice daily 11 kg to less than 13 kg 8 to less than 18 months 100 mg two 50 mg packets twice daily 18 to less than 24 months 110 mg one 110 mg packet twice daily 13 kg to less than 16 kg 10 to less than 11 months 100 mg two 50 mg packets twice daily 11 to less than 24 months 140 mg one 30 mg packet plus one 110 mg packet twice daily 16 kg to less than 21 kg 12 to less than 24 months 140 mg one 30 mg packet plus one 110 mg packet twice daily 21 kg to less than 26 kg 18 to less than 24 months 180 mg one 30 mg packet plus one 150 mg packet twice daily Table 2 Weight-Based Dosage for PRADAXA Oral Pellets for Pediatric Patients between 2 Years to less than 12 Years Old Actual Weight (kg) Dosage (mg) twice daily Number of Packets Needed 7 kg to less than 9 kg 70 mg one 30…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS PRADAXA Oral Pellets are available in the following strengths: 20 mg yellowish pellets in a packet 30 mg yellowish pellets in a packet 40 mg yellowish pellets in a packet 50 mg yellowish pellets in a packet 110 mg yellowish pellets in a packet 150 mg yellowish pellets in a packet Oral pellets: 20 mg, 30 mg, 40 mg, 50 mg, 110 mg, 150 mg per packet ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS PRADAXA is contraindicated in patients with: Active pathological bleeding [see Warnings and Precautions (5.2) and Adverse Reactions (6.1) ] History of a serious hypersensitivity reaction to dabigatran, dabigatran etexilate, or to one of the excipients of the product (e.g., anaphylactic reaction or anaphylactic shock) [see Adverse Reactions (6.1) ] Mechanical prosthetic heart valve [see Warnings and Precautions (5.4) ] Active pathological bleeding ( 4 ) History of serious hypersensitivity reaction to PRADAXA ( 4 ) Mechanical prosthetic heart valve ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Bleeding: PRADAXA can cause serious and fatal bleeding ( 5.2 ) Bioprosthetic heart valves: PRADAXA use not recommended ( 5.4 ) Increased Risk of Thrombosis in Patients with Triple-Positive Antiphospholipid Syndrome: PRADAXA use not recommended ( 5.6 )
5.1Increased Risk of Thrombotic Events after Premature Discontinuation Premature discontinuation of any oral anticoagulant, including PRADAXA, in the absence of adequate alternative anticoagulation increases the risk of thrombotic events. If PRADAXA Oral Pellets are discontinued for a reason other than pathological bleeding or completion of a course of therapy, consider coverage with another anticoagulant and restart PRADAXA Oral Pellets as soon as medically appropriate [see Dosage and Administration (2.5 , 2.6 , 2.7) ].
5.2Risk of Bleeding PRADAXA increases the risk of bleeding and can cause significant and, sometimes, fatal bleeding. Promptly evaluate any signs or symptoms of blood loss (e.g., a drop in hemoglobin and/or hematocrit or hypotension). Discontinue PRADAXA Oral Pellets in patients with active pathological bleeding [see Dosage and Administration (2.2) ].
Risk factors for bleeding include the concomitant use of other drugs that increase the risk of bleeding (e.g., anti-platelet agents, heparin, fibrinolytic therapy, and chronic use of NSAIDs). PRADAXA's anticoagulant activity and half-life are increased in patients with renal impairment [see Clinical Pharmacology (12.2) ]. Reversal of Anticoagulant Effect Hemodialysis can remove dabigatran; however the clinical experience supporting the use of hemodialysis as a treatment for bleeding is limited [see Overdosage (10) ] .
Prothrombin complex concentrates or recombinant Factor VIIa may be considered but their use has not been evaluated in clinical trials. Protamine sulfate and vitamin K are not expected to affect the anticoagulant activity of dabigatran. Consider administration of platelet concentrates in cases where thrombocytopenia is present or long-acting antiplatelet drugs have been used.
In adults, a specific reversal agent (idarucizumab) for PRADAXA is available when reversal of the anticoagulant effect of dabigatran is needed. In pediatric patients, the efficacy and safety of idarucizumab have not been established.
5.3Spinal/Epidural Anesthesia or Puncture When neuraxial anesthesia (spinal/epidural anesthesia) or spinal puncture is employed, patients treated with anticoagulant agents are at risk of developing an epidural or spinal hematoma which can result in long-term or permanent paralysis [see Boxed Warning ] . To reduce the potential risk of bleeding associated with the concurrent use of PRADAXA and epidural or spinal anesthesia/analgesia or spinal puncture, consider the pharmacokinetic profile of dabigatran [see Clinical Pharmacology (12.3) ] .
Placement or removal of an epidural catheter or lumbar puncture is best performed when the anticoagulant effect of dabigatran is low; however, the exact timing to reach a sufficiently low anticoagulant effect in each patient is not known. Should the physician decide to administer anticoagulation in the context of epidural or spinal anesthesia/analgesia or lumbar puncture, monitor frequently to detect any signs or symptoms of neurological impairment, such as midline back pain, sensory and motor deficits (numbness, tingling, or weakness in lower limbs), and bowel and/or bladder dysfunction.
Instruct patients to immediately report if they experience any of the above signs or symptoms. If signs or symptoms of spinal hematoma are suspected, initiate urgent diagnosis and treatment including consideration for spinal cord decompression even though such treatment may not prevent or reverse neurological sequelae.
5.4Thromboembolic and Bleeding Events in Patients with Prosthetic Heart Valves The safety and efficacy of PRADAXA Capsules in adult patients with bileaflet mechanical prosthetic heart valves was evaluated in the RE-ALIGN trial, in which pa…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Increased Risk of Thrombotic Events after Premature Discontinuation [see Warnings and Precautions (5.1) ] Risk of Bleeding [see Warnings and Precautions (5.2) ] Spinal/Epidural Anesthesia or Puncture [see Warnings and Precautions (5.3) ] Thromboembolic and Bleeding Events in Patients with Prosthetic Heart Valves [see Warnings and Precautions (5.4) ] Increased Risk of Thrombosis in Patients with Triple-Positive Antiphospholipid Syndrome [see Warnings and Precautions (5.6) ] The most serious adverse reactions reported with PRADAXA were related to bleeding [see Warnings and Precautions (5.2) ] .
Most common adverse reactions (> 15%) are gastrointestinal adverse reactions and bleeding. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at (800) 542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reactions rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Pediatric Trials Treatment of VTE in Pediatric Patients The safety of PRADAXA in the treatment of VTE in pediatric patients was studied in one phase III trial (DIVERSITY). The DIVERSITY study was a randomized, open-label, active-controlled, parallel-group trial comparing PRADAXA with standard of care – SOC (vitamin K antagonists, low molecular weight heparin, or fondaparinux).
There were 266 pediatric patients who received study treatment, 176 patients treated with PRADAXA and 90 patients treated with SOC. Patients on PRADAXA received age- and weight-adjusted dosages of an age-appropriate formulation of PRADAXA (capsules, pellets, or oral solution) twice daily. Patients had a median age of 14 years (range: 0-17 years), 92% were white, and half the patients were male (50%).
Following at least 5 days of parenteral anticoagulant therapy, the median duration of treatment with PRADAXA was 85 days (range: 1-105). Patients with estimated glomerular filtration rate (eGFR) < 50 mL/min/1.73 m 2 were excluded from the trial. Bleeding Data on adjudicated major bleeding, clinically relevant non-major (CRNM) bleeding, and minor bleeding events for the PRADAXA group and the SOC group in the DIVERSITY study are reported in Table 3.
There was no statistically significant difference in the time to first major bleeding event. Table 3 Summary of All Adjudicated Bleeding Events During On-Treatment Period in DIVERSITY PRADAXA N (%) Standard of Care (SOC) N (%) Patients N=176 N=90 1 Major bleeding event if at least one of the following criteria applied: fatal bleeding, symptomatic bleeding in a critical area or organ (intraocular, intracranial, intraspinal or intramuscular with compartment syndrome, retroperitoneal bleeding, intra-articular bleeding, or pericardial bleeding), bleeding causing a fall in hemoglobin level of 2.0 g/dL (1.24 mmol/L) or more, or leading to transfusion of 2 or more units of whole blood or red cells.
Major bleeding event 1 4 (2.3) 2 (2.2) Fatal bleeding 0 1 (1.1) Clinically relevant non-major bleeding 2 (1.1) 1 (1.1) Minor bleeding 33 (19) 21 (23) Major and clinically relevant non-major bleeding 6 (3.4) 3 (3.3) Any bleeding 38 (22) 22 (24) Site-specific bleeding rates were comparable between the two arms, with the exception of the rate of any gastrointestinal bleeds (5.7% in PRADAXA arm vs 1.8% in SOC arm). Gastrointestinal Adverse Reactions The incidence of gastrointestinal adverse reactions for patients on PRADAXA and SOC was 32% and 12%, respectively, with the following occurring in ≥ 5% of patients taking PRADAXA: dyspepsia (including term gastro-esophageal reflux disease, gastric pH decreased and esophagitis) in 9% (vs 2%), upper abdominal pain in 5% (vs 1%), vomiting in 8%…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The concomitant use of PRADAXA with P-gp inhibitors has not been studied in pediatric patients but may increase exposure to dabigatran [see Warnings and Precautions (5.5) ] . P-gp inducers: Avoid coadministration with PRADAXA ( 5.5 ) The concomitant use of PRADAXA with P-gp inhibitors has not been studied in pediatric patients but may increase exposure to dabigatran ( 5.5 , 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding not recommended ( 8.2 )
8.1Pregnancy Risk Summary The limited available data on PRADAXA use in pregnant women are insufficient to determine drug-associated risks for adverse developmental outcomes. There are risks to the mother associated with untreated venous thromboembolism in pregnancy and a risk of hemorrhage in the mother and fetus associated with the use of anticoagulants (see Clinical Considerations ) . In pregnant rats treated from implantation until weaning, dabigatran increased the number of dead offspring and caused excess vaginal/uterine bleeding close to parturition at an exposure 2.6 times the human exposure.
At a similar exposure, dabigatran decreased the number of implantations when rats were treated prior to mating and up to implantation (gestation Day 6). Dabigatran administered to pregnant rats and rabbits during organogenesis up to exposures 8 and 13 times the human exposure, respectively, did not induce major malformations. However, the incidence of delayed or irregular ossification of fetal skull bones and vertebrae was increased in the rat (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high-risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy. Fetal/Neonatal adverse reaction Use of anticoagulants, including PRADAXA, may increase the risk of bleeding in the fetus and neonate.
Monitor neonates for bleeding [see Warnings and Precautions (5.2) ]. Labor or delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. PRADAXA use during labor or delivery in women who are receiving neuraxial anesthesia may result in epidural or spinal hematomas.
Consider discontinuation or use of shorter acting anticoagulant as delivery approaches [see Warnings and Precautions (5.2 , 5.3) ] . Data Animal Data Dabigatran has been shown to decrease the number of implantations when male and female rats were treated at a dosage of 70 mg/kg (about 2.6 to 3.0 times the human exposure at MRHD of 300 mg/day based on area under the curve [AUC] comparisons) prior to mating and up to implantation (gestation Day 6). Treatment of pregnant rats after implantation with dabigatran at the same dose increased the number of dead offspring and caused excess vaginal/uterine bleeding close to parturition.
Dabigatran administered to pregnant rats and rabbits during organogenesis up to maternally toxic doses of 200 mg/kg (8 and 13 times the human exposure, respectively, at a MRHD of 300 mg/day based on AUC comparisons) did not induce major malformations, but increased the incidence of delayed or irregular ossification of fetal skull bones and vertebrae in the rat. Death of offspring and mother rats during labor in association with uterine bleeding occurred during treatment of pregnant rats from implantation (gestation Day 7) to weaning (lactation Day 21) with dabigatran at a dose of 70 mg/kg (about 2.6 times the human exposure at MRHD of 300 mg/day based on AUC comparisons).
8.2Lactation Risk Summary There are insufficient data to assess the presence of dabigatran in human milk. There are no data on the effects of dabigatran on the breastfed child or on milk production. Dabigatran and/or its metabolites were present in rat milk. Breastfeeding is not recommended during treatment with PRADAXA.
8.3 Females and Males of Repr…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited available data on PRADAXA use in pregnant women are insufficient to determine drug-associated risks for adverse developmental outcomes. There are risks to the mother associated with untreated venous thromboembolism in pregnancy and a risk of hemorrhage in the mother and fetus associated with the use of anticoagulants (see Clinical Considerations ) . In pregnant rats treated from implantation until weaning, dabigatran increased the number of dead offspring and caused excess vaginal/uterine bleeding close to parturition at an exposure 2.6 times the human exposure.
At a similar exposure, dabigatran decreased the number of implantations when rats were treated prior to mating and up to implantation (gestation Day 6). Dabigatran administered to pregnant rats and rabbits during organogenesis up to exposures 8 and 13 times the human exposure, respectively, did not induce major malformations. However, the incidence of delayed or irregular ossification of fetal skull bones and vertebrae was increased in the rat (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high-risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy. Fetal/Neonatal adverse reaction Use of anticoagulants, including PRADAXA, may increase the risk of bleeding in the fetus and neonate.
Monitor neonates for bleeding [see Warnings and Precautions (5.2) ]. Labor or delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. PRADAXA use during labor or delivery in women who are receiving neuraxial anesthesia may result in epidural or spinal hematomas.
Consider discontinuation or use of shorter acting anticoagulant as delivery approaches [see Warnings and Precautions (5.2 , 5.3) ] . Data Animal Data Dabigatran has been shown to decrease the number of implantations when male and female rats were treated at a dosage of 70 mg/kg (about 2.6 to 3.0 times the human exposure at MRHD of 300 mg/day based on area under the curve [AUC] comparisons) prior to mating and up to implantation (gestation Day 6). Treatment of pregnant rats after implantation with dabigatran at the same dose increased the number of dead offspring and caused excess vaginal/uterine bleeding close to parturition.
Dabigatran administered to pregnant rats and rabbits during organogenesis up to maternally toxic doses of 200 mg/kg (8 and 13 times the human exposure, respectively, at a MRHD of 300 mg/day based on AUC comparisons) did not induce major malformations, but increased the incidence of delayed or irregular ossification of fetal skull bones and vertebrae in the rat. Death of offspring and mother rats during labor in association with uterine bleeding occurred during treatment of pregnant rats from implantation (gestation Day 7) to weaning (lactation Day 21) with dabigatran at a dose of 70 mg/kg (about 2.6 times the human exposure at MRHD of 300 mg/day based on AUC comparisons).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of PRADAXA Oral Pellets for the treatment and the reduction in risk of recurrence of venous thromboembolism have been established in pediatric patients less than 12 years of age. Use of PRADAXA Oral Pellets for this indication is supported by evidence from adequate and well-controlled studies in pediatric patients. These studies included an open-label, randomized, parallel-group study and an open-label, single-arm safety study [see Adverse Reactions (6.1) and Clinical Studies (14.1 , 14.2) ] .
Other age-appropriate pediatric formulations of dabigatran etexilate are available for pediatric patients aged 12 years and older for these indications. Safety and effectiveness of PRADAXA have not been established in pediatric patients with non-valvular atrial fibrillation or those who have undergone hip replacement surgery.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of PRADAXA Oral Pellets did not include patients 65 years of age and older. Information on the use of PRADAXA Capsules in geriatric patients is available in that prescribing information.
🆘 Overdosage ▾
10 OVERDOSAGE Accidental overdose may lead to hemorrhagic complications. In the event of hemorrhagic complications, initiate appropriate clinical support, discontinue treatment with PRADAXA, and investigate the source of bleeding. A specific reversal agent (idarucizumab) is available for adult patients.
Dabigatran is primarily eliminated by the kidneys with a low plasma protein binding of approximately 35%. Hemodialysis can remove dabigatran; however, data supporting this approach are limited. Using a high-flux dialyzer, blood flow rate of 200 mL/min, and dialysate flow rate of 700 mL/min, approximately 49% of total dabigatran can be cleared from plasma over 4 hours.
At the same dialysate flow rate, approximately 57% can be cleared using a dialyzer blood flow rate of 300 mL/min, with no appreciable increase in clearance observed at higher blood flow rates. Upon cessation of hemodialysis, a redistribution effect of approximately 7% to 15% is seen. The effect of dialysis on dabigatran's plasma concentration would be expected to vary based on patient specific characteristics.
Measurement of aPTT or ECT may help guide therapy [see Warnings and Precautions (5.2) and Clinical Pharmacology (12.2) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Dabigatran and its acyl glucuronides are competitive, direct thrombin inhibitors. Because thrombin (serine protease) enables the conversion of fibrinogen into fibrin during the coagulation cascade, its inhibition prevents the development of a thrombus. Both free and clot-bound thrombin, and thrombin-induced platelet aggregation are inhibited by the active moieties.
12.2Pharmacodynamics At recommended therapeutic doses, dabigatran etexilate prolongs the coagulation markers such as aPTT, ECT, TT, and dTT. INR is relatively insensitive to the exposure to dabigatran and cannot be interpreted the same way as used for warfarin monitoring. As in adults, there is a correlation between plasma dabigatran concentrations and the degree of its anticoagulant effect in pediatric patients with venous thromboembolism.
The parameters dTT and ECT increased in direct linear proportion to the plasma concentration of dabigatran, whereas aPTT prolongation increases in a nonlinear fashion with dabigatran plasma concentrations. Similar PK/PD relationships for aPTT, ECT and dTT were observed across age groups of pediatric patients (ages 26 days to < 18 years) and between pediatric and adult patients with venous thromboembolism. This similarity in PK/PD relationship suggests that similar exposure-response relationship is expected for dabigatran etexilate treatment across the pediatric age groups and adult patients.
Cardiac Electrophysiology No prolongation of the QTc interval was observed with dabigatran etexilate at doses up to 600 mg.
12.3Pharmacokinetics Dabigatran etexilate mesylate is absorbed as the dabigatran etexilate ester. The ester is then hydrolyzed, forming dabigatran, the active moiety. Dabigatran is metabolized to four different acyl glucuronides and both the glucuronides and dabigatran have similar pharmacological activity.
Pharmacokinetics described here refer to the sum of dabigatran and its glucuronides. Dabigatran displays dose-proportional pharmacokinetics in healthy adult subjects and adult patients in the range of doses from 10 mg to 400 mg. Given twice daily, dabigatran's accumulation factor in pediatric patients receiving pellets is 1.5-1.7.
Absorption The absolute bioavailability of dabigatran following oral administration of dabigatran etexilate is approximately 3% to 7%. Dabigatran etexilate is a substrate of the efflux transporter P-gp. After oral administration of dabigatran etexilate in healthy volunteers, C max occurs at 1 hour post-administration in the fasted state.
Coadministration of PRADAXA with a high-fat meal delays the time to C max by approximately 2 hours but has no effect on the bioavailability of dabigatran; PRADAXA may be administered with or without food. PRADAXA is available in Capsules and Oral Pellets. The approved indications and intended age groups are not the same.
Oral absorption of dabigatran etexilate is formulation-dependent. Dabigatran etexilate oral pellets show 37% higher relative bioavailability in healthy adults compared to dabigatran etexilate capsules. In addition, the relative bioavailability between the two dosage forms is age dependent.
The relative bioavailability observed in adult patients cannot be translated to pediatric patients. Distribution Dabigatran is approximately 35% bound to human plasma proteins. The red blood cell to plasma partitioning of dabigatran measured as total radioactivity is less than 0.3.
The volume of distribution of dabigatran is 50 to 70 L. Elimination Dabigatran is eliminated primarily in the urine. Renal clearance of dabigatran is 80% of total clearance after intravenous administration.
After oral administration of radiolabeled dabigatran, 7% of radioactivity is recovered in urine and 86% in feces. The elimination half-life of dabigatran in pediatric patients receiving pellets is approximately 9 to 11 hours. Metabolism After oral administration, dabigatran etexilate is converted to dabigatran.
The cleavage…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Dabigatran and its acyl glucuronides are competitive, direct thrombin inhibitors. Because thrombin (serine protease) enables the conversion of fibrinogen into fibrin during the coagulation cascade, its inhibition prevents the development of a thrombus. Both free and clot-bound thrombin, and thrombin-induced platelet aggregation are inhibited by the active moieties.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING PRADAXA Oral Pellets are yellowish in a silver-colored, child-resistant packet. The packets are placed in an aluminum bag with a desiccant. PRADAXA Oral Pellets are supplied as follows: Strength Package NDC 20 mg unit of use carton with 1 aluminum bag containing 60 packets 0597-0425-78 30 mg unit of use carton with 1 aluminum bag containing 60 packets 0597-0430-18 40 mg unit of use carton with 1 aluminum bag containing 60 packets 0597-0435-96 50 mg unit of use carton with 1 aluminum bag containing 60 packets 0597-0440-53 110 mg unit of use carton with 1 aluminum bag containing 60 packets 0597-0445-87 150 mg unit of use carton with 1 aluminum bag containing 60 packets 0597-0450-16 Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Store in the original package to protect from moisture. Do not open the packets until ready for use. Use the PRADAXA Oral Pellets within 6 months of opening the aluminum bag containing the packets.
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store in the original package to protect from moisture. Do not open the packets until ready for use. Use the PRADAXA Oral Pellets within 6 months of opening the aluminum bag containing the packets.
📋 Description ▾
11 DESCRIPTION PRADAXA Oral Pellets contain dabigatran etexilate mesylate, a direct thrombin inhibitor. The chemical name of dabigatran etexilate mesylate is β-Alanine, N-[[2-[[[4-[[[(hexyloxy)carbonyl]amino]iminomethyl] phenyl]amino]methyl]-1-methyl-1H-benzimidazol-5-yl]carbonyl]-N-2-pyridinyl-,ethyl ester, methanesulfonate and it has a molecular formula of C 34 H 41 N 7 O 5 ∙ CH 4 O 3 S and molecular weight of 723.86 for the mesylate salt and 627.75 for the free base. The structural formula is: Dabigatran etexilate mesylate is a yellow-white to yellow powder.
It is freely soluble in methanol, slightly soluble in ethanol, and sparingly soluble in isopropanol. A saturated solution in pure water has a solubility of 1.8 mg/mL. Each packet of PRADAXA Oral Pellets contains 20 mg, 30 mg, 40 mg, 50 mg, 110 mg, or 150 mg dabigatran etexilate (equivalent to 23.06 mg, 34.59 mg, 46.12 mg, 57.65 mg, 126.83 mg, or 172.95 mg dabigatran etexilate mesylate) along with the following inactive ingredients: acacia, dimethicone, hydroxypropyl cellulose, hypromellose, talc, and tartaric acid.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient or caregiver to read the FDA-approved patient labeling (Medication Guide and Instruction for Use). Instructions for Patients Tell patients or their caregivers to take or administer PRADAXA Oral Pellets exactly as prescribed. Tell patients or their caregivers to remove desiccant from the aluminum bag and throw away.
Remind patients or their caregivers not to discontinue PRADAXA Oral Pellets without talking to the healthcare provider who prescribed it. Provide the following instructions on administration to the patients or caregivers: Take the prescribed dosage of PRADAXA Oral Pellets twice a day, approximately 12 hours apart; PRADAXA Oral Pellets may be sprinkled on mashed carrots, apple sauce, or mashed banana, or may be taken with approximately 1-2 ounces of apple juice; PRADAXA Oral Pellets should not be mixed with milk or with foods that contain milk; Once the PRADAXA Oral Pellets are mixed with the soft food or apple juice, the patient should take the dose within 30 minutes; If a dose of PRADAXA Oral Pellets is not taken at the scheduled time, the dose should be skipped if it cannot be taken at least 6 hours before the next scheduled dose.
The dose of PRADAXA Oral Pellets should not be doubled to make up for a missed dose. [see Boxed Warning , and Dosage and Administration (2.2 , 2.4) ] Bleeding Inform patients or their caregivers that they may bleed more easily, may bleed longer, and should call their healthcare provider for any signs or symptoms of bleeding [see Warnings and Precautions (5.2) ] . Instruct patients or their caregivers to seek emergency care right away if they have any of the following, which may be a sign or symptom of serious bleeding: Unusual bruising (bruises that appear without known cause or that get bigger) Pink or brown urine Red or black, tarry stools Coughing up blood Vomiting blood, or vomit that looks like coffee grounds Instruct patients or their caregivers to call their healthcare provider or to get prompt medical attention if they experience any signs or symptoms of bleeding: Pain, swelling or discomfort in a joint Headaches, dizziness, or weakness Reoccurring nose bleeds Unusual bleeding from gums Bleeding from a cut that takes a long time to stop Menstrual bleeding or vaginal bleeding that is heavier than normal If patients have had neuraxial anesthesia or spinal puncture, and particularly, if they are taking concomitant NSAIDs or platelet inhibitors, advise patients or their caregivers to watch for signs and symptoms of spinal or epidural hematoma, such as back pain, tingling, numbness (especially in the lower limbs), muscle weakness, and stool or urine incontinence.
If any of these symptoms occur, advise the patient or their caregivers to contact his or her physician immediately [see Boxed Warning ] . Gastrointestinal Adverse Reactions Instruct patients or their caregivers to call their healthcare provider if they experience any signs or symptoms of dyspepsia or gastritis: Dyspepsia (upset stomach), burning, or nausea Abdominal pain or discomfort Epigastric discomfort, GERD (gastric indigestion) [see Adverse Reactions (6.1) ] Invasive or Surgical Procedures Instruct patients or their caregivers to inform their healthcare provider that they are taking PRADAXA before any invasive procedure (including dental procedures) is scheduled [see Dosage and Administration (2.7) ] .
Concomitant Medications Ask patients or their caregivers to list all prescription medications, over-the-counter medications, or dietary supplements they are taking or plan to take so the patient's healthcare provider knows about other treatments that may affect bleeding risk (e.g., aspirin or NSAIDs) or dabigatran exposure (e.g., dronedarone or systemic ketoconazole) [see Warnings and Precautions (5.2 , 5.5) ] . Prosthetic Heart Valves Instruct patients or their caregivers to inform their healthcare provider if they will have or have had surgery to place a prosthetic he…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 6/2025 MEDICATION GUIDE PRADAXA (pra dax a) (dabigatran etexilate) Oral Pellets This Medication Guide is for PRADAXA Oral Pellets.
If your child is over 8 years of age and your healthcare provider prescribes PRADAXA Capsules for your child, read the Medication Guide that comes with your medicine. Read this Medication Guide before you start giving PRADAXA Oral Pellets to your child and each time you get a refill. There may be new information.
This Medication Guide does not take the place of talking with your healthcare provider about your child's medical condition or their treatment. What is the most important information I should know about PRADAXA? Do not stop giving PRADAXA without talking to the healthcare provider who prescribes it for your child.
Stopping PRADAXA increases your child's risk of a clot forming in their blood. PRADAXA may need to be stopped, if possible, before surgery or a medical or dental procedure. Ask the healthcare provider who prescribed PRADAXA for your child when your child should stop taking it.
Your healthcare provider will tell you when you may start giving PRADAXA to your child again after their surgery or procedure. If your child has to stop taking PRADAXA, your healthcare provider may prescribe another medicine to help prevent a blood clot from forming. PRADAXA can cause bleeding which can be serious, and sometimes lead to death.
This is because PRADAXA is a blood thinner medicine that lowers the chance of blood clots forming in the body. Your child may have a higher risk of bleeding if your child takes PRADAXA and: has kidney problems has stomach or intestine bleeding that is recent or keeps coming back, or a stomach ulcer takes other medicines that increase the risk of bleeding, including: aspirin or aspirin-containing products long-term (chronic) use of non-steroidal anti-inflammatory drugs (NSAIDs) a medicine that contains warfarin sodium a medicine that contains heparin a medicine that contains clopidogrel bisulfate a medicine that contains prasugrel has certain kidney problems and also takes a medicine that contains dronedarone or ketoconazole tablets Tell your healthcare provider if your child takes any of these medicines.
Ask your healthcare provider or pharmacist if you are not sure if your child's medicine is one listed above. PRADAXA can increase your child's risk of bleeding because it lessens the ability of your child's blood to clot. During treatment with PRADAXA: he or she may bruise more easily it may take longer for any bleeding to stop Call your healthcare provider or get medical help right away if your child has any of these signs or symptoms of bleeding: unexpected bleeding or bleeding that lasts a long time, such as: unusual bleeding from the gums nose bleeds that happen often menstrual bleeding or vaginal bleeding that is heavier than normal bleeding that is severe or you cannot control pink or brown urine red or black stools (looks like tar) bruises that happen without a known cause or get larger cough up blood or blood clots vomit blood or your vomit looks like "coffee grounds" unexpected pain, swelling, or joint pain headaches, feeling dizzy or weak Take PRADAXA Oral Pellets exactly as prescribed.
Do not stop giving PRADAXA Oral Pellets to your child without first talking to the healthcare provider who prescribes it for your child. Stopping PRADAXA increases your child's risk of a clot forming in their blood. Spinal or epidural blood clots (hematoma).
People who take a blood thinner medicine (anticoagulant) like PRADAXA, and have medicine injected into their spinal and epidural area, or have a spinal puncture have a risk of forming a blood clot that can cause long-term or permanent loss of the ability to move (paralysis). Your child's risk of developing a spinal or epidural blood clot is higher if: a thin tube called an epidural catheter is placed in your child's back to give the…