
Retisert Fluocinolone Acetonide .59 mg Implant, 1 implant — NDC 24208-416-01 (Billing 24208-0416-01)
This is a package of 1 implant of Retisert Fluocinolone Acetonide .59 mg Implant from Bausch & Lomb Incorporated, no longer marketed (first marketed Apr 2005), no longer in the FDA NDC Directory. It is this product's only package size.
Other active recalls for Fluocinolone Acetonide (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059043
- GCN: 24598
- GPI-14 (Medi-Span): 86300017102320
- HICL (First Databank): 002896
- AHFS class code: 52:08.08.00
- RxCUI (RxNorm): 1191323
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Creams, ointments and solutions calm itchy, inflamed skin. The oils treat atopic dermatitis or, for ear oil, chronic eczematous external otitis. Eye impl...
- Use the smallest amount that covers the area. Creams and ointments are usually a thin film a few times a day, and the oils follow their own schedule. If there's no improvement in 2...
- Tilt your head, gently pull your ear lobe back and up, and use the dropper to put in 5 drops. Stay tilted for about a minute, then pat away extra oil with a cotton ball. It's usual...
- Not the oil, unless your provider tells you to. Skin folds, armpits and groin carry a higher risk of side effects. Keep it out of your eyes, mouth and vagina.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7311 | $338.804 / J7311 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 24208-0416-01 You're viewing this Main listing | 1 POUCH in 1 CARTON / 1 IMPLANT in 1 POUCH | 2005-04-08 | — | Discontinued by firm |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Retisert .59 mgthis 24208-0416-01 | Bausch | 1 implant | — | — | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE RETISERT ® is indicated for the treatment of chronic non-infectious uveitis affecting the posterior segment of the eye. RETISERT is a corticosteroid indicated for the treatment of chronic noninfectious uveitis affecting the posterior segment of the eye. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION RETISERT is surgically implanted into the posterior segment of the affected eye through a pars plana incision. (2.1) RETISERT is designed to release fluocinolone acetonide at a nominal initial rate of 0.6 mcg/day, decreasing over the first month to a steady state between 0.3-0.4 mcg/day over approximately 30 months. (2.1) Aseptic technique should be maintained at all times prior to and during the surgical implantation procedure.
(2.2)
2.1Dosing Information RETISERT is implanted into the posterior segment of the affected eye through a pars plana incision. The implant contains one tablet of 0.59 mg of fluocinolone acetonide. RETISERT is designed to release fluocinolone acetonide at a nominal initial rate of 0.6 mcg/day, decreasing over the first month to a steady state between 0.3-0.4 mcg/day over approximately 30 months.
Following depletion of fluocinolone acetonide as evidenced by recurrence of uveitis, RETISERT may be replaced.
2.2Handling of Implant Caution should be exercised in handling RETISERT in order to avoid damage to the implant, which may result in an increased rate of drug release from the implant. Thus, RETISERT should be handled only by the suture tab. Care should be taken during implantation and explantation to avoid sheer forces on the implant that could disengage the silicone cup reservoir (which contains a fluocinolone acetonide tablet) from the suture tab.
Aseptic technique should be maintained at all times prior to and during the surgical implantation procedure. RETISERT should not be resterilized by any method.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 0.59 mg fluocinolone acetonide intravitreal implant. 0.59 mg fluocinolone acetonide intravitreal implant. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Surgical placement of RETISERT is contraindicated in active viral, bacterial, mycobacterial and fungal infections of ocular structures. (4.1)
4.1Viral, Bacterial, Mycobacterial and Fungal Infections of Ocular Structures Surgical placement of RETISERT is contraindicated in active viral diseases of the cornea and conjunctiva including epithelial herpes simplex keratitis (dendritic keratitis), vaccinia, and varicella, and also in active bacterial, mycobacterial or fungal infections of the eye.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cataract formation: Nearly all phakic patients are expected to develop cataracts and require cataract surgery. (5.1) Endophthalmitis: Late onset endophthalmitis has been observed. (5.2) Increase in intraocular pressure: Use of corticosteroids may result in elevated IOP and/or glaucoma.
(5.3) IOP lowering medications were required in > 75% of patients; filtering surgeries were required in > 35% of patients. (6.1) Separation of implant components: Physicians should periodically monitor the integrity of the implant by visual inspection. (5.4)
5.1Cataract Formation Use of corticosteroids may result in posterior subcapsular cataract formation. Based on clinical trials with RETISERT, during the 3-year post-implantation period, nearly all phakic eyes are expected to develop cataracts and require cataract surgery.
5.2Endophthalmitis and Surgical Complications Late onset endophthalmitis has been observed. These events are often related to the integrity of the surgical wound site. Careful attention to assure tight closure of the scleral wound and the integrity of the overlying conjunctiva at the wound site is important.
Potential complications accompanying intraocular surgery to place RETISERT into the vitreous cavity may include, but are not limited to, the following: cataract formation, choroidal detachment, endophthalmitis, hypotony, increased intraocular pressure, exacerbation of intraocular inflammation, retinal detachment, vitreous hemorrhage, vitreous loss, and wound dehiscence. Following implantation of RETISERT, nearly all patients will experience an immediate and temporary decrease in visual acuity in the implanted eye which lasts for approximately one to four weeks post-operatively.
5.3Increase in Intraocular Pressure Prolonged use of corticosteroids may result in elevated IOP and/or glaucoma with damage to the optic nerve, defects in visual acuity and fields of vision. Steroids should be used with caution in the presence of glaucoma. Patients must be monitored for elevated IOP.
Based on clinical trials with RETISERT, within 3-years post-implantation, approximately 77% of patients will require IOP lowering medications to control intraocular pressure and 37% of patients will require filtering procedures to control intraocular pressure [see Adverse Reactions ( 6.1 )] .
5.4Separation of Implant Components In vitro stability studies show that the strength of the adhesive bond between the silicone cup reservoir and the suture tab is reduced with prolonged hydration, indicating a potential for the separation of these components. The suture tab composition is a silicone elastomer reinforced with a polyester mesh. Physicians should periodically monitor the integrity of the implant by visual inspection.
5.5Other Corticosteroid Induced Adverse Reactions RETISERT should be used with caution in patients with a history of a viral, bacterial, mycobacterial or fungal infection of the cornea and conjunctiva including epithelial herpes simplex keratitis (dendritic keratitis), vaccinia and varicella. Use of ocular steroids may prolong the course and may exacerbate the severity of many viral infections of the eye (including herpes simplex). Employment of a corticosteroid medication in the treatment of patients with a history of herpes simplex requires great caution.
Prolonged use of corticosteroids may suppress the host response and thus increase the hazard of secondary ocular infections (bacterial, fungal, and viral). In acute purulent conditions of the eye, steroids may mask infection or enhance existing infection. Fungal and viral infections of the cornea are particularly prone to develop coincidentally with long-term application of steroids.
The possibility of fungal invasion should be considered in any persistent corneal ulceration where steroid treatment has been used. Since resistance to infections is known to be reduced by corticosteroids, simultaneous bilateral implantation should not be carried out, in… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Ocular adverse events included procedural complications, and eye pain (> 50%). Thirty-five to forty percent of patients reported ocular/conjunctival hyperemia, reduced visual acuity, and conjunctival hemorrhage. (6.1) The most common non-ocular event reported was headache (33%). (6.2) To report SUSPECTED ADVERSE REACTIONS, contactBausch & Lomb Incorporated at 1-800-553-5340or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience - Ocular Events The available safety data includes exposure to RETISERT in patients with chronic non-infectious uveitis affecting the posterior segment in two multicenter controlled clinical trials. Patients were randomized to dosage regimens of 0.59 mg or 2.1 mg implants. The most frequently reported ocular adverse events were cataract, increased intraocular pressure, procedural complication, and eye pain.
These events occurred in approximately 50 - 90% of patients. Cataract includes aggravated cataract, and posterior capsular opacification. Procedural complications includes post-op complication, post-op wound complication, post-op wound site erythema, and wound dehiscense.
Based on clinical trials with RETISERT, during the 3-year post-implantation period, nearly all phakic eyes are expected to develop cataracts and require cataract surgery. IOP lowering medications to lower intraocular pressure were required in approximately 77% of patients; filtering surgeries were required to control intraocular pressure in 37% of patients. Ocular adverse events occurring in approximately 10 - 40% of patients in decreasing order of incidence were ocular/conjunctival hyperemia, reduced visual acuity, glaucoma, conjunctival hemorrhage, blurred vision, abnormal sensation in the eye, eye irritation, maculopathy, vitreous floaters, hypotony, pruritus, ptosis, increased tearing, vitreous hemorrhage, dry eye, eyelid edema, macular edema and visual disturbance.
Ocular adverse events occurring in approximately 5 - 9% of patients in decreasing order of incidence were eye discharge, photophobia, blepharitis, corneal edema, iris adhesions, choroidal detachment, diplopia, eye swelling, retinal detachment, photopsia, retinal hemorrhage and hyphema.
6.2Clinical Trials Experience - Non-Ocular Events The most frequently reported non-ocular adverse event was headache (33%). Other non-ocular adverse events occurring in approximately 5-20% of patients in decreasing order of incidence were nasopharyngitis, arthralgia, sinusitis, dizziness, pyrexia, upper respiratory tract infection, influenza, vomiting, nausea, cough, back pain, limb pain, and rash.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Adequate and well-controlled studies with RETISERT have not been conducted in pregnant women to inform drug-associated risk. Animal reproduction studies have not been conducted with RETISERT. It is not known whether RETISERT can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity.
Corticosteroids have been shown to be teratogenic in laboratory animals when administered systemically at relatively low dosage levels. RETISERT should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary There are no data on the presence of RETISERT in human milk, the effects on the breastfed infant, or the effects on milk production. Systemically administered corticosteroids are present in human milk and can suppress growth, interfere with endogenous corticosteroid production, or cause other unwanted effects. Clinical or nonclinical lactation studies have not been conducted with RETISERT.
It is not known whether intravitreal treatment with RETISERT could result in sufficient systemic absorption to produce detectable quantities of fluocinolone acetonide in human milk, or affect breastfed infants or milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for RETISERT and any potential adverse effects on the breastfed child from RETISERT or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients below the age of 12 years have not been established.
8.5Geriatric Use No overall differences in safety and effectiveness have been observed between elderly and younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Adequate and well-controlled studies with RETISERT have not been conducted in pregnant women to inform drug-associated risk. Animal reproduction studies have not been conducted with RETISERT. It is not known whether RETISERT can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity.
Corticosteroids have been shown to be teratogenic in laboratory animals when administered systemically at relatively low dosage levels. RETISERT should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients below the age of 12 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety and effectiveness have been observed between elderly and younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Corticosteroids inhibit the inflammatory response to a variety of inciting agents and probably delay or slow healing. They inhibit the edema, fibrin deposition, capillary dilation, leukocyte migration, capillary proliferation, fibroblast proliferation, deposition of collagen, and scar formation associated with inflammation. There is no generally accepted explanation for the mechanism of action of ocular corticosteroids.
However, corticosteroids are thought to act by the induction of phospholipase A 2 inhibitory proteins, collectively called lipocortins. It is postulated that these proteins control the biosynthesis of potent mediators of inflammation such as prostaglandins and leukotrienes by inhibiting the release of their common precursor arachidonic acid. Arachidonic acid is released from membrane phospholipids by phospholipase A 2 .
Corticosteroids are capable of producing a rise in intraocular pressure.
12.3Pharmacokinetics In a subset of patients who received the intravitreal implant, and had blood samples taken at various times (weeks 1, 4 and 34) after implantation, plasma levels of fluocinolone acetonide were below the limit of detection (0.2 ng/mL) at all times. Aqueous and vitreous humor samples were assayed for fluocinolone acetonide in a further subset of patients. While detectable concentrations of fluocinolone acetonide were seen throughout the observation interval (up to 34 months), the concentrations were highly variable, ranging from below the limit of detection (0.2 ng/mL) to 589 ng/mL.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Corticosteroids inhibit the inflammatory response to a variety of inciting agents and probably delay or slow healing. They inhibit the edema, fibrin deposition, capillary dilation, leukocyte migration, capillary proliferation, fibroblast proliferation, deposition of collagen, and scar formation associated with inflammation. There is no generally accepted explanation for the mechanism of action of ocular corticosteroids.
However, corticosteroids are thought to act by the induction of phospholipase A 2 inhibitory proteins, collectively called lipocortins. It is postulated that these proteins control the biosynthesis of potent mediators of inflammation such as prostaglandins and leukotrienes by inhibiting the release of their common precursor arachidonic acid. Arachidonic acid is released from membrane phospholipids by phospholipase A 2 .
Corticosteroids are capable of producing a rise in intraocular pressure.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING The implant consists of a tablet encased in a silicone elastomer cup containing a release orifice and a polyvinyl alcohol membrane positioned between the tablet and the orifice. The silicone elastomer cup assembly is attached to a silicone elastomer suture tab with silicone adhesive. Each RETISERT is approximately 3 mm x 2 mm x 5 mm.
Each implant is stored in a clear polycarbonate case within a foil pouch within a Tyvek peelable overwrap. Each packaged implant is provided in a carton which includes the package insert. NDC 24208-416-01 0.59 mg 1 count Storage: Store in the original container at 15°C to 25°C (59°F to 77°F).
Protect from freezing.
📋 Description ▾
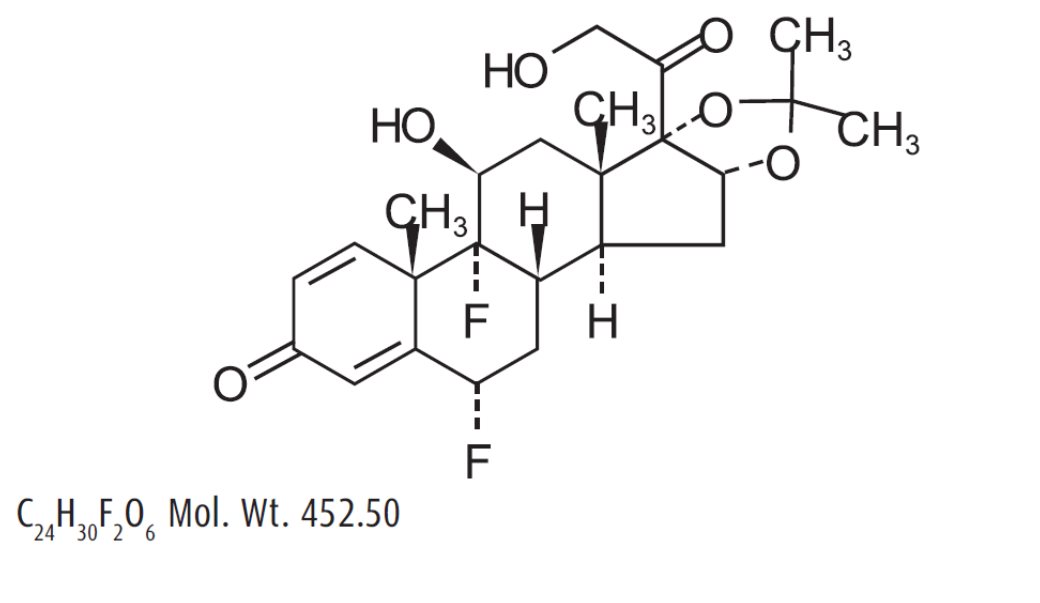
11 DESCRIPTION RETISERT ® (fluocinolone acetonide intravitreal implant) 0.59 mg is a sterile implant designed to release fluocinolone acetonide locally to the posterior segment of the eye at a nominal initial rate of 0.6 mcg/day, decreasing over the first month to a steady state between 0.3-0.4 mcg/day over approximately 30 months. The drug substance is the synthetic corticosteroid fluocinolone acetonide, represented by the following structural formula: C 24 H 30 F 2 O 6 Mol. Wt.
452.50 Chemical Name: Pregna-1,4-diene-3,20-dione,6,9-difluoro-11,21-dihydroxy-16,17-[(1-methyl-ethylidene)bis(oxy)],(6α,11β ,16α)-. Fluocinolone acetonide is a white crystalline powder, insoluble in water, and soluble in methanol. It has a melting point of 265-266ºC.
Each RETISERT consists of a tablet containing 0.59 mg of the active ingredient, Fluocinolone Acetonide, USP, and the following inactives: magnesium stearate, microcrystalline cellulose, and polyvinyl alcohol. chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients should be advised to have ophthalmologic follow-up examinations of both eyes at appropriate intervals following implantation of RETISERT. As with any surgical procedure, there is risk involved. Potential complications accompanying intraocular surgery to place RETISERT into the vitreous cavity may include, but are not limited to, the following: cataract formation, choroidal detachment, temporary decreased visual acuity, endophthalmitis, hypotony, increased intraocular pressure, exacerbation of intraocular inflammation, retinal detachment, vitreous hemorrhage, vitreous loss, and wound dehiscence.
Following implantation of RETISERT, nearly all patients will experience an immediate and temporary decrease in visual acuity in the implanted eye which lasts for approximately one to four weeks post-operatively. Based on clinical trials with RETISERT, within 3 years post-implantation, approximately 77% of patients will require IOP lowering medications to control intraocular pressure and 37% of patients will require filtering procedures to control intraocular pressure [see Adverse Reactions ( 6.1 )] . Based on clinical trials with RETISERT, during the 3-year post-implantation period, nearly all phakic eyes are expected to develop cataracts and require cataract surgery.
Manufactured for: Bausch & Lomb Americas Inc Bridgewater, NJ 08807 USA Manufactured by: Bausch + Lomb Ireland Limited Waterford, Ireland RETISERT is a trademark of Bausch & Lomb Incorporated or its affiliates. © 2025 Bausch & Lomb Incorporated or its affiliates 9028012
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics In a subset of patients who received the intravitreal implant, and had blood samples taken at various times (weeks 1, 4 and 34) after implantation, plasma levels of fluocinolone acetonide were below the limit of detection (0.2 ng/mL) at all times. Aqueous and vitreous humor samples were assayed for fluocinolone acetonide in a further subset of patients. While detectable concentrations of fluocinolone acetonide were seen throughout the observation interval (up to 34 months), the concentrations were highly variable, ranging from below the limit of detection (0.2 ng/mL) to 589 ng/mL.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES In two randomized, double-masked, multicenter controlled clinical trials, 224 patients with chronic (a one year or greater history) non-infectious uveitis affecting the posterior segment of one or both eyes were randomized to receive a 0.59 mg RETISERT. The primary efficacy endpoint in both trials was the rate of recurrence of uveitis affecting the posterior segment of the study eye in the 34 week pre-implantation period compared to the rate of recurrence in the 34 week post-implantation period. Uveitis recurrence rates at 1, 2, and 3 year post-implantation were also compared to the 34 week pre-implantation period.
Detailed results are shown in Table 1 below: Table 1: Uveitis Recurrence Rates TIME POINT STUDY 1 STUDY 2 N=108 N=116 Uveitis Recurrence Rates 1,2 N (%) 34 Weeks Pre- implantation 58 (53.7) 46 (39.7) 34 Weeks Post- implantation 2 (1.8) 15 (12.9) 1 Year Post-implantation 4 (3.7) 15 (12.9) 2 Years Post-implantation 11 (10.2) 16 (13.8) 3 Years Post-implantation 22 (20.4) 20 (17.2) 3 Years 3 Post- implantation 33 (30.6) 28 (24.1) 1 Recurrence of uveitis for all post-implantation time points was compared to the 34 weeks pre-implantation time point.
2 p-value <0.01 from McNemar’s χ 2 test. 3 Results presented include imputed recurrences. Recurrences were imputed when a subject was not seen within 10 weeks of their final scheduled visit.
In assessing the effect of RETISERT on the corneal endothelial cell density in eyes that have been implanted for a minimum of 1 year, the results indicate that eyes containing the RETISERT implant for an average of 3.54 years had a lower mean corneal endothelial cell density (mean paired difference of -435 cells/mm 2 ) compared with non-implanted eyes (p<0.01).
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term animal studies have not been performed to determine the carcinogenic potential or the effect on fertility of RETISERT. Fluocinolone acetonide was not genotoxic in vitro in the Ames test (S. typhimurium and E. coli), the mouse lymphoma TK assay, or in vivo in the mouse bone marrow micronucleus assay.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term animal studies have not been performed to determine the carcinogenic potential or the effect on fertility of RETISERT. Fluocinolone acetonide was not genotoxic in vitro in the Ames test (S. typhimurium and E. coli), the mouse lymphoma TK assay, or in vivo in the mouse bone marrow micronucleus assay.
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 24208-416-01 Rx only Retisert ® (fluocinolone acetonide intravitreal implant) 0.59 mg STERILE FOR INTRAVITREAL IMPLANTATION ONLY Contents: One sterile Retisert ® (fluocinolone acetonide intravitreal implant) 0.59 mg Content sterile in unopened, undamaged package. BAUSCH + LOMB carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |