
Ga-68-DOTATOC EDOTREOTIDE GALLIUM GA-68 4 mCi/mL Injection, Solution, 14 mL — NDC 24417-681-30 (Billing 24417-0681-30)
This is a package of 14 mL of Ga-68-DOTATOC EDOTREOTIDE GALLIUM GA-68 4 mCi/mL Injection, Solution from UIHC P E T Imaging Center, marketed since Sep 2019 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 080433
- GCN: 47267
- GPI-14 (Medi-Span): 94354035302030
- HICL (First Databank): 046184
- AHFS class code: 36:68.00.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 24417-0681-30 You're viewing this Main listing | 14 mL in 1 VIAL, MULTI-DOSE | 2019-09-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ga-68-DOTATOC 4 mCi/mLthis 24417-0681-30 | UIHC | 14 ml | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Code | What it grants | Expires |
|---|---|---|
| ODE-383 | Orphan Drug Exclusivity (7-year) | Aug 21, 2026 |
| W | FDA-granted marketing exclusivity | Aug 21, 2026 |
Is there a generic version of GALLIUM GA-68 DOTATOC 18.5-148?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ga 68 DOTATOC Injection is indicated for use with positron emission tomography (PET) for the localization of somatostatin receptor positive neuroendocrine tumors (NETs) in adult and pediatric patients. Ga 68 DOTATOC Injection is a radioactive diagnostic agent indicated for use with positron emission tomography (PET) for localization of somatostatin receptor positive neuroendocrine tumors (NETs) in adult and pediatric patients. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dose for adults is 148 MBq (4 mCi) as a bolus intravenous injection ( 2.2 ) Recommended dose for pediatric patients is
1.59MBq/kg (0.043 mCi/kg) with a range of
11.1MBq (0.3 mCi) to 111 MBq (3 mCi), as a bolus intravenous injection ( 2.2 ) Initiate imaging 55 to 90 minutes after drug administration ( 2.4 ) See full prescribing information for additional preparation, administration, imaging and radiation dosimetry information ( 2 )
2.1Radiation Safety – Drug Handling Handle Ga 68 DOTATOC Injection with appropriate safety measures to minimize radiation exposure [see Warnings and Precautions (5.1) ] . Use waterproof gloves, effective radiation shielding and appropriate safety measures when preparing and handling Ga 68 DOTATOC Injection. Radiopharmaceuticals should be used by or under the control of physicians who are qualified by specific training and experience in the safe use and handling of radionuclides, and whose experience and training have been approved by the appropriate governmental agency authorized to license the use of radionuclides.
2.2Recommended Dosage and Administration Instructions Recommended Dosage In adults, the recommended amount of radioactivity to be administered for PET imaging is 4 mCi (148 MBq) with a range of 3 mCi to 5 mCi (111 MBq to 185 MBq) administered as an intravenous injection with an injection rate of approximately 10 seconds per mL. In pediatric patients, the recommended amount of radioactivity to be administered for PET imaging is 0.043 mCi/kg of body weight (1.59 MBq/kg) with a range of 0.3 mCi (11.1 MBq) to 3 mCi (111 MBq) as an intravenous injection with an injection rate of approximately 10 seconds per mL.
Administration Use Ga 68 DOTATOC Injection within 3 hours of calibration time. Use aseptic technique and radiation shielding when withdrawing and administering Ga 68 DOTATOC Injection. Inspect Ga 68 DOTATOC Injection visually for particulate matter and discoloration before administration.
Do not use the drug if the solution contains particulate matter or is discolored. Calculate the necessary volume to administer based on measured activity, volume, calibration time, and date. Measure the patient dose immediately prior to administration in a dose calibrator.
After injection of Ga 68 DOTATOC Injection, administer an intravenous flush of sodium chloride injection, 0.9% to ensure full delivery of the dose. Dispose of any unused drug in a safe manner in compliance with applicable regulations.
2.3Use with Somatostatin Analogs and Patient Hydration Somatostatin Analogs Somatostatin analogs bind to the same somatostatin receptors as Ga 68 DOTATOC Discontinue short-acting somatostatin analogs 24 hours before imaging with Ga 68 DOTATOC Injection . Image patients with Ga 68 DOTATOC Injection just prior to dosing with long-acting analogs of somatostatin [see Drug Interactions (7) ] . Patient Hydration Instruct patients to drink water to ensure adequate hydration prior to administration of Ga 68 DOTATOC Injection and to continue to drink and void frequently during the first hours following administration to reduce radiation exposure [see Warnings and Precautions (5.1) ] .
2.4Image Acquisition For Ga 68 DOTATOC PET imaging, a whole-body acquisition from the skull vertex to mid-thigh is recommended. Image acquisition can begin at 60 minutes (range 55 to 90 minutes) after the intravenous administration of the Ga 68 DOTATOC Injection. Adapt Ga 68 DOTATOC Injection uptake time and scan duration according to the equipment used, and the patient and tumor characteristics, to obtain the optimal image quality.
2.5Image Interpretation Ga 68 DOTATOC binds to somatostatin receptors. Based upon the intensity of the signals, PET images obtained using Ga 68 DOTATOC Injection indicate the presence and density of somatostatin receptors in tissues, .Uptake can also be seen in a variety of non-NET tumors that contain somatostatin receptors or as a normal physiologic varian… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: Gallium Ga 68 DOTATOC Injection is a clear, colorless solution in a 30 mL multiple-dose vial containing
18.5MBq/mL to 148 MBq/mL (0.5 mCi/mL to 4 mCi/mL) of Ga 68 DOTATOC Injection at calibration date and time. Injection:
18.5MBq/mL to 148 MBq/mL (0.5 mCi/mL to 4 mCi/mL) of Ga 68 DOTATOC Injection in a multiple-dose glass vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Radiation Risk: Ensure safe handling and preparation procedures to protect patients and health care workers from unintentional radiation exposure Advise patients to hydrate before and after administration and to void frequently after administration ( 2.1 , 2.3 , 5.1 ) Hypersensitivity Reactions: Most reported reactions were rash and pruritus and reversible either spontaneously or with routine symptomatic management. ( 5.2 ) Risk for Image Misinterpretation: Uptake of Ga 68 DOTATOC injection can be seen in a variety of tumor types that contain somatostatin receptors, and in other pathologic conditions, and as a normal physiologic variant (e.g. uncinate process of the pancreas) ( 5.3 )
5.1Radiation Risk Ga 68 DOTATOC Injection contributes to a patient's overall long-term cumulative radiation exposure. Long-term cumulative radiation exposure is associated with an increased risk of cancer. Ensure safe handling and preparation procedures to protect patients and health care workers from unintentional radiation exposure.
Advise patients to hydrate before and after administration and to void frequently after administration [see Dosage and Administration (2.1 , 2.3 )] .
5.2Hypersensitivity Reactions Hypersensitivity reactions following administration of somatostatin receptor imaging agents predominantly consisted of cutaneous reactions such as rash and pruritus. Reactions reversed either spontaneously or with routine symptomatic management. Less frequently hypersensitivity reactions included angioedema or cases with features of anaphylaxis.
5.3Risk for Image Misinterpretation The uptake of Ga 68 DOTATOC Injection reflects the level of somatostatin receptor density in NETs, however, uptake can also be seen in a variety of other tumors that also express somatostatin receptors. Increased uptake might also be seen in other non-cancerous pathologic conditions that express somatostatin receptors including thyroid disease or in subacute inflammation, or might occur as a normal physiologic variant (e.g. uncinate process of the pancreas) [see Dosage and Administration (2.5) ] .
A negative scan after the administration of Ga 68 DOTATOC Injection in patients who do not have a history of NET disease does not rule out disease [see Clinical Studies (14) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hypersensitivity reactions Reported adverse reactions include: Nausea, pruritis, and flushing. To report SUSPECTED ADVERSE REACTIONS, contact the UIHC – P E T Imaging Center at 1-319-356-1092 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch ( 6 )
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of Ga-68 DOTATOC injection was evaluated in 334 patients in clinical trials of patients receiving a single dose of Ga-68 DOTATOC injection for imaging known or suspected NET. The following adverse reactions occurred at a rate of < 2%: Gastrointestinal Disorders : nausea The following adverse reactions occurred at a rate of a < 1% Skin and Subcutaneous Tissue Disorders: pruritus Vascular Disorders : flushing
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of other somatostatin receptor imaging agents. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to the drug. Immune System Disorders : Hypersensitivity reactions , predominantly rash, pruritus, less frequently angioedema or features of anaphylaxis
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Non-radioactive somatostatin analogs bind to the same somatostatin receptors as Ga 68 DOTATOC Injection. Image patients with Ga 68 DOTATOC Injection just prior to dosing with long-acting analogs of somatostatin. Short-acting analogs of somatostatin can be used up to 24 hours before imaging with Ga 68 DOTATOC Injection [see Dosage and Administration (2.3) ] .
Somatostatin Analogs: Somatostatin analogs competitively bind to the same somatostatin receptors as Ga 68 DOTATOC Injection and may affect imaging –Discontinue short-acting somatostatin analogs 24 hours before imaging with Ga 68 DOTATOC and image just prior to dosing with long-acting somatostatin analogs ( 2.3 , 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breast milk should be pumped and discarded for 8 hours after administration ( 8.2 )
8.1Pregnancy Risk Summary There are no available data on the use of Ga 68 DOTATOC Injection in pregnant women to identify a risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Animal reproduction studies have not been conducted with Ga 68 DOTATOC. However, all radiopharmaceuticals, including Ga 68 DOTATOC Injection have the potential to cause fetal harm depending on the fetal stage of development and the magnitude of the radiation dose.
If considering Ga 68 DOTATOC Injection administration to a pregnant woman, inform the patient of the potential for adverse pregnancy outcomes based on the radiation dose from Ga 68 DOTATOC Injection and the gestational timing of exposure. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2-4% and 15-20%, respectively.
8.2Lactation Risk Summary There is no information on the presence of Ga 68 DOTATOC in human milk, the effect on the breastfed infant, or the effect on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for Ga 68 DOTATOC Injection and any potential adverse effects on the breastfed child from Ga 68 DOTATOC Injection or from the underlying maternal condition. Clinical Considerations To decrease exposure to the breastfed infant, advise a lactating woman to interrupt breastfeeding and pump and discard breast milk for 8 hours after Ga 68 DOTATOC Injection administration.
8.4Pediatric Use The safety and efficacy of Ga 68 DOTATOC Injection have been established in pediatric patients with neuroendocrine tumors. Efficacy is based on data from 14 patients in Study A and B demonstrating the ability of Ga 68 DOTATOC to image NETs [see Clinical Studies (14) ] . The safety profile of Ga 68 DOTATOC Injection is similar in adult and pediatric patients with somatostatin receptor positive tumors.
The recommended Ga 68 DOTATOC injected dose in pediatric patients is weight based [see Dosage and Administration (2.2) ] .
8.5Geriatric Use Clinical studies of Ga 68 DOTATOC did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on the use of Ga 68 DOTATOC Injection in pregnant women to identify a risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Animal reproduction studies have not been conducted with Ga 68 DOTATOC. However, all radiopharmaceuticals, including Ga 68 DOTATOC Injection have the potential to cause fetal harm depending on the fetal stage of development and the magnitude of the radiation dose.
If considering Ga 68 DOTATOC Injection administration to a pregnant woman, inform the patient of the potential for adverse pregnancy outcomes based on the radiation dose from Ga 68 DOTATOC Injection and the gestational timing of exposure. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2-4% and 15-20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of Ga 68 DOTATOC Injection have been established in pediatric patients with neuroendocrine tumors. Efficacy is based on data from 14 patients in Study A and B demonstrating the ability of Ga 68 DOTATOC to image NETs [see Clinical Studies (14) ] . The safety profile of Ga 68 DOTATOC Injection is similar in adult and pediatric patients with somatostatin receptor positive tumors.
The recommended Ga 68 DOTATOC injected dose in pediatric patients is weight based [see Dosage and Administration (2.2) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Ga 68 DOTATOC did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of a radiation overdose, reduce the absorbed dose to the patient by increasing the elimination of the radionuclide from the body by reinforced hydration, frequent bladder voiding, and diuretics, if needed. If possible, perform an estimate of the radioactive dose given to the patient.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ga 68 DOTATOC binds to somatostatin receptors, with highest affinity (K i = 2.5± 0.5 nanomolar) for subtype 2 receptors (sstr2). Ga 68 DOTATOC binds to cells that express somatostatin receptors including malignant neuroendocrine cells, which overexpress sstr2 receptors. Gallium 68 is a β+ emitting radionuclide with associated 511 keV annihilation photons that allow positron emission tomography (PET) imaging.
12.2Pharmacodynamics The relationship between Ga 68 DOTATOC plasma concentrations and successful imaging was not explored in clinical trials.
12.3Pharmacokinetics Distribution Ga 68 DOTATOC distributes to all sstr2-expressing organs such as pituitary, thyroid, spleen, adrenals, kidney, pancreas, prostate, liver, and salivary glands. Uptake in the lung and lymph nodes are lower as compared to other sstr-2 expressing organs. Elimination Radiotracer elimination is exclusively via urine. Approximately 16% of the injected dose is excreted in urine in the first two to four hours post-injection.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ga 68 DOTATOC binds to somatostatin receptors, with highest affinity (K i = 2.5± 0.5 nanomolar) for subtype 2 receptors (sstr2). Ga 68 DOTATOC binds to cells that express somatostatin receptors including malignant neuroendocrine cells, which overexpress sstr2 receptors. Gallium 68 is a β+ emitting radionuclide with associated 511 keV annihilation photons that allow positron emission tomography (PET) imaging.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ga 68 DOTATOC Injection is supplied in a multiple-dose, capped 30 mL glass vial containing
18.5MBq/mL to 148 MBq/mL (0.5 mCi/mL to 4 mCi/mL) of Ga 68 DOTATOC at calibration time in approximately 14 mL of solution (NDC 24417-681-30). Store Ga 68 DOTATOC Injection upright in a lead shielded container at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). Receipt, transfer, handling, possession or use of this product is subject to the radioactive material regulations and licensing requirements of the U.S.
Nuclear Regulatory Commission, Agreement States or Licensing States as appropriate. Store and dispose of Ga 68 DOTATOC Injection in accordance with the regulations and a general license, or its equivalent, of an Agreement State or a Licensing State.
📦 Storage and Handling ▾
Store Ga 68 DOTATOC Injection upright in a lead shielded container at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). Receipt, transfer, handling, possession or use of this product is subject to the radioactive material regulations and licensing requirements of the U.S. Nuclear Regulatory Commission, Agreement States or Licensing States as appropriate.
Store and dispose of Ga 68 DOTATOC Injection in accordance with the regulations and a general license, or its equivalent, of an Agreement State or a Licensing State.
📋 Description ▾
11 DESCRIPTION
11.1Chemical Characteristics Ga 68 DOTATOC Injection is a radioactive diagnostic agent for intravenous administration. It contains 3.6 mcg/mL (DOTA-0-Phe1-Tyr3) octreotide,
18.5MBq/mL to 148 MBq/mL (0.5 mCi to 4 mCi/mL) of Ga 68 DOTATOC at calibration time, and ethanol (10% v/v) in sodium chloride (9 mg/mL) solution (approximately 14 mL volume). Ga 68 DOTATOC Injection is a sterile, pyrogen free, clear, colorless, buffered solution, with a pH between 4 to 8. Ga 68 DOTATOC, also known as Gallium-68 (DOTA0-Phe1-Tyr3) octreotide, is a cyclic 8 amino acid peptide with a covalently bound chelator (DOTA).
The peptide has the amino acid sequence: H-D-Phe-Cys-Tyr-D-Trp-Lys-Thr-Cys-Thr-OH, and contains one disulfide bond. Ga 68 DOTATOC has a molecular weight of 1489.65 g/mol and its chemical structure is shown in Figure 1. Figure 1: Chemical Structure of Ga 68 DOTATOC Gallium-68 labeled 2-[4-[2-[[(2R)-1-[[(4R,7S,10S,13R,16S,19R)-10-(4-aminobutyl)-4-[[(2R,3R)-1,3-dihydroxybutan-2-yl]carbamoyl]-7-[(1R)-1-hydroxyethyl]-16-[(4-hydroxyphenyl)methyl]-13-(1H-indol-3-ylmethyl)-6,9,12,15,18-pentaoxo-1,2-dithia-5,8,11,14,17-pentazacycloicos-19-yl]amino]-1-oxo-3-phenylpropan-2-yl]amino]-2-oxoethyl]-7,10-bis(carboxymethyl)-1,4,7,10-tetrazacyclododec-1-yl]acetic acid.
Figure 1
11.2Physical Characteristics Table 3 and Table 4 display the principal radiation emission data and physical decay of Ga 68. Gallium-68 (Ga 68) decays with a half-life of 68 minutes to stable Zn 68: 89% through positron emission with a mean energy of 836 keV followed by emission of two 511 keV annihilation photons (178%), 10% through orbital electron capture (with associated X-ray or Auger emissions), and 3% through 13 gamma transitions from 5 excited levels of the daughter Zn 68 nucleus. The most probable prompt gamma emission is a 1088 keV gamma with a 3.2% per decay probability.
Table 3: Principal Radiation Emission Data (>1%) Radiation/Emission % Disintegration Mean Energy (MeV) beta+ 88% 0.8360 beta+ 1.1% 0.3526 gamma 178% 0.5110 gamma 3% 1.0770 X-ray 2.8% 0.0086 X-ray 1.4% 0.0086 Table 4: Physical Decay Chart for Gallium Ga-68 Minutes Fraction Remaining 0 1.000 15 0.858 30 0.736 60 0.541 90 0.398 120 0.293 180 0.158 360 0.025
11.3External Radiation Gamma constant: 1.8 × 10 -4 mSv/hr per MBq at 1 meter [0.67 mrem/hr per mCi at 1 meter] Table 5 displays the radiation attenuation by lead shielding of Ga 68. Table 5: Radiation Attenuation of 511 keV Photons by Lead (Pb) Shielding Shield Thickness (Pb) mm Coefficient of Attenuation 6 0.5 12 0.25 17 0.1 34 0.01 51 0.001
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Radiation Risk Advise patients to drink water to ensure adequate hydration prior to their PET study and recommend they drink and urinate as often as possible during the first hours following the administration of Ga 68 DOTATOC Injection, in order to reduce radiation exposure [see Dosage and Administration (2.3) and Warnings and Precautions (5.1) ] . Lactation Advise a lactating woman to interrupt breastfeeding and pump and discard breast milk for 8 hours after Ga 68 DOTATOC Injection administration in order to minimize radiation exposure to a breastfed infant [see Use in Specific Populations (8.2) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Distribution Ga 68 DOTATOC distributes to all sstr2-expressing organs such as pituitary, thyroid, spleen, adrenals, kidney, pancreas, prostate, liver, and salivary glands. Uptake in the lung and lymph nodes are lower as compared to other sstr-2 expressing organs. Elimination Radiotracer elimination is exclusively via urine. Approximately 16% of the injected dose is excreted in urine in the first two to four hours post-injection.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The relationship between Ga 68 DOTATOC plasma concentrations and successful imaging was not explored in clinical trials.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The safety and efficacy of Ga-68 DOTATOC Injection were established in two single-center, open-label studies (Study A and Study B) in which 282 patients with known or suspected SSTR-positive NETs received a single dose of Ga-68 DOTATOC. A total of 238 of the 282 patients (84%) had a history of neoplasm at the time of Ga-68 DOTATOC imaging. Among the 282 patients, 59% were female and 95% white; the mean age was 54 years (range from 4 to 82 years).
The Ga-68 DOTATOC images were rated by two independent readers blinded to clinical information as either positive or negative for NET within each patient. The imaging results were compared to a composite reference consisting of histopathology and imaging (MR, CT, or In-111 pentetreotide imaging) acquired within 1 year of the Ga-68 DOTATOC imaging, as well as chromogranin A and pancreastatin levels. The proportion of patients positive for NET per composite reference who were identified as positive by the Ga-68 DOTATOC image was used to quantify positive percent agreement.
The proportion of patients without NET per composite reference who were identified as negative by the Ga-68 DOTATOC image was used to quantify negative percent agreement. Study A (NCT: 01619865) included 220 subjects with known or suspected SSTR positive tumors referred for diagnosis or evaluation of disease extension before or after treatment. A total of 178 of the 220 patients (81%) had a history of neoplasm at the time of Ga-68 DOTATOC imaging.
In 177 of the 220 patients, sufficient data to establish NET status per composite reference was available for efficacy evaluation. Table 6 shows the performance of Ga-68 DOTATOC in the detection of NETs for Study A. Table 6: Study A.
Performance of Ga-68 DOTATOC in the detection of NET by reader N = 177 NET status as identified by reader Reference Positive Negative N: number of patients, CI: confidence interval, Reader 1 Positive 121 5 Negative 12 39 Agreement (%) Percent reader agreement with reference; (95% CI) Exact method 91 (85, 95) 89 (75, 96) Reader 2 Positive 120 6 Negative 13 38 Agreement (%) (95% CI) 90 (84, 95) 86 (73, 95) Study B (NCT: 01869725) included 62 patients with histologically positive NET or other SSTR positive tumor referred for evaluation of disease before or after treatment.
In 59 of the 62 patients, sufficient data to establish NET status per composite reference was available for efficacy evaluation. The estimated positive and negative percent agreements were 92% and 75% for reader 1 and 90% and 75% for reader 2, respectively.
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.2 ) 12/2021
📄 Package Label / Principal Display Panel ▾
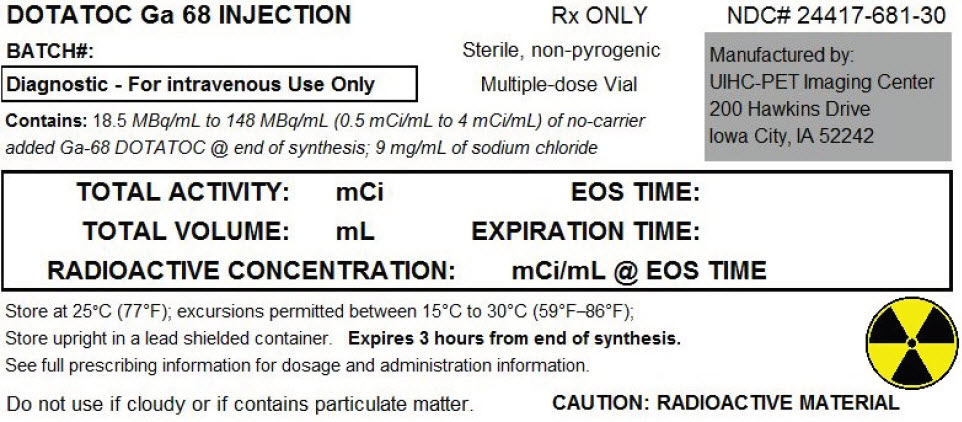
PRINCIPAL DISPLAY PANEL - 14 mL Vial Label DOTATOC Ga 68 INJECTION BATCH# Diagnostic - For intravenous Use Only Contains:
18.5MBq/mL to 148 MBq/mL (0.5 mCi/mL to 4 mCi/mL) of no-carrier added Ga-68 DOTATOC @ end of synthesis; 9 mg/mL of sodium chloride Rx ONLY Sterile, non-pyrogenic Multiple-dose Vial NDC# 24417-681-30 Manufactured by: UIHC-PET Imaging Center 200 Hawkins Drive Iowa City, IA 52242 TOTAL ACTIVITY: mCi TOTAL VOLUME: mL RADIOACTIVE CONCENTRATION: mCi/mL @ EOS TIME EOS TIME: EXPIRATION TIME: Store at 25°C (77°F); excursions permitted between 15°C to 30°C (59°F–86°F); Store upright in a lead shielded container. Expires 3 hours from end of synthesis.
See full prescribing information for dosage and administration information. Do not use if cloudy or if contains particulate matter. CAUTION: RADIOACTIVE MATERIAL PRINCIPAL DISPLAY PANEL - 14 mL Vial Label
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |