
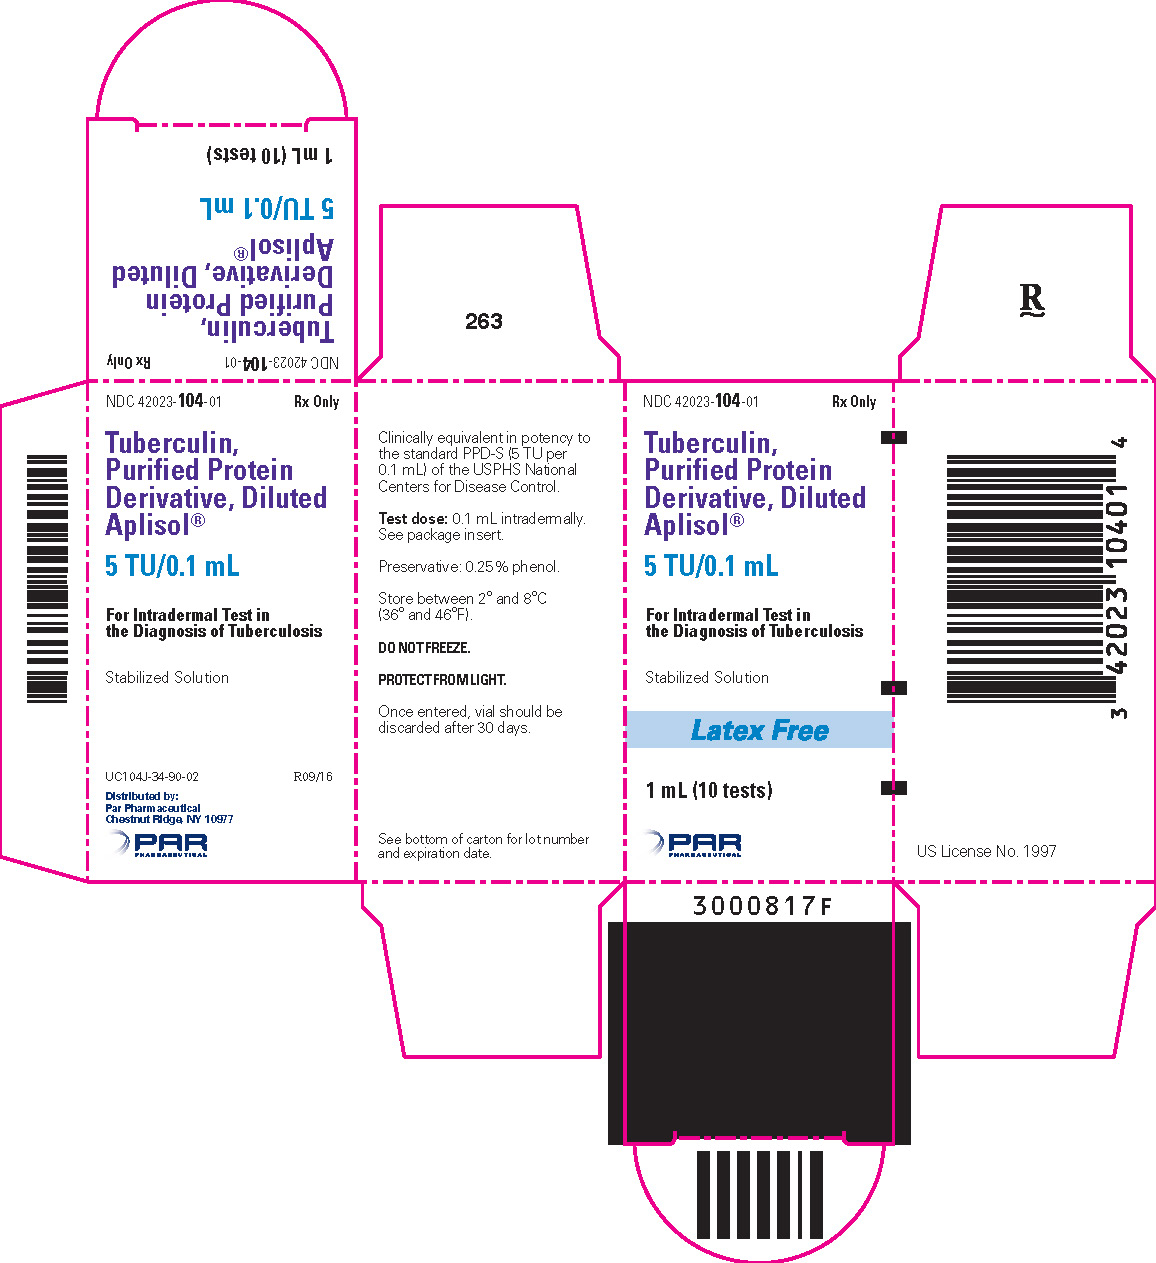
Aplisol Tuberculin Purified Protein Derivative 5 [iU]/.1mL Injection, 1 vial
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Tuberculosis Skin Test class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 339NCG44TV
Phenol is a chemical compound derived from coal tar or petroleum. It serves as a preservative and antimicrobial agent in medicines, helping prevent bacterial and fungal growth to keep the product stable and safe during storage.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $120.453 | $120.45 / 1 ml |
| Medicaid paysCMS SDUD · 12 mo | $97.56 | $97.56 / 1 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Aplisol 5 [iU]/.1mLthis 42023-0104-01 | ENDO | 1 vial | $120.453 | — | Discontinued | — |
| Tubersol 5 [iU]/.1mL 49281-0752-21 | Sanofi | 1 vial | — | — | FDA listed | — |
| Tubersol 5 [iU]/.1mL 50090-0261-00 | A-S | 1 vial | — | — | FDA listed | — |
| Aplisol 5 [iU]/.1mL 50090-1336-00 | A-S | 1 vial | — | — | FDA listed | — |
| Tubersol 5 [iU]/.1mL 50090-1668-00 | A-S | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 42023-0104-01 You're viewing this | 1 VIAL in 1 CARTON (42023-104-01) / 1 mL in 1 VIAL | $120.45 / mL | $120.45 | 2008-04-25 | Inactivated by FDA |
| 42023-0104-05 | 1 VIAL in 1 CARTON (42023-104-05) / 5 mL in 1 VIAL | $93.15 / mL | $465.73 | 2008-04-25 | Inactivated by FDA |
Per mL, this pack runs about 29% above the cheapest pack (NDC 42023-0104-05, $93.15 vs $120.45 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 87% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 42023-0104-01?
What NDC number is used to bill for this package of Aplisol Tuberculin Purified Protein Derivative 5 [iU]/.1mL Injection?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Tuberculin PPD is indicated as an aid in the detection of infection with Mycobacterium tuberculosis . The standard tuberculin test employs the intradermal (Mantoux) test using a 5 TU dose of tuberculin PPD. 7 The 0.1 mL test dose of Aplisol (tuberculin PPD, diluted) is equivalent to the 5 TU dose which has been clinically utilized and standardized with PPD-S.
Tuberculin skin testing is not contraindicated for persons who have been vaccinated with BCG and the skin-test results of such persons are used to support or exclude the diagnosis of M. tuberculosis infections. 4 HIV infection is a strong risk factor for the development of TB disease in persons having TB infection. All HIV-infected persons should receive a PPD-tuberculin skin test.
3
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Aplisol vials should be inspected visually for both particulate matter and discoloration prior to administration and discarded if either is seen. Vials in use for more than 30 days should be discarded. The 0.1 mL dose of Aplisol (tuberculin PPD, diluted) is equivalent to the 5 tuberculin units (TU) dose of Tuberculin PPD, which is the standard strength used for intradermal Mantoux testing.
Standard Method (Mantoux Test) The Mantoux test is performed by intradermally injecting, on the volar aspect of the forearm, with a syringe and needle, exactly 0.1 mL of Aplisol. The result is read 48 to 72 hours later and palpable induration only is considered in interpreting the test . Induration is a hard, raised area with clearly defined margins at and around the injection site (see Interpretation of Tuberculin Reaction ).
Erythema may develop at the injection site but has no diagnostic value. The standard test is performed as follows: The site of the test is usually the volar or dorsal surface of the forearm about 4" below the elbow. Other skin sites may be used, but the volar surface of the forearm is preferred.
The use of a skin area free of lesions and away from any veins is recommended. 7 The skin at the injection site is cleansed with 70% alcohol and allowed to dry. The test material is administered with a tuberculin syringe (0.5 or 1.0 mL) fitted with a short (1/4 to 1/2") 27 gauge needle.
A separate, sterile, single-use disposable syringe and needle should be used for each individual patient. The diaphragm of the vial-stopper should be wiped with 70% alcohol. The needle is inserted through the stopper diaphragm of the inverted vial.
Exactly 0.1 mL is filled into the syringe with care being taken to exclude air bubbles and to maintain the lumen of the needle filled. The point of the needle is inserted into the most superficial layers of the skin with the needle bevel pointed upward. As the Tuberculin solution is injected, a pale bleb 6 to 10 mm in size (1/3") will rise over the point of the needle.
This is quickly absorbed and no dressing is required. There may be a drop of blood when the needle is withdrawn. This is normal.
Use a gauze pad and gently dab to remove the blood. Do not press down as this may squeeze out the tuberculin thereby disrupting the test. In the event the injection is delivered subcutaneously (i.e., no bleb will form), or if a significant part of the dose leaks from the injection site, the test should be repeated immediately at another site at least 5 cm (2") removed from the initial injection site.
Interpretation of Tuberculin Reaction Readings of Mantoux reactions should be made by a trained health professional during the period from 48 to 72 hours after the injection. Induration only should be considered in interpreting the test. The diameter of induration should be measured transversely to the long axis of the forearm and recorded in millimeters.
Erythema has no diagnostic value and should be disregarded. The presence and size of necrosis and edema if present should be recorded although not used in the interpretation of the test. In the absence of induration, an area of erythema greater than 10 mm in diameter may indicate the injection was made too deeply and retesting is indicated.
Find the margins of the induration by drawing the index or middle finger lightly across the reaction. The tip of a ballpoint pen pushed at a 45° angle toward the site of injection will also stop at the edges of induration. The diameter of induration should be measured (preferable with a caliper) transversely to the long axis of the forearm and recorded in millimeters.
Erythema has no diagnostic value and should be disregarded. The absence of induration should be recorded as "0 mm" not "negative". Reactions should be interpreted as follows (Please refer to most recent guidelines): Based on current guidelines, 3,7,14, 19 interpretation of reactions is as follows: Positive reactions: Reaction ≥ 5 mm of I…
⛔ Contraindications ▾
CONTRAINDICATIONS Aplisol is contraindicated in patients with known hypersensitivity or allergy to Aplisol or any of its components. Aplisol should not be administered to persons who have previously experienced a severe reaction (e.g., vesiculation, ulceration, or necrosis) because of the severity of reactions that may occur at the test site.
⚠️ Warnings ▾
WARNINGS Aplisol should not be administered to persons who previously experienced a severe reaction (e.g., vesiculation, ulceration, or necrosis) because of the severity of reactions that may occur at the test site (see CONTRAINDICATIONS ). Not all infected persons will have a delayed hypersensitivity reaction to a tuberculin test. A number of factors have been reported to cause a decreased ability to respond to the tuberculin test, such as the presence of infections, viral infections (measles, mumps, chickenpox, HIV), live virus vaccinations (measles, mumps, rubella and other live vaccines), bacterial infections (typhoid fever, brucellosis, typhus, leprosy, pertussis, overwhelming tuberculosis, tuberculous pleurisy), fungal infections (South American blastomycosis), drugs (corticosteroids and other immunosuppressive agents), metabolic derangements (chronic renal failure), low protein states (severe protein depletion, afibrinogenemia), age (newborns, elderly patients with waned sensitivity), stress (surgery, burns, mental illness, graft-versus-host reactions), diseases affecting lymphoid organs (Hodgkin's disease, lymphoma, chronic leukemia, sarcoidosis), and malignancy.
7,8,9 Any condition that impairs or attenuates cell mediated immunity potentially can cause a false negative reaction, including aging. 10,11 Tuberculin skin test results are less reliable in HIV-infected individuals as CD4 counts decline (see CLINICAL PHARMACOLOGY ). 3 Avoid injecting tuberculin subcutaneously.
If this occurs, no local reaction develops, but a general febrile reaction and/or acute inflammation around old tuberculous lesions may occur in highly sensitive individuals.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In highly sensitive individuals, strongly positive reactions including vesiculation, ulceration or necrosis may occur at the test site. Cold packs or topical steroid preparations may be employed for symptomatic relief of the associated pain, pruritus and discomfort. Strongly positive test reactions may result in scarring at the test site.
Immediate erythematous or other reactions may occur at the injection site. Local hypersensitivity reactions may occur at the injection site including erythema, pruritus, edema, urticaria and rash. Systemic allergic reactions including anaphylaxis/anaphylactoid reactions have been reported to occur in association with the use of Aplisol.
The reactions, including anaphylaxis, generally occurred within 24 hours of exposure and manifestations included rash, urticaria, edema/angioedema and pruritus. To report SUSPECTED ADVERSE REACTIONS, contact Endo at 1-800-828-9393 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
Drug Interactions In patients who are receiving corticosteroids or immunosuppressive agents, reactivity to the test may be depressed or suppressed. This reduced reactivity may be present for as long as 5–6 weeks after discontinuation of therapy (see PRECAUTIONS – General ). 9 The reactivity to PPD may be temporarily depressed by certain live virus vaccines (measles, mumps, rubella, oral polio, yellow fever, and varicella).
Therefore, if a tuberculin test is to be performed, it should be administered either before the live vaccine or given simultaneously, but at a separate site than the live vaccine, or testing should be postponed for 4–6 weeks. 9
🤰 Pregnancy ▾
Pregnancy Teratogenic effects: Pregnancy Category C Animal reproduction studies have not been conducted with Aplisol. It is also not known whether Aplisol can cause fetal harm when administered to a pregnant woman or can affect the reproduction capacity. Aplisol should be given to a pregnant woman only if clearly needed.
However, the risk of unrecognized tuberculosis and the postpartum contact between a mother with active disease and an infant leaves the infant in grave danger of tuberculosis and complications such as tuberculous meningitis. Although there have not been any reported adverse effects upon the fetus recognized as being due to tuberculosis skin testing, the prescribing physician will want to consider if the potential benefits outweigh the possible risks for performing the tuberculin test on a pregnant woman or a woman of childbearing age, particularly in certain high risk populations.
Tuberculin skin testing is considered valid and safe throughout pregnancy. 3
🧒 Pediatric Use ▾
Pediatric Use Because their immune systems are immature, many neonates and infants <6 weeks of age, who are infected with M. tuberculosis , may not have a delayed hypersensitivity reaction to a tuberculin test (see WARNINGS ). Older infants and children develop tuberculin sensitivity 3-6 weeks, and up to 3 months, after initial infection. 5,20 Infants and children who have been exposed to persons with active tuberculosis should be considered positive when reaction to the tuberculin skin test measures ≥ 5 mm.
Those children younger than 4 years of age who are exposed to persons at increased risk to acquire tuberculosis are considered positive when reaction measures ≥10 mm. Children with minimal risk exposure to tuberculosis would be considered positive when reaction measures ≥15 mm. 5,20 Other criteria for positive tuberculin reactions that are applicable to both pediatric and adult patients are provided in DOSAGE AND ADMINISTRATION, Interpretation of Tuberculin Reaction .
🧓 Geriatric Use ▾
Geriatric Use Once acquired, tuberculin sensitivity tends to persist, although it often wanes with time and advancing age. In geriatric patients or in patients receiving a tuberculin skin test for the first time, the reaction may develop more slowly and may not be maximal until after 72 hours. 6,7 (see CLINICAL PHARMACOLOGY ).
Not all infected persons will have a delayed hypersensitivity reaction to a tuberculin test. A number of factors have been reported to cause a decreased ability to respond to the tuberculin test, such as elderly patients with waned sensitivity. 7 Any condition that impairs or attenuates cell mediated immunity potentially can cause a false negative reaction, including aging 10,11 (see WARNINGS ).
An induration of >10 mm is classified as positive in all persons who do not meet any of the criteria listed under an induration of >5 mm, but who belong to one or more of the following groups at high risk for TB, including residents and employees of high risk congregate settings, such as nursing homes and other long-term facilities for the elderly. The negative tuberculin skin test should never be used to exclude the possibility of active tuberculosis among person for whom the diagnosis is being considered (symptoms compatible with tuberculosis) (see DOSAGE AND ADMINISTRATION-Interpretation of Tuberculin Reaction ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY In the United States, the prevalence of Mycobacterium tuberculosis infection and active disease varies for different segments of the population; however, the risk for M. tuberculosis infection in the overall population is low. Tuberculosis (TB) case rates declined steadily for decades in the United States. However, in 1985 the TB case rate stabilized and subsequently increased through 1992, accompanied by a 14% increase in the TB mortality rate in 1988.
This has been attributed to several complex social and medical factors, including the human immunodeficiency virus (HIV) epidemic, the occurrence of TB in foreign-born persons from countries that have a high prevalence of TB, the emergence of drug-resistant strains of TB, and the transmission of M. tuberculosis in congregate settings (e.g., health-care facilities, correctional facilities, drug-treatment centers, and homeless shelters). Because the overall risk of acquiring M. tuberculosis is low for the total U.S. population, the primary strategy for preventing and controlling TB in the United States is to minimize the risk of transmission by the early identification and treatment of patients who have active infectious TB, finding and screening persons who have been in contact with active infectious TB patients and screening high risk populations.
Tuberculin PPD is indicated as an aid in the detection of infection with Mycobacterium tuberculosis . 3,4 After a person becomes infected with mycobacteria, T lymphocytes proliferate and become sensitized. These sensitized T cells enter the bloodstream and circulate for months or years.
This sensitization process occurs principally in the regional lymph nodes and may take 2–10 weeks to develop following infection. Once acquired, tuberculin sensitivity tends to persist, although it often wanes with time and advancing age. The injection of tuberculin into the skin stimulates the lymphocytes and activates the series of events leading to a delayed-type hypersensitivity (DTH) response.
This response is called "delayed" because the reaction becomes evident hours after injection. Dermal reactivity involves vasodilation, edema, and the infiltration of lymphocytes, basophils, monocytes, and neutrophils into the site of antigen injection. Antigen-specific T lymphocytes proliferate and release lymphokines, which mediate the accumulation of other cells at the site.
The area of induration reflects DTH activity. 5 In most tuberculin-sensitive individuals, the delayed hypersensitivity reaction is evident 5–6 hours after administration of a tuberculin skin test and is maximal 48–72 hours. In geriatric patients or in patients receiving a tuberculin skin test for the first time, the reaction may develop more slowly and may not be maximal until after 72 hours.
6,7 Because their immune systems are immature, many neonates and infants <6 weeks of age, who are infected with M. tuberculosis , do not react at all to tuberculin tests. 5 Immediate erythematous or other hypersensitivity reactions to tuberculin or the constituents of the diluent may occur at the injection site. A possible decrease in responsiveness to skin testing may occur in the presence of infections, viral infections (measles, mumps, chickenpox, HIV), live virus vaccinations (measles, mumps, rubella, oral polio, varicella, yellow fever), bacterial infections (typhoid fever, brucellosis, typhus, leprosy, pertussis, overwhelming tuberculosis, tuberculous pleurisy), fungal infections (South American blastomycosis), drugs (corticosteroids and other immunosuppressive agents), metabolic derangements (chronic renal failure), low protein states (severe protein depletion, afibrinogenemia), age (newborns, elderly patients with waned sensitivity), stress (surgery, burns, mental illness, graft-versus-host reactions), diseases affecting lymphoid organs (Hodgkin's disease, lymphoma, chronic leukemia, sarcoidosis) and malignancy (see WARNINGS ).
Tuberculin skin-test results are also le…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Tuberculin PPD-Aplisol bioequivalent to 5 US units (TU) PPD-S per test dose (0.1 mL) is available in the following presentations: NDC 42023-104-01 (Bio. 1525) 1 mL (10 tests) – multiple dose vial NDC 42023-104-05 (Bio.1607) 5 mL (50 tests) – multiple dose vial This product is ready for use without further dilution. Storage DO NOT FREEZE This product should be stored between 2° and 8°C (36° and 46°F) and protected from light.
Vials in use more than 30 days should be discarded due to possible oxidation and degradation which may affect potency. *PPD-S - World Health Organization International PPD-Tuberculin Standard **U.S. Tuberculin Unit
📦 Storage and Handling ▾
Storage DO NOT FREEZE This product should be stored between 2° and 8°C (36° and 46°F) and protected from light. Vials in use more than 30 days should be discarded due to possible oxidation and degradation which may affect potency. *PPD-S - World Health Organization International PPD-Tuberculin Standard **U.S. Tuberculin Unit
📋 Description ▾
DESCRIPTION Aplisol (tuberculin PPD, diluted) is a sterile aqueous solution of a purified protein fraction for intradermal administration as an aid in the diagnosis of tuberculosis. The solution is stabilized with polysorbate (Tween) 80, buffered with potassium and sodium phosphates and contains approximately 0.25% phenol as a preservative. This product is ready for immediate use without further dilution.
The purified protein fraction is isolated from culture media filtrates of a human strain of Mycobacterium tuberculosis by the method of F.B. Seibert. 1,2 Tuberculin PPD, diluted, is prepared from Tuberculin PPD which is clinically bioequivalent in potency to the standard PPD-S* (5 TU** per 0.1mL) of the U.S.
Public Health Service, National Centers for Disease Control. The potency of each lot of tuberculin PPD, diluted is determined in sensitized guinea pigs.
💬 Information for Patients ▾
Information to Patients Patients should be instructed to report adverse events such as vesiculation, ulceration or necrosis which may occur at the test site in highly sensitive individuals. Patients should be informed that pain, pruritus and discomfort may occur at injection site. Patients should be informed of the need to return to their physician or health care provider for the reading of the test and of the need to keep and maintain a personal immunization record.