
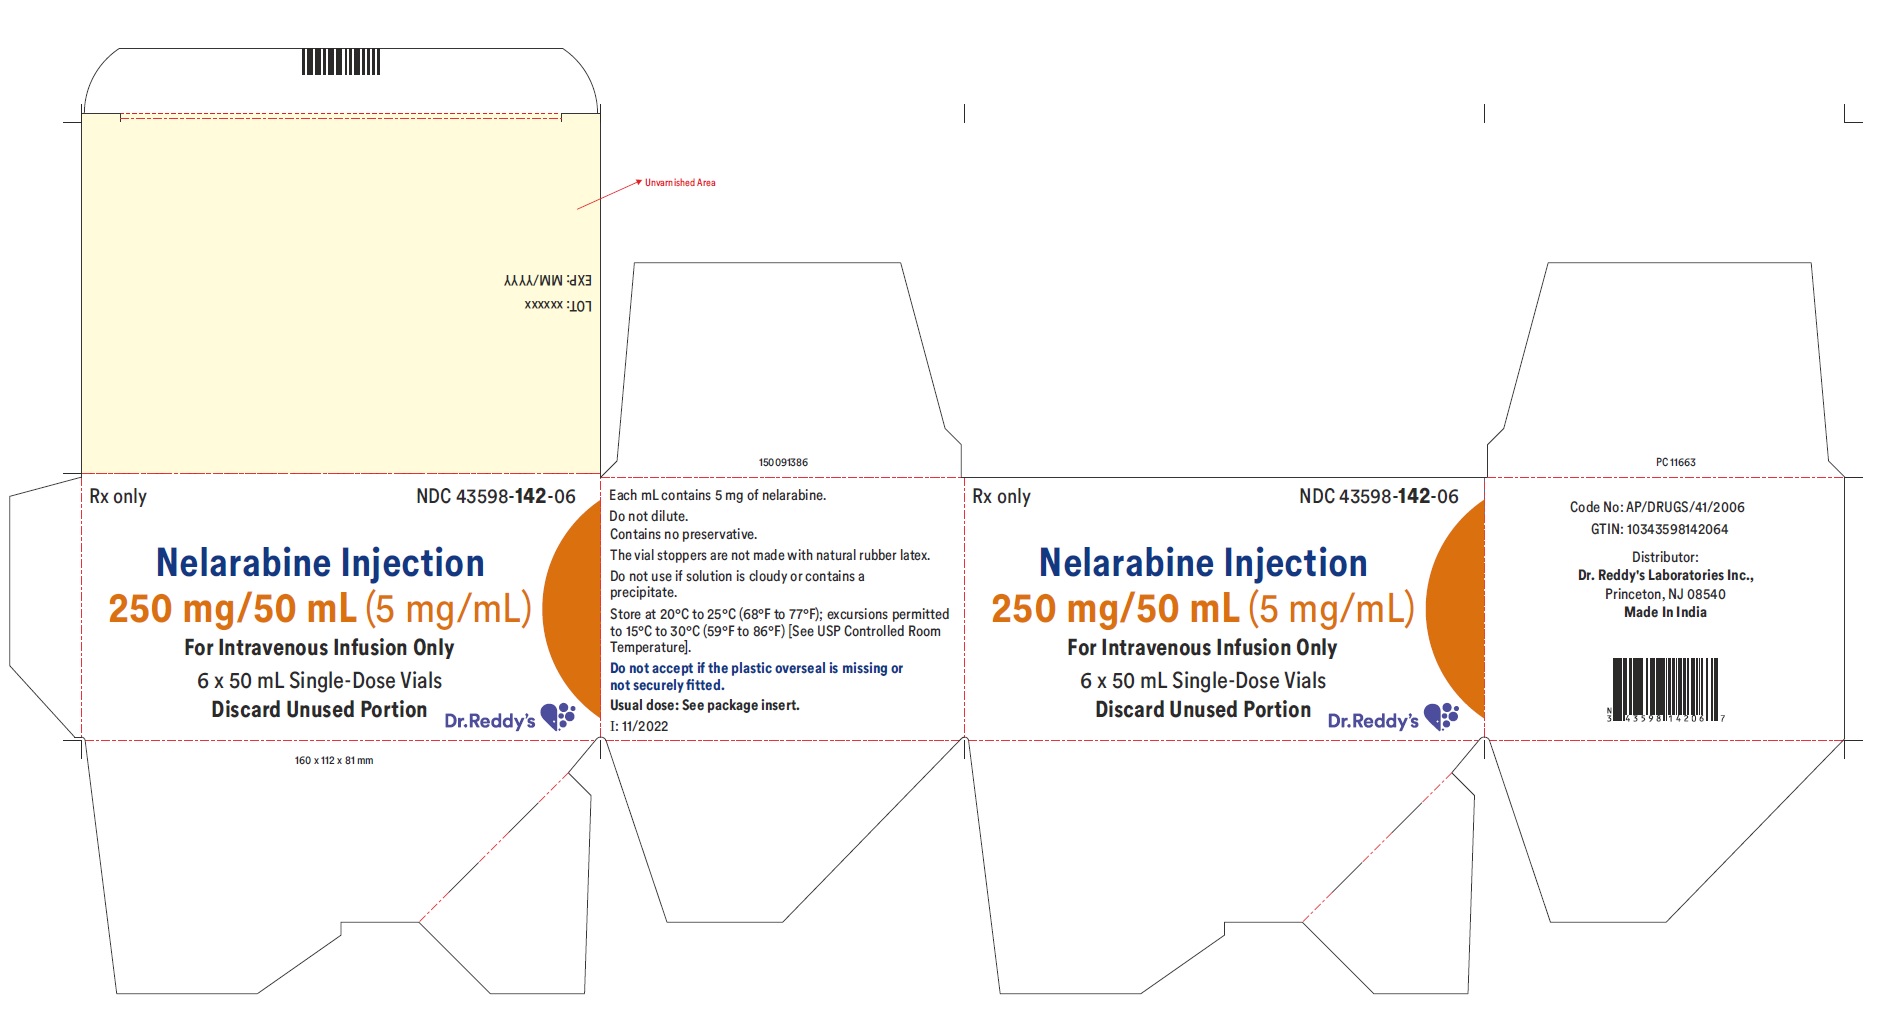
Nelarabine 5 mg/mL Injection — NDC 43598-142-06 (Billing 43598-0142-06)
This is a package of Nelarabine 5 mg/mL Injection from Dr. Reddy's Laboratories, Inc., marketed since Jan 2023 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 43598-142-06 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 43598 labeler · 142 product · 06 package
- Package marketed since
- Jan 9, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0343598142111, 0343598142067
- FDA record last changed
- Jul 24, 2026
Other active recalls for Nelarabine (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059981
- GCN: 25932
- GPI-14 (Medi-Span): 21300052002020
- HICL (First Databank): 033304
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 603566
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Nucleoside Metabolic Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Nelarabine is used to treat certain types of leukemia (cancer that begins in the white blood cells) and lymphoma (cancer that begins in the cells of the immune system) that have not improved or that have come back after treatment with other medications. Nelarabine is in a class of medications called antimetabolites. It works by killing cancer cells.
Read the full MedlinePlus article ↗- Nelarabine (Arranon) is a chemotherapy used for two types of aggressive blood cancers: T-cell acute lymphoblastic leukemia (T-ALL) and T-cell lymphoblastic lymphoma (T-LBL). It's s...
- Yes, absolutely. Nelarabine is given only by IV infusion in a clinical setting — it goes directly into a vein and has to be administered by trained healthcare professionals. You ca...
- How will I receive this medication — will I need to go to a clinic?
- The most important ones to act on right away are neurological — things like sudden severe drowsiness, confusion, seizures, muscle weakness, numbness or tingling that's getting wors...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nelarabine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9261 | $65.407 / J9261 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 43598-0142-06 You're viewing this | 6 VIAL, SINGLE-DOSE in 1 CARTON / 50 mL in 1 VIAL, SINGLE-DOSE | 2023-01-09 | — | Active |
| 43598-0142-11 43598-142-11 Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 50 mL in 1 VIAL, SINGLE-DOSE | 2023-03-01 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Nelarabine 5 mg/mL Injection?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Arranon 5 mg/mL 00078-0683-61 | Novartis | 50 ml | — | AP | Discontinued | — |
| Nelarabine 5 mg/mL 25021-0259-50 | Sagent | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 39822-0650-01 | XGen | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mLthis 43598-0142-06 | Dr. | 6 vials | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 46708-0813-50 | Alembic | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 62332-0813-50 | Alembic | 1 vial | — | AP | FDA listed | — |
| Arranon 5 mg/mL 66758-0165-94 | Sandoz | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 68083-0233-06 | Gland | 6 vials | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 70121-1743-04 | Amneal | 6 vials | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 70710-1726-01 | Zydus | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 70710-1839-01 | Zydus | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 70771-1685-01 | Zydus | 1 vial | — | AP | FDA listed | — |
| Nelarabine 5 mg/mL 71288-0165-53 | Meitheal | 6 vials | — | AP | Discontinued | — |
| Nelarabine 5 mg/mL 72205-0154-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
| nelarabine 5 mg/mL 81927-0111-01 | Shorla | 1 vial | — | — | FDA listed | — |
| nelarabine 5 mg/mL 81927-0375-01 | Shorla | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Dr. Reddy's Laboratories, Inc. labeler code 43598
- Hydroxychloroquine Sulfate 400 mg Tablet, Film Coated NDC 43598-131-01
- Hydroxychloroquine Sulfate 300 mg Tablet, Film Coated NDC 43598-132-01
- Hydroxychloroquine Sulfate 100 mg Tablet, Film Coated NDC 43598-133-01
- Ketorolac Tromethamine 10 mg Tablet, Film Coated NDC 43598-139-01
- CHLORPROMAZINE HCI 25 mg/mL Injection NDC 43598-140-25
- CHLORPROMAZINE HCI 25 mg/mL Injection NDC 43598-141-25
- Nintedanib 150 mg Capsule NDC 43598-147-60
- Nintedanib 100 mg Capsule NDC 43598-148-60
- eltrombopag 12.5 mg Tablet, Film Coated NDC 43598-151-30
- POTASSIUM CHLORIDE 40 meq/30mL Solution NDC 43598-160-01
- Lansoprazole 15 mg Capsule, Delayed Release NDC 43598-161-33
- JAVYGTOR Sapropterin Dihydrochloride 500 mg Powder, For Solution NDC 43598-162-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: NEUROLOGIC ADVERSE REACTIONS Severe neurologic adverse reactions have been reported with the use of nelarabine. These adverse reactions have included altered mental states including severe somnolence, central nervous system effects including convulsions, and peripheral neuropathy ranging from numbness and paresthesias to motor weakness and paralysis. There have also been reports of adverse reactions associated with demyelination, and ascending peripheral neuropathies similar in appearance to Guillain-Barré syndrome [ see Warnings and Precautions ( 5.1 ) ] .
Full recovery from these adverse reactions has not always occurred with cessation of therapy with nelarabine. Monitor frequently for signs and symptoms of neurologic toxicity during treatment with nelarabine injection. Discontinue nelarabine injection for neurologic adverse reactions of NCI Common Toxicity Criteria for Adverse Events (CTCAE) Grade 2 or greater [ see Warnings and Precautions ( 5.1 ) ] .
WARNING: NEUROLOGIC ADVERSE REACTIONS See full prescribing information for complete boxed warning. Severe neurologic adverse reactions have been reported with the use of nelarabine.These adverse reactions have included altered mental states including severe somnolence, central nervous system effects including convulsions, and peripheral neuropathy ranging from numbness and paresthesias to motor weakness and paralysis. There have also been reports of adverse reactions associated with demyelination, and ascending peripheral neuropathies similar in appearance to Guillain-Barré syndrome.
( 5.1 ) Full recovery from these adverse reactions has not always occurred with cessation of therapy with nelarabine. Monitor frequently for signs and symptoms of neurologic toxicity. Discontinue nelarabine injection for neurologic adverse reactions of NCI Common Toxicity Criteria for Adverse Events (CTCAE) Grade 2 or greater.
( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Nelarabine injection is indicated for the treatment of T-cell acute lymphoblastic leukemia (T-ALL) and T-cell lymphoblastic lymphoma (T-LBL) in adult and pediatric patients age 1 year and older whose disease has not responded to or has relapsed following treatment with at least 2 chemotherapy regimens. Nelarabine Injection is a nucleoside metabolic inhibitor indicated for the treatment of patients with T-cell acute lymphoblastic leukemia (T-ALL) and T-cell lymphoblastic lymphoma (T-LBL) in adult and pediatric patients age 1 year and older whose disease has not responded to or has relapsed following treatment with at least two chemotherapy regimens.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Adult Dose : 1,500 mg/m² administered by intravenous infusion over 2 hours on Days 1, 3, and 5 repeated every 21 days. ( 2.1 ) • Pediatric Dose : 650 mg/m² administered by intravenous infusion over 1 hour daily for 5 consecutive days repeated every 21 days. ( 2.1 ) • Discontinue treatment for neurologic reactions greater than or equal to Grade 2.
( 2.2 ) • Dosage may be delayed for hematologic reactions. ( 2.2 ) • Take measures to prevent hyperuricemia. ( 2.4 )
2.1Recommended Dosage This product is for intravenous use only. Adult Dosage : The recommended adult dose of nelarabine injection is 1,500 mg/m² administered by intravenous infusion over 2 hours on Days 1, 3, and 5 repeated every 21 days. Administer nelarabine injection undiluted.
Pediatric Dosage : The recommended pediatric dose of nelarabine injection is 650 mg/m² administered by intravenous infusion over 1 hour daily for 5 consecutive days repeated every 21 days. Administer nelarabine injection undiluted. The recommended duration of treatment for adult and pediatric patients has not been clearly established.
In clinical trials, treatment was generally continued until there was evidence of disease progression, the patient experienced unacceptable toxicity, the patient became a candidate for hematopoietic stem cell transplantation (HSCT), or the patient no longer continued to benefit from treatment.
2.2Dosage Modification Discontinue nelarabine injection if the patient develops a neurologic adverse reaction of NCI CTCAE Grade 2 or greater. Dosage may be delayed for other toxicity, including hematologic toxicity [ see Boxed Warning , Warnings and Precautions ( 5.1 , 5.2 ) ] .
2.3Dosage in Special Populations Nelarabine injection has not been studied in patients with renal or hepatic dysfunction [ see Use in Specific Populations ( 8.6 , 8.7 ) ] . No dose adjustment is recommended for patients with a creatinine clearance (CLCr) greater than or equal to 50 mL/min [ see Clinical Pharmacology ( 12.3 ) ] . There are insufficient data to support a dose recommendation for patients with a CLCr less than 50 mL/min.
2.4Prevention of Hyperuricemia Take precautions against hyperuricemia (e.g., hydration, urine alkalinization, and prophylaxis with allopurinol) [ see Warnings and Precautions ( 5.4 ) ] .
2.5Instructions for Handling, Preparation, and Administration Handling : Nelarabine is a hazardous drug. Caution should be used during handling and preparation. Use of gloves and other protective clothing to prevent skin contact is recommended.
Proper aseptic technique should be used. Guidelines for proper handling and disposal of anticancer drugs have been published. 1 Preparation and Administration : Administer nelarabine injection undiluted.
Transfer the appropriate dose of nelarabine injection into polyvinylchloride (PVC) infusion bags or glass containers and administer as a 2-hour infusion in adult patients and as a 1-hour infusion in pediatric patients. Prior to administration, inspect the drug product visually for particulate matter and discoloration. Stability : Nelarabine injection is stable in PVC infusion bags and glass containers for up to 8 hours at up to 30°C.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nelarabine injection 250 mg/50 mL (5 mg/mL) is supplied as a clear, colorless, sterile solution in Type I, clear glass single-dose vials with a gray chlorobutyl rubber stopper (not made with natural rubber latex) and a red snap-off aluminum seal. Injection: 250 mg/50 mL (5 mg/mL) single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Neurologic Adverse Reactions : Severe neurologic reactions have been reported. Monitor for signs and symptoms of neurologic toxicity. ( 5.1 ) • Hematologic Reactions : Complete blood counts including platelets should be monitored regularly.
( 5.2 ) • Embryo-Fetal Toxicity : Can cause fetal harm. Advise females of reproductive potential of the potential risk to the fetus and to use effective contraception; and advise males to use condoms. ( 5.3 , 8.1 , 8.3 ) • Effects on Ability to Drive and Use Machines : Somnolence may occur.
Advise patients to refrain from these activities until somnolence has resolved. ( 5.6 )
5.1Neurologic Adverse Reactions Nervous system adverse reactions of any grade were reported for 223 (76%) adult patients across the Phase I and Phase II trials, and Grade 3 or higher (severe, life-threatening, or fatal) adverse reactions were reported for 55 (19%) patients following initiation of nelarabine therapy [ see Adverse Reactions ( 6.1 )]. Based on patients with complete data, the median time to onset of first event is 5 days from start of first infusion (range: 1 to 166), and the median duration is 6 days (range: 1 to 393 days).
Nervous system adverse reactions of any grade were reported for 69 (42%) pediatric patients across the Phase I and Phase II trials, and Grade 3 or higher (severe, life-threatening, or fatal) adverse reactions were reported for 25 (15%) patients following initiation of nelarabine therapy [ see Adverse Reactions ( 6.1 ) ]. Based on patients with complete data, the median time to onset of first event is 8 days from start of first infusion (range: 1 to 269), and the median duration is 2 days (range: 1 to 82 days). Common signs and symptoms of nelarabine injection-related neurotoxicity include somnolence, headache, paresthesia and dysesthesia, dizziness, neuropathy (sensory and motor), cerebellar disturbances and tremor.
Severe neurologic toxicity can manifest as coma, status epilepticus, craniospinal demyelination, or ascending neuropathy similar in presentation to Guillain-Barré syndrome. Full recovery from these adverse reactions has not always occurred with cessation of therapy with nelarabine injection. Patients treated previously or concurrently with intrathecal chemotherapy or previously with craniospinal irradiation may be at increased risk for neurologic adverse events.
Monitor patients frequently for signs and symptoms of neurologic toxicity during and for at least 24 hours after completion of treatment with nelarabine injection. Discontinue nelarabine injection for neurologic adverse reactions of NCI CTCAE Grade 2 or greater and provide supportive care [ see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 )].
5.2Hematologic Adverse Reactions Leukopenia, thrombocytopenia, anemia, and neutropenia, including febrile neutropenia, have been associated with nelarabine injection therapy. Complete blood counts including platelets should be monitored regularly [ see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ) ] .
5.3Embryo-Fetal Toxicity Based on its mechanism of action and findings in animal studies, nelarabine can cause fetal harm when administered to a pregnant woman [ see Clinical Pharmacology ( 12.1 ) ] . In animal reproduction studies, intravenous administration of nelarabine to pregnant rabbits during the period of organogenesis resulted in teratogenicity at maternal doses below the recommended human adult dose of 1,500 mg/m 2 /day ( see Data ). Advise pregnant women of the potential risk to the fetus.
Advise females of reproductive potential to use effective contraception during treatment with nelarabine injection. Advise males with female partners of reproductive potential to use condoms during treatment with nelarabine injection and for 3 months after the last dose [ see Use in Specific Populations ( 8.1 , 8.3 ), Nonclinical Toxicology ( 13.1 ) ] .
5.4Tumor Lysis Syndrome Patients receiving nelarabine injection shoul… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically-significant adverse reactions are discussed in greater detail in other sections of the label: • Neurologic [ see Boxed Warning , Warnings and Precautions ( 5.1 ) ] • Hematologic [ see Warnings and Precautions ( 5.2 ) ] • Tumor Lysis Syndrome [ see Warnings and Precautions ( 5.4 ) ] • Effects on Ability to Drive and Use Machines [ see Warnings and Precautions ( 5.6 ) ] The most common (≥ 20%) adverse reactions were: • Adult : anemia, thrombocytopenia, neutropenia, nausea, diarrhea, vomiting, constipation, fatigue, pyrexia, cough, and dyspnea ( 6.1 ) • Pediatric : anemia, neutropenia, thrombocytopenia, and leukopenia ( 6.1) The most common (> 10%) neurological adverse reactions were: • Adult : somnolence, dizziness, peripheral neurologic disorders, hypoesthesia, headache, and paresthesia ( 6.1 ) • Pediatric : headache and peripheral neurologic disorders ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Dr.
Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Relapsed or Refractory T-ALL and T-LBL Nelarabine was studied in 459 patients in Phase I and Phase II clinical trials. Adult Patient: The safety profile of nelarabine is based on data from 103 adult patients treated with the recommended dose and schedule in 2 studies: an adult T-ALL/T-cell T-LBL trial and an adult chronic lymphocytic leukemia trial.
The most common adverse reactions in adults were fatigue; gastrointestinal disorders (nausea, diarrhea, vomiting, and constipation); hematologic disorders (anemia, neutropenia, and thrombocytopenia); respiratory disorders (cough and dyspnea); nervous system disorders (somnolence and dizziness); and pyrexia. The most common adverse reactions in adults by Body System, including severe or life-threatening adverse reactions (NCI CTCAE Grade 3 or Grade 4) and fatal adverse reactions (Grade 5) are shown in Table 1. Table 1.
Most Commonly Reported (≥ 5% Overall) Adverse Reactions in Adult Patients Treated With 1,500 mg/m 2 of Nelarabine Administered by Intravenous Infusion Over 2 Hours on Days 1, 3, and 5 Repeated Every 21 Days Percentage of Patients (N = 103) Body System Adverse Reaction Toxicity Grade Grade 3 % Grades 4 and5 a % All Grades % Blood and Lymphatic System Disorders Anemia 20 14 99 Thrombocytopenia 37 22 86 Neutropenia 14 49 81 Febrile neutropenia 9 1 12 Cardiac Disorders Sinus tachycardia 1 0 8 Gastrointestinal Disorders Nausea 0 0 41 Diarrhea 1 0 22 Vomiting 1 0 22 Constipation 1 0 21 Abdominal pain 1 0 9 Stomatitis 1 0 8 Abdominal distension 0 0 6 General Disorders and Administration Site Conditions Fatigue 10 2 50 Pyrexia 5 0 23 Asthenia 0 1 17 Edema, peripheral 0 0 15 Edema 0 0 11 Pain 3 0 11 Rigors 0 0 8 Gait, abnormal 0 0 6 Chest pain 0 0 5 Noncardiac chest pain 0 1 5 Infections Infection 2 1 9 Pneumonia 4 1 8 Sinusitis 1 0 7 Hepatobiliary Disorders AST increased 1 1 6 Metabolism and Nutrition Disorders Anorexia 0 0 9 Dehydration 3 1 7 Hyperglycemia 1 0 6 Musculoskeletal and Connective Tissue Disorders Myalgia 1 0 13 Arthralgia 1 0 9 Back pain 0 0 8 Muscular weakness 5 0 8 Painin extremity 1 0 7 Nervous System Disorders (see Table2) Psychiatric Disorders Confusional state 2 0 8 Insomnia 0 7 Depression 1 0 6 Respiratory, Thoracic, and Mediastinal Disorders Cough 0 0 25 Dyspnea 4 2 20 Pleural effusion 5 1 10 Epistaxis 0 0 8 Dyspnea, exertional 0 0 7 Wheezing 0 0 5 Vascular Disorders Petechiae 2 0 12 Hypotension 1 1 8 Abbreviation: AST, aspartate transaminase. a Five (5) patients had a fatal adverse reaction.
Fatal adverse reactions included hypotension (n = 1), respiratory arrest (n = 1), pleural effusion/pneumothorax (n = 1), pneumonia… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Administration of nelarabine injection in combination with adenosine deaminase (ADA) inhibitors, such as pentostatin, is not recommended [ see Clinical Pharmacology ( 12.3 ) ] . Administration in combination with adenosine deaminase (ADA) inhibitors, such as pentostatin, is not recommended. ( 7 , 12.3 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation : Advise not to breastfeed. ( 8.2 ) • Renal Impairment : Closely monitor patients with moderate or severe renal impairment for toxicities. ( 8.6 ) • Hepatic Impairment : Closely monitor patients with severe hepatic impairment for toxicities. ( 8.7 )
8.1Pregnancy Risk Summary Based on its mechanism of action and findings in animal studies, nelarabine can cause fetal harm when administered to a pregnant woman [ see Clinical Pharmacology ( 12.1 ) ]. Limited available data with nelarabine use in pregnant women are insufficient to determine a drug-associated risk for major birth defects, miscarriage or adverse maternal, or fetal outcomes. There are risks to the pregnant woman associated with untreated leukemia or lymphoma ( see Clinical Considerations ).
In animal reproduction studies, intravenous administration of nelarabine to pregnant rabbits during the period of organogenesis resulted in teratogenicity at maternal doses below the recommended human adult dose of 1,500 mg/m 2 /day ( see Data ). Advise pregnant women of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-fetal Risk There are risks to the mother from untreated leukemia or lymphoma, including anemia, thrombocytopenia, and death.
Data Animal Data In an embryo-fetal development study in which pregnant rabbits were administered daily doses of nelarabine during organogenesis, increased incidences of fetal malformations, anomalies, and variations were observed at doses greater than or equal to 360 mg/m 2 /day (8-hour IV infusion; approximately 25% of the recommended human adult dose compared on a mg/m 2 basis), which was the lowest dose tested. Cleft palate was seen in rabbits given 3,600 mg/m 2 /day (approximately 2-fold the adult dose), absent pollices (digits) in rabbits given greater than or equal to 1,200 mg/m 2 /day (approximately 75% of the recommended adult dose), while absent gall bladder, absent accessory lung lobes, fused or extra sternebrae, and delayed ossification was seen at all doses.
Maternal body weight gain and fetal body weights were reduced in rabbits given 3,600 mg/m 2 /day (approximately 2-fold the adult dose), but could not account for the increased incidence of malformations seen at this or lower administered doses.
8.2Lactation Risk Summary There are no data on the presence of nelarabine or ara-G in human or animal milk, the effect on the breastfed child, or the effect on milk production. Because of the potential for serious adverse reactions in the breastfed child from nelarabine, such as severe neurological reactions, advise women not to breastfeed during treatment with nelarabine.
8.3Females and Males of Reproductive Potential Pregnancy Testing Nelarabine can cause fetal harm when administered to a pregnant woman [ see Use in Specific Populations ( 8.1 ) ] . Verify the pregnancy status of females of reproductive potential prior to starting treatment with nelarabine injection. Contraception Females Nelarabine can cause fetal harm when administered to a pregnant woman [ see Warnings and Precautions ( 5.3 ), Use in Specific Population s ( 8.1 ) ] .
Because of the potential for genotoxicity, advise females of reproductive potential to use effective contraception during treatment with nelarabine injection. Males Because of the potential for genotoxicity, advise males (including those who have had vasectomies) with female partners of reproductive potential to use condoms during treatment with nelarabine injection and for 3 months after the last dose [ see Nonclinical Toxicology ( 13.1… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action and findings in animal studies, nelarabine can cause fetal harm when administered to a pregnant woman [ see Clinical Pharmacology ( 12.1 ) ]. Limited available data with nelarabine use in pregnant women are insufficient to determine a drug-associated risk for major birth defects, miscarriage or adverse maternal, or fetal outcomes. There are risks to the pregnant woman associated with untreated leukemia or lymphoma ( see Clinical Considerations ).
In animal reproduction studies, intravenous administration of nelarabine to pregnant rabbits during the period of organogenesis resulted in teratogenicity at maternal doses below the recommended human adult dose of 1,500 mg/m 2 /day ( see Data ). Advise pregnant women of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-fetal Risk There are risks to the mother from untreated leukemia or lymphoma, including anemia, thrombocytopenia, and death.
Data Animal Data In an embryo-fetal development study in which pregnant rabbits were administered daily doses of nelarabine during organogenesis, increased incidences of fetal malformations, anomalies, and variations were observed at doses greater than or equal to 360 mg/m 2 /day (8-hour IV infusion; approximately 25% of the recommended human adult dose compared on a mg/m 2 basis), which was the lowest dose tested. Cleft palate was seen in rabbits given 3,600 mg/m 2 /day (approximately 2-fold the adult dose), absent pollices (digits) in rabbits given greater than or equal to 1,200 mg/m 2 /day (approximately 75% of the recommended adult dose), while absent gall bladder, absent accessory lung lobes, fused or extra sternebrae, and delayed ossification was seen at all doses.
Maternal body weight gain and fetal body weights were reduced in rabbits given 3,600 mg/m 2 /day (approximately 2-fold the adult dose), but could not account for the increased incidence of malformations seen at this or lower administered doses.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of nelarabine for relapsed or refractory T-ALL and T-LBL has been established in pediatric patients age 1 year and older. The effectiveness of nelarabine in pediatric patients is supported by one single-arm clinical trial, and safety has been asssessed in 165 pediatric patients age 1 year and older across multiple Phase I and Phase II trials. The trial establishing efficacy included 84 patients age 21 years and younger, who had relapsed or refractory T-ALL or T-LBL.
The most frequent adverse reactions of any grade occurring on treatment in this study were hematologic laboratory abnormalities. Hematologic toxicity observed in the pediatric population was higher than that seen in the adult population. [ see Dosage and Administration ( 2.1 ), Adverse Reactions ( 6.1 ), Clinical Studies ( 14.2 ) ] . Nervous system adverse reactions have been reported for 42% of pediatric patients across the Phase I and Phase II trials.
The incidence of nervous system adverse reactions was less in the pediatric population than that seen in adult patients with relapsed/refractory T-ALL/T-LBL [ see Adverse Reactions ( 6.1 )] . In a phase III study of nelarabine in combination with multi-agent chemotherapy as first-line therapy, there were 411 patients with T-ALL or T-LBL treated with nelarabine. The safety profile in the 357 patients age 1 to 16 years was consistent with that seen in older patients in the study. [ see Adverse Reactions ( 6.1 ) ] .
Due to lack of long-term follow up data, a determination of the impact of nelarabine on the growth and pubertal development of pediatric patients cannot be made.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of nelarabine did not include sufficient numbers of patients age 65 and over to determine whether they respond differently from younger patients. In an exploratory analysis, increasing age, especially age 65 years and older, appeared to be associated with increased rates of neurologic adverse reactions. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection [ see Use in Specific Populations ( 8.6 ) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no known antidote for overdoses of nelarabine injection. It is anticipated that overdosage would result in severe neurotoxicity (possibly including paralysis, coma), myelosuppression, and potentially death. In the event of overdose, supportive care consistent with good clinical practice should be provided.
At a dose of 2,200 mg/m 2 given on Days 1, 3, and 5 every 21 days, 2 patients developed a significant Grade 3 ascending sensory neuropathy. Magnetic resonance imaging evaluations of the 2 patients demonstrated findings consistent with a demyelinating process in the cervical spine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Nelarabine is a prodrug of the deoxyguanosine analogue 9-β-D-arabinofuranosylguanine (ara-G), a nucleoside metabolic inhibitor. Nelarabine is demethylated by ADA to ara-G, mono-phosphorylated by deoxyguanosine kinase and deoxycytidine kinase, and subsequently converted to the active 5’-triphosphate, ara-GTP. Accumulation of ara-GTP in leukemic blasts allows for incorporation into deoxyribonucleic acid (DNA), leading to inhibition of DNA synthesis and cell death.
Other mechanisms may contribute to the cytotoxic and systemic toxicity of nelarabine.
12.3Pharmacokinetics Absorption : Following intravenous administration of nelarabine to adult patients with refractory leukemia or lymphoma, plasma ara-G C max values generally occurred at the end of the nelarabine infusion and were generally higher than nelarabine C max values, suggesting rapid and extensive conversion of nelarabine to ara-G. Mean plasma nelarabine and ara-G C max values were 5 ± 3 mcg/mL and 31.4 ± 5.6 mcg/mL, respectively, after a 1,500 mg/m 2 nelarabine dose infused over 2 hours in adult patients.
The area under the concentration-time curve (AUC) of ara-G is 37 times higher than that for nelarabine on Day 1 after nelarabine IV infusion of 1,500 mg/m 2 dose (162 ± 49 mcg·h/mL versus 4.4 ± 2.2 mcg·h/mL, respectively). Comparable C max and AUC values were obtained for nelarabine between Days 1 and 5 at the nelarabine adult dosage of 1,500 mg/m 2 , indicating that nelarabine does not accumulate after multiple-dosing. There are not enough ara-G data to make a comparison between Day 1 and Day 5.
After a nelarabine adult dose of 1,500 mg/m 2 , intracellular C max for ara-GTP appeared within 3 to 25 hours on Day 1. Exposure (AUC) to intracellular ara-GTP was 532 times higher than that for nelarabine and 14 times higher than that for ara-G (2,339 ± 2,628 mcg·h/mL versus 4.4 ± 2.2 mcg·h/mL and 162 ± 49 mcg·h/mL, respectively). Because the intracellular levels of ara-GTP were so prolonged, its elimination half-life could not be accurately estimated.
Distribution : Nelarabine and ara-G are extensively distributed throughout the body. For nelarabine, V SS values were 197 ± 216 L/m 2 in adult patients. For ara-G, V SS /F values were 50 ± 24 L/m 2 in adult patients.
Nelarabine and ara-G are not substantially bound to human plasma proteins (< 25%) in vitro , and binding is independent of nelarabine or ara-G concentrations up to 600 mcM. Metabolism : The principal route of metabolism for nelarabine is O-demethylation by ADA to form ara-G, which undergoes hydrolysis to form guanine. In addition, some nelarabine is hydrolyzed to form methylguanine, which is O-demethylated to form guanine.
Guanine is N-deaminated to form xanthine, which is further oxidized to yield uric acid. Excretion : Nelarabine and ara-G are partially eliminated by the kidneys. Mean urinary excretion of nelarabine and ara-G was 6.6 ± 4.7% and 27 ± 15% of the administered dose, respectively, in 28 adult patients over the 24 hours after nelarabine infusion on Day 1.
Renal clearance averaged 24 ± 23 L/h for nelarabine and 6.2 ± 5 L/h for ara-G in 21 adult patients. Combined Phase I pharmacokinetic data at nelarabine doses of 199 to 2,900 mg/m 2 (n = 66 adult patients) indicate that the mean clearance (CL) of nelarabine is 197 ± 189 L/h/m 2 on Day 1. The apparent clearance of ara-G (CL/F) is 10.5 ±
4.5L/h/m 2 on Day 1. Nelarabine and ara-G are rapidly eliminated from plasma with a mean half-life of 18 minutes and 3.2 hours, respectively, in adult patients. Pediatrics : No pharmacokinetic data are available in pediatric patients at the once-daily 650 mg/m 2 nelarabine dosage.
Combined Phase I pharmacokinetic data at nelarabine doses of 104 to 2,900 mg/m 2 indicate that the mean clearance (CL) of nelarabine is about 30% higher in pediatric patients than in adult patients (259 ± 409 L/h/m 2 versus 197 ± 189 L/h/m 2 , respectively) (n = 66 adults, n = 22 pediatric patie… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Nelarabine is a prodrug of the deoxyguanosine analogue 9-β-D-arabinofuranosylguanine (ara-G), a nucleoside metabolic inhibitor. Nelarabine is demethylated by ADA to ara-G, mono-phosphorylated by deoxyguanosine kinase and deoxycytidine kinase, and subsequently converted to the active 5’-triphosphate, ara-GTP. Accumulation of ara-GTP in leukemic blasts allows for incorporation into deoxyribonucleic acid (DNA), leading to inhibition of DNA synthesis and cell death.
Other mechanisms may contribute to the cytotoxic and systemic toxicity of nelarabine.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Nelarabine injection is supplied as a clear, colorless, sterile solution in Type I, clear glass single-dose vials with a gray chlorobutyl rubber stopper (not made with natural rubber latex) and a red snap-off aluminum seal. Each vial contains 250 mg of nelarabine (5 mg nelarabine per mL) and the inactive ingredient sodium chloride (4.5 mg per mL) in 50 mL Water for Injection, USP. Single-dose Vials (NDC 43598-142-11) are available in the following carton size: (NDC 43598-142-11) (package of 1).
NDC 43598‑142-06 (package of 6). Store nelarabine injection between 20°C and 25°C (68°F and 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. Discard Unused Portion.
📋 Description ▾
11 DESCRIPTION Nelarabine is a prodrug of the cytotoxic deoxyguanosine analogue, 9-β-Darabinofuranosylguanine (ara-G). The chemical name for nelarabine is 2-amino-9-β-D-arabinofuranosyl-6-methoxy-9H-purine. It has the molecular formula C 11 H 15 N 5 O 5 and a molecular weight of 297.27.
Nelarabine has the following structural formula: Nelarabine is soluble in dimethylformamide, slightly soluble in water, practically insoluble in acetone, and melts with decomposition between 209°C and 214°C. Nelarabine Injection is supplied as a clear, colorless, sterile solution in glass single-dose vials. Each vial contains 250 mg of nelarabine (5 mg nelarabine per mL) and the inactive ingredient sodium chloride (4.5 mg per mL) in 50 mL, Water for Injection, USP.
Nelarabine injection is intended for intravenous infusion. Hydrochloric acid and sodium hydroxide may have been used to adjust the pH. The solution pH ranges from 5 to 7.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Hematologic Adverse Reactions • Advise patients that leukopenia, thrombocytopenia, anemia, and neutropenia, including febrile neutropenia, have been associated with nelarabine injection. • Advise patients that complete blood counts, including platelets, will be monitored regularly during treatment [ see Warnings and Precautions ( 5.2 ), Adverse Reactions ( 6.1 ) ] Embryo-Fetal Toxicity • Advise pregnant females of reproductive potential and males with female partners of reproductive potential of the potential risk to the fetus.
Advise females of reproductive potential to use effective contraception during treatment with nelarabine injection. Instruct females to inform their physician of a known or suspected pregnancy. • Advise male patients with partners of reproductive potential to use condoms during treatment with nelarabine injection and for 3 months after the last dose [ see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.1 , 8.3 ) ] . Tumor Lysis Syndrome • Advise patients of the risk of tumor lysis syndrome [ see Warnings and Precautions ( 5.4 ), Adverse Reactions ( 6.1 ) ] .
Vaccinations • Instruct patients not to receive live vaccines during treatment with nelarabine injection [ see Warnings and Precautions ( 5.5 ), Adverse Reactions ( 6.1 ) ] Effects on Ability to Drive and Use Machines • Patients receiving nelarabine injection may experience somnolence during and for several days after treatment. Instruct patients to not drive or engage in hazardous occupations or activities until somnolence has resolved [ see Warnings and Precautions ( 5.6 ), Adverse Reactions ( 6.1 ) ] . Neurologic Adverse Reactions • Instruct patients to contact their physician if they experience new or worsening symptoms of peripheral neuropathy [ see Boxed Warning , Dosage and Administration ( 2.3 ), Warnings and Precautions ( 5.1 ), Adverse Reactions ( 6.1 ) ] .
These signs and symptoms include: tingling or numbness in fingers, hands, toes, or feet; difficulty with the fine motor coordination tasks such as buttoning clothing; unsteadiness while walking; weakness arising from a low chair; weakness in climbing stairs; increased tripping while walking over uneven surfaces. • Advise patients of the risk of seizures [ see Adverse Reactions ( 6.1 ) ] . If a seizure occurs, instruct patients to promptly notify the physician administering nelarabine injection. Infection • Instruct patients to promptly notify their physician if they develop fever or signs of infection while on therapy [ see Adverse Reactions ( 6.1 , 6.2 ) ] .
Lactation • Advise women not to breastfeed during treatment with nelarabine injection [ see Use in Specific Populations ( 8.2 ) ] . Rx only Distributor: Dr. Reddy’s Laboratories Inc., Princeton, NJ 08540 Made in India
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Pregnancy Testing Nelarabine can cause fetal harm when administered to a pregnant woman [ see Use in Specific Populations ( 8.1 ) ] . Verify the pregnancy status of females of reproductive potential prior to starting treatment with nelarabine injection. Contraception Females Nelarabine can cause fetal harm when administered to a pregnant woman [ see Warnings and Precautions ( 5.3 ), Use in Specific Population s ( 8.1 ) ] .
Because of the potential for genotoxicity, advise females of reproductive potential to use effective contraception during treatment with nelarabine injection. Males Because of the potential for genotoxicity, advise males (including those who have had vasectomies) with female partners of reproductive potential to use condoms during treatment with nelarabine injection and for 3 months after the last dose [ see Nonclinical Toxicology ( 13.1 ) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption : Following intravenous administration of nelarabine to adult patients with refractory leukemia or lymphoma, plasma ara-G C max values generally occurred at the end of the nelarabine infusion and were generally higher than nelarabine C max values, suggesting rapid and extensive conversion of nelarabine to ara-G. Mean plasma nelarabine and ara-G C max values were 5 ± 3 mcg/mL and 31.4 ± 5.6 mcg/mL, respectively, after a 1,500 mg/m 2 nelarabine dose infused over 2 hours in adult patients.
The area under the concentration-time curve (AUC) of ara-G is 37 times higher than that for nelarabine on Day 1 after nelarabine IV infusion of 1,500 mg/m 2 dose (162 ± 49 mcg·h/mL versus 4.4 ± 2.2 mcg·h/mL, respectively). Comparable C max and AUC values were obtained for nelarabine between Days 1 and 5 at the nelarabine adult dosage of 1,500 mg/m 2 , indicating that nelarabine does not accumulate after multiple-dosing. There are not enough ara-G data to make a comparison between Day 1 and Day 5.
After a nelarabine adult dose of 1,500 mg/m 2 , intracellular C max for ara-GTP appeared within 3 to 25 hours on Day 1. Exposure (AUC) to intracellular ara-GTP was 532 times higher than that for nelarabine and 14 times higher than that for ara-G (2,339 ± 2,628 mcg·h/mL versus 4.4 ± 2.2 mcg·h/mL and 162 ± 49 mcg·h/mL, respectively). Because the intracellular levels of ara-GTP were so prolonged, its elimination half-life could not be accurately estimated.
Distribution : Nelarabine and ara-G are extensively distributed throughout the body. For nelarabine, V SS values were 197 ± 216 L/m 2 in adult patients. For ara-G, V SS /F values were 50 ± 24 L/m 2 in adult patients.
Nelarabine and ara-G are not substantially bound to human plasma proteins (< 25%) in vitro , and binding is independent of nelarabine or ara-G concentrations up to 600 mcM. Metabolism : The principal route of metabolism for nelarabine is O-demethylation by ADA to form ara-G, which undergoes hydrolysis to form guanine. In addition, some nelarabine is hydrolyzed to form methylguanine, which is O-demethylated to form guanine.
Guanine is N-deaminated to form xanthine, which is further oxidized to yield uric acid. Excretion : Nelarabine and ara-G are partially eliminated by the kidneys. Mean urinary excretion of nelarabine and ara-G was 6.6 ± 4.7% and 27 ± 15% of the administered dose, respectively, in 28 adult patients over the 24 hours after nelarabine infusion on Day 1.
Renal clearance averaged 24 ± 23 L/h for nelarabine and 6.2 ± 5 L/h for ara-G in 21 adult patients. Combined Phase I pharmacokinetic data at nelarabine doses of 199 to 2,900 mg/m 2 (n = 66 adult patients) indicate that the mean clearance (CL) of nelarabine is 197 ± 189 L/h/m 2 on Day 1. The apparent clearance of ara-G (CL/F) is 10.5 ±
4.5L/h/m 2 on Day 1. Nelarabine and ara-G are rapidly eliminated from plasma with a mean half-life of 18 minutes and 3.2 hours, respectively, in adult patients. Pediatrics : No pharmacokinetic data are available in pediatric patients at the once-daily 650 mg/m 2 nelarabine dosage.
Combined Phase I pharmacokinetic data at nelarabine doses of 104 to 2,900 mg/m 2 indicate that the mean clearance (CL) of nelarabine is about 30% higher in pediatric patients than in adult patients (259 ± 409 L/h/m 2 versus 197 ± 189 L/h/m 2 , respectively) (n = 66 adults, n = 22 pediatric patients) on Day 1. The apparent clearance of ara-G (CL/F) is comparable between the 2 groups (10.5 ±
4.5L/h/m 2 in adult patients and 11.3 ±
4.2L/h/m 2 in pediatric patients) on Day 1. Nelarabine and ara-G are extensively distributed throughout the body. For nelarabine, V SS values were 213 ± 358 L/m 2 in pediatric patients. For ara-G, V SS /F values were 33 ±
9.3L/m 2 in pediatric patients. Nelarabine and ara-G are rapidly eliminated from plasma in pediatric patients, with a half-life of 13 minutes and 2 hours, respectively. Effect of Age : Age has no effect on the pharmacokinetics of nelarabine… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adult Clinical Trial in Relapsed or Refractory T-ALL and T-LBL The safety and efficacy of nelarabine in adult patients were studied in a clinical trial which included 39 treated patients, 28 who had T-ALL or T-LBL that had relapsed following or was refractory to at least two prior induction regimens. A 1,500 mg/m 2 dose of nelarabine was administeredby intravenous infusion over 2 hours on Days 1, 3, and 5 repeated every 21 days. Patients who experienced signs or symptoms of Grade 2 or greater neurologic toxicity on therapy were to be discontinued from further therapy with nelarabine.
Seventeen patients had a diagnosis of T-ALL and 11 had a diagnosis of T-LBL. For patients with ≥ 2 prior inductions, the age range was 16 to 65 years (mean: 34 years) and most patients were male (82%) and Caucasian (61%).Patients with central nervous system (CNS) disease were not eligible. Complete response (CR) in this trial was defined as bone marrow blast counts ≤ 5%, no other evidence of disease, and full recovery of peripheral blood counts.
Complete response without complete hematologic recovery (CR*) was also assessed. The results of the trial for patients who had received ≥ 2 prior inductions are shown in Table 5. Table 5.
Efficacy Results in Adult Patients With ≥ 2 Prior Inductions Treated With 1,500 mg/m 2 of Nelarabine Administered by Intravenous Infusion Over 2 Hours on Days 1, 3, and 5 Repeated Every 21 Days N = 28 CR plus CR* % (n) [95% CI] 21% (6) [8%, 41%] CR % (n) [95% CI] 18% (5) [6%, 37%] CR* % (n) [95% CI] 4% (1) [0%, 18%] Duration of CR plus CR* (range in weeks) a 4 to 195+ Median overall survival (weeks) [95% CI] 20.6 weeks [10.4, 36.4] Abbreviations: CR, complete response; CI, confidence interval; CR*, complete response without hematologic recovery. a Does not include 1 patient who was transplanted (duration of response was 156+ weeks).
The mean number of days on therapy was 56 days (range of 10 to 136 days). Time to CR plus CR* ranged from 2.9 to 11.7 weeks.
14.2Pediatric Clinical Trial in Relapsed or Refractory T-ALL and T-LBL The safety and efficacy of nelarabine in pediatric patients were studied in a clinical trial which included patients age 21 years and younger, who had relapsed or refractory T-ALL or T-LBL. Eighty-four (84) patients, 39 of whom had received two or more prior induction regimens, were treated with 650 mg/m 2 /day of nelarabine administered by intravenous infusion over 1 hour daily for 5 consecutive days repeated every 21 days (see Table 6). Patients who experienced signs or symptoms of Grade 2 or greater neurologic toxicity on therapy were to be discontinued from further therapy with nelarabine.
Table 6. Pediatric Clinical Trial - Patient Allocation Patient Population N Patients treated at 650 mg/m 2 /day x 5 days,every 21 days 84 Patients with T-ALL or T-LBL with two or more prior induction treated at 650 mg/m 2 /day x 5 days, every 21 days 39 Patients with T-ALL or T-LBL with one prior induction treated at 650 mg/m 2 /day x 5 days, every 21 days 31 Abbreviations: T-ALL, T-cell acute lymphoblastic leukemia; T-LBL, T-cell lymphoblastic lymphoma. The 84 patients ranged in age from 2.5 to 21.7 years (overall mean: 11.9 years), 52% were 3 to 12 years of age and most were male (74%) and Caucasian (62%).
The majority (77%) of patients had a diagnosis of T-ALL. Complete response (CR) in this trial was defined as bone marrow blast counts ≤ 5%, no other evidence of disease, and full recovery of peripheral blood counts. Complete response without full hematologic recovery (CR*) was also assessed as a meaningful outcome in this trial.
Duration of response is reported from date of response to date of relapse, and may include subsequent stem cell transplant. Efficacy results are presented in Table 7. Table 7.
Efficacy Results in Patients Age 21 Years and Younger at Diagnosis With ≥ 2 Prior Inductions Treated With 650 mg/m 2 of Nelarabine Administered by Intravenous Infusion Over 1 Hour Dail… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity testing of nelarabine has not been done. However, nelarabine was mutagenic when tested in vitro in L5178Y/TK mouse lymphoma cells with and without metabolic activation. No studies have been conducted in animals to assess genotoxic potential or effects on fertility. The effect on human fertility is unknown.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity testing of nelarabine has not been done. However, nelarabine was mutagenic when tested in vitro in L5178Y/TK mouse lymphoma cells with and without metabolic activation. No studies have been conducted in animals to assess genotoxic potential or effects on fertility. The effect on human fertility is unknown.
📚 References ▾
15 REFERENCES 1. “OSHA Hazardous Drugs.” OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Patient Package Insert ▾
P ATIENT INFORMATION Nelarabine (nel ar' a been) Injection Read the Patient Information that comes with nelarabine injection before you or your child starts treatment with nelarabine injection. Read the information you get each time before each treatment with nelarabine injection. There may be new information.
This information does not take the place of talking with the doctor about your or your child’s medical condition or treatment. Talk to your or your child’s doctor, if you have any questions. What is the most important information I should know about nelarabine injection ?
Nelarabine injection may cause blood related adverse reactions. Your doctor will do blood tests regularly during treatment to monitor blood counts, including platelets. Nelarabine injection may cause serious nervous system problems including: extreme sleepiness seizures coma numbness and tingling in the hands, fingers, feet, or toes (peripheral neuropathy) weakness and paralysis Call the doctor right away if you or your child has the following symptoms: seizures numbness and tingling in the hands, fingers, feet, or toes problems with fine motor skills such as buttoning clothes unsteadiness while walking increased tripping while walking weakness when getting out of a chair or walking upstairs These symptoms may not go away even when treatment with nelarabine injection is stopped.
What is nelarabine injection ? Nelarabine injection is an anti-cancer medicine used to treat adults and children who have: T-cell acute lymphoblastic leukemia (T-ALL) T-cell lymphoblastic lymphoma (T-LBL) What should you tell the doctor before you or your child starts nelarabine injection ? Tell the doctor about all health conditions you or your child have, including if you or your child: have any nervous system problems. have kidney problems. are breastfeeding or plan to breastfeed.
It is not known whether nelarabine passes through breast milk. You should not breastfeed during treatment with nelarabine injection. are pregnant or plan to become pregnant. Nelarabine injection can harm your unborn baby.
You should not become pregnant while you are taking nelarabine injection.You should use effective birth control to avoid getting pregnant. Talk with your doctor about your choices. are male (including if you have had a vasectomy) with a sexual partner who is pregnant, think that they may be pregnant, or who could become pregnant. You should use condoms during sexual intercourse during treatment with nelarabine injection and for 3 months after last dose.
Tell the doctor about all the medicines you or your child take, including prescription and nonprescription medicines, vitamins, and herbal supplements. How is nelarabine injection given? Nelarabine injection is an intravenous medicine.
This means it is given through a tube in your vein. What should you or your child avoid during treatment with nelarabine injection ? You or your child should not drive or operate dangerous machines.
Nelarabine injection may cause sleepiness during and for several days after treatment. You or your child should not receive vaccines made with live germs during treatment with nelarabine injection. What are the possible side effects of nelarabine injection ?
Nelarabine injection may cause serious nervous system problems. See “What is the most important information I should know about nelarabine injection?” Nelarabine injection may also cause: decreased blood counts such as low red blood cells, low white blood cells, and low platelets. Blood tests should be done regularly to check blood counts.
Call the doctor right away if you or your child: is more tired than usual, pale, or has trouble breathing has a fever or other signs of an infection bruises easy or has any unusual bleeding stomach area problems such as nausea, vomiting, diarrhea, and constipation headache sleepiness blurry eyesight Call your doctor right away if you experience unexplained muscle pain, tenderness, or weakness while taking nelarabine… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL PRINCIPAL DISPLAY PANEL SECTION Nelarabine Injection, 250 mg/50 mL (5 mg/mL) - Vial Label
Nelarabine Injection, 250 mg/50 mL (5 mg/mL) - Carton Label-6's package
Nelarabine Injection, 250 mg/50 mL (5 mg/mL) - Carton Label-1's package
Medicaid utilization by pack size
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |