
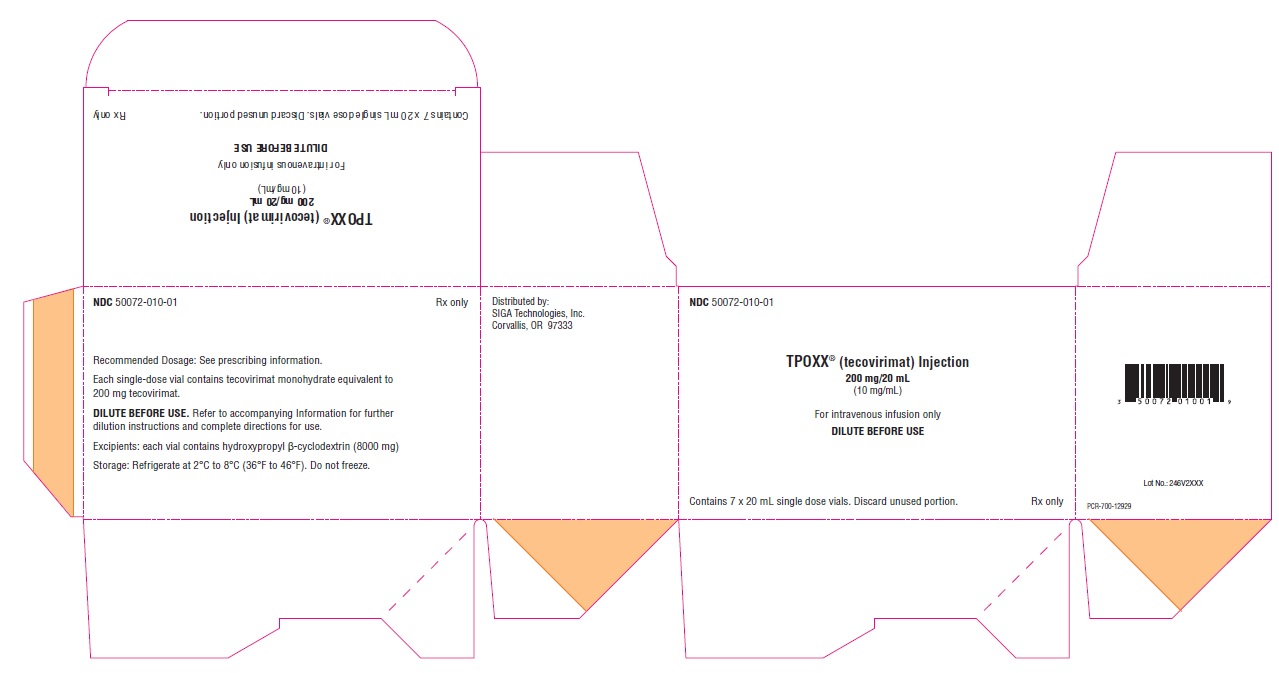
TPOXX tecovirimat monohydrate 10 mg/mL Injection, Solution, Concentrate
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Orthopoxvirus VP37 Envelope Wrapping Protein Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tpoxx 10 mg/mLthis 50072-0010-01 | SIGA | 7 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7737168 ↗ | Method of use | U-3377 | Sep 4, 2031 |
| US 9907859 ↗ | Method of use | U-3377 | Aug 2, 2031 |
| US 10576165 ↗ | Drug product | — | Aug 2, 2031 |
| US 8039504 ↗ | Drug product | — | Jul 23, 2027 |
| US 9233097 ↗ | Drug product | — | Aug 2, 2031 |
Is there a generic version of TPOXX 200 MG/20 ML (STOCKPILE)?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 50072-0010-01 You're viewing this | 7 VIAL in 1 CARTON (50072-010-01) / 20 mL in 1 VIAL (50072-010-30) | 2022-05-31 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TPOXX is an inhibitor of the orthopoxvirus VP37 envelope wrapping protein and is indicated for the treatment of human smallpox disease in adults and pediatric patients weighing at least 3 kg. ( 1.1 ) Limitations of Use: The effectiveness of TPOXX for treatment of smallpox disease has not been determined in humans because adequate and well-controlled field trials have not been feasible, and inducing smallpox disease in humans to study the drug’s efficacy is not ethical. ( 1.2 ) TPOXX efficacy may be reduced in immunocompromised patients based on studies demonstrating reduced efficacy in immunocompromised animal models.
( 1.2 )
1.1Treatment of Human Smallpox Disease TPOXX ® is indicated for the treatment of human smallpox disease caused by variola virus in adults and pediatric patients weighing at least 3 kg.
1.2Limitations of Use The effectiveness of TPOXX for treatment of smallpox disease has not been determined in humans because adequate and well-controlled field trials have not been feasible, and inducing smallpox disease in humans to study the drug’s efficacy is not ethical [see Clinical Studies ( 14 )] . TPOXX efficacy may be reduced in immunocompromised patients based on studies demonstrating reduced efficacy in immunocompromised animal models.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Pediatric and Adult Patients weighing 40 kg or more ( 2.3 ) (Oral Dosing): 40 kg to less than 120 kg: 600 mg of TPOXX every 12 hours for 14 days 120 kg or more: 600 mg of TPOXX every 8 hours for 14 days Pediatrics and adult patients weighing 13 kg or more and those who cannot swallow capsules ( 2.3 ) (Oral Dosing): TPOXX Capsules can be administered by carefully opening the number of capsule noted below and mixing and administering the entire contents in 30 mL of liquid (e.g., milk, chocolate milk) or soft food (e.g., apple sauce, yogurt): 13 kg to less than 25 kg: 200 mg (1 Capsule) of TPOXX every 12 hours for 14 days 25 kg to less than 40 kg: 400 mg (2 Capsules) of TPOXX every 12 hours for 14 days 40 kg to less than 120 kg: 600 mg (3 Capsules) of TPOXX every 12 hours for 14 days 120 kg or more: 600 mg (3 capsules) every 8 hours for 14 days Patients weighing 3 kg and above ( 2.5 ) (Intravenous Dosing): 3 kg to less than 35 kg: 6 mg/kg every 12 hours by intravenous infusion over 6 hours for up to 14 days 35 kg to less than 120 kg: 200 mg every 12 hours by intravenous infusion over 6 hours for up to 14 days 120 kg and above: 300 mg every 12 hours by intravenous infusion over 6 hours for up to 14 days Pediatric patients weighing 13 kg or more should be switched to TPOXX Capsules to complete the 14-day treatment course as soon as oral therapy can be tolerated.
Administration Instruction for TPOXX Capsules: Take within 30 minutes after a full meal containing moderate or high fat. ( 2.1 , 2.3 ) Administration Instructions for TPOXX Injection: Infuse over 6 hours via infusion pump. ( 2.5 ) See Full Prescribing Information for additional information on the administration and preparation of TPOXX Capsules and Injection.
( 2 )
2.1Important Dosing Instructions It is recommended that patients 13 kg and above initiate oral treatment with TPOXX capsules if possible. If patients are unable to take oral TPOXX capsules or Drug-Food Preparation, treatment may be initiated with TPOXX injection as a 6 hour intravenous (IV) infusion. If IV treatment is necessary, conversion from IV to oral TPOXX is recommended as soon as oral treatment can be tolerated [see Dosage and Administration ( 2.3 )] .
In patients receiving an IV infusion, the first dose of oral treatment should be given at the time of and in place of the next scheduled IV dosing. In patients receiving an oral treatment who subsequently require IV treatment, the first dose of IV infusion should be given at the time of and in place of the next scheduled oral dosing. TPOXX capsules Take TPOXX capsules within 30 minutes after a full meal containing moderate or high fat.
Missed Dose If a dose of oral TPOXX is missed, the patient should take the dose as soon as possible and anytime up to 8 hours prior to the next scheduled dose. If less than 8 hours remain before the next scheduled dose, do not take the missed dose, and resume dosing at the next scheduled dose. TPOXX injection Administer TPOXX injection by IV infusion over 6 hours via an infusion pump.
Must dilute TPOXX Injection prior to use [see Dosage and Administration ( 2.5 )] .
2.2Testing Before Initiating and During Treatment with TPOXX Injection Determine creatinine clearance in all patients before starting TPOXX injection and monitor while receiving TPOXX injection as clinically appropriate [see Dosage and Administration ( 2.4 ), Contraindictions ( 4 ), Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.4 , 8.6 )] .
2.3TPOXX Oral Dosage for Pediatric Patients Weighing at Least 13 kg and Adults The recommended dosage of TPOXX capsules in pediatric patients weighing at least 13 kg and adults is displayed in Table 1 below. Table 1: Recommended Dosage and Preparation Instructions for TPOXX Capsules in Pediatric Patients Weighing at Least 13 kg and Adults a TPOXX capsules should be taken within 30 minutes after a full meal containing moderate or high fat [see Clinical Pharmacology ( 12.3 )]…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS TPOXX Capsules TPOXX capsules are hard gelatin with an opaque orange body imprinted in white ink with “SIGA” followed by the SIGA logo followed by “®”, and an opaque black cap imprinted in white ink with “ST-246 ® ”, containing white to off-white powder. Each capsule contains 200 mg of tecovirimat. TPOXX Injection TPOXX injection: 200 mg/20 mL (10 mg/mL) of tecovirimat as a clear, colorless to pale yellow solution in a single-dose vial for further dilution.
Capsules 200 mg of tecovirimat ( 2.4 ) Injection A single-dose vial containing 200 mg of tecovirimat in 20 mL for further dilution prior to intravenous infusion. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TPOXX Capsules: None. TPOXX Injection: The excipient hydroxypropyl-β-cyclodextrin is eliminated through glomerular filtration. Therefore, TPOXX Injection is contraindicated in patients with severe renal impairment (defined as creatinine clearance below 30 mL/min) [see Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.6 )] .
TPOXX capsules: None TPOXX injection: TPOXX Injection is contraindicated in patients with severe renal impairment (defined as creatinine clearance below 30 mL/min) ( 4 , 5.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypoglycemia: Co-administration with repaglinide may cause hypoglycemia. Monitor blood glucose and monitor for hypoglycemic symptoms during co-administration. ( 5.1 )
5.1Hypoglycemia When Co-Administered with Repaglinide Co-administration of repaglinide and tecovirimat may cause mild to moderate hypoglycemia. Monitor blood glucose and monitor for hypoglycemic symptoms when administering TPOXX with repaglinide [see Drug Interactions ( 7.1 ) and Clinical Pharmacology ( 12.3 )] . In a drug interaction study, 10 of 30 healthy subjects experienced mild (6 subjects) or moderate (4 subjects) hypoglycemia following co-administration of repaglinide (2 mg) and TPOXX.
Symptoms resolved in all subjects after intake of food and/or oral glucose.
5.2Risks of Hydroxypropyl-β-Cyclodextrin Excipient for Patients with Renal Insufficiency and Pediatric Patients < 2 Years of Age Patients with renal insufficiency TPOXX Injection: In healthy patients and in patients with mild to severe renal insufficiency, the majority of an 8 g dose of hydroxypropyl-β-cyclodextrin (per 200 mg tecovirimat/20 mL solution) is eliminated in the urine. It is known that clearance of hydroxypropyl-β-cyclodextrin is reduced in patients with mild, moderate, and severe renal impairment, resulting in higher exposure to hydroxypropyl-β-cyclodextrin; in these patients, half-life values are increased over normal values by approximately two-, four-, and six-fold, respectively.
In these patients, successive infusions may result in accumulation of hydroxypropyl-β-cyclodextrin until steady state is reached. In patients with mild (defined as creatinine clearance 60-89 mL/min) and moderate (defined as creatinine clearance 30-59 mL/min) renal impairment, TPOXX Injection should be used with caution. Creatinine clearance should be closely monitored and, if renal toxicity is suspected, consideration should be given to administering TPOXX orally if possible or to using an alternative medication.
TPOXX Injection is contraindicated in patients with severe renal impairment (creatinine clearance 30 mL/min) [see Contraindictions ( 4 ) and Clinical Pharmacology ( 12.3 )] . Pediatric patients TPOXX Injection: In pediatric patients less than 2 years of age, there are limited data regarding the use of hydroxypropyl-β-cyclodextrin. Given that renal tubular function rapidly matures over the first few years of life, clearance of hydroxypropyl-β-cyclodextrin may be reduced in young pediatric patients, resulting in higher exposure to hydroxypropyl-β-cyclodextrin.
TPOXX Injection should be used with caution in this population given that animal studies have shown potential for nephrotoxicity at very high exposure levels of hydroxypropyl-β-cyclodextrin. Given the potential for drug accumulation due to renal immaturity in pediatric patients less than 2 years, monitoring of renal function after treatment is recommended [see Use in Specific Populations ( 8.4 ) and Clinical Pharmacology ( 12.3 )] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions are: TPOXX Capsules (incidence ≥ 2%): headache, nausea, abdominal pain, and vomiting. ( 6.1 ) TPOXX Injection (incidence ≥ 4%): administration site reactions and headache. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact SIGA Technologies Inc. at 1-888-899-3472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of TPOXX has not been studied in patients with smallpox disease. TPOXX Clinical Trial (Oral Administration) The safety of TPOXX was evaluated in 359 healthy adult subjects ages 18-79 years in a Phase 3 clinical trial.
Of the subjects who received at least one 600 mg dose of TPOXX, 59% were female, 69% were White, 28% were Black/African American, 1% were Asian, and 12% were Hispanic or Latino. Ten percent of the subjects who participated in the study were age 65 or older. Of these 359 subjects, 336 subjects received at least 23 of 28 doses of 600 mg TPOXX in a twice daily (every 12 hours) regimen for 14 days.
Most Frequently Reported Adverse Reactions The most frequently reported adverse reactions were headache and nausea. Adverse reactions that occurred in at least 2% of subjects in the TPOXX treatment group are shown in Table 3 . Table 3: Treatment-Related Adverse Reactions Reported in ≥ 2% of Healthy Adult Subjects Receiving at Least One Dose of TPOXX Capsules 600 mg a Includes abdominal pain, abdominal pain upper, abdominal distension, abdominal discomfort, abdominal pain lower, epigastric pain Adverse Reaction TPOXX 600 mg N = 359 (%) Placebo N = 90 (%) Headache 12 8 Nausea 5 4 Abdominal pain a 2 1 Vomiting 2 0 Adverse Reactions Leading to Discontinuation of TPOXX Six subjects (2%) had their treatment with TPOXX discontinued due to adverse reactions.
Each of these subject’s adverse reactions (with severity) is listed below: EEG change, abnormal Mild upset stomach, dry mouth, decreased concentration and dysphoria Mild nausea and fever, moderate diarrhea, severe headache Mild palpable purpura Mild nausea, fever and chills Mild facial redness, facial swelling and pruritus Less Common Adverse Reactions Clinically significant adverse reactions that were reported in <2% of subjects exposed to TPOXX and at rates higher than subjects who received placebo are listed below: Gastrointestinal: dry mouth, chapped lips, dyspepsia, eructation, oral paresthesia General and administration site: pyrexia, pain, chills, malaise, thirst Investigations: abnormal electroencephalogram, hematocrit decreased, hemoglobin decreased, heart rate increased Musculoskeletal and connective tissue: arthralgia, osteoarthritis Nervous system: migraine, disturbance in attention, dysgeusia, paresthesia Psychiatric: depression, dysphoria, irritability, panic attack Respiratory, Thoracic and Mediastinal Disorders: oropharyngeal pain Skin and subcutaneous tissue: palpable purpura, rash, pruritic rash, facial redness, facial swelling, pruritus TPOXX Clinical Trial (Intravenous Administration) The safety of multiple doses of 240 mg of TPOXX injection for IV infusion was evaluated in 26 healthy adult subjects ages 23-62 years, inclusive.
An additional 6 subjects received placebo. TPOXX injection was administered over a 6 hour period via infusion pump twice daily (every 12 hours) for 7 days. Of the 26 subjects administered TPOXX, 42% were female, 69% were White, 23% were Black/African American, and 42% were Hispanic or Latino.
Most Frequently Reported Adverse Reactions The most frequently reported adverse reactions included infusion site pain, infusion site swelling, infusion site erythema, infusion site extravasation, and headache. Adverse reactions that occurred in at least 4% of subjects in the TPOXX…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consult the full prescribing information prior to and during treatment for potential drug interactions. ( 5.1 , 7 , 12.3 )
7.1Effect of TPOXX on Other Drugs Tecovirimat is a weak inducer of cytochrome P450 (CYP)3A and a weak inhibitor of CYP2C8 and CYP2C19. However, the effects are not expected to be clinically relevant for most substrates of those enzymes based on the magnitude of interactions and the duration of treatment of TPOXX. Table 5 provides a listing of established or significant drug interactions and clinical recommendations for select sensitive substrates [see Warnings and Precautions ( 5.1 ) and Clinical Pharmacology ( 12.3 )] .
Table 5: Significant Drug Interactions with Effect of TPOXX on Other Drugs a ↓ = decrease, ↑ = increase b These interactions have been studied in healthy adults. Concomitant Drug Class: Drug Name Effect on Concentration a Clinical Effect/Recommendation Blood Glucose-Lowering Agent: Repaglinide b ↑ repaglinide Monitor blood glucose and monitor for hypoglycemic symptoms in patients when TPOXX is co-administered with repaglinide [see Warnings and Precautions ( 5.1 )] . CNS Depressant: Midazolam b ↓ midazolam Monitor for effectiveness of midazolam.
7.2Effect of Other drugs on TPOXX Co-administration of phosphate binders with tecovirimat increases tecovirimat bioavailability. Table 6 provides a listing of established drug interactions and clinical recommendations for select phosphate binders [see Clinical Pharmacology ( 12.3 )] . Table 6: Significant Drug Interactions with Effect of Other Drugs on TPOXX a ↑ = increase b These interactions have been studied in healthy adults.
Concomitant Drug Class: Drug Name Effect on Concentration a Clinical Effect/Recommendation Phosphate Binders b : Calcium acetate Lanthanum carbonate Sevelamer carbonate Sucroferric oxyhydroxide ↑ tecovirimat Monitor for signs or symptoms of adverse effects when TPOXX is co-administered with phosphate binders [see Overdose ( 10 )] .
7.3Drugs Without Clinically Significant Interactions With TPOXX Based on a drug interaction study, no clinically significant drug interactions have been observed when TPOXX is co-administered with bupropion, flurbiprofen, or omeprazole [see Clinical Pharmacology ( 12.3 )] .
7.4Vaccine Interactions No vaccine-drug interaction studies have been performed in human subjects. Some animal studies have indicated that co-administration of TPOXX at the same time as live smallpox vaccine (vaccinia virus) may reduce the immune response to the vaccine. The clinical impact of this interaction on vaccine efficacy is unknown.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended in patients with smallpox. ( 8.2 )
8.1Pregnancy Risk Summary There are no available data on the use of tecovirimat in pregnant individuals to evaluate for a drug-associated risk of major birth defects, miscarriage, and other adverse maternal and fetal outcomes. In animal reproduction studies, no embryofetal developmental toxicity was observed in mice during the period of organogenesis at tecovirimat exposures (area under the curve [AUC]) up to 23 times higher than human exposure at the recommended human dose (RHD). In rabbits, no embryofetal developmental toxicity was observed during organogenesis at tecovirimat exposures (AUC) less than human exposures at the RHD.
In a mouse pre-/post-natal development study, no toxicities were observed at maternal tecovirimat exposures up to 24 times higher than human exposure at the RHD (see Data) . The background risk of major birth defects and miscarriage for the indicated population is unknown, and the estimated background risk of miscarriage for the indicated population is higher than the general population. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Tecovirimat was administered orally to pregnant mice at doses up to 1,000 mg/kg/day from gestation Days 6-15. No embryofetal toxicities were observed at doses up to 1,000 mg/kg/day (approximately 23 times higher than human exposure at the RHD).
Tecovirimat was administered orally to pregnant rabbits at doses up to 100 mg/kg/day from gestation Days 6-19. No embryofetal toxicities were observed at doses up to 100 mg/kg/day (0.4 times the human exposure at the RHD). In the pre-/post-natal development study, tecovirimat was administered orally to pregnant mice at doses up to 1,000 mg/kg/day from gestation Day 6 to post-natal Day 20.
No toxicities were observed at doses up to 1,000 mg/kg/day (approximately 24 times higher than human exposure at the RHD).
8.2Lactation Risk Summary Because of the potential for variola virus transmission through direct contact with the breastfed infant, breastfeeding is not recommended in patients with smallpox. There are no data on the presence of tecovirimat in human milk, the effects of the drug on the breastfed infant, or on milk production. Tecovirimat was present in animal milk (see Data) .
When a drug is present in animal milk, it is likely to be present in human milk. Data In a lactation study at doses up to 1,000 mg/kg/day, mean tecovirimat milk to plasma ratios up to approximately 0.8 were observed at 6 and 24 hours post-dose when administered orally to mice on lactation Day 10 or 11.
8.3Females and Males of Reproductive Potential Infertility There are no data on the effect of tecovirimat on human fertility. Decreased fertility due to testicular toxicity was observed in male mice [see Nonclinical Toxicology ( 13.1 )] .
8.4Pediatric Use As in adults, the effectiveness of TPOXX in pediatric patients is based solely on efficacy studies in animal models of orthopoxvirus disease. As exposure of healthy pediatric subjects to TPOXX with no potential for direct clinical benefit is not ethical, pharmacokinetic simulation was used to derive dosing regimens that are predicted to provide pediatric patients with exposures comparable to the observed exposure in adults receiving 600 mg orally twice daily (every 12 hours) or 200 mg intravenously twice daily (every 12 hours).
The dosage for pediatric patients is based on weight [see Dosage and Administration ( 2.2 ) and Clinical Pharmacology ( 12.3 )] . TPOXX Injection: There are limited data regarding the use of hydroxypropyl-β-cyclodextrin, an ingredient in TPOXX injection, in pediatric patients less than 2 years of age. Given the potential for drug accumulation d…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on the use of tecovirimat in pregnant individuals to evaluate for a drug-associated risk of major birth defects, miscarriage, and other adverse maternal and fetal outcomes. In animal reproduction studies, no embryofetal developmental toxicity was observed in mice during the period of organogenesis at tecovirimat exposures (area under the curve [AUC]) up to 23 times higher than human exposure at the recommended human dose (RHD). In rabbits, no embryofetal developmental toxicity was observed during organogenesis at tecovirimat exposures (AUC) less than human exposures at the RHD.
In a mouse pre-/post-natal development study, no toxicities were observed at maternal tecovirimat exposures up to 24 times higher than human exposure at the RHD (see Data) . The background risk of major birth defects and miscarriage for the indicated population is unknown, and the estimated background risk of miscarriage for the indicated population is higher than the general population. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Tecovirimat was administered orally to pregnant mice at doses up to 1,000 mg/kg/day from gestation Days 6-15. No embryofetal toxicities were observed at doses up to 1,000 mg/kg/day (approximately 23 times higher than human exposure at the RHD).
Tecovirimat was administered orally to pregnant rabbits at doses up to 100 mg/kg/day from gestation Days 6-19. No embryofetal toxicities were observed at doses up to 100 mg/kg/day (0.4 times the human exposure at the RHD). In the pre-/post-natal development study, tecovirimat was administered orally to pregnant mice at doses up to 1,000 mg/kg/day from gestation Day 6 to post-natal Day 20.
No toxicities were observed at doses up to 1,000 mg/kg/day (approximately 24 times higher than human exposure at the RHD).
🧒 Pediatric Use ▾
8.4Pediatric Use As in adults, the effectiveness of TPOXX in pediatric patients is based solely on efficacy studies in animal models of orthopoxvirus disease. As exposure of healthy pediatric subjects to TPOXX with no potential for direct clinical benefit is not ethical, pharmacokinetic simulation was used to derive dosing regimens that are predicted to provide pediatric patients with exposures comparable to the observed exposure in adults receiving 600 mg orally twice daily (every 12 hours) or 200 mg intravenously twice daily (every 12 hours).
The dosage for pediatric patients is based on weight [see Dosage and Administration ( 2.2 ) and Clinical Pharmacology ( 12.3 )] . TPOXX Injection: There are limited data regarding the use of hydroxypropyl-β-cyclodextrin, an ingredient in TPOXX injection, in pediatric patients less than 2 years of age. Given the potential for drug accumulation due to renal immaturity in pediatric patients less than 2 years, monitoring of renal function after treatment is recommended [see Warnings and Precautions ( 5.2 ) and Clinical Pharmacology ( 12.3 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of TPOXX did not include sufficient numbers of subjects aged 65 and over to determine whether the safety profile of TPOXX is different in this population compared to younger subjects. Of the 359 subjects in the clinical study of TPOXX, 10% (36/359) were ≥ 65 years of age, and 1% (4/359) were ≥ 75 years of age. No alteration of dosing is needed for patients ≥ 65 years of age [see Clinical Pharmacology ( 12.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no clinical experience with overdosage of TPOXX. In case of overdosage, monitor patients for any signs or symptoms of adverse effects. Hemodialysis will not significantly remove TPOXX in overdosed patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tecovirimat is an antiviral drug against variola (smallpox) virus [see Microbiology ( 12.4 )] .
12.2Pharmacodynamics Cardiac Electrophysiology TPOXX does not prolong the QT interval to any clinically relevant extent at the anticipated therapeutic exposure.
12.3Pharmacokinetics At the recommended oral dosage of 600 mg every 12 hours administered in healthy adults weighing less than 120 kg, the mean steady-state values of tecovirimat AUC 0-24hr , C max , and C tau/trough are 29816 hr•ng/mL (n, CV: 43, 34%), 2159 ng/mL (n, CV: 46, 32%), and 845 ng/mL (n, CV: 45, 47%), respectively. At the recommended intravenous dosage of 200 mg every 12 hours administered by IV infusion over 6 hours in healthy adults, the mean steady-state values of tecovirimat AUC 0-24hr , C max , and C min are 39405 hr•ng/mL (n, CV: 22, 23%), 2630 ng/mL (n, CV: 22, 22%), and 747 ng/mL (n, CV: 22, 29%).
Refer to Table 7 for pharmacokinetic parameters of tecovirimat. Tecovirimat steady-state is achieved by Day 4-6. Table 7: Pharmacokinetic Properties of Tecovirimat a Value reflects administration of drug with food. b Value refers to mean systemic exposure (AUC 24hr ).
Meal: ~ 600 kcal, ~ 25 g fat. c Tecovirimat is metabolized by hydrolysis of the amide bond and glucuronidation. The following inactive metabolites were detected in plasma: M4 (N-{3,5-dioxo-4-azatetracyclo[5.3.2.0{2,6}.0{8,10}]dodec-11-en-4- yl}amine), M5 (3,5 dioxo-4-aminotetracyclo[5.3.2.0{2,6}.0{8,10}]dodec-11-ene), and TFMBA (4 (trifluoromethyl) benzoic acid) d Uridine diphosphate (UDP)-glucuronosyl transferase (UGT) enzymes e t 1/2 value refers to mean terminal plasma half-life. f Single dose administration of [ 14 C]-tecovirimat in mass balance study.
KEY: NA = Not Applicable or Not Available Absorption 200 mg intravenous 600 mg oral Median T max (h) (Range) 6 (6-6.5) 6 (2-24) a Effect of food (relative to fasting) NA ↑39% b Distribution % Bound to human plasma proteins 77-82 Blood-to-plasma ratio (drug or drug-related materials) 0.62-0.90 Volume of distribution (Vz or Vz/F, L) (CV%) 383 (46%) 1030 Metabolism Metabolic pathways c Hydrolysis, UGT1A1 d , UGT1A4 Elimination Major route of elimination Metabolism Clearance (CL or CL/F, L/hr) (CV%) 13 (23%) 31 t 1/2 (h) e (CV%) 21 (45%) 19 (29%) % of dose excreted in urine f NA 73, predominantly as metabolites % of dose excreted in feces f NA 23, predominantly as tecovirimat Comparison of Animal and Human PK Data to Support Effective Human Dose Selection Because the effectiveness of TPOXX cannot be tested in humans, a comparison of tecovirimat exposures achieved in healthy human subjects to those observed in animal models of orthopoxvirus infection (nonhuman primates and rabbits infected with monkeypox virus and rabbitpox virus, respectively) in therapeutic efficacy studies was necessary to support the dosage regimen of 600 mg every 12 hours for treatment of smallpox disease in humans.
Humans achieve greater systemic exposure (AUC, C max , and C min ) of tecovirimat following a dose of 600 mg every 12 hours when compared to the therapeutic exposures in these animal models. Specific Populations No clinically significant differences in the pharmacokinetics of tecovirimat were observed based on age, sex, ethnicity, renal impairment (based on estimated GFR), or hepatic impairment (Child Pugh Scores A, B or C). At the 600 mg twice-daily dosage, tecovirimat exposure was reduced in adult subjects weighing more than 120 kg compared to the exposures in adult subjects weighing less than 120 kg.
Specifically, in 34 adult subjects weighing more than 120 kg who received 600 mg TPOXX orally every 12 hours, the observed mean steady state values of AUC 0-24hr , C max , and C trough were 19500 hr•ng/mL (CV: 23%), 1300 ng/mL (CV: 29%), and 585 ng/mL (CV: 31%), respectively. Pediatric Patients TPOXX pharmacokinetics has not been evaluated in pediatric patients. The recommended pediatric dosing regimen is expected to…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tecovirimat is an antiviral drug against variola (smallpox) virus [see Microbiology ( 12.4 )] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TPOXX Capsule How Supplied Each TPOXX capsule contains 200 mg of tecovirimat. TPOXX capsules are hard gelatin with an opaque orange body imprinted in white ink with “SIGA” followed by the SIGA logo followed by “®”, and an opaque black cap imprinted in white ink with "ST-246 ® ", containing white to off-white powder. Each bottle contains 42 capsules (NDC 50072-200-42) with an induction seal and child-resistant cap.
Storage and Handling Store capsules in the original bottle at 20°C to 25°C (68°F to 77°F); excursions permitted 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. TPOXX Injection How Supplied TPOXX injection is supplied in a 30 mL single-dose vial as a clear, colorless to pale yellow solution for intravenous administration containing 200 mg/20 mL (10 mg/mL) of tecovirimat (NDC 50072-010-30). This solution is intended for dilution with either 0.9% (w/v) sodium chloride injection or 5% (w/v) dextrose injection solution.
The vial stopper is not made with natural rubber latex. The vials are packed in cartons of seven vials. Short-term (up to 24 hours) storage and handling at an ambient temperature is acceptable.
Storage and Handling Store TPOXX injection in a refrigerator at 2°C to 8°C (36°F to 46°F) Do not freeze. The diluted solution(s) of TPOXX injection with either 0.9% (w/v) sodium chloride (normal saline) or 5% (w/v) dextrose solution should be used within 4 hours of preparation if stored at room temperature or within 24 hours of preparation if stored at 2°C to 8°C [see Dosage and Administration ( 2.5 )] .
📋 Description ▾
11 DESCRIPTION TPOXX capsules and TPOXX injection contains tecovirimat, an inhibitor of the orthopoxvirus VP37 envelope wrapping protein. TPOXX (tecovirimat) capsules, for oral use are immediate release capsules containing tecovirimat monohydrate equivalent to 200 mg of tecovirimat for oral administration. The capsules include the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hydroxypropyl methyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium lauryl sulfate.
The capsule shell is composed of gelatin, FD&C blue #1, FD&C red #3, FD&C yellow #6, and titanium dioxide. TPOXX (tecovirimat) injection, for intravenous use is a sterile, colorless to pale yellow solution free of visible particles that is intended for intravenous use following dilution. Tecovirimat injection is available in a single-dose vial containing 200 mg/20 mL (10 mg/mL) of tecovirimat and 8,000 mg (400 mg/mL) of Hydroxypropyl Betadex, NF (hydroxypropyl β-cyclodextrin) and Water for Injection, USP/NF.
Tecovirimat monohydrate is a white to off-white crystalline solid with the chemical name Benzamide, N-[(3a R ,4 R ,4a R ,5a S ,6 S ,6a S )-3,3a,4,4a,5,5a,6,6a-octahydro-1,3-dioxo-4,6 ethenocycloprop[f]isoindol-2(1H)-yl]-4-(trifluoromethyl), rel-(monohydrate). The chemical formula is C 19 H 15 F 3 N 2 O 3 ·H 2 O representing a molecular weight of 394.35 g/moL. The molecular structure is as follows: Tecovirimat monohydrate is practically insoluble in water and across the pH range of 2.0-6.5 (< 0.1 mg/mL).
Tecovirimat Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Efficacy Based on Animal Models Alone Inform patients that the efficacy of TPOXX is based solely on efficacy studies demonstrating a survival benefit in animals and that the effectiveness of TPOXX has not been tested in humans with smallpox disease [see Clinical Studies ( 14 )] . Important Dosage and Administration Information Advise patients to take TPOXX capsules as directed within 30 minutes of eating a full meal containing moderate or high fat with 6-8 oz. of water [see Clinical Pharmacology ( 12.3 )] .
Inform patients to take TPOXX for the entire duration without missing or skipping a dose [see Dosage and Administration ( 2 )] . Inform patients who cannot swallow capsules to refer to the Instructions for Use [see Dosage and Administration ( 2 )] . Drug Interactions Inform patients that TPOXX may interact with other drugs.
Advise patients to report to their healthcare provider the use of other prescription drugs [see Drug Interactions ( 7 )] . Co-administration of TPOXX with repaglinide may cause hypoglycemia [see Warnings and Precautions ( 5.1 ) and Drug Interactions ( 7.1 )] . TPOXX injection: Hydroxypropyl-β-cyclodextrin, a required component of TPOXX injection, is eliminated through glomerular filtration.
Therefore, in patients with severe renal impairment (defined as creatinine clearance below 30 mL/min), the use of TPOXX injection is contraindicated [see Contraindications ( 4 )] . In patients with mild (defined as creatinine clearance 60-89 mL/min) and moderate (defined as creatinine clearance 30-59 mL/min) renal impairment, TPOXX injection should be used with caution [see Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.6 )] . Lactation Instruct individuals with smallpox not to breastfeed their infant because of the risk of passing variola virus to the breastfed infant [see Use in Specific Populations ( 8.2 )] .
TPOXX capsules Manufactured by: Catalent Pharma Solutions, LLC 1100 Enterprise Drive Winchester, KY 40391 TPOXX injection manufactured by: Patheon Manufacturing Services LLC 5900 Martin Luther King Jr. Highway Greenville, NC 27834 Distributed by: SIGA Technologies, Inc. 4575 SW Research Way, Suite 110 Corvallis, OR 97333