
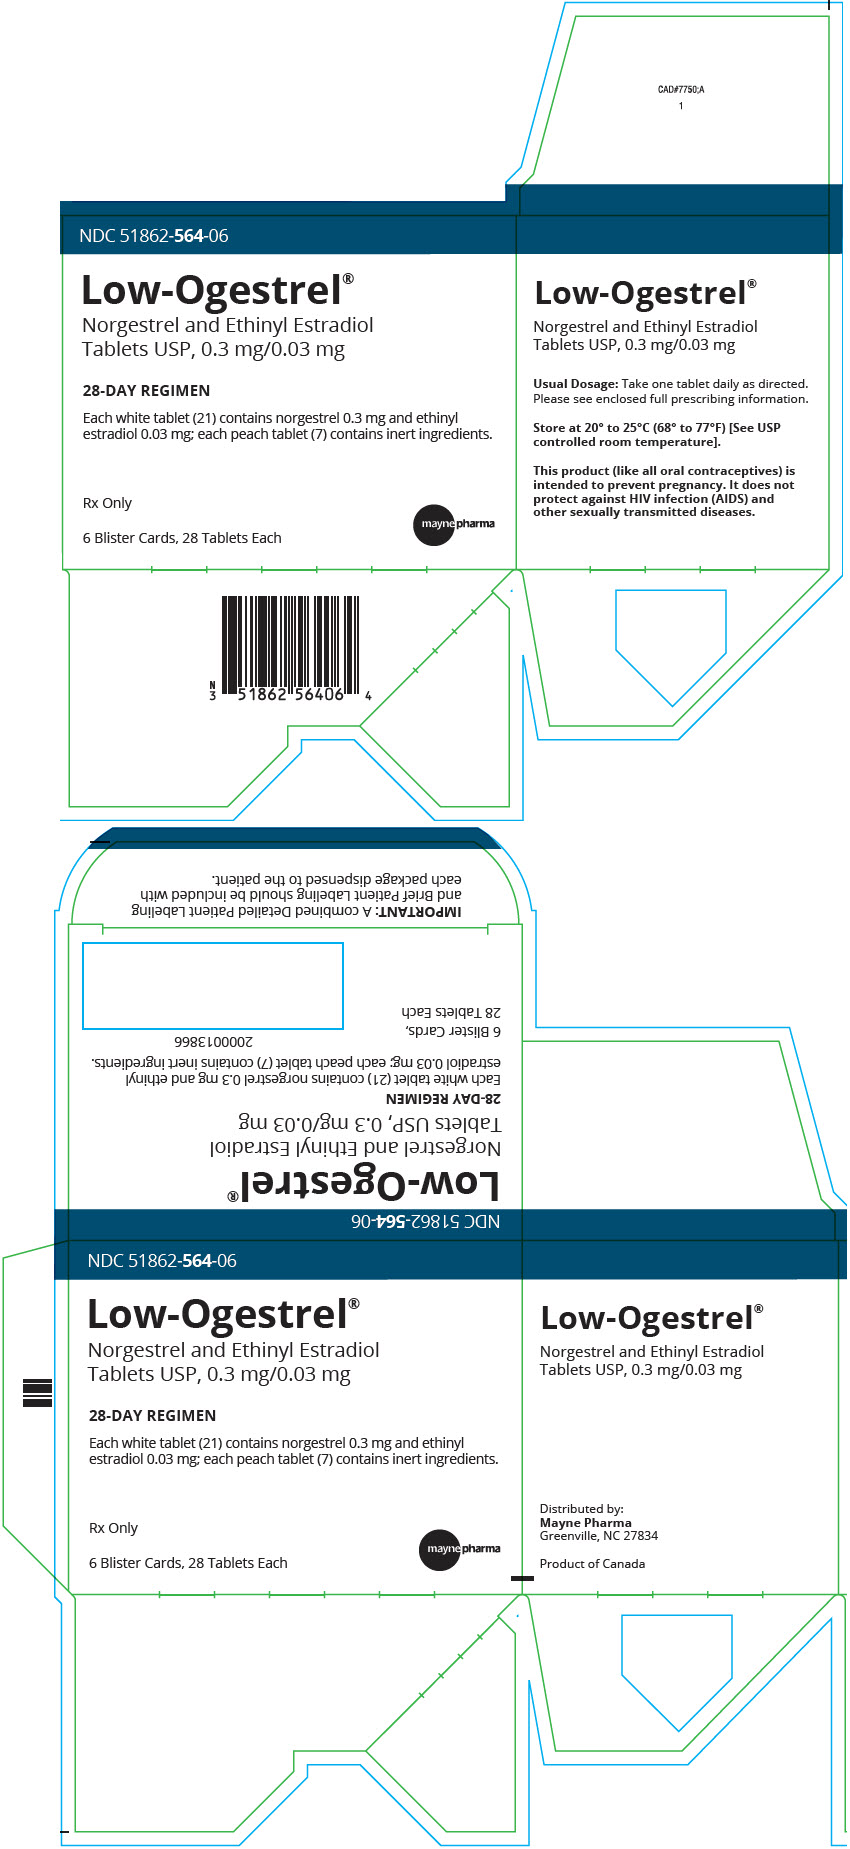
Low-Ogestrel Norgestrel and Ethinyl Estradiol Kit — NDC 51862-564-06 (Billing 51862-0564-06)
This is a package of Low-Ogestrel Norgestrel and Ethinyl Estradiol Kit from Mayne Pharma Inc., marketed since Aug 2016 and currently FDA-listed, this package's marketing is listed to end Jan 2027; retail pharmacies pay about $0.3021 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 51862-564-06 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 51862 labeler · 564 product · 06 package
- Package marketed since
- Aug 3, 2016
- Package marketing ended
- Jan 31, 2027
- Sample package
- No — commercial package
- Barcode (UPC-A, from the NDC)
- 3 5186256406 4
- Medicaid fills, this package
- 5,056 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003310
- GCN: 11500
- GPI-14 (Medi-Span): 25990002900310
- HICL (First Databank): 001457
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 311359
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and norethindrone (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work mainly by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.302 | $1.81 / 6 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.5589 | $3.35 / 6 kit |
| Medicare drug plans payPart D · Q2 2026 | $0.4928 | $2.96 / 6 kit |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51862-0564-06 You're viewing this Main listing | 6 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | 2016-08-03 | Jan 31, 2027 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Low-Ogestrelthis 51862-0564-06 | Mayne | 1 kit | $0.302 | — | Availability likely | — |
| Cryselle 00555-9049-58 | Teva | 6 pouches | $0.302 | AB | Availability likely | — |
| Elinest 16714-0365-01 | Northstar | 1 packet | $0.302 | AB | Availability likely | — |
| Cryselle 00480-3493-16 | Teva | 126 tablets | $0.302 | AB | Availability likely | — |
| Turqoz 68180-0895-13 | Lupin | 1 kit | $0.302 | AB | Availability likely | — |
| Cryselle 71205-0803-28 | Proficient | 1 kit | — | AB | FDA listed | — |
| Turqoz 50090-7978-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Cryselle 50090-2183-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Cryselle 50090-7917-00 | A-S | 126 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Mayne Pharma Inc. labeler code 51862
- Clonidine .3 mg/24h Patch, Extended Release NDC 51862-455-04
- Tolsura Itraconazole 65 mg Capsule, Gelatin Coated NDC 51862-462-08
- calcipotriene 50 ug/g Aerosol, Foam NDC 51862-512-60
- Desogestrel and Ethinyl Estradiol Kit NDC 51862-514-01
- SRONYX Levonorgestrel and Ethinyl Estradiol Kit NDC 51862-545-06
- Doryx Mpc doxycycline hyclate 60 mg Tablet, Delayed Release NDC 51862-560-00
- Methylphenidate Hydrochloride (LA) 30 mg Capsule, Extended Release NDC 51862-611-01
- Methylphenidate Hydrochloride (LA) 40 mg Capsule, Extended Release NDC 51862-612-01
- Lexette halobetasol propionate .5 mg/g Aerosol, Foam NDC 51862-618-50
- Tamoxifen Citrate 20 mg Tablet, Film Coated NDC 51862-643-10
- Nymyo norgestimate and ethinyl estradiol Kit NDC 51862-645-01
- Tri-Nymyo Norgestimate and Ethinyl Estradiol Kit NDC 51862-646-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs are contraindicated in women who are over 35 years of age and smoke [see Contraindications ] .
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Low-Ogestrel is indicated for use by females of reproductive potential to prevent pregnancy. In a study of 1,287 women with a total of 11,085 cycles or 852.7 women-years of usage, the pregnancy rate in women age 15-40 years was approximately 1 pregnancy per 100 women-years of use.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Low-Ogestrel (norgestrel and ethinyl estradiol tablets) must be taken exactly as directed and at intervals not exceeding 24 hours. The dosage of Low-Ogestrel is one white tablet daily for 21 consecutive days, followed by one peach inert tablet daily for 7 consecutive days, according to prescribed schedule. It is recommended that Low-Ogestrel tablets be taken by mouth at the same time each day.
How to Start Low-Ogestrel Consider the possibility of ovulation and conception prior to initiation of medication. Instruct the patient to begin taking Low-Ogestrel on the first Sunday after the onset of menstruation. If menstruation begins on a Sunday, the first tablet (white) is taken that day.
The patient should take one white tablet daily for 21 consecutive days followed by one peach inert tablet daily for 7 consecutive days. Withdrawal bleeding will usually occur within 3 days following discontinuation of white tablets and may not have finished before the next pack is started. During the first cycle, the patient should not rely on Low-Ogestrel for contraception until a white tablet has been taken daily for 7 consecutive days and she should use a non-hormonal back-up method of birth control during those 7 days.
After the first cycle of use The patient is to begin her next and all subsequent 28-day courses of tablets on the same day of the week (Sunday) on which she began her first course, following the same schedule: 21 days of white tablets, followed by 7 days of peach inert tablets. If in any cycle the patient starts tablets later than the proper day, instruct her to protect herself against pregnancy by using a non-hormonal back-up method of birth control until she has taken a white tablet daily for 7 consecutive days. Switching from another hormonal method of contraception When the patient is switching from a 21-day regimen of tablets, instruct her to wait 7 days after her last tablet before she starts Low-Ogestrel.
She will probably experience withdrawal bleeding during that week. Instruct her not to let more than 7 days pass after her previous 21-day regimen before she starts Low-Ogestrel. When the patient is switching from a 28-day regimen of tablets, instruct her to start her first pack of Low-Ogestrel on the day after her last tablet.
She should not wait any days between packs. The patient may switch any day from a progestin-only pill and should begin Low-Ogestrel the next day. If switching from an implant or injection, instruct the patient to start Low-Ogestrel on the day of implant removal or the day the next injection would be due.
If switching from a contraceptive vaginal ring or transdermal patch instruct the patient to start Low-Ogestrel on the day they would have inserted the next ring or applied the next patch. If switching from an Intrauterine Device (IUD) or Intrauterine System (IUS), instruct the patient to start Low-Ogestrel on the day of IUD/IUS removal. If the IUD/IUS is not removed on the first day of the patient's menstrual cycle, instruct her to use a non-hormonal back-up method of birth control for the first 7 days of tablet-taking.
Use after pregnancy, abortion, or miscarriage Initiate Low-Ogestrel no earlier than day 28 postpartum in the nonlactating mother or after a second-trimester abortion due to the increased risk for thromboembolism (see Contraindications , Warnings and Precautions concerning thromboembolic disease). Advise the patient to use a non-hormonal back-up method for the first 7 days of tablet-taking. Low-Ogestrel may be initiated immediately after a first-trimester abortion or miscarriage.
If the patient starts Low-Ogestrel immediately, back-up contraception is not needed. If spotting or breakthrough bleeding occurs If spotting or breakthrough bleeding occurs, instruct the patient to continue on the same regimen. This type of bleeding is usually transient and without significance; however, advise the patient to consult… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Low-Ogestrel is contraindicated in females who are known to have or develop the following conditions: A high risk of arterial or venous thrombotic diseases. Examples include women who are known to: Smoke, if over age 35 Have deep-vein thrombosis or pulmonary embolism, now or in the past Have inherited or acquired coagulopathies Have cerebrovascular disease Have coronary artery disease Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease or atrial fibrillation) Have uncontrolled hypertension Have diabetes mellitus with vascular disease Headaches with focal neurological symptoms or migraine headaches with aura Women over age 35 with any migraine headaches Liver tumors, benign or malignant, or liver disease Undiagnosed abnormal uterine bleeding Pregnancy, because there is no reason to use COCs during pregnancy Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive Hypersensitivity to any of the components of Low-Ogestrel Women who are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT Elevations (see Warnings, Risk of liver enzyme elevations with concomitant hepatitis c treatment ).
⚠️ Warnings ▾
WARNINGS 1. Thromboembolic Disorders and Other Vascular Problems Stop Low-Ogestrel if an arterial thrombotic event or venous thromboembolic (VTE) event occurs. Stop Low-Ogestrel if there is unexplained loss of vision, proptosis, diplopia, papilledema, or retinal vascular lesions.
Evaluate for retinal vein thrombosis immediately. If feasible, stop Low-Ogestrel at least 4 weeks before and through 2 weeks after major surgery or other surgeries known to have an elevated risk of VTE as well as during and following prolonged immobilization. Start Low-Ogestrel no earlier than 4 weeks after delivery, in women who are not breastfeeding.
The risk of postpartum VTE decreases after the third postpartum week, whereas the risk of ovulation increases after the third postpartum week. The use of COCs increases the risk of VTE. However, pregnancy increases the risk of VTE as much or more than the use of COCs.
The risk of VTE in women using COCs is 3 to 9 cases per 10,000 woman-years. The risk of VTE is highest during the first year of use of COCs and when restarting hormonal contraception after a break of 4 weeks or longer. The risk of thromboembolic disease due to COCs gradually disappears after use is discontinued.
Use of COCs also increases the risk of arterial thromboses such as strokes and myocardial infarctions, especially in women with other risk factors for these events. COCs have been shown to increase both the relative and attributable risks of cerebrovascular events (thrombotic and hemorrhagic strokes). This risk increases with age, particularly in women over 35 years of age who smoke.
Use COCs with caution in women with cardiovascular disease risk factors. 2. Liver Disease Impaired Liver Function Do not use Low-Ogestrel in women with liver disease, such as acute viral hepatitis or severe (decompensated) cirrhosis of the liver [see Contraindications ] .
Acute or chronic disturbances of liver function may necessitate the discontinuation of COC use until markers of liver function return to normal and COC causation has been excluded. Discontinue Low-Ogestrel if jaundice develops. Liver Tumors Low-Ogestrel is contraindicated in women with benign and malignant liver tumors [see Contraindications ] .
Hepatic adenomas are associated with COC use. An estimate of the attributable risk is 3.3 cases/100,000 users. Rupture of hepatic adenomas may cause death through intra-abdominal hemorrhage.
Studies have shown an increased risk of developing hepatocellular carcinoma in long-term (>8 years) COC users. However, the risk of liver cancers in COC users approaches less than one case per million users. Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment During clinical trials with the Hepatitis C combination drug regimen that contains ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, ALT elevations greater than 5 times the upper limit of normal (ULN), including some cases greater than 20 times the ULN, were significantly more frequent in women using ethinyl estradiol-containing medications such as COCs.
Discontinue Low-Ogestrel prior to starting therapy with the combination drug regimen ombitasvir/paritaprevir/ritonavir, with or without dasabuvir [see Contraindications ]. Low-Ogestrel can be restarted approximately 2 weeks following completion of treatment with the combination drug regimen. 3.
High Blood Pressure Low-Ogestrel is contraindicated in women with uncontrolled hypertension or hypertension with vascular disease [see Contraindications ] . For women with well-controlled hypertension, monitor blood pressure and stop Low-Ogestrel if blood pressure rises significantly. An increase in blood pressure has been reported in women taking COCs, and this increase is more likely in older women with extended duration of use.
The incidence of hypertension increases with increasing quantities of progestin. 4. Gallbladder Disease Studies suggest a small increased relative risk of developing gallbladder disease among COC users.… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS An increased risk of the following serious adverse reactions (see Warnings section for additional information) has been associated with the use of oral contraceptives: Serious cardiovascular events and stroke [see Boxed Warning ] Vascular events Liver disease Adverse reactions commonly reported by COC users are: Irregular uterine bleeding Nausea Breast tenderness Headache Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
The safety of Low-Ogestrel was evaluated in 1,343 healthy women of child-bearing potential who participated in 9 clinical trials and received at least one dose of Low-Ogestrel for contraception. Subjects were exposed for a total of 11,085 cycles, with 429 women completing one year of exposure. Subjects ranged in age from 15-40 years.
Demographics were 69% Caucasian, 28% Black, and 3% other. Common Adverse Reactions (≥ 2% of women): Weight increase (11%) Cervical erosion (9%) Weight decrease (6%) Acne (4%) Dysmenorrhea (4%) Vaginal discharge (4%) Abdominal pain, cramps, and bloating (3%) Appetite increase (3%) Depression (3%) Nervousness (3%) Chloasma/melasma (2%) Fatigue (2%) Varicose veins, aggravation of (2%) A total of 8% of subjects discontinued the trials prematurely due to an adverse reaction, most commonly due to unscheduled bleeding, spotting, headache (including migraine), nausea, acne, changes in menstrual flow, weight increase, nervousness, high blood pressure, and depression.
Postmarketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 - 1.12 (Figure 1). Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 1). One of these studies reported no association between breast cancer risk and COC use.
The other two studies found an increased relative risk of 1.19 - 1.33 with current or recent use. Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8-10 years of COC use. Figure 1: Risk of Breast Cancer with Combined Oral Contraceptive Use RR = relative risk; OR = odds ratio; HR = hazard ratio. "ever COC" are females with current or past COC use; "never COC use" are females that never used COCs.
The following additional adverse drug reactions have been reported from worldwide postmarketing experience with Low-Ogestrel. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Arterial Events: Arterial thromboembolism, Myocardial infarction, Cerebral hemorrhage Eye Disorder: Optic neuritis, which may lead to partial or complete loss of vision, Intolerance to contact lenses, Change (steepening) in corneal curvature Gastrointestinal Disorders: Colitis, Nausea, Pancreatitis Hepatobiliary Disorders: Gallbladder disease, Cholestatic jaundice, Budd-Chiari syndrome Immune System Disorders: Anaphylactic/anaphylactoid reactions, including urticaria, angioedema, and severe reactions with respiratory and circulatory symptoms Metabolism and Nutrition Disorders: Carbohydrate and lipid effects, Porphyria, exacerbation of Porphyria Neoplasms, Benign, Malignant, and Unspecified: Carcinoma of the reproductive organs and breasts , Hepatic neoplasia (including hepatic adenomas or benign liver tumors) Psychiatric Disorders: Mood changes Reproductive System and Breast Disorders: Temporary inferti… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
4. Drug Interactions Consult the labeling of all concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations . Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Do not co-administer Low-Ogestrel with HCV drug combinations containing ombitasvir/ paritaprevir/ritonavir, with or without dasabuvir, due to potential for ALT elevations (see Warnings, Risk of liver enzyme elevations with concomitant hepatitis c treatment ).
Effects of Other Drugs on Combined Oral Contraceptives Substances decreasing the plasma concentrations of COCs and potentially diminishing the efficacy of COCs Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the plasma concentrations of COCs and potentially diminish the effectiveness of COCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, topiramate rifabutin, rufinamide, aprepitant, and products containing St.
John's wort. Interactions between hormonal contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability.
Colesevelam Colesevelam, a bile acid sequestrant, given together with a COC, has been shown to significantly decrease the AUC of EE. The drug interaction between the contraceptive and colesevelam was decreased when the two drug products were given 4 hours apart. Substances increasing the plasma concentrations of COCs Co-administration of atorvastatin or rosuvastatin and certain COCs containing EE increase AUC values for EE by approximately 20-25%.
Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. Concomitant administration of CYP3A4 inhibitors such as itraconazole, fluconazole, grapefruit juice or ketoconazole may increase plasma hormone concentrations. Human immunodeficiency virus (HIV)/ Hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors Significant changes (increase or decrease) in the plasma concentrations of the estrogen and/or progestin have been noted when COCs are co-administered with some HIV protease inhibitors (decrease [e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos) amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir], or increase [e.g., indinavir and atazanavir/ritonavir] HCV protease inhibitors (decrease [e.g., nevirapine] or increase [e.g., etravirine]).
Effects of Combined Oral Contraceptives on Other Drugs COCs containing EE may inhibit the metabolism of other drugs (e.g., cyclosporine, prednisolone, theophylline, tizanidine, and voriconazole) and increase their plasma concentrations. COCs have been shown to decrease plasma concentrations of acetaminophen, clofibric acid, morphine, salicylic acid, temazepam and lamotrigine. Significant decrease in the plasma concentration of lamotrigine has been shown, likely due to induction of lamotrigine glucuronidation.
This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary. Women on thyroid hormone replacement therapy may need increased doses of thyroid hormone because serum concentration of thyroid-binding globulin increases with use of COCs.
🤰 Pregnancy ▾
7. Pregnancy There is little or no increased risk of birth defects in women who inadvertently use COCs during early pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb reduction defects) following exposure to low dose COCs prior to conception or during early pregnancy.
Discontinue Low-Ogestrel use if pregnancy is confirmed. Do not administer COCs to induce withdrawal bleeding as a test for pregnancy. Do not use COCs during pregnancy to treat threatened or habitual abortion.
🧒 Pediatric Use ▾
9. Pediatric Use Safety and efficacy of Low-Ogestrel tablets have been established in women of reproductive age. Efficacy is expected to be the same for post-pubertal adolescents under the age of 16 and for users 16 years and older. Use of Low-Ogestrel before menarche is not indicated.
🧓 Geriatric Use ▾
10. Geriatric Use Low-Ogestrel has not been studied in postmenopausal women and is not indicated in this population.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of serious ill effects from overdosage of oral contraceptives, including ingestion by children. Overdosage may cause withdrawal bleeding in females and nausea.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Combined oral contraceptives (COCs) prevent pregnancy primarily by suppressing ovulation.
🧬 Mechanism of Action ▾
Mechanism of Action Combined oral contraceptives (COCs) prevent pregnancy primarily by suppressing ovulation.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Low-Ogestrel ® Tablets (0.3 mg norgestrel and 0.03 mg ethinyl estradiol) are available in cartons of 6 dispensers ( NDC 51862-564-06 ), each containing 28 tablets as follows: 21 white, unscored, round active tablets debossed "WATSON" on one side and "847" on the other side. 7 peach, unscored, round inert tablets debossed "WATSON" on one side and "P1" on the other side. Store at 20°C to 25°C (68°F to 77°F) [See USP controlled room temperature].
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F) [See USP controlled room temperature].
📋 Description ▾
DESCRIPTION Low-Ogestrel is a combination oral contraceptive containing the progestational compound norgestrel and the estrogenic compound ethinyl estradiol. Norgestrel is designated as (2) (±)-13 Ethyl-17-hydroxy-18,19-dinor-17α-pregn-4-en-20-yn-3-one and ethinyl estradiol is designated as (19-nor-17α-pregna-1,3,5 (10)-trien-20-yne-3,17-diol). Each white active Low-Ogestrel tablet contains 0.3 mg norgestrel and 0.03 mg ethinyl estradiol and the following inert ingredients: croscarmellose sodium, lactose, magnesium stearate, microcrystalline cellulose, and povidone.
Each peach placebo tablet contains only the following inert ingredients: anhydrous lactose, FD&C Yellow No. 6 Lake, lactose monohydrate, magnesium stearate, and microcrystalline cellulose. Each pill pack contains 21 white active tablets and 7 peach inert tablets.
Norgestrel C 21 H 28 O 2 M.W. 312.45 Ethinyl Estradiol C 20 H 24 O 2 M.W. 296.40 Chemical Structure Chemical Structure
💬 Information for Patients ▾
11. Information for the Patient See FDA-approved patient labeling (Patient Information and Instructions for Use). Counsel patients about the following information: Cigarette smoking increases the risk of serious cardiovascular events from COC use, and that women who are over 35 years old and smoke should not use COCs [ see Boxed Warning ].
Increased risk of VTE compared to non-users of COCs is greatest after initially starting a COC or restarting (following a 4-week or greater pill-free interval) the same or a different COC. Low-Ogestrel does not protect against HIV infection and other sexually transmitted infections. Low-Ogestrel is not to be used during pregnancy; if pregnancy occurs during use of Low-Ogestrel, instruct the patient to stop further use.
Take one tablet daily by mouth at the same time every day. Instruct patients what to do in the event tablets are missed. Use a back-up or alternative method of contraception when enzyme inducers are used with Low-Ogestrel.
COCs may reduce breast milk production; this is less likely to occur if breastfeeding is well established. Women who start COCs postpartum, and who have not yet had a period, should use an additional method of contraception until they have taken an active tablet for 7 consecutive days. Amenorrhea may occur.
Consider pregnancy in the event of amenorrhea at the time of the first missed period. Rule out pregnancy in the event of amenorrhea in two or more consecutive cycles.
⚠️ Precautions ▾
PRECAUTIONS 1. Effect on Binding Globulins The estrogen component of COCs may raise the serum concentrations of thyroxine-binding globulin, sex hormone-binding globulin, and cortisol-binding globulin. The dose of replacement thyroid hormone or cortisol therapy may need to be increased.
2. Hereditary Angioedema In females with hereditary angioedema, exogenous estrogens may induce or exacerbate symptoms of angioedema. 3.
Chloasma Chloasma may occasionally occur, especially in women with a history of chloasma gravidarum. Women with a tendency to chloasma should avoid exposure to the sun or ultraviolet radiation while taking Low-Ogestrel. 4.
Drug Interactions Consult the labeling of all concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations . Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Do not co-administer Low-Ogestrel with HCV drug combinations containing ombitasvir/ paritaprevir/ritonavir, with or without dasabuvir, due to potential for ALT elevations (see Warnings, Risk of liver enzyme elevations with concomitant hepatitis c treatment ). Effects of Other Drugs on Combined Oral Contraceptives Substances decreasing the plasma concentrations of COCs and potentially diminishing the efficacy of COCs Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the plasma concentrations of COCs and potentially diminish the effectiveness of COCs or increase breakthrough bleeding.
Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, topiramate rifabutin, rufinamide, aprepitant, and products containing St. John's wort. Interactions between hormonal contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure.
Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability. Colesevelam Colesevelam, a bile acid sequestrant, given together with a COC, has been shown to significantly decrease the AUC of EE. The drug interaction between the contraceptive and colesevelam was decreased when the two drug products were given 4 hours apart.
Substances increasing the plasma concentrations of COCs Co-administration of atorvastatin or rosuvastatin and certain COCs containing EE increase AUC values for EE by approximately 20-25%. Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. Concomitant administration of CYP3A4 inhibitors such as itraconazole, fluconazole, grapefruit juice or ketoconazole may increase plasma hormone concentrations.
Human immunodeficiency virus (HIV)/ Hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors Significant changes (increase or decrease) in the plasma concentrations of the estrogen and/or progestin have been noted when COCs are co-administered with some HIV protease inhibitors (decrease [e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos) amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir], or increase [e.g., indinavir and atazanavir/ritonavir] HCV protease inhibitors (decrease [e.g., nevirapine] or increase [e.g., etravirine]).
Effects of Combined Oral Contraceptives on Other Drugs COCs containing EE may inhibit the metabolism of other drugs (e.g., cyclosporine, prednisolone, theophylline, tizanidine, and voriconazole) and increase their plasma concentrations. COCs have been shown to decrease plasma concentrations of acetaminophen, clofibric acid, morphine, salicylic acid, temazepam and lamotrigine. Significant decrease in the plasma concentration of lamotrigine has been shown, likely du… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8. Nursing Mothers Advise the nursing mother to use other forms of contraception, when possible, until she has weaned her child. COCs can reduce milk production in breastfeeding mothers. This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women. Small amounts of oral contraceptive steroids and/or metabolites are present in breast milk.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
6. Carcinogenesis See WARNINGS Section 2 and WARNINGS Section 9 .
📄 Patient Package Insert ▾
FDA-Approved Patient Labeling Low-Ogestrel [Lo-Ogest-rell] (norgestrel and ethinyl estradiol tablets) What is the most important information I should know about Low-Ogestrel? Do not use Low-Ogestrel if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects from hormonal birth control pills, including death from heart attack, blood clots or stroke.
This risk increases with age and the number of cigarettes you smoke. What is Low-Ogestrel? Low-Ogestrel is a birth control pill (oral contraceptive) used by women to prevent pregnancy.
How does Low-Ogestrel work for contraception? Your chance of getting pregnant depends on how well you follow the directions for taking your birth control pills. The better you follow the directions, the less chance you have of getting pregnant.
Based on the results of clinical studies, about 1 out of 100 women may get pregnant during the first year they use Low-Ogestrel. The following chart shows the chance of getting pregnant for women who use different methods of birth control. Each box on the chart contains a list of birth control methods that are similar in effectiveness.
The most effective methods are at the top of the chart. The box on the bottom of the chart shows the chance of getting pregnant for women who do not use birth control and are trying to get pregnant. Who should not take Low-Ogestrel?
Do not take Low-Ogestrel if you: smoke and are over 35 years old had blood clots in the legs, arms, lungs, or eyes had a problem with your blood that makes it clot more than normal have certain heart valve problems or irregular heart beat that increases your risk of having blood clots had a stroke had a heart attack have high blood pressure that cannot be controlled by medicine have diabetes with kidney, eye, nerve or blood vessel damage have certain kinds of severe migraine headaches with aura, numbness, weakness or changes in vision, or have any migraine headaches if you are over 35 years of age have liver problems, including liver tumors have any unexplained vaginal bleeding are pregnant have or had breast cancer or any cancer that is sensitive to female hormones have a known allergy or hypersensitivity to any of the components of Low-Ogestrel (norgestrel and ethinyl estradiol tablets) You should not take the pill if you take any Hepatitis C drug combination containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir.
This may increase levels of the liver enzyme "alanine aminotransferase" (ALT) in the blood. If any of these conditions happen while you are taking Low-Ogestrel, stop taking Low-Ogestrel right away and talk to your healthcare provider. Use non-hormonal contraception when you stop taking Low-Ogestrel.
What should I tell my healthcare provider before taking Low-Ogestrel? Tell your healthcare provider if you: are pregnant or think you may be pregnant are depressed now or have been depressed in the past had yellowing of your skin or eyes (jaundice) caused by pregnancy (cholestasis of pregnancy) have a condition called hereditary angioedema are breastfeeding or plan to breastfeed. Low-Ogestrel may decrease the amount of breast milk you make.
A small amount of the hormones in Low-Ogestrel may pass into your breast milk. Talk to your healthcare provider about the best birth control method for you while breastfeeding. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins and herbal supplements.
Low-Ogestrel may affect the way other medicines work, and other medicines may affect how well Low-Ogestrel works. Know the medicines you take. Keep a list of them to show your healthcare provider and pharmacist when you get a new medicine.
How should I take Low-Ogestrel? Read the Instructions for Use at the end of this Patient Information. What are the possible serious side effects of Low-Ogestrel?
Like pregnancy, Low-Ogestrel may cause serious side effects, in… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use Important Information about taking Low-Ogestrel Take 1 pill every day at the same time. Take the pills in the order directed on your pill dispenser. Do not skip your pills, even if you do not have sex often.
If you miss pills (including starting the pack late) you could get pregnant . The more pills you miss, the more likely you are to get pregnant. If you have trouble remembering to take Low-Ogestrel, talk to your healthcare provider.
When you first start taking Low-Ogestrel, spotting or light bleeding in between your periods may occur. Contact your healthcare provider if this does not go away after a few months. You may feel sick to your stomach (nauseous), especially during the first few months of taking Low-Ogestrel.
If you feel sick to your stomach, do not stop taking the pill. The problem will usually go away. If your nausea does not go away, call your healthcare provider.
Missing pills can also cause spotting or light bleeding, even when you take the missed pills later. On the days you take 2 pills to make up for missed pills (see WHAT TO DO IF YOU MISS PILLS? below), you could also feel a little sick to your stomach. It is not uncommon to miss a period.
However, if you miss a period and have not taken Low-Ogestrel according to directions, or miss 2 periods in a row, or feel like you may be pregnant, call your healthcare provider. If you have a positive pregnancy test, you should stop taking Low-Ogestrel. If you have vomiting or diarrhea within 3–4 hours of taking your pill, take another pill of the same color from your extra pill dispenser.
If you do not have an extra pill dispenser, take the next pill in the dispenser you are currently using. Continue taking all your remaining pills in order. Start the first pill of your next pill dispenser the day after finishing your current pill dispenser.
This will be 1 day earlier than originally scheduled. Continue on your new schedule. If you have vomiting or diarrhea for more than 1 day, your birth control pills may not work as well.
Use an additional birth control method, like condoms or spermicide, until you check with your healthcare provider. Stop taking Low-Ogestrel at least 4 weeks before you have major surgery and do not restart after the surgery without asking your healthcare provider. Be sure to use another form of contraception (like condoms or spermicide) during this time period.
BEFORE YOU START TAKING Low-Ogestrel 1. DECIDE WHAT TIME OF DAY YOU WANT TO TAKE YOUR PILL. It is important to take it at about the same time every day.
2. LOOK AT YOUR PILL PACK: The pill pack has 21 "active" white pills (with hormones) to take for 3 weeks, followed by 1 week of reminder peach pills (without hormones). 3.
FIND: 1) where on the pack to start taking pills, and 2) in what order to take the pills (follow the arrows). 4. BE SURE YOU HAVE READY AT ALL TIMES: Another kind of birth control (such as condoms or spermicide) to use as a back-up in case you miss pills An extra, full pill pack WHEN TO START THE FIRST PACK OF PILLS SUNDAY START: 1.
Take the first "active" white pill of the first pack on the Sunday after your period starts, even if you are still bleeding. If your period begins on Sunday, start the pack that same day. 2.
Use a non-hormonal method of birth control (such as condoms or spermicide) as a back-up method if you have sex anytime from the Sunday you start your first pack until the next Sunday (7 days). WHAT TO DO DURING THE MONTH Take one pill at the same time every day until the pack is empty. Do not skip pills even if you are spotting or bleeding between monthly periods or feel sick to your stomach (nausea).
Do not skip pills even if you do not have sex very often. When you finish a pack: Start the next pack on the day after your last "reminder" pill. Do not wait any days between packs.
IF YOU SWITCH FROM ANOTHER BRAND OF COMBINATION PILLS: If your previous brand had 21 pills: Wait 7 days to start taking Low-Ogestrel. You will probably have y… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - Kit Carton NDC 51862-564-06 Low-Ogestrel ® Norgestrel and Ethinyl Estradiol Tablets USP, 0.3 mg/0.03 mg 28-DAY REGIMEN Each white tablet (21) contains norgestrel 0.3 mg and ethinyl estradiol 0.03 mg; each peach tablet (7) contains inert ingredients. Rx Only 6 Blister Cards, 28 Tablets Each mayne pharma PRINCIPAL DISPLAY PANEL - Kit Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |