
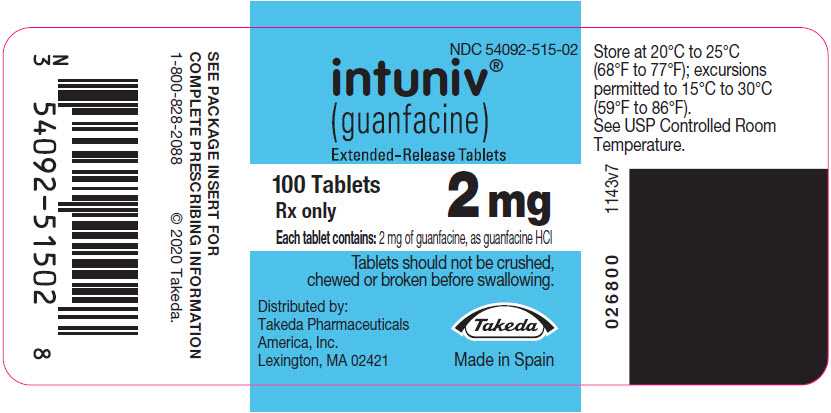
Intuniv guanfacine 2 mg Tablet, Extended Release, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's used for both, depending on which form you have. The regular (immediate-release) tablet is prescribed for high blood pressure. The extended-release version — brand name Intuni...
- What is guanfacine actually used for — is it for ADHD or blood pressure?
- No, Intuniv is not a stimulant at all. It works on a different part of the brain than medications like Adderall or Ritalin. That's actually one reason it's sometimes used alongside...
- My child takes Intuniv for ADHD — is it a stimulant?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Guanfacine — tap one for details:
Guanfacine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 88XHZ13131
Fumaric acid is an organic acid used in medications as a buffer and pH regulator. It helps maintain the proper acidity level in the medicine and may aid in tablet disintegration.
-
UNII R8WTH25YS2
Glyceryl dibehenate is a wax-like substance made from behenate fatty acids and glycerol. It functions as a binder and release-control agent in tablets and capsules, helping hold ingredients together and regulate how quickly the medicine dissolves and releases in your body.
-
UNII Z78RG6M2N2
Hypromellose 2208 is a plant-derived thickening agent used as a binder and film-coating material in tablets and capsules. It helps hold ingredients together and creates a protective coating that controls how quickly the medicine dissolves.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 74G4R6TH13
A synthetic polymer made by combining two plastic-like chemicals. It forms a coating on tablets or capsules that dissolves at a specific point in the digestive tract, controlling where and when the medicine releases.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.313 | $931.27 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $9.21 | $920.75 / 100 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| guanfacine 2 mg 00228-2851-11 | Actavis | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine Extended-Release 2 mg 24979-0534-01 | Upsher-Smith | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine 2 mg 29300-0461-01 | Unichem | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine extended-release 2 mg 60505-3928-01 | Apotex | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine 2 mg 62332-0746-31 | Alembic | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine 2 mg 70436-0040-01 | Slate | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine 2 mg 72266-0256-55 | Fosun | 100 tablets | $0.157 | AB | Availability likely | save 98% |
| Guanfacine 2 mg 63304-0925-01 | Sun | 100 tablets | $0.206 | — | FDA listed | save 98% |
| Guanfacine 2 mg 16714-0191-01 | NORTHSTAR | 100 tablets | $0.222 | — | FDA listed | save 98% |
| Intuniv 2 mgthis 54092-0515-02 | Takeda | 100 tablets | $9.313 | AB | Availability likely | — |
| guanfacine 2 mg 42291-0325-01 | AvKARE | 100 tablets | — | AB | Discontinued | — |
| Guanfacine 2 mg 46708-0746-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 51407-0953-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Guanfacine Extended-Release 2 mg 60429-0961-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 63629-8203-01 | Bryant | 30 tablets | — | — | Discontinued | — |
| Guanfacine Extended-Release 2 mg 70518-3809-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine extended-release 2 mg 70518-4266-00 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| Guanfacine 2 mg 70518-4675-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine Extended-Release 2 mg 71205-0945-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Guanfacine extended-release 2 mg 71335-2852-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Guanfacine extended-release 2 mg 71335-9750-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 72162-1799-01 | Bryant | 100 tablets | — | — | FDA listed | — |
| Guanfacine 2 mg 72888-0225-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 54092-0515-02 You're viewing this | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (54092-515-02) | 2009-09-02 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE INTUNIV ® is indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) as monotherapy and as adjunctive therapy to stimulant medications [see Clinical Studies (14) ]. INTUNIV is a central alpha 2A -adrenergic receptor agonist indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) as monotherapy and as adjunctive therapy to stimulant medications ( 1 , 14 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dose: 1 mg to 7 mg (0.05 to 0.12 mg/kg target weight based dose range) once daily in the morning or evening based on clinical response and tolerability ( 2.2 ). Begin at a dose of 1 mg once daily and adjust in increments of no more than 1 mg/week ( 2.2 ). Do not crush, chew or break tablets before swallowing ( 2.1 ).
Do not administer with high-fat meals, because of increased exposure ( 2.1 ). Do not substitute for immediate-release guanfacine tablets on a mg-per-mg basis, because of differing pharmacokinetic profiles ( 2.3 ). If switching from immediate-release guanfacine, discontinue that treatment and titrate with INTUNIV as directed ( 2.3 ).
When discontinuing, taper the dose in decrements of no more than 1 mg every 3 to 7 days to avoid rebound hypertension ( 2.5 ).
2.1General Instruction for Use Swallow tablets whole. Do not crush, chew, or break tablets because this will increase the rate of guanfacine release. Do not administer with high fat meals, due to increased exposure.
2.2Dose Selection Take INTUNIV orally once daily, either in the morning or evening, at approximately the same time each day. Begin at a dose of 1 mg/day, and adjust in increments of no more than 1 mg/week. In monotherapy clinical trials, there was dose- and exposure-related clinical improvement as well as risks for several clinically significant adverse reactions (hypotension, bradycardia, sedative events).
To balance the exposure-related potential benefits and risks, the recommended target dose range depending on clinical response and tolerability for INTUNIV is 0.05 to 0.12 mg/kg/day (total daily dose between 1 to 7 mg) (See Table 1 ). Table 1: Recommended Target Dose Range for Therapy with INTUNIV Weight Target dose range (0.05 to 0.12 mg/kg/day) Doses above 4 mg/day have not been evaluated in children (ages 6 to 12 years) and doses above 7 mg/day have not been evaluated in adolescents (ages 13 to 17 years) 25 to 33.9 kg 2 to 3 mg/day 34 to 41.4 kg 2 to 4 mg/day 41.5 to 49.4 kg 3 to 5 mg/day 49.5 to 58.4 kg 3 to 6 mg/day 58.5 to 91 kg 4 to 7 mg/day >91 kg 5 to 7 mg/day In the adjunctive trial which evaluated INTUNIV treatment with psychostimulants, the majority of patients reached optimal doses in the 0.05 to 0.12 mg/kg/day range.
Doses above 4 mg/day have not been studied in adjunctive trials.
2.3Switching from Immediate-Release Guanfacine to INTUNIV If switching from immediate-release guanfacine, discontinue that treatment, and titrate with INTUNIV following above recommended schedule. Do not substitute for immediate-release guanfacine tablets on a milligram-per-milligram basis, because of differing pharmacokinetic profiles. INTUNIV has significantly reduced C max (60% lower), bioavailability (43% lower), and a delayed T max (3 hours later) compared to those of the same dose of immediate-release guanfacine [see Clinical Pharmacology (12.3) ] .
2.4Maintenance Treatment Pharmacological treatment of ADHD may be needed for extended periods. Healthcare providers should periodically re-evaluate the long-term use of INTUNIV, and adjust weight-based dosage as needed. The majority of children and adolescents reach optimal doses in the 0.05 to 0.12 mg/kg/day range.
Doses above 4 mg/day have not been evaluated in children (ages 6 to 12 years) and above 7 mg/day have not been evaluated in adolescents (ages 13 to 17 years) [see Clinical Studies (14) ] .
2.5Discontinuation of Treatment Following discontinuation of INTUNIV, patients may experience increases in blood pressure and heart rate [see Warnings and Precautions (5.4) and Adverse Reactions (6) ] . Patients/caregivers should be instructed not to discontinue INTUNIV without consulting their health care provider. Monitor blood pressure and pulse when reducing the dose or discontinuing the drug.
Taper the daily dose in decrements of no more than 1 mg every 3 to 7 days to minimize the risk of rebound hypertension.
2.6 Missed Doses When reinitiating patients to th…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 1 mg, 2 mg, 3 mg, and 4 mg extended-release tablets Extended-release tablets: 1 mg, 2 mg, 3 mg, and 4 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS INTUNIV is contraindicated in patients with a history of a hypersensitivity reaction to INTUNIV or its inactive ingredients, or other products containing guanfacine. Rash and pruritus have been reported. History of hypersensitivity to INTUNIV , its inactive ingredients, or other products containing guanfacine ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension, bradycardia, syncope: Titrate slowly and monitor vital signs frequently in patients at risk for hypotension, heart block, bradycardia, syncope, cardiovascular disease, vascular disease, cerebrovascular disease or chronic renal failure. Measure heart rate and blood pressure prior to initiation of therapy, following dose increases, and periodically while on therapy. Avoid concomitant use of drugs with additive effects unless clinically indicated.
Advise patients to avoid becoming dehydrated or overheated ( 5.1 ). Sedation and somnolence: Occur commonly with INTUNIV . Consider the potential for additive sedative effects with CNS depressant drugs.
Caution patients against operating heavy equipment or driving until they know how they respond to INTUNIV ( 5.2 ). Cardiac Conduction Abnormalities: May worsen sinus node dysfunction and atrioventricular (AV) block, especially in patients taking other sympatholytic drugs. Titrate slowly and monitor vital signs frequently ( 5.3 ).
Rebound Hypertension: Abrupt discontinuation of INTUNIV can lead to clinically significant and persistent rebound hypertension. Subsequent hypertensive encephalopathy was also reported. To minimize the risk of rebound hypertension upon discontinuation, the total daily dose of INTUNIV should be tapered in decrements of no more than 1 mg every 3 to 7 days ( 5.4 ).
5.1Hypotension, Bradycardia, and Syncope Treatment with INTUNIV can cause dose-dependent decreases in blood pressure and heart rate. Decreases were less pronounced over time of treatment. Orthostatic hypotension and syncope have been reported [see Adverse Reactions (6.1) ] .
Measure heart rate and blood pressure prior to initiation of therapy, following dose increases, and periodically while on therapy. Titrate INTUNIV slowly in patients with a history of hypotension, and those with underlying conditions that may be worsened by hypotension and bradycardia; e.g., heart block, bradycardia, cardiovascular disease, vascular disease, cerebrovascular disease, or chronic renal failure. In patients who have a history of syncope or may have a condition that predisposes them to syncope, such as hypotension, orthostatic hypotension, bradycardia, or dehydration, advise patients to avoid becoming dehydrated or overheated.
Monitor blood pressure and heart rate, and adjust dosages accordingly in patients treated concomitantly with antihypertensives or other drugs that can reduce blood pressure or heart rate or increase the risk of syncope.
5.2Sedation and Somnolence Somnolence and sedation were commonly reported adverse reactions in clinical studies [see Adverse Reactions (6.1) ] . Before using INTUNIV with other centrally active depressants, consider the potential for additive sedative effects. Caution patients against operating heavy equipment or driving until they know how they respond to treatment with INTUNIV . Advise patients to avoid use with alcohol.
5.3Cardiac Conduction Abnormalities The sympatholytic action of INTUNIV may worsen sinus node dysfunction and atrioventricular (AV) block, especially in patients taking other sympatholytic drugs. Titrate INTUNIV slowly and monitor vital signs frequently in patients with cardiac conduction abnormalities or patients concomitantly treated with other sympatholytic drugs.
5.4Rebound Hypertension In post marketing experience, abrupt discontinuation of INTUNIV has resulted in clinically significant and persistent rebound hypertension above baseline levels and increases in heart rate. Hypertensive encephalopathy has also been reported in association with rebound hypertension with both INTUNIV and immediate release guanfacine [see Adverse Reactions (6.2) ] . In these cases, high-dosage guanfacine was discontinued; concomitant stimulant use was also reported, which may potentially increase hypertensive response upon abrupt discontinuation of guanfacine.
Children commonly have gastrointestinal illnesses that lead to vomiting, and a…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Hypotension, bradycardia, and syncope [see Warnings and Precautions (5.1) ] Sedation and somnolence [see Warnings and Precautions (5.2) ] Cardiac conduction abnormalities [see Warnings and Precautions (5.3) ] Rebound Hypertension [see Warnings and Precautions (5.4) ] Most common adverse reactions (≥5% and at least twice placebo rate) in fixed-dose monotherapy ADHD trials in children and adolescents (6 to 17 years): hypotension, somnolence, fatigue, nausea, and lethargy ( 6.1 ) Flexible dose-optimization ADHD trials in children (6 to 12 years) and adolescents (13 to 17 years): somnolence, hypotension, abdominal pain, insomnia, fatigue, dizziness, dry mouth, irritability, nausea, vomiting, and bradycardia ( 6.1 ).
Adjunctive treatment to psychostimulant ADHD trial in children and adolescents (6 to 17 years): somnolence, fatigue, insomnia, dizziness, and abdominal pain ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Takeda Pharmaceuticals at 1-877-TAKEDA-7 (1-877-825-3327) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect clinical trial exposure to INTUNIV in 2,825 patients. This includes 2,330 patients from completed studies in children and adolescents, ages 6 to 17 years and 495 patients in completed studies in adult healthy volunteers.
The mean duration of exposure of 446 patients that previously participated in two 2-year, open-label long-term studies was approximately 10 months. Fixed Dose Trials Table 3: Percentage of Patients Experiencing Most Common (≥5% and at least twice the rate for placebo) Adverse Reactions in Fixed Dose Studies 1 and 2 INTUNIV (mg) Adverse Reaction Term Placebo (N=149) 1 mg The lowest dose of 1 mg used in Study 2 was not randomized to patients weighing more than 50 kg. (N=61) 2 mg (N=150) 3 mg (N=151) 4 mg (N=151) All Doses of INTUNIV (N=513) Somnolence The somnolence term includes somnolence, sedation, and hypersomnia.
11% 28% 30% 38% 51% 38% Fatigue 3% 10% 13% 17% 15% 14% Hypotension The hypotension term includes hypotension, diastolic hypotension, orthostatic hypotension, blood pressure decreased, blood pressure diastolic decreased, blood pressure systolic decreased). 3% 8% 5% 7% 8% 7% Dizziness 4% 5% 3% 7% 10% 6% Lethargy 3% 2% 3% 8% 7% 6% Nausea 2% 7% 5% 5% 6% 6% Dry mouth 1% 0% 1% 6% 7% 4% Table 4: Adverse Reactions Leading to Discontinuation (≥2% for all doses of INTUNIV and >rate than in placebo) in Fixed Dose Studies 1 and 2 INTUNIV (mg) Adverse Reaction Term Placebo (N=149) 1 mg The lowest dose of 1 mg used in Study 2 was not randomized to patients weighing more than 50 kg.
(N=61) 2 mg (N=150) 3 mg (N=151) 4 mg (N=151) All Doses of INTUNIV (N=513) n (%) n (%) n (%) n (%) n (%) n (%) Adverse reactions leading to discontinuation in ≥2% in any dose group but did not meet this criteria in all doses combined: hypotension (hypotension, diastolic hypotension, orthostatic hypotension, blood pressure decreased, blood pressure diastolic decreased, blood pressure systolic decreased), headache, and dizziness. Total patients 4 (3%) 2 (3%) 10 (7%) 15 (10%) 27 (18%) 54 (11%) Somnolence The somnolence term includes somnolence, sedation, and hypersomnia.
1 (1%) 2 (3%) 5 (3%) 6 (4%) 17 (11%) 30 (6%) Fatigue 0 (0%) 0 (0%) 2 (1%) 2 (1%) 4 (3%) 8 (2%) Table 5: Other Common Adverse Reactions (≥2% for all doses of INTUNIV and >rate than in placebo) in Fixed Dose Studies 1 and 2 INTUNIV (mg) Adverse Reaction Term Placebo (N=149) 1 mg The lowest dose of 1 mg used in Study 2 was not randomized to patients weighing more than 50 kg. (N=61) 2 mg (N=150) 3 mg (N=151) 4 mg (N=151) All Doses…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 14 contains clinically important drug interactions with INTUNIV [see Clinical Pharmacology (12.3) ]. Table 14: Clinically Important Drug Interactions: Effect of other Drugs on INTUNIV Concomitant Drug Name or Drug Class Clinical Rationale and Magnitude of Drug Interaction Clinical Recommendation Strong and moderate CYP3A4 inhibitors, e.g., ketoconazole, fluconazole Guanfacine is primarily metabolized by CYP3A4 and its plasma concentrations can be significantly affected resulting in an increase in exposure Consider dose reduction [see Dosage and administration (2.7) ] Strong and moderate CYP3A4 inducers, e.g., rifampin, efavirenz Guanfacine is primarily metabolized by CYP3A4 and its plasma concentrations can be significantly affected resulting in a decrease in exposure Consider dose increase [see Dosage and administration (2.7) ] Strong and moderate CYP3A4 inhibitors increase guanfacine exposure.
Decrease INTUNIV to 50% of target dosage when coadministered with strong and moderate CYP3A4 inhibitors ( 2.7 ). Strong and moderate CYP3A4 inducers decrease guanfacine exposure. Based on patient response, consider titrating INTUNIV dosage up to double the target dosage over 1 to 2 weeks ( 2.7 ).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including INTUNIV, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388. Risk Summary Available data with guanfacine over decades of use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
However, use of guanfacine in pregnant women over this time has been infrequent. In animal reproduction studies, rabbits and rats exposed to 3 and 4 times the maximum recommended human dose (MRHD), respectively, showed no adverse outcomes. However, higher doses were associated with reduced fetal survival and maternal toxicity ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Reproduction studies conducted in rats have shown that guanfacine crosses the placenta. However, administration of guanfacine to rabbits and rats during organogenesis at 3 (rabbit) and 4 (rat) times the MRHD of 0.12 mg/kg/day on a mg/m 2 basis resulted in no evidence of harm to the fetus. Higher doses (13.5 times the MRHD in both rabbits and rats) were associated with reduced fetal survival and maternal toxicity.
8.2Lactation Risk Summary There are no data on the presence of guanfacine in human milk or the effects on the breastfed infant. The effects on milk production are also unknown. Guanfacine is present in the milk of lactating rats (see Data ) .
If a drug is present in animal milk, it is likely that the drug will be present in human milk. If an infant is exposed to guanfacine through breastmilk, monitor for symptoms of hypotension and bradycardia such as sedation, lethargy, and poor feeding (see Clinical Considerations ). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for INTUNIV and any potential adverse effects on the breastfed child from INTUNIV or from the underlying maternal condition.
Clinical Considerations Monitor breastfeeding infants exposed to guanfacine through breastmilk for sedation, lethargy, and poor feeding. Data Guanfacine was excreted in breast milk of lactating rats at a concentration comparable to that observed in blood, but slightly less than the concentration in plasma when administered following a single oral dose of 5 mg/kg. The concentration of drug in animal milk does not necessarily predict the concentration of drug in human milk.
8.4Pediatric Use Safety and efficacy of INTUNIV in pediatric patients less than 6 years of age have not been established. The efficacy of INTUNIV was studied for the treatment of ADHD in five controlled monotherapy clinical trials (up to 15 weeks in duration), one randomized withdrawal study and one controlled adjunctive trial with psychostimulants (8 weeks in duration) in children and adolescents ages 6 to 17 who met DSM-IV ® criteria for ADHD [see Adverse Reactions (6) and Clinical Studies (14) ]. Animal Data In studies in juvenile rats, guanfacine alone produced a slight delay in sexual maturation in males and females at 2 to 3 times the maximum recommended human dose (MRHD).
Guanfacine in combination with methylphenidate produced a slight delay in sexual maturation and decreased growth as measured by a decrease in bone length in males at a dose of guanfacine comparable to the MRHD and a dose of methylphenidate approximately 4 times the MRHD. In a study where juvenile rats were treated with guanfacine alone from 7 to 59 days of age, de…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including INTUNIV, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388. Risk Summary Available data with guanfacine over decades of use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
However, use of guanfacine in pregnant women over this time has been infrequent. In animal reproduction studies, rabbits and rats exposed to 3 and 4 times the maximum recommended human dose (MRHD), respectively, showed no adverse outcomes. However, higher doses were associated with reduced fetal survival and maternal toxicity ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Reproduction studies conducted in rats have shown that guanfacine crosses the placenta. However, administration of guanfacine to rabbits and rats during organogenesis at 3 (rabbit) and 4 (rat) times the MRHD of 0.12 mg/kg/day on a mg/m 2 basis resulted in no evidence of harm to the fetus. Higher doses (13.5 times the MRHD in both rabbits and rats) were associated with reduced fetal survival and maternal toxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of INTUNIV in pediatric patients less than 6 years of age have not been established. The efficacy of INTUNIV was studied for the treatment of ADHD in five controlled monotherapy clinical trials (up to 15 weeks in duration), one randomized withdrawal study and one controlled adjunctive trial with psychostimulants (8 weeks in duration) in children and adolescents ages 6 to 17 who met DSM-IV ® criteria for ADHD [see Adverse Reactions (6) and Clinical Studies (14) ]. Animal Data In studies in juvenile rats, guanfacine alone produced a slight delay in sexual maturation in males and females at 2 to 3 times the maximum recommended human dose (MRHD).
Guanfacine in combination with methylphenidate produced a slight delay in sexual maturation and decreased growth as measured by a decrease in bone length in males at a dose of guanfacine comparable to the MRHD and a dose of methylphenidate approximately 4 times the MRHD. In a study where juvenile rats were treated with guanfacine alone from 7 to 59 days of age, development was delayed as indicated by a slight delay in sexual maturation and decreased body weight gain in males at 2 mg/kg/day and in females at 3 mg/kg/day.
The No Adverse Effect Level (NOAEL) for delayed sexual maturation was 1 mg/kg/day, which is equivalent to the MRHD of 4 mg/day, on a mg/m 2 basis. The effects on fertility were not evaluated in this study. In a study where juvenile rats were treated with guanfacine in combination with methylphenidate from 7 to 59 days of age, a decrease in ulna bone length and a slight delay in sexual maturation were observed in males given 1 mg/kg/day of guanfacine in combination with 50 mg/kg/day of methylphenidate.
The NOAELs for these findings were 0.3 mg/kg of guanfacine in combination with 16 mg/kg/day of methylphenidate, which are equivalent to 0.3 and 1.4 times the MRHD of 4 mg/day and 54 mg/day for guanfacine and methylphenidate, respectively, on a mg/m 2 basis. These findings were not observed with guanfacine alone at 1 mg/kg/day or methylphenidate alone at 50 mg/kg/day.
🧓 Geriatric Use ▾
8.5Geriatric Use The safety and efficacy of INTUNIV in geriatric patients have not been established.
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms Postmarketing reports of guanfacine overdosage indicate that hypotension, drowsiness, lethargy, and bradycardia have been observed following overdose. Initial hypertension may develop early and may be followed by hypotension. Similar symptoms have been described in voluntary reports to the American Association of Poison Control Center's National Poison Data System.
Miosis of the pupils may be noted on examination . No fatal overdoses of guanfacine have been reported in published literature. Treatment Consult a Certified Poison Control Center by calling 1-800-222-1222 for up-to-date guidance and advice.
Management of INTUNIV overdose should include monitoring for and the treatment of initial hypertension, if that occurs, as well as hypotension, bradycardia, lethargy, and respiratory depression. Children and adolescents who develop lethargy should be observed for the development of more serious toxicity including coma, bradycardia, and hypotension for up to 24 hours, due to the possibility of delayed onset hypotension.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Guanfacine is a central alpha 2A -adrenergic receptor agonist. Guanfacine is not a central nervous system (CNS) stimulant. The mechanism of action of guanfacine in ADHD is not known.
12.2Pharmacodynamics Guanfacine is a selective central alpha 2A -adrenergic receptor agonist in that it has a 15 to 20 times higher affinity for this receptor subtype than for the alpha 2B or alpha 2C subtypes. Guanfacine is a known antihypertensive agent. By stimulating central alpha 2A -adrenergic receptors, guanfacine reduces sympathetic nerve impulses from the vasomotor center to the heart and blood vessels.
This results in a decrease in peripheral vascular resistance and a reduction in heart rate. In a thorough QT study, the administration of two dose levels of immediate-release guanfacine (4 mg and 8 mg) produced concentrations approximately 2 to 4 times the concentrations observed with the maximum recommended dose of INTUNIV of 0.12 mg/kg. Guanfacine was not shown to prolong the QTc interval to any clinically relevant extent.
12.3Pharmacokinetics Absorption and Distribution Guanfacine is readily absorbed and approximately 70% bound to plasma proteins independent of drug concentration. After oral administration of INTUNIV the time to peak plasma concentration is approximately 5 hours in children and adolescents with ADHD. Immediate-release guanfacine and INTUNIV have different pharmacokinetic characteristics; dose substitution on a milligram per milligram basis will result in differences in exposure.
A comparison across studies suggests that the C max is 60% lower and AUC 0-∞ 43% lower, respectively, for INTUNIV compared to immediate-release guanfacine. Therefore, the relative bioavailability of INTUNIV to immediate-release guanfacine is 58%. The mean pharmacokinetic parameters in adults following the administration of INTUNIV 1 mg once daily and immediate-release guanfacine 1 mg once daily are summarized in Table 15.
Table 15: Comparison of Pharmacokinetics: INTUNIV vs. Immediate release Guanfacine in Adults Parameter INTUNIV 1 mg once daily (n=52) Immediate-release guanfacine 1 mg once daily (n=12) Note: Values are mean +/- SD, except for t max which is median (range) C max (ng/mL) 1.0 ± 0.3 2.5 ±
0.6AUC 0-∞ (ng∙h/mL) 32 ± 9 56 ± 15 t max (h) 6.0 (4.0 – 8.0) 3.0 (1.5-4.0) t ½ (h) 18 ± 4 16 ± 3 Figure 1: Comparison of Pharmacokinetics: INTUNIV vs. Immediate-release guanfacine in Adults Exposure to guanfacine was higher in children (ages 6 to 12) compared to adolescents (ages 13 to 17) and adults. After oral administration of multiple doses of INTUNIV 4 mg, the C max was 10 ng/mL compared to 7 ng/mL and the AUC was 162 ng∙h/mL compared to 116 ng∙h/mL in children (ages 6 to 12) and adolescents (ages 13 to 17), respectively.
These differences are probably attributable to the lower body weight of children compared to adolescents and adults. The pharmacokinetics were affected by intake of food when a single dose of INTUNIV 4 mg was administered with a high-fat breakfast. The mean exposure increased (C max ~75% and AUC ~40%) compared to dosing in a fasted state.
Figure 1 Dose Proportionality Following administration of INTUNIV in single doses of 1 mg, 2 mg, 3 mg, and 4 mg to adults, C max and AUC 0-∞ of guanfacine were proportional to dose. Metabolism and Elimination In vitro studies with human liver microsomes and recombinant CYP's demonstrated that guanfacine was primarily metabolized by CYP3A4. In pooled human hepatic microsomes, guanfacine did not inhibit the activities of the major cytochrome P450 isoenzymes (CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP3A4/5); guanfacine is also not an inducer of CYP3A, CYP1A2, and CYP2B6.
Guanfacine is a substrate of CYP3A4/5 and exposure is affected by CYP3A4/5 inducers/inhibitors. Guanfacine inhibits MATE1 and OCT1, but does not inhibit BSEP, MRP2, OATP1B1, OATP1B3, OAT1, OAT3, OCT2, or MATE2K. Guanfacine is a substrate of OCT1 and OCT2, but…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Guanfacine is a central alpha 2A -adrenergic receptor agonist. Guanfacine is not a central nervous system (CNS) stimulant. The mechanism of action of guanfacine in ADHD is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING INTUNIV is supplied in 1 mg, 2 mg, 3 mg, and 4 mg strength extended-release tablets in 100 count bottles. 1 mg 2 mg 3 mg 4 mg Color White/off-white White/off-white Green Green Shape Round Caplet Round Caplet Debossment (top/bottom) 503 / 1 mg 503 / 2 mg 503 / 3 mg 503 / 4 mg NDC number 54092-513-02 54092-515-02 54092-517-02 54092-519-02 Storage - Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). See USP Controlled Room Temperature.
📦 Storage and Handling ▾
Storage - Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). See USP Controlled Room Temperature.
📋 Description ▾
11 DESCRIPTION INTUNIV is a once-daily, extended-release formulation of guanfacine hydrochloride (HCl) in a matrix tablet formulation for oral administration only. The chemical designation is N-amidino-2-(2,6-dichlorophenyl) acetamide monohydrochloride. The molecular formula is C 9 H 9 Cl 2 N 3 O∙HCl corresponding to a molecular weight of 282.55 g/mol.
The chemical structure is: Guanfacine HCl is a white to off-white crystalline powder, sparingly soluble in water (approximately 1 mg/mL) and alcohol and slightly soluble in acetone. The only organic solvent in which it has relatively high solubility is methanol (>30 mg/mL). Each tablet contains guanfacine HCl equivalent to 1 mg, 2 mg, 3 mg, or 4 mg of guanfacine base.
The tablets also contain hypromellose, methacrylic acid copolymer, lactose, povidone, crospovidone, microcrystalline cellulose, fumaric acid, and glyceryl behenate. In addition, the 3-mg and 4-mg tablets also contain green pigment blend PB-1763. Chemical Stucture
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Dosing and Administration Instruct patients to swallow INTUNIV whole with water, milk, or other liquid. Tablets should not be crushed, chewed or broken prior to administration because this may increase the rate of release of the active drug .
Patients should not take INTUNIV together with a high-fat meal, since this can raise blood levels of INTUNIV. Instruct the parent or caregiver to supervise the child or adolescent taking INTUNIV and to keep the bottle of tablets out of reach of children. Advise patients not to abruptly discontinue INTUNIV as abrupt discontinuation can result in clinically significant rebound hypertension.
Concomitant stimulant use and abrupt discontinuation of INTUNIV may increase this hypertensive response. Instruct patients on how to properly taper the dose to minimize the risk of rebound hypertension [see Dosage and Administration (2.5) and Warnings and Precautions (5.4) ]. Adverse Reactions Advise patients that sedation can occur, particularly early in treatment or with dose increases.
Caution against operating heavy equipment or driving until they know how they respond to treatment with INTUNIV [see Warnings and Precautions (5.2) ]. Headache and abdominal pain can also occur. If any of these symptoms persist, or other symptoms occur, the patient should be advised to discuss the symptoms with the health care provider.
Advise patients to avoid becoming dehydrated or overheated, which may potentially increase the risks of hypotension and syncope [see Warnings and Precautions (5.1) ] . Advise patients to avoid use with alcohol. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in patients exposed to INTUNIV during pregnancy [see Use in Specific Populations (8.1) ].
Lactation Advise breastfeeding mothers to monitor infants exposed to guanfacine through breastmilk for sedation, lethargy, and poor feeding [see Use in Specific Populations (8.2) ].