
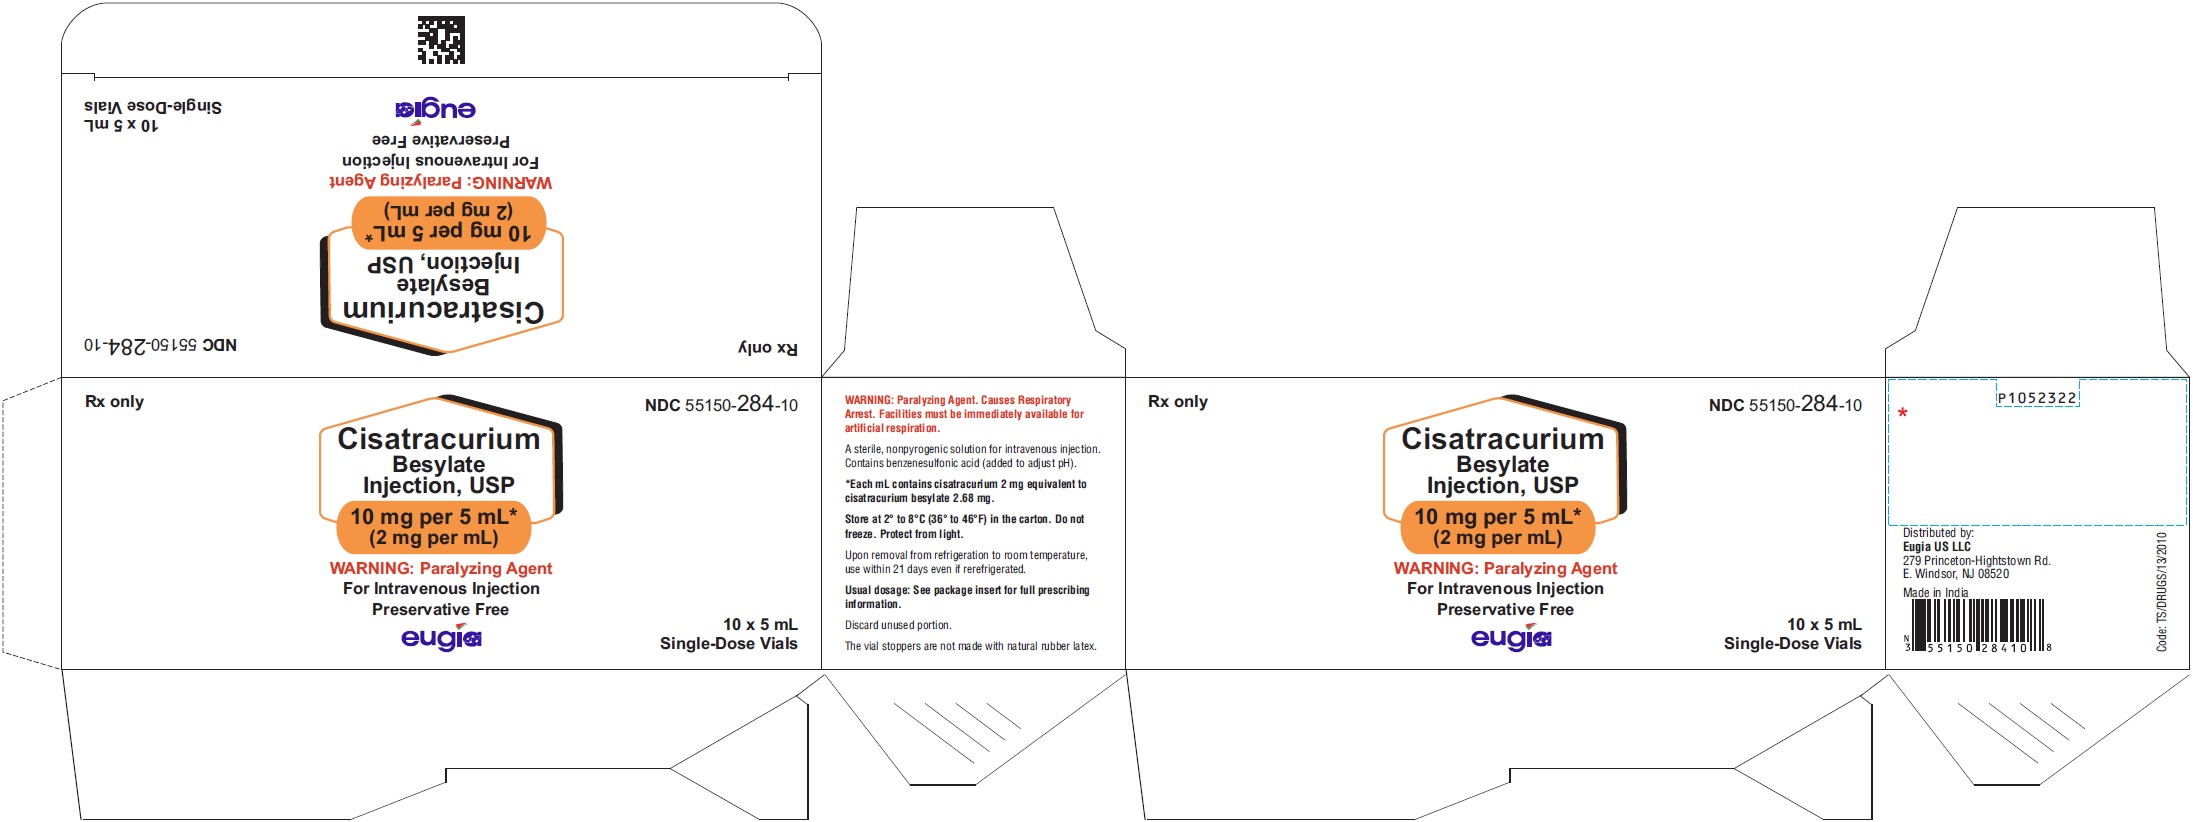
Cisatracurium Besylate 10 mg/5mL Injection
Other active recalls for Cisatracurium Besylate (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nondepolarizing Neuromuscular Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Cisatracurium temporarily paralyzes your skeletal muscles — the muscles you use to move your arms, legs, and breathe. It does this by blocking the signal between your nerves and mu...
- What exactly does cisatracurium do to my body?
- No — cisatracurium is always given alongside general anesthesia or appropriate sedation. The drug itself only relaxes your muscles; it does not cause unconsciousness or prevent you...
- Will I be awake or aware of anything while this drug is working?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 685928Z18A
A synthetic organic acid used as a buffer and pH adjuster in medicines. It helps maintain the proper acidity level so the drug stays stable and works effectively in the formulation.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cisatracurium Besylate 2 mg/mL 00143-9396-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Cisatracurium Besylate 2 mg/mL 00409-1098-02 | Hospira, | 10 vials | — | AP | FDA listed | — |
| cisatracurium besylate 2 mg/mL 00781-3150-95 | Sandoz | 1 vial | — | AP | FDA listed | — |
| Cisatracurium Besylate 2 mg/mL 31722-0313-10 | Camber | 10 vials | — | AP | FDA listed | — |
| Cisatracurium Besylate 10 mg/5mLthis 55150-0284-10 | Eugia | 10 vials | — | — | FDA listed | — |
| Cisatracurium 2 mg/mL 63323-0416-05 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Cisatracurium besylate 2 mg/mL 65145-0135-01 | Caplin | 1 vial | — | AP | FDA listed | — |
| Cisatracurium besylate 2 mg/mL 68083-0486-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Cisatracurium Besylate 2 mg/mL 70069-0141-01 | Somerset | 1 vial | — | AP | FDA listed | — |
| Cisatracurium besylate 2 mg/mL 70436-0112-82 | Slate | 10 vials | — | AP | FDA listed | — |
| cisatracurium besylate 2 mg/mL 70710-1532-06 | Zydus | 10 vials | — | AP | FDA listed | — |
| Cisatracurium Besylate 10 mg/5mL 71288-0712-06 | Meitheal | 10 vials | — | AP | FDA listed | — |
| cisatracurium besylate 2 mg/mL 72785-0008-06 | Zydus | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55150-0284-10 You're viewing this | 10 VIAL, SINGLE-DOSE in 1 CARTON (55150-284-10) / 5 mL in 1 VIAL, SINGLE-DOSE (55150-284-01) | 2020-10-27 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Cisatracurium besylate injection is indicated: as an adjunct to general anesthesia to facilitate tracheal intubation in adults and in pediatric patients 1 month to 12 years of age to provide skeletal muscle relaxation in adults during surgical procedures or during mechanical ventilation in the ICU to provide skeletal muscle relaxation during surgical procedures via infusion in pediatric patients 2 years and older Limitations of Use Cisatracurium besylate injection is not recommended for rapid sequence endotracheal intubation due to the time required for its onset of action.
Cisatracurium besylate injection is a nondepolarizing neuromuscular blocker indicated: as an adjunct to general anesthesia to facilitate tracheal intubation in adults and in pediatric patients 1 month to 12 years of age (1) to provide skeletal muscle relaxation during surgery in adults and in pediatric patients 2 to 12 years of age as a bolus or infusion maintenance (1) for mechanical ventilation in the ICU in adults (1) Limitations of Use: Cisatracurium besylate injection is not recommended for rapid sequence endotracheal intubation due to the time required for its onset of action (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Store cisatracurium besylate injection with the cap and ferrule intact and in a manner that minimizes the possibility of selecting the wrong product ( 2.1 ) Administer intravenously only by or under the supervision of experienced clinicians familiar with drug’s actions and possible complications ( 2.1 ) Use only if personnel and facilities for resuscitation and life support, and a cisatracurium besylate injection antagonist are immediately available ( 2.1 ) Use a peripheral nerve stimulator to determine adequacy of blockade (e.g., need for additional doses), minimize risk of overdosage or underdosage, assess extent of recovery from blockade, potentially limit exposure to toxic metabolites through dose titration, and facilitate more rapid reversal of cisatracurium besylate injection-induced paralysis ( 2.1 ) See the Full Prescribing Information for: Dosage and administration instructions in adults, pediatric patients, geriatric patients, patients with neuromuscular disease, burns, end-stage renal disease, and patients undergoing coronary artery bypass graft surgery with induced hypothermia ( 2.2 , 2.3 , 2.4 , 2.5 ) Continuous infusion rates ( 2.6 ) Preparation instructions ( 2.7 ) Drug compatibility ( 2.8 )
2.1Important Dosage and Administration Instructions Risk of Medication Errors Accidental administration of neuromuscular blocking agents may be fatal. Store cisatracurium besylate injection with the cap and ferrule intact and in a manner that minimizes the possibility of selecting the wrong product [see Warnings and Precautions (5.5) ]. Important Administration Instructions Cisatracurium besylate injection is for intravenous use only.
Administer cisatracurium besylate injection in carefully adjusted dosage by or under the supervision of experienced clinicians who are familiar with the drug’s actions and the possible complications. Use cisatracurium besylate injection only if the following are immediately available: personnel and facilities for resuscitation and life support (tracheal intubation, artificial ventilation, oxygen therapy); and an antagonist of cisatracurium besylate injection [see Overdosage (10) ] . The dosage information which follows is intended to serve as an initial guide for individual patients; base subsequent cisatracurium besylate injection dosage on the patients’ responses to the initial doses.
Use a peripheral nerve stimulator to: Determine the adequacy of neuromuscular blockade (e.g., need for additional cisatracurium besylate injection doses, reduction of the infusion rate). Minimize risk of overdosage or underdosage. Assess the extent of recovery from neuromuscular blockade (e.g., spontaneous recovery or recovery after administration of a reversal agent, e.g., neostigmine).
Appropriately titrate doses to potentially limit exposure to toxic metabolites. Facilitate more rapid reversal of the cisatracurium besylate injection-induced paralysis.
2.2Recommended Cisatracurium Besylate Injection Dose for Performing Tracheal Intubation Tracheal Intubation in Adults Prior to selecting the initial cisatracurium besylate injection bolus dose, consider the desired time to tracheal intubation and the anticipated length of surgery, factors affecting time to onset of complete neuromuscular block such as age and renal function, and factors that may influence intubation conditions such as the presence of co-induction agents (e.g., fentanyl and midazolam) and the depth of anesthesia.
In conjunction with a propofol/nitrous oxide/oxygen induction-intubation technique or a thiopental/nitrous oxide/oxygen induction-intubation technique, the recommended starting weight-based dose of cisatracurium besylate injection is between 0.15 mg/kg and 0.2 mg/kg administered by bolus intravenous injection. Doses up to 0.4 mg/kg have been safely administered by bolus intravenous injection to healthy patients and patients with serious cardiovascular disease [see Clinical Pharmacology (12.2) ] . Patients wi…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Cisatracurium besylate injection is available as a clear colorless to slightly yellow or greenish-yellow solution in the following strengths: 10 mg of cisatracurium per 5 mL (2 mg/mL) in single-dose vials (equivalent to 2.68 mg/mL cisatracurium besylate) 20 mg of cisatracurium per 10 mL (2 mg/mL) in multiple-dose vials (equivalent to 2.68 mg/mL cisatracurium besylate) with benzyl alcohol as a preservative. Injection: 10 mg/5 mL (2 mg/mL) in single-dose vials ( 3 ) 20 mg/10 mL (2 mg/mL) and benzyl alcohol as a preservative in multiple-dose vials ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Cisatracurium besylate injection is contraindicated in patients with known hypersensitivity to cisatracurium. Severe anaphylactic reactions to cisatracurium have been reported [see Warnings and Precautions (5.4) ] . The use of 10 mL cisatracurium besylate injection multiple-dose vials is contraindicated for use in pediatric patients less than 1 month of age and low birth-weight infants because the formulation contains benzyl alcohol [see Warnings and Precautions (5.2) and Use in Specific Populations (8.4) ].
Known hypersensitivity to cisatracurium ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Residual Paralysis : Patients with neuromuscular diseases are at higher risk. Use a lower initial bolus dose and consider using a reversal agent in these patients. ( 2.2 , 5.1 ) Benzyl Alcohol : Consider combined daily load of benzyl alcohol from all sources when the 10 mL multiple dose vials are used in infants ( 4 , 5.2 ) Risk of Seizure : Monitor level of neuromuscular blockade during long-term administration to limit exposure to toxic metabolites ( 5.3 ) Hypersensitivity Reactions and Anaphylaxis : Severe hypersensitivity reactions including anaphylactic reactions have been reported.
Consider cross-reactivity among neuromuscular blocking agents, both depolarizing and non-depolarizing. ( 4 , 5.4 ) Risk of Death due to Medication Errors : Accidental administration can cause death. ( 5.5 ) Inadequate Anesthesia : Use cisatracurium besylate in the presence of appropriate sedation or general anesthesia and monitor patients to ensure level of anesthesia is adequate ( 5.6 )
5.1Residual Paralysis Cisatracurium has been associated with residual paralysis. Patients with neuromuscular diseases (e.g., myasthenia gravis and myasthenic syndrome) and carcinomatosis may be at higher risk of residual paralysis; thus, a lower maximum initial bolus is recommended in these patients [see Dosage and Administration (2.2) and Use in Specific Populations (8.10) ] . To prevent complications resulting from cisatracurium-associated residual paralysis, extubation is recommended only after the patient has recovered sufficiently from neuromuscular blockade.
Consider use of a reversal agent especially in cases where residual paralysis is more likely to occur [see Overdosage (10) ] .
5.2Risk of Serious Adverse Reactions in Infants due to Benzyl Alcohol Preservative in 10 mL Multiple-Dose Vials Serious and fatal adverse reactions including “gasping syndrome” can occur in neonates and infants treated with benzyl alcohol-preserved drugs, including cisatracurium (10 mL multiple-dose vials). This warning is not applicable to the 5 mL and 20 mL cisatracurium single-dose vials because these vials do not contain benzyl alcohol. The “gasping syndrome” is characterized by central nervous system depression, metabolic acidosis, and gasping respirations.
When prescribing the 10 mL multiple-dose cisatracurium vials in infants consider the combined daily metabolic load of benzyl alcohol from all sources including cisatracurium (multiple-dose vials contain 9 mg of benzyl alcohol per mL) and other drugs containing benzyl alcohol. The minimum amount of benzyl alcohol at which serious adverse reactions may occur is not known [see Use in Specific Populations (8.4) ]. The use of 10 mL cisatracurium multiple-dose vials is contraindicated in pediatric patients less than 1 month of age and low birth-weight infants because these patients are more likely to develop benzyl alcohol toxicity [see Contraindications (4) ].
5.3Risk of Seizure Laudanosine, an active metabolite of cisatracurium, has been shown to cause seizures in animals. Cisatracurium-treated patients with renal or hepatic impairment may have higher metabolite concentrations (including laudanosine) than patients with normal renal and hepatic function [see Clinical Pharmacology (12.3) ] . Therefore, patients with renal or hepatic impairment receiving extended administration of cisatracurium may be at higher risk of seizures.
The level of neuromuscular blockade during long-term cisatracurium administration should be monitored with a nerve stimulator to titrate cisatracurium administration to the patients’ needs and limit exposure to toxic metabolites.
5.4Hypersensitivity Reactions Including Anaphylaxis Severe hypersensitivity reactions, including fatal and life-threatening anaphylactic reactions, have been reported [see Contraindications (4) ] . There have been reports of wheezing, laryngospasm, bronchospasm, rash and itching following cisatracurium administration in pediatric patients. Due…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (0.1% to 0.4%) were bradycardia, hypotension, flushing, bronchospasm, and rash. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Eugia US LLC at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Adverse Reactions in Clinical Trials of Cisatracurium in Surgical Patients The data presented below are based on studies involving 945 surgical patients who received cisatracurium in conjunction with other drugs in US and European clinical studies in a variety of procedures [see Clinical Studies (14.1) ] .
Table 3 displays adverse reactions that occurred at a rate of less than 1%. Table 3. Adverse Reactions in Clinical Trials of Cisatracurium in Surgical Patients Adverse Reaction Incidence Bradycardia 0.4% Hypotension 0.2% Flushing 0.2% Bronchospasm 0.2% Rash 0.1% Adverse Reactions in Clinical Trials of Cisatracurium in Intensive Care Unit Patients The adverse reactions presented below were from studies involving 68 adult ICU patients who received cisatracurium in conjunction with other drugs in US and European clinical studies [see Clinical Studies (14.3) ] .
One patient experienced bronchospasm. In one of the two ICU studies, a randomized and double-blind study of ICU patients using TOF neuromuscular monitoring, there were two reports of prolonged recovery (range: 167 and 270 minutes) among 28 patients administered cisatracurium and 13 reports of prolonged recovery (range: 90 minutes to 33 hours) among 30 patients administered vecuronium.
6.2Postmarketing Experience The following events have been identified during post-approval use of cisatracurium in conjunction with one or more anesthetic agents in clinical practice. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. These events have been chosen for inclusion due to a combination of their seriousness, frequency of reporting, or potential causal connection to cisatracurium: anaphylaxis, histamine release, prolonged neuromuscular block, muscle weakness, myopathy.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Succinylcholine: May decrease time to onset of maximum neuromuscular blockade ( 7.1 ) Inhalational anesthetics, antibiotics, local anesthetics, magnesium salts, procainamide, lithium, quinidine : May potentiate or prolong neuromuscular blockade action of cisatracurium besylate. Use peripheral nerve stimulator and monitor clinical signs of neuromuscular blockade. ( 5.8 , 7.1 ) Phenytoin and Carbamazepine : May shorten duration of neuromuscular blockade.
Use peripheral nerve stimulator and monitor clinical signs of neuromuscular blockade. ( 5.9 , 7.1 )
7.1Clinically Significant Drug Interactions Table 4 displays clinically significant drug interactions with cisatracurium. Table 4. Clinically Significant Drug Interactions with Cisatracurium * The use of peripheral nerve stimulator is strongly recommended to evaluate the level of neuromuscular blockade, to assess the need for additional doses of cisatracurium, and to determine whether adjustments need to be made to the dose with subsequent administration. † Examples: aminoglycosides, tetracyclines, bacitracin, polymyxins, lincomycin, clindamycin, colistin, sodium colistimethate Drug or Drug Class Clinical Implications* Succinylcholine The use of succinylcholine prior to cisatracurium administration may decrease the time to onset of maximum neuromuscular blockade but has no effect on the duration of neuromuscular blockade.
Inhalational Anesthetics Administration of inhalational anesthetics with nitrous oxide/oxygen for greater than 30 minutes to achieve
1.25Minimum Alveolar Concentration (MAC) may prolong the duration of action of initial and maintenance doses of cisatracurium. This may potentiate the neuromuscular blockade. Antibiotics † Local anesthetics Magnesium salts Procainamide Lithium Quinidine May prolong the neuromuscular blockade action of cisatracurium Phenytoin, Carbamazepine May increase resistance to the neuromuscular blockade action of cisatracurium resulting in shorter durations of neuromuscular blockade and infusion rate requirements may be higher.
7.2Drugs Without Clinically Significant Drug Interactions with Cisatracurium Besylate In clinical studies, propofol had no effect on the duration of action or dosing requirements for cisatracurium. Cisatracurium is not compatible with propofol for Y-site administration.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Patients with Hemiparesis or Paraparesis : Perform neuromuscular monitoring on non-paretic limb ( 8.9 )
8.1Pregnancy Risk Summary The 10 mL cisatracurium besylate injection multiple-dose vials contain the preservative benzyl alcohol. Therefore, if cisatracurium besylate injection is needed during pregnancy, consider using a benzyl alcohol-free formulation (i.e., 5 mL cisatracurium besylate injection single-dose vials). Because benzyl alcohol is rapidly metabolized by a pregnant woman, benzyl alcohol exposure in the fetus is unlikely.
However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Contraindications (4) , Warnings and Precautions (5.2) , and Use in Specific Populations (8.4) ]. There are no available clinical trial data on cisatracurium use in pregnancy to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal studies conducted in rats administered cisatracurium besylate during organogenesis (Gestational Day 6 to 15) found no evidence of fetal harm at 0.8 times (ventilated rats) the exposure from a human starting IV bolus dose of 0.2 mg/kg (see Data).
The estimated background risk for major birth defects and miscarriage in the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Labor or Delivery The action of neuromuscular blocking agents may be enhanced by magnesium salts administered for the management of preeclampsia or eclampsia of pregnancy. Data Animal Data Two embryofetal developmental reproductive toxicity studies were conducted in rats. In a non- ventilated rat study, pregnant animals were treated with cisatracurium besylate subcutaneously twice per day from Gestational Day 6 to 15 using subparalyzing doses (2 and 4 mg/kg daily; equivalent to 6- and 12-times, respectively, the AUC exposure in humans following a bolus dose of 0.2 mg/kg IV).
In the ventilated rat study, pregnant animals were treated with cisatracurium besylate intravenously once a day between Gestational Day 6 to 15 using paralyzing doses (0.5 and 1 mg/kg; equivalent to 0.4- and 0.8-times, respectively, the exposure in humans following a bolus dose of 0.2 mg/kg IV based on mg/m 2 comparison). Neither of these studies revealed maternal or fetal toxicity or malformations.
8.2Lactation Risk Summary The 10 mL cisatracurium besylate injection multiple-dose vials contains the preservative benzyl alcohol. Therefore, if cisatracurium besylate injection is needed during lactation, consider using a benzyl alcohol-free formulation (i.e., 5 mL cisatracurium besylate injection single-dose vials). Because benzyl alcohol is rapidly metabolized by a lactating woman, benzyl alcohol exposure in the breastfed infant is unlikely.
However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Contraindications (4) , Warnings and Precautions (5.2) and Use in Specific Populations (8.4) ]. There are no data on the presence of cisatracurium besylate in human milk, the effects on the breastfed child, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for cisatracurium and any potential adverse effects on the breastfed child from cisatracurium or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of cisatracurium as an adjunct to general anesthesia to facilitate tracheal intubation, and to provide skeletal muscle relaxation during surgery in pediatric patients 1 month t…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The 10 mL cisatracurium besylate injection multiple-dose vials contain the preservative benzyl alcohol. Therefore, if cisatracurium besylate injection is needed during pregnancy, consider using a benzyl alcohol-free formulation (i.e., 5 mL cisatracurium besylate injection single-dose vials). Because benzyl alcohol is rapidly metabolized by a pregnant woman, benzyl alcohol exposure in the fetus is unlikely.
However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Contraindications (4) , Warnings and Precautions (5.2) , and Use in Specific Populations (8.4) ]. There are no available clinical trial data on cisatracurium use in pregnancy to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal studies conducted in rats administered cisatracurium besylate during organogenesis (Gestational Day 6 to 15) found no evidence of fetal harm at 0.8 times (ventilated rats) the exposure from a human starting IV bolus dose of 0.2 mg/kg (see Data).
The estimated background risk for major birth defects and miscarriage in the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Labor or Delivery The action of neuromuscular blocking agents may be enhanced by magnesium salts administered for the management of preeclampsia or eclampsia of pregnancy. Data Animal Data Two embryofetal developmental reproductive toxicity studies were conducted in rats. In a non- ventilated rat study, pregnant animals were treated with cisatracurium besylate subcutaneously twice per day from Gestational Day 6 to 15 using subparalyzing doses (2 and 4 mg/kg daily; equivalent to 6- and 12-times, respectively, the AUC exposure in humans following a bolus dose of 0.2 mg/kg IV).
In the ventilated rat study, pregnant animals were treated with cisatracurium besylate intravenously once a day between Gestational Day 6 to 15 using paralyzing doses (0.5 and 1 mg/kg; equivalent to 0.4- and 0.8-times, respectively, the exposure in humans following a bolus dose of 0.2 mg/kg IV based on mg/m 2 comparison). Neither of these studies revealed maternal or fetal toxicity or malformations.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of cisatracurium as an adjunct to general anesthesia to facilitate tracheal intubation, and to provide skeletal muscle relaxation during surgery in pediatric patients 1 month through 12 years of age were established from three studies in pediatric patients [see Dosing and Administration (2.2 , 2.5 ) and Clinical Studies (14.2) ] . The three open-label studies are summarized below. The safety and effectiveness of cisatracurium have not been established in pediatric patients less than 1 month of age.
Tracheal Intubation A study of 0.15 mg/kg cisatracurium evaluated 230 pediatric patients (ages 1 month to 12 years). Excellent or good intubating conditions were produced 120 seconds following 0.15 mg/kg of cisatracurium in 88 of 90 of patients induced with halothane and in 85 of 90 of patients induced with thiopentone and fentanyl. The study also evaluated 50 pediatric patients during opioid anesthesia, with maximum neuromuscular blockade achieved in an average of about 3 minutes and a clinically effective block for 36 minutes in patients ages 2 to 12 years, and maximum neuromuscular block in about 2 minutes and a clinically effective block for about 43 minutes in infants 1 to 23 months [see Clinical Studies (14.2) ] .
In a study of 0.1 mg/kg cisatracurium administered in 16 pediatric patients (ages 2 to 12 years) during opioid/nitrous oxide/oxygen anesthesia, maximum neuromuscular blockade was achieved in an average of 2.8 minutes with a clinically effective block for 28 minutes [see Clinical Studies (14.2) ] . Skeletal Muscle Relaxation During Surgery In a study of cisatracurium administered during halothane/nitrous oxide/oxygen anesthesia, 18 pediatric patients (ages 2 to 12 years) were scheduled for surgical procedures that required neuromuscular block for 60 minutes or longer.
The average duration of continuous infusion was 62.8 minutes (range: 17 to 145 minutes). The overall mean infusion rate for 9 patients whose infusion was 45 minutes or longer was 1.7 mcg/kg/minute (range: 1.19 to 2.14 mcg/kg/minute). Serious Adverse Reactions in InfantsDue to BenzylAlcoholPreservative in 10 mLMultiple-Dose Vials Seriousadversereactionsincludingfatalreactionsand the “gasping syndrome” occurred in premature neonatesandinfants in the neonatal intensive care unit whoreceiveddrugs containing benzylalcoholas a preservative.Inthesecases,benzylalcoholdosages of 99 to 234 mg/kg/dayproducedhighlevels of benzylalcoholand its metabolites in the blood andurine (bloodlevels of benzylalcoholwere 0.61 to 1.378 mmol/L).Additionaladversereactionsincludedgradualneurologicaldeterioration,seizures,intracranialhemorrhage,hematologicabnormalities, skin breakdown, hepatic andrenalfailure,hypotension,bradycardia,andcardiovascularcollapse.
Preterm,low-birthweightinfants may be more likely to develop these reactions because they may be lessable to metabolize benzyl alcohol. When prescribing the 10 mLmultiple-dose cisatracurium vials in infantsconsider the combined daily metabolic loadof benzylalcohol from allsources including cisatracurium (multiple-dose vialscontain 9 mg of benzyl alcohol per mL) and other drugscontainingbenzylalcohol.The minimum amount of benzylalcoholatwhich serious adversereactionsmay occur is not known [see Warnings and Precautions (5.2) ] .
This warning is not applicable to the 5 mL and 20 mL cisatracurium single-dose vials because these vials do not contain benzyl alcohol. The use of 10 mL cisatracurium multiple-dose vials is contraindicated in pediatric patients less than 1 month of age and low birth-weight infants because these patients are more likely to develop benzyl alcohol toxicity.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects (135) in clinical studies of cisatracurium, 57, 63, and 15 subjects were 65 to 70 years old, 70 to 80 years old, and greater than 80 years old, respectively. The geriatric population included a subset of patients with significant cardiovascular disease [see Clinical Pharmacology (12.3) ] . Because the time to maximum neuromuscular blockade is approximately 1 minute slower in geriatric patients compared to younger patients, consider extending the interval between administering cisatracurium and attempting intubation by at least 1 minute to achieve adequate intubation conditions [see Dosage and Administration (2.2) and Clinical Pharmacology (12.2) ] .
The time to maximum neuromuscular blockade is approximately 1 minute slower in geriatric patients, a difference that should be taken into account when selecting a neuromuscular blocking agent (e.g., the need to rapidly secure the airway) and when initiating laryngoscopy [see Clinical Pharmacology (12.3) ] . Minor differences in the pharmacokinetics of cisatracurium between elderly and young adult patients were not associated with clinically significant differences in the recovery profile of cisatracurium following a single 0.1 mg/kg dose.
Besides the differences noted above, no overall differences in safety or effectiveness were observed between geriatric and younger subjects, and other reported clinical experience has not identified differences in responses between geriatric and younger subjects, but greater sensitivity of some older individuals to cisatracurium cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage with neuromuscular blocking agents may result in neuromuscular blockade beyond the time needed for surgery and anesthesia. The primary treatment is maintenance of a patent airway and controlled ventilation until recovery of normal neuromuscular function is assured. Once recovery from neuromuscular block begins, further recovery may be facilitated by administration of a cholinesterase inhibitor (e.g., neostigmine, edrophonium) in conjunction with an appropriate cholinergic inhibitor.
Cholinesterase inhibitors should not be administered when complete neuromuscular blockade is evident or suspected because the reversal of paralysis may not be sufficient to maintain a patent airway and support an appropriate level of spontaneous ventilation. Neostigmine : Administration of 0.04 to 0.07 mg/kg of neostigmine at approximately 10% recovery from neuromuscular blockade (range: 0 to 15%) produced 95% recovery of the muscle twitch response and a T 4 :T 1 ratio ≥ 70% in an average of 9 to 10 minutes. The times from 25% recovery of the muscle twitch response to a T 4 :T 1 ratio ≥ 70% following these doses of neostigmine averaged 7 minutes.
The mean 25% to 75% recovery index following reversal was 3 to 4 minutes. Edrophonium : Administration of 1 mg/kg of edrophonium at approximately 25% recovery from neuromuscular blockade (range: 16% to 30%) produced 95% recovery and a T 4 :T 1 ratio ≥ 70% in an average of 3 to 5 minutes. For providers treating patients treated with cholinesterase inhibitors: Use a peripheral nerve stimulator to evaluate recovery and antagonism of neuromuscular blockade.
Evaluate for evidence of adequate clinical recovery (e.g., 5-second head lift and grip strength). Support ventilation until adequate spontaneous ventilation has resumed. The onset of antagonism may be delayed in the presence of debilitation, cachexia, carcinomatosis, and the concomitant use of certain broad spectrum antibiotics, or anesthetic agents and other drugs which enhance neuromuscular block or separately cause respiratory depression [see Drug Interactions (7.1) ] .
Under such circumstances the management is the same as that of prolonged neuromuscular block.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Cisatracurium binds competitively to cholinergic receptors on the motor end-plate to antagonize the action of acetylcholine, resulting in blockade of neuromuscular transmission. This action is antagonized by acetylcholinesterase inhibitors such as neostigmine.
12.2Pharmacodynamics The average ED 95 (dose required to produce 95% suppression of the adductor pollicis muscle twitch response to ulnar nerve stimulation) of cisatracurium is 0.05 mg/kg (range: 0.048 to 0.053) in adults receiving opioid/nitrous oxide/oxygen anesthesia. The pharmacodynamics of various cisatracurium doses administered over 5 to 10 seconds during opioid/nitrous oxide/oxygen anesthesia are summarized in Table 5. When the cisatracurium dose is doubled, the clinically effective duration of blockade increases by approximately 25 minutes.
Once recovery begins, the rate of recovery is independent of dose. Isoflurane or enflurane administered with nitrous oxide/oxygen to achieve
1.25MAC (Minimum Alveolar Concentration) prolonged the clinically effective duration of action of initial and maintenance cisatracurium doses, and decreased the average infusion rate requirement of cisatracurium. The magnitude of these effects depended on the duration of administration of the volatile agents: Fifteen to 30 minutes of exposure to
1.25MAC isoflurane or enflurane had minimal effects on the duration of action of initial doses of cisatracurium. In surgical procedures during enflurane or isoflurane anesthesia greater than 30 minutes, less frequent maintenance dosing, lower maintenance doses, or reduced infusion rates of cisatracurium were required. The average infusion rate requirement was decreased by as much as 30% to 40% [see Drug Interactions (7.1) ] .
The onset, duration of action, and recovery profiles of cisatracurium during propofol/oxygen or propofol/nitrous oxide/oxygen anesthesia were similar to those during opioid/nitrous oxide/oxygen anesthesia (see Table 5). Repeated administration of maintenance cisatracurium doses or a continuous cisatracurium infusion for up to 3 hours was not associated with development of tachyphylaxis or cumulative neuromuscular blocking effects. The time needed to recover from successive maintenance doses did not change with the number of doses administered when partial recovery occurred between doses.
The rate of spontaneous recovery of neuromuscular function after cisatracurium infusion was independent of the duration of infusion and comparable to the rate of recovery following initial doses (see Table 5). Pediatric patients including infants generally had a shorter time to maximum neuromuscular blockade and a faster recovery from neuromuscular blockade compared to adults treated with the same weight-based doses (see Table 5). Table 5.
Pharmacodynamic Dose Response* of Cisatracurium During Opioid/Nitrous Oxide/Oxygen Anesthesia Cisatracurium Dose Time to 90% Block in minutes Time to Maximum Block in minutes 5% Recovery in minutes 25% Recovery † in minutes 95% Recovery in minutes T 4 :T 1 Ratio ‡ ≥ 70% in minutes 25% to 75% Recovery Index in minutes * Values shown are the median values from the means from individual studies. Values in parentheses are ranges of individual patient values. † Clinically effective duration of block ‡ Train-of-four ratio § n = the number of patients with Time to Maximum Block data || Propofol anesthesia ¶ Halothane anesthesia ** Thiopentone, alfentanil, N 2 O/O 2 anesthesia Adults 0.1 mg/kg (2 × ED 95 ) (n § = 98) 3.3 (1.0 to 8.7) 5.0 (1.2 to 17.2) 33 (15 to 51) 42 (22 to 63) 64 (25 to 93) 64 (32 to 91) 13 (5 to 30) 0.15|| mg/kg (3 × ED 95 ) (n = 39) 2.6 (1.0 to 4.4) 3.5 (1.6 to 6.8) 46 (28 to 65) 55 (44 to 74) 76 (60 to 103) 75 (63 to 98) 13 (11 to 16) 0.2 mg/kg (4 × ED 95 ) (n = 30) 2.4 (1.5 to 4.5) 2.9 (1.9 to 5.2) 59 (31 to 103) 65 (43 to 103) 81 (53 to 114) 85 (55 to 114) 12 (2 to 30) 0.25 mg/kg (5 × ED 95 ) (n = 15) 1.6 (0.8 to 3.3) 2.0 (1.2 to 3.7) 70…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Cisatracurium binds competitively to cholinergic receptors on the motor end-plate to antagonize the action of acetylcholine, resulting in blockade of neuromuscular transmission. This action is antagonized by acetylcholinesterase inhibitors such as neostigmine.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Cisatracurium besylate injection, USP is a clear colorless to slightly yellow or greenish-yellow solution and is supplied as follows: 10 mg per 5 mL (2 mg/mL) 5 mL Single-Dose Vials in a carton of 10 NDC 55150-284-10 Does not contain benzyl alcohol. Discard unused portion of the 5 mL single-dose vials. 20 mg per 10 mL (2 mg/mL) 10 mL Multiple-Dose Vials in a carton of 10 NDC 55150-286-10 Contains 0.9% w/v benzyl alcohol [see Warnings and Precautions (5.2) ] Storage Refrigerate cisatracurium besylate injection, USP at 2°C to 8°C (36°F to 46°F) in the carton to preserve potency.
Protect from light. DO NOT FREEZE. Upon removal of the unused vial from refrigeration to room temperature storage conditions (25°C/77°F), use cisatracurium besylate injection, USP within 21 days even if re-refrigerated.
The vial stoppers are not made with natural rubber latex.
📋 Description ▾
11 DESCRIPTION Cisatracurium besylate injection, USP is a nondepolarizing skeletal neuromuscular blocker for intravenous administration. Compared to other neuromuscular blockers, it is intermediate in its onset and duration of action. Cisatracurium besylate injection, USP contains cisatracurium besylate as the active pharmaceutical ingredient.
Cisatracurium besylate is one of 10 isomers of atracurium besylate and constitutes approximately 15% of that mixture. Cisatracurium besylate is [1 R -[1α,2α(1' R *,2' R *)]]-2,2'-[1,5-pentanediylbis[oxy(3-oxo-3,1-propanediyl)]]bis[1-[(3,4-dimethoxyphenyl)methyl]-1,2,3,4-tetrahydro-6,7-dimethoxy-2-methylisoquinolinium] dibenzenesulfonate. The molecular formula of the cisatracurium parent bis-cation is C 53 H 72 N 2 O 12 and the molecular weight is 929.2.
The molecular formula of cisatracurium as the besylate salt is C 65 H 82 N 2 O 18 S 2 and the molecular weight is 1243.49. The structural formula of cisatracurium besylate is: The log of the partition coefficient of cisatracurium besylate is -2.12 in a 1-octanol/distilled water system at 25°C. Cisatracurium besylate injection, USP is a sterile, non-pyrogenic, clear colorless to slightly yellow or greenish-yellow solution.
Each mL in the single-dose vials contains 2 mg of cisatracurium (equivalent to 2.68 mg of cisatracurium besylate, USP), and benzenesulfonic acid as pH adjuster in water for injection. Each mL in the multiple-dose vials contains 2 mg of cisatracurium (equivalent to 2.68 mg of cisatracurium besylate, USP), benzenesulfonic acid as pH adjuster, and also contains 9 mg of benzyl alcohol as preservative, in water for injection. The pH of cisatracurium besylate injection, USP is between 3.0 and 3.8.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Including Anaphylaxis Advise the caregiver and/or family that severe hypersensitivity reactions have occurred with cisatracurium [see Warnings and Precautions (5.4) ] . Distributed by: Eugia US LLC 279 Princeton-Hightstown Rd. E. Windsor, NJ 08520 Manufactured by: Eugia Pharma Specialities Limited Hyderabad – 500032 India