
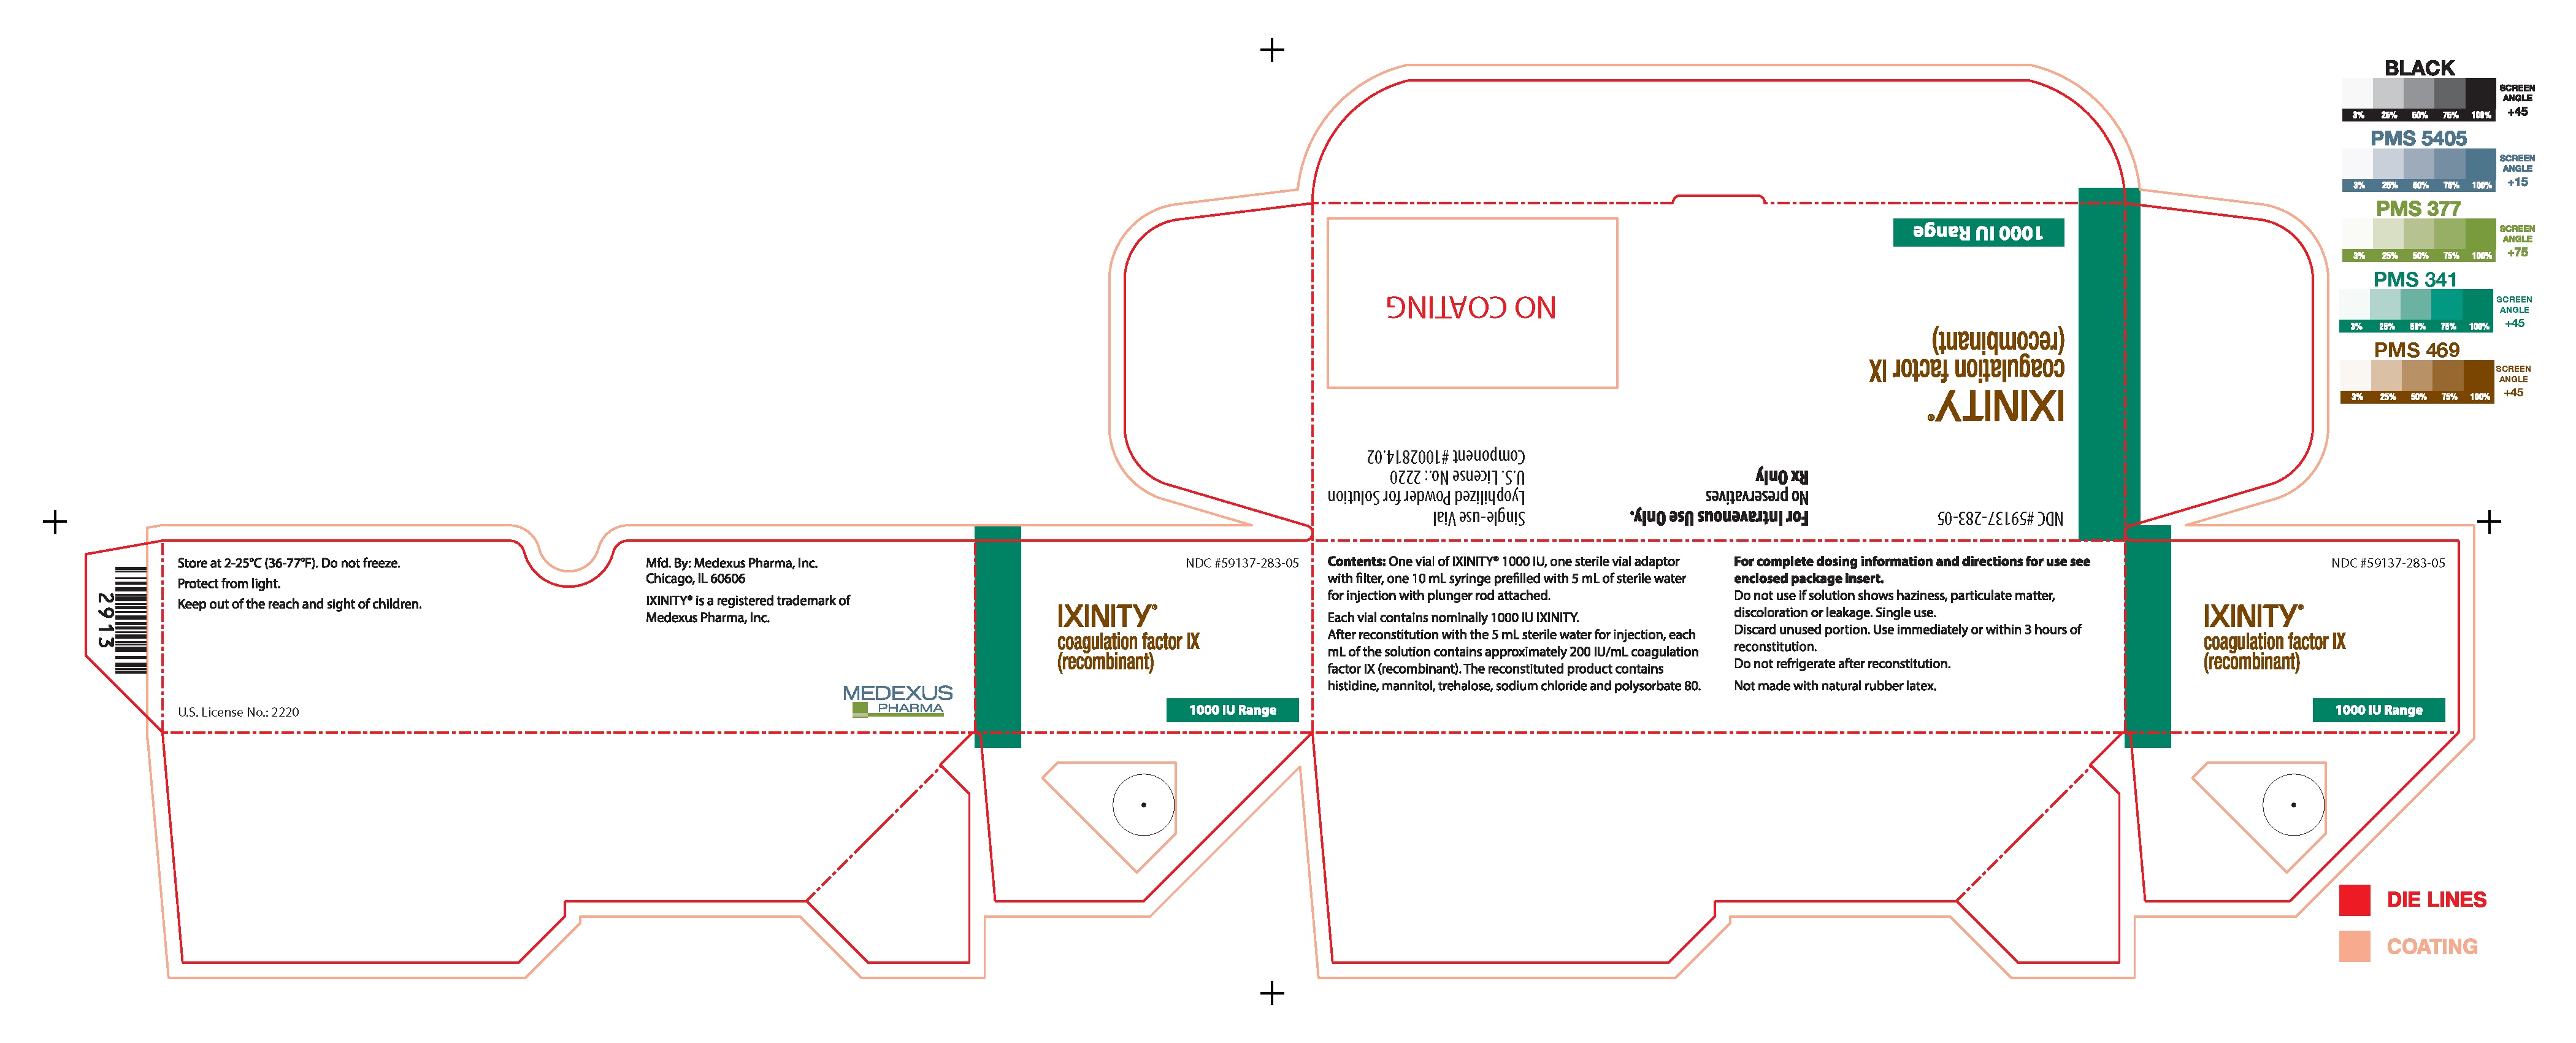
Ixinity coagulation factor IX (recombinant) Kit — NDC 59137-283-05 (Billing 59137-0283-05)
This is a package of Ixinity coagulation factor IX (recombinant) Kit from Medexus Pharma, Inc., marketed since May 2017 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 59137-283-05 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 59137 labeler · 283 product · 05 package
- Package marketed since
- Jul 1, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0059137275010, 0059137272019, 0059137271012, 0059137270015 +3 more
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 074100
- GCN: 38648
- GPI-14 (Medi-Span): 85100028202140
- HICL (First Databank): 042040
- AHFS class code: 20:28.16.00
- RxCUI (RxNorm): 1666311
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Human Blood Coagulation Factor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7213 | $1.939 / J7213 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 6, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59137-0283-05 You're viewing this Main listing | 1 KIT in 1 CARTON * 5 mL in 1 VIAL * 5 mL in 1 SYRINGE | 2021-07-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ixinity 59137-0282-05 | Medexus | 1 kit | — | — | FDA listed | — |
| Ixinitythis 59137-0283-05 | Medexus | 1 kit | — | — | FDA listed | — |
| Ixinity 59137-0284-05 | Medexus | 1 kit | — | — | FDA listed | — |
| Ixinity 59137-0289-05 | Medexus | 1 kit | — | — | FDA listed | — |
| BeneFIX 58394-0635-03 | Wyeth | 1 kit | — | — | FDA listed | — |
| Rixubis 00944-3034-02 | Takeda | 1 kit | — | — | FDA listed | — |
| Rixubis 00944-3030-02 | Takeda | 1 kit | — | — | FDA listed | — |
| BeneFIX 58394-0636-03 | Wyeth | 1 kit | — | — | FDA listed | — |
| Rixubis 00944-3032-02 | Takeda | 1 kit | — | — | FDA listed | — |
| BeneFIX 58394-0634-03 | Wyeth | 1 kit | — | — | FDA listed | — |
| Rixubis 00944-3026-02 | Takeda | 1 kit | — | — | FDA listed | — |
| Rixubis 00944-3028-02 | Takeda | 1 kit | — | — | FDA listed | — |
| BeneFIX 58394-0637-03 | Wyeth | 1 kit | — | — | FDA listed | — |
| BeneFIX 58394-0633-03 | Wyeth | 1 kit | — | — | FDA listed | — |
| Ixinity 59137-0287-05 | Medexus | 1 kit | — | — | Discontinued | — |
| Ixinity 59137-0288-05 | Medexus | 1 kit | — | — | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Apr 29, 2027 |
Is there a biosimilar for IXINITY 1,000 UNIT RANGE?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Medexus Pharma, Inc. labeler code 59137
- Gleolan Aminolevulinic Acid Hydrochloride 1500 mg Powder, For Solution NDC 59137-231-01
- Ixinity coagulation factor IX (recombinant) Kit NDC 59137-282-05
- Ixinity coagulation factor IX (recombinant) Kit NDC 59137-284-05
- Ixinity coagulation factor IX (recombinant) Kit NDC 59137-287-05
- Ixinity coagulation factor IX (recombinant) Kit NDC 59137-288-05
- Ixinity coagulation factor IX (recombinant) Kit NDC 59137-289-05
- Grafapex treosulfan 1000 mg/g Injection, Powder, Lyophilized, For Solution NDC 59137-335-01
- Grafapex treosulfan 5000 mg/5g Injection, Powder, Lyophilized, For Solution NDC 59137-365-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE IXINITY, Coagulation Factor IX (Recombinant), is a human blood coagulation factor indicated in adults and children with hemophilia B for: On-demand treatment and control of bleeding episodes Perioperative management Routine prophylaxis to reduce the frequency of bleeding episodes IXINITY is not indicated for induction of immune tolerance in patients with hemophilia B [see Warnings and Precautions ( 5.3 ) ]. IXINITY, Coagulation Factor IX (Recombinant), is a human blood coagulation factor indicated in adults and children with hemophilia B for: On-demand treatment and control of bleeding episodes ( 1 ) Perioperative management ( 1 ) Routine prophylaxis to reduce the frequency of bleeding episodes ( 1 ) IXINITY is not indicated for induction of immune tolerance in patients with hemophilia B.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For intravenous use after reconstitution only. For intravenous use after reconstitution only. On-demand treatment and control of bleeding episodes and perioperative management of bleeding: Adolescents/Adults (≥ 12 years of age): One international unit (IU) of IXINITY per kg body weight increases the circulating activity of factor IX by
0.98IU/dL. ( 2.1 ) Children (< 12 years of age): One international (IU) of IXINITY per kg body weight increases the circulating activity of factor IX by
0.79IU/dL. ( 2.1 ) Initial dose: Required factor IX units (IU) = body weight (kg) x desired factor IX increase (% of normal or IU/dL) x reciprocal of observed recovery (IU/kg per IU/dL). ( 2.1 ) The maintenance dose depends on the type of bleed or surgery, the intensity of the hemostatic challenge, and number of days until adequate wound healing is achieved.
( 2.1 ) Routine prophylaxis: Adolescents/Adults (≥ 12 years of age): 40 to 70 IU/kg twice weekly. ( 2.1 ) Children (< 12 years of age): 35 to 75 IU/kg twice weekly. Adjust the dosing regimen (dose or frequency) based on the patient’s clinical response.
( 2.1 )
2.1Dose Each vial of IXINITY has the recombinant factor IX (rFIX) potency in international units (IU) stated on the vial. Dosage and duration of treatment for factor IX products depend on the severity of the factor IX deficiency, the location and extent of bleeding, the patient’s clinical condition, age, and pharmacokinetic parameters of factor IX, such as incremental recovery and half-life. Initial Dose Adolescents/Adults ≥ 12 years of age): Calculate the initial dose of IXINITY based on the empirical finding that one international unit (IU) of IXINITY per kg body weight increases the circulating level of factor IX by 0.98 international units/dL (IU/dL) of plasma in adults and children ≥ 12 years of age.
Children (< 12 years of age): Calculate the initial dose of IXINITY based on the empirical finding that one international unit (IU) of IXINITY per kg body weight increases the circulating level of factor IX by 0.79 international units/dL (IU/dL) of plasma in children < 12 years of age. Initial Dose = body weight (kg) x desired factor IX increase (% of normal or IU/dL) × reciprocal of observed recovery (IU/kg per IU/dL) Incremental Recovery in Previously Treated Patients (PTPs) Base calculation of the dose on the patient’s individual incremental recovery using serial factor IX activity assays, to account for the wide range of inter-individual differences in incremental recovery and the type of aPTT reagent used for the assay.
Titrate the dose based on the patient’s clinical response and individual pharmacokinetics, in particular incremental recovery and half-life. Adolescents/Adults (≥ 12 years of age): For an incremental recovery of
0.98IU/dL per IU/kg (0.98% of normal), calculate the dose as follows: Dose (IU) = body weight (kg) x desired factor IX increase (% of normal or IU/dL) × 1.02 dL/kg Examples (assuming patient’s baseline factor IX level is < 1% of normal): A peak of 70% is required in a 60 kg patient. The appropriate dose would be (60 kg × 70 IU/dL)/(0.98 IU/dL per IU/kg) = 4286 IU A dose of 4550 international units (IUs) of IXINITY administered to a 70 kg patient should be expected to result in a peak post-infusion factor IX increase of 4550 IU x (0.98 IU/dL per IU/kg)/(70 kg) = 64 IU/dL (approximately 64% of normal) Children (< 12 years of age): A lower recovery has been observed in pediatric patients (< 12 years, n=20).
For an incremental recovery of
0.79IU/dL per IU/kg (0.79% of normal), calculate the dose as follows: Dose (IU) = body weight (kg) x desired factor IX increase (% of normal or IU/dL) × 1.27 dL/kg Examples (assuming patient’s baseline factor IX level is < 1% of normal): A peak of 60% is required in a 20 kg patient. The appropriate dose would be (20 kg x 60 IU/dL)/(0.79 IU/dL per IU/kg) = 1519 IU A dose of 500 international units (IUs) of IXINITY administered to a 7 kg patient… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS IXINITY is available as a lyophilized white or almost white powder, in single-dose glass vials containing nominally 250, 500, 1000, 1500, 2000, or 3000 IU per vial. IXINITY is available as a lyophilized white or almost white powder, in single-dose glass vials containing nominally 250, 500, 1000, 1500, 2000, or 3000 international units (IU) per vial (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS IXINITY is contraindicated in patients who have known hypersensitivity to IXINITY or its excipients, including hamster protein [see Warnings and Precautions (5.1) ]. Do not use in patients with known hypersensitivity to IXINITY or its excipients, including hamster protein ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity reactions, including anaphylaxis has occurred. Should symptoms occur, discontinue IXINITY and administer appropriate treatment. Patients may also develop hypersensitivity to hamster (CHO) protein, which is present in trace amounts in the product ( 5.1 ) Development of neutralizing antibodies (inhibitors) to IXINITY may occur.
If expected factor IX activity plasma levels are not attained, or if bleeding is not controlled with an appropriate dose, perform an assay that measures factor IX inhibitor concentration ( 5.2 ) Nephrotic syndrome has been reported following immune tolerance induction with factor IX products in hemophilia B patients with factor IX inhibitors ( 5.3 ) Thromboembolism has occurred with IXINITY use ( 5.4 )
5.1Hypersensitivity Reactions Hypersensitivity reactions, including anaphylaxis, has occurred with IXINITY. Signs of allergic reactions, which can progress to anaphylaxis, include urticaria, angioedema, chest or throat tightness, hypotension, lethargy, nausea, vomiting, dysphagia, paresthesia, restlessness, wheezing and dyspnea. Immediately discontinue administration and initiate appropriate treatment if allergic or anaphylactic-type reactions occur.
In case of severe allergic reactions, consider alternative hemostatic measures. There are literature reports of allergic reactions occurring in close temporal association with the development of factor IX inhibitors. IXINITY contains trace amounts of Chinese hamster ovary (CHO) proteins.
Patients treated with this product may develop hypersensitivity to CHO proteins.
5.2Neutralizing Antibodies Development of neutralizing antibodies (inhibitors) to IXINITY may occur. If expected factor IX activity plasma levels are not attained, or if bleeding is not controlled as expected with the calculated dose, perform an assay that measures factor IX inhibitor concentration [see Warnings and Precautions (5.5) ]. Patients with factor IX inhibitors are at an increased risk of severe hypersensitivity reactions or anaphylaxis if re-exposed to IXINITY.
5.3Nephrotic Syndrome Nephrotic syndrome may occur with IXINITY. Nephrotic syndrome has been reported following attempted immune tolerance induction in hemophilia B patients with factor IX inhibitors and a history of allergic reactions.
5.4Thromboembolism Thromboembolism has occurred with IXINITY use. One thrombotic event of deep vein thrombosis was reported in an adult female over 45 years of age from post-marketing experience. Because of the potential risk for thromboembolism with the use of factor IX products, monitor for early signs of thromboembolism and consumptive coagulopathy when administering IXINITY to patients with liver disease, fibrinolysis, peri-operative status, or risk for thromboembolic events or disseminated intravascular coagulation.
5.5Monitoring Laboratory Tests Monitor patients for factor IX activity levels with the one-stage clotting assay to confirm that adequate factor IX levels have been achieved and maintained, when clinically indicated. Factor IX results can be affected by the type of aPTT reagent used [see Dosage and Administration (2.1) ]. Monitor patients for the development of inhibitors if expected factor IX activity plasma levels are not attained, or if bleeding is not controlled with the recommended dose of IXINITY.
Assays used to determine if factor IX inhibitor is present should be titered in Bethesda Units (BUs).
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reaction (> 2%) reported in clinical trials was headache. The most common adverse reaction observed in > 2% of patients in clinical trials was headache ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Medexus Pharma, Inc. at 1-844-859-6675 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. A total of 15 adverse reactions were reported following IXINITY administration among 7 of the 98 subjects who received at least one dose of IXINITY in trials of previously treated patients (PTPs), which included 11 subjects 12 - 18 years of age and 21 subjects < 12 years of age.
A total of 12,952 infusions of IXINITY were administered to the 98 subjects. The adverse reactions that were assessed as probably or possibly related to study drug are provided in the table below. Table 3 Summary of Adverse Reactions MedDRA Standard System Organ Class Adverse Reaction Number of Events Number of Subjects (n = 98) (%) Congenital, familial and genetic disorders Hemophilia (i.e., lack of efficacy) 1 1 (1.0%) General disorders and administration site conditions Asthenia 1 1 (1.0%) Injection site discomfort 1 1 (1.0%) Immune System Disorders Hypersensitivity 1 1 (1.0%) Infections and infestations Influenza 1 1 (1.0%) Nervous system disorders Headache 5 2 (2.0%) Dysgeusia 1 1 (1.0%) Lethargy 1 1 (1.0%) Psychiatric disorders Apathy 1 1 (1.0%) Depression 1 1 (1.0%) Skin and subcutaneous tissue disorders Rash pruritic 1 1 (1.0%)
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of IXINITY. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Immune System Disorders: Anaphylaxis Vascular Disorders: Deep vein thrombosis The following class adverse reactions have been seen with another recombinant factor IX: inadequate factor IX recovery, inhibitor development, angioedema, hypotension, and thrombosis.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric Use: The safety and effectiveness of IXINITY have been established in pediatric patients. Lower recovery, shorter half-life, and higher clearance (based on kg body weight) have been observed in children (< 12 years). Dose adjustment may be needed. ( 8.4 , 12.3 )
8.1Pregnancy Risk Summary There are no data with IXINITY use in pregnant women to inform a drug-associated risk. Animal reproduction studies have not been conducted with IXINITY. In the U.S. general population, the estimated background risk of major birth defect and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
8.2Lactation Risk Summary There is no information regarding the presence of IXINITY in human milk, the effect on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for IXINITY and any potential adverse effects on the breastfed infant from IXINITY or from the underlying maternal condition.
8.4Pediatric Use The safety, efficacy, and pharmacokinetics of IXINITY have been evaluated in previously treated pediatric patients (PTP). Subjects received twice or once weekly prophylaxis treatment (four subjects were prescribed once a week treatment, 17 were prescribed twice a week treatment) with IXINITY for a mean of 158.7 exposure days [see Clinical Studies ( 14 ) ]. Compared to adolescents and adults (≥ 12 years old), children (< 12 years old) showed higher Factor IX body weight-adjusted clearance, shorter half-life, and lower recovery.
Adjustment in dose or dosing frequency may be needed [see Dosage and Administration ( 2.1 ) and Clinical Pharmacology ( 12.3 ) ]. There were no inhibitors detected [see Clinical Pharmacology ( 12.6 ) ]. One patient in the pediatric study had an adverse reaction of hypersensitivity resulting in withdrawal from the study.
No new safety concerns were identified in the pediatric trial [see Adverse Reactions ( 6.1 ) ].
8.5Geriatric Use Clinical studies of IXINITY did not include subjects aged 65 and over. It is not known whether elderly patients respond differently than younger patients. Individualize dose selection for elderly patients [see Dosage and Administration (2.1) ].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no data with IXINITY use in pregnant women to inform a drug-associated risk. Animal reproduction studies have not been conducted with IXINITY. In the U.S. general population, the estimated background risk of major birth defect and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety, efficacy, and pharmacokinetics of IXINITY have been evaluated in previously treated pediatric patients (PTP). Subjects received twice or once weekly prophylaxis treatment (four subjects were prescribed once a week treatment, 17 were prescribed twice a week treatment) with IXINITY for a mean of 158.7 exposure days [see Clinical Studies ( 14 ) ]. Compared to adolescents and adults (≥ 12 years old), children (< 12 years old) showed higher Factor IX body weight-adjusted clearance, shorter half-life, and lower recovery.
Adjustment in dose or dosing frequency may be needed [see Dosage and Administration ( 2.1 ) and Clinical Pharmacology ( 12.3 ) ]. There were no inhibitors detected [see Clinical Pharmacology ( 12.6 ) ]. One patient in the pediatric study had an adverse reaction of hypersensitivity resulting in withdrawal from the study.
No new safety concerns were identified in the pediatric trial [see Adverse Reactions ( 6.1 ) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of IXINITY did not include subjects aged 65 and over. It is not known whether elderly patients respond differently than younger patients. Individualize dose selection for elderly patients [see Dosage and Administration (2.1) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Hemophilia B is a sex-linked hereditary disorder of blood coagulation caused by a deficiency in factor IX and results in bleeding into joints, muscles or internal organs, either spontaneously or as a result of accidental or surgical trauma. Treatment with IXINITY replaces factor IX, thereby enabling a temporary correction of the factor deficiency and correction of the bleeding tendencies.
12.2Pharmacodynamics The administration of IXINITY increases plasma levels of factor IX and can temporarily correct the coagulation defect in these patients, as reflected by decrease in the aPTT.
12.3Pharmacokinetics PTPs ≥ 12 years of age Pharmacokinetic studies with IXINITY were conducted in 32 previously treated patients (PTPs) ≥ 12 years of age with severe to moderately severe hemophilia B (factor IX ≤ 2 IU/dL). Intravenous administration of 75 ± 5 IU/kg of IXINITY to 32 PTPs showed an initial recovery ranging from 51 to 113 IU/dL (median 70 IU/dL). The results of pharmacokinetic studies are summarized below in Table 4 .
Table 4 Pharmacokinetic Parameters for IXINITY PTPs ≥ 12 Years of Age (n = 32) Parameters Mean (± SD) (Range) AUC 0–∞ (IU/dL/hr) 1573 (± 451) (862-2643) Incremental Recovery (IU/dL per IU/kg) 0.98 (± 0.21) (0.67-1.50) Terminal Half-life (hours) 24 (± 7) (13-43) C max (IU/dL) 73 (± 17) (51-113) Mean Residence Time (hours) 32 (± 6) (19-47) VD ss (mL/kg) 175 (± 57) (102-314) Clearance [mL/(kg·hr)] 5.1 (± 1.3) (2.8-7.7) Pharmacokinetic parameters were re-assessed in a subset of 14 subjects after routine treatment with IXINITY for a median of 5.8 months (range 3.1 to 18.6 months) as summarized in Table 5 below.
Table 5 Pharmacokinetic Parameters for IXINITY Following Repeat-Dosing PTPs ≥ 12 Years of Age (n = 14) Parameters Initial Mean (± SD) Repeat-Dosing PK Mean (± SD) AUC 0–∞ (IU/dL/hr) 1438 (± 409) 1530 (± 435) Incremental Recovery (IU/dL per IU/kg) 0.96 (± 0.22) 0.95 (± 0.18) Terminal Half-life (hours) 24 (± 7) 24 (± 6) C max (IU/dL) 73 (± 16) 73 (± 15) Mean Residence Time (hours) 30 (± 6) 31 (± 5) VD ss (mL/kg) 193 (± 62) 185 (± 70) Clearance [mL/(kg·hr)] 5.6 ± (1.3) 5.3 (± 1.5) Repeat dosing did not impact the pharmacokinetics of IXINITY.
The PK data were divided into two subgroups of subjects with a BMI ≤ 30 (n = 26) or BMI > 30 (n = 6). The AUC (0-∞) and C max values of IXINITY were 40% and 34% higher, respectively, in subjects with BMI > 30. PTPs <12 years of age Pharmacokinetics were evaluated in 20 previously treated patients (PTPs) < 12 years of age with severe to moderately severe hemophilia B (factor IX ≤ 2 IU/dL).
Following a single intravenous administration of 75 ± 5 IU/kg of IXINITY, an initial recovery ranged from 44 to 109 IU/dL (median 77 IU/dL). Pediatric patients < 12 years of age showed higher clearance, shorter half-life, and lower incremental recovery compared to adults and adolescents (≥ 12 years old). The results of pharmacokinetic studies are summarized below in Table 6 .
Table 6 Pharmacokinetic Parameters for PTPs <12 Years of Age Following 75 ± 5 IU/kg of IXINITY (n=20) a n=6 for t1/2, AUC 0-∞ , MRT, CL, and Vd ss b n=6 for t1/2 and n=5 for AUC 0-∞ , MRT, CL, and Vd ss c n=12 for t1/2 and n=11 for AUC 0-∞ , MRT, CL, and Vd ss Parameters < 6 years N=10 a Mean (± SD) 6 to < 12 years N=10 b Mean (± SD) All subjects < 12 years N=20 c Mean (± SD) AUC 0–∞ (IU/dL/hr) 1118 (± 307) 1232 (± 81.7) 1170 (± 231) Incremental Recovery (IU/dL per IU/kg) 0.73 (± 0.15) 0.85 (± 0.15) 0.79 (± 0.16) Terminal Half-life (hours) 15.9 (± 1.4) 16.8 (± 2.8) 16.3 (± 2.2) C max (IU/dL) 56.4 (± 13.7) 63.7 (± 9.86) 60.1 (± 12.2) Mean Residence Time (hours) 19.9 (± 2.48) 20.0 (± 2.87) 20.0 (± 2.53) VD ss (mL/kg) 144 (± 36.7) 123 (± 18.9) 134 (± 30.6) Clearance [mL/(kg·hr)] 7.3 (± 1.9) 6.1 (± 0.5) 6.8 (± 1.5)
12.6Immunogenicity The observed incidence of anti-drug antibodies is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods precl… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Hemophilia B is a sex-linked hereditary disorder of blood coagulation caused by a deficiency in factor IX and results in bleeding into joints, muscles or internal organs, either spontaneously or as a result of accidental or surgical trauma. Treatment with IXINITY replaces factor IX, thereby enabling a temporary correction of the factor deficiency and correction of the bleeding tendencies.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING IXINITY is supplied as a lyophilized powder in single-dose glass vials containing the labeled amount of factor IX activity, expressed in international units (IU). The actual factor IX activity in IU is stated on the label of each vial. Kits include one single-dose vial (containing nominally 250, 500, 1000, 1500, 2000, or 3000 IU per vial), a 10 mL syringe pre-filled with 5 mL of Sterile Water for Injection with plunger rod attached, and a vial adapter with filter.
None of the kit components are made with natural rubber latex. Color Code Nominal Strength Kit NDC Number Yellow 250 IU 59137-287-05 Blue 500 IU 59137-282-05 Green 1000 IU 59137-283-05 Orange 1500 IU 59137-284-05 Red 2000 IU 59137-288-05 Brown 3000 IU 59137-289-05 250 IU strength only; store at 2 to 8°C (36 to 46°F). 500, 1000, 1500, 2000, and 3000 IU strengths: store at 2 to 25°C (36 to 77°F).
Do not freeze. Keep the vial in the carton and protect from light. Infuse reconstituted solution immediately or within 3 hours of storage at room temperature after reconstitution.
Do not refrigerate after reconstitution.
📋 Description ▾
11 DESCRIPTION IXINITY [coagulation factor IX (recombinant)] is a purified protein that has 415 amino acids. It has an amino acid sequence that is comparable to the Thr148 allelic form of plasma-derived factor IX. Coagulation factor IX (recombinant) is a single-chain glycoprotein with a molecular mass of about 55,000 Dalton that is secreted by a genetically engineered mammalian cell line derived from Chinese hamster ovary (CHO) cells.
No human or animal proteins are added during any stage of manufacturing or formulation of IXINITY. The CHO cell line secretes recombinant factor IX into a defined cell culture medium that does not contain hormones. The recombinant factor IX is purified by a chromatography purification process.
The process includes three validated steps for virus inactivation and removal, namely, solvent/detergent treatment, a chromatographic step, and nanofiltration. The process also includes a validated step to reduce the presence of CHO proteins in the final drug product. IXINITY is formulated as a sterile, nonpyrogenic lyophilized powder to be reconstituted with Sterile Water for Injection for intravenous administration.
It does not contain any preservatives and is available in single-dose vials containing the labeled amount of factor IX activity, expressed in international units (IU). Each vial contains nominally 250, 500, 1000, 1500, 2000, or 3000 IU of recombinant coagulation factor IX. After reconstitution of the lyophilized powder, all dosage strengths yield a clear, colorless solution.
The concentrations of excipients are: Excipient Concentration Histidine 10 mM Mannitol 3% Trehalose Dihydrate 1% Sodium Chloride 66 mM Polysorbate 80 0.0075%
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling ( Patient Information and Instructions for Use ). Inform patients of the early signs of hypersensitivity reactions (including hives, generalized urticaria, chest tightness, wheezing, and hypotension) and anaphylaxis. Instruct patients to discontinue use of the product and contact their physician if these symptoms occur.
Advise patients to contact their physician or treatment facility for further treatment and/or assessment if they experience a lack of clinical response to factor IX replacement therapy, as in some cases this may be a manifestation of an inhibitor. Manufactured by: Medexus Pharma, Inc. Chicago, IL 60606 U.S.
License No. 2220
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics PTPs ≥ 12 years of age Pharmacokinetic studies with IXINITY were conducted in 32 previously treated patients (PTPs) ≥ 12 years of age with severe to moderately severe hemophilia B (factor IX ≤ 2 IU/dL). Intravenous administration of 75 ± 5 IU/kg of IXINITY to 32 PTPs showed an initial recovery ranging from 51 to 113 IU/dL (median 70 IU/dL). The results of pharmacokinetic studies are summarized below in Table 4 .
Table 4 Pharmacokinetic Parameters for IXINITY PTPs ≥ 12 Years of Age (n = 32) Parameters Mean (± SD) (Range) AUC 0–∞ (IU/dL/hr) 1573 (± 451) (862-2643) Incremental Recovery (IU/dL per IU/kg) 0.98 (± 0.21) (0.67-1.50) Terminal Half-life (hours) 24 (± 7) (13-43) C max (IU/dL) 73 (± 17) (51-113) Mean Residence Time (hours) 32 (± 6) (19-47) VD ss (mL/kg) 175 (± 57) (102-314) Clearance [mL/(kg·hr)] 5.1 (± 1.3) (2.8-7.7) Pharmacokinetic parameters were re-assessed in a subset of 14 subjects after routine treatment with IXINITY for a median of 5.8 months (range 3.1 to 18.6 months) as summarized in Table 5 below.
Table 5 Pharmacokinetic Parameters for IXINITY Following Repeat-Dosing PTPs ≥ 12 Years of Age (n = 14) Parameters Initial Mean (± SD) Repeat-Dosing PK Mean (± SD) AUC 0–∞ (IU/dL/hr) 1438 (± 409) 1530 (± 435) Incremental Recovery (IU/dL per IU/kg) 0.96 (± 0.22) 0.95 (± 0.18) Terminal Half-life (hours) 24 (± 7) 24 (± 6) C max (IU/dL) 73 (± 16) 73 (± 15) Mean Residence Time (hours) 30 (± 6) 31 (± 5) VD ss (mL/kg) 193 (± 62) 185 (± 70) Clearance [mL/(kg·hr)] 5.6 ± (1.3) 5.3 (± 1.5) Repeat dosing did not impact the pharmacokinetics of IXINITY.
The PK data were divided into two subgroups of subjects with a BMI ≤ 30 (n = 26) or BMI > 30 (n = 6). The AUC (0-∞) and C max values of IXINITY were 40% and 34% higher, respectively, in subjects with BMI > 30. PTPs <12 years of age Pharmacokinetics were evaluated in 20 previously treated patients (PTPs) < 12 years of age with severe to moderately severe hemophilia B (factor IX ≤ 2 IU/dL).
Following a single intravenous administration of 75 ± 5 IU/kg of IXINITY, an initial recovery ranged from 44 to 109 IU/dL (median 77 IU/dL). Pediatric patients < 12 years of age showed higher clearance, shorter half-life, and lower incremental recovery compared to adults and adolescents (≥ 12 years old). The results of pharmacokinetic studies are summarized below in Table 6 .
Table 6 Pharmacokinetic Parameters for PTPs <12 Years of Age Following 75 ± 5 IU/kg of IXINITY (n=20) a n=6 for t1/2, AUC 0-∞ , MRT, CL, and Vd ss b n=6 for t1/2 and n=5 for AUC 0-∞ , MRT, CL, and Vd ss c n=12 for t1/2 and n=11 for AUC 0-∞ , MRT, CL, and Vd ss Parameters < 6 years N=10 a Mean (± SD) 6 to < 12 years N=10 b Mean (± SD) All subjects < 12 years N=20 c Mean (± SD) AUC 0–∞ (IU/dL/hr) 1118 (± 307) 1232 (± 81.7) 1170 (± 231) Incremental Recovery (IU/dL per IU/kg) 0.73 (± 0.15) 0.85 (± 0.15) 0.79 (± 0.16) Terminal Half-life (hours) 15.9 (± 1.4) 16.8 (± 2.8) 16.3 (± 2.2) C max (IU/dL) 56.4 (± 13.7) 63.7 (± 9.86) 60.1 (± 12.2) Mean Residence Time (hours) 19.9 (± 2.48) 20.0 (± 2.87) 20.0 (± 2.53) VD ss (mL/kg) 144 (± 36.7) 123 (± 18.9) 134 (± 30.6) Clearance [mL/(kg·hr)] 7.3 (± 1.9) 6.1 (± 0.5) 6.8 (± 1.5)
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The administration of IXINITY increases plasma levels of factor IX and can temporarily correct the coagulation defect in these patients, as reflected by decrease in the aPTT.
12.6Immunogenicity The observed incidence of anti-drug antibodies is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of anti-drug antibodies in the studies described below with the incidence of anti-drug antibodies in other studies, including those of IXINITY or of other factor IX products. Routine Prophylaxis PTPs ≥ 12 years of age All subjects participating in the clinical trial were monitored for inhibitory and non-inhibitory antibodies to factor IX and antibodies for CHO cell proteins (CHOP) at the following time points; pre-infusion, after the first five exposure days, and then every three months thereafter.
No subjects developed inhibitors to factor IX, including 55 subjects with more than 50 exposure days and 45 of those subjects with more than 100 exposure days. Non-inhibitory factor IX binding antibodies were detected in 30% (23/77) of subjects, including five subjects positive at baseline. In three of the subjects, the non-inhibitory factor IX antibodies were persistent, while in the remainder the antibodies were sporadic and non-persistent.
Antibodies against CHOP were observed in 29% (20/68) of subjects. The manufacturing process for IXINITY was modified to include an additional step to ensure increased clearance of CHOP to address the anti-CHOP response seen in clinical trials. Subjects who transitioned to the modified IXINITY for at least three months (n = 17), anti-CHOP antibodies remained negative (n = 10), stable/nonspecific assay binding (n = 5) or declined (n = 2) after the transition.
PTPs <12 years of age All subjects participating in the clinical trial were monitored for inhibitory and non-inhibitory antibodies to factor IX and antibodies for CHOP at the following time points; at screening, pre-infusion, then at exposure day 5, 12, 25, 50, 75, 100, and then every three months thereafter. No subjects developed inhibitors to factor IX, including 19 subjects with more than 50 exposure days and 16 of those subjects with more than 100 exposure days. Non-inhibitory factor IX binding antibodies were detected in 14% (3/21) of subjects, including two subjects positive at baseline; in one subject, the non-inhibitory factor IX antibodies were persistent.
Anti-CHOP antibodies were detected in 14% (3/21) of subjects; in one subject, the anti-CHOP antibodies were persistent. There was no correlation between the three subjects who developed non-inhibitory anti-factor IX antibodies and the three subjects who tested positive for anti-CHOP antibodies. Effects of non-inhibitory anti-factor IX antibodies and anti-CHOP antibodies Detection of non-inhibitory anti-factor IX antibodies or anti-CHOP antibodies has been reported following administration of other factor IX products or other recombinant coagulation factor products produced in CHO cells.
No adverse events were associated with non-inhibitory anti-factor IX antibodies or anti-CHOP antibodies. However, the effect of these antibodies on the pharmacokinetics and effectiveness of IXINITY is unknown.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Routine Prophylaxis PTPs ≥ 12 years of age The efficacy of IXINITY was evaluated in a prospective, open-label, uncontrolled multicenter study in which a total of 77 subjects (76 male, 1 female carrier in surgery study) were exposed to IXINITY for treatment of hemophilia B or for perioperative management. All male subjects either had severe or moderately severe (factor IX level ≤ 2 IU/dL) hemophilia B, or had factor IX levels between 2-8 IU/dL and clinically severe hemophilia B with recurrent hemarthroses and required surgery (n = 3 in surgery study, one continued to treatment phase).
Previously treated patients (PTPs) were defined as patients with a minimum of 150 exposures to another factor IX preparation. Of the 77 subjects, 68 PTPs between 7 and 64 years of age received IXINITY either as routine prophylaxis or on-demand treatment. Routine prophylaxis treatment was defined as PTPs who received a starting dose of 40-70 international units (IU) per kg twice weekly.
Excluded from the study were patients with a history of a detectable factor IX inhibitor (≥
0.6BU), a history of hypersensitivity reactions following exposure to factor IX-containing products, a known allergic reaction to hamster proteins, evidence of severe liver impairment, evidence of impaired renal function, CD4 count < 400 cells/mm 3 , or any coagulation defect other than hemophilia B. In addition, there was a prospective, open-label, uncontrolled, multicenter substudy where 17 subjects (16 male, 1 female carrier) underwent surgeries (19 major procedures in males) receiving IXINITY for perioperative management; some of the surgery subjects also participated in the treatment trial.
Of the 68 PTPs in the treatment group, subjects were primarily prescribed a routine prophylaxis (n = 58) or an on-demand regimen (n = 9); one subject was not assigned a regimen. Subjects were allowed to switch regimens during the course of the study. As a result, 61 subjects were treated at some point with routine prophylaxis treatment and 12 were treated at some point with an on-demand regimen.
Subjects in the routine prophylaxis therapy group received mean intravenous doses of 55 ±
12.8IU/kg of IXINITY twice weekly. Subjects in the on-demand therapy group received mean doses of 60 ±
18.2IU/kg (median 59.3, interquartile range 49.9, 71.8) for bleeding episodes. The mean number of exposure days (ED) was 138.2 (median 127.5), including 45 subjects with ≥ 100 ED and 55 subjects with ≥ 50 ED. Median duration on study for the on-demand group was 14.1 months (range 2.3-36.9).
Annualized bleeding rates for PTPs ≥12 years of age in prophylaxis arm are summarized in Table 7 . Table 7: Efficacy of Prophylaxis with IXINITY (N=61) for subjects ≥ 12 years of age a The lower quartile, or first quartile (Q1) is the value under which 25% of data points are found when arranged in increasing order. The upper quartile, or third quartile (Q3), is the value under which 75% of data points are found when arranged in increasing order.
Total ABR Mean ± SD 3.55 ±
7.19Median (Q1, Q3) a 1.52 (0;3.47) Spontaneous ABR Mean ± SD 1.07±
3.06Median (Q1, Q3) a 0.00 (0;1.22) Subjects with zero bleeding episodes n (%) 19 (31.1%) PTP < 12 years of age The PK, safety and efficacy of IXINITY for treatment of hemophilia B was evaluated in a prospective multi-center, multi-country study of 21 previously treated patients (PTPs) (10 subjects < 6 years of age and 11 subjects 6 to < 12 years of age). PTP were defined as patients who were exposed to a factor IX containing product for ≥ 50 exposure days (ED). All subjects had severe to moderately severe (factor ≤ 2%).
Subjects with history of hypersensitivity reactions following exposure to factor IX-containing products, a known allergic reaction to hamster proteins, evidence of severe liver impairment, evidence of impaired renal function, CD4 count < 400 cells/mm 3 , or any coagulation defect other than hemophilia B, evidence of thrombotic disease, fibrin… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No macroscopic or microscopic pathologies in reproductive organs were observed in repeated dose toxicity studies of IXINITY in animals. Animal studies regarding impairment of fertility were not conducted. No nonclinical investigations of genotoxicity, carcinogenicity, or toxicity to reproduction and development have been conducted with IXINITY.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No macroscopic or microscopic pathologies in reproductive organs were observed in repeated dose toxicity studies of IXINITY in animals. Animal studies regarding impairment of fertility were not conducted. No nonclinical investigations of genotoxicity, carcinogenicity, or toxicity to reproduction and development have been conducted with IXINITY.
📚 References ▾
15 REFERENCES Srivastava A, et al. World Federation of Hemophilia, Guidelines for the management of hemophilia. Haemophilia. 2013; 19(1):e1–e47. Ingerslev J, Christiansen K, Ravn HB, et al. Antibodies to heterologous proteins in hemophilia A patients receiving recombinant factor VIII (Recombinate™). Thromb Haemost. 2002; 87:626–634.
📄 Patient Package Insert ▾
Patient Information IXINITY ® [coagulation factor IX (recombinant)] This leaflet summarizes important information about IXINITY. Please read it carefully before using this medicine. This information does not take the place of talking with your healthcare provider, and it does not include all of the important information about IXINITY.
If you have any questions after reading this, ask your healthcare provider. What is IXINITY? IXINITY is a medicine used to replace clotting factor (factor IX) that is missing in people with hemophilia B.
Hemophilia B is also called congenital factor IX deficiency or Christmas disease. Hemophilia B is an inherited bleeding disorder that prevents clotting. Your healthcare provider may give you IXINITY when you have surgery.
Who should not use IXINITY? You should not use IXINITY if you: Are allergic to hamsters Are allergic to any ingredients in IXINITY Tell your healthcare provider if you are pregnant or breastfeeding because IXINITY may not be right for you. What should I tell my healthcare provider before using IXINITY?
You should tell your healthcare provider if you: Have or have had any medical problems Take any medicines, including prescription and non-prescription medicines, such as over-the-counter medicines, supplements, or herbal remedies Have any allergies, including allergies to hamsters Are breastfeeding. It is not known if IXINITY passes into your milk and if it can harm your baby Are pregnant or planning to become pregnant. It is not known if IXINITY may harm your baby Have been told that you have inhibitors to factor IX (because IXINITY may not work for you) How should I infuse IXINITY?
IXINITY is given directly into the bloodstream. IXINITY should be administered as ordered by your healthcare provider. You should be trained on how to do infusions by your healthcare provider or hemophilia treatment center.
Many people with hemophilia B learn to infuse their IXINITY by themselves or with the help of a family member. See the step-by-step guide ( Instructions for Use ) provided at the end of this leaflet. Your healthcare provider will tell you how much IXINITY to use based on your weight, the severity of you hemophilia B, and where you are bleeding.
You may have to have blood tests done after getting IXINITY to be sure that your blood level of factor IX is high enough to stop the bleeding. Call you healthcare provider right away if your bleeding does not stop after taking IXINITY. What are the possible side effects of IXINITY?
Allergic reactions may occur with IXINITY. Call your healthcare provider or get emergency treatment right away if you get any of the following symptoms: rash, hives, itching, tightness of the throat, chest pain or tightness, difficulty breathing, light-headedness, dizziness, nausea, or fainting. Tell your healthcare provider about any side effect that bothers you or does not go away.
The most common side effect of IXINITY in clinical trials was headache. These are not all the side effects possible with IXINITY. You can ask your healthcare provider for information that is written for healthcare professionals.
Call your healthcare provider for medical advice about side effects. You may report side effects to the FDA at 1-800-FDA-1088. What are the IXINITY dosage strengths?
IXINITY comes in vials containing six different dosage strengths: 250, 500, 1000, 1500, 2000 and 3000 international units (IU). The actual strength will be printed on the label of the vial and on the box. The six different strengths in the vials are color coded as follows: Color Code Nominal Strength Yellow 250 IU Blue 500 IU Green 1000 IU Orange 1500 IU Red 2000 IU Brown 3000 IU Always check the actual dosage strength printed on the label to make sure you are using the strength prescribed by your healthcare provider.
How should I store IXINITY? 250 IU strength only; store at 2 to 8°C (36 to 46°F). Do not freeze.
500, 1000, 1500, 2000, and 3000 IU strengths; store at 2 to 25°C (36 to 77°F). Do not… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use IXINITY [coagulation factor IX (recombinant)] For intravenous use after reconstitution only Do not attempt to do an infusion to yourself unless you have been taught how by your healthcare provider or hemophilia center. Always follow the specific instructions given by your healthcare provider. The steps listed below are general guidelines for using IXINITY.
If you are unsure of the procedures, please call your healthcare provider before using IXINITY. Your healthcare provider will prescribe the dose that you should take. Before starting reconstitution and administration you will need the following items that are included in each kit of IXINITY: One (or more) vial(s) of IXINITY 250, 500, 1000, 1500, 2000, or 3000 IU powder, as prescribed by your healthcare provider One (or more) 10 mL syringe(s), pre-filled with 5 mL of Sterile Water for Injection (pre-filled syringe) with plunger rod attached Sterile vial adapter with filter In addition, you will need the following items that are not included in the kit: One sterile LUER-LOK syringe (administration syringe); additional or larger syringes may be required if pooling multiple vials Sterile alcohol swabs Sterile infusion set Sterile gauze pad Sterile bandage IXINITY is supplied in kits that include single-dose vials which contain vials of IXINITY (250, 500, 1000, 1500, 2000, or 3000 IU of powder), a 10 mL syringe pre-filled with 5 mL of Sterile Water for Injection with plunger rod attached (to be used for reconstitution only), and a sterile vial adapter with filter.
RECONSTITUTION INSTRUCTIONS Wash your hands and then clean a flat area before starting the steps for reconstituting IXINITY. Use an aseptic technique during reconstitution. 1.
Remove the pre-filled syringe and IXINITY vial from storage and allow them to reach room temperature before use. Check the expiration date on the IXINITY vial. 2.
Remove the plastic cap from the IXINITY vial and place the vial top up on the clean surface. You will see a rubber circle on the top of the vial. 3.
Wipe the top of the IXINITY vial with a sterile alcohol swab and allow it to dry. After cleaning, do not touch the rubber circle with your hands or allow it to touch another object. 4.
Peel back the paper cover of the vial adapter package. Be careful not to touch the LUER-LOK (tip) in the center of the vial adapter. Do not remove the adapter from the package.
5. Leave the vial adapter in the package and place it open end up on the clean surface with the LUER-LOK pointing up. 6.
Twist off the tip cap counterclockwise from the pre-filled syringe. Do not touch the inside of the cap or the syringe tip. 7.
While firmly holding the package containing the adapter with one hand and the barrel of the pre-filled syringe with the other, connect the pre-filled syringe to the vial adapter by pushing the syringe tip down onto the LUER-LOK in the center of the vial adapter, turning clockwise until the syringe is secured. 8. Carefully lift up the combined syringe-and-vial-adapter and remove it from the plastic package and discard packaging.
9. With one hand, continue to hold the combined syringe-and-vial-adapter. With the other hand, hold the IXINITY vial tightly on the clean, flat surface.
Do not touch the top of the IXINITY vial or the filter spike of the combined syringe and vial adapter. 10. Place the vial adapter over the IXINITY vial on the table; firmly push the filter spike of the vial adapter through the center of the IXINITY vial rubber circle until the clear plastic cap snaps onto the IXINITY vial.
11. Slowly push the plunger rod down to transfer all of the liquid from the syringe into the IXINITY vial. With the syringe and the vial still attached, gently swirl, in a circular motion, the IXINITY vial until the product is fully dissolved.
IXINITY is a clear, colorless solution without visible particles. Inspect the final solution for specks before administration. Do not use contents of vial if specks or particles persist after… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 03/2024 Dosage and Administration ( 2.1 ) 03/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - NDC: 59137-275-01 - 250 IU Single-Use Vial Label 250 IU Single-Use Vial Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-287-05 - 250 IU Kit Carton 250 IU Kit Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-270-01 - 500 IU Single-Use Vial Label 500 IU Single-Use Vial Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-282-05 - 500 IU Kit Carton 500 IU Kit Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-271-01 - 1000 IU Single-Use Vial Label 1000 IU Single-Use Vial Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-283-05 - 1000 IU Kit Carton 1000 IU Kit Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-272-01 - 1500 IU Single-Use Vial Label 1500 IU Single-Use Vial Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-284-05 - 1500 IU Kit Carton 1500 IU Kit Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-276-01 - 2000 IU Single-Use Vial Label 2000 IU Single-Use Vial Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-288-05 - 2000 IU Kit Carton 2000 IU Kit Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-277-01 - 3000 IU Single-Use Vial Label 3000 IU Single-Use Vial Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-289-05 - 3000 IU Kit Carton 3000 IU Kit Label
PRINCIPAL DISPLAY PANEL - NDC: 59137-280-01 - Water for Injection 5 mL Single-Use Syringe Label Water for Injection 5 mL Single-Use Syringe Label
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |