
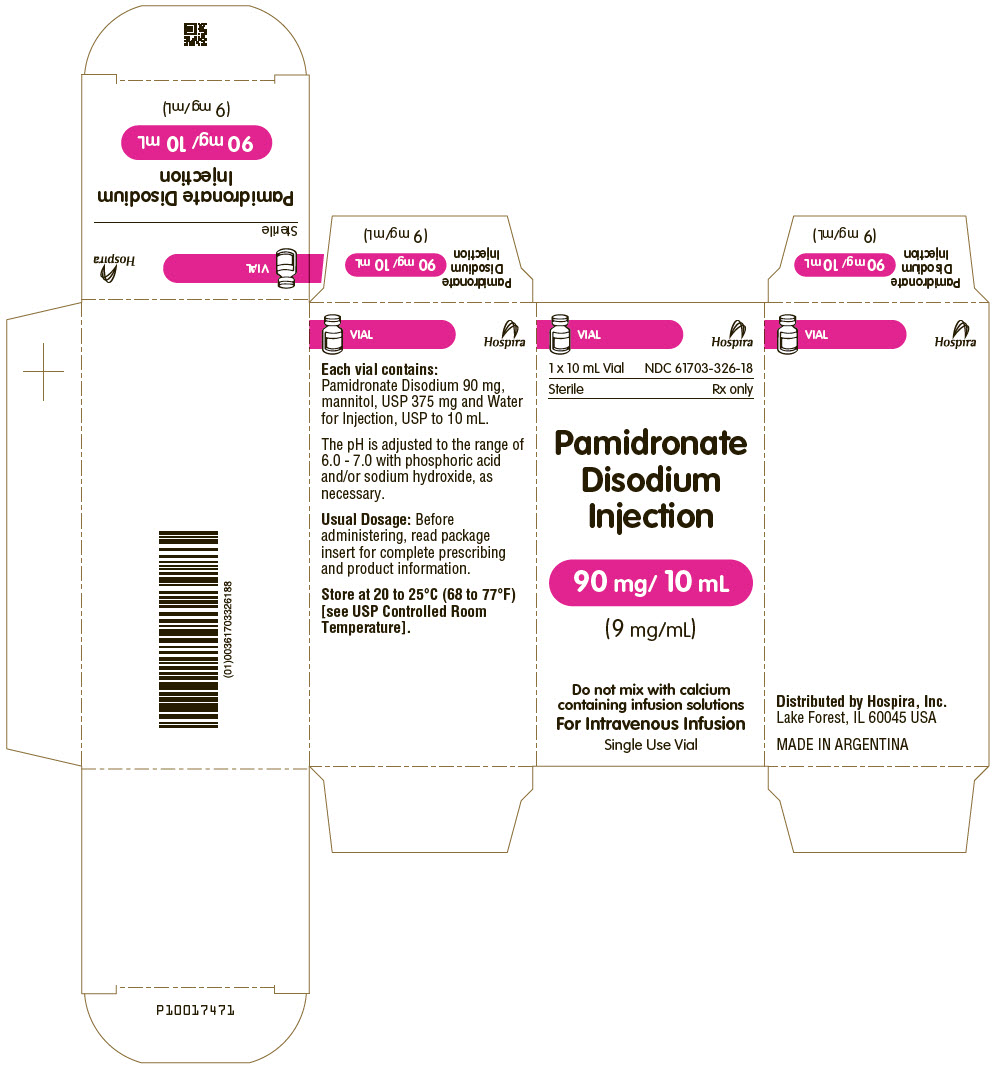
Pamidronate Disodium 9 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Bisphosphonate class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Pamidronate is used to treat high levels of calcium in the blood that may be caused by certain types of cancer. Pamidronate is also used along with cancer chemotherapy to treat bone damage caused by multiple myeloma (cancer that begins in the plasma cells [a type of white blood cell that produces substances needed to fight infection]) or by breast cancer that has spread to the bones. Pamidronate is also used to treat Paget's disease (a condition in which the bones are soft and weak and may be deformed, painful, or easily broken). Pamidronate injection is in a class of medications called bispho...
Read the full MedlinePlus article ↗- Pamidronate is used for conditions where bones are breaking down too fast. Depending on what your doctor has prescribed it for, it could be treating dangerously high calcium in you...
- What exactly is pamidronate being used for in my case?
- Pamidronate is given through an IV line in a clinic or hospital — you can't take it as a pill. Each infusion takes at least 2 hours, and sometimes longer. The slower pace is intent...
- How is this medication given, and how long does each infusion take?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
37.5 mg / 1 mL
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII E4GA8884NN
Phosphoric acid is a weak mineral acid used in medicines as a buffer and pH adjuster. It helps stabilize the product and control its acidity level.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2430 | $12.025 / J2430 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Pamidronate Disodium 9 mg/mLthis 61703-0326-18 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Pamidronate Disodium 9 mg/mL 67457-0446-10 | Mylan | 1 vial | — | AP2 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 61703-0326-18 You're viewing this | 1 VIAL, SINGLE-DOSE in 1 CARTON (61703-326-18) / 10 mL in 1 VIAL, SINGLE-DOSE | 2005-10-01 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypercalcemia of Malignancy Pamidronate disodium, in conjunction with adequate hydration, is indicated for the treatment of moderate or severe hypercalcemia associated with malignancy, with or without bone metastases. Patients who have either epidermoid or non-epidermoid tumors respond to treatment with pamidronate disodium. Vigorous saline hydration, an integral part of hypercalcemia therapy, should be initiated promptly and an attempt should be made to restore the urine output to about 2 L/day throughout treatment.
Mild or asymptomatic hypercalcemia may be treated with conservative measures (i.e., saline hydration, with or without loop diuretics). Patients should be hydrated adequately throughout the treatment, but overhydration, especially in those patients who have cardiac failure, must be avoided. Diuretic therapy should not be employed prior to correction of hypovolemia.
The safety and efficacy of pamidronate disodium in the treatment of hypercalcemia associated with hyperparathyroidism or with other non-tumor-related conditions has not been established. Paget’s Disease Pamidronate disodium is indicated for the treatment of patients with moderate to severe Paget’s disease of bone. The effectiveness of pamidronate disodium was demonstrated primarily in patients with serum alkaline phosphatase ≥ 3 times the upper limit of normal.
Pamidronate disodium therapy in patients with Paget’s disease has been effective in reducing serum alkaline phosphatase and urinary hydroxyproline levels by ≥ 50% in at least 50% of patients, and by ≥ 30% in at least 80% of patients. Pamidronate disodium therapy has also been effective in reducing these biochemical markers in patients with Paget’s disease who failed to respond, or no longer responded to other treatments. Osteolytic Bone Metastases of Breast Cancer and Osteolytic Lesions of Multiple Myeloma Pamidronate disodium is indicated, in conjunction with standard antineoplastic therapy, for the treatment of osteolytic bone metastases of breast cancer and osteolytic lesions of multiple myeloma.
The pamidronate disodium treatment effect appeared to be smaller in the study of breast cancer patients receiving hormonal therapy than in the study of those receiving chemotherapy, however, overall evidence of clinical benefit has been demonstrated (see CLINICAL PHARMACOLOGY , Osteolytic Bone Metastases of Breast Cancer and Osteolytic Lesions of Multiple Myeloma, Clinical Trials section).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypercalcemia of Malignancy Consideration should be given to the severity of as well as the symptoms of hypercalcemia. Vigorous saline hydration alone may be sufficient for treating mild, asymptomatic hypercalcemia. Overhydration should be avoided in patients who have potential for cardiac failure.
In hypercalcemia associated with hematologic malignancies, the use of glucocorticoid therapy may be helpful. Moderate Hypercalcemia The recommended dose of pamidronate disodium in moderate hypercalcemia (corrected serum calcium* of approximately 12 to 13.5 mg/dL) is 60 to 90 mg given as a SINGLE DOSE, intravenous infusion over 2 to 24 hours. Longer infusions (i.e., >2 hours) may reduce the risk for renal toxicity, particularly in patients with preexisting renal insufficiency.
Severe Hypercalcemia The recommended dose of pamidronate disodium in severe hypercalcemia (corrected serum calcium* >13.5 mg/dL) is 90 mg given as a SINGLE DOSE, intravenous infusion over 2 to 24 hours. Longer infusions (i.e., >2 hours) may reduce the risk for renal toxicity, particularly in patients with preexisting renal insufficiency. * Albumin-corrected serum calcium (CCa, mg/dL) = serum calcium, mg/dL + 0.8 (4.0-serum albumin, g/dL). Retreatment A limited number of patients have received more than one treatment with pamidronate disodium for hypercalcemia.
Retreatment with pamidronate disodium, in patients who show complete or partial response initially, may be carried out if serum calcium does not return to normal or remain normal after initial treatment. It is recommended that a minimum of 7 days elapse before retreatment, to allow for full response to the initial dose . The dose and manner of retreatment is identical to that of the initial therapy.
Paget’s Disease The recommended dose of pamidronate disodium in patients with moderate to severe Paget’s disease of bone is 30 mg daily, administered as a 4-hour infusion on 3 consecutive days for a total dose of 90 mg. Retreatment A limited number of patients with Paget’s disease have received more than one treatment of pamidronate disodium in clinical trials. When clinically indicated, patients should be retreated at the dose of initial therapy.
Osteolytic Bone Lesions of Multiple Myeloma The recommended dose of pamidronate disodium in patients with osteolytic bone lesions of multiple myeloma is 90 mg administered as a 4-hour infusion given on a monthly basis. Patients with marked Bence-Jones proteinuria and dehydration should receive adequate hydration prior to pamidronate disodium infusion. Limited information is available on the use of pamidronate disodium in multiple myeloma patients with a serum creatinine ≥ 3.0 mg/dL.
Patients who receive pamidronate disodium should have serum creatinine assessed prior to each treatment. Treatment should be withheld for renal deterioration. In a clinical study, renal deterioration was defined as follows: For patients with normal baseline creatinine, increase of 0.5 mg/dL.
For patients with abnormal baseline creatinine, increase of 1.0 mg/dL. In this clinical study, pamidronate disodium treatment was resumed only when the creatinine returned to within 10% of the baseline value. The optimal duration of therapy is not yet known, however, in a study of patients with myeloma, final analysis after 21 months demonstrated overall benefits (see Clinical Trials section).
Osteolytic Bone Metastases of Breast Cancer The recommended dose of pamidronate disodium in patients with osteolytic bone metastases is 90 mg administered over a 2-hour infusion given every 3 to 4 weeks. Pamidronate disodium has been frequently used with doxorubicin, fluorouracil, cyclophosphamide, methotrexate, mitoxantrone, vinblastine, dexamethasone, prednisone, melphalan, vincristine, megesterol, and tamoxifen. It has been given less frequently with etoposide, cisplatin, cytarabine, paclitaxel, and aminoglutethimide.
Patients who receive pamidronate disodium should have serum creati…
⛔ Contraindications ▾
CONTRAINDICATIONS Pamidronate disodium is contraindicated in patients with clinically significant hypersensitivity to pamidronate disodium or other bisphosphonates.
⚠️ Warnings ▾
WARNINGS Deterioration in Renal Function Bisphosphonates, including pamidronate disodium, have been associated with renal toxicity manifested as deterioration of renal function and potential renal failure. DUE TO THE RISK OF CLINICALLY SIGNIFICANT DETERIORATION IN RENAL FUNCTION, WHICH MAY PROGRESS TO RENAL FAILURE, SINGLE DOSES OF PAMIDRONATE DISODIUM SHOULD NOT EXCEED 90 MG (see DOSAGE AND ADMINISTRATION for appropriate infusion durations). Renal deterioration, progression to renal failure, and dialysis have been reported in patients after the initial or a single dose of pamidronate disodium.
Focal segmental glomerulosclerosis (including the collapsing variant) with or without nephrotic syndrome, which may lead to renal failure, has been reported in pamidronate disodium-treated patients, particularly in the setting of multiple myeloma and breast cancer. Some of these patients had gradual improvement in renal status after pamidronate disodium was discontinued. Patients who receive pamidronate disodium should have serum creatinine assessed prior to each treatment.
Patients treated with pamidronate disodium for bone metastases should have the dose withheld if renal function has deteriorated (see DOSAGE AND ADMINISTRATION ). PREGNANCY: Bisphosphonates, such as pamidronate disodium, are incorporated into the bone matrix, from where they are gradually released over periods of weeks to years. Pamidronate disodium may cause fetal harm when administered to a pregnant woman.
In reproductive studies in rats and rabbits, pamidronate doses equivalent to 0.6 to 8.3 times the highest human recommended dose resulted in maternal toxicity and embryo/fetal effects. There are no adequate and well-controlled studies of pamidronate disodium in pregnant women. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, apprise the patient of the potential hazard to the fetus (See PRECAUTIONS ).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical Studies Hypercalcemia of Malignancy Transient mild elevation of temperature by at least 1°C was noted 24 to 48 hours after administration of pamidronate disodium in 34% of patients in clinical trials. In the saline trial, 18% of patients had a temperature elevation of at least 1°C 24 to 48 hours after treatment.
Drug-related local soft-tissue symptoms (redness, swelling or induration and pain on palpation) at the site of catheter insertion were most common in patients treated with 90 mg of pamidronate disodium. Symptomatic treatment resulted in rapid resolution in all patients. Rare cases of uveitis, iritis, scleritis, and episcleritis have been reported, including one case of scleritis, and one case of uveitis upon separate rechallenges.
Five of 231 patients (2%) who received pamidronate disodium during the four U.S. controlled hypercalcemia clinical studies were reported to have had seizures, 2 of whom had preexisting seizure disorders. None of the seizures were considered to be drug-related by the investigators. However, a possible relationship between the drug and the occurrence of seizures cannot be ruled out.
It should be noted that in the saline arm 1 patient (4%) had a seizure. There are no controlled clinical trials comparing the efficacy and safety of 90 mg pamidronate disodium over 24 hours to 2 hours in patients with hypercalcemia of malignancy. However, a comparison of data from separate clinical trials suggests that the overall safety profile in patients who received 90 mg pamidronate disodium over 24 hours is similar to those who received 90 mg pamidronate disodium over 2 hours.
The only notable differences observed were an increase in the proportion of patients in the pamidronate disodium 24-hour group who experienced fluid overload and electrolyte/mineral abnormalities. At least 15% of patients treated with pamidronate disodium for hypercalcemia of malignancy also experienced the following adverse events during a clinical trial: General: Fluid overload, generalized pain Cardiovascular: Hypertension Gastrointestinal: Abdominal pain, anorexia, constipation, nausea, vomiting Genitourinary: Urinary tract infection Musculoskeletal: Bone pain Laboratory Abnormality: Anemia, hypokalemia, hypomagnesemia, hypophosphatemia.
Many of these adverse experiences may have been related to the underlying disease state. The following table lists the adverse experiences considered to be treatment-related during comparative, controlled U.S. trials. Treatment-Related Adverse Experiences Reported in Three U.S.
Controlled Clinical Trials Percent of Patients Pamidronate Disodium Etidronate Disodium Saline 60 mg over 4 hr 60 mg over 24 hr 90 mg over 24 hr 7.5 mg/kg × 3 days n=23 n=73 n=17 n=35 n=23 General Edema 0 1 0 0 0 Fatigue 0 0 12 0 0 Fever 26 19 18 9 0 Fluid overload 0 0 0 6 0 Infusion-site reaction 0 4 18 0 0 Moniliasis 0 0 6 0 0 Rigors 0 0 0 0 4 Gastrointestinal Abdominal pain 0 1 0 0 0 Anorexia 4 1 12 0 0 Constipation 4 0 6 3 0 Diarrhea 0 1 0 0 0 Dyspepsia 4 0 0 0 0 Gastrointestinal hemorrhage 0 0 6 0 0 Nausea 4 0 18 6 0 Stomatitis 0 1 0 3 0 Vomiting 4 0 0 0 0 Respiratory Dyspnea 0 0 0 3 0 Rales 0 0 6 0 0 Rhinitis 0 0 6 0 0 Upper respiratory infection 0 3 0 0 0 CNS Anxiety 0 0 0 0 4 Convulsions 0 0 0 3 0 Insomnia 0 1 0 0 0 Nervousness 0 0 0 0 4 Psychosis 4 0 0 0 0 Somnolence 0 1 6 0 0 Taste perversion 0 0 0 3 0 Cardiovascular Atrial fibrillation 0 0 6 0 4 Atrial flutter 0 1 0 0 0 Cardiac failure 0 1 0 0 0 Hypertension 0 0 6 0 4 Syncope 0 0 6 0 0 Tachycardia 0 0 6 0 4 Endocrine Hypothyroidism 0 0 6 0 0 Hemic and Lymphatic Anemia 0 0 6 0 0 Leukopenia 4 0 0 0 0 Neutropenia 0 1 0 0 0 Thrombocytopenia 0 1 0 0 0 Musculoskeletal Myalgia 0 1 0 0 0…
🆘 Overdosage ▾
OVERDOSAGE There have been several cases of drug maladministration of intravenous pamidronate disodium in hypercalcemia patients with total doses of 225 mg to 300 mg given over 2½ to 4 days. All of these patients survived, but they experienced hypocalcemia that required intravenous and/or oral administration of calcium. Single doses of pamidronate disodium should not exceed 90 mg and the duration of the intravenous infusion should be no less than 2 hours (See WARNINGS ).
In addition, one obese woman (95 kg) who was treated with 285 mg of pamidronate disodium/day for 3 days experienced high fever (39.5°C), hypotension (from 170/90 mmHg to 90/60 mmHg), and transient taste perversion, noted about 6 hours after the first infusion. The fever and hypotension were rapidly corrected with steroids. If overdosage occurs, symptomatic hypocalcemia could also result; such patients should be treated with short-term intravenous calcium.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The principal pharmacologic action of pamidronate disodium is inhibition of bone resorption. Although the mechanism of antiresorptive action is not completely understood, several factors are thought to contribute to this action. Pamidronate disodium adsorbs to calcium phosphate (hydroxyapatite) crystals in bone and may directly block dissolution of this mineral component of bone.
In vitro studies also suggest that inhibition of osteoclast activity contributes to inhibition of bone resorption. In animal studies, at doses recommended for the treatment of hypercalcemia, pamidronate disodium inhibits bone resorption apparently without inhibiting bone formation and mineralization. Of relevance to the treatment of hypercalcemia of malignancy is the finding that pamidronate disodium inhibits the accelerated bone resorption that results from osteoclast hyperactivity induced by various tumors in animal studies.
Pharmacokinetics Cancer patients (n=24) who had minimal or no bony involvement were given an intravenous infusion of 30, 60, or 90 mg of pamidronate disodium over 4 hours and 90 mg of pamidronate disodium over 24 hours (Table 1). Distribution The mean ± SD body retention of pamidronate was calculated to be 54 ± 16% of the dose over 120 hours. Metabolism Pamidronate is not metabolized and is exclusively eliminated by renal excretion.
Excretion After administration of 30, 60, and 90 mg of pamidronate disodium over 4 hours, and 90 mg of pamidronate disodium over 24 hours, an overall mean ± SD of 46 ± 16% of the drug was excreted unchanged in the urine within 120 hours. Cumulative urinary excretion was linearly related to dose. The mean ± SD elimination half-life is 28 ± 7 hours.
Mean ± SD total and renal clearances of pamidronate were 107 ± 50 mL/min and 49 ± 28 mL/min, respectively. The rate of elimination from bone has not been determined. Special Populations There are no data available on the effects of age, gender, or race on the pharmacokinetics of pamidronate.
Pediatric Pamidronate is not labeled for use in the pediatric population. Renal Insufficiency The pharmacokinetics of pamidronate were studied in cancer patients (n=19) with normal and varying degrees of renal impairment. Each patient received a single 90 mg dose of pamidronate disodium infused over 4 hours.
The renal clearance of pamidronate in patients was found to closely correlate with creatinine clearance (see Figure 1). A trend toward a lower percentage of drug excreted unchanged in urine was observed in renally impaired patients. Adverse experiences noted were not found to be related to changes in renal clearance of pamidronate.
Given the recommended dose, 90 mg infused over 4 hours, excessive accumulation of pamidronate in renally impaired patients is not anticipated if pamidronate disodium is administered on a monthly basis. Figure 1: Pamidronate renal clearance as a function of creatinine clearance in patients with normal and impaired renal function. The lines are the mean prediction line and 95% confidence intervals.
Hepatic Insufficiency The pharmacokinetics of pamidronate were studied in male cancer patients at risk for bone metastases with normal hepatic function (n=6) and mild to moderate hepatic dysfunction (n=7). Each patient received a single 90 mg dose of pamidronate disodium infused over 4 hours. Although there was a statistically significant difference in the pharmacokinetics between patients with normal and impaired hepatic function, the difference was not considered clinically relevant.
Patients with hepatic impairment exhibited higher mean AUC (53%) and C max (29%), and decreased plasma clearance (33%) values. Nevertheless, pamidronate was still rapidly cleared from the plasma. Drug levels were not detectable in patients by 12 to 36 hours after drug infusion.
Because pamidronate disodium is administered on a monthly basis, drug accumulation is not expected. No changes in pamidronate disodium dosing regimen are recommended fo…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Vials – 3 mg/mL, 10 mL vial - each contains 30 mg of Pamidronate Disodium and 470 mg of Mannitol, USP in 10 mL Water for Injection, USP. Unit of Sale Concentration NDC 61703-324-18 Carton of 1 Single-dose vial 30 mg/10 mL (3 mg/mL) Vials – 6 mg/mL, 10 mL vial - each contains 60 mg of Pamidronate Disodium and 400 mg of Mannitol, USP in 10 mL Water for Injection, USP. Unit of Sale Concentration NDC 61703-325-18 Carton of 1 Single-dose vial 60 mg/10 mL (6 mg/mL) Vials – 9 mg/mL, 10 mL vial - each contains 90 mg of Pamidronate Disodium and 375 mg of Mannitol, USP in 10 mL Water for Injection, USP.
Unit of Sale Concentration NDC 61703-326-18 Carton of 1 Single-dose vial 90 mg/10 mL (9 mg/mL) Store at 20 to 25°C (68 to 77°F) [see USP Controlled Room Temperature]. Distributed by Hospira, Inc., Lake Forest, IL 60045 USA LAB-1156-3.0 Revised: 4/2021 Logo
📋 Description ▾
DESCRIPTION Pamidronate disodium is a bisphosphonate available in 30 mg, 60 mg, or 90 mg vials for intravenous administration. The pamidronate disodium obtained by combining pamidronic acid and sodium hydroxide is provided in a sterile, ready to use solution for injection. Each mL of the 30 mg vial contains: 3 mg Pamidronate Disodium; 47 mg Mannitol, USP; Water for Injection, USP, q.s.; Phosphoric Acid and/or Sodium Hydroxide, as necessary to adjust pH.
Each mL of the 60 mg vial contains: 6 mg Pamidronate Disodium; 40 mg Mannitol, USP; Water for Injection, USP, q.s.; Phosphoric Acid and/or Sodium Hydroxide, as necessary to adjust pH. Each mL of the 90 mg vial contains: 9 mg Pamidronate Disodium; 37.5 mg Mannitol, USP; Water for Injection, USP, q.s.; Phosphoric Acid and/or Sodium Hydroxide, as necessary to adjust pH. The pH of a 1% solution of pamidronate disodium in distilled water is approximately 8.3.
Pamidronate, a member of the group of chemical compounds known as bisphosphonates, is an analog of pyrophosphate. Pamidronate disodium is designated chemically as phosphonic acid (3-amino-1-hydroxypropylidene) bis-, disodium salt, and its structural formula is: Pamidronate disodium is soluble in water and in 2N sodium hydroxide, sparingly soluble in 0.1N hydrochloric acid and in 0.1N acetic acid, and practically insoluble in organic solvents. Its molecular formula is C 3 H 9 NO 7 P 2 Na 2 and its molecular weight is 279.1 (calculated as the anhydrous form).
Inactive Ingredients. Mannitol, USP, Phosphoric Acid and/or Sodium Hydroxide, as necessary (for adjustment to pH range of 6.0 - 7.0) and Water for Injection, USP. structural formula pamidronate disodium