
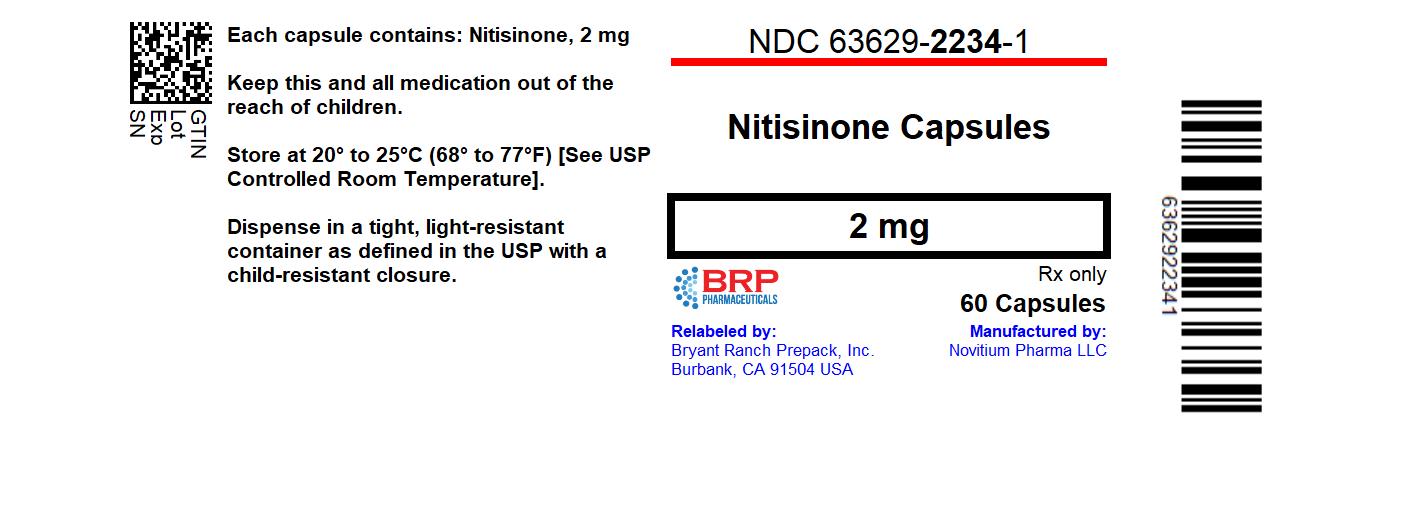
Nitisinone 2 mg Capsule, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the 4-Hydroxyphenyl-Pyruvate Dioxygenase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Nitisinone works by blocking an enzyme that's part of how your body breaks down an amino acid called tyrosine. In HT-1, when that breakdown goes wrong, it creates toxic byproducts...
- What exactly does nitisinone do, and why do I have to follow such a strict diet with it?
- The most common issue is a rise in blood tyrosine levels, which is why diet is so important. Some people also develop low blood cell counts, which your doctor monitors with regular...
- What side effects should I actually expect, and which ones should I call my doctor about right away?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with nitisinone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $55.68 | $3,340.99 / 60 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nitisinone 2 mg 00254-3020-02 | Par | 60 capsules | — | AB | FDA listed | — |
| Nitisinone 2 mgthis 63629-2234-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| Orfadin 2 mg 66658-0102-60 | SWEDISH | 60 capsules | — | AB | FDA listed | — |
| Nitisinone 2 mg 70505-0202-60 | Analog | 60 capsules | — | AB | FDA listed | — |
| Nitisinone 2 mg 71863-0119-60 | Eton | 60 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63629-2234-01 You're viewing this | 1 BOTTLE in 1 CARTON (63629-2234-1) / 60 CAPSULE in 1 BOTTLE | 2021-03-22 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Nitisinone capsules are indicated for the treatment of adult and pediatric patients with hereditary tyrosinemia type 1 (HT-1) in combination with dietary restriction of tyrosine and phenylalanine. Nitisinone is a hydroxy-phenylpyruvate dioxygenase inhibitor indicated for the treatment of adult and pediatric patients with hereditary tyrosinemia type 1 (HT-1) in combination with dietary restriction of tyrosine and phenylalanine.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION Recommended Dosage ( 2.1 ): The recommended starting dosage is 0.5 mg/kg orally twice daily. Titrate the dosage based on biochemical and/or clinical response, as described in the full prescribing information. The maximum total daily dosage is 2 mg/kg orally.
Administration ( 2.2 ): Maintain dietary restriction of tyrosine and phenylalanine Take Nitisinone capsules at least one hour before, or two hours after a meal For patients who have difficulties swallowing capsules, the capsules may be opened and the contents suspended in a small amount of water, formula or apple sauce immediately before use.
2.1Dosage Starting Dosage The recommended starting dosage of Nitisinone capsules is 0.5 mg/kg administered orally twice daily Dosage Titration Titrate the dosage in each individual patient based on biochemical and/or clinical response. Monitor plasma and/or urine succinylacetone concentrations, liver function parameters and alpha-fetoprotein levels. If succinylacetone is still detectable in blood or urine 4 weeks after the start of nitisinone treatment, increase the nitisinone dosage to 0.75 mg/kg twice daily.
A maximum total daily dosage of 2 mg/kg may be needed based on the evaluation of all biochemical parameters. If the biochemical response is satisfactory (undetectable blood and/or urine succinylacetone), the dosage should be adjusted only according to body weight gain and not according to plasma tyrosine levels. During initiation of therapy, or if there is a deterioration in the patient’s condition, it may be necessary to follow all available biochemical parameters more closely (i.e. plasma and/or urine succinylacetone, urine 5-aminolevulinate (ALA) and erythrocyte porphobilinogen (PBG)-synthase activity).
Maintain plasma tyrosine levels below 500 micromol/L by dietary restriction of tyrosine and phenylalanine intake [see Warnings and Precautions ( 5.1 )]. In patients who develop plasma tyrosine levels above 500 micromol/L, assess dietary tyrosine and phenylalanine intake. Do not adjust the nitisinone dosage in order to lower the plasma tyrosine concentration.
Additional pediatric use information is approved for Swedish Orphan Biovitrum AB PUBL’s ORFADIN (nitisinone) capsules. However, due to Swedish Orphan Biovitrum AB PUBL’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
2.2Administration Administration of Nitisinone Capsules: Maintain dietary restriction of tyrosine and phenylalanine when taking nitisinone. Capsules:Take at least one hour before, or two hours after a meal [see Clinical Pharmacology (12.3)] . For patients who have difficulty swallowing the capsules, the capsules may be opened and the contents suspended in a small amount of water, formula or apple sauce immediately before use.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Nitisinone Capsules are available as: 2 mg: White Opaque Hard gelatin capsule shell Size #3, imprinted with black ink as "008" on cap and "Novitium 2 mg" on body, filled with white to off white powder blend. 5 mg: White Opaque Hard gelatin capsule shell Size #3, imprinted with black ink as "009" on cap and "Novitium 5 mg" on body, filled with white to off white powder blend. 10 mg: White Opaque Hard gelatin capsule shell Size #3, imprinted with black ink as "010" on cap and "Novitium 10 mg" on body, filled with white to off white powder blend.
Capsules: 2 mg, 5 mg, 10 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Elevated Plasma Tyrosine Levels, Ocular Symptoms, Developmental Delay and Hyperkeratotic Plaques : Inadequate restriction of tyrosine and phenylalanine intake can lead to elevations in plasma tyrosine, which at levels above 500 micromol/L can result in symptoms, intellectual disability and developmental delay or painful hyperkeratotic plaques on the soles and palms; do not adjust nitisinone dosage in order to lower the plasma tyrosine concentration. Obtain slit-lamp examination prior to treatment, regularly during treatment; Reexamine patients if symptoms develop or tyrosine levels are > 500 micromol/L.
Assess plasma tyrosine levels in patients with an abrupt change in neurologic status. ( 5.1 ) Leukopenia and Severe Thrombocytopenia : Monitor platelet and white blood cell counts. ( 5.2 )
5.1Elevated Plasma Tyrosine Levels, Ocular Symptoms, Developmental Delay and Hyperkeratotic Plaques Nitisinone is an inhibitor of 4-hydroxyphenyl-pyruvate dioxygenase, an enzyme in the tyrosine metabolic pathway [ see Clinical Pharmacology ( 12.1 ) ]. Therefore, treatment with nitisinone may cause an increase in plasma tyrosine levels in patients with HT-1. Maintain concomitant reduction in dietary tyrosine and phenylalanine while on nitisinone treatment.
Do not adjust nitisinone dosage in order to lower the plasma tyrosine concentration. Maintain plasma tyrosine levels below 500 micromol/L. Inadequate restriction of tyrosine and phenylalanine intake can lead to elevations in plasma tyrosine levels and levels greater than 500 micromol/L may lead to the following: Ocular signs and symptoms including corneal ulcers, corneal opacities, keratitis, conjunctivitis, eye pain, and photophobia have been reported in patients treated with nitisinone [see Adverse Reactions ( 6.1 )] .
In a clinical study in a non HT-1 population without dietary restriction and reported tyrosine levels >500 micromol/l both symptomatic and asymptomatic keratopathies have been observed. Therefore, perform a baseline ophthalmologic examination including slit-lamp examination prior to initiating nitisinone treatment and regularly thereafter. Patients who develop photophobia, eye pain, or signs of inflammation such as redness, swelling, or burning of the eyes or tyrosine levels are >500 micromol/L during treatment with nitisinone should undergo slit-lamp reexamination and immediate measurement of the plasma tyrosine concentration.
Variable degrees of intellectual disability and developmental delay. In patients treated with nitisinone who exhibit an abrupt change in neurologic status, perform a clinical laboratory assessment including plasma tyrosine levels. Painful hyperkeratotic plaques on the soles and palms In patients with HT-1 treated with dietary restrictions and nitisinone who develop elevated plasma tyrosine levels, assess dietary tyrosine and phenylalanine intake.
5.2Leukopenia and Severe Thrombocytopenia In clinical trials, patients treated with nitisinone and dietary restriction developed transient leukopenia (3%), thrombocytopenia (3%), or both (1.5%) [see Adverse Reactions ( 6.1 )] . No patients developed infections or bleeding as a result of the episodes of leukopenia and thrombocytopenia. Monitor platelet and white blood cell counts during nitisinone therapy.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (>1%) are elevated tyrosine levels, thrombocytopenia, leukopenia, conjunctivitis, corneal opacity, keratitis, photophobia, eye pain, blepharitis, cataracts, granulocytopenia, epistaxis, pruritus, exfoliative dermatitis, dry skin, maculopapular rash and alopecia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novitium Pharma at 1-855-204-1431 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical trials experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Nitisinone was studied in one open-label, uncontrolled study of 207 patients with HT-1, ages 0 to 22 years at enrollment (median age 9 months), who were diagnosed with HT-1 by the presence of succinylacetone in the urine or plasma.
The starting dose of nitisinone was 0.3 to 0.5 mg/kg twice daily, and the dose was increased in some patients to 1 mg/kg twice daily based on weight, biochemical, and enzyme markers. The recommended starting dosage of nitisinone is 0.5 mg/kg twice daily [see Dosage and Administration ( 2.1 )]. Median duration of treatment was 22 months (range 0.1 to 80 months).
The most serious adverse reactions reported during nitisinone treatment were thrombocytopenia, leukopenia, porphyria, and ocular/visual complaints associated with elevated tyrosine levels [see Warnings and Precautions ( 5.1 , 5.2 )] . Fourteen patients experienced ocular/visual events. The duration of the symptoms varied from 5 days to 2 years.
Six patients had thrombocytopenia, three of which had platelet counts 30,000/microL or lower. In 4 patients with thrombocytopenia, platelet counts gradually returned to normal (duration up to 47 days) without change in nitisinone dose. No patients developed infections or bleeding as a result of the episodes of leukopenia and thrombocytopenia.
Patients with HT- 1 are at increased risk of developing porphyric crises, hepatic neoplasms, and liver failure requiring liver transplantation. These complications of HT-1 were observed in patients treated with nitisinone for a median of 22 months during the clinical trial (liver transplantation 13%, liver failure 7%, malignant hepatic neoplasms 5%, benign hepatic neoplasms 3%, porphyria 1%). The most common adverse reactions reported in the clinical trial are summarized in Table 1.
TABLE 1 Most Common Adverse Reactions in Patients with HT-1 Treated with Nitisinone* Elevated tyrosine levels >10% Leukopenia 3% Thrombocytopenia 3% Conjunctivitis 2% Corneal opacity 2% Keratitis 2% Photophobia 2% Eye pain 1% Blepharitis 1% Cataracts 1% Granulocytopenia 1% Epistaxis 1% Pruritus 1% Exfoliative dermatitis 1% Dry skin 1% Maculopapular rash 1% Alopecia 1% *reported in at least 1% of patients Adverse reactions reported in less than 1% of the patients, included death, seizure, brain tumor, encephalopathy, hyperkinesia, cyanosis, abdominal pain, diarrhea, enanthema, gastrointestinal hemorrhage, melena, elevated hepatic enzymes, liver enlargement, hypoglycemia, septicemia, and bronchitis.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nitisinone is a moderate CYP2C9 inhibitor, a weak CYP2E1 inducer and an inhibitor of OAT1/OAT3. Table 2 includes drugs with clinically important drug interactions when administered concomitantly with nitisinone and instructions for preventing or managing them. Table 2: Clinically Relevant Interactions Affecting Co-Administered Drugs Sensitive CYP2C9 Substrates (e.g., celecoxib, tolbutamide) or CYP2C9 Substrates with a Narrow Therapeutic Index (e.g., phenytoin, warfarin) Clinical Impact Increased exposure of the co-administered drugs metabolized by CYP2C9. [see Clinical Pharmacology ( 12.3 )] Intervention Reduce the dosage of the co-administered drugs metabolized by CYP2C9 drug by half.
Additional dosage adjustments may be needed to maintain therapeutic drug concentrations for narrow therapeutic index drugs. See prescribing information for those drugs. OAT1/OAT3 Substrates (e.g., adefovir, ganciclovir, methotrexate) Clinical Impact Increased exposure of the interacting drug [see Clinical Pharmacology ( 12.3 )] Intervention Monitor for potential adverse reactions related to the co-administered drug.
CYP2C9 Substrates : Increased systemic exposure of these co-administered drugs; reduce the dosage. Additional dosage adjustments may be needed to maintain therapeutic drug concentrations for narrow therapeutic index drugs. ( 7 ) OAT1/OAT3 Substrates : Increased systemic exposure of these co-administered drugs; monitor for potential adverse reactions.
( 7 ) Additional pediatric use information is approved for Swedish Orphan Biovitrum AB PUBL's Orfadin (nitisinone) capsules. However, due to Swedish Orphan Biovitrum AB PUBL's marketing exclusivity rights, this drug product is not labeled with that pediatric information.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Limited available data with nitisinone use in pregnant women are not sufficient to determine a drug-associated risk of adverse developmental outcomes. Animal reproduction studies have been conducted for nitisinone. In these studies, nitisinone was administered to mice and rabbits during organogenesis with oral doses of nitisinone up to 20 and 8 times respectively, the recommended initial dose of 1 mg/kg/day.
In mice, nitisinone caused incomplete skeletal ossification of fetal bones and decreased pup survival at doses 0.4 times the recommended initial dose, and increased gestational length at doses 4 times the recommended initial dose. In rabbits, nitisinone caused maternal toxicity and incomplete skeletal ossification of fetal bones at doses 1.6 times the recommended initial dose [see Data]. The background risk of major birth defects and miscarriage for the indicated population are unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproduction studies have been performed in mice at oral doses of about 0.4, 4 and 20 times the recommended initial dose (1 mg/kg/day) and in rabbits at oral doses of about 1.6, 4 and 8 times the recommended initial dose based on the body surface area. In mice, nitisinone has been shown to cause incomplete skeletal ossification of fetal bones at 0.4, 4 and 20 times the recommended initial dose, increased gestational length at 4 and 20 times the recommended initial dose, and decreased pup survival at 0.4 times the recommended initial dose based on the body surface area.
In rabbits, nitisinone caused incomplete skeletal ossification of fetal bones at 1.6, 4 and 8 times the recommended initial dose based on the body surface area.
8.2Lactation Risk Summary There are no data on the presence of nitisinone in human milk, the effects on the breastfed infant, or the effects on milk production. Data suggest that nitisinone is present in rat milk due to findings of ocular toxicity and lower body weight seen in drug naive nursing rat pups. The development and health benefits of breastfeeding should be considered along with the mother's clinical need for nitisinone and any potential adverse effects on the breastfed infant from nitisinone or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of nitisinone have been established in pediatric patients for the treatment of HT-1 in combination with dietary restriction of tyrosine and phenylalanine. Use of nitisinone in pediatric patients is supported by evidence from one open-label, uncontrolled clinical study conducted in 207 patients with HT-1 ages 0 to 22 years (median age 9 months) [see Clinical Studies ( 14 )].
8.5Geriatric Use Clinical studies of nitisinone did not include any subjects aged 65 and over. No pharmacokinetic studies of nitisinone have been performed in geriatric patients. In general, dose selection for an elderly patient should be cautious reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease or other drug therapy in this patient population.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with nitisinone use in pregnant women are not sufficient to determine a drug-associated risk of adverse developmental outcomes. Animal reproduction studies have been conducted for nitisinone. In these studies, nitisinone was administered to mice and rabbits during organogenesis with oral doses of nitisinone up to 20 and 8 times respectively, the recommended initial dose of 1 mg/kg/day.
In mice, nitisinone caused incomplete skeletal ossification of fetal bones and decreased pup survival at doses 0.4 times the recommended initial dose, and increased gestational length at doses 4 times the recommended initial dose. In rabbits, nitisinone caused maternal toxicity and incomplete skeletal ossification of fetal bones at doses 1.6 times the recommended initial dose [see Data]. The background risk of major birth defects and miscarriage for the indicated population are unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproduction studies have been performed in mice at oral doses of about 0.4, 4 and 20 times the recommended initial dose (1 mg/kg/day) and in rabbits at oral doses of about 1.6, 4 and 8 times the recommended initial dose based on the body surface area. In mice, nitisinone has been shown to cause incomplete skeletal ossification of fetal bones at 0.4, 4 and 20 times the recommended initial dose, increased gestational length at 4 and 20 times the recommended initial dose, and decreased pup survival at 0.4 times the recommended initial dose based on the body surface area.
In rabbits, nitisinone caused incomplete skeletal ossification of fetal bones at 1.6, 4 and 8 times the recommended initial dose based on the body surface area.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of nitisinone have been established in pediatric patients for the treatment of HT-1 in combination with dietary restriction of tyrosine and phenylalanine. Use of nitisinone in pediatric patients is supported by evidence from one open-label, uncontrolled clinical study conducted in 207 patients with HT-1 ages 0 to 22 years (median age 9 months) [see Clinical Studies ( 14 )].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of nitisinone did not include any subjects aged 65 and over. No pharmacokinetic studies of nitisinone have been performed in geriatric patients. In general, dose selection for an elderly patient should be cautious reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease or other drug therapy in this patient population.
🆘 Overdosage ▾
10 OVERDOSAGE Accidental ingestion of nitisinone by individuals eating normal diets not restricted in tyrosine and phenylalanine will result in elevated tyrosine levels. In healthy subjects given a single 1 mg/kg dose of nitisinone, the plasma tyrosine level reached a maximum of 1200 micromol/L at 48 to 120 hours after dosing. After a washout period of 14 days, the mean value of plasma tyrosine was still 808 micromol/L.
Fasted follow-up samples obtained from volunteers several weeks later showed tyrosine values back to normal. There were no reports of changes in vital signs or laboratory data of any clinical significance. One patient reported sensitivity to sunlight.
Hyper-tyrosinemia has been reported with nitisinone treatment [see Warnings and Precautions ( 5.1 )] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Nitisinone is a competitive inhibitor of 4-hydroxyphenyl-pyruvate dioxygenase, an enzyme upstream of fumarylacetoacetate hydrolase (FAH) in the tyrosine catabolic pathway. By inhibiting the normal catabolism of tyrosine in patients with HT-1, nitisinone prevents the accumulation of the catabolic intermediates maleylacetoacetate and fumarylacetoacetate. In patients with HT-1, these catabolic intermediates are converted to the toxic metabolites succinylacetone and succinylacetoacetate, which are responsible for the observed liver and kidney toxicity.
Succinylacetone can also inhibit the porphyrin synthesis pathway leading to the accumulation of 5-aminolevulinate, a neurotoxin responsible for the porphyric crises characteristic of HT-1.
12.2Pharmacodynamics In a clinical study, patients with HT-1 were diagnosed by the presence of succinylacetone in urine or plasma and treated with nitisinone [see Clinical Studies ( 14 )] . In all 186 patients whose urine succinylacetone was measured, the urinary succinylacetone concentration decreased to less than 1 mmol/mol creatinine, the lower limit of quantitation. The median time to normalization of urine succinylacetone was 0.3 months.
The probability of recurrence of abnormal values of urine succinylacetone was 1% at a nitisinone concentration of 37 micromol/L (95% confidence interval: 23, 51 micromol/L). In 87% (150/172) of patients whose plasma succinylacetone was measured, the plasma succinylacetone concentration decreased to less than 0.1 micromol/L, the lower limit of quantitation. The median time to normalization of plasma succinylacetone was 3.9 months.
Nitisinone inhibits catabolism of the amino acid tyrosine and can result in elevated plasma levels of tyrosine. Therefore, treatment with nitisinone requires restriction of the dietary intake of tyrosine and phenylalanine to prevent the toxicity associated with elevated plasma levels of tyrosine [see Warnings and Precautions ( 5.1 )] . Additional pediatric use information is approved for Swedish Orphan Biovitrum ABPUBL's Orfadin (nitisinone) capsules.
However, due to Swedish Orphan Biovitrum ABPUBL's marketing exclusivity rights, this drug product is not labeled with that pediatric information.
12.3Pharmacokinetics The single-dose pharmacokinetics of nitisinone have been studied for nitisinone capsules in healthy adult subjects and the multiple-dose pharmacokinetics have been studied for nitisinone capsules in healthy subjects. Absorption The pharmacokinetic characteristics following single oral administration of nitisinone 30 mg under fasting conditions are shown in Table 3. The multiple-dose characteristics of nitisinone 80 mg once daily are shown in Table 4.
Steady-state (SS) was reached within 14 days dosing in all subjects. TABLE 3 Nitisinone Arithmetic Mean (CV%) Pharmacokinetic Parameters in Healthy Subjects Following a Single Oral 30 mg Dose of Nitisinone Under Fasting Conditions Treatment C max (micromol/L) [range] t max * (h) [range] AUC 0-72h (micromol·h/L) [range] Nitisinone capsule (n=12) 10.5 (26) 3.5 [0.8 to 8.0] 406 (13) * presented as median [range] TABLE 4 Nitisinone Arithmetic Mean (CV%) Pharmacokinetic Parameters in Healthy Subjects Following Repeated Once Daily Administration of 80 mg Nitisisnone Under Fasting Conditions.
C max,ss (micromol/L) C min,ss (micromol/L) t max,ss * (h) AUC0-24h,ss (micromol·h/L) Treatment [CV%] [range] [range] [range] Nitisisnone capsule (n=18) 120 (23) 73(24) 4.0 2204(18) [0.0 to 16.0] * presented as median [range] Food Effect: No food effect study was conducted with nitisinone capsules. Distribution In vitro binding of nitisinone to human plasma proteins is greater than 95% at 50 micromolar concentration. Elimination The mean terminal plasma half-life of single dose nitisinone in healthy male subjects is 54 hours.
The mean (CV%) apparent plasma clearance in 18 healthy adults following multiple once daily doses of Nitisinone 80 mg is…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Nitisinone is a competitive inhibitor of 4-hydroxyphenyl-pyruvate dioxygenase, an enzyme upstream of fumarylacetoacetate hydrolase (FAH) in the tyrosine catabolic pathway. By inhibiting the normal catabolism of tyrosine in patients with HT-1, nitisinone prevents the accumulation of the catabolic intermediates maleylacetoacetate and fumarylacetoacetate. In patients with HT-1, these catabolic intermediates are converted to the toxic metabolites succinylacetone and succinylacetoacetate, which are responsible for the observed liver and kidney toxicity.
Succinylacetone can also inhibit the porphyrin synthesis pathway leading to the accumulation of 5-aminolevulinate, a neurotoxin responsible for the porphyric crises characteristic of HT-1.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Nitisinone Capsules 2 mg for oral administration containing 2 mg of nitisinone, are supplied as follows: White Opaque Hard gelatin capsule shell Size #3, imprinted with black ink as "008" on cap and "Novitium 2 mg" on body, filled with white to off white powder blend. NDC 63629-2234-1 Bottles of 60 capsules with child-resistant closure and tamper resistant induction sealing Store at room temperature between 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Nitisinone capsules contains nitisinone, which is a hydroxyphenyl-pyruvate dioxygenase inhibitor indicated as an adjunct to dietary restriction of tyrosine and phenylalanine in the treatment of hereditary tyrosinemia type 1 (HT-1). Nitisinone occurs as white to yellow colored powder. It is practically insoluble in water and sparingly soluble in 2M Sodium Hydroxide, Ethanol and Methanol.
Chemically, nitisinone is 2-[2-nitro-4-(trifluoromethyl)benzoyl] cyclohexane-1,3-dione, and the structural formula is: Figure 1. The molecular formula is C14H10F3NO5 with a relative mass of 329.23 Inert ingredients in the formulation are: Citric acid anhydrous, hypromellose, mannitol and stearic acid. The empty hard gelatin capsules contains gelatin, sodium lauryl sulfate and titanium dioxide.
The capsules shells are imprinted in edible ink which contains black iron oxide, potassium hydroxide, propylene glycol, shellac and strong ammonia solution.
💬 Information for Patients ▾
17 PATIENT COUNSELLING INFORMATION Administration [see Dosage and Administration ( 2.2 )] Administration of Nitisinone Capsules Maintain dietary restriction of tyrosine and phenylalanine when taking nitisinone. Capsules: Take at least one hour before, or two hours after a meal. For patients who have difficulty swallowing the capsules, the capsules may be opened and the contents suspended in a small amount of water, formula or apple sauce immediately before use.
Elevated Plasma Tyrosine Levels, Ocular Symptoms, Developmental Delay and Hyperkeratotic Plaques Inform patients that inadequate restriction may be associated with ocular signs and symptoms, intellectual disability and developmental delay, and painful hyperkeratotic plaques on the soles and palms. Advise patients and caregivers of the need to maintain dietary restriction of tyrosine and phenylalanine and to report any unexplained ocular, neurologic, or other symptoms promptly to their healthcare provider [ see Warnings and Precautions ( 5.1 ) ].
Manufactured by: Novitium Pharma LLC 70 Lake Drive, East Windsor New Jersey 08520 Distributed by: Par Pharmaceutical Chestnut Ridge, NY 10977 Revised: August, 2019