
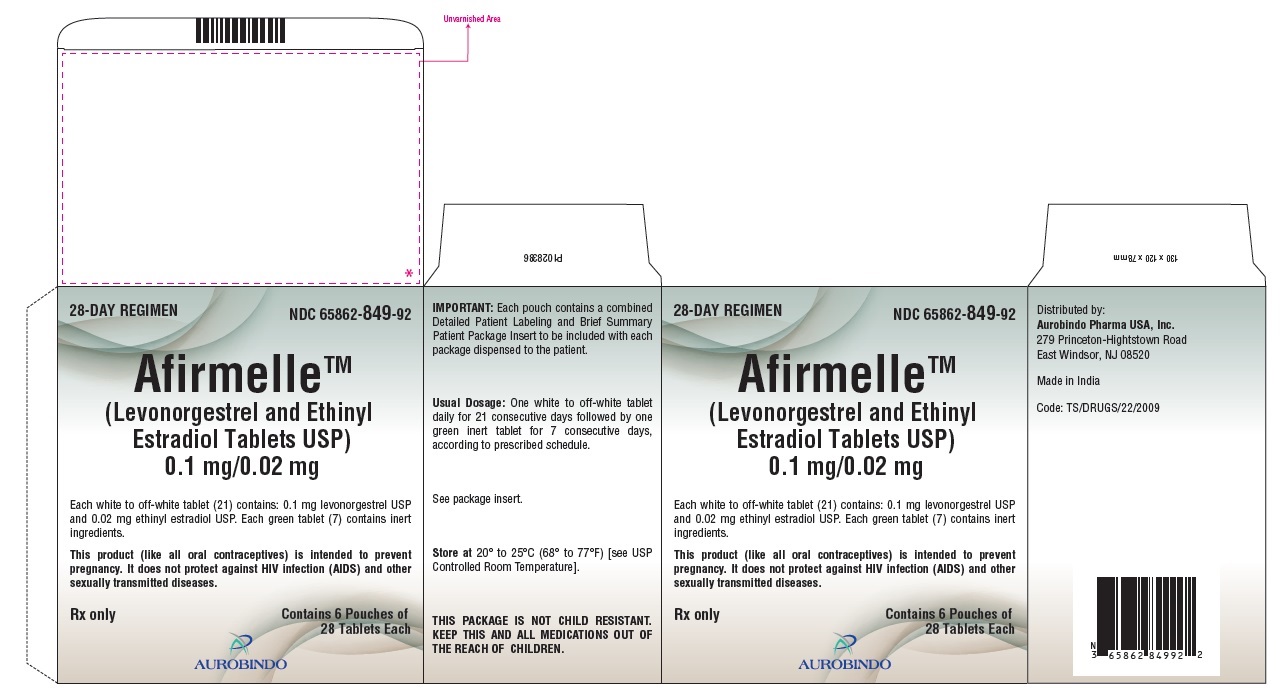
Afirmelle Levonorgestrel and Ethinyl Estradiol Kit, 6 pouches — NDC 65862-849-92 (Billing 65862-0849-92)
This is a package of 6 pouches of Afirmelle Levonorgestrel and Ethinyl Estradiol Kit from Aurobindo Pharma Limited, marketed since Nov 2016 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 030986
- GCN: 11534
- GPI-14 (Medi-Span): 25990002400305
- HICL (First Databank): 001460
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 242297
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It prevents pregnancy. It is a combined hormonal birth control with an estrogen and a progestin. It comes as daily tablets or as the weekly Twirla patch.
- With tablets, you take one at the same time every day, no more than 24 hours apart. With the Twirla patch, you wear one patch for a week, three weeks in a row, then take a patch-fr...
- Headache, nausea, acne, breast tenderness, mood changes, and irregular bleeding are the common ones. Bleeding changes often settle with time. Call your doctor if they persist.
- Get help for chest pain, sudden shortness of breath, leg swelling or pain, vision loss, or severe new headaches. These can signal a blood clot or stroke. Also report yellowing of y...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0849-88 65862-849-88 Main listing | 3 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | $0.2250 / ea | $0.67 | 2016-11-14 | — | Active |
| 65862-0849-92 You're viewing this | 6 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | — | — | 2016-11-14 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0849-88?
What NDC number is used to bill for this package of Afirmelle Levonorgestrel and Ethinyl Estradiol Kit?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levonorgestrel And Ethinyl Estradiol 00378-6550-53 | Mylan | 3 pouches | $0.113 | AB | Discontinued | — |
| Altavera 70700-0116-85 | Xiromed, | 1 kit | $0.114 | AB | Availability likely | — |
| Ayuna 65862-0848-88 | Aurobindo | 3 pouches | $0.114 | AB | Availability likely | — |
| Chateal EQ 50102-0230-23 | Afaxys | 3 pouches | $0.114 | AB | Availability likely | — |
| Marlissa 68462-0388-29 | Glenmark | 1 kit | $0.114 | AB | Availability likely | — |
| Kurvelo 68180-0844-73 | Lupin | 63 tablets | $0.114 | AB | Availability likely | — |
| Portia 00555-9020-58 | Teva | 6 pouches | $0.114 | — | Availability likely | — |
| Daysee 68180-0846-13 | Lupin | 2 pouches | $0.125 | AB | Availability likely | — |
| Levora 51862-0097-06 | Mayne | 1 kit | $0.145 | AB | Discontinued | — |
| Levonorgestrel And Ethinyl Estradiol 00378-7287-53 | Mylan | 3 pouches | $0.151 | AB1 | Availability likely | — |
| Lutera 51862-0028-06 | Mayne | 1 kit | $0.152 | AB1 | Discontinued | — |
| Lessina 00555-9014-67 | Teva | 3 pouches | $0.154 | — | Availability likely | — |
| Aubra EQ 50102-0220-23 | Afaxys | 3 pouches | $0.154 | AB1 | Availability likely | — |
| Levonorgestrel and Ethinyl Estradiol 68180-0854-73 | Lupin | 1 kit | $0.154 | AB1 | Availability likely | — |
| Aviane 00555-9045-58 | Teva | 6 pouches | $0.154 | — | Availability likely | — |
| Vienva 70700-0118-85 | Xiromed, | 1 kit | $0.154 | AB1 | Availability likely | — |
| Falmina 16714-0359-01 | Northstar | 1 packet | $0.154 | AB1 | Availability likely | — |
| Sronyx 51862-0545-06 | Mayne | 1 kit | $0.174 | AB2 | Discontinued | — |
| Introvale 70700-0117-87 | Xiromed, | 1 kit | $0.184 | AB | FDA listed | — |
| Iclevia 65862-0865-83 | Aurobindo | 3 pouches | $0.227 | AB | FDA listed | — |
| Setlakin 16714-0366-03 | Northstar | 3 pouches | $0.227 | AB | Availability likely | — |
| Levonorgestrel and Ethinyl Estradiol 68180-0843-13 | Lupin | 1 kit | $0.227 | AB | Availability likely | — |
| levonorgestrel and ethinyl estradiol 68462-0672-95 | Glenmark | 3 pouches | $0.227 | AB | Availability likely | — |
| Levonorgestrel and Ethinyl Estradiol and Ethinyl Estradiol 68180-0848-13 | Lupin | 2 pouches | $0.239 | AB | Availability likely | — |
| Levonest 16714-0340-01 | Northstar | 1 packet | $0.324 | AB | Availability likely | — |
| Levonorgestrel and Ethinyl Estradiol 68180-0857-73 | Lupin | 1 kit | $0.324 | AB | Availability likely | — |
| Tyblume 00642-7471-01 | Exeltis | 1 kit | $0.828 | — | Availability likely | — |
| levonorgestrel and ethinyl estradiol 42192-0623-03 | Acella | 1 kit | $3.445 | AB3 | Availability likely | — |
| Levonest 50090-2505-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Kurvelo 50090-6374-00 | A-S | 21 tablets | — | AB | FDA listed | — |
| Altavera 63629-2343-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Afirmellethis 65862-0849-92 | Aurobindo | 6 pouches | — | AB1 | FDA listed | — |
| Lutera 55741-0005-06 | Dr. | 1 kit | — | AB1 | FDA listed | — |
| Balcoltra 75854-0602-02 | Avion | 1 kit | — | AB3 | FDA listed | — |
| Vienva Tm 50090-5580-00 | A-S | 1 kit | — | AB1 | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 79929-0003-07 | Naari | 1 kit | — | AB | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 60505-4898-08 | Apotex | 1 kit | — | AB1 | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 60505-4899-08 | Apotex | 1 kit | — | AB | FDA listed | — |
| Vienva TM 63629-2344-01 | Bryant | 1 kit | — | AB1 | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 79929-0004-07 | Naari | 1 kit | — | AB1 | FDA listed | — |
| Aviane 63187-0889-28 | Proficient | 1 pouch | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Cigarette smoking increases the risk of serious cardiovascular side effects from oral-contraceptive use. This risk increases with age and with the extent of smoking (in epidemiologic studies, 15 or more cigarettes per day was associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should be strongly advised not to smoke.
Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels from oral-contraceptive use. This risk increases with age and with the amount of smoking (15 or more cigarettes per day has been associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should not smoke.
Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels from oral-contraceptive use. This risk increases with age and with the amount of smoking (15 or more cigarettes per day has been associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should not smoke.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Afirmelle is indicated for the prevention of pregnancy in women who elect to use oral contraceptives as a method of contraception. Oral contraceptives are highly effective. Table II lists the typical accidental pregnancy rates for users of combination oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, the IUD, and Norplant ® System, depends upon the reliability with which they are used. Correct and consistent use of methods can result in lower failure rates. % of Women Experiencing an Unintended Pregnancy within the First Year of Use % of Women Continuing Use at One Year 3 Method Typical Use 1 Perfect Use 2 (1) (2) (3) (4) Chance 4 85 85 Spermicides 5 26 6 40 Periodic abstinence 25 63 Calendar 9 Ovulation Method 3 Sympto-Thermal 6 2 Post-Ovulation 1 Cap 7 Parous Women 40 26 42 Nulliparous Women 20 9 56 Sponge Parous Women 40 20 42 Nulliparous Women 20 9 56 Diaphragm 7 20 6 56 Withdrawal 19 4 Condom 8 Female (Reality) 21 5 56 Male 14 3 61 Pill 5 71 Progestin only
0.5 Combined
0.1IUD Progesterone T 2.0 1.5 81 Copper T380A 0.8 0.6 78 LNg 20 0.1 0.1 81 Depo-Provera ® 0.3 0.3 70 Levonorgestrel Implants (Norplant ® ) 0.05 0.05 88 Female Sterilization 0.5 0.5 100 Male Sterilization 0.15 0.10 100 Emergency Contraceptive Pills: The FDA has concluded that certain combined oral contraceptives containing ethinyl estradiol and norgestrel or levonorgestrel are safe and effective for use as postcoital emergency contraception. Treatment initiated within 72 hours after unprotected intercourse reduces the risk of pregnancy by at least 75%.
9 Lactation Amenorrhea Method: LAM is a highly effective, temporary method of contraception. 10 Source: Trussell J. Contraceptive efficacy.
In: Hatcher RA, Trussell J, Stewart F, Cates W, Stewart GK, Kowel D, Guest F. Contraceptive Technology: Seventeenth Revised Edition. New York NY: Irvington Publishers; 1998.
1. Among typical couples who initiate use of a method (not necessarily for the first time), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. 2.
Among couples who initiate use of a method (not necessarily for the first time) and who use it perfectly (both consistently and correctly), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. 3. Among couples attempting to avoid pregnancy, the percentage who continue to use a method for one year.
4. The percents becoming pregnant in columns (2) and (3) are based on data from populations where contraception is not used and from women who cease using contraception in order to become pregnant. Among such populations, about 89% become pregnant within one year.
This estimate was lowered slightly (to 85%) to represent the percent who would become pregnant within one year among women now relying on reversible methods of contraception if they abandoned contraception altogether. 5. Foams, creams, gels, vaginal suppositories, and vaginal film.
6. Cervical mucus (ovulation) method supplemented by calendar in the pre-ovulatory and basal body temperature in the post-ovulatory phases. 7.
With spermicidal cream or jelly. 8. Without spermicides.
9. The treatment schedule is one dose within 72 hours after unprotected intercourse, and a second dose 12 hours after the first dose. The FDA has declared the following dosage regimens of oral contraceptives to be safe and effective for emergency contraception: for tablets containing 50 mcg of ethinyl estradiol and 500 mcg of norgestrel 1 dose is 2 tablets; for tablets containing 20 mcg of ethinyl estradiol and 100 mcg of levonorgestrel 1 dose is 5 tablets; for tablets containing 30 mcg of ethinyl estradiol and 150 mcg of levonorgestrel 1 dose is 4 tablets.
10. However, to maintain effective protection against pregnancy, another method of contraception must be used as soon as menstruation resumes, the… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Afirmelle TM (levonorgestrel and ethinyl estradiol tablets) must be taken exactly as directed and at intervals not exceeding 24 hours. The dosage of Afirmelle is one white tablet daily for 21 consecutive days, followed by one green inert tablet daily for 7 consecutive days, according to prescribed schedule. It is recommended that Afirmelle tablets be taken at the same time each day.
The blister pack should be kept in the pouch supplied to avoid possible fading of the pills. If the pills fade, patients should continue to take them as directed. During The First Cycle of Use The possibility of ovulation and conception prior to initiation of medication should be considered.
The patient should be instructed to begin taking Afirmelle on either the first Sunday after the onset of menstruation (Sunday Start) or on Day 1 of menstruation (Day 1 Start). Sunday Start The patient is instructed to begin taking Afirmelle on the first Sunday after the onset of menstruation. If menstruation begins on a Sunday, the first tablet (white) is taken that day.
One white tablet should be taken daily for 21 consecutive days, followed by one green inert tablet daily for 7 consecutive days. Withdrawal bleeding should usually occur within 3 days following discontinuation of white tablets and may not have finished before the next pack is started. During the first cycle, contraceptive reliance should not be placed on Afirmelle until a white tablet has been taken daily for 7 consecutive days, and a nonhormonal back-up method of birth control should be used during those 7 days.
Day 1 Start During the first cycle of medication, the patient is instructed to begin taking Afirmelle during the first 24 hours of her period (day one of her menstrual cycle). One white tablet should be taken daily for 21 consecutive days, followed by one green inert tablet daily for 7 consecutive days. Withdrawal bleeding should usually occur within 3 days following discontinuation of white tablets and may not have finished before the next pack is started.
If medication is begun on day one of the menstrual cycle, no back-up contraception is necessary. If Afirmelle tablets are started later than day one of the first menstrual cycle or postpartum, contraceptive reliance should not be placed on Afirmelle tablets until after the first 7 consecutive days of administration, and a nonhormonal back-up method of birth control should be used during those 7 days. After the First Cycle of Use The patient begins her next and all subsequent courses of tablets on the day after taking her last green tablet.
She should follow the same dosing schedule: 21 days on white tablets followed by 7 days on green tablets. If in any cycle the patient starts tablets later than the proper day, she should protect herself against pregnancy by using a nonhormonal back-up method of birth control until she has taken a white tablet daily for 7 consecutive days. Switching from Another Hormonal Method of Contraception When the patient is switching from a 21-day regimen of tablets, she should wait 7 days after her last tablet before she starts Afirmelle.
She will probably experience withdrawal bleeding during that week. She should be sure that no more than 7 days pass after her previous 21-day regimen. When the patient is switching from a 28-day regimen of tablets, she should start her first pack of Afirmelle on the day after her last tablet.
She should not wait any days between packs. The patient may switch any day from a progestin-only pill and should begin Afirmelle the next day. If switching from an implant or injection, the patient should start Afirmelle on the day of implant removal or, if using an injection, the day the next injection would be due.
In switching from a progestin-only pill, injection, or implant, the patient should be advised to use a nonhormonal back-up method of birth control for the first 7 days of tablet-taking. If Spotting… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Afirmelle is contraindicated in females who are known to have or develop the following conditions: Thrombophlebitis or thromboembolic disorders A history of deep-vein thrombophlebitis or thromboembolic disorders Cerebrovascular or coronary artery disease (current or past history) Valvular heart disease with thrombogenic complications Thrombogenic rhythm disorders Hereditary or acquired thrombophilias Major surgery with prolonged immobilization Diabetes with vascular involvement Headaches with focal neurological symptoms Uncontrolled hypertension Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Hepatic adenomas or carcinomas, or active liver disease Known or suspected pregnancy Hypersensitivity to any of the components of Afirmelle Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see WARNINGS, RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ).
⚠️ Warnings ▾
WARNINGS Cigarette smoking increases the risk of serious cardiovascular side effects from oral-contraceptive use. This risk increases with age and with the extent of smoking (in epidemiologic studies, 15 or more cigarettes per day was associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should be strongly advised not to smoke.
The use of oral contraceptives is associated with increased risks of several serious conditions including venous and arterial thrombotic and thromboembolic events (such as myocardial infarction, thromboembolism, and stroke), hepatic neoplasia, gallbladder disease, and hypertension, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as certain inherited or acquired thrombophilias, hypertension, hyperlipidemias, obesity, diabetes, and surgery or trauma with increased risk of thrombosis (see CONTRAINDICATIONS ).
Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks. The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with higher doses of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with lower doses of both estrogens and progestogens remains to be determined.
Throughout this labeling, epidemiological studies reported are of two types: retrospective or case control studies and prospective or cohort studies. Case control studies provide a measure of the relative risk of disease, namely, a ratio of the incidence of a disease among oral-contraceptive users to that among nonusers. The relative risk does not provide information on the actual clinical occurrence of a disease.
Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral-contraceptive users and nonusers. The attributable risk does provide information about the actual occurrence of a disease in the population. For further information, the reader is referred to a text on epidemiological methods.
1. Thromboembolic Disorders and Other Vascular Problems a. Myocardial Infarction An increased risk of myocardial infarction has been attributed to oral-contraceptive use.
This risk is primarily in smokers or women with other underlying risk factors for coronary-artery disease such as hypertension, hypercholesterolemia, morbid obesity, and diabetes. The relative risk of heart attack for current oral-contraceptive users has been estimated to be two to six. The risk is very low under the age of 30.
Smoking in combination with oral-contraceptive use has been shown to contribute substantially to the incidence of myocardial infarction in women in their mid-thirties or older with smoking accounting for the majority of excess cases. Mortality rates associated with circulatory disease have been shown to increase substantially in smokers over the age of 35 and nonsmokers over the age of 40 (FIGURE II) among women who use oral contraceptives. FIGURE II.
(Adapted from P.M. Layde and V. Beral, Lancet, 1:541-546, 1981.) Oral contraceptives may compound the effects of well-known risk factors, such as hypertension, diabetes, hyperlipidemias, age, and obesity.
In particular, some progestogens are known to decrease HDL cholesterol and cause glucose intolerance, while estrogens may create a state of hyperinsulinism. Oral contraceptives have been shown to increase blood pressure among users (see section 9 in WARNINGS ). Similar effects on risk factors have been associated with an increased risk of heart disease.
Oral contraceptives must be used with caution in women with cardiovascular disease risk factors. b. Venous Thrombosis and Thromboembolism An incre… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS An increased risk of the following serious adverse reactions (see WARNINGS section for additional information) has been associated with the use of oral contraceptives: Thromboembolic and thrombotic disorders and other vascular problems (including thrombophlebitis and venous thrombosis with or without pulmonary embolism, mesenteric thrombosis, arterial thromboembolism, myocardial infarction, cerebral hemorrhage, cerebral thrombosis), carcinoma of the reproductive organs and breasts, hepatic neoplasia (including hepatic adenomas or benign liver tumors), ocular lesions (including retinal vascular thrombosis), gallbladder disease, carbohydrate and lipid effects, elevated blood pressure, and headache including migraine.
The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug related (alphabetically listed): Acne Amenorrhea Anaphylactic/anaphylactoid reactions, including urticaria, angioedema, and severe reactions with respiratory and circulatory symptoms. Breast changes: tenderness, pain, enlargement, secretion Budd-Chiari syndrome Cervical erosion and secretion, change in Cholestatic jaundice Chorea, exacerbation of Colitis Contact lenses, intolerance to Corneal curvature (steepening), change in Dizziness Edema/fluid retention Erythema multiforme Erythema nodosum Gastrointestinal symptoms (such as abdominal pain, cramps, and bloating) Hirsutism Infertility after discontinuation of treatment, temporary Lactation, diminution in, when given immediately postpartum Libido, change in Melasma/chloasma which may persist Menstrual flow, change in Mood changes, including depression Nausea Nervousness Pancreatitis Porphyria, exacerbation of Rash (allergic) Scalp hair, loss of Serum folate levels, decrease in Spotting Systemic lupus erythematosus, exacerbation of Unscheduled bleeding Vaginitis, including candidiasis Varicose veins, aggravation of Vomiting Weight or appetite (increase or decrease), change in The following adverse reactions have been reported in users of oral contraceptives: Cataracts Cystitis-like syndrome Dysmenorrhea Hemolytic uremic syndrome Hemorrhagic eruption Optic neuritis, which may lead to partial or complete loss of vision Premenstrual syndrome Renal function, impaired Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 to 1.12 (Figure III).
Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure III). One of these studies reported no association between breast cancer risk and COC use. The other two studies found an increased relative risk of 1.19 to 1.33 with current or recent use.
Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8 to 10 years of COC use. Figure III: Risk of Breast Cancer with Combined Oral Contraceptive Use RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs. Figure III: Risk of Breast Cancer with Combined Oral Contraceptive Use
🔄 Drug Interactions ▾
9. Drug Interactions Changes in Contraceptive Effectiveness Associated with Coadministration of Other Products: Contraceptive effectiveness may be reduced when hormonal contraceptives are coadministered with antibiotics, anticonvulsants, and other drugs that increase the metabolism of contraceptive steroids. This could result in unintended pregnancy or breakthrough bleeding.
Examples include rifampin, rifabutin, barbiturates, primidone, phenylbutazone, phenytoin, dexamethasone, carbamazepine, felbamate, oxcarbazepine, topiramate, griseofulvin, and modafinil. In such cases a back-up nonhormonal method of birth control should be considered. Several cases of contraceptive failure and breakthrough bleeding have been reported in the literature with concomitant administration of antibiotics such as ampicillin and other penicillins, and tetracyclines.
However, clinical pharmacology studies investigating drug interactions between combined oral contraceptives and these antibiotics have reported inconsistent results. Several of the anti-HIV protease inhibitors have been studied with co-administration of oral combination hormonal contraceptives; significant changes (increase and decrease) in the plasma levels of the estrogen and progestin have been noted in some cases. The safety and efficacy of oral contraceptive products may be affected with coadministration of anti-HIV protease inhibitors.
Healthcare providers should refer to the label of the individual anti-HIV protease inhibitors for further drug-drug interaction information. Herbal products containing St. John’s Wort ( Hypericum perforatum ) may induce hepatic enzymes (cytochrome P 450) and p-glycoprotein transporter and may reduce the effectiveness of contraceptive steroids.
This may also result in breakthrough bleeding. Increase in Plasma Levels Associated with Co-Administered Drugs Co-administration of atorvastatin and certain oral contraceptives containing ethinyl estradiol increases AUC values for ethinyl estradiol by approximately 20%. Ascorbic acid and acetaminophen increase the bioavailability of ethinyl estradiol since these drugs act as competitive inhibitors for sulfation of ethinyl estradiol in the gastrointestinal wall, a known pathway of elimination for ethinyl estradiol.
CYP 3A4 inhibitors such as indinavir, itraconazole, ketoconazole, fluconazole, and troleandomycin may increase plasma hormone levels. Troleandomycin may also increase the risk of intrahepatic cholestasis during coadministration with combination oral contraceptives. Changes in Plasma Levels of Co-Administered Drugs Combination hormonal contraceptives containing some synthetic estrogens (e.g., ethinyl estradiol) may inhibit the metabolism of other compounds.
Increased plasma concentrations of cyclosporine, prednisolone and other corticosteroids, and theophylline have been reported with concomitant administration of oral contraceptives. Decreased plasma concentrations of acetaminophen and increased clearance of temazepam, salicylic acid, morphine, and clofibric acid, due to induction of conjugation (particularly glucuronidation), have been noted when these drugs were administered with oral contraceptives. The prescribing information of concomitant medications should be consulted to identify potential interactions.
Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Do not co-administer Afirmelle with HCV drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to potential for ALT elevations (see WARNINGS, RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ).
🤰 Pregnancy ▾
12. Pregnancy Pregnancy Category X. See CONTRAINDICATIONS and WARNINGS sections.
🧒 Pediatric Use ▾
14. Pediatric Use Safety and efficacy of Afirmelle tablets have been established in women of reproductive age. Safety and efficacy are expected to be the same for postpubertal adolescents under the age of 16 and for users 16 years and older. Use of Afirmelle before menarche is not indicated.
🧓 Geriatric Use ▾
15. Geriatric Use Afirmelle has not been studied in women over 65 years of age and is not indicated in this population.
🆘 Overdosage ▾
OVERDOSAGE Symptoms of oral contraceptive overdosage in adults and children may include nausea, vomiting, and drowsiness/fatigue; withdrawal bleeding may occur in females. There is no specific antidote and further treatment of overdose, if necessary, is directed to the symptoms. NONCONTRACEPTIVE HEALTH BENEFITS The following noncontraceptive health benefits related to the use of oral contraceptives are supported by epidemiological studies which largely utilized oral-contraceptive formulations containing doses exceeding 0.035 mg of ethinyl estradiol or 0.05 mg of mestranol.
Effects on menses: Increased menstrual cycle regularity Decreased blood loss and decreased incidence of iron-deficiency anemia Decreased incidence of dysmenorrhea Effects related to inhibition of ovulation: Decreased incidence of functional ovarian cysts Decreased incidence of ectopic pregnancies Effects from long-term use: Decreased incidence of fibroadenomas and fibrocystic disease of the breast Decreased incidence of acute pelvic inflammatory disease Decreased incidence of endometrial cancer Decreased incidence of ovarian cancer
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mode of Action Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation). Pharmacokinetics Absorption No specific investigation of the absolute bioavailability of Afirmelle in humans has been conducted.
However, literature indicates that levonorgestrel is rapidly and completely absorbed after oral administration (bioavailability about 100%) and is not subject to first-pass metabolism. Ethinyl estradiol is rapidly and almost completely absorbed from the gastrointestinal tract but, due to first-pass metabolism in gut mucosa and liver, the bioavailability of ethinyl estradiol is between 38% and 48%. After a single dose of Afirmelle to 22 women under fasting conditions, maximum serum concentrations of levonorgestrel are 2.8 ± 0.9 ng/mL (mean ± SD) at 1.6 ± 0.9 hours.
At steady state, attained from day 19 onwards, maximum levonorgestrel concentrations of 6.0 ± 2.7 ng/mL are reached at 1.5 ± 0.5 hours after the daily dose. The minimum serum levels of levonorgestrel at steady state are 1.9 ± 1.0 ng/mL. Observed levonorgestrel concentrations increased from day 1 (single dose) to days 6 and 21 (multiple doses) by 34% and 96%, respectively (Figure 1).
Unbound levonorgestrel concentrations increased from day 1 to days 6 and 21 by 25% and 83%, respectively. The kinetics of total levonorgestrel are non-linear due to an increase in binding of levonorgestrel to sex hormone binding globulin (SHBG), which is attributed to increased SHBG levels that are induced by the daily administration of ethinyl estradiol. Following a single dose, maximum serum concentrations of ethinyl estradiol of 62 ± 21 pg/mL are reached at 1.5 ± 0.5 hours.
At steady state attained from at least day 6 onwards, maximum concentrations of ethinyl estradiol were 77 ± 30 pg/mL and were reached at 1.3 ± 0.7 hours after the daily dose. The minimum serum levels of ethinyl estradiol at steady state are 10.5 ± 5.1 pg/mL. Ethinyl estradiol concentrations did not increase from days 1 to 6, but did increase by 19% from days 1 to 21 (FIGURE I).
FIGURE I: Mean (SE) levonorgestrel and ethinyl estradiol serum concentrations in 22 subjects receiving Afirmelle (100 mcg levonorgestrel and 20 mcg ethinyl estradiol) TABLE I provides a summary of levonorgestrel and ethinyl estradiol pharmacokinetic parameters. TABLE I: MEAN (SD) PHARMACOKINETIC PARAMETERS OF AFIRMELLE OVER A 21-DAY DOSING PERIOD Levonorgestrel Day C max ng/mL T max h AUC ng . h/mL CL/F mL/h/kg Vλz/F L/kg SHBG nmol/L 1 2.75 (0.88) 1.6 (0.9) 35.2 (12.8) 53.7 (20.8) 2.66 (1.09) 57 (18) 6 4.52 (1.79) 1.5 (0.7) 46.0 (18.8) 40.8 (14.5) 2.05 (0.86) 81 (25) 21 6.00 (2.65) 1.5 (0.5) 68.3 (32.5) 28.4 (10.3) 1.43 (0.62) 93 (40) Unbound Levonorgestrel pg/mL h pg . h/mL L/h/kg L/kg fu % 1 51.2 (12.9) 1.6 (0.9) 654 (201) 2.79 (0.97) 135.9 (41.8) 1.92 (0.30) 6 77.9 (22.0) 1.5 (0.7) 794 (240) 2.24 (0.59) 112.4 (40.5) 1.80 (0.24) 21 103.6 (36.9) 1.5 (0.5) 1177 (452) 1.57 (0.49) 78.6 (29.7) 1.78 (0.19) Ethinyl Estradiol pg/mL h pg . h/mL mL/h/kg L/kg 1 62.0 (20.5) 1.5 (0.5) 653 (227) 567 (204) 14.3 (3.7) 6 76.7 (29.9) 1.3 (0.7) 604 (231) 610 (196) 15.5 (4.0) 21 82.3 (33.2) 1.4 (0.6) 776 (308) 486 (179) 12.4 (4.1) Distribution Levonorgestrel in serum is primarily bound to SHBG.
Ethinyl estradiol is about 97% bound to plasma albumin. Ethinyl estradiol does not bind to SHBG, but induces SHBG synthesis. Metabolism Levonorgestrel: The most important metabolic pathway occurs in the reduction of the Δ4-3-oxo group and hydroxylation at positions 2α, 1β, and 16β, followed by conjugation.
Most of the metabolites that circulate in the blood are sulfates of 3α,5β-tetrahydro-levonorgestrel, while excretion occurs predominantly in the form of glucuronides. Some of the pa… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Afirmelle TM (Levonorgestrel and ethinyl estradiol tablets USP) 0.1 mg/0.02 mg is available in cartons of 3 pouches and 6 pouches, each containing 28 tablets: 21 active tablets: White to off-white, round, biconvex, beveled-edge tablets, debossed with “S” on one side and “59” on other side of the tablet. 7 inert tablets: Green, round, mottled, biconvex, beveled-edge uncoated tablets, debossed with “S” on one side and “61” on other side of the tablet. 1 Pouch of 28 tablets NDC 65862-849-28 Carton of 3 Pouches NDC 65862-849-88 Carton of 6 Pouches NDC 65862-849-92 Store at 20º to 25°C (68° to 77º F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Each active, white tablet (21) contains 0.1 mg of levonorgestrel USP, d(-)-13β-ethyl-17α-ethinyl-17β-hydroxygon-4-en-3-one, a totally synthetic progestogen, and 0.02 mg of ethinyl estradiol USP, 17α-ethinyl-1,3,5(10)-estratriene-3, 17β-diol. The inactive ingredients present are croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and povidone. Each inactive, green tablet (7) contains the following inactive ingredients: croscarmellose sodium, FD & C Blue No.
2 Aluminum Lake, ferric oxide (sicovit yellow 10), lactose anhydrous, magnesium stearate, microcrystalline cellulose, and povidone. Chemical Structure
💬 Information for Patients ▾
16. Information for the Patient See Patient Labeling Printed Below.
⚠️ Precautions ▾
PRECAUTIONS 1. General Patients should be counseled that oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. 2.
Physical Examination and Follow-Up A periodic personal and family medical history and complete physical examination are appropriate for all women, including women using oral contraceptives. The physical examination, however, may be deferred until after initiation of oral contraceptives if requested by the woman and judged appropriate by the clinician. The physical examination should include special reference to blood pressure, breasts, abdomen, and pelvic organs, including cervical cytology, and relevant laboratory tests.
In case of undiagnosed, persistent, or recurrent abnormal vaginal bleeding, appropriate diagnostic measures should be conducted to rule out malignancy. Women with a strong family history of breast cancer or who have breast nodules should be monitored with particular care. 3.
Lipid Disorders Women who are being treated for hyperlipidemias should be followed closely if they elect to use oral contraceptives. Some progestogens may elevate LDL levels and may render the control of hyperlipidemias more difficult. (See WARNINGS, 1a ., 1d ., and 8 .) A small proportion of women will have adverse lipid changes while taking oral contraceptives.
Nonhormonal contraception should be considered in women with uncontrolled dyslipidemias. Persistent hypertriglyceridemia may occur in a small population of combination oral contraceptive users. Elevations of plasma triglycerides may lead to pancreatitis and other complications.
4. Liver Function If jaundice develops in any woman receiving such drugs, the medication should be discontinued. Steroid hormones may be poorly metabolized in patients with impaired liver function.
5. Fluid Retention Oral contraceptives may cause some degree of fluid retention. They should be prescribed with caution, and only with careful monitoring, in patients with conditions which might be aggravated by fluid retention.
6. Emotional Disorders Patients becoming significantly depressed while taking oral contraceptives should stop the medication and use an alternate method of contraception in an attempt to determine whether the symptom is drug related. Women with a history of depression should be carefully observed and the drug discontinued if depression recurs to a serious degree.
7. Contact Lenses Contact-lens wearers who develop visual changes or changes in lens tolerance should be assessed by an ophthalmologist. 8.
Gastrointestinal Diarrhea and/or vomiting may reduce hormone absorption resulting in decreased serum concentrations. 9. Drug Interactions Changes in Contraceptive Effectiveness Associated with Coadministration of Other Products: Contraceptive effectiveness may be reduced when hormonal contraceptives are coadministered with antibiotics, anticonvulsants, and other drugs that increase the metabolism of contraceptive steroids.
This could result in unintended pregnancy or breakthrough bleeding. Examples include rifampin, rifabutin, barbiturates, primidone, phenylbutazone, phenytoin, dexamethasone, carbamazepine, felbamate, oxcarbazepine, topiramate, griseofulvin, and modafinil. In such cases a back-up nonhormonal method of birth control should be considered.
Several cases of contraceptive failure and breakthrough bleeding have been reported in the literature with concomitant administration of antibiotics such as ampicillin and other penicillins, and tetracyclines. However, clinical pharmacology studies investigating drug interactions between combined oral contraceptives and these antibiotics have reported inconsistent results. Several of the anti-HIV protease inhibitors have been studied with co-administration of oral combination hormonal contraceptives; significant changes (increase and decrease) in the plasma levels of the estrogen an… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
13. Nursing Mothers Small amounts of oral-contraceptive steroids and/or metabolites have been identified in the milk of nursing mothers, and a few adverse effects on the child have been reported, including jaundice and breast enlargement. In addition, combination oral contraceptives given in the postpartum period may interfere with lactation by decreasing the quantity and quality of breast milk.
If possible, the nursing mother should be advised not to use combination oral contraceptives but to use other forms of contraception until she has completely weaned her child.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
11. Carcinogenesis See WARNINGS section.
📄 Patient Package Insert ▾
Brief Summary Patient Package Insert This product (like all oral contraceptives) is intended to prevent pregnancy. Oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. Oral contraceptives, also known as “birth-control pills” or “the pill,” are taken to prevent pregnancy, and when taken correctly, have a failure rate of approximately 1.0% per year (1 pregnancy per 100 women per year of use) when used without missing any pills.
The average failure rate of large numbers of pill users is approximately 5% per year (5 pregnancies per 100 women per year of use) when women who miss pills are included. For most women oral contraceptives are also free of serious or unpleasant side effects. However, forgetting to take pills considerably increases the chances of pregnancy.
For the majority of women, oral contraceptives can be taken safely. But there are some women who are at high risk of developing certain serious diseases that can be life-threatening or may cause temporary or permanent disability or death. The risks associated with taking oral contraceptives increase significantly if you: smoke. have high blood pressure, diabetes, high cholesterol, or a tendency to form blood clots. have or have had clotting disorders, heart attack, stroke, angina pectoris, cancer of the breast or sex organs, jaundice, malignant or benign liver tumors, or major surgery with prolonged immobilization. have headaches with neurological symptoms.
You should not take the pill if you suspect you are pregnant or have unexplained vaginal bleeding. Although cardiovascular disease risks may be increased with oral-contraceptive use after age 40 in healthy, nonsmoking women, there are also greater potential health risks associated with pregnancy in older women. Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels from oral-contraceptive use.
This risk increases with age and with the amount of smoking (15 or more cigarettes per day has been associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should not smoke. Most side effects of the pill are not serious.
The most common such effects are nausea, vomiting, bleeding between menstrual periods, weight gain, breast tenderness, and difficulty wearing contact lenses. These side effects, especially nausea and vomiting, may subside within the first three months of use. The serious side effects of the pill occur very infrequently, especially if you are in good health and do not smoke.
However, you should know that the following medical conditions have been associated with or made worse by the pill: Blood clots in the legs (thrombophlebitis) and lungs (pulmonary embolism), blockage or rupture of a blood vessel in the brain (stroke), blockage of blood vessels in the heart (heart attack and angina pectoris) or other organs of the body. As mentioned above, smoking increases the risk of heart attacks and strokes and subsequent serious medical consequences. Women with migraine also may be at increased risk of stroke with pill use.
Liver tumors, which may rupture and cause severe bleeding. A possible but not definite association has been found with the pill and liver cancer. However, liver cancers are extremely rare.
The chance of developing liver cancer from using the pill is thus even rarer. High blood pressure, although blood pressure usually returns to normal when the pill is stopped. The symptoms associated with these serious side effects are discussed in the detailed leaflet given to you with your supply of pills.
Notify your health-care provider if you notice any unusual physical disturbances while taking the pill. In addition, drugs such as rifampin, as well as some anticonvulsants and some antibiotics, herbal preparations containing St. John’s Wort ( Hyper… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.1 mg/0.02 mg (28 Tablets Pouch) 28-DAY REGIMEN NDC 65862-849-28 Afirmelle TM (Levonorgestrel and Ethinyl Estradiol Tablets USP) 0.1 mg/0.02 mg Each white to off-white tablet (21) contains: 0.1 mg levonorgestrel USP and 0.02 mg ethinyl estradiol USP. Each green tablet (7) contains inert ingredients. This product (like all oral contraceptives) is intended to prevent pregnancy.
It does not protect against HIV infection (AIDS) and other sexually transmitted diseases. Rx only Contains 1 Blister Card of 28 Tablets AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.1 mg/0.02 mg (28 Tablets Pouch)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.1 mg/0.02 mg (Contains 6 Pouches of 28 Tablets Each) 28-DAY REGIMEN NDC 65862-849-92 Afirmelle TM (Levonorgestrel and Ethinyl Estradiol Tablets USP) 0.1 mg/0.02 mg Each white to off-white tablet (21) contains: 0.1 mg levonorgestrel USP and 0.02 mg ethinyl estradiol USP. Each green tablet (7) contains inert ingredients. This Product (like all oral contraceptives) is intended to prevent pregnancy.
It does not protect against HIV infection (AIDS) and other sexually transmitted diseases. Rx only Contains 6 Pouches of 28 Tablets Each Aurobindo PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.1 mg/0.02 mg (Contains 6 Pouches of 28 Tablets Each)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |