
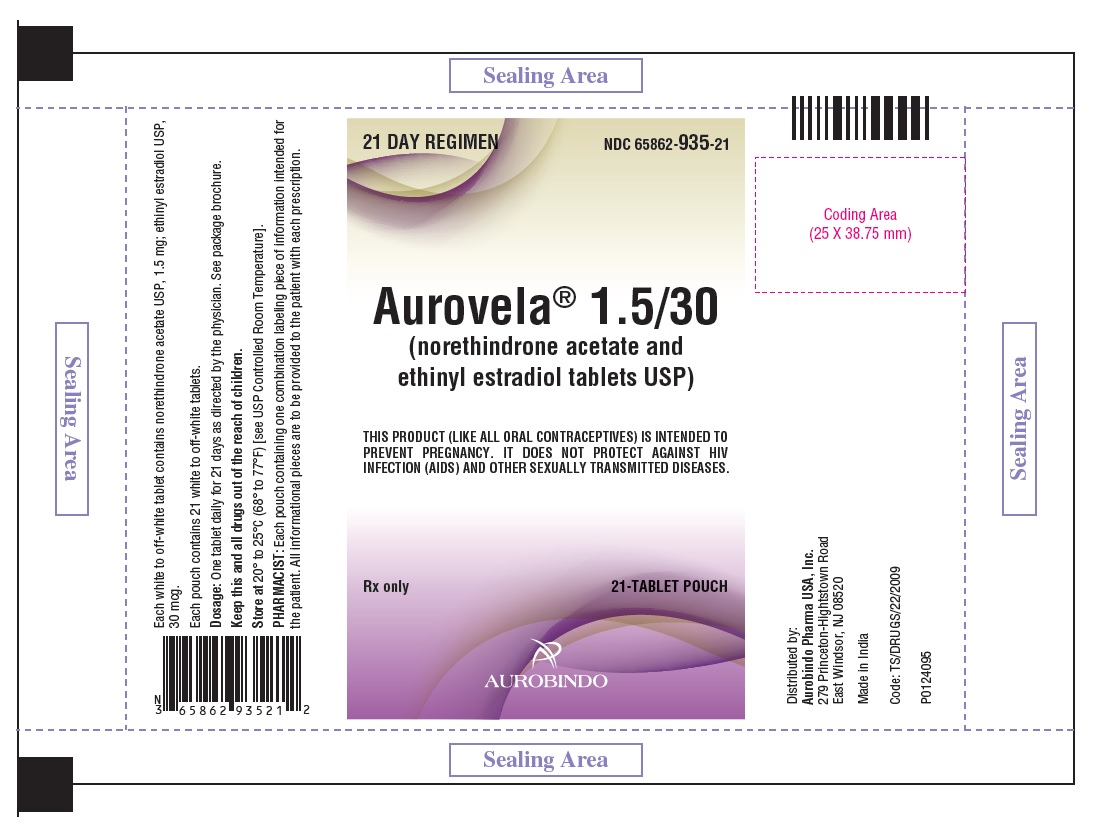
Aurovela 1.5/30 Norethindrone Acetate and Ethinyl Estradiol 1.5 mg; 30 ug Tablet, 105-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and norethindrone (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work mainly by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H4N855PNZ1
Alpha-tocopherol is a form of vitamin E, a fat-soluble antioxidant derived from natural or synthetic sources. In medicines, it prevents oils and fats from breaking down and becoming rancid, protecting the product's stability and shelf life.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Junel 21 Day 1.5 mg/1; 30 ug 00555-9027-42 | Teva | 63 tablets | $0.343 | AB | Availability likely | — |
| Aurovela 1.5/30 1.5 mg/1; 30 ugthis 65862-0935-54 | Aurobindo | 105 tablets | — | AB | FDA listed | — |
| Loestrin 21 Day 1.5 mg/1; 30 ug 51285-0127-97 | Teva | 105 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0935-54 You're viewing this | 5 POUCH in 1 CARTON (65862-935-54) / 1 BLISTER PACK in 1 POUCH / 21 TABLET in 1 BLISTER PACK | — | — | 2017-06-26 | Active |
| 65862-0935-74 | 3 POUCH in 1 CARTON (65862-935-74) / 1 BLISTER PACK in 1 POUCH / 21 TABLET in 1 BLISTER PACK | $0.3427 / ea | $21.59 | 2017-06-26 | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0935-54?
What is the difference between NDC 65862-0935-54 and NDC 65862-0935-74?
What NDC number is used to bill for this package of Aurovela 1.5/30 Norethindrone Acetate and Ethinyl Estradiol 1.5 mg; 30 ug Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs, including Aurovela 1.5/30, are contraindicated in women who are over 35 years of age and smoke (see CONTRAINDICATIONS and WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Aurovela 1.5/30 is indicated for the prevention of pregnancy in women who elect to use oral contraceptives as a method of contraception. Oral contraceptives are highly effective. Table I lists the typical accidental pregnancy rates for users of combination oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, depends upon the reliability with which they are used. Correct and consistent use of methods can result in lower failure rates. TABLE 1 LOWEST EXPECTED AND TYPICAL FAILURE RATES DURING THE FIRST YEAR OF CONTINUOUS USE OF A METHOD Adapted from RA Hatcher et al, Reference 7. *The authors’ best guess of the percentage of women expected to experience an accidental pregnancy among couples who initiate a method (not necessarily for the first time) and who use it consistently and correctly during the first year if they do not stop for any other reason. **This term represents “typical” couples who initiate use of a method (not necessarily for the first time), who experience an accidental pregnancy during the first year if they do not stop use for any other reason. ***N/A-Data not available. % Of Women Experiencing an Unintended Pregnancy in the First Year of Continuous Use Method Lowest Expected* Typical** (No contraception) Oral contraceptives Combined progestin only Diaphragm with spermicidal cream or jelly Spermicides alone (foam, creams, gels, vaginal suppositories, and vaginal film) Vaginal Sponge nulliparous parous Implant Injection: depot medroxyprogesterone acetate IUD progesterone T copper T 380A LNg 20 Condom without spermicides female male Cervical Cap with spermicidal cream or jelly nulliparous parous Periodic abstinence (all methods) Withdrawal Female sterilization Male sterilization (85) 0.1 0.5 6 6 9 20 0.05 0.3 1.5 0.6 0.1 5 3 9 26 1 to 9 4 0.5 0.1 (85) 3 N/A*** N/A*** 20 26 20 40 0.05 0.3 2 0.8 0.1 21 14 20 40 25 19 0.5 0.15
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The blister pack has been designed to make oral contraceptive dosing as easy and as convenient as possible. The tablets are arranged in three rows of seven tablets each, with the days of the week appearing on the blister pack above the first row of tablets. Note: Each blister pack has been preprinted with the days of the week, starting with Sunday, to facilitate a Sunday-Start regimen.
Six different day label stickers have been provided with the Detailed Patient & Brief Summary Patient Package Insert in order to accommodate a Day-1 Start regimen. If the patient is using the Day-1 Start regimen, she should place the self-adhesive day label sticker that corresponds to her starting day over the preprinted days. Important: The patient should be instructed to use an additional method of protection until after the first week of administration in the initial cycle when utilizing the Sunday-Start regimen.
The possibility of ovulation and conception prior to initiation of use should be considered. To achieve maximum contraceptive effectiveness, Aurovela 1.5/30 must be taken exactly as directed and at intervals not exceeding 24 hours. Aurovela 1.5/30 provides the patient with a convenient tablet schedule of “3 weeks on-1 week off”.
Two dosage regimens are described, one of which may be more convenient or suitable than the other for an individual patient. For the initial cycle of therapy, the patient begins her tablets according to the Day-1 Start or Sunday-Start regimen. With either regimen, the patient takes one tablet daily for 21 consecutive days followed by one week of no tablets.
A. Sunday-Start Regimen: The patient begins taking tablets from the top row on the first Sunday after menstrual flow begins. When menstrual flow begins on Sunday, the first tablet is taken on the same day.
The last tablet in the blister pack will then be taken on a Saturday, followed by no tablets for a week (7 days). For all subsequent cycles, the patient then begins a new 21-tablet regimen on the eighth day, Sunday, after taking her last tablet. Following this regimen, of 21 days on-7 days off, the patient will start all subsequent cycles on a Sunday.
B. Day-1 Start Regimen: The first day of menstrual flow is Day 1. The patient places the self-adhesive day label sticker that corresponds to her starting day over the preprinted days on the blister pack.
She starts taking one tablet daily, beginning with the first tablet in the top row. The patient completes her 21-tablet regimen when she has taken the last tablet in the blister pack. She will then take no tablets for a week (7 days).
For all subsequent cycles, the patient begins a new 21-tablet regimen on the eighth day after taking her last tablet, again starting with the first tablet in the top row after placing the appropriate day label sticker over the preprinted days on the blister pack. Following this regimen of 21 days on-7 days off, the patient will start all subsequent cycles on the same day of the week as the first course. Likewise, the interval of no tablets will always start on the same day of the week.
Tablets should be taken regularly with a meal or at bedtime. It should be stressed that efficacy of medication depends on strict adherence to the dosage schedule. Special Notes on Administration Menstruation usually begins two or three days, but may begin as late as the fourth or fifth day, after discontinuing medication.
If spotting occurs while on the usual regimen of one tablet daily, the patient should continue medication without interruption. If the patient forgets to take one or more tablets, the following is suggested: One tablet is missed take tablet as soon as remembered take next tablet at the regular time Two consecutive tablets are missed (week 1 or week 2) take two tablets as soon as remembered take two tablets the next day use another birth control method for seven days following the missed tablets Two consecutive tablets are missed (week 3) Sunday-Start R…
⛔ Contraindications ▾
CONTRAINDICATIONS Oral contraceptives are contraindicated in women who currently have the following conditions: Thrombophlebitis or thromboembolic disorders A past history of deep vein thrombophlebitis or thromboembolic disorders Cerebral vascular or coronary artery disease Current diagnosis of, or history of, breast cancer, which may be hormone sensitive Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Hepatic adenomas or carcinomas Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see Warnings , RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ).
⚠️ Warnings ▾
WARNINGS The use of oral contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as hypertension, hyperlipidemias, obesity, and diabetes. Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks.
The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with higher formulations of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with lower formulations of both estrogens and progestogens remains to be determined. Throughout this labeling, epidemiological studies reported are of two types: retrospective or case control studies and prospective or cohort studies.
Case control studies provide a measure of the relative risk of a disease, namely, a ratio of the incidence of a disease among oral contraceptive users to that among nonusers. The relative risk does not provide information on the actual clinical occurrence of a disease. Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral contraceptive users and nonusers.
The attributable risk does provide information about the actual occurrence of a disease in the population (adapted from References 8 and 9 with the author’s permission). For further information, the reader is referred to a text on epidemiological methods. 1.
Thromboembolic Disorders and Other Vascular Problems a. Myocardial infarction An increased risk of myocardial infarction has been attributed to oral contraceptive use. This risk is primarily in smokers or women with other underlying risk factors for coronary artery disease such as hypertension, hypercholesterolemia, morbid obesity, and diabetes.
The relative risk of heart attack for current oral contraceptive users has been estimated to be two to six (10 to 16). The risk is very low under the age of 30. Smoking in combination with oral contraceptive use has been shown to contribute substantially to the incidence of myocardial infarctions in women in their mid-thirties or older with smoking accounting for the majority of excess cases (17).
Mortality rates associated with circulatory disease have been shown to increase substantially in smokers over the age of 35 and non-smokers over the age of 40 (Table II) among women who use oral contraceptives. Adapted from P.M. Layde and V.
Beral, Reference 18. Oral contraceptives may compound the effects of well-known risk factors, such as hypertension, diabetes, hyperlipidemias, age and obesity (19). In particular, some progestogens are known to decrease HDL cholesterol and cause glucose intolerance, while estrogens may create a state of hyperinsulinism (20 to 24).
Oral contraceptives have been shown to increase blood pressure among users (see section 9 in WARNINGS ). Similar effects on risk factors have been associated with an increased risk of heart disease. Oral contraceptives must be used with caution in women with cardiovascular disease risk factors. b.
Thromboembolism An increased risk of thromboembolic and thrombotic disease associated with the use of oral contraceptives is well established. Case control studies have found the relative risk of users compared to non-users to be 3 for the first episode of superficial venous thrombosis, 4 to 11 for deep vein thrombosis or pulmonary embolism, and 1.5 to 6 for women with predisposing conditions for venous thromboembolic disease (9,10, 25 to 30). Cohort studies have shown the relative risk to be somewhat lower, about 3 for new cases and about 4.5 for new cases requ…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives (see WARNINGS section): Thrombophlebitis Arterial thromboembolism Pulmonary embolism Myocardial infarction Cerebral hemorrhage Cerebral thrombosis Hypertension Gallbladder disease Hepatic adenomas or benign liver tumors Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 to 1.12 (Figure 1) (70 to 74).
Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 1) (70,73,75). One of these studies reported no association between breast cancer risk and COC use. The other two studies found an increased relative risk of 1.19 to 1.33 with current or recent use.
Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8 to 10 years of COC use. FIGURE 1: RELEVANT STUDIES OF RISK OF BREAST CANCER WITH COMBINED ORAL CONTRACEPTIVES RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs. There is evidence of an association between the following conditions and the use of oral contraceptives, although additional confirmatory studies are needed: Mesenteric thrombosis Retinal thrombosis The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug-related: Nausea Vomiting Gastrointestinal symptoms (such as abdominal cramps and bloating) Breakthrough bleeding Spotting Change in menstrual flow Amenorrhea Temporary infertility after discontinuation of treatment Edema Melasma which may persist Breast changes: tenderness, enlargement, secretion Change in weight (increase or decrease) Change in cervical erosion and secretion Diminution in lactation when given immediately postpartum Cholestatic jaundice Migraine Rash (allergic) Depression Reduced tolerance to carbohydrates Vaginal candidiasis Change in corneal curvature (steepening) Intolerance to contact lenses The following adverse reactions have been reported in users of oral contraceptives and the association has been neither confirmed nor refuted: Pre-menstrual syndrome Cataracts Changes in appetite Cystitis-like syndrome Headache Nervousness Dizziness Hirsutism Loss of scalp hair Erythema multiforme Erythema nodosum Hemorrhagic eruption Vaginitis Porphyria Impaired renal function Hemolytic uremic syndrome Budd-Chiari syndrome Acne Changes in libido Colitis FIGURE 1: RELEVANT STUDIES OF RISK OF BREAST CANCER WITH COMBINED ORAL CONTRACEPTIVES
🔄 Drug Interactions ▾
7. Drug Interactions Effects of Other Drugs on Oral Contraceptives (69) Rifampin: Metabolism of both norethindrone and ethinyl estradiol is increased by rifampin. A reduction in contraceptive effectiveness and increased incidence of breakthrough bleeding and menstrual irregularities have been associated with concomitant use of rifampin.
Anticonvulsants: Anticonvulsants such as phenobarbital, phenytoin, and carbamazepine, have been shown to increase the metabolism of ethinyl estradiol and/or norethindrone, which could result in a reduction in contraceptive effectiveness. Troglitazone: Administration of troglitazone with an oral contraceptive containing ethinyl estradiol and norethindrone reduced the plasma concentrations of both by approximately 30%, which could result in a reduction in contraceptive effectiveness. Antibiotics: Pregnancy while taking oral contraceptives has been reported when the oral contraceptives were administered with antimicrobials such as ampicillin, tetracycline, and griseofulvin.
However, clinical pharmacokinetic studies have not demonstrated any consistent effect of antibiotics (other than rifampin) on plasma concentrations of synthetic steroids. Atorvastatin: Coadministration of atorvastatin and an oral contraceptive increased AUC values for norethindrone and ethinyl estradiol by approximately 30% and 20%, respectively. Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Co-administration of Aurovela 1.5/30 with HCV drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir is contraindicated due to potential for ALT elevations (see Warnings, RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ).
Co-administration of Aurovela 1.5/30 and glecaprevir/pibrentasvir is not recommended due to potential for ALT elevations. Other: Ascorbic acid and acetaminophen may increase plasma ethinyl estradiol concentrations, possibly by inhibition of conjugation. A reduction in contraceptive effectiveness and increased incidence of breakthrough bleeding has been suggested with phenylbutazone.
Effects of Oral Contraceptives on Other Drugs Oral contraceptive combinations containing ethinyl estradiol may inhibit the metabolism of other compounds. Increased plasma concentrations of cyclosporine, prednisolone, and theophylline have been reported with concomitant administration of oral contraceptives. In addition, oral contraceptives may induce the conjugation of other compounds.
Decreased plasma concentrations of acetaminophen and increased clearance of temazepam, salicylic acid, morphine, and clofibric acid have been noted when these drugs were administered with oral contraceptives. 8. Interactions With Laboratory Tests Certain endocrine and liver function tests and blood components may be affected by oral contraceptives: a.
Increased prothrombin and factors VII, VIII, IX, and X; decreased antithrombin 3; increased norepinephrine-induced platelet aggregability. b. Increased thyroid binding globulin (TBG) leading to increased circulating total thyroid hormone, as measured by protein-bound iodine (PBI), T 4 by column or by radioimmunoassay. Free T 3 resin uptake is decreased, reflecting the elevated TBG; free T 4 concentration is unaltered. c.
Other binding proteins may be elevated in serum. d. Sex-binding globulins are increased and result in elevated levels of total circulating sex steroids and corticoids; however, free or biologically active levels remain unchanged. e. Triglycerides may be increased. f.
Glucose tolerance may be decreased. g. Serum folate levels may be depressed by oral contraceptive therapy. This may be of clinical significance if a woman becomes pregnant shortly after discontinuing oral contraceptives.
🤰 Pregnancy ▾
10. Pregnancy Discontinue Aurovela 1.5/30 if pregnancy occurs because there is no reason to use COCs in pregnancy. See WARNINGS section.
🧒 Pediatric Use ▾
12. Pediatric Use Safety and efficacy of Aurovela 1.5/30 has been established in women of reproductive age. Safety and efficacy are expected to be the same for postpubertal adolescents under the age of 16 and for users 16 years and older. Use of this product before menarche is not indicated.
🆘 Overdosage ▾
OVERDOSAGE Serious ill effects have not been reported following acute ingestion of large doses of oral contraceptives by young children. Overdosage may cause nausea, and withdrawal bleeding may occur in females. NON-CONTRACEPTIVE HEALTH BENEFITS The following non-contraceptive health benefits related to the use of oral contraceptives are supported by epidemiological studies which largely utilized oral contraceptive formulations containing estrogen doses exceeding 0.035 mg of ethinyl estradiol or 0.05 mg of mestranol (76 to 81).
Effects on menses: Increased menstrual cycle regularity Decreased blood loss and decreased incidence of iron deficiency anemia Decreased incidence of dysmenorrhea Effects related to inhibition of ovulation: Decreased incidence of functional ovarian cysts Decreased incidence of ectopic pregnancies Effects from long-term use: Decreased incidence of fibroadenomas and fibrocystic disease of the breast Decreased incidence of acute pelvic inflammatory disease Decreased incidence of endometrial cancer Decreased incidence of ovarian cancer
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation). Pharmacokinetics The pharmacokinetics of Aurovela 1.5/30 have not been characterized; however, the following pharmacokinetic information regarding norethindrone acetate and ethinyl estradiol is taken from the literature.
Absorption Norethindrone acetate appears to be completely and rapidly deacetylated to norethindrone after oral administration, since the disposition of norethindrone acetate is indistinguishable from that of orally administered norethindrone (1). Norethindrone acetate and ethinyl estradiol are subject to first-pass metabolism after oral dosing, resulting in an absolute bioavailability of approximately 64% for norethindrone and 43% for ethinyl estradiol (1 to 3). Distribution Volume of distribution of norethindrone and ethinyl estradiol ranges from 2 to 4 L/kg (1 to 3).
Plasma protein binding of both steroids is extensive (greater than 95%); norethindrone binds to both albumin and sex hormone binding globulin, whereas ethinyl estradiol binds only to albumin (4). Metabolism Norethindrone undergoes extensive biotransformation, primarily via reduction, followed by sulfate and glucuronide conjugation. The majority of metabolites in the circulation are sulfates, with glucuronides accounting for most of the urinary metabolites (5).
A small amount of norethindrone acetate is metabolically converted to ethinyl estradiol. Ethinyl estradiol is also extensively metabolized, both by oxidation and by conjugation with sulfate and glucuronide. Sulfates are the major circulating conjugates of ethinyl estradiol and glucuronides predominate in urine.
The primary oxidative metabolite is 2-hydroxy ethinyl estradiol, formed by the CYP3A4 isoform of cytochrome P450. Part of the first-pass metabolism of ethinyl estradiol is believed to occur in gastrointestinal mucosa. Ethinyl estradiol may undergo enterohepatic circulation (6).
Excretion Norethindrone and ethinyl estradiol are excreted in both urine and feces, primarily as metabolites (5, 6). Plasma clearance values for norethindrone and ethinyl estradiol are similar (approximately
0.4L/hr/kg) (1 to 3). Special Population Race: The effect of race on the disposition of Aurovela 1.5/30 has not been evaluated. Renal Insufficiency The effect of renal disease on the disposition of Aurovela 1.5/30 has not been evaluated.
In premenopausal women with chronic renal failure undergoing peritoneal dialysis who received multiple doses of an oral contraceptive containing ethinyl estradiol and norethindrone, plasma ethinyl estradiol concentrations were higher and norethindrone concentrations were unchanged compared to concentrations in premenopausal women with normal renal function. Hepatic Insufficiency The effect of hepatic disease on the disposition of Aurovela 1.5/30 has not been evaluated. However, ethinyl estradiol and norethindrone may be poorly metabolized in patients with impaired liver function.
Drug-Drug Interactions Numerous drug-drug interactions have been reported for oral contraceptives. A summary of these is found under PRECAUTIONS , Drug Interactions .
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Aurovela ® 1.5/30 (norethindrone acetate and ethinyl estradiol tablets USP, 1.5 mg/30 mcg) is white to off-white, round, flat-faced, beveled-edge, uncoated tablets, debossed with ‘S’ on one side and ‘69’ on other side of the tablet. 1 pouch of 21 tablets NDC 65862-935-21 Carton of 3 Pouches NDC 65862-935-74 Carton of 5 Pouches NDC 65862-935-54 Store at 20 o to 25 o C (68 o to 77 o F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Aurovela 1.5/30 is progestogen-estrogen combination. Each white to off-white tablet contains norethindrone acetate USP (17 alpha-ethinyl-19-nortestosterone acetate), 1.5 mg; ethinyl estradiol USP (17 alpha -ethinyl-1,3,5(10)-estratriene-3, 17 beta-diol), 30 mcg. Each white to off-white tablet contains the following inactive ingredients: compressible sugar, croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone, and vitamin E.
The structural formulas are as follows: Meets USP Dissolution Test 2. Norethindrone Chemical Structure Ethinylestradiol Chemical Structure
💬 Information for Patients ▾
PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( PATIENT PACKAGE INSERT BRIEF SUMMARY and DETAILED PATIENT PACKAGE INSERT ). Counsel patients that cigarette smoking increases the risk of serious cardiovascular events from COC use, and that women who are over 35 years old and smoke should not use COCs (see BOXED WARNING and CONTRAINDICATIONS ). Counsel patients that the increased risk of venous thromboembolism compared to non-users of CHCs is greatest after initially starting a CHC or restarting (following a 4-week or greater interruption in intake) the same or a different CHC (see WARNINGS ).
Counsel patients that this product does not protect against HIV-infection (AIDS) and other sexually transmitted infections. Counsel patients to take one tablet daily by mouth at the same time every day. Instruct patients what to do in the event pills are missed (see DOSAGE AND ADMINISTRATION ).
Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs (see PRECAUTIONS ). Counsel patients who are breastfeeding or who desire to breastfeed that COCs may reduce breast milk production. This is less likely to occur if breastfeeding is well established (see PRECAUTIONS ).
Counsel any patient who starts Aurovela 1.5/30 postpartum, and who has not yet had a period, to use an additional method of contraception until she has taken a light-orange tablet for 7 consecutive days (see DOSAGE AND ADMINISTRATION ). Counsel patients that amenorrhea may occur. Pregnancy should be considered in the event of amenorrhea, and should be ruled out if amenorrhea is associated with symptoms of pregnancy, such as morning sickness or unusual breast tenderness (see WARNINGS ).
Counsel patients with a history of depression that depression may reoccur. Women should contact their healthcare provider if depression occurs (see WARNINGS ).