
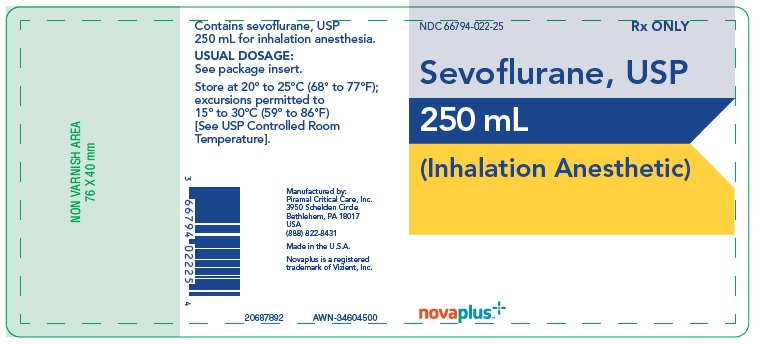
Sevoflurane 1 mL/mL Liquid, 250 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the General Anesthetic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Sevoflurane is the anesthetic gas your surgical team will use to put you into a deep sleep for your operation and keep you there safely throughout. It's inhaled through a mask or b...
- What exactly is sevoflurane and why is my surgical team using it?
- Nausea and vomiting are the most common side effects — they happen in a significant number of patients after general anesthesia with sevoflurane. You may also feel drowsy, dizzy, o...
- Will I feel sick or groggy when I wake up?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Sevoflurane — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ultane 250 mL/250mL 00074-4456-04 | AbbVie | 250 ml | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 00527-6123-74 | Lannett | 1 bottle | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 00781-6160-86 | Sandoz | 6 bottles | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 10019-0651-64 | Baxter | 6 bottles | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 10019-0653-64 | Baxter | 6 bottles | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 10019-0655-06 | Baxter | 6 bottles | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 10019-0657-06 | Baxter | 6 bottles | — | AN | FDA listed | — |
| Sevoflurane 1 mL/mL 12164-0005-25 | Halocarbon | 250 ml | — | AN | FDA listed | — |
| Sevoflurane 250 mL/250mL 42677-0308-01 | Shandong | 1 bottle | — | AN | FDA listed | — |
| Sojourn 1 mL/mL 66794-0012-10 | Piramal | 100 ml | — | AN | FDA listed | — |
| Sevoflurane 1 mL/mL 66794-0015-10 | Piramal | 100 ml | — | — | FDA listed | — |
| Sevoflurane 1 mL/mLthis 66794-0022-25 | Piramal | 250 ml | — | AN | FDA listed | — |
| Sevoflurane 1 mL/mL 72162-2245-02 | Bryant | 250 ml | — | AN | FDA listed | — |
| Sevoflurane, (Volatile for Inhalation) 250 mL/250mL 83301-0070-01 | Mullan | 1 bottle | — | AN | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 66794-0022-25 You're viewing this | 250 mL in 1 BOTTLE (66794-022-25) | 2020-10-01 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Sevoflurane, USP is indicated for induction and maintenance of general anesthesia in adult and pediatric patients for inpatient and outpatient surgery. Sevoflurane, USP should be administered only by persons trained in the administration of general anesthesia. Facilities for maintenance of a patent airway, artificial ventilation, oxygen enrichment, and circulatory resuscitation must be immediately available.
Since level of anesthesia may be altered rapidly, only vaporizers producing predictable concentrations of sevoflurane should be used.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The concentration of sevoflurane being delivered from a vaporizer should be known. This may be accomplished by using a vaporizer calibrated specifically for sevoflurane. The administration of general anesthesia must be individualized based on the patient's response.
Replacement of Desiccated CO 2 Absorbents When a clinician suspects that the CO 2 absorbent may be desiccated, it should be replaced. The exothermic reaction that occurs with sevoflurane and CO 2 absorbents is increased when the CO 2 absorbent becomes desiccated, such as after an extended period of dry gas flow through the CO 2 absorbent canisters (see PRECAUTIONS ). Pre-anesthetic Medication No specific premedication is either indicated or contraindicated with sevoflurane.
The decision as to whether or not to premedicate and the choice of premedication is left to the discretion of the anesthesiologist. Induction Sevoflurane has a nonpungent odor and does not cause respiratory irritability; it is suitable for mask induction in pediatrics and adults. Maintenance Surgical levels of anesthesia can usually be achieved with concentrations of 0.5 - 3% sevoflurane with or without the concomitant use of nitrous oxide.
Sevoflurane can be administered with any type of anesthesia circuit. Table 9. MAC Values for Adults and Pediatric Patients According to Age Age of Patient (years) Sevoflurane in Oxygen Sevoflurane in 65% N 2 O/35% O 2 0 - 1 months # 3.3% 1 - < 6 months 3.0% 6 months - < 3 years 2.8% 2.0%@ 3 - 12 2.5% 25 2.6% 1.4% 40 2.1% 1.1% 60 1.7% 0.9% 80 1.4% 0.7% # Neonates are full-term gestational age.
MAC in premature infants has not been determined. @ In 1 - < 3 year old pediatric patients, 60% N 2 O/40% O 2 was used.
⛔ Contraindications ▾
CONTRAINDICATIONS • Known or suspected genetic susceptibility to malignant hyperthermia. (see WARNINGS - Malignant Hyperthermia , CLINICAL PHARMACOLOGY - Pharmacogenomics ). • Known or suspected sensitivity to sevoflurane or to other halogenated inhalational anesthetics.
⚠️ Warnings ▾
WARNINGS Risk of Renal Injury Although data from controlled clinical studies at low flow rates are limited, findings taken from patient and animal studies suggest that there is a potential for renal injury which is presumed due to Compound A. Animal and human studies demonstrate that sevoflurane administered for more than 2 MACꞏhours and at fresh gas flow rates of < 2 L/min may be associated with proteinuria and glycosuria. While a level of Compound A exposure at which clinical nephrotoxicity might be expected to occur has not been established, it is prudent to consider all of the factors leading to Compound A exposure in humans, especially duration of exposure, fresh gas flow rate, and concentration of sevoflurane.
During sevoflurane anesthesia the clinician should adjust inspired concentration and fresh gas flow rate to minimize exposure to Compound A. To minimize exposure to Compound A, sevoflurane exposure should not exceed 2 MACꞏhours at flow rates of 1 to < 2 L/min. Fresh gas flow rates < 1 L/min are not recommended.
Because clinical experience in administering sevoflurane to patients with renal insufficiency (creatinine > 1.5 mg/dL) is limited, its safety in these patients has not been established. Sevoflurane may be associated with glycosuria and proteinuria when used for long procedures at low flow rates. The safety of low flow sevoflurane on renal function was evaluated in patients with normal preoperative renal function.
One study compared sevoflurane (N = 98) to an active control (N = 90) administered for ≥ 2 hours at a fresh gas flow rate of ≤ 1 Liter/minute. Per study defined criteria, one patient in the sevoflurane group developed elevations of creatinine, in addition to glycosuria and proteinuria. This patient received sevoflurane at fresh gas flow rates of ≤ 800 mL/minute.
Using these same criteria, there were no patients in the active control group who developed treatment emergent elevations in serum creatinine. Sevoflurane may present an increased risk in patients with known sensitivity to volatile halogenated anesthetic agents. KOH containing CO 2 absorbents are not recommended for use with sevoflurane.
Risk of Respiratory Depression Sevoflurane may cause respiratory depression, which may be augmented by opioid premedication or other agents causing respiratory depression. Monitor respiration and, if necessary, assist with ventilation (see PRECAUTIONS ). Risk of QT Prolongation Reports of QT prolongation, associated with torsade de pointes (in exceptional cases, fatal), have been received.
Caution should be exercised when administering sevoflurane to susceptible patients (e.g., patients with congenital Long QT Syndrome or patients taking drugs that can prolong the QT interval). Malignant Hyperthermia In susceptible individuals, volatile anesthetic agents, including sevoflurane, may trigger malignant hyperthermia, a skeletal muscle hypermetabolic state leading to high oxygen demand. Fatal outcomes of malignant hyperthermia have been reported.
In clinical studies of sevoflurane, 1 case of malignant hyperthermia was reported. The risk of developing malignant hyperthermia increases with the concomitant administration of succinylcholine and volatile anesthetic agents. Sevoflurane can induce malignant hyperthermia in patients with known or suspected susceptibility based on genetic factors or family history, including those with certain inherited ryanodine receptor ( RYR1 ) or dihydropyridine receptor ( CACNA1S ) variants (see CONTRAINDICATIONS , CLINICAL PHARMACOLOGY - Pharmacogenomics ).
Signs consistent with malignant hyperthermia may include hyperthermia, hypoxia, hypercapnia, muscle rigidity (e.g., jaw muscle spasm), tachycardia (e.g., particularly that unresponsive to deepening anesthesia or analgesic medication administration), tachypnea, cyanosis, arrhythmias, hypovolemia, and hemodynamic instability. Skin mottling, coagulopathies, and renal failure may occur later in the course of the hypermetabolic proces…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical Trials Experience Adverse events are derived from controlled clinical studies conducted in the United States, Canada, and Europe. The reference drugs were isoflurane, enflurane, and propofol in adults and halothane in pediatric patients. The studies were conducted using a variety of premedications, other anesthetics, and surgical procedures of varying length.
Most adverse events reported were mild and transient, and may reflect the surgical procedures, patient characteristics (including disease) and/or medications administered. Of the 5182 patients enrolled in the clinical studies, 2906 were exposed to sevoflurane, including 118 adults and 507 pediatric patients who underwent mask induction. Each patient was counted once for each type of adverse event.
Adverse events reported in patients in clinical studies and considered to be possibly or probably related to sevoflurane are presented within each body system in order of decreasing frequency in the following listings. One case of malignant hyperthermia was reported in pre-registration clinical studies. Adverse Events During the Induction Period (from Onset of Anesthesia by Mask Induction to Surgical Incision) Incidence > 1% Adult Patients (N = 118) Cardiovascular Bradycardia 5%, Hypotension 4%, Tachycardia 2% Nervous System Agitation 7% Respiratory System Laryngospasm 8%, Airway obstruction 8%, Breathholding 5%, Cough Increased 5% Pediatric Patients (N = 507) Cardiovascular Tachycardia 6%, Hypotension 4% Nervous System Agitation 15% Respiratory System Breathholding 5%, Cough Increased 5%, Laryngospasm 3%, Apnea 2% Digestive System Increased salivation 2% Adverse Events During Maintenance and Emergence Periods, Incidence > 1% (N = 2906) Body as a whole Fever 1%, Shivering 6%, Hypothermia 1%, Movement 1%, Headache 1% Cardiovascular Hypotension 11%, Hypertension 2%, Bradycardia 5%, Tachycardia 2% Nervous System Somnolence 9%, Agitation 9%, Dizziness 4%, Increased salivation 4% Digestive System Nausea 25%, Vomiting 18% Respiratory System Cough increased 11%, Breathholding 2%, Laryngospasm 2% Adverse Events, All Patients in Clinical Studies (N = 2906), All Anesthetic Periods, Incidence < 1% (Reported in 3 or More Patients) Body as a whole Asthenia, Pain Cardiovascular Arrhythmia, Ventricular Extrasystoles, Supraventricular Extrasystoles, Complete AV Block, Bigeminy, Hemorrhage, Inverted T Wave, Atrial Fibrillation, Atrial Arrhythmia, Second Degree AV Block, Syncope, S-T Depressed Nervous System Crying, Nervousness, Confusion, Hypertonia, Dry Mouth, Insomnia Respiratory System Sputum Increased, Apnea, Hypoxia, Wheezing, Bronchospasm, Hyperventilation, Pharyngitis, Hiccup, Hypoventilation, Dyspnea, Stridor Metabolism and Nutrition Increases in LDH, AST, ALT, BUN, Alkaline Phosphatase, Creatinine, Bilirubinemia, Glycosuria, Fluorosis, Albuminuria, Hypophosphatemia, Acidosis, Hyperglycemia Hemic and Lymphatic System Leucocytosis, Thrombocytopenia Skin and Special Senses Amblyopia, Pruritus, Taste Perversion, Rash, Conjunctivitis Urogenital Urination Impaired, Urine Abnormality, Urinary Retention, Oliguria See WARNINGS for information regarding malignant hyperthermia.
🆘 Overdosage ▾
OVERDOSAGE In the event of overdosage, or what may appear to be overdosage, the following action should be taken: discontinue administration of sevoflurane, maintain a patent airway, initiate assisted or controlled ventilation with oxygen, and maintain adequate cardiovascular function.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Sevoflurane is an inhalational anesthetic agent for use in induction and maintenance of general anesthesia. Minimum alveolar concentration (MAC) of sevoflurane in oxygen for a 40-year-old adult is 2.1%. The MAC of sevoflurane decreases with age (see DOSAGE AND ADMINISTRATION for details).
Pharmacokinetics Uptake and Distribution Solubility Because of the low solubility of sevoflurane in blood (blood/gas partition coefficient @ 37°C = 0.63-0.69), a minimal amount of sevoflurane is required to be dissolved in the blood before the alveolar partial pressure is in equilibrium with the arterial partial pressure. Therefore, there is a rapid rate of increase in the alveolar (end-tidal) concentration (F A ) toward the inspired concentration (F I ) during induction. Induction of Anesthesia In a study in which seven healthy male volunteers were administered 70% N 2 O/30%O 2 for 30 minutes followed by 1.0% sevoflurane and 0.6% isoflurane for another 30 minutes the FA/FI ratio was greater for sevoflurane than isoflurane at all time points.
The time for the concentration in the alveoli to reach 50% of the inspired concentration was 4-8 minutes for isoflurane and approximately 1 minute for sevoflurane. F A /F I data from this study were compared with F A /F I data of other halogenated anesthetic agents from another study. When all data were normalized to isoflurane, the uptake and distribution of sevoflurane was shown to be faster than isoflurane and halothane, but slower than desflurane.
The results are depicted in Figure 3. Recovery from Anesthesia The low solubility of sevoflurane facilitates rapid elimination via the lungs. The rate of elimination is quantified as the rate of change of the alveolar (end-tidal) concentration following termination of anesthesia (F A ), relative to the last alveolar concentration (Fa O ) measured immediately before discontinuance of the anesthetic.
In the healthy volunteer study described above, rate of elimination of sevoflurane was similar compared with desflurane, but faster compared with either halothane or isoflurane. These results are depicted in Figure 4. Figure 3.
Ratio of Concentration of Anesthetic in Alveolar Gas to Inspired Gas Figure 4. Concentration of Anesthetic in Alveolar Gas Following Termination of Anesthesia Protein Binding The effects of sevoflurane on the displacement of drugs from serum and tissue proteins have not been investigated. Other fluorinated volatile anesthetics have been shown to displace drugs from serum and tissue proteins in vitro .
The clinical significance of this is unknown. Clinical studies have shown no untoward effects when sevoflurane is administered to patients taking drugs that are highly bound and have a small volume of distribution (e.g., phenytoin). Metabolism Sevoflurane is metabolized by cytochrome P450 2E1, to hexafluoroisopropanol (HFIP) with release of inorganic fluoride and CO 2 .
Once formed HFIP is rapidly conjugated with glucuronic acid and eliminated as a urinary metabolite. No other metabolic pathways for sevoflurane have been identified. In vivo metabolism studies suggest that approximately 5% of the sevoflurane dose may be metabolized.
Cytochrome P450 2E1 is the principal isoform identified for sevoflurane metabolism and this may be induced by chronic exposure to isoniazid and ethanol. This is similar to the metabolism of isoflurane and enflurane and is distinct from that of methoxyflurane which is metabolized via a variety of cytochrome P450 isoforms. The metabolism of sevoflurane is not inducible by barbiturates.
As shown in Figure 5, inorganic fluoride concentrations peak within 2 hours of the end of sevoflurane anesthesia and return to baseline concentrations within 48 hours post- anesthesia in the majority of cases (67%). The rapid and extensive pulmonary elimination of sevoflurane minimizes the amount of anesthetic available for metabolism. Figure 5.
Serum Inorganic Fluoride Concentrations for Sevoflurane and Other Vol…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Sevoflurane, USP, Volatile Liquid for Inhalation, is packaged in amber colored bottles containing 250 mL Sevoflurane, USP, NDC # 66794-022-25.
📋 Description ▾
DESCRIPTION Sevoflurane, USP, volatile liquid for inhalation, a nonflammable and nonexplosive liquid administered by vaporization, is a halogenated general inhalation anesthetic drug. Sevoflurane is fluoromethyl 2,2,2,-trifluoro-1-(trifluoromethyl) ethyl ether and its structural formula is: Sevoflurane, Physical Constants are: Molecular weight 200.05 Boiling point at 760 mm Hg 58.6°C Specific gravity at 20°C 1.520 - 1.525 Vapor pressure in mm Hg 157 mm Hg at 20°C 197 mm Hg at 25°C 317 mm Hg at 36°C Distribution Partition Coefficients at 37°C: Blood/Gas 0.63 -
0.69 Water/Gas
0.36 Olive Oil/Gas 47 – 54 Brain/Gas
1.15Mean Component/Gas Partition Coefficients at 25°C for Polymers Used Commonly in Medical Applications: Conductive rubber
14.0 Butyl rubber
7.7 Polyvinylchloride
17.4 Polyethylene
1.3Sevoflurane is nonflammable and nonexplosive as defined by the requirements of International Electrotechnical Commission 601-2-13. Sevoflurane is a clear, colorless, liquid containing no additives. Sevoflurane is not corrosive to stainless steel, brass, aluminum, nickel-plated brass, chrome-plated brass or copper beryllium.
Sevoflurane is nonpungent. It is miscible with ethanol, ether, chloroform, and benzene, and it is slightly soluble in water. Sevoflurane is stable when stored under normal room lighting conditions according to instructions.
No discernible degradation of sevoflurane occurs in the presence of strong acids or heat. When in contact with alkaline CO 2 absorbents (e.g., Baralyme ® and to a lesser extent soda lime) within the anesthesia machine, sevoflurane can undergo degradation under certain conditions. Degradation of sevoflurane is minimal, and degradants are either undetectable or present in non-toxic amounts when used as directed with fresh absorbents.
Sevoflurane degradation and subsequent degradant formation are enhanced by increasing absorbent temperature increased sevoflurane concentration, decreased fresh gas flow and desiccated CO 2 absorbents (especially with potassium hydroxide containing absorbents e.g. Baralyme). Sevoflurane alkaline degradation occurs by two pathways.
The first results from the loss of hydrogen fluoride with the formation of pentafluoroisopropenyl fluoromethyl ether, (PIFE, C 4 H 2 F 6 O), also known as Compound A, and trace amounts of pentafluoromethoxy isopropyl fluoromethyl ether, (PMFE, C 5 H 6 F 6 O), also known as Compound B. The second pathway for degradation of sevoflurane, which occurs primarily in the presence of desiccated CO 2 absorbents, is discussed later. In the first pathway, the defluorination pathway, the production of degradants in the anesthesia circuit results from the extraction of the acidic proton in the presence of a strong base (KOH and/or NaOH) forming an alkene (Compound A) from sevoflurane similar to formation of 2-bromo-2-chloro-1,1- difluoro ethylene (BCDFE) from halothane.
Laboratory simulations have shown that the concentration of these degradants is inversely correlated with the fresh gas flow rate (See Figure 1). Figure 1. Fresh Gas Flow Rate versus Compound A Levels in a Circle Absorber System Since the reaction of carbon dioxide with absorbents is exothermic, the temperature increase will be determined by quantities of CO 2 absorbed, which in turn will depend on fresh gas flow in the anesthesia circle system, metabolic status of the patient, and ventilation.
The relationship of temperature produced by varying levels of CO 2 and Compound A production is illustrated in the following in vitro simulation where CO 2 was added to a circle absorber system. Figure 2. Carbon Dioxide Flow versus Compound A and Maximum Temperature Compound A concentration in a circle absorber system increases as a function of increasing CO 2 absorbent temperature and composition (Baralyme producing higher levels than soda lime), increased body temperature, and increased minute ventilation, and decreasing fresh gas flow rates.
It has been reported that the concentration of Compound A…