
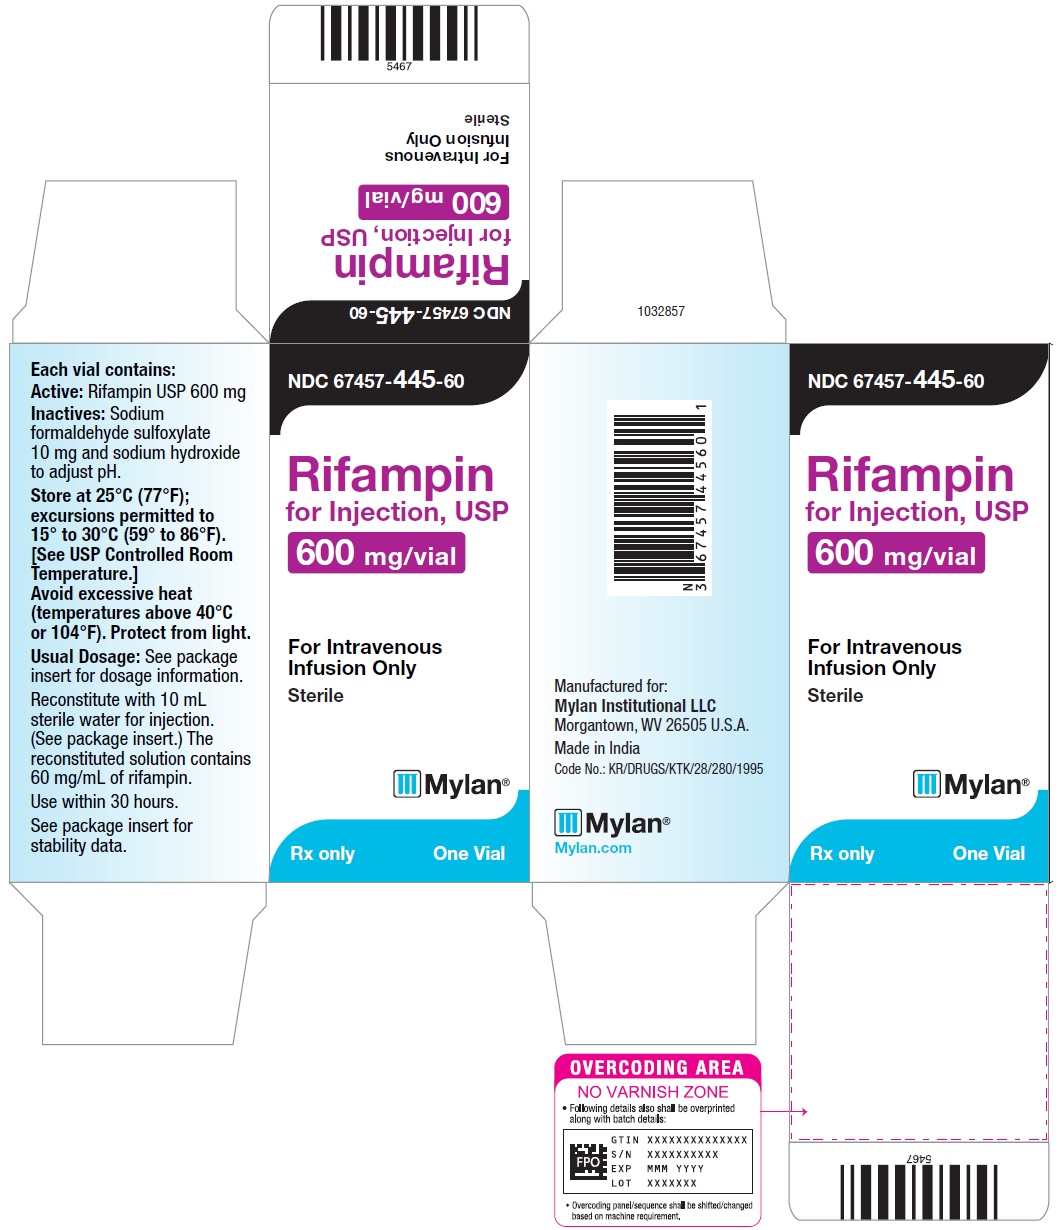
Rifampin 600 mg/10mL Injection, Powder, Lyophilized, For Solution
Past resolved recalls for this product (1)
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Rifamycin Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That's completely expected with rifampin and nothing to worry about medically. The drug naturally gives a reddish-orange color to urine, sweat, saliva, tears, and even stool. It's...
- Why is my urine and sweat turning orange? Is that dangerous?
- Yes, this is a real and important concern. Rifampin significantly reduces the effectiveness of hormonal birth control — including the pill, patch, ring, and hormonal IUD. You shoul...
- I've heard rifampin can affect my birth control. What should I do?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Rifampin — tap one for details:
Rifampin may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII X4ZGP7K714
Sodium formaldehyde sulfoxylate is a chemical compound used as a reducing agent and preservative in medicines. It helps prevent breakdown of certain active ingredients and may reduce microbial growth in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $113.54 | $1,135.42 / 10 ml |
| Medicare drug plans payPart D · Q2 2026 | $107.69 | $1,076.87 / 10 ml |
| Medicare Part B allowsASP · J2804 | $0.172 / J2804 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rifadin IV 600 mg/10mL 00068-0597-01 | Sanofi-Aventis | 1 vial | — | AP | FDA listed | — |
| Rifampin 600 mg 00143-9230-01 | Hikma | 1 injection | — | AP | FDA listed | — |
| Rifampin 600 mg 63323-0351-20 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Rifampin 600 mg/10mLthis 67457-0445-60 | Mylan | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 67457-0445-60 You're viewing this | 1 VIAL in 1 CARTON (67457-445-60) / 10 mL in 1 VIAL | 2015-01-21 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE In the treatment of both tuberculosis and the meningococcal carrier state, the small number of resistant cells present within large populations of susceptible cells can rapidly become the predominant type. Bacteriologic cultures should be obtained before the start of therapy to confirm the susceptibility of the organism to rifampin and they should be repeated throughout therapy to monitor the response to treatment. Since resistance can emerge rapidly, susceptibility tests should be performed in the event of persistent positive cultures during the course of treatment.
If test results show resistance to rifampin and the patient is not responding to therapy, the drug regimen should be modified. Tuberculosis Rifampin is indicated in the treatment of all forms of tuberculosis. A three-drug regimen consisting of rifampin, isoniazid, and pyrazinamide is recommended in the initial phase of short-course therapy which is usually continued for 2 months.
The Advisory Council for the Elimination of Tuberculosis, the American Thoracic Society, and Centers for Disease Control and Prevention recommend that either streptomycin or ethambutol be added as a fourth drug in a regimen containing isoniazid (INH), rifampin, and pyrazinamide for initial treatment of tuberculosis unless the likelihood of INH resistance is very low. The need for a fourth drug should be reassessed when the results of susceptibility testing are known. If community rates of INH resistance are currently less than 4%, an initial treatment regimen with less than four drugs may be considered.
Following the initial phase, treatment should be continued with rifampin and isoniazid for at least 4 months. Treatment should be continued for longer if the patient is still sputum or culture positive, if resistant organisms are present, or if the patient is HIV positive. Rifampin for injection is indicated for the initial treatment and retreatment of tuberculosis when the drug cannot be taken by mouth.
Meningococcal Carriers Rifampin is indicated for the treatment of asymptomatic carriers of Neisseria meningitidis to eliminate meningococci from the nasopharynx. Rifampin is not indicated for the treatment of meningococcal infection because of the possibility of the rapid emergence of resistant organisms. (See WARNINGS .) Rifampin should not be used indiscriminately, and, therefore, diagnostic laboratory procedures, including serotyping and susceptibility testing, should be performed for establishment of the carrier state and the correct treatment.
So that the usefulness of rifampin in the treatment of asymptomatic meningococcal carriers is preserved, the drug should be used only when the risk of meningococcal disease is high. To reduce the development of drug-resistant bacteria and maintain the effectiveness of rifampin and other antibacterial drugs, rifampin should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy.
In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Rifampin can be administered by IV infusion (see INDICATIONS AND USAGE ). IV doses are the same as those for oral. See CLINICAL PHARMACOLOGY for dosing information in patients with renal failure.
Tuberculosis Adults: 10 mg/kg, in a single daily administration, not to exceed 600 mg/day, IV Pediatric Patients: 10-20 mg/kg, not to exceed 600 mg/day, IV Rifampin is indicated in the treatment of all forms of tuberculosis. A three-drug regimen consisting of rifampin, isoniazid, and pyrazinamide is recommended in the initial phase of short-course therapy which is usually continued for 2 months. The Advisory Council for the Elimination of Tuberculosis, the American Thoracic Society, and the Centers for Disease Control and Prevention recommend that either streptomycin or ethambutol be added as a fourth drug in a regimen containing isoniazid (INH), rifampin, and pyrazinamide for initial treatment of tuberculosis unless the likelihood of INH resistance is very low.
The need for a fourth drug should be reassessed when the results of susceptibility testing are known. If community rates of INH resistance are currently less than 4%, an initial treatment regimen with less than four drugs may be considered. Following the initial phase, treatment should be continued with rifampin and isoniazid for at least 4 months.
Treatment should be continued for longer if the patient is still sputum or culture positive, if resistant organisms are present, or if the patient is HIV positive. Preparation of Solution for IV Infusion Reconstitute the lyophilized powder by transferring 10 mL of sterile water for injection to a vial containing 600 mg of rifampin for injection. Swirl vial gently to completely dissolve the antibiotic.
The reconstituted solution contains 60 mg rifampin per mL and is stable at room temperature for up to 30 hours. Prior to administration, withdraw from the reconstituted solution a volume equivalent to the amount of rifampin calculated to be administered and add to 500 mL of infusion medium. Mix well and infuse at a rate allowing for complete infusion within 3 hours.
Alternatively, the amount of rifampin calculated to be administered may be added to 100 mL of infusion medium and infused in 30 minutes. Dilutions in dextrose 5% for injection (D5W) are stable at room temperature for up to 8 hours and should be prepared and used within this time. Precipitation of rifampin from the infusion solution may occur beyond this time.
Dilutions in normal saline are stable at room temperature for up to 6 hours and should be prepared and used within this time. Other infusion solutions are not recommended. Incompatibilities Physical incompatibility (precipitate) was observed with undiluted (5 mg/mL) and diluted (1 mg/mL in normal saline) diltiazem hydrochloride and rifampin (6 mg/mL in normal saline) during simulated Y-site administration.
⛔ Contraindications ▾
CONTRAINDICATIONS Rifampin is contraindicated in patients with a history of hypersensitivity to rifampin or any of the components, or to any of the rifamycins. (See WARNINGS .) Rifampin is contraindicated in patients who are also receiving ritonavir-boosted saquinavir due to an increased risk of severe hepatocellular toxicity. (See PRECAUTIONS, Drug Interactions .) Rifampin is contraindicated in patients who are also receiving atazanavir, darunavir, fosamprenavir, saquinavir, tipranavir, cabotegravir, fostemsavir and lenacapavir (see prescribing information for SUNLENCA ® ) due to the potential of rifampin to substantially decrease plasma concentrations of these antiviral drugs, which may result in decreased antiviral efficacy and/or development of viral resistance.
(See PRECAUTIONS, Drug Interactions .) Rifampin is contraindicated in patients receiving praziquantel since therapeutically effective blood levels of praziquantel may not be achieved. In patients receiving rifampin who need immediate treatment with praziquantel alternative agents should be considered. However, if treatment with praziquantel is necessary, rifampin should be discontinued 4 weeks before administration of praziquantel.
Treatment with rifampin can then be restarted one day after completion of praziquantel treatment. Rifampin is contraindicated in patients receiving lurasidone. Concomitant use of lurasidone with strong CYP3A4 inducers (e.g., rifampin) decreased the exposure of lurasidone compared to the use of lurasidone alone.
(See PRECAUTIONS, Drug Interactions ).
⚠️ Warnings ▾
WARNINGS Hepatotoxicity of hepatocellular, cholestatic, and mixed patterns has been reported in patients treated with rifampin. Severity ranged from asymptomatic elevations in liver enzymes, isolated jaundice/hyperbilirubinemia, symptomatic self-limited hepatitis to fulminant liver failure and death. Severe hepatic dysfunction including fatalities were reported in patients with liver disease and in patients taking rifampin with other hepatotoxic agents.
Monitor for symptoms and clinical/laboratory signs of liver injury, especially if treatment is prolonged or given with other hepatotoxic drugs. Patients with impaired liver function should be given rifampin only in cases of necessity and then under strict medical supervision. In these patients, careful monitoring of liver function should be done prior to therapy and then every 2 to 4 weeks during therapy.
If signs of hepatic damage occur or worsen, discontinue rifampin. Rifampin has enzyme-inducing properties, including induction of delta amino levulinic acid synthetase. Isolated reports have associated porphyria exacerbation with rifampin administration.
The possibility of rapid emergence of resistant meningococci restricts the use of rifampin to short-term treatment of the asymptomatic carrier state. Rifampin is not to be used for the treatment of meningococcal disease. Systemic hypersensitivity reactions were reported with rifampin administration.
Signs and symptoms of hypersensitivity reactions may include fever, rash, urticaria, angioedema, hypotension, acute bronchospasm, conjunctivitis, thrombocytopenia, neutropenia, elevated liver transaminases or flu-like syndrome (weakness, fatigue, muscle pain, nausea, vomiting, headache, chills, aches, itching, sweats, dizziness, shortness of breath, chest pain, cough, syncope, palpitations). Manifestations of hypersensitivity, such as fever, lymphadenopathy or laboratory abnormalities (including eosinophilia, liver abnormalities) may be present even though rash is not evident.
Monitor patients receiving rifampin for signs and/or symptoms of hypersensitivity reactions. If these signs or symptoms occur, discontinue rifampin and administer supportive measures. Cases of severe cutaneous adverse reactions (SCAR) such as Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), acute generalized exanthematous pustulosis (AGEP), and drug reaction with eosinophilia and systemic symptoms (DRESS) syndrome have been reported with rifampin.
If symptoms or signs of severe cutaneous adverse reactions develop, discontinue rifampin immediately and institute appropriate therapy. Rifampin may cause vitamin K–dependent coagulation disorders and bleeding (see ADVERSE REACTIONS ). Monitor coagulation tests during rifampin treatment (prothrombin time and other coagulation tests) in patients at risk of vitamin K deficiency (such as those with chronic liver disease, poor nutritional status, on prolonged antibacterial drugs or anticoagulants).
Consider discontinuation of rifampin if abnormal coagulation tests and/or bleeding occur. Supplemental vitamin K administration should be considered when appropriate. Pulmonary toxicity manifested as interstitial lung disease (including, but not limited to, pneumonitis, hypersensitivity pneumonitis, eosinophilic pneumonia, pulmonary infiltrates, and organizing pneumonia) has been reported with rifampin treatment.
Pulmonary toxicity could be fatal. If symptoms or signs of severe pulmonary toxicity (including respiratory failure, pulmonary fibrosis, and acute respiratory distress syndrome) develop, discontinue rifampin immediately and initiate appropriate treatment. Postmarketing reports suggest that concomitant administration of high doses of cefazolin and rifampin may prolong the prothrombin time, leading to severe vitamin K–dependent coagulation disorders that may be life-threatening or fatal.
Avoid concomitant use of cefazolin and rifampin in patients at increased risk for bleeding. If no alternative treatm…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions associated with the use of rifampin were identified in clinical studies or postmarketing reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Gastrointestinal Heartburn, epigastric distress, anorexia, nausea, vomiting, jaundice, flatulence, cramps, and diarrhea have been noted in some patients.
Although Clostridium difficile has been shown in vitro to be sensitive to rifampin, pseudomembranous colitis has been reported with the use of rifampin (and other broad-spectrum antibiotics). Therefore, it is important to consider this diagnosis in patients who develop diarrhea in association with antibiotic use. Tooth discoloration (which may be permanent) may occur.
Hepatic Hepatotoxicity including transient abnormalities in liver function tests (e.g., elevations in serum bilirubin, alkaline phosphatase, serum transaminases, gamma-glutamyl transferase), hepatitis, shock-like syndrome with hepatic involvement and abnormal liver function tests, and cholestasis have been reported (see WARNINGS ). Hematologic Cases of thrombotic microangiopathy, including thrombotic thrombocytopenic purpura and hemolytic uremic syndrome, have been reported (see WARNINGS ). Thrombocytopenia has occurred primarily with high dose intermittent therapy but has also been noted after resumption of interrupted treatment.
It rarely occurs during well-supervised daily therapy. This effect is reversible if the drug is discontinued as soon as purpura occurs. Cerebral hemorrhage and fatalities have been reported when rifampin administration has been continued or resumed after the appearance of purpura.
Rare reports of disseminated intravascular coagulation have been observed. Leukopenia, hemolytic anemia, decreased hemoglobin, bleeding, and vitamin K–dependent coagulation disorders (abnormal prolongation of prothrombin time or low vitamin K–dependent coagulation factors) have been observed. Agranulocytosis has been reported very rarely.
Central Nervous System Headache, fever, drowsiness, fatigue, ataxia, dizziness, inability to concentrate, mental confusion, behavioral changes, muscular weakness, pains in extremities, and generalized numbness have been observed. Psychoses have been rarely reported. Rare reports of myopathy have also been observed.
Ocular Visual disturbances have been observed. Endocrine Menstrual disturbances have been observed. Rare reports of adrenal insufficiency in patients with compromised adrenal function have been observed.
Renal Elevations in BUN and serum uric acid have been reported. Rarely, hemolysis, hemoglobinuria, hematuria, interstitial nephritis, acute tubular necrosis, renal insufficiency, and acute renal failure have been noted. These are generally considered to be hypersensitivity reactions.
They usually occur during intermittent therapy or when treatment is resumed following intentional or accidental interruption of a daily dosage regimen, and are reversible when rifampin is discontinued and appropriate therapy instituted. Dermatologic Cutaneous reactions are mild and self-limiting and do not appear to be hypersensitivity reactions. Typically, they consist of flushing and itching with or without a rash.
More serious cutaneous reactions which may be due to hypersensitivity occur but are uncommon. Hypersensitivity Reactions Occasionally, pruritus, urticaria, rash, pemphigoid reaction, erythema multiforme, acute generalized exanthematous pustulosis, Stevens-Johnson syndrome, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic symptoms syndrome (see WARNINGS ), vasculitis, eosinophilia, sore mouth, sore tongue, and conjunctivitis have been observed. Anaphylaxis has been reported rarely.
Respiratory, Thoracic and Mediastinal Disorders Pulmonary toxicity (including, but not limited to, interstitial lung…
🔄 Drug Interactions ▾
Drug Interactions Pharmacodynamic Interactions Healthy subjects who received rifampin 600 mg once daily concomitantly with saquinavir 1000 mg/ritonavir 100 mg twice daily (ritonavir-boosted saquinavir) developed severe hepatocellular toxicity. Therefore, concomitant use of these medications is contraindicated. (See CONTRAINDICATIONS .) When rifampin is given concomitantly with other hepatotoxic medications such as halothane or isoniazid, the potential for hepatotoxicity is increased.
The concomitant use of rifampin and halothane should be avoided. Patients receiving both rifampin and isoniazid should be monitored closely for hepatotoxicity. Effect of Rifampin on Other Drugs Induction of Drug Metabolizing Enzymes and Transporters Drug metabolizing enzymes and transporters affected by rifampin include cytochromes P450 (CYP) 1A2, 2B6, 2C8, 2C9, 2C19, and 3A4, UDP-glucuronyltransferases (UGT), sulfotransferases, carboxylesterases, and transporters including P-glycoprotein (P-gp) and multidrug resistance-associated protein 2 (MRP2).
Most drugs are substrates for one or more of these enzyme or transporter pathways and these pathways may be induced by rifampin simultaneously. Therefore, rifampin may increase the metabolism and decrease the activity of certain coadministered drugs or increase the activity of a coadministered pro-drug (where metabolic activation is required), and has the potential to perpetuate clinically important drug-drug interactions against many drugs and across many drug classes (Table 1). Table 1 summarizes the effect of rifampin on other drugs or drug classes.
Adjust dosages of concomitant drugs based on approved drug labeling and if applicable, therapeutic drug monitoring, unless otherwise specified. Table 1: Drug Interactions with Rifampin that Affect Concomitant Drug Concentrations Administered with rifampin 600 mg daily, unless otherwise specified AUC = area under the time-concentration curve Drug or Drug Class and Prevention or Management Clinical Effect Antiretrovirals Prevention or Management: Concomitant use is contraindicated (see CONTRAINDICATIONS ) Atazanavir Decrease AUC by 72% Darunavir Rifampin dosage used concomitantly with the drug(s) is not specified in the proposed package insert.
Substantial decrease in exposure, which may result in loss of therapeutic effect and development of resistance. Tipranavir Fosamprenavir Administered with rifampin 300 mg daily Decrease AUC by 82% Saquinavir Decrease AUC by 70% Coadministration may result in severe hepatocellular toxicity. Cabotegravir Decrease AUC by 59% Fostemsavir Decrease AUC by 82% Lenacapavir (SUNLENCA) Indicated for the treatment of human immunodeficiency virus-1 (HIV-1) infection Decrease AUC by 84% Antiretrovirals Prevention or Management: Avoid concomitant use Zidovudine Decrease AUC by 47% Indinavir Decrease AUC by 92% Efavirenz Decrease AUC by 26% Antiretrovirals Prevention or Management: Dose adjustment is indicated Lenacapavir (YEZTUGO ® ) Indicated for HIV-1 pre-exposure prophylaxis (PrEP) Refer to the YEZTUGO prescribing information for YEZTUGO dose adjustment.
Decrease AUC by 84% Cortisol Receptor Blocker Mifepristone Prevention or Management: Avoid concomitant use Decrease exposure Hepatitis C Antiviral Prevention or Management: Avoid concomitant use Daclatasvir Decrease AUC by 79% Simeprevir Decrease AUC by 48% Sofosbuvir Decrease AUC by 72% Coadministration of sofosbuvir with rifampin may decrease sofosbuvir plasma concentrations, leading to reduced therapeutic effect of sofosbuvir. Telaprevir Decrease AUC by 92% Systemic Hormonal Contraceptives Prevention or Management: Advise patients to change to non-hormonal methods of birth control during rifampin therapy Estrogens Decrease exposure Progestins Anticonvulsants Phenytoin Administered with rifampin 450 mg daily Decrease exposure Antiarrhythmics Disopyramide Decrease exposure Mexiletine Decrease exposure Quinidine Decrease exposure Propafenone Decrease AUC by 50%-67% Tocainide De…
🧒 Pediatric Use ▾
Pediatric Use See CLINICAL PHARMACOLOGY–Pediatrics ; see also DOSAGE AND ADMINISTRATION .
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of rifampin did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Caution should therefore be observed in using rifampin in elderly patients. (See WARNINGS .)
🆘 Overdosage ▾
OVERDOSAGE Signs and Symptoms Nausea, vomiting, abdominal pain, pruritus, headache, and increasing lethargy will probably occur within a short time after ingestion; unconsciousness may occur when there is severe hepatic disease. Transient increases in liver enzymes and/or bilirubin may occur. Brownish-red or orange discoloration of the skin, urine, sweat, saliva, tears, and feces will occur, and its intensity is proportional to the amount ingested.
Liver enlargement, possibly with tenderness, can develop within a few hours after severe overdosage; bilirubin levels may increase and jaundice may develop rapidly. Hepatic involvement may be more marked in patients with prior impairment of hepatic function. Other physical findings remain essentially normal.
A direct effect upon the hematopoietic system, electrolyte levels, or acid-base balance is unlikely. Facial or periorbital edema has also been reported in pediatric patients. Hypotension, sinus tachycardia, ventricular arrhythmias, seizures, and cardiac arrest were reported in some fatal cases.
Acute Toxicity The minimum acute lethal or toxic dose is not well established. However, nonfatal acute overdoses in adults have been reported with doses ranging from 9 to 12 gm rifampin. Fatal acute overdoses in adults have been reported with doses ranging from 14 to 60 gm.
Alcohol or a history of alcohol abuse was involved in some of the fatal and nonfatal reports. Nonfatal overdoses in pediatric patients ages 1 to 4 years old of 100 mg/kg for one to two doses has been reported. Treatment Intensive support measures should be instituted and individual symptoms treated as they arise.
The airway should be secured and adequate respiratory exchange established. Since nausea and vomiting are likely to be present, gastric lavage within the first 2 to 3 hours after ingestion is probably preferable to induction of emesis. Following evacuation of the gastric contents, the instillation of activated charcoal slurry into the stomach may help absorb any remaining drug from the gastrointestinal tract.
Antiemetic medication may be required to control severe nausea and vomiting. Active diuresis (with measured intake and output) will help promote excretion of the drug. For severe cases, extracorporeal hemodialysis may be required.
If this is not available, peritoneal dialysis can be used along with forced diuresis.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Intravenous Administration After intravenous administration of a 300 or 600 mg dose of rifampin infused over 30 minutes to healthy male volunteers (n = 12), mean peak plasma concentrations were 9.0 ± 3.0 and 17.5 ± 5.0 mcg/mL, respectively. Total body clearances after the 300 and 600 mg IV doses were 0.19 ± 0.06 and 0.14 ±
0.03L/hr/kg, respectively. Volumes of distribution at steady state were 0.66 ± 0.14 and 0.64 ±
0.11L/kg for the 300 and 600 mg IV doses, respectively. After intravenous administration of 300 or 600 mg doses, rifampin plasma concentrations in these volunteers remained detectable for 8 and 12 hours, respectively (see Table). Plasma Concentrations (mean ± standard deviation, mcg/mL) Rifampin Dosage IV 30 min 1 hr 2 hr 4 hr 8 hr 12 hr 300 mg 8.9 ± 2.9 4.9 ± 1.3 4.0 ± 1.3 2.5 ± 1.0 1.1 ± 0.6 < 0.4 600 mg 17.4 ± 5.1 11.7 ± 2.8 9.4 ± 2.3 6.4 ± 1.7 3.5 ± 1.4 1.2 ±
0.6Plasma concentrations after the 600 mg dose, which were disproportionately higher (up to 30% greater than expected) than those found after the 300 mg dose, indicated that the elimination of larger doses was not as rapid. After repeated once-a-day infusions (3-hr duration) of 600 mg in patients (n = 5) for 7 days, concentrations of IV rifampin decreased from 5.81 ± 3.38 mcg/mL 8 hours after the infusion on day 1 to 2.6 ± 1.88 mcg/mL 8 hours after the infusion on day 7. Rifampin is widely distributed throughout the body.
It is present in effective concentrations in many organs and body fluids, including cerebrospinal fluid. Rifampin is about 80% protein bound. Most of the unbound fraction is not ionized and therefore diffuses freely into tissues.
Rifampin is rapidly eliminated in the bile and undergoes progressive enterohepatic circulation and deacetylation to the primary metabolite, 25-desacetyl-rifampin. This metabolite is microbiologically active. Less than 30% of the dose is excreted in the urine as rifampin or metabolites.
Serum concentrations do not differ in patients with renal failure at a studied dose of 300 mg, and consequently, no dosage adjustment is required. Pediatrics Intravenous Administration In pediatric patients 0.25 to 12.8 years old (n = 12), the mean peak serum concentration of rifampin at the end of a 30-minute infusion of approximately 300 mg/m 2 was 25.9 ± 1.3 mcg/mL; individual peak concentrations 1 to 4 days after initiation of therapy ranged from 11.7 to 41.5 mcg/mL; individual peak concentrations 5 to 14 days after initiation of therapy were 13.6 to 37.4 mcg/mL.
The individual serum half-life of rifampin changed from 1.04 to 3.81 hours early in therapy to 1.17 to 3.19 hours 5 to 14 days after therapy was initiated. In a pharmacokinetics (PK) study of 22 pediatric patients (median gestational age 27.5 weeks [range; 23-41 weeks] and median postnatal age (PNA) 7.5 days [range: 0-56 days]) receiving intravenous rifampin 10-20 mg/kg/day over 30 minutes, pediatric patients ≤ 7 days old had a median clearance of
0.09L/kg/hr (range: 0.056-0.14 L/kg/hr) and a median area under the plasma drug concentration-time curve at infinity (AUC ∞ ) of 105 mg*hr/L (range: 80172 mg*hr/L); pediatric patients > 7 days PNA had a median clearance of
0.23L/kg/hr (range: 0.14-0.32 L/kg/hr) and a median AUC ∞ of 78 mg*hr/L (range: 51-170 mg*hr/L). Based on PK modeling and simulation analyses, a dose of 12 mg/kg infused over 60 minutes once daily in pediatric patients ≤ 7 days PNA resulted in median (90% prediction interval) for maximum plasma concentration (C max ) of 8.4 mcg/mL (range: 5.3-13.3 mcg/mL) and AUC ∞ of 96.4 mg*hr/L (range: 64.5-141.6 mg*hr/L); in pediatric patients > 7 days and < 90 days PNA a dose of 14 mg/kg infused over 60 minutes once daily resulted in a median (90% prediction interval) for C max of 9.6 mcg/mL (range: 6.l-15.1 mcg/mL) and AUC ∞ of 73.l mg*hr/L (range: 45.6-131.6 mg*hr/L).
All simulated AUC ∞ were within the range of AUC ∞ values reported in other studies in adults treated for tuberculosis. Micr…
🧬 Mechanism of Action ▾
Mechanism of Action Rifampin inhibits DNA-dependent RNA polymerase activity in susceptible Mycobacterium tuberculosis organisms. Specifically, it interacts with bacterial RNA polymerase but does not inhibit the mammalian enzyme.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Rifampin for Injection, USP is available in sterile glass vials containing 600 mg rifampin, USP (NDC 67457-445-60). Storage: Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.] Avoid excessive heat (temperatures above 40°C or 104°F). Protect from light.
The brands listed are trademarks of their respective owners. Manufactured for: Mylan Institutional LLC Morgantown, WV 26505 U.S.A. Manufactured by: OneSource Specialty Pharma Limited (Sterile Product Division) Bengaluru 560076, India Revised: 5/2026 MI/OS:RIFAMIJ:RX
📋 Description ▾
DESCRIPTION Rifampin for Injection, USP is a red colored lyophilized powder or cake that contains rifampin, USP 600 mg, sodium formaldehyde sulfoxylate 10 mg, and sodium hydroxide to adjust pH. Rifampin is a semisynthetic antibiotic derivative of rifamycin SV. Rifampin, USP is a red to brown crystalline powder very slightly soluble in water at neutral pH, freely soluble in chloroform, soluble in ethyl acetate and in methanol.
Its molecular weight is 822.95 and its chemical formula is C 43 H 58 N 4 O 12 . The chemical name for rifampin is either: 3-[[(4-Methyl-1-piperazinyl)imino]methyl]rifamycin or 5,6,9,17,19,21-hexahydroxy-23-methoxy-2,4,12,16,18,20,22–heptamethyl-8-[ N -(4-methyl-1-piperazinyl)formimidoyl]-2,7-(epoxypentadeca[1,11,13]trienimino)naphtho[2,1- b ]furan-1,11(2 H )-dione 21-acetate. Its structural formula is: Rifampin Structural Formula
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including rifampin should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When rifampin is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by rifampin or other antibacterial drugs in the future. The patient should be told that rifampin may produce a discoloration (yellow, orange, red, brown) of the teeth, urine, sweat, sputum, and tears, and the patient should be forewarned of this. Soft contact lenses may be permanently stained.
Rifampin is a well characterized and potent inducer of drug metabolizing enzymes and transporters and might therefore decrease or increase concomitant drug exposure and impact safety and efficacy (see DRUG INTERACTIONS ). Therefore, patients should be advised not to take any other medication without medical advice. The patient should be advised that the reliability of oral or other systemic hormonal contraceptives may be affected; consideration should be given to using alternative contraceptive measures.
Patients should be instructed to notify their physician immediately if they experience any of the following: rash with fever or blisters, with or without peeling skin, itching, or swollen lymph nodes, loss of appetite, malaise, nausea, vomiting, abdominal pain, darkened urine, yellowish discoloration of the skin and eyes, light-colored bowel movements, fever, headache, fatigue, myalgias, cough, shortness of breath, chest pain, wheezing, and pain or swelling of the joints. Patients should be advised to seek medical advice immediately if their symptoms of mycobacterial disease, including, but not limited to, cough, fever, tiredness, shortness of breath, malaise, headache, pain, night sweats, swollen lymph nodes, loss of appetite, weight loss, weakness, skin ulcers or lesions, worsen (see ADVERSE REACTIONS ).
Advise patients to abstain from alcohol, hepatotoxic medications or herbal products while taking rifampin. Compliance with the full course of therapy must be emphasized, and the importance of not missing any doses must be stressed.