
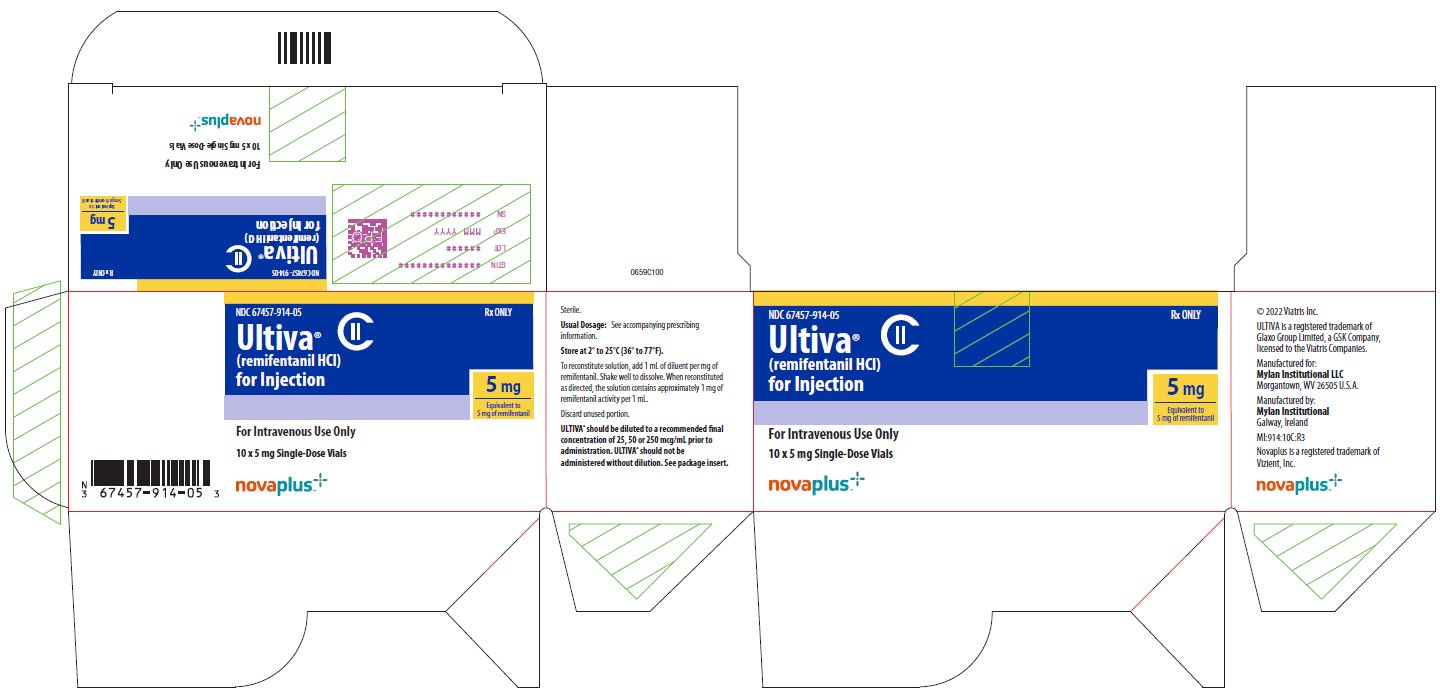
Ultiva Remifentanil Hydrochloride 1 mg/mL Injection, Powder, Lyophilized, For Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Opioid Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Remifentanil is a specialized opioid used only in surgery and closely monitored settings. It works within seconds and wears off within minutes, which gives your anesthesia team pre...
- Why am I getting remifentanil instead of a regular pain medicine?
- Remifentanil controls pain but cannot put you to sleep on its own, so it is always used together with other anesthetics that do cause unconsciousness. Your team combines it with me...
- Will I be awake or remember anything during surgery if I'm given this?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
15 ug / 1 mL
UNII TE7660XO1C
Glycine is an amino acid used in medicines as a buffer to help stabilize pH and improve taste. It may also serve as a filler or binder to give the product proper form and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Remifentanil Hydrochloride 5 mg/5mL 00143-9393-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Remifentanil Hydrochloride 1 mg/mL 63323-0725-10 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Ultiva 1 mg/mLthis 67457-0914-05 | Mylan | 10 vials | — | AP | FDA listed | — |
| Ultiva 1 mg/mL 72078-0036-05 | Mylan | 10 vials | — | AP | FDA listed | — |
| Remifentanil Hydrochloride 1 mg/mL 00143-9391-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Ultiva 1 mg/mL 67457-0913-02 | Mylan | 10 vials | — | AP | FDA listed | — |
| Remifentanil Hydrochloride 1 mg/mL 63323-0724-05 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Remifentanil Hydrochloride 1 mg/mL 63323-0723-03 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Ultiva 1 mg/mL 72078-0035-02 | Mylan | 10 vials | — | AP | FDA listed | — |
| Ultiva 1 mg/mL 67457-0912-01 | Mylan | 10 vials | — | AP | FDA listed | — |
| Ultiva 1 mg/mL 72078-0034-01 | Mylan | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 67457-0914-05 You're viewing this | 10 VIAL, GLASS in 1 CARTON (67457-914-05) / 10 mL in 1 VIAL, GLASS (67457-914-00) | 2020-04-15 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF ULTIVA Addiction, Abuse, and Misuse Because the use of ULTIVA exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient’s risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [see Warnings and Precautions (5.1) ] . Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of ULTIVA, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of ULTIVA are essential [see Warnings and Precautions (5.2) ] . Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of ULTIVA and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate [see Warnings and Precautions (5.3) , Drug Interactions (7) ] .
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF ULTIVA See full prescribing information for complete boxed warning. • ULTIVA exposes users to the risks of addiction, abuse, and misuse. Assess patient’s risk before prescribing and reassess regularly for the development of these behaviors and conditions. ( 5.1 ) • Serious, life-threatening, or fatal respiratory depression may occur with use of ULTIVA, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of ULTIVA are essential. ( 5.2 ) • Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing for use in patients for whom alternative treatment options are inadequate.
( 5.3 , 7 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ULTIVA is indicated for intravenous (IV) administration: • As an analgesic agent for use during the induction and maintenance of general anesthesia for inpatient and outpatient procedures. • For continuation as an analgesic into the immediate postoperative period in adult patients under the direct supervision of an anesthesia practitioner in a postoperative anesthesia care unit or intensive care setting. • As an analgesic component of monitored anesthesia care in adult patients. ULTIVA is an opioid agonist indicated for intravenous administration: • As an analgesic agent for use during the induction and maintenance of general anesthesia for inpatient and outpatient procedures.
( 1 ) • For continuation as an analgesic into the immediate postoperative period in adult patients under the direct supervision of an anesthesia practitioner in a postoperative anesthesia care unit or intensive care setting. ( 1 ) • As an analgesic component of monitored anesthesia care in adult patients. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Monitor patients closely for respiratory depression when initiating therapy and following dosage increases and adjust the dosage accordingly. ( 2.1 ) • Administration : Continuous infusions of ULTIVA should be administered only by an infusion device. ( 2.1 ) • Initial Dosage in Adults : See full prescribing information for recommended doses in adult patients.
( 2.2 , 2.3 ) • Initial Dosage in Pediatric Patients : See full prescribing information for recommended doses in pediatric patients. ( 2.2 ) • Geriatric Patients : The starting doses should be decreased by 50% in elderly patients (> 65 years). ( 2.6 )
2.1Important Dosage and Administration Information • Monitor patients closely for respiratory depression when initiating therapy and following dosage increases with ULTIVA and adjust the dosage accordingly [see Warnings and Precautions (5.2) ]. • ULTIVA is for IV use only. • ULTIVA should not be administered without dilution. • Continuous infusions of ULTIVA should be administered only by an infusion device. IV bolus administration of ULTIVA should be used only during the maintenance of general anesthesia. In nonintubated patients, single doses of ULTIVA should be administered over 30 to 60 seconds. • Interruption of an infusion of ULTIVA will result in rapid offset of effect.
Rapid clearance and lack of drug accumulation result in rapid dissipation of respiratory depressant and analgesic effects upon discontinuation of ULTIVA at recommended doses. Discontinuation of an infusion of ULTIVA should be preceded by the establishment of adequate postoperative analgesia. • Injections of ULTIVA should be made into IV tubing at or close to the venous cannula. Upon discontinuation of ULTIVA, the IV tubing should be cleared to prevent the inadvertent administration of ULTIVA at a later point in time.
Failure to adequately clear the IV tubing to remove residual ULTIVA has been associated with the appearance of respiratory depression, apnea, and muscle rigidity upon the administration of additional fluids or medications through the same IV tubing. • Consider an alternative to ULTIVA for patients taking mixed agonist/antagonist and partial agonist opioid analgesics due to reduced analgesic effect or potential withdrawal symptoms. If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment.
Discontinue ULTIVA if patient is not responding appropriately to treatment. • Discard unused portion.
2.2General Anesthesia ULTIVA is not recommended as the sole agent in general anesthesia because loss of consciousness cannot be assured and because of a high incidence of apnea, muscle rigidity, and tachycardia. ULTIVA is synergistic with other anesthetics; therefore, clinicians may need to reduce doses of thiopental, propofol, isoflurane, and midazolam by up to 75% with the coadministration of ULTIVA. The administration of ULTIVA must be individualized based on the patient's response.
Induction of Anesthesia ULTIVA should be administered at an infusion rate of 0.5 to 1 mcg/kg/min with a hypnotic or volatile agent for the induction of anesthesia. If endotracheal intubation is to occur less than 8 minutes after the start of the infusion of ULTIVA, then an initial dose of 1 mcg/kg may be administered over 30 to 60 seconds. ULTIVA should not be used as a sole agent for induction of anesthesia because loss of consciousness cannot be assured and because of a high incidence of apnea, muscle rigidity, and tachycardia.
Maintenance of Anesthesia After endotracheal intubation, the infusion rate of ULTIVA should be decreased in accordance with the dosing guidelines in Tables 1 (adults, predominately ASA physical status I, II, or III) and 2 (pediatric patients). • Due to the fast onset and short duration of action of ULTIVA, the rate of administration during anesthesia can be titrated upward in 25% to 100% increments in adult patients or up to 50% increments in pediatri…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 1 mg, 2 mg, and 5 mg: 3 mL Vial 1 mg lyophilized powder 5 mL Vial 2 mg lyophilized powder 10 mL Vial 5 mg lyophilized powder For injection: 1 mg, 2 mg, and 5 mg for intravenous administration after reconstitution and dilution ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ULTIVA is contraindicated: • For epidural or intrathecal administration due to the presence of glycine in the formulation [see Nonclinical Toxicology (13) ] . • In patients with hypersensitivity to remifentanil (e.g., anaphylaxis) [see Adverse Reactions (6.2) ] . ULTIVA is contraindicated: • For epidural or intrathecal administration due to the presence of glycine in the formulation. ( 4 ) • In patients with hypersensitivity to remifentanil (e.g., anaphylaxis).
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Life-Threatening Respiratory Depression : Monitor closely, particularly during initiation and titration. ( 5.2 ) • Risks from Use as Postoperative Analgesia with Concomitant Benzodiazepines or other CNS Depressants : Hypotension, profound sedation, respiratory depression, coma, and death may result from the concomitant use of ULTIVA with benzodiazepines or other CNS depressants ( 5.3 ) • Opioid-Induced Hyperalgesia and Allodynia : Opioid-Induced Hyperalgesia (OIH) occurs when an opioid analgesic paradoxically causes an increase in pain, or an increase in sensitivity to pain.
If OIH is suspected, carefully consider appropriately decreasing the dose of the current opioid analgesic or opioid rotation. ( 5.4 ) • Serotonin Syndrome : Potentially life-threatening condition could result from concomitant serotonergic drug administration. Discontinue ULTIVA if serotonin syndrome is suspected.
( 5.5 ) • Skeletal Muscle Rigidity : is related to the dose and speed of administration. Muscle rigidity induced by ULTIVA should be managed in the context of the patient's clinical condition. ( 5.6 ) • Potential Inactivation by Nonspecific Esterases in Blood Products : ULTIVA should not be administered into the same IV tubing with blood due to potential inactivation by nonspecific esterases in blood products.
( 5.7 ) • Bradycardia : Monitor heart rate during dosage initiation and titration. It is responsive to ephedrine or anticholinergic drugs ( 5.8 ) • Hypotension : Monitor blood pressure during dosage initiation and titration. It is responsive to decreases in the administration of ULTIVA or to IV fluids or catecholamine administration ( 5.9 ) • Intraoperative Awareness : Inoperative awareness has been reported in patients under 55 years of age when ULTIVA has been administered with propofol infusion rates of ≤ 75 mcg/kg/min ( 5.10 ) • Risks of Use in Spontaneously Breathing Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness : Monitor for sedation and respiratory depression.
( 5.11 ) • Risks of Use in Patients with Biliary Tract Disease : Monitor patients with biliary tract disease, including acute pancreatitis, for worsening symptoms. ( 5.12 ) • Increased Risk of Seizures in Patients with Seizure Disorders : Monitor patients with a history of seizure disorders for worsened seizure control during ULTIVA therapy. ( 5.13 ) • Rapid Offset of Action : Standard monitoring should be maintained in the postoperative period to ensure adequate recovery without stimulation.
( 5.14 )
5.1Addiction, Abuse, and Misuse ULTIVA contains remifentanil, a Schedule II controlled substance. As an opioid, ULTIVA exposes users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence (9) ]. Opioids are sought for nonmedical use and are subject to diversion from legitimate prescribed use.
Consider these risks when handling ULTIVA. Strategies to reduce these risks include proper product storage and control practices for a C-II drug. Contact local state professional licensing board or state-controlled substances authority for information on how to prevent and detect abuse or diversion of this product.
5.2Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death. ULTIVA should be administered only by persons specifically trained in the use of anesthetic drugs and the management of the respiratory effects of potent opioids, including respiration and cardiac resuscitation of patients in the age group being treated.
Such training must include the establishment and maintenance of a patent airway and assisted ventilation. Resuscitative and intubation equipment, oxygen, and opioid overdose reversal agents (e.g., naloxone, nalmefene) must be readily available . Res…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described, or described in greater detail, in other sections: • Addiction, Abuse, and Misuse [see Warnings and Precautions (5.1) ] • Life-Threatening Respiratory Depression [see Warnings and Precautions (5.2) ] • Interactions with Benzodiazepines or other CNS Depressants [see Warnings and Precautions (5.3) ] • Opioid-Induced Hyperalgesia and Allodynia [see Warnings and Precautions (5.4) ] • Serotonin Syndrome [see Warnings and Precautions (5.5) ] • Skeletal Muscle Rigidity [see Warnings and Precautions (5.6) ] • Bradycardia [see Warnings and Precautions (5.8) ] • Hypotension [see Warnings and Precautions (5.9) ] • Biliary Tract Disease [see Warnings and Precautions (5.12) ] • Seizures [see Warnings and Precautions (5.13) ] Most common adverse reactions (incidence ≥ 1%) were respiratory depression, bradycardia, hypotension, and skeletal muscle rigidity.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Viatris at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse event information is derived from controlled clinical studies that were conducted in a variety of surgical procedures of varying duration, using a variety of premedications and other anesthetics, and in patient populations with diverse characteristics including underlying disease.
Adults Approximately 2,770 adult patients were exposed to ULTIVA in controlled clinical studies. The frequencies of adverse events during general anesthesia with the recommended doses of ULTIVA are given in Table 11. Each patient was counted once for each type of adverse event.
Table 11: Adverse Events Reported in ≥ 1% of Adult Patients in General Anesthesia Studies Does not include adverse events from cardiac studies or the neonatal study. See Tables 14, 15, and 16 for cardiac information. at the Recommended Doses See Table 1 for recommended doses. Not all doses of ULTIVA were equipotent to the comparator opioid.
Administration of ULTIVA in excess of the recommended dose (i.e., doses > 1 and up to 20 mcg/kg) resulted in a higher incidence of some adverse events: muscle rigidity (37%), bradycardia (12%), hypertension (4%), and tachycardia (4%). of ULTIVA Adverse Event Induction/Maintenance Postoperative Analgesia After Discontinuation ULTIVA (n = 921) Alfentanil/Fentanyl (n = 466) ULTIVA (n = 281) Morphine (n = 98) ULTIVA (n = 929) Alfentanil/Fentanyl (n = 466) Nausea 8 (< 1%) 0 61 (22%) 15 (15%) 339 (36%) 202 (43%) Hypotension 178 (19%) 30 (6%) 0 0 16 (2%) 9 (2%) Vomiting 4 (< 1%) 1 (< 1%) 22 (8%) 5 (5%) 150 (16%) 91 (20%) Muscle rigidity 98 (11%) Included in the muscle rigidity incidence is chest wall rigidity (5%).
The overall muscle rigidity incidence is < 1% when remifentanil is administered concurrently or after a hypnotic induction agent. 37 (8%) 7 (2%) 0 2 (< 1%) 1 (< 1%) Bradycardia 62 (7%) 24 (5%) 3 (1%) 3 (3%) 11 (1%) 6 (1%) Shivering 3 (< 1%) 0 15 (5%) 9 (9%) 49 (5%) 10 (2%) Fever 1 (< 1%) 0 2 (< 1%) 0 44 (5%) 9 (2%) Dizziness 0 0 1 (< 1%) 0 27 (3%) 9 (2%) Visual disturbance 0 0 0 0 24 (3%) 14 (3%) Headache 0 0 1 (< 1%) 1 (1%) 21 (2%) 8 (2%) Respiratory depression 1 (< 1%) 0 19 (7%) 4 (4%) 17 (2%) 20 (4%) Apnea 0 1 (< 1%) 9 (3%) 2 (2%) 2 (< 1%) 1 (< 1%) Pruritus 2 (< 1%) 0 7 (2%) 1 (1%) 22 (2%) 7 (2%) Tachycardia 6 (< 1%) 7 (2%) 0 0 10 (1%) 8 (2%) Postoperative pain 0 0 7 (2%) 0 4 (< 1%) 5 (1%) Hypertension 10 (1%) 7 (2%) 5 (2%) 3 (3%) 12 (1%) 8 (2%) Agitation 2 (< 1%) 0 3 (1%) 1 (1%) 6 (< 1%) 1 (< 1%) Hypoxia 0 0 1 (< 1%) 0 10 (1%) 7 (2%) In the elderly population (> 65 years), the incidence of hypotension is higher, whereas the incidence of nausea and vomiting is lower.
Table 12: Inci…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 18 includes clinically significant drug interactions with ULTIVA. Table 18: Clinically Significant Drug Interactions with ULTIVA Benzodiazepines and other Central Nervous System (CNS) Depressants Clinical Impact: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants including alcohol, increases the risk of hypotension, respiratory depression, profound sedation, coma, and death [see Warnings and Precautions (5.3) ] . Intervention: Limit dosages and durations to the minimum required.
Follow patients closely for signs of respiratory depression and sedation. Patients should be advised to avoid alcohol for 24 hours after surgery [see Warnings and Precautions (5.3) ] . Examples: Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids (gabapentin or pregabalin), other opioids, alcohol.
Serotonergic Drugs Clinical Impact: The concomitant use of opioids with other drugs that affect the serotonergic neurotransmitter system has resulted in serotonin syndrome [see Warnings and Precautions (5.5) ] . Intervention: If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment. Discontinue ULTIVA if serotonin syndrome is suspected.
Examples: Selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), triptans, 5-HT3 receptor antagonists, drugs that effect the serotonin neurotransmitter system (e.g., mirtazapine, trazodone, tramadol), certain muscle relaxants (i.e., cyclobenzaprine, metaxalone), monoamine oxidase (MAO) inhibitors (those intended to treat psychiatric disorders and also others, such as linezolid and intravenous methylene blue). Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: MAOI interactions with opioids may manifest as serotonin syndrome [see Warnings and Precautions (5.5) ] or opioid toxicity (e.g., respiratory depression, coma) [see Warnings and Precautions (5.2) ].
If urgent use of ULTIVA is necessary, use test doses and frequent titration of small doses while closely monitoring blood pressure and signs and symptoms of CNS and respiratory depression. Intervention: The use of ULTIVA is not recommended for patients taking MAOIs or within 14 days of stopping such treatment. Mixed Agonist/Antagonist and Partial Agonist Opioid Analgesics Clinical Impact: May reduce the analgesic effect of ULTIVA and/or precipitate withdrawal symptoms.
Intervention: If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment. Consider discontinuing ULTIVA if patient is not responding appropriately to treatment and institute alternative analgesic treatment. Examples: butorphanol, nalbuphine, pentazocine, buprenorphine • Mixed Agonist/Antagonist and Partial Agonist Opioid Analgesics : May reduce the analgesic effect of ULTIVA and/or precipitate withdrawal symptoms.
If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment. ( 7 )
Drug Interactions In animals the duration of muscle paralysis from succinylcholine is not prolonged by remifentanil.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy : May cause fetal harm. ( 8.1 ) • Labor or Delivery : Respiratory depression and other opioid effects may occur in newborns whose mothers are given ULTIVA shortly before delivery. ( 8.1 ) • Lactation : Infants exposed to ULTIVA through breast milk should be monitored for excess sedation and respiratory depression.
( 8.2 ) • Pediatric Use : ULTIVA has not been studied in pediatric patients for use as a postoperative analgesic or as an analgesic component of monitored anesthesia care. ( 8.4 )
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome. Available data with remifentanil hydrochloride in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, reduced fetal rat body weight and pup weights were reported at 2.2 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min for a surgical procedure lasting 3 hours.
There were no malformations noted when remifentanil was administered via bolus injection to pregnant rats or rabbits during organogenesis at doses approximately 5 times and approximately equal, respectively, to a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min for a surgical procedure lasting 3 hours [see Data ] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate.
ULTIVA is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate. Opioid analgesics, including ULTIVA, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor.
Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression. Data Human Data In a human clinical trial, the average maternal remifentanil concentrations were approximately twice those seen in the fetus. In some cases, however, fetal concentrations were similar to those in the mother.
The umbilical arteriovenous ratio of remifentanil concentrations was approximately 30% suggesting metabolism of remifentanil in the neonate. Animal Data Pregnant rats were treated from Gestation Day 6 to 15 with intravenous remifentanil doses of 0.5, 1.6, or 5 mg/kg/day (0.2, 0.7, or 2.2 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min based on body surface area for a surgical procedure lasting 3 hours based on body surface area, respectively). Reduced fetal weights were reported in the high dose group; however, no malformations were reported in surviving fetuses despite a non-dose dependent increase in maternal mortality.
Pregnant rabbits were treated from Gestation Day 6 to 18 with intravenous remifentanil doses of 0.1, 0.5, or 0.8 mg/kg/day (0.09, 0.4, or 0.7 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min based on body surface area for a surgical procedure lasting 3 hours based on body surface area, respectively). No malformations were reported in survivi…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome. Available data with remifentanil hydrochloride in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, reduced fetal rat body weight and pup weights were reported at 2.2 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min for a surgical procedure lasting 3 hours.
There were no malformations noted when remifentanil was administered via bolus injection to pregnant rats or rabbits during organogenesis at doses approximately 5 times and approximately equal, respectively, to a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min for a surgical procedure lasting 3 hours [see Data ] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate.
ULTIVA is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate. Opioid analgesics, including ULTIVA, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor.
Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression. Data Human Data In a human clinical trial, the average maternal remifentanil concentrations were approximately twice those seen in the fetus. In some cases, however, fetal concentrations were similar to those in the mother.
The umbilical arteriovenous ratio of remifentanil concentrations was approximately 30% suggesting metabolism of remifentanil in the neonate. Animal Data Pregnant rats were treated from Gestation Day 6 to 15 with intravenous remifentanil doses of 0.5, 1.6, or 5 mg/kg/day (0.2, 0.7, or 2.2 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min based on body surface area for a surgical procedure lasting 3 hours based on body surface area, respectively). Reduced fetal weights were reported in the high dose group; however, no malformations were reported in surviving fetuses despite a non-dose dependent increase in maternal mortality.
Pregnant rabbits were treated from Gestation Day 6 to 18 with intravenous remifentanil doses of 0.1, 0.5, or 0.8 mg/kg/day (0.09, 0.4, or 0.7 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min based on body surface area for a surgical procedure lasting 3 hours based on body surface area, respectively). No malformations were reported in surviving fetuses despite clear maternal toxicity (decreased food consumption and body weights and increased mortality in all treatment groups).
Pregnant rats were treated from Gestation Day 6 to Lactation Day 21 with intravenous boluses of remifentanil 0.5, 1.6, or 5 mg/kg/day (0.2, 0.7, or 2.2 times a human intravenous infusion of an induction dose of 1 mcg/kg with a maintenance dose of 2 mcg/kg/min based on body surface area for a surgical procedure lasting 3 hours based on body surface area, respectively). Reduced birth weights were no…
🧒 Pediatric Use ▾
8.4Pediatric Use The efficacy and safety of ULTIVA as an analgesic agent for use in the maintenance of general anesthesia in outpatient and inpatient pediatric surgery have been established in controlled clinical studies in pediatric patients from birth to 12 years [see Clinical Studies (14.4) ] . The initial maintenance infusion regimen of ULTIVA evaluated in pediatric patients from birth to 2 months of age was 0.4 mcg/kg/min, the approved adult regimen for use with N 2 O. The clearance rate observed in neonates was highly variable and on average was 2 times higher than in the young healthy adult population.
Therefore, while a starting infusion rate of 0.4 mcg/kg/min may be appropriate for some neonates, an increased infusion rate may be necessary to maintain adequate surgical anesthesia, and additional bolus doses may be required. The individual dose for each patient should be carefully titrated. [See Clinical Pharmacology: Specific Populations: Pediatric Population (12.3) and Dosage and Administration, Table 2 and Maintenance of Anesthesia (2.2) .] ULTIVA has not been studied in pediatric patients for use as a postoperative analgesic or as an analgesic component of monitored anesthesia care.
🧓 Geriatric Use ▾
8.5Geriatric Use Respiratory depression is the chief risk for elderly patients treated with opioids and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration. Titrate the dosage of ULTIVA slowly in geriatric patients and frequently reevaluate the patient for signs of central nervous system and respiratory depression [see Warnings and Precautions (5.2) ] . Of the total number of subjects in clinical studies of ULTIVA, 486 were 65 and over (age range 66 to 90 years).
While the effective biological half-life of remifentanil is unchanged, elderly patients have been shown to be twice as sensitive as the younger population to the pharmacodynamic effects of remifentanil. The recommended starting dose of ULTIVA should be decreased by 50% in patients over 65 years of age [see Clinical Pharmacology (12.3) and Dosage and Administration (2.2) ] . Titrate the dosage of ULTIVA slowly in geriatric patients. [See Warnings and Precautions (5.5) .] The clearance of remifentanil is reduced (approximately 25%) in the elderly (> 65 years of age) compared to young adults (average 25 years of age).
However, remifentanil blood concentrations fall as rapidly after termination of administration in the elderly as in young adults. This drug is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute overdose with remifentanil can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see Clinical Pharmacology (12.2) ] . Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures.
For clinically significant respiratory or circulatory depression secondary to remifentanil overdose, stop the infusion or administer an opioid overdose reversal agent such as naloxone or nalmefene. Opioid overdose reversal agents should not be administered in the absence of clinically significant respiratory or circulatory depression secondary to remifentanil overdose. In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome.
The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be begun with care and by titration with smaller than usual doses of the reversal agent.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action ULTIVA is a µ-opioid agonist with rapid onset and peak effect, and short duration of action. The µ-opioid activity of ULTIVA is antagonized by opioid antagonists, including overdose reversal agents such as naloxone or nalmefene. Unlike other opioids, ULTIVA is rapidly metabolized by hydrolysis of the propanoic acid-methyl ester linkage by nonspecific blood and tissue esterases.
ULTIVA is not a substrate for plasma cholinesterase (pseudocholinesterase) and, therefore, patients with atypical cholinesterase are expected to have a normal duration of action.
12.2Pharmacodynamics The analgesic effects of ULTIVA are rapid in onset and offset. Its effects and side effects are dose dependent and similar to other µ-opioids. ULTIVA in humans has a rapid blood-brain equilibration half-time of 1 ± 1 minutes (mean ± SD) and a rapid onset of action.
The pharmacodynamic effects of ULTIVA closely follow the measured blood concentrations, allowing direct correlation between dose, blood levels, and response. Blood concentration decreases 50% in 3 to 6 minutes after a 1-minute infusion or after prolonged continuous infusion due to rapid distribution and elimination processes and is independent of duration of drug administration. Recovery from the effects of ULTIVA occurs rapidly (within 5 to 10 minutes).
New steady-state concentrations occur within 5 to 10 minutes after changes in infusion rate. When used as a component of an anesthetic technique, ULTIVA can be rapidly titrated to the desired depth of anesthesia/analgesia (e.g., as required by varying levels of intraoperative stress) by changing the continuous infusion rate or by administering an IV bolus injection. Effects on the Central Nervous System Remifentanil produces respiratory depression by direct action on brain stem respiratory centers.
The respiratory depression involves both a reduction in the responsiveness of the brain stem respiratory centers to increases in carbon dioxide tension and to electrical stimulation. Remifentanil causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings).
Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Remifentanil causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased.
Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED). Effects on the Cardiovascular System Remifentanil produces peripheral vasodilation which may result in orthostatic hypotension or syncope.
Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes and sweating and/or orthostatic hypotension. Caution must be used in hypovolemic patients, such as those suffering acute myocardial infarction, because remifentanil may cause or further aggravate their hypotension. Caution must also be used in patients with cor pulmonale who have received therapeutic doses of opioids.
Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans. They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models.
The clinical significance of these finding…
🧬 Mechanism of Action ▾
12.1Mechanism of Action ULTIVA is a µ-opioid agonist with rapid onset and peak effect, and short duration of action. The µ-opioid activity of ULTIVA is antagonized by opioid antagonists, including overdose reversal agents such as naloxone or nalmefene. Unlike other opioids, ULTIVA is rapidly metabolized by hydrolysis of the propanoic acid-methyl ester linkage by nonspecific blood and tissue esterases.
ULTIVA is not a substrate for plasma cholinesterase (pseudocholinesterase) and, therefore, patients with atypical cholinesterase are expected to have a normal duration of action.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ULTIVA (remifentanil hydrochloride) for Injection, for intravenous use, is supplied as follows: NDC Number Container Concentration Quantity 67457-912-01 3 mL Single-Dose Vial 1 mg lyophilized powder Box of 10 67457-913-02 5 mL Single-Dose Vial 2 mg lyophilized powder Box of 10 67457-914-05 10 mL Single-Dose Vial 5 mg lyophilized powder Box of 10 ULTIVA should be stored at 2° to 25°C (36° to 77°F). Discard unused portion.
📋 Description ▾
11 DESCRIPTION ULTIVA (remifentanil hydrochloride) for injection is an opioid agonist. The chemical name is 3-[4-methoxycarbonyl-4-[(1-oxopropyl)phenylamino]-1-piperidine]propanoic acid methyl ester, hydrochloride salt. The molecular weight is 412.91.
Its molecular formula is C 20 H 28 N 2 O 5 •HCl, and it has the following chemical structure. ULTIVA is a sterile, nonpyrogenic, preservative-free, white to off-white lyophilized powder for intravenous (IV) administration after reconstitution and dilution. Each vial contains 1 mg, 2 mg, or 5 mg of remifentanil base; 15 mg glycine; and hydrochloric acid to buffer the solutions to a nominal pH of 3 after reconstitution.
When reconstituted as directed, solutions of ULTIVA are clear and colorless and contain remifentanil hydrochloride (HCl) equivalent to 1 mg/mL of remifentanil base. The pH of reconstituted solutions of ULTIVA ranges from 2.5 to 3.5. Remifentanil hydrochloride has a pKa of 7.07.
Remifentanil hydrochloride has an n-octanol:water partition coefficient of 17.9 at pH 7.3. Remifentanil Hydrochloride Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Addiction, Abuse, and Misuse Inform patients that the use of ULTIVA, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions (5.1) ] . Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting ULTIVA or when the dosage is increased, and that it can occur even at recommended dosages. Hyperalgesia and Allodynia Advise patients to inform their healthcare provider if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see Warnings and Precautions (5.4) , Adverse Reactions (6) ] .
Serotonin Syndrome Inform patients that opioids could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop after discharge from the hospital. Instruct patients to inform their healthcare provider if they are taking, or plan to take serotonergic medications [see Warnings and Precautions (5.5) , Drug Interactions (7) ] .
Constipation Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention [see Adverse Reactions (6) , Clinical Pharmacology (12.2) ] . © 2026 Viatris Inc. ULTIVA is a registered trademark of Glaxo Group Limited, a GSK Company, licensed to the Viatris Companies. Diprivan ® is a registered trademark of Fresenius Kabi USA, LLC.
Manufactured in Ireland for: Mylan Institutional LLC, a Viatris Company Morgantown, WV 26505 U.S.A. 50109957 MI/NP:ULTIIJ:R10 Novaplus is a registered trademark of Vizient, Inc.