
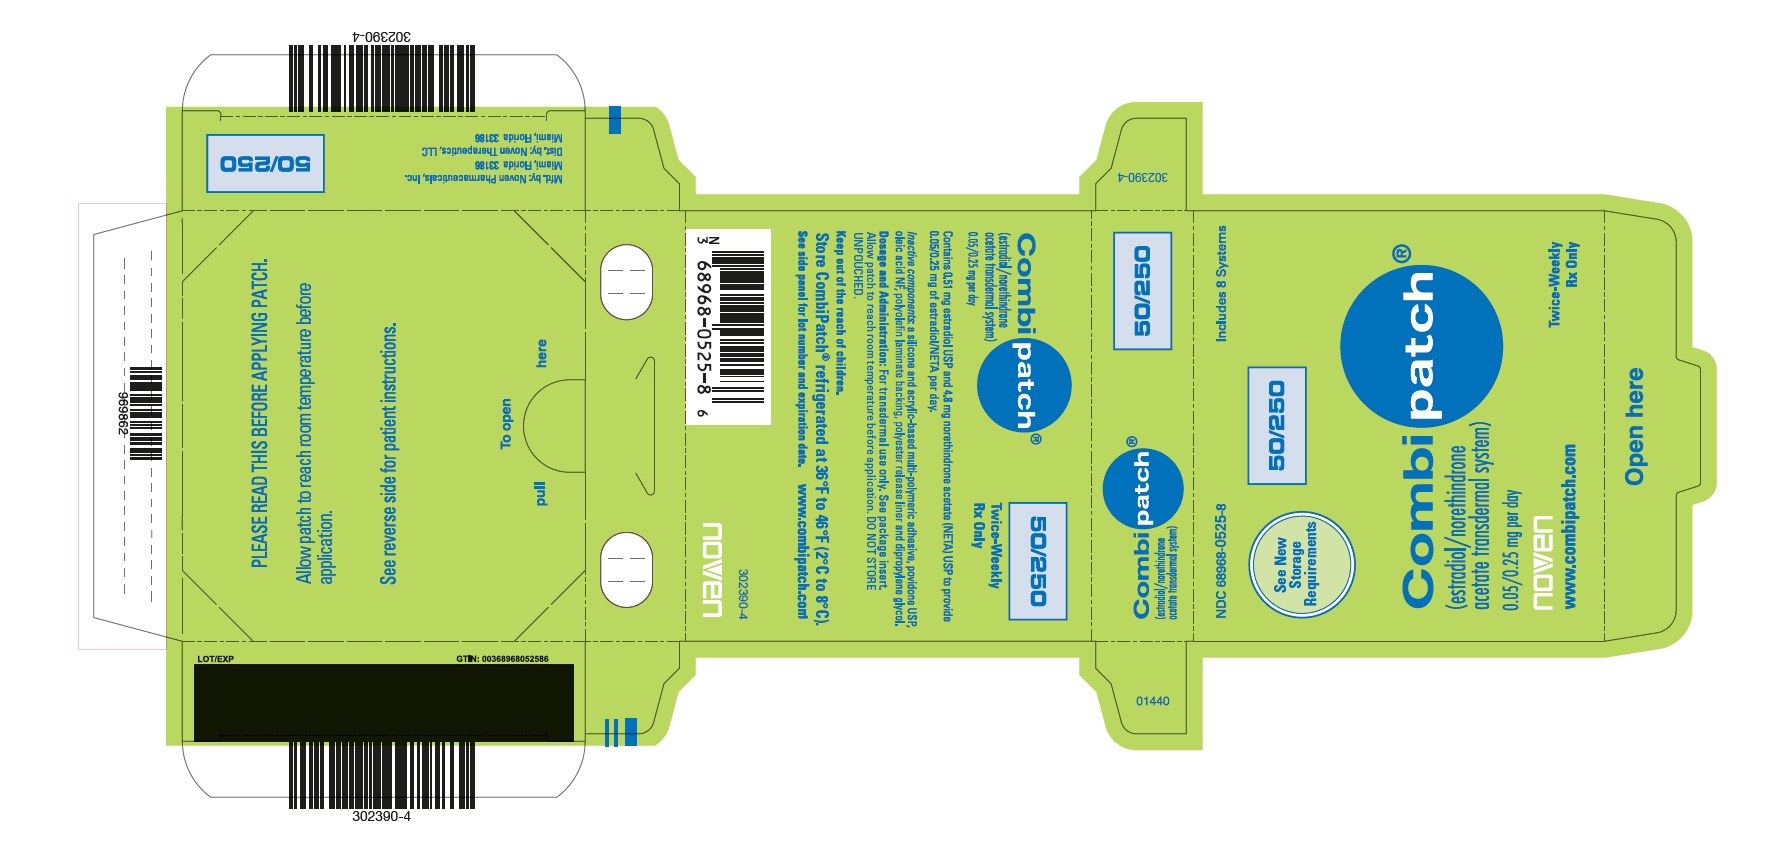
CombiPatch (estradiol/norethindrone acetate transdermal system) .05 mg/d; .25 mg/d Patch, Extended Release, 8 patches — NDC 68968-0525-8 (Billing 68968-0525-08)
This is a package of 8 patches of CombiPatch (estradiol/norethindrone acetate transdermal system) .05 mg/d; .25 mg/d Patch, Extended Release from Noven Therapeutics, LLC, marketed since Aug 1998 and currently FDA-listed; retail pharmacies pay about $31.79 per patche (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 040924
- GCN: 69124
- GPI-14 (Medi-Span): 24993002128730
- HICL (First Databank): 007310
- AHFS class code: 68:16.04.00
- RxCUI (RxNorm): 1251493
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Radioactive Diagnostic Agent class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Great question. The estradiol (the estrogen part) is what actually relieves your hot flashes, night sweats, and vaginal dryness by replacing the estrogen your body stopped making a...
- What exactly is this medicine doing for me — why do I need both an estrogen and a progestin?
- Most women notice things like breast tenderness, some spotting or light bleeding, headaches, or nausea — especially in the first few months. Those are common and usually settle dow...
- What are the most important side effects I should actually watch out for?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $31.786 | $254.29 / 8 patch |
| Medicaid paysCMS SDUD · 12 mo | $32.08 | $256.64 / 8 patch |
| Medicare drug plans payPart D · Q2 2026 | $32.02 | $256.18 / 8 patch |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68968-0525-08 You're viewing this Main listing | 8 POUCH in 1 CARTON / 1 PATCH in 1 POUCH / 3.5 d in 1 PATCH | 1998-08-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| CombiPatch (estradiol/norethindrone acetate transdermal system) .05 mg/d; .25 mg/dthis 68968-0525-08 | Noven | 8 patches | $31.786 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII E107L85C40
Dipropylene glycol is a clear liquid made from propylene glycol. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 2UMI9U37CP
Oleic acid is a naturally occurring fatty acid derived from plant or animal oils. It functions as an emulsifier and solvent in medicines, helping blend water and oil-based ingredients together and dissolving other components.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR DISORDERS, BREAST CANCER, ENDOMETRIAL CANCER, AND PROBABLE DEMENTIA Estrogen Plus Progestin Therapy Cardiovascular Disorders and Probable Dementia Estrogen plus progestin therapy should not be used for the prevention of cardiovascular disease or dementia. (See CLINICAL STUDIES and WARNINGS , Cardiovascular Disorders and Probable Dementia ). The Women’s Health Initiative (WHI) estrogen plus progestin substudy reported an increased risk of deep vein thrombosis (DVT), pulmonary embolism (PE), stroke and myocardial infarction (MI) in postmenopausal women (50 to 79 years of age) during 5.6 years of treatment with daily oral conjugated estrogens (CE) [0.625 mg] combined with medroxyprogesterone acetate (MPA) [2.5 mg], relative to placebo.
(See CLINICAL STUDIES and WARNINGS , Cardiovascular Disorders ). The WHI Memory Study (WHIMS) estrogen plus progestin ancillary study of the WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age or older during 4 years of treatment with daily CE (0.625 mg) combined with MPA (2.5 mg), relative to placebo. It is unknown whether this finding applies to younger postmenopausal women.
(See CLINICAL STUDIES and WARNINGS , Probable Dementia and PRECAUTIONS , Geriatric Use ). Breast Cancer The WHI estrogen plus progestin substudy demonstrated an increased risk of invasive breast cancer. (See CLINICAL STUDIES and WARNINGS , Malignant Neoplasms , Breast Cancer ).
In the absence of comparable data, these risks should be assumed to be similar for other doses of CE and MPA, and other combinations and dosage forms of estrogens and progestins. Estrogens with or without progestins should be prescribed at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman. Estrogen-Alone Therapy Endometrial Cancer There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens.
Adding a progestin to estrogen therapy has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Adequate diagnostic measures, including directed or random endometrial sampling when indicated, should be undertaken to rule out malignancy in postmenopausal women with undiagnosed persistent or recurring abnormal genital bleeding. (See WARNINGS , Malignant Neoplasms , Endometrial Cancer ).
Cardiovascular Disorders and Probable Dementia Estrogen-alone therapy should not be used for the prevention of cardiovascular disease or dementia (See CLINICAL STUDIES and WARNINGS , Cardiovascular Disorders and Probable Dementia ). The WHI estrogen-alone substudy reported increased risks of stroke and DVT in postmenopausal women (50 to 79 years of age) during 7.1 years of treatment with daily oral CE (0.625 mg)-alone, relative to placebo. (See CLINICAL STUDIES and WARNINGS , Cardiovascular Disorders ).
The WHIMS estrogen-alone ancillary study of the WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age or older during 5.2 years of treatment with daily CE (0.625 mg)-alone, relative to placebo. It is unknown whether this finding applies to younger postmenopausal women. (See CLINICAL STUDIES and WARNINGS , Probable Dementia and PRECAUTIONS , Geriatric Use ).
In the absence of comparable data, these risks should be assumed to be similar for other doses of CE and other dosage forms of estrogens. Estrogens with or without progestins should be prescribed at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE CombiPatch is indicated in a woman with a uterus for: Treatment of moderate to severe vasomotor symptoms due to menopause. Treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause. When prescribing solely for the treatment of symptoms of vulvar and vaginal atrophy, topical vaginal products should be considered. Treatment of hypoestrogenism due to hypogonadism, castration, or primary ovarian failure.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Generally, when estrogen therapy is prescribed for a postmenopausal woman with a uterus, a progestin should be considered to reduce the risk of endometrial cancer. A woman without a uterus generally does not need a progestin. In some cases, however, hysterectomized women with a history of endometriosis may need a progestin.
Use of estrogen-alone or in combination with a progestin, should be with the lowest effective dose and for the shortest duration consistent with treatment goals and risks for the individual woman. Postmenopausal women should be reevaluated periodically as clinically appropriate to determine whether treatment is still necessary. Adequate diagnostic measures, such as directed or random endometrial sampling, when indicated, should be undertaken to rule out malignancy in a postmenopausal woman with a uterus with undiagnosed persistent or recurring abnormal genital bleeding.
Initiation of Therapy Patients should be started at the lowest dose. Estrogens with or without progestins should be prescribed at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman. The lowest effective dose of CombiPatch has not been determined in clinical trials.
Women not currently using continuous estrogen or combination estrogen plus progestin therapy may start therapy with CombiPatch at any time. However, women currently using continuous estrogen or combination estrogen plus progestin therapy should complete the current cycle of therapy, before initiating CombiPatch therapy. Women often experience withdrawal bleeding at the completion of the cycle.
The first day of this bleeding would be an appropriate time to begin CombiPatch therapy. Therapeutic Regimens Combination estrogen plus progestin regimens are indicated for women with an intact uterus. Two CombiPatch (estradiol/NETA) transdermal delivery systems are available: 0.05 mg estradiol with 0.14 mg NETA per day (9 cm 2 ) and 0.05 mg estradiol with 0.25 mg NETA per day (16 cm 2 ).
The lowest effective dose should be used. For all regimens, women should be reevaluated at 3- to 6-month intervals to determine if changes in hormone therapy or if continued hormone therapy is appropriate. Continuous Combined Regimen CombiPatch 0.05 mg estradiol/0.14 mg NETA per day (9 cm 2 ) matrix transdermal system is used for continuous uninterrupted treatment applied twice weekly on the lower abdomen.
A new system should be applied to the skin every 3 to 4 days (twice weekly) during a 28-day cycle. Additionally, a dose of 0.05 mg estradiol/0.25 mg NETA (16 cm 2 system) is available if a greater progestin dose is desired. Irregular bleeding may occur particularly in the first six months, but generally decreases with time, and often to an amenorrheic state.
Continuous Sequential Regimen CombiPatch can be applied as a sequential regimen in combination with an estradiol-only transdermal delivery system. In this treatment regimen, a 0.05 mg per day (nominal delivery rate) estradiol transdermal system (Vivelle-Dot ® ) is worn for the first 14 days of a 28-day cycle, replacing the system every 3 to 4 days (twice weekly) according to product directions. For the remaining 14 days of the 28-day cycle, CombiPatch 0.05 mg estradiol/0.14 mg NETA per day (9 cm 2 ) transdermal system should be worn continuously on the lower abdomen.
The CombiPatch system should be replaced every 3 to 4 days (twice weekly) during this 14-day period in the 28-day cycle. Additionally, a dose of 0.05 mg estradiol/0.25 mg NETA (16 cm 2 system) is available if a greater progestin dose is desired. Women should be advised that monthly withdrawal bleeding often occurs.
Application of the System Site Selection CombiPatch should be placed on a smooth (fold-free), clean, dry area of the skin on the lower abdomen. CombiPatch should not be applied to or near the breasts. The area selected should not be oily (which can impair adherence of the system),… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS CombiPatch is contraindicated in women with any of the following conditions: Undiagnosed abnormal genital bleeding. Known, suspected, or history of breast cancer. Known or suspected estrogen-dependent neoplasia.
Active DVT, PE, or history of these conditions. Active arterial thromboembolic disease (for example, stroke and MI), or a history of these conditions. Known anaphylactic reaction or angioedema or hypersensitivity with CombiPatch.
Known liver impairment or disease. Known protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders. Known or suspected pregnancy.
⚠️ Warnings ▾
WARNINGS See BOXED WARNING . 1. Cardiovascular Disorders An increased risk of PE, DVT, stroke and MI has been reported with estrogen plus progestin therapy.
An increased risk of stroke and DVT has been reported with estrogen-alone therapy. Should any of these occur or be suspected, estrogen with or without progestin therapy should be discontinued immediately. Risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (VTE) (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus) should be managed appropriately. a.
Stroke In the WHI estrogen plus progestin substudy, a statistically significant increased risk of stroke was reported in women 50 to 79 years of age receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 per 10,000 women-years). (See CLINICAL STUDIES ) The increase in risk was demonstrated after the first year and persisted. 1 Should a stroke occur or be suspected, estrogen plus progestin therapy should be discontinued immediately.
In the WHI estrogen-alone substudy, a statistically significant increased risk of stroke was reported in women 50 to 79 years of age receiving daily CE (0.625 mg)-alone compared to women in the same age group receiving placebo (45 versus 33 per 10,000 women-years). (See CLINICAL STUDIES ) The increase in risk was demonstrated in year 1 and persisted. Should a stroke occur or be suspected, estrogen-alone therapy should be discontinued immediately.
Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving CE (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years). 1 b. Coronary Heart Disease In the WHI estrogen plus progestin substudy, there was a statistically non-significant increased risk of CHD events (defined as nonfatal MI, silent MI, or CHD death) reported in women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (41 versus 34 per 10,000 women years).
1 An increase in relative risk was demonstrated in year 1, and a trend toward decreasing relative risk was reported in years 2 through 5 (See CLINICAL STUDIES ). In the WHI estrogen-alone substudy, no overall effect on CHD events was reported in women receiving estrogen-alone compared to placebo. 2 (See CLINICAL STUDIES ) Subgroup analyses of women 50 to 59 years of age suggest a statistically nonsignificant reduction in CHD events (CE [0.625 mg]-alone compared to placebo) in women less than 10 years since menopause (8 versus 16 per 10,000 women-years).
1 In postmenopausal women with documented heart disease (n=2,763, average 66.7 years of age), in a controlled clinical trial of secondary prevention of cardiovascular disease (Heart and Estrogen/Progestin Replacement Study; HERS), treatment with daily CE (0.625 mg) plus MPA (2.5 mg) demonstrated no cardiovascular benefit. During an average follow-up of 4.1 years, treatment with CE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established CHD. There were more CHD events in the CE plus MPA-treated group than in the placebo group in year 1, but not during the subsequent years.
Two thousand three hundred twenty-one (2,321) women from the original HERS trial agreed to participate in an open-label extension of HERS, HERS II. Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years overall. Rates of CHD events were comparable among women in the CE plus MPA group and the placebo group in the HERS, the HERS II, and overall. c.
Venous Thromboembolism In the WHI estrogen plus progestin substudy, a statistically significant 2-fold greater rate of VTE (DVT and PE) was reported in women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to placebo (35 versus 17 per 10,000 women-years). Statistically signi… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS See BOXED WARNING , WARNINGS , and PRECAUTIONS . Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Table 9.
All Adverse Reactions Regardless of Relationship Reported at a Frequency of Greater than or Equal to 5 percent with CombiPatch VASOMOTOR SYMPTOM STUDIES CombiPatch 0.05/0.14 mg per day† CombiPatch 0.05/0.25 mg per day† Placebo n=113 n=112 n=107 Body as a Whole 46% 48% 41% Abdominal Pain 7% 6% 4% Accidental Injury 4% 5% 8% Asthenia 8% 12% 4% Back Pain 11% 9% 5% Flu Syndrome 9% 5% 7% Headache 18% 20% 20% Pain 6% 4% 9% Digestive 19% 23% 24% Diarrhea 4% 5% 7% Dyspepsia 1% 5% 5% Flatulence 4% 5% 4% Nausea 11% 8% 7% Nervous 16% 28% 28% Depression 3% 5% 9% Insomnia 3% 6% 7% Nervousness 3% 5% 1% Respiratory 24% 38% 26% Pharyngitis 4% 10% 2% Respiratory Disorder 7% 12% 7% Rhinitis 7% 13% 9% Sinusitis 4% 9% 9% Skin and Appendages 8% 17% 16% Application Site Reaction* 2% 6% 4% Urogenital 54% 63% 28% Breast Pain 25% 31% 7% Dysmenorrhea 20% 21% 5% Leukorrhea 5% 5% 3% Menstrual Disorder 6% 12% 2% Papanicolaou Smear Suspicious 8% 4% 5% Vaginitis 6% 13% 5% †Represents milligrams of estradiol/NETA delivered daily by each system. *Application site reactions includes localized bleeding, bruising, burning, discomfort, dryness, eczema, edema, erythema, inflammation, irritation, pain, papules, paresthesia, pruritus, rash, skin discoloration, skin pigmentation, swelling, urticaria, and vesicles.
Table 10. All Adverse Reactions Regardless of Relationship Reported at a Frequency of Greater than or Equal to 5 percent with CombiPatch ENDOMETRIAL HYPERPLASIA STUDIES CombiPatch 0.05/0.14 mg per day† n=325 CombiPatch 0.05/0.25 mg per day† n=312 Vivelle 0.05 mg per day n=318 Body as a Whole 61% 60% 59% Abdominal Pain 12% 14% 16% Accidental Injury 10% 11% 8% Asthenia 10% 13% 11% Back Pain 15% 14% 13% Flu Syndrome 14% 10% 7% Headache 25% 17% 21% Infection 5% 3% 3% Pain 19% 15% 13% Digestive 42% 32% 31% Constipation 2% 5% 3% Diarrhea 14% 9% 7% Dyspepsia 8% 6% 5% Flatulence 7% 5% 6% Nausea 8% 12% 11% Tooth Disorder 6% 4% 1% Metabolic and Nutritional Disorders 12% 13% 11% Peripheral Edema 6% 6% 5% Musculoskeletal 17% 17% 15% Arthralgia 6% 6% 5% Nervous 33% 30% 28% Depression 8% 9% 8% Dizziness 6% 7% 5% Insomnia 8% 6% 4% Nervousness 5% 6% 3% Respiratory 45% 43% 40% Bronchitis 5% 3% 4% Pharyngitis 9% 9% 8% Respiratory Disorder 13% 9% 13% Rhinitis 19% 22% 17% Sinusitis 10% 12% 12% Skin and Appendages 38% 37% 31% Acne 4% 5% 4% Application Site Reaction* 20% 23% 17% Rash 6% 5% 3% Urogenital 71% 79% 74% Breast Enlargement 2% 7% 2% Breast Pain 34% 48% 40% Dysmenorrhea 30% 31% 19% Leukorrhea 10% 8% 9% Menorrhagia 2% 5% 9% Menstrual Disorder 17% 19% 14% Vaginal Hemorrhage 3% 6% 12% Vaginitis 9% 13% 13% †Represents milligrams of estradiol/NETA delivered daily by each system. *Application site reactions includes localized bleeding, bruising, burning, discomfort, dryness, eczema, edema, erythema, inflammation, irritation, pain, papules, paresthesia, pruritus, rash, skin discoloration, skin pigmentation, swelling, urticaria, and vesicles.
Postmarketing Experience The following additional adverse reactions have been identified during post-approval use of CombiPatch. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Genitourinary System Endometrial hyperplasia, endocervical polyp, uterine leiomyomata, fallopian tube cyst, uterine spasms.
Breast Breast cancer. Cardiovascular Hypertension, varicose veins. Gastrointestinal Jaundice cholestatic, cholelithiasis, gall bladder disorder, transaminases increased.
Skin Skin discoloration. Central Nervous System Affect lability, libido disorder, migraine, vertig… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions No drug interaction studies have been conducted with CombiPatch. In vitro and in vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4). Therefore, inducers or inhibitors of CYP3A4 may affect estrogen drug metabolism.
Inducers of CYP3A4 such as St. John’s wort ( Hypericum perforatum ) preparations, anticonvulsants (e.g., phenobarbital, phenytoin and carbamazepine), phenylbutazone, and anti-infectives (e.g., rifampin, rifabutin, nevirapine and efavirenz) may reduce plasma concentrations of estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile. Inhibitors of CYP3A4 such as erythromycin, clarithromycin, ketoconazole, itraconazole, ritonavir, nelfinavir and grapefruit juice may increase plasma concentrations of estrogens and may result in side effects.
Adhesion Averaging across 6 clinical trials lasting 3 months to 1 year, of 1,287 patients treated, CombiPatch transdermal systems completely adhered to the skin nearly 90 percent of the time over the 3- to 4-day wear period. Less than 2 percent of the patients required reapplication or replacement of systems due to lifting or detachment. Two patients (0.2 percent) discontinued therapy during clinical trials due to adhesion failure.
🔄 Drug / Laboratory Test Interactions ▾
D. Drug-Laboratory Test Interactions 1. Accelerated prothrombin time, partial thromboplastin time, and platelet aggregation time; increased platelet count; increased factors II, VII antigen, VIII antigen, VIII coagulant activity, IX, X, XII, VII-X complex, II-VII-X complex; and beta-thromboglobulin; decreased levels of anti-factor Xa and antithrombin III; decreased antithrombin III activity; increased levels of fibrinogen and fibrinogen activity; increased plasminogen antigen and activity.
2. Increased TBG leading to increased circulating total thyroid hormone, as measured by protein-bound iodine (PBI), T 4 levels (by column or by radioimmunoassay) or T 3 levels by radioimmunoassay. T 3 resin uptake is decreased, reflecting the elevated TBG.
Free T 4 and free T 3 concentrations are unaltered. Women on thyroid replacement therapy may require higher doses of thyroid hormone. 3.
Other binding proteins may be elevated in serum (i.e., corticosteroid binding globulin [CBG], SHBG), leading to increased circulating corticosteroids and sex steroids, respectively. Free hormone concentrations, such as testosterone and estradiol, may be decreased. Other plasma proteins may be increased (angiotensinogen/renin substrate, alpha-1-antitrypsin, ceruloplasmin).
4. Increased plasma high density lipoprotein (HDL) and HDL-2 subfraction concentrations, reduced low density lipoprotein (LDL) cholesterol concentration, increased triglycerides levels. 5.
Impaired glucose tolerance.
🤰 Pregnancy ▾
F. Pregnancy CombiPatch should not be used during pregnancy. (See CONTRAINDICATIONS .) There appears to be little or no increased risk of birth defects in children born to women who have used estrogens and progestins as an oral contraceptive inadvertently during early pregnancy.
🧒 Pediatric Use ▾
H. Pediatric Use CombiPatch is not indicated in children. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
I. Geriatric Use There have not been sufficient numbers of geriatric women involved in studies utilizing CombiPatch to determine whether those over 65 years of age differ from younger subjects in their response to CombiPatch. The Women’s Health Initiative Studies In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age.
(See CLINICAL STUDIES . ) In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age. (See CLINICAL STUDIES . ) The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen plus progestin or estrogen-alone when compared to placebo. (See CLINICAL STUDIES and WARNINGS , Probable Dementia . ) Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women.
(See CLINICAL STUDIES and WARNINGS , Probable Dementia . )
🆘 Overdosage ▾
OVERDOSAGE Overdosage of estrogen or estrogen plus progestin may cause nausea, vomiting, breast tenderness, abdominal pain, drowsiness and fatigue, and withdrawal bleeding may occur in women. Treatment of overdose consists of discontinuation of CombiPatch therapy with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, 2 estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH), and follicle stimulating hormone (FSH) through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women. Pharmacokinetics Absorption Estradiol: Estrogens used in hormone therapy are well absorbed through the skin, mucous membranes, and gastrointestinal tract. Administration of CombiPatch every 3 to 4 days in postmenopausal women produces average steady-state estradiol serum concentrations of 45 to 50 pg/mL, which are equivalent to the normal ranges observed at the early follicular phase in premenopausal women.
These concentrations are achieved within 12 to 24 hours following CombiPatch application. Minimal fluctuations in serum estradiol concentrations are observed following CombiPatch application, indicating consistent hormone delivery over the application interval. In 1 study, serum concentrations of estradiol were measured in 40 healthy, postmenopausal women throughout 3 consecutive CombiPatch applications to the abdomen (each dose was applied for three 3.5-day periods).
The corresponding pharmacokinetic parameters are summarized in Table 1. Table 1. Mean (SD) Serum Estradiol and Estrone Concentrations (pg/mL) at Steady-State (Uncorrected for Baseline Levels) Estradiol System Size Dose Estradiol/NETA (mg per day) C max C min C avg 9 cm 2 0.05/0.14 71 (32) 27 (17) 45 (21) 16 cm 2 0.05/0.25 71 (30) 37 (17) 50 (21) Estrone 9 cm 2 0.05/0.14 72 (23) 49 (19) 54 (19) 16 cm 2 0.05/0.25 78 (22) 58 (22) 60 (18) Norethindrone: Progestins used in hormone therapy are well absorbed through the skin, mucous membranes, and gastrointestinal tract.
Norethindrone steady-state concentrations are attained within 24 hours of application of the CombiPatch transdermal delivery systems. Minimal fluctuations in serum norethindrone concentrations are observed following CombiPatch treatment, indicating consistent hormone delivery over the application interval. Serum concentrations of norethindrone increase linearly with increasing doses of NETA.
In 1 study, serum concentrations of norethindrone were measured in 40 healthy, postmenopausal women throughout 3 consecutive CombiPatch applications to the abdomen (each dose was applied for three 3.5-day periods). The corresponding pharmacokinetic parameters are summarized in Table 2. Table 2.
Mean (SD) Serum Norethindrone Concentrations (pg/mL) at Steady-State System Size Dose Estradiol/NETA (mg per day) C max C min C avg 9 cm 2 0.05/0.14 617 (341) 386 (137) 489 (244) 16 cm 2 0.05/0.25 1060 (543) 686 (306) 840 (414) Distribution Estradiol: The distribution of exogenous estrogens is similar to that of endogenous estrogens. Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in the blood larg… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED CombiPatch estradiol/NETA transdermal delivery system is available in: System Nominal Delivery Rate * Size Estradiol/NETA Presentation NDC Markings 9 cm 2 0.05/0.14 mg per day 8 systems per carton 68968-0514-8 CombiPatch 0.05/0.14 mg per day 16 cm 2 0.05/0.25 mg per day 8 systems per carton 68968-0525-8 CombiPatch 0.05/0.25 mg per day * Nominal delivery rate described. See DESCRIPTION for more details regarding drug delivery. Storage Conditions Store CombiPatch in the refrigerator at 36℉ to 46℉ (2℃ to 8℃).
Store the systems in the sealed foil pouch. Do not store the system in areas where extreme temperatures can occur. Keep this and all medicines out of the reach of children.
Vivelle® is a registered trademark of Novartis Corporation. & Vivelle-Dot ® is a registered trademark of Novartis AG.
📋 Description ▾
DESCRIPTION CombiPatch ® (estradiol/norethindrone acetate transdermal system) is an adhesive-based matrix transdermal patch designed to release both estradiol, an estrogen, and norethindrone acetate (NETA), a progestational agent, continuously upon application to intact skin. Two systems are available, providing the following in vivo delivery rates of estradiol and NETA. 1 NETA=norethindrone acetate.
2 Based on in vivo/in vitro flux data, delivery of both components per day via skin of average permeability (interindividual variation in skin permeability is approximately 20 percent). System Size Estradiol (mg) NETA 1 (mg) Nominal Delivery Rate 2 (mg per day) Estradiol / NETA 9 cm 2 round 0.62 2.7 0.05/0.14 16 cm 2 round 0.51 4.8 0.05/0.25 Estradiol USP (estradiol) is a white to creamy white, odorless, crystalline powder, chemically described as estra-1,3,5(10)-triene-3,17 β -diol. The molecular weight of estradiol is 272.39 and the molecular formula is C 18 H 24 O 2 .
NETA USP is a white to creamy white, odorless, crystalline powder, chemically described as 17-hydroxy-19-nor-17α-pregn-4-en-20-yn-3-one acetate. The molecular weight of NETA is 340.47 and the molecular formula is C 22 H 28 O 3 . The structural formulas for estradiol and NETA are: CombiPatch is comprised of 3 layers.
Proceeding from the visible surface toward the surface attached to the skin, these layers are (1) a translucent polyolefin film backing, (2) an adhesive layer containing estradiol, NETA, acrylic adhesive, silicone adhesive, oleic acid NF, povidone USP and dipropylene glycol, and (3) a polyester release protective liner, which is attached to the adhesive surface and must be removed before the system can be used. The active components of the system are estradiol USP and NETA USP. The remaining components of the system are pharmacologically inactive.
Chemical Structure Layer
💬 Information for Patients ▾
B. Patient Information Physicians are advised to discuss the content of the PATIENT INFORMATION leaflet and INSTRUCTIONS FOR USE with patients for whom they prescribe CombiPatch.
Patient Information CombiPatch (käm-bē `pach) (estradiol/norethindrone acetate transdermal system) Read this Patient Information before you start using CombiPatch and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your menopausal symptoms or your treatment.
What is the most important information I should know about CombiPatch (a combination of estrogen and progestin hormones)? Do not use estrogens with progestins to prevent heart disease, heart attacks, strokes, or dementia (decline of brain function). Using estrogens with progestins may increase your chances of getting heart attacks, strokes, breast cancer, or blood clots.
Using estrogens with progestins may increase your chance of getting dementia, based on a study of women 65 years of age or older. Do not use estrogen-alone to prevent heart disease, heart attacks, strokes or dementia. Using estrogen-alone may increase your chances of getting cancer of the uterus (womb).
Using estrogen-alone may increase your chance of getting stroke or blood clots. Using estrogen-alone may increase your chance of getting dementia, based on a study of women 65 years of age or older. You and your healthcare provider should talk regularly about whether you still need treatment with CombiPatch.
What is CombiPatch? CombiPatch is a prescription medicine patch (Transdermal System) that contains 2 kinds of hormones, estrogen and progestin. What is CombiPatch used for?
CombiPatch is used after menopause to: Reduce moderate to severe hot flashes Estrogens are hormones made by a woman’s ovaries. The ovaries normally stop making estrogens when a woman is between 45 and 55 years old. This drop in body estrogen levels causes the “change of life” or menopause (the end of monthly menstrual periods).
Sometimes, both ovaries are removed during an operation before natural menopause takes place. The sudden drop in estrogen levels causes “surgical menopause.” When estrogen levels begin dropping, some women get very uncomfortable symptoms, such as feelings of warmth in the face, neck, and chest or sudden strong feelings of heat and sweating (“hot flashes” or “hot flushes”). In some women, the symptoms are mild, and they will not need to use estrogens.
In other women, symptoms can be more severe. Treat moderate to severe menopausal changes in and around your vagina You and your healthcare provider should talk regularly about whether you still need treatment with CombiPatch to control these problems. If you use CombiPatch only to treat menopausal changes in and around your vagina, talk with your healthcare provider about whether a topical vaginal product would be better for you.
Treat certain conditions in women before menopause if their ovaries do not make enough estrogens naturally. You and your healthcare provider should talk regularly about whether you still need treatment with CombiPatch. Who should not use CombiPatch?
Do not use CombiPatch if you have had your uterus (womb) removed (hysterectomy). CombiPatch contains a progestin to decrease the chance of getting cancer of the uterus. If you do not have a uterus, you do not need a progestin and you should not use CombiPatch.
Do not start using CombiPatch if you: have unusual vaginal bleeding Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. currently have or have had certain cancers Estrogens may increase the chance of getting certain types of cancers, including cancer of the breast or uterus. If you have or have had cancer, talk with your health care provider about whether you should use CombiPatch. had a stroke or heart attack currently have or have had blood c… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS A. General 1. Addition of a Progestin when a Woman has not had a Hysterectomy Studies of the addition of a progestin for 10 or more days of a cycle of estrogen administration, or daily with estrogen in a continuous regimen, have reported a lowered incidence of endometrial hyperplasia than would be induced by estrogen treatment alone.
Endometrial hyperplasia may be a precursor to endometrial cancer. There are, however, possible risks that may be associated with the use of progestins with estrogens compared to estrogen-alone regimens. These include an increased risk of breast cancer.
2. Elevated Blood Pressure In a small number of case reports, substantial increases in blood pressure have been attributed to idiosyncratic reactions to estrogens. In a large, randomized, placebo-controlled clinical trial, a generalized effect of estrogen therapy on blood pressure was not seen.
3. Hypertriglyceridemia In women with preexisting hypertriglyceridemia, estrogen therapy may be associated with elevations of plasma triglycerides leading to pancreatitis. Consider discontinuation of treatment if pancreatitis occurs.
4. Hepatic Impairment and/or Past History of Cholestatic Jaundice Although transdermally administered estrogen therapy avoids first-pass hepatic metabolism, estrogens may be poorly metabolized in women with impaired liver function. For women with a history of cholestatic jaundice associated with past estrogen use or with pregnancy, caution should be exercised and in the case of recurrence, medication should be discontinued.
5. Hypothyroidism Estrogen administration leads to increased thyroid-binding globulin (TBG) levels. Women with normal thyroid function can compensate for the increased TBG by making more thyroid hormone, thus maintaining free T 4 and T 3 serum concentrations in the normal range.
Women dependent on thyroid hormone replacement therapy who are also receiving estrogens may require increased doses of their thyroid replacement therapy. These women should have their thyroid function monitored in order to maintain their free thyroid hormone levels in an acceptable range. 6.
Fluid Retention Estrogens plus progestins may cause some degree of fluid retention. Women with conditions which might be influenced by this factor, such as cardiac or renal impairment warrant careful observation when estrogens plus progestins are prescribed. 7.
Hypocalcemia Estrogen therapy should be used with caution in women with hypoparathyroidism as estrogen-induced hypocalcemia may occur. 8. Exacerbation of Endometriosis A few cases of malignant transformation of residual endometrial implants have been reported in women treated post-hysterectomy with estrogen-alone therapy.
For women known to have residual endometriosis post-hysterectomy, the addition of progestin should be considered. 9. Exacerbation of Other Conditions Estrogen therapy may cause an exacerbation of asthma, diabetes mellitus, epilepsy, migraine or porphyria, systemic lupus erythematosus, and hepatic hemangiomas and should be used with caution in women with these conditions.
B. Patient Information Physicians are advised to discuss the content of the PATIENT INFORMATION leaflet and INSTRUCTIONS FOR USE with patients for whom they prescribe CombiPatch. C.
Laboratory Tests Serum FSH and estradiol levels have not been shown to be useful in the management of moderate to severe vasomotor symptoms and moderate to severe symptoms of vulvar and vaginal atrophy. Laboratory parameters may be useful in guiding dosage for the treatment of hypoestrogenism due to hypogonadism, castration and primary ovarian failure. D.
Drug-Laboratory Test Interactions 1. Accelerated prothrombin time, partial thromboplastin time, and platelet aggregation time; increased platelet count; increased factors II, VII antigen, VIII antigen, VIII coagulant activity, IX, X, XII, VII-X complex, II-VII-X complex; and beta-thromboglobulin; decreased levels of anti-factor Xa and antithrombin III; decreased ant… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
G. Nursing Mothers CombiPatch should not be used during lactation. Estrogen administration to nursing women has been shown to decrease the quantity and quality of the breast milk. Detectable amounts of estrogens and progestins have been identified in the breast milk of women receiving these drugs. Caution should be exercised when CombiPatch is administered to a nursing woman.
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption Estradiol: Estrogens used in hormone therapy are well absorbed through the skin, mucous membranes, and gastrointestinal tract. Administration of CombiPatch every 3 to 4 days in postmenopausal women produces average steady-state estradiol serum concentrations of 45 to 50 pg/mL, which are equivalent to the normal ranges observed at the early follicular phase in premenopausal women. These concentrations are achieved within 12 to 24 hours following CombiPatch application.
Minimal fluctuations in serum estradiol concentrations are observed following CombiPatch application, indicating consistent hormone delivery over the application interval. In 1 study, serum concentrations of estradiol were measured in 40 healthy, postmenopausal women throughout 3 consecutive CombiPatch applications to the abdomen (each dose was applied for three 3.5-day periods). The corresponding pharmacokinetic parameters are summarized in Table 1.
Table 1. Mean (SD) Serum Estradiol and Estrone Concentrations (pg/mL) at Steady-State (Uncorrected for Baseline Levels) Estradiol System Size Dose Estradiol/NETA (mg per day) C max C min C avg 9 cm 2 0.05/0.14 71 (32) 27 (17) 45 (21) 16 cm 2 0.05/0.25 71 (30) 37 (17) 50 (21) Estrone 9 cm 2 0.05/0.14 72 (23) 49 (19) 54 (19) 16 cm 2 0.05/0.25 78 (22) 58 (22) 60 (18) Norethindrone: Progestins used in hormone therapy are well absorbed through the skin, mucous membranes, and gastrointestinal tract. Norethindrone steady-state concentrations are attained within 24 hours of application of the CombiPatch transdermal delivery systems.
Minimal fluctuations in serum norethindrone concentrations are observed following CombiPatch treatment, indicating consistent hormone delivery over the application interval. Serum concentrations of norethindrone increase linearly with increasing doses of NETA. In 1 study, serum concentrations of norethindrone were measured in 40 healthy, postmenopausal women throughout 3 consecutive CombiPatch applications to the abdomen (each dose was applied for three 3.5-day periods).
The corresponding pharmacokinetic parameters are summarized in Table 2. Table 2. Mean (SD) Serum Norethindrone Concentrations (pg/mL) at Steady-State System Size Dose Estradiol/NETA (mg per day) C max C min C avg 9 cm 2 0.05/0.14 617 (341) 386 (137) 489 (244) 16 cm 2 0.05/0.25 1060 (543) 686 (306) 840 (414) Distribution Estradiol: The distribution of exogenous estrogens is similar to that of endogenous estrogens.
Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in the blood largely bound to sex hormone-binding globulin (SHBG) and albumin. Norethindrone: In plasma, norethindrone is bound approximately 90 percent to SHBG and albumin.
Metabolism Estradiol: Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. These transformations take place mainly in the liver.
Estradiol is converted reversibly to estrone, and both can be converted to estriol, which is a major urinary metabolite. Estrogens also undergo enterohepatic recirculation via sulfate and glucuronide conjugation in the liver, biliary secretion of conjugates into the intestine, and hydrolysis in the intestine followed by reabsorption. In postmenopausal women a significant portion of the circulating estrogens exist as sulfate conjugates, especially estrone sulfate, which serves as a circulating reservoir for the formation of more active estrogens.
Norethindrone: NETA is hydrolyzed to the active moiety, norethindrone, in most tissues including skin and blood. Norethindrone is primarily metabolized in the liver. Excretion Estradiol: Estradiol, estrone, and estriol are excreted in the urine along with glucuronide and sulfate conjugates.
Estradiol has a short elimination half-life of approximately 2 to 3 hours; therefore, a rapid decline in serum l… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
CLINICAL STUDIES Effects on Vasomotor Symptoms In 2 clinical trials designed to assess the degree of relief of moderate to severe vasomotor symptoms in postmenopausal women (n=332), CombiPatch was administered for 3 28-day cycles in Continuous Combined or Continuous Sequential treatment regimens versus placebo. In the Continuous Combined regimen, CombiPatch was applied throughout the 3 cycles, replacing the system twice weekly. In the Continuous Sequential regimen, an estradiol-only transdermal system (Vivelle ® 0.05 mg) was applied twice weekly during the first 14 days of a 28-day cycle; CombiPatch was applied for the remaining 14 days of the cycle and replaced twice weekly, as well.
The mean number of hot flushes at baseline were 10 to 11 per day and 11 to 12 per day in the Continuous Combined and Continuous Sequential regimen trials, respectively. The mean number and intensity of daily hot flushes (intent-to-treat population) was significantly reduced from baseline to endpoint with either the Continuous Combined or Continuous Sequential administration of CombiPatch at all doses as compared to placebo (intent-to-treat population). (See Tables 3 and 4 ) Table 3.
Adjusted Mean Change in the Number of Hot Flushes and Daily Intensity of Hot Flushes per Day in CombiPatch Continuous Combined Transdermal Therapy 1 Means were adjusted for imbalance among treatment groups and investigators (least squares mean from ANOVA). 2 Represents the milligrams of estradiol/NETA delivered daily by each system. 3 Population represents those patients who had baseline and endpoint observations.
4 The intensity of hot flushes was evaluated on a scale of 0 to 9 (none=0, mild=1-3, moderate= 4-6, severe=7-9). 5 P-value versus placebo = <0.001. 6 Total number of patients with available data is 56.
7 Total number of patients with available data is 50. CombiPatch Continuous Combined Placebo Adjusted Mean Change from Baseline 1 0.05/0.14 mg per day 2 n=57 0.05/0.25 mg per day 2 n=52 n=51 Number of Hot Flushes 3 -9.3 5 -8.9 5 -6.2 Daily Intensity of Hot Flushes 3,4 -4.6 5,6 -5.0 5 -2.8 7 Table 4. Adjusted Mean Change in the Number of Hot Flushes and Daily Intensity of Hot Flushes per Day in CombiPatch Continuous Sequential Transdermal Therapy 1 Means were adjusted for imbalance among treatment groups and investigators (least squares mean from ANOVA).
2 Represents the milligrams of estradiol/NETA delivered daily by each system. 3 Population represents those patients who had baseline and endpoint observations. 4 The intensity of hot flushes was evaluated on a scale of 0 to 9 (none=0, mild=1-3, moderate= 4-6, severe=7-9).
5 P-value versus placebo = <0.001. CombiPatch ® Continuous Combined Placebo Adjusted Mean Change from Baseline 1 0.05/0.14 mg per day 2 n=54 0.05/0.25 mg per day 2 n=59 n=53 Number of Hot Flushes 3 -9.3 5 -9.5 5 -5.5 Daily Intensity of Hot Flushes 3,4 -4.4 5 -4.5 5 -2.1 Effects on the Endometrium The use of unopposed estrogen therapy has been associated with an increased risk of endometrial hyperplasia, a possible precursor of endometrial adenocarcinoma. Progestins counter the estrogenic effects by decreasing the number of nuclear estradiol receptors and suppressing epithelial DNA synthesis in endometrial tissue.
Clinical studies indicate that the addition of a progestin to an estrogen regimen at least 12 days per cycle reduces the incidence of endometrial hyperplasia and the potential risk of adenocarcinoma in women with intact uteri. The addition of a progestin to an estrogen regimen has not been shown to interfere with the efficacy of estrogen therapy for its approved indications. CombiPatch was effective in reducing the incidence of estrogen-induced endometrial hyperplasia after 1 year of therapy in two clinical trials.
Nine hundred fifty-five (955) postmenopausal women (with intact uteri) were treated with (i) a continuous regimen of CombiPatch alone ( Continuous Combined regimen), (ii) a sequential regimen with an estradiol-only (Vivell… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
E. Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver. NETA was not mutagenic in a battery of in vitro or in vivo genetic toxicity assays.
📚 References ▾
REFERENCES Rossouw JE, et al. Postmenopausal Hormone Therapy and Risk of Cardiovascular Disease by Age and Years Since Menopause. JAMA.
2007;297:1465-1477. Hsia J, et al. Conjugated Equine Estrogens and Coronary Heart Disease.
Arch Int Med. 2006;166:357-365. Cushman M, et al.
Estrogen Plus Progestin and Risk of Venous Thrombosis. JAMA. 2004;292:1573-1580.
Curb JD, et al. Venous Thrombosis and Conjugated Equine Estrogen in Women Without a Uterus. Arch Int Med.
2006;166:772-780. Chlebowski RT, et al. Influence of Estrogen Plus Progestin on Breast Cancer and Mammography in Healthy Postmenopausal Women.
JAMA. 2003;289:3234-3253. Stefanick ML, et al.
Effects of Conjugated Equine Estrogens on Breast Cancer and Mammography Screening in Postmenopausal Women With Hysterectomy. JAMA. 2006;295:1647-1657.
Anderson GL, et al. Effects of Estrogen Plus Progestin on Gynecologic Cancers and Associated Diagnostic Procedures. JAMA.
2003;290:1739-1748. Shumaker SA, et al. Conjugated Equine Estrogens and Incidence of Probable Dementia and Mild Cognitive Impairment in Postmenopausal Women.
JAMA. 2004;291:2947-2958. Jackson RD, et al.
Effects of Conjugated Equine Estrogen on Risk of Fractures and BMD in Postmenopausal Women With Hysterectomy: Results From the Women's Health Initiative Randomized Trial. J Bone Miner Res. 2006;21:817-828.
Hendrix SL, et al. Effects of Conjugated Equine Estrogen on Stroke in the Women's Health Initiative. Circulation.
2006;113:2425-2434. CombiPatch ® is a registered trademark of Noven Pharmaceuticals, Inc. Manufactured by: Noven Pharmaceuticals Inc.
Miami, FL 33186 Distributed by: Noven Therapeutics, LLC Miami, FL 33186 © 2024 Noven Pharmaceuticals, Inc. For more information call 1-800-455-8070 or visit www.combipatch.com. 102538-5
📖 Instructions for Use ▾
Instructions for Use CombiPatch (käm-bē `pach) (estradiol/norethindrone acetate transdermal system) Step 1. Pick the days you will change your CombiPatch. You will need to change your patch every 3 to 4 days (twice weekly).
Step 2. Remove CombiPatch from the pouch. Tear open the protective pouch at the slit (do not use scissors) and remove the patch.
See Figure A. The pouch should not be opened until you are ready to put the patch on. Step 3.
Remove the adhesive liner. Peel off one side of the protective liner. See Figure B.
Do not touch the sticky part of the patch with your fingers. See Figure B. Step 4.
Placing the CombiPatch on your skin. Put the sticky side of the patch on the lower abdomen (below the panty line). See Figure C.
Peel off the second side of the protective liner. See Figure C. Press the patch firmly in place with your hand for about 10 seconds.
See Figure D. Note: Avoid the waistline, since clothing and belts may cause the CombiPatch to be rubbed off. Do not apply the CombiPatch to or near your breasts.
Only apply the CombiPatch to skin that is clean, dry, and free of any powder, oil, or lotion. You should not apply the CombiPatch to injured, burned, or irritated skin, or areas with skin conditions (such as birth marks, tattoos, or that is very hairy). Step 5.
Press the CombiPatch firmly onto your skin. Rub the edges of the CombiPatch with your fingers to make sure that it will stick to your skin. See Figure E.
Note: Bathing, swimming, or showering will not affect the CombiPatch. Once in place, the patch should not be exposed to the sun for prolonged periods of time. If your CombiPatch falls off reapply it.
If you cannot reapply the CombiPatch, apply a new CombiPatch to another area (See Figures C , D and E ) and continue to follow your original placement schedule. If you stop using your CombiPatch or forget to apply a new CombiPatch as scheduled you may have spotting, or bleeding, and your symptoms may come back. Step 6.
Throwing away your used CombiPatch. When it is time to change your CombiPatch, remove the old CombiPatch before you apply a new one. To throw away the patch, fold the sticky side of the patch together, place it in a sturdy child-proof container, and place this container in the trash.
Used patches should not be flushed in the toilet. This Patient Information and Instructions for Use have been approved by the U.S. Food and Drug Administration.
Manufactured by: Noven Pharmaceuticals Inc. Miami, FL 33186 Distributed by: Noven Therapeutics, LLC Miami, FL 33186 For more information call 1-800-455-8070 or visit www.combipatch.com. © 2024 Noven Pharmaceuticals, Inc. 102538-5 02/2024 Figure A Figure B Figure C,D Figure E
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - NDC - 68968-0514-8 CombiPatch Count - 50/140 NDC 68968-0514-8 Includes 8 Systems See New Storage Requirements Combipatch ® 50/140 (estradiol/norethindrone acetate transdermal system) 0.05/0.14 mg per day Noven www.combipatch.com Twice-Weekly Rx Only Combipatch ® 50/140 (estradiol/norethindrone acetate transdermal system) 0.05/0.14 mg per day Twice-Weekly Rx Only Contains 0.62 mg estradiol USP and 2.7 mg norethindrone acetate (NETA) USP to provide 0.05/0.14 mg of estradiol/NETA per day. Inactive components : a silicone and acrylic-based multi-polymeric adhesive, povidone USP, oleic acid NF, polyolefin laminate backing, polyester release liner and dipropylene glycol.
Dosage and Administration: For transdermal use only. See package insert. Allow patch to reach room temperature before application.
DO NOT STORE UNPOUCHED. Keep out of the reach of children. Store Combipatch ® refrigerated at 36°F to 46°F (2°C to 8°C) See side panel for lot number and expiration date. www.combipatch.com N3 68968-0514-8 0 302391-4 Noven PLEASE READ THIS BEFORE APPLYING PATCH.
Allow patch to reach room temperature before application. See reverse side for patient instructions. pull To open here LOT/EXP GTIN 00368968051480 969864 Mfd. By: Noven Pharmaceuticals, Inc.
Miami, Florida 33186 Dist. By Noven Therapeutics, LLC Miami, Florida 33186 Combi patch Count - 50/140
PRINCIPAL DISPLAY PANEL - NDC - 68968-0525-8 CombiPatch Count - 50/250 NDC 68968-0525-8 Includes 8 Systems See New Storage Requirements Combipatch ® 50/250 (estradiol/norethindrone acetate transdermal system) 0.05/0.25 mg per day Noven www.combipatch.com Twice-Weekly Rx Only Combipatch ® 50/250 (estradiol/norethindrone acetate transdermal system) 0.05/0.25 mg per day Twice-Weekly Rx Only Contains 0.51 mg estradiol USP and 4.8 mg norethindrone acetate (NETA) USP to provide 0.05/0.25 mg of estradiol/NETA per day. Inactive components : a silicone and acrylic-based multi-polymeric adhesive, povidone USP, oleic acid NF, polyolefin laminate backing, polyester release liner and dipropylene glycol.
Dosage and Administration: For transdermal use only. See package insert. Allow patch to reach room temperature before application.
DO NOT STORE UNPOUCHED. Keep out of the reach of children. Store Combipatch ® refrigerated at 36°F to 46°F (2°C to 8°C) See side panel for lot number and expiration date. www.combipatch.com N3 68968-0525-8 0 302390-4 Noven PLEASE READ THIS BEFORE APPLYING PATCH.
Allow patch to reach room temperature before application. See reverse side for patient instructions. pull To open here LOT/EXP GTIN 00368968052586 969864 Mfd. By: Noven Pharmaceuticals, Inc.
Miami, Florida 33186 Dist. By Noven Therapeutics, LLC Miami, Florida 33186 Combi patch Count - 50/250