
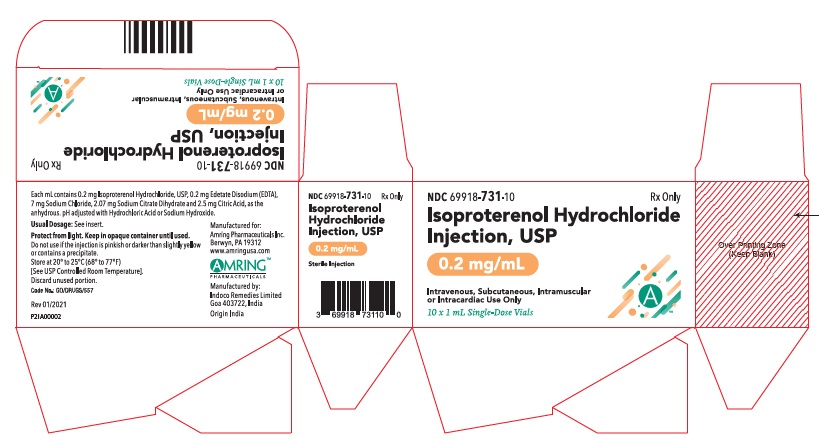
Isoproterenol Hydrochloride .2 mg/mL Injection, Solution, 10 vials
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Isoproterenol may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
2.5 mg / 1 mL
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
0.2 mg / 1 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
7.0 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
2.07 mg / 1 mL
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $43.50 | $434.96 / 10 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Isoproterenol Hydrochloride .2 mg/mL 00548-9501-00 | Amphastar | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 14789-0011-01 | Nexus | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 23155-0660-41 | Heritage | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 25021-0324-01 | Sagent | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 42571-0294-79 | Micro | 5 ampules | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 55150-0316-25 | Eugia | 25 ampules | — | — | FDA listed | — |
| isoproterenol hydrochloride .2 mg/mL 68083-0585-25 | Gland | 25 vials | — | AP | FDA listed | — |
| Isoproterenol .2 mg/mL 69097-0521-31 | Cipla | 25 ampules | — | — | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mLthis 69918-0731-10 | Nordic | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 70121-1604-07 | Amneal | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 83634-0303-01 | Avenacy, | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 00548-9502-00 | Amphastar | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 72485-0113-10 | Armas | 10 ampules | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 69918-0735-10 | Nordic | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69918-0731-10 You're viewing this | 10 VIAL, SINGLE-DOSE in 1 CARTON (69918-731-10) / 1 mL in 1 VIAL, SINGLE-DOSE | 2021-08-01 | Active |
| 69918-0731-11 | 10 VIAL, SINGLE-DOSE in 1 CARTON (69918-731-11) / 1 mL in 1 VIAL, SINGLE-DOSE | 2024-06-01 | Active |
Pack size FAQ
What quantity is in NDC 69918-0731-10?
What is the difference between NDC 69918-0731-10 and NDC 69918-0731-11?
What NDC number is used to bill for this package of Isoproterenol Hydrochloride .2 mg/mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Isoproterenol hydrochloride injection is indicated: To improve hemodynamic status in patients in distributive shock and shock due to reduced cardiac output For bronchospasm occurring during anesthesia Isoproterenol hydrochloride injection is a beta-adrenergic agonist indicated: To improve hemodynamic status in patients in distributive shock and shock due to reduced cardiac output ( 1 ) For treatment of bronchospasm occurring during anesthesia ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initiate isoproterenol hydrochloride injection at the lowest recommended dose and increase gradually based on patient response ( 2.2 ) Recommended initial dosage: Shock: 0.5 mcg to 5 mcg per minute as an intravenous infusion ( 2.2 ) Bronchospasm: 10 mcg to 20 mcg intravenous injection ( 2.2 )
2.1General Considerations Inspect visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not use if the injection is pinkish or darker than slightly yellow or contains a precipitate. Discard any unused portion. Diluted solution should be used immediately. Unused material should be discarded.
2.2Recommended Dosage Dosage should generally be started at the lowest recommended dose and increased gradually based on patient response. Recommended dosage for adults with shock and hypoperfusion states: Route of Administration Preparation of Dilution Concentrations up to 10 times greater have been used when limitation of volume is essential. Infusion Rate Rates over 30 mcg per minute have been used in advanced stages of shock.
Intravenous infusion Dilute 5 mL (1 mg) in 500 mL of 5% Dextrose Injection, USP 0.5 mcg to 5 mcg per minute (0.25 mL to 2.5 mL of diluted solution) Adjust the rate of infusion based on heart rate, central venous pressure, systemic blood pressure, and urine flow. If the heart rate exceeds 110 beats per minute, consider decreasing or temporarily discontinuing the infusion. Recommended dosage for adults with bronchospasm occurring during anesthesia: Route of Administration Preparation of Dilution Initial Dose Subsequent Dose Bolus intravenous injection Dilute 1 mL (0.2 mg) to 10 mL with Sodium Chloride Injection, USP, or 5% Dextrose Injection, USP 10 mcg to 20 mcg (0.5 mL to 1 mL of diluted solution) The initial dose may be repeated when necessary There are no well-controlled studies in children to establish appropriate dosing; however, the American Heart Association recommends an initial infusion rate of 0.1 mcg/kg/min, with the usual range being 0.1 mcg/kg/min to 1 mcg/kg/min.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection solution: single dose, clear glass vials containing isoproterenol in a clear, colorless solution; 1 mL containing 0.2 mg/1 mL (0.2 mg/mL) 5 mL containing 1 mg/5 mL (0.2 mg/mL) Injection: 0.2 mg/mL and 1 mg/5 mL (0.2 mg/mL) single dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Isoproterenol hydrochloride injection is contraindicated in patients with: tachycardia ventricular arrhythmias angina pectoris Isoproterenol hydrochloride injection is contraindicated in patients with: Tachycardia ( 4 ) Ventricular arrhythmias ( 4 ) Angina pectoris ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiac arrhythmias and ischemia may be induced by isoproterenol hydrochloride injection ( 5.1 ) Sulfite: Isoproterenol hydrochloride injection contains metabisulfite, which may cause allergic reaction ( 5.2 )
5.1Cardiac Arrhythmias and Ischemia Isoproterenol may induce cardiac arrhythmias and myocardial ischemia in patients, especially patients with coronary artery disease, or cardiomyopathy.
5.2Allergic Reactions associated with Sulfite Isoproterenol hydrochloride injection contains sodium metabisulfite, which may cause mild to severe allergic reactions including anaphylaxis or asthmatic episodes, particularly in patients with a history of allergies. However, the presence of metabisulfite in this product should not preclude its use for treatment in emergency situations, even if the patient is sulfite-sensitive, as the alternatives to using isoproterenol in a life-threatening situation may not be satisfactory.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions have been associated with use of isoproterenol. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency reliably or to establish a causal relationship to drug exposure. Nervous system disorders: Nervousness, headache, dizziness, visual blurring Cardiovascular: Tachycardia, tachyarrhythmias, palpitations, angina, ventricular arrhythmias, Adams-Stokes attacks, pulmonary edema Respiratory: Dyspnea Other: Flushing of the skin, sweating, mild tremors, pallor, nausea Common adverse reactions with isoproterenol include tachycardia and palpitations ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Nordic Pharma, Inc. at 1-844-267-4641 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 1. Clinically Relevant Interactions with Isoproterenol Epinephrine Clinical Impact Both drugs are direct cardiac stimulants, and their combined effects may induce serious arrhythmias upon simultaneous administration. Intervention Isoproterenol hydrochloride injection and epinephrine should not be administered simultaneously.
Drugs that may potentiate clinical response of Isoproterenol Clinical Impact The effects of isoproterenol may be potentiated by tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxinesodium, and certain antihistamines, notably chlorpheniramine, tripelennamine, and diphenhydramine. Intervention Monitor hemodynamic parameters in patients who concurrently are taking tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium and certain antihistamines. Adjust doses appropriately.
Drugs that may reduce clinical response of Isoproterenol Clinical Impact The cardiostimulating and bronchodilating effects of isoproterenol are antagonized by beta-adrenergic blocking drugs, such as propranolol. Intervention Monitor for hemodynamic response and relief of bronchospasm and adjust dose appropriately. Do not administer isoproterenol hydrochloride injection and epinephrine simultaneously due to combined effects may induce serious arrhythmias ( 7 ) Concomitant use of tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium and certain antihistamines; hemodynamic parameters may potentiate a clinical response of isoproterenol ( 7 ) Beta-adrenergic blocking drugs may reduce cardiostimulating and bronchodilating effects of isoproterenol ( 7 ) See 17 for PATIENT COUNSELING INFORMATION.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Prolonged experience with isoproterenol use in pregnant women over several decades, based on published literature, do not identify a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. However, there are risks to the mother and fetus associated with isoproterenol use during labor or delivery (see Clinical Considerations ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the United States general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Hypotension associated with shock is a medical emergency in pregnancy which can be fatal if left untreated.
Delaying treatment in pregnant women with hypotension associated with shock may increase the risk of maternal and fetal morbidity and mortality. Life-sustaining therapy for the pregnant woman should not be withheld due to potential concerns regarding the effects of isoproterenol on the fetus. Labor and Delivery Isoproterenol usually inhibits spontaneous or oxytocin induced contractions of the pregnant human uterus and may delay the second stage of labor.
Avoid isoproterenol during the second stage of labor. Avoid isoproterenol in obstetrics when maternal blood pressure exceeds 130/80 mmHg. Although isoproterenol may improve maternal hypotension associated with shock, it may result in uterine vasoconstriction, decreased uterine blood flow, uterine atony with hemorrhage, and fetal anoxia.
8.2Lactation Risk Summary There is no information regarding the presence of isoproterenol in milk or the effects of isoproterenol on the breastfed infant or on milk production. However, due to its short half-life, isoproterenol exposure is expected to be very low in the breastfed infant.
8.4Pediatric Use Safety and efficacy of isoproterenol in pediatric patients have not been established. Intravenous infusions of isoproterenol in refractory asthmatic children at rates of 0.05-2.7 μg/kg/min have caused clinical deterioration, myocardial necrosis, congestive heart failure and death. The risks of cardiac toxicity appear to be increased by some factors [acidosis, hypoxemia, coadministration of corticosteroids, coadministration of methylxanthines (theophylline, theobromine) or aminophylline] that are especially likely to be present in these patients.
If I.V. isoproterenol is used in children with refractory asthma, patient monitoring must include continuous assessment of vital signs, frequent electrocardiography, and daily measurements of cardiac enzymes, including CPK-MB.
8.5Geriatric Use Clinical studies of isoproterenol hydrochloride injection did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects in clinical circumstances. There are, however, some data that suggest that elderly healthy or hypertensive patients are less responsive to beta-adrenergic stimulation than are younger subjects. In general, dose selection for elderly patients should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function and of concomitant diseases or other drug therapy.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Prolonged experience with isoproterenol use in pregnant women over several decades, based on published literature, do not identify a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. However, there are risks to the mother and fetus associated with isoproterenol use during labor or delivery (see Clinical Considerations ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the United States general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Hypotension associated with shock is a medical emergency in pregnancy which can be fatal if left untreated.
Delaying treatment in pregnant women with hypotension associated with shock may increase the risk of maternal and fetal morbidity and mortality. Life-sustaining therapy for the pregnant woman should not be withheld due to potential concerns regarding the effects of isoproterenol on the fetus. Labor and Delivery Isoproterenol usually inhibits spontaneous or oxytocin induced contractions of the pregnant human uterus and may delay the second stage of labor.
Avoid isoproterenol during the second stage of labor. Avoid isoproterenol in obstetrics when maternal blood pressure exceeds 130/80 mmHg. Although isoproterenol may improve maternal hypotension associated with shock, it may result in uterine vasoconstriction, decreased uterine blood flow, uterine atony with hemorrhage, and fetal anoxia.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of isoproterenol in pediatric patients have not been established. Intravenous infusions of isoproterenol in refractory asthmatic children at rates of 0.05-2.7 μg/kg/min have caused clinical deterioration, myocardial necrosis, congestive heart failure and death. The risks of cardiac toxicity appear to be increased by some factors [acidosis, hypoxemia, coadministration of corticosteroids, coadministration of methylxanthines (theophylline, theobromine) or aminophylline] that are especially likely to be present in these patients.
If I.V. isoproterenol is used in children with refractory asthma, patient monitoring must include continuous assessment of vital signs, frequent electrocardiography, and daily measurements of cardiac enzymes, including CPK-MB.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of isoproterenol hydrochloride injection did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects in clinical circumstances. There are, however, some data that suggest that elderly healthy or hypertensive patients are less responsive to beta-adrenergic stimulation than are younger subjects. In general, dose selection for elderly patients should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function and of concomitant diseases or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of isoproterenol can cause tachycardia or other arrhythmias, palpitations, angina, hypotension, or hypertension. In case of overdosage, reduce the rate of administration or discontinue isoproterenol hydrochloride injection until patient’s condition stabilizes. Monitor blood pressure, pulse, respiration, and EKG. It is not known whether isoproterenol hydrochloride is dialyzable.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Isoproterenol is a potent nonselective beta-adrenergic agonist with very low affinity for alpha-adrenergic receptors.
12.2Pharmacodynamics Intravenous infusion of isoproterenol in man lowers peripheral vascular resistance, primarily in skeletal muscle but also in renal and mesenteric vascular beds. Diastolic pressure falls. Renal blood flow is decreased in normotensive subjects but is increased markedly in shock.
Systolic blood pressure may remain unchanged or rise, although mean arterial pressure typically falls. Cardiac output is increased because of the positive inotropic and chronotropic effects of the drug in the face of diminished peripheral vascular resistance. Isoproterenol relaxes almost all varieties of smooth muscle when the tone is high, but this action is most pronounced on bronchial and gastrointestinal smooth muscle.
It prevents or relieves bronchoconstriction, but tolerance to this effect develops with overuse of the drug. In man, isoproterenol causes less hyperglycemia than does epinephrine. Isoproterenol and epinephrine are equally effective in stimulating the release of free fatty acids and energy production.
12.3Pharmacokinetics Absorption Isoproterenol is readily absorbed when given parenterally or as an aerosol. Elimination Isoproterenol is metabolized primarily in the liver and other tissues by COMT. Isoproterenol is a relatively poor substrate for MAO and is not taken up by sympathetic neurons to the same extent as are epinephrine and norepinephrine.
The duration of action of isoproterenol may therefore be longer than that of epinephrine but is still brief.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Isoproterenol is a potent nonselective beta-adrenergic agonist with very low affinity for alpha-adrenergic receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Isoproterenol hydrochloride injection, USP 0.2 mg/mL and 1 mg/5 mL is supplied as a sterile, clear, colorless solution free from visible particulate matter in 3 mL and 5 mL single-dose glass vials respectively. NDC Container Concentration Fill Quantity 69918-731-10 Single-Dose Vial 0.2 mg/mL 1 mL Carton of 10 Single-Dose Vials 69918-735-10 Single-Dose Vial 1 mg/5 mL (0.2 mg/mL) 5 mL Carton of 10 Single-Dose Vials Protect from light. Keep in opaque container until used.
Store at 20º to 25ºC (68º to 77ºF) [See USP Controlled Room Temperature]. Do not use if the injection is pinkish or darker than slightly yellow or contains a precipitate. Discard unused portion.
Manufactured for: Nordic Pharma, Inc. Berwyn, PA 19312 USA www.nordicpharmausa.com The Nordic Pharma Logo is a trademark of Nordic Group B.V. Manufactured by: Indoco Remedies Limited Verna, Goa, 403722, India Origin India Revised: 04/2024 2011016 Structural Formula
📋 Description ▾
11 DESCRIPTION Isoproterenol hydrochloride, USP is 3,4-Dihydroxy-α-[(isopropylamino)methyl] benzyl alcohol hydrochloride, a synthetic sympathomimetic amine that is structurally related to epinephrine but acts almost exclusively on beta receptors. The molecular formula is C 11 H 17 NO 3 • HCl. It has a molecular weight of 247.72 and the following structural formula: Isoproterenol hydrochloride, USP is a racemic compound.
Each milliliter of the sterile solution contains: Isoproterenol Hydrochloride, USP 0.2 mg Edetate Disodium (EDTA) 0.2 mg Sodium Chloride 7.0 mg Sodium Citrate, Dihydrate 2.07 mg Citric Acid, Anhydrous 2.5 mg Water for Injection 1.0 mL The pH is adjusted between 2.5 and 4.5 with hydrochloric acid or sodium hydroxide. The sterile solution is nonpyrogenic and can be administered by the intravenous, intramuscular, subcutaneous, or intracardiac routes. Structural Formula