
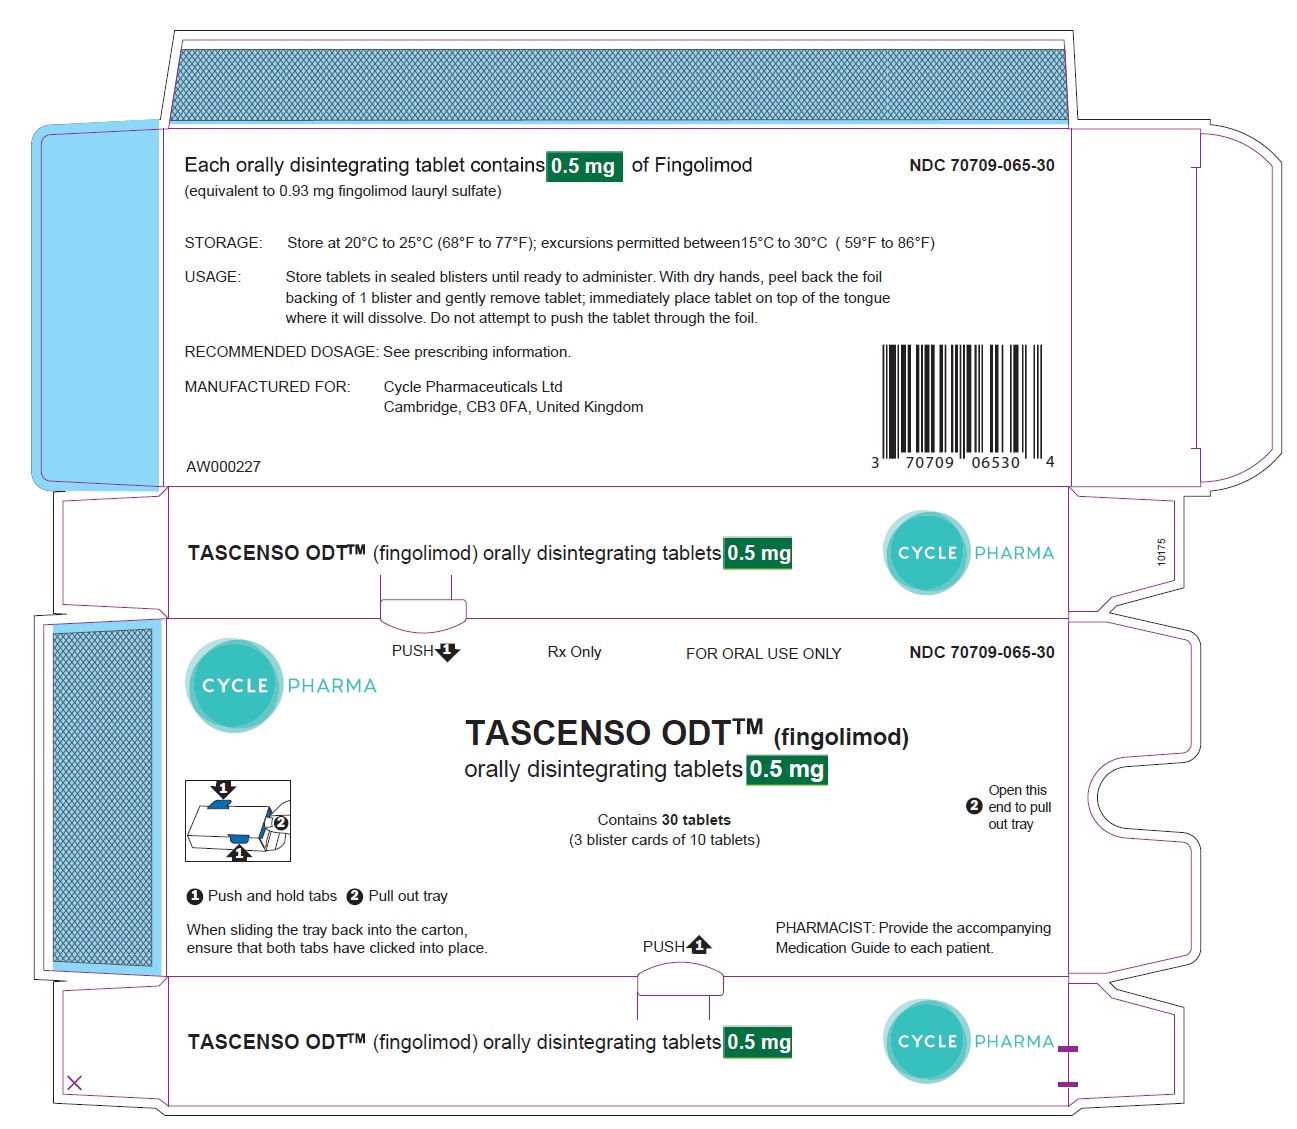
TASCENSO ODT Fingolimod Lauryl Sulfate .5 mg Tablet, Orally Disintegrating — NDC 70709-065-30 (Billing 70709-0065-30)
This is a package of TASCENSO ODT Fingolimod Lauryl Sulfate .5 mg Tablet, Orally Disintegrating from Cycle Pharmaceuticals Ltd, marketed since Feb 2023 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 70709-065-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70709 labeler · 065 product · 30 package
- Package marketed since
- Feb 1, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC)
- 0370709062303
- Medicaid fills, this package
- 41 prescriptions in the last four reported quarters
- FDA record last changed
- Sep 3, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 084181
- GCN: 53376
- HICL (First Databank): 048165
- AHFS class code: 90:04.16.00
- RxCUI (RxNorm): 2610295
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Sphingosine 1-phosphate Receptor Modulator class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats relapsing forms of multiple sclerosis, including clinically isolated syndrome, relapsing-remitting disease and active secondary progressive disease. It is approved for pe...
- Take it by mouth once a day, with or without food. If you have Tascenso ODT, place it on your tongue and let it dissolve. Follow your prescriber's directions exactly.
- Fingolimod can slow your heart rate and cause heart block, mostly in the first 6 hours. We check your pulse, blood pressure and ECG. Some people need overnight monitoring. This may...
- Why do I have to be watched after the first dose?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $355.75 | $10,672.42 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $363.44 | $10,903.18 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70709-0065-30 You're viewing this Main listing | 3 BLISTER PACK in 1 CARTON / 10 TABLET, ORALLY DISINTEGRATING in 1 BLISTER PACK | 2023-02-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tascenso Odt .5 mgthis 70709-0065-30 | Cycle | 10 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10555902 ↗ | Method of use | U-3268 | Jan 19, 2036 |
| US 10555902 ↗ | Method of use | U-3493 | Jan 19, 2036 |
| US 9925138 ↗ | Drug product | — | Jan 19, 2036 |
| US 10925829 ↗ | Drug product | — | Jan 19, 2036 |
| US 10925829 ↗ | Drug product | — | Jan 19, 2036 |
| US 9925138 ↗ | Drug product | — | Jan 19, 2036 |
Is there a generic version of TASCENSO ODT 0.5 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Cycle Pharmaceuticals Ltd labeler code 70709
- NITYR Nitisinone 10 mg Tablet NDC 70709-000-60
- NITYR Nitisinone 2 mg Tablet NDC 70709-002-60
- NITYR Nitisinone 5 mg Tablet NDC 70709-005-60
- SAJAZIR ICATIBANT 30 mg/3mL Injection NDC 70709-013-01
- TASCENSO ODT Fingolimod Lauryl Sulfate .25 mg Tablet, Orally Disintegrating NDC 70709-062-30
- ORMALVI Dichlorphenamide 50 mg Tablet NDC 70709-085-10
- AAGYLUR Penicillamine 250 mg Capsule NDC 70709-102-10
- Harliku nitisinone 2 mg Tablet NDC 70709-112-60
- Venxxiva tiopronin 100 mg Tablet, Delayed Release NDC 70709-121-30
- Venxxiva tiopronin 300 mg Tablet, Delayed Release NDC 70709-123-90
- Phyrago dasatinib 20 mg Tablet NDC 70709-151-20
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TASCENSO ODT is indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in patients 10 years of age and older. TASCENSO ODT is a sphingosine 1-phosphate receptor modulator indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in patients 10 years of age and older.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Assessments are required prior to initiating TASCENSO ODT ( 2.1 ) Recommended dosage for adults and pediatric patients (10 years of age and older) weighing more than 40 kg: 0.5 mg orally once daily, with or without food. ( 2.2 , 2.3 ) Recommended dosage for pediatric patients (10 years of age and older) weighing less than or equal to 40 kg: 0.25 mg orally once daily, with or without food ( 2.2 , 2.3 ). Administer TASCENSO ODT with or without water.
Place tablet directly on the tongue and allow it to dissolve before swallowing. ( 2.2 ) First-Dose Monitoring (including reinitiation after discontinuation greater than 14 days and dose increases): Observe all patients for bradycardia for at least 6 hours; monitor pulse and blood pressure hourly. Electrocardiograms (ECGs) prior to dosing and at end of observation period required.
( 2.4 ) Monitor until resolution if heart rate < 45 beats per minute (bpm) in adults, < 55 bpm in patients aged 12 years and above, or < 60 bpm in pediatric patients aged 10 to below 12 years, atrioventricular (AV) block, or if lowest postdose heart rate is at the end of the observation period. ( 2.4 ) Monitor symptomatic bradycardia with ECG until resolved. Continue overnight if intervention is required; repeat first-dose monitoring for second dose.
( 2.4 ) Observe patients overnight if at higher risk of symptomatic bradycardia, heart block, prolonged QTc interval, or if taking drugs with known risk of torsades de pointes. ( 2.4 , 7.1 )
2.1Assessment Prior to Initiating TASCENSO ODT Cardiac Evaluation Obtain a cardiac evaluation in patients with certain preexisting conditions [see Dosage and Administration (2.4) and Warnings and Precautions (5.1) ]. Prior to starting treatment, determine whether patients are taking drugs that could slow heart rate or atrioventricular (AV) conduction [see Dosage and Administration (2.4) , Drug Interactions (7.5) ] . Complete Blood Count (CBC) Review results of a recent CBC [see Warnings and Precautions (5.2) , Drug Interactions (7.6) ].
Serum Transaminases (ALT and AST) and Total Bilirubin Levels Prior to starting treatment with TASCENSO ODT (i.e., within 6 months), review serum transaminases [alanine transaminase (ALT) and aspartate transferase (AST)] and total bilirubin levels [see Warnings and Precautions (5.5) ] . Ophthalmic Assessment Obtain a baseline evaluation of the fundus, including the macula, near the start of treatment with TASCENSO ODT [see Warnings and Precautions ( 5.4 )]. Skin Examination Obtain a baseline skin examination prior to or shortly after initiation of TASCENSO ODT.
If a suspicious skin lesion is observed, it should be promptly evaluated [see Warnings and Precautions ( 5.12 )]. Prior Medications If patients are taking antineoplastic, immunosuppressive, or immune-modulating therapies, or if there is a history of prior use of these drugs, consider possible unintended additive immunosuppressive effects prior to initiating treatment with TASCENSO ODT [see Warnings and Precautions (5.2) , Drug Interactions (7.4) ]. Vaccinations Prior to initiating TASCENSO ODT, test patients for antibodies to varicella zoster virus (VZV).
VZV vaccination of antibody- negative patients is recommended prior to commencing treatment with TASCENSO ODT [see Warnings and Precautions (5.2) ] . It is recommended that pediatric patients if possible, complete all other immunizations in accordance with current immunization guidelines prior to initiating TASCENSO ODT.
2.2Important Administration Instructions Patients who initiate TASCENSO ODT, and those who reinitiate treatment after discontinuation for longer than 14 days, require first- dose monitoring. This monitoring is also recommended when the dose is increased in pediatric patients. Patients who are currently treated with another fingolimod product and underwent first-dose monitoring at initiation may be switched to TASCENSO ODT at the same daily dose without a need to repeat first-dose monitori… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS TASCENSO ODT is available as: 0.25 mg orally disintegrating tablets are white to off white, round tablets debossed with . 0.5 mg orally disintegrating tablets are white to off white, round tablets debossed with . Orally disintegrating tablets: 0.25 mg and 0.5 mg ( 3 ) image image description
⛔ Contraindications ▾
4 CONTRAINDICATIONS TASCENSO ODT is contraindicated in patients who have: In the last 6 months experienced myocardial infarction, unstable angina, stroke, transient ischemic attack (TIA), decompensated heart failure requiring hospitalization or Class III/IV heart failure. A history or presence of Mobitz Type II second-degree or third-degree AV block or sick sinus syndrome, unless patient has a functioning pacemaker [see Warnings and Precautions (5.1) ] A baseline QTc interval ≥ 500 msec Cardiac arrhythmias requiring anti-arrhythmic treatment with Class Ia or Class III anti-arrhythmic drugs Had a hypersensitivity reaction to fingolimod or any of the excipients in TASCENSO ODT.
Observed reactions include rash, urticaria, and angioedema [see Warnings and Precautions (5.14) ]. Recent myocardial infarction, unstable angina, stroke, transient ischemic attack, decompensated heart failure with hospitalization, or Class III/IV heart failure. ( 4 ) History of Mobitz Type II 2 nd degree or 3 rd degree AV block or sick sinus syndrome, unless patient has a pacemaker.
( 4 ) Baseline QTc interval ≥ 500 msec. ( 4 ) Cardiac arrhythmias requiring anti-arrhythmic treatment with Class Ia or Class III anti-arrhythmic drugs. ( 4 ) Hypersensitivity to fingolimod or its excipients.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Bradyarrhythmia and Atrioventricular Blocks : Because of a risk for bradyarrhythmia and AV blocks, monitor during initiation of treatment ( 2.4 , 5.1 ) Infections : TASCENSO ODT may increase the risk. Obtain a complete blood count (CBC) before initiating TASCENSO ODT (i.e., within 6 months). Monitor for infection during treatment and for 2 months after discontinuation.
Do not start in patients with active infections. ( 5.2 ) Progressive Multifocal Leukoencephalopathy (PML) : Withhold TASCENSO ODT at the first sign or symptom suggestive of PML. ( 5.3 ) Macular Edema : Increases the risk of macular edema.
Obtain a baseline evaluation of the fundus, including the macula, near the start of treatment with TASCENSO ODT. Conduct an evaluation of the fundus, including the macula, 3 to 4 months after treatment start, periodically while on therapy, and any time there is a change in vision. Consider discontinuing TASCENSO ODT if macular edema develops.
Diabetes mellitus and uveitis increase the risk. ( 5.4 ) Liver Injury : Obtain liver enzyme results before initiation and periodically during treatment. Closely monitor patients with severe hepatic impairment.
Discontinue if evidence of liver injury without other cause. ( 5.5 , 8.6 , 12.3 ) Posterior Reversible Encephalopathy Syndrome (PRES) : If suspected, discontinue TASCENSO ODT. ( 5.6 ) Respiratory Effects : Evaluate when clinically indicated.
( 5.7 ) Fetal Risk : May cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use an effective method of contraception during treatment and for 2 months after stopping TASCENSO ODT. ( 5.8 , 8.1 , 8.3 ) Severe Increase in Disability After Stopping TASCENSO ODT: Monitor for development of severe increase in disability following discontinuation and begin appropriate treatment as needed.
( 5.9 ) Tumefactive MS : Consider when severe MS relapse occurs during treatment or after discontinuation. Obtain imaging and begin treatment as needed. ( 5.10 ) Increased Blood Pressure (BP) : Monitor BP in adult and pediatric patients during treatment.
( 5.11 ) Malignancies : Skin examination prior to or shortly after the start of treatment and periodically thereafter is recommended. Suspicious skin lesions should be evaluated. ( 5.12 )
5.1Bradyarrhythmia and Atrioventricular Blocks Because of a risk for bradyarrhythmia and AV blocks, patients should be monitored during TASCENSO ODT treatment initiation [see Dosage and Administration (2.4) ] . Reduction in Heart Rate After the first dose of TASCENSO ODT, the heart rate decrease starts within an hour. On Day 1, the maximum decline in heart rate generally occurs within 6 hours and recovers, although not to baseline levels, by 8 to 10 hours postdose.
Because of physiological diurnal variation, there is a second period of heart rate decrease within 24 hours after the first dose. In some patients, heart rate decrease during the second period is more pronounced than the decrease observed in the first 6 hours. Heart rates below 40 beats per minute (bpm) in adults, and below 50 bpm in pediatric patients occurred rarely.
In controlled clinical trials in adult patients, adverse reactions of symptomatic bradycardia following the first dose were reported in 0.6% of patients receiving fingolimod 0.5 mg and in 0.1% of patients on placebo. Patients who experienced bradycardia were generally asymptomatic, but some patients experienced hypotension, dizziness, fatigue, palpitations, and/or chest pain that usually resolved within the first 24 hours on treatment. Patients with some preexisting conditions (e.g., ischemic heart disease, history of myocardial infarction, congestive heart failure, history of cardiac arrest, cerebrovascular disease, uncontrolled hypertension, history of symptomatic bradycardia, history of recurrent syncope, severe untreated sleep apnea, AV block, sinoatrial heart block) may poorly tolerate the TASCENSO ODT-induced bradycardia, or exp… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in labeling: Bradyarrhythmia and Atrioventricular Blocks [see Warnings and Precautions (5.1) ] Infections [see Warnings and Precautions (5.2) ] Progressive Multifocal Leukoencephalopathy [see Warnings and Precautions (5.3) ] Macular Edema [see Warnings and Precautions (5.4) ] Liver Injury [see Warnings and Precautions (5.5) ] Posterior Reversible Encephalopathy Syndrome [see Warnings and Precautions (5.6) ] Respiratory Effects [see Warnings and Precautions (5.7) ] Fetal Risk [see Warnings and Precautions (5.8) ] Severe Increase in Disability After Stopping TASCENSO ODT [see Warnings and Precautions (5.9) ] Tumefactive Multiple Sclerosis [see Warnings and Precautions (5.10) ] Increased Blood Pressure [see Warnings and Precautions (5.11) ] Malignancies [see Warnings and Precautions (5.12) ] Immune System Effects Following TASCENSO ODT Discontinuation [see Warnings and Precautions (5.13) ] Hypersensitivity Reactions [see Warnings and Precautions (5.14) ] Most common adverse reactions (incidence ≥ 10% and greater than placebo): Headache, liver transaminase elevation, diarrhea, cough, influenza, sinusitis, back pain, abdominal pain, and pain in extremity.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Cycle Pharmaceuticals Ltd at 1-888-533-1625 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults In clinical trials (Studies 1, 2, and 3), a total of 1212 patients with relapsing forms of multiple sclerosis received fingolimod 0.5 mg capsules. This included 783 patients who received fingolimod 0.5 mg in the 2-year placebo-controlled trials (Studies 1 and 3) and 429 patients who received fingolimod 0.5 mg in the 1-year active-controlled trial (Study 2).
The overall exposure in the controlled trials was equivalent to 1716 person-years. Approximately 1000 patients received at least 2 years of treatment with fingolimod 0.5 mg capsules. In all clinical studies, including uncontrolled extension studies, the exposure to fingolimod 0.5 mg capsules was approximately 4119 person-years.
In placebo-controlled trials, the most frequent adverse reactions (incidence ≥ 10% and greater than placebo) for fingolimod 0.5 mg capsules were headache, liver transaminase elevation, diarrhea, cough, influenza, sinusitis, back pain, abdominal pain, and pain in extremity. Adverse events that led to treatment discontinuation and occurred in more than 1% of patients taking fingolimod 0.5 mg capsules, were serum transaminase elevations (4.7% compared to 1% on placebo) and basal cell carcinoma (1% compared to 0.5% on placebo).
Table 1 lists adverse reactions in clinical studies in adults that occurred in ≥ 1% of fingolimod-treated patients and ≥ 1% higher rate than for placebo. Table 1: Adverse Reactions Reported in Adult Studies 1 and 3 (Occurring in ≥ 1% of Patients and Reported for Fingolimod 0.5 mg Capsules at ≥ 1% Higher Rate than for Placebo) Fingolimod 0.5 mg Capsules N = 783 Placebo N = 773 Adverse Drug Reactions % % Infections Influenza 11 8 Sinusitis 11 8 Bronchitis 8 5 Herpes zoster 2 1 Tinea versicolor 2 < 1 Cardiac disorders Bradycardia 3 1 Nervous system disorders Headache 25 24 Migraine 6 4 Gastrointestinal disorders Nausea 13 12 Diarrhea 13 10 Abdominal pain 11 10 General disorders and administration-site conditions Asthenia 2 1 Musculoskeletal and connective tissue disorders Back pain 10 9 Pain in extremity 10 7 Skin and subcutaneous tissue disorders Alopecia 3 2 Actinic keratosis 2 1 Investigations Liver transaminase elevations (ALT/GGT/AST) 15 4 Blood triglycerides increased 3 1 Respiratory, thoracic, and mediastinal disorders Cough 12 11 Dyspnea 9 7 Eye disorders… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Systemic Ketoconazole : Monitor during concomitant use. ( 7.2 , 12.3 ) Vaccines : Avoid live attenuated vaccines during, and for 2 months after stopping TASCENSO ODT treatment. ( 5.3 , 7.3 )
7.1QT Prolonging Drugs TASCENSO ODT has not been studied in patients treated with drugs that prolong the QT interval. Drugs that prolong the QT interval have been associated with cases of torsades de pointes in patients with bradycardia. Since initiation of TASCENSO ODT treatment results in decreased heart rate and may prolong the QT interval, patients on QT prolonging drugs with a known risk of torsades de pointes (e.g., citalopram, chlorpromazine, haloperidol, methadone, erythromycin) should be monitored overnight with continuous ECG in a medical facility [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ].
7.2Ketoconazole The blood levels of fingolimod and fingolimod-phosphate are increased by 1.7-fold when used concomitantly with ketoconazole. Patients who use TASCENSO ODT and systemic ketoconazole concomitantly should be closely monitored, as the risk of adverse reactions is greater.
7.3Vaccines TASCENSO ODT reduces the immune response to vaccination. Vaccination may be less effective during and for up to 2 months after discontinuation of treatment with TASCENSO ODT [see Clinical Pharmacology (12.2) ] . Avoid the use of live attenuated vaccines during and for 2 months after treatment with TASCENSO ODT because of the risk of infection.
It is recommended that pediatric patients, if possible, be brought up to date with all immunizations in agreement with current immunization guidelines prior to initiating TASCENSO ODT therapy.
7.4Antineoplastic, Immunosuppressive, or Immune-Modulating Therapies Antineoplastic, immune-modulating, or immunosuppressive therapies, (including corticosteroids) are expected to increase the risk of immunosuppression, and the risk of additive immune system effects must be considered if these therapies are coadministered with TASCENSO ODT. When switching from drugs with prolonged immune effects, such as natalizumab, teriflunomide or mitoxantrone, the duration and mode of action of these drugs must be considered to avoid unintended additive immunosuppressive effects when initiating TASCENSO ODT [see Warnings and Precautions (5.2) ].
7.5Drugs That Slow Heart Rate or Atrioventricular Conduction (e.g., beta blockers or diltiazem) Experience with fingolimod in patients receiving concurrent therapy with drugs that slow the heart rate or AV conduction (e.g., beta blockers, digoxin, or heart rate-slowing calcium channel blockers such as diltiazem or verapamil) is limited. Because initiation of TASCENSO ODT treatment may result in an additional decrease in heart rate, concomitant use of these drugs during TASCENSO ODT initiation may be associated with severe bradycardia or heart block.
Seek advice from the physician prescribing these drugs regarding the possibility to switch to drugs that do not slow the heart rate or atrioventricular conduction before initiating TASCENSO ODT. Patients who cannot switch should have overnight continuous ECG monitoring after the first dose [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ].
7.6Laboratory Test Interaction Because fingolimod reduces blood lymphocyte counts via redistribution in secondary lymphoid organs, peripheral blood lymphocyte counts cannot be utilized to evaluate the lymphocyte subset status of a patient treated with fingolimod. A recent CBC should be available before initiating treatment with TASCENSO ODT.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available observational pregnancy registry data suggest that use of TASCENSO ODT is associated with an increased prevalence of major birth defects in comparison to the general population. However, limitations in the number of exposed pregnant women and in the study design preclude definitive conclusions (see Data ) . Data from prospective reports to the fingolimod pregnancy registry are currently not sufficient to allow for an adequate assessment of the drug-associated risk for miscarriage.
Based on findings from animal studies, TASCENSO ODT may cause fetal harm when administered to a pregnant woman. In oral studies conducted in rats and rabbits, fingolimod demonstrated developmental toxicity, including an increase in malformations (rats) and embryolethality, when given to pregnant animals. In rats, the highest no-effect dose was less than the recommended human dose of 0.5 mg/day on a body surface area (mg/m 2 ) basis.
The most common fetal visceral malformations in rats were persistent truncus arteriosus and ventricular septal defect. The receptor affected by fingolimod (sphingosine 1-phosphate receptor) is known to be involved in vascular formation during embryogenesis (see Data ). Advise pregnant women of the potential risk to a fetus.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Clinical Considerations In females planning to become pregnant, TASCENSO ODT should be stopped 2 months before planned conception.
The possibility of severe increase in disability should be considered in women who discontinue or are considering discontinuation of TASCENSO ODT because of pregnancy or planned pregnancy. In many of the cases in which increase in disability was reported after stopping fingolimod, the active moiety in TASCENSO ODT, patients had stopped fingolimod because of pregnancy or planned pregnancy [see Warnings and Precautions (5.9 ] . Data Human Data In a prospective observational fingolimod pregnancy registry (2011 - 2024), the rate of major birth defects among 147 live births, stillbirths, or terminations of pregnancy due to fetal anomalies from women who were administered fingolimod during the first trimester was 8.2% (95% CI: 4.3-13.8) using the European Registration of Congenital Anomalies and Twin classification and 10.9% (95% CI: 6.4-17.1) using the Metropolitan Atlanta Congenital Defects Program classification.
The most frequent major birth defects were congenital heart defects, renal/urinary malformations, and limb/musculoskeletal malformations. Study limitations include no adjustment for confounders, no re-adjudication in case of spontaneous resolution, lack of an internal comparator cohort, and small sample size. In fingolimod prospective pharmacovigilance data, the most frequent major birth defect types were similar to those reported in the fingolimod pregnancy registry.
The pattern of malformations reported for fingolimod is similar to that observed in the general population. There is no evidence of clustering of specific birth defects with fingolimod. Animal Data When fingolimod was orally administered to pregnant rats during the period of organogenesis (0, 0.03, 0.1, and 0.3 mg/kg/day or 0, 1, 3, and 10 mg/kg/day), increased incidences of fetal malformations and embryofetal deaths were observed at all but the lowest dose tested (0.03 mg/kg/day), which is less than the recommended human dose (RHD) on a mg/m 2 basis.
Oral administration to pregnant rabbits during organogenesis (0, 0.5, 1.5, and 5 mg/kg/day) resulted in increased incidences of embryofetal mortality and fetal growth retardation at the mid and high doses. The no-effect dose for these effects in rabbits (0.5 mg/kg/day) is approximately 20 times the RHD on a mg/m 2 basis. Whe… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available observational pregnancy registry data suggest that use of TASCENSO ODT is associated with an increased prevalence of major birth defects in comparison to the general population. However, limitations in the number of exposed pregnant women and in the study design preclude definitive conclusions (see Data ) . Data from prospective reports to the fingolimod pregnancy registry are currently not sufficient to allow for an adequate assessment of the drug-associated risk for miscarriage.
Based on findings from animal studies, TASCENSO ODT may cause fetal harm when administered to a pregnant woman. In oral studies conducted in rats and rabbits, fingolimod demonstrated developmental toxicity, including an increase in malformations (rats) and embryolethality, when given to pregnant animals. In rats, the highest no-effect dose was less than the recommended human dose of 0.5 mg/day on a body surface area (mg/m 2 ) basis.
The most common fetal visceral malformations in rats were persistent truncus arteriosus and ventricular septal defect. The receptor affected by fingolimod (sphingosine 1-phosphate receptor) is known to be involved in vascular formation during embryogenesis (see Data ). Advise pregnant women of the potential risk to a fetus.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Clinical Considerations In females planning to become pregnant, TASCENSO ODT should be stopped 2 months before planned conception.
The possibility of severe increase in disability should be considered in women who discontinue or are considering discontinuation of TASCENSO ODT because of pregnancy or planned pregnancy. In many of the cases in which increase in disability was reported after stopping fingolimod, the active moiety in TASCENSO ODT, patients had stopped fingolimod because of pregnancy or planned pregnancy [see Warnings and Precautions (5.9 ] . Data Human Data In a prospective observational fingolimod pregnancy registry (2011 - 2024), the rate of major birth defects among 147 live births, stillbirths, or terminations of pregnancy due to fetal anomalies from women who were administered fingolimod during the first trimester was 8.2% (95% CI: 4.3-13.8) using the European Registration of Congenital Anomalies and Twin classification and 10.9% (95% CI: 6.4-17.1) using the Metropolitan Atlanta Congenital Defects Program classification.
The most frequent major birth defects were congenital heart defects, renal/urinary malformations, and limb/musculoskeletal malformations. Study limitations include no adjustment for confounders, no re-adjudication in case of spontaneous resolution, lack of an internal comparator cohort, and small sample size. In fingolimod prospective pharmacovigilance data, the most frequent major birth defect types were similar to those reported in the fingolimod pregnancy registry.
The pattern of malformations reported for fingolimod is similar to that observed in the general population. There is no evidence of clustering of specific birth defects with fingolimod. Animal Data When fingolimod was orally administered to pregnant rats during the period of organogenesis (0, 0.03, 0.1, and 0.3 mg/kg/day or 0, 1, 3, and 10 mg/kg/day), increased incidences of fetal malformations and embryofetal deaths were observed at all but the lowest dose tested (0.03 mg/kg/day), which is less than the recommended human dose (RHD) on a mg/m 2 basis.
Oral administration to pregnant rabbits during organogenesis (0, 0.5, 1.5, and 5 mg/kg/day) resulted in increased incidences of embryofetal mortality and fetal growth retardation at the mid and high doses. The no-effect dose for these effects in rabbits (0.5 mg/kg/day) is approximately 20 times the RHD on a mg/m 2 basis. When fingolimod was orally admini… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of fingolimod for the treatment of relapsing forms of multiple sclerosis in pediatric patients 10 to less than 18 years of age were established in one randomized, double-blind clinical study in 215 patients (fingolimod n = 107; intramuscular interferon (IFN) beta-1a n = 108) [see Clinical Studies (14.2) ] . In the controlled pediatric study, the safety profile in pediatric patients (10 to less than 18 years of age) receiving fingolimod 0.25 mg or 0.5 mg capsules daily was similar to that seen in adult patients.
In the pediatric study, cases of seizures were reported in 5.6% of fingolimod-treated patients and 0.9% of interferon beta-1a-treated patients. It is recommended that pediatric patients, if possible, complete all immunizations in accordance with current immunization guidelines prior to initiating TASCENSO ODT therapy. Safety and effectiveness of TASCENSO ODT in pediatric patients below the age of 10 years have not been established.
Juvenile Animal Toxicity Data In a study in which fingolimod (0.3, 1.5, or 7.5 mg/kg/day) was orally administered to young rats from weaning through sexual maturity, changes in bone mineral density and persistent neurobehavioral impairment (altered auditory startle) were observed at all doses. Delayed sexual maturation was noted in females at the highest dose tested and in males at all doses. The bone changes observed in fingolimod-treated juvenile rats are consistent with a reported role of S1P in the regulation of bone mineral homeostasis.
When fingolimod (0.5 or 5 mg/kg/day) was orally administered to rats from the neonatal period through sexual maturity, a marked decrease in T-cell dependent antibody response was observed at both doses. This effect had not fully recovered by 6 to 8 weeks after the end of treatment. Overall, a no-effect dose for adverse developmental effects in juvenile animals was not identified.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical MS studies of fingolimod capsules did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently than younger patients. TASCENSO ODT should be used with caution in patients aged 65 years and over, reflecting the greater frequency of decreased hepatic, or renal, function and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Fingolimod, the active moiety in TASCENSO ODT, can induce bradycardia as well as AV conduction blocks (including complete AV block). The decline in heart rate usually starts within 1 hour of the first dose and is maximal within 6 hours in most patients [see Warnings and Precautions (5.1) ]. In case of TASCENSO ODT overdosage, observe patients overnight with continuous ECG monitoring in a medical facility, and obtain regular measurements of blood pressure. [see Dosage and Administration (2.4) ].
Neither dialysis nor plasma exchange results in removal of fingolimod from the body.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Fingolimod is metabolized by sphingosine kinase to the active metabolite, fingolimod-phosphate. Fingolimod phosphate is a sphingosine 1-phosphate receptor modulator and binds with high affinity to sphingosine 1-phosphate receptors 1, 3, 4, and 5. Fingolimod-phosphate blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood.
The mechanism by which fingolimod exerts therapeutic effects in multiple sclerosis is unknown but may involve reduction of lymphocyte migration into the central nervous system.
12.2Pharmacodynamics Heart Rate and Rhythm Fingolimod causes a transient reduction in heart rate and AV conduction at treatment initiation [see Warnings and Precautions (5.1) ] . Heart rate progressively increases after the first day, returning to baseline values within 1 month of the start of chronic treatment. Autonomic responses of the heart, including diurnal variation of heart rate and response to exercise, are not affected by fingolimod treatment.
Fingolimod treatment is not associated with a decrease in cardiac output. Potential to Prolong the QT Interval In a thorough QT interval study of doses of 1.25 or 2.5 mg fingolimod capsules at steady-state, when a negative chronotropic effect of fingolimod was still present, fingolimod treatment resulted in a prolongation of QTc, with the upper boundary of the 90% confidence interval (CI) of 14.0 msec. There is no consistent signal of increased incidence of QTc outliers, either absolute or change from baseline, associated with fingolimod treatment.
In MS studies, there was no clinically relevant prolongation of the QT interval, but patients at risk for QT prolongation were not included in clinical studies. Immune System Effects on Immune Cell Numbers in the Blood In a study in which 12 adult subjects received fingolimod 0.5 mg capsules daily, the lymphocyte count decreased to approximately 60% of baseline within 4 to 6 hours after the first dose. With continued daily dosing, the lymphocyte count continued to decrease over a 2-week period, reaching a nadir count of approximately 500 cells/mcL or approximately 30% of baseline.
In a placebo-controlled study in 1272 MS patients (of whom 425 received fingolimod 0.5 mg capsules daily and 418 received placebo), 18% (N = 78) of patients on fingolimod 0.5 mg reached a nadir of < 200 cells/mcL on at least 1 occasion. No patient on placebo reached a nadir of < 200 cells/mcL. Low lymphocyte counts are maintained with chronic daily dosing of fingolimod 0.5 mg daily.
Chronic fingolimod dosing leads to a mild decrease in the neutrophil count to approximately 80% of baseline. Monocytes are unaffected by fingolimod. Peripheral lymphocyte count increases are evident within days of stopping fingolimod treatment and typically normal counts are reached within 1 to 2 months.
Effect on Antibody Response Fingolimod reduces the immune response to vaccination, as evaluated in 2 studies. In the first study, the immunogenicity of keyhole limpet hemocyanin (KLH) and pneumococcal polysaccharide vaccine (PPV-23) immunization were assessed by IgM and IgG titers in a steady-state, randomized, placebo-controlled study in healthy adult volunteers. Compared to placebo, antigen-specific IgM titers were decreased by 91% and 25% in response to KLH and PPV-23, respectively, in subjects on fingolimod 0.5 mg capsules.
Similarly, IgG titers were decreased by 45% and 50%, in response to KLH and PPV-23, respectively, in subjects on fingolimod 0.5 mg daily compared to placebo. The responder rate for fingolimod 0.5 mg as measured by the number of subjects with a > 4-fold increase in KLH IgG was comparable to placebo and 25% lower for PPV-23 IgG, while the number of subjects with a > 4-fold increase in KLH and PPV-23 IgM was 75% and 40% lower, respectively, compared to placebo. The capacity to mount a skin delayed-type hypersensitivity reaction to Candida and tetanus toxo… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Fingolimod is metabolized by sphingosine kinase to the active metabolite, fingolimod-phosphate. Fingolimod phosphate is a sphingosine 1-phosphate receptor modulator and binds with high affinity to sphingosine 1-phosphate receptors 1, 3, 4, and 5. Fingolimod-phosphate blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood.
The mechanism by which fingolimod exerts therapeutic effects in multiple sclerosis is unknown but may involve reduction of lymphocyte migration into the central nervous system.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied 0.25 mg TASCENSO ODT orally disintegrating tablets are supplied as follows: White to off-white, round, orally disintegrating tablet debossed with . Carton of 30 orally disintegrating tablets containing 3 blister cards of 10 orally disintegrating tablets per blister card NDC 70709-062-30 0.5 mg TASCENSO ODT orally disintegrating tablets are supplied as follows: White to off-white, round, orally disintegrating tablet debossed with . Carton of 30 orally disintegrating tablets containing 3 blister cards of 10 orally disintegrating tablets per blister card NDC 70709-065-30 image description image description
16.2Storage and Handling TASCENSO ODT should be stored at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). Protect from moisture. Store in sealed blister pack. Do not open blister until ready to administer.
📦 Storage and Handling ▾
16.1How Supplied 0.25 mg TASCENSO ODT orally disintegrating tablets are supplied as follows: White to off-white, round, orally disintegrating tablet debossed with . Carton of 30 orally disintegrating tablets containing 3 blister cards of 10 orally disintegrating tablets per blister card NDC 70709-062-30 0.5 mg TASCENSO ODT orally disintegrating tablets are supplied as follows: White to off-white, round, orally disintegrating tablet debossed with . Carton of 30 orally disintegrating tablets containing 3 blister cards of 10 orally disintegrating tablets per blister card NDC 70709-065-30 image description image description
16.2Storage and Handling TASCENSO ODT should be stored at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). Protect from moisture. Store in sealed blister pack. Do not open blister until ready to administer.
📋 Description ▾
11 DESCRIPTION Fingolimod is a sphingosine 1-phosphate receptor modulator. Chemically, fingolimod lauryl sulfate is 2-amino-2-[2-(4-octylphenyl)ethyl]propan-1,3-diol lauryl sulfate. Its structure is shown below: Fingolimod lauryl sulfate is a white to practically white powder that is practically insoluble in water.
It has a molecular weight of 573.87 g/mol. TASCENSO ODT is provided as 0.25 mg and 0.5 mg orally disintegrating tablets for oral use. Each orally disintegrating tablet contains 0.25 mg or 0.5 mg of fingolimod (equivalent to 0.47 mg or 0.93 mg of fingolimod lauryl sulfate) and the following inactive ingredients: gelatin, mannitol, medium-chain triglycerides, sodium chloride, and sodium lauryl sulfate.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Administration Tell patients not to discontinue TASCENSO ODT without first discussing this with the prescribing healthcare provider. Advise patients to contact their healthcare provider if they accidently take more TASCENSO ODT than prescribed.
Advise patients to use dry hands when opening the blister pack. Instruct patients to not push the ODT through the lidding foil, but to peel back the lidding foil and then push the underside [see Dosage and Administration ( 2.2 )]. Cardiac Effects Advise patients that initiation of TASCENSO ODT treatment results in a transient decrease in heart rate.
Inform patients that they will need to be observed in the healthcare professional's office or other facility for at least 6 hours after the first dose, after reinitiation if treatment is interrupted or discontinued for certain periods, and after the dosage is increased [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ]. Risk of Infections Inform patients that they may have an increased risk of infections, some of which could be life-threatening, when taking TASCENSO ODT, and that they should contact their healthcare provider if they develop symptoms of infection.
Advise patients that the use of some vaccines should be avoided during treatment with TASCENSO ODT and for 2 months after discontinuation. Recommend to patients that they delay treatment with TASCENSO ODT until after VZV vaccination if they have not had chickenpox or a previous VZV vaccination. Inform patients that prior or concomitant use of drugs that suppress the immune system may increase the risk of infection [see Warnings and Precautions (5.2)].
Progressive Multifocal Leukoencephalopathy Inform patients that cases of progressive multifocal leukoencephalopathy (PML) have occurred in patients who received fingolimod, the active moiety in TASCENSO ODT. Inform the patient that PML is characterized by a progression of deficits and usually leads to death or severe disability over weeks or months. Instruct the patient of the importance of contacting their healthcare provider if they develop any symptoms suggestive of PML.
Inform the patient that typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes [see Warnings and Precautions (5.3) ] . Macular Edema Advise patients that TASCENSO ODT may cause macular edema, and that they should obtain an eye exam near the start of treatment with TASCENSO ODT, have their eyes monitored periodically by an eye care professional while receiving therapy, and contact their healthcare provider if they experience any changes in their vision while taking TASCENSO ODT.
Inform patients with diabetes mellitus or a history of uveitis that their risk of macular edema is increased [see Warnings and Precautions ( 5.4 )]. Hepatic Effects Inform patients that TASCENSO ODT may cause liver injury. Advise patients that they should contact their healthcare provider if they have any unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine [see Warnings and Precautions (5.5) ].
Posterior Reversible Encephalopathy Syndrome Advise patients to immediately report to their healthcare provider any symptoms involving sudden onset of severe headache, altered mental status, visual disturbances, or seizure. Inform patients that delayed treatment could lead to permanent neurological sequelae [see Warnings and Precautions (5.6) ]. Respiratory Effects Advise patients that they should contact their healthcare provider if they experience new onset or worsening of dyspnea [see Warnings and Precautions (5.7) ] .
Fetal Risk Advise pregnant women and females of reproductive potential of the potential… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE TASCENSO ODT ® (tuh-SEN-soh ODT) (fingolimod) orally disintegrating tablets This Medication Guide has been approved by the U.S. Food and Drug Administration Revised: 6/2026 Read this Medication Guide before you start taking TASCENSO ODT and each time you get a refill. There may be new information.
If you are the parent of a child who is being treated with TASCENSO ODT, the following information applies to your child. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment. What is the most important information I should know about TASCENSO ODT?
TASCENSO ODT may cause serious side effects, including: 1. Slow heart rate (bradycardia or bradyarrhythmia) when you start taking TASCENSO ODT. TASCENSO ODT can cause your heart rate to slow down, especially after you take your first dose.
You will have a test, called an electrocardiogram (ECG), to check the electrical activity of your heart before you take your first dose of TASCENSO ODT. All adults and children will be observed by a healthcare professional for at least 6 hours after taking their first dose of TASCENSO ODT. Children should also be observed by a healthcare professional for at least 6 hours after taking their first dose of 0.5 mg of TASCENSO ODT when switching from the 0.25 mg dose.
After you take your first dose of TASCENSO ODT, and after a child takes their first dose of 0.5 mg of TASCENSO ODT when switching from the 0.25 mg dose: Your pulse and blood pressure should be checked every hour. You should be observed by a healthcare professional to see if you have any serious side effects. If your heart rate slows down too much, you may have symptoms, such as: dizziness tiredness feeling like your heart is beating slowly or skipping beats chest pain If you have any symptoms of slow heart rate, they will usually happen during the first 6 hours after your first dose of TASCENSO ODT.
Symptoms can happen up to 24 hours after you take your first dose of TASCENSO ODT. 6 hours after you take your first dose of TASCENSO ODT you will have another ECG. If your ECG shows any heart problems or if your heart rate is still too low or continues to decrease, you will continue to be observed.
If you have any serious side effects after your first dose of TASCENSO ODT, especially those that require treatment with other medicines, you will stay in the medical facility to be observed overnight. You will also be observed for any serious side effects for at least 6 hours after you take your second dose of TASCENSO ODT the next day. If you have certain types of heart problems, or if you are taking certain types of medicines that can affect your heart, you will be observed overnight after you take your first dose of TASCENSO ODT.
Your slow heart rate will usually return to normal within 1 month after you start taking TASCENSO ODT. Call your healthcare provider or go to the nearest hospital emergency room right away if you have any symptoms of a slow heart rate. If you miss 1 or more doses of TASCENSO ODT, you may need to be observed by a healthcare professional when you take your next dose.
Call your healthcare provider if you miss a dose of TASCENSO ODT. See "How should I take TASCENSO ODT?" 2. Pregnancy.
Please consult your healthcare provider before getting pregnant. You should avoid becoming pregnant while taking TASCENSO ODT or in the two months after you stop taking it because of the risk of harm to the baby. 3.
Infections. TASCENSO ODT can increase your risk of serious infections that can be life-threatening and cause death. You should not receive live vaccines during treatment with TASCENSO ODT and for 2 months after you stop taking TASCENSO ODT.
Talk to your healthcare provider before you receive a vaccine during treatment and for 2 months after treatment with TASCENSO ODT. If you receive a live vaccine, you may get the infection the vaccine was meant to prevent. Vaccines may not work as well when given… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The T max of fingolimod is 12 to 16 hours. The apparent absolute oral bioavailability is 93%. Food intake does not alter C max or (AUC) of fingolimod or fingolimod-phosphate.
Therefore, TASCENSO ODT may be taken without regard to meals. Steady-state blood concentrations of fingolimod are reached within 1 to 2 months following once-daily administration and steady-state levels are approximately 10-fold greater than with the initial dose. Distribution Fingolimod highly (86%) distributes in red blood cells.
Fingolimod-phosphate has a smaller uptake in blood cells of < 17%. Fingolimod and fingolimod-phosphate are > 99.7% protein bound. Fingolimod and fingolimod-phosphate protein binding is not altered by renal or hepatic impairment.
Fingolimod is extensively distributed to body tissues with a volume of distribution of about 1200 ± 260 L. Metabolism The biotransformation of fingolimod in humans occurs by 3 main pathways: by reversible stereoselective phosphorylation to the pharmacologically active ( S )-enantiomer of fingolimod-phosphate, by oxidative biotransformation catalyzed mainly by the cytochrome P450 4F2 (CYP4F2) and possibly other CYP4F isoenzymes with subsequent fatty acid-like degradation to inactive metabolites, and by formation of pharmacologically inactive non-polar ceramide analogs of fingolimod.
Inhibitors or inducers of CYP4F2 and possibly other CYP4F isozymes might alter the exposure of fingolimod or fingolimod-phosphate. In vitro studies in hepatocytes indicated that CYP3A4 may contribute to fingolimod metabolism in the case of strong induction of CYP3A4. Following single oral administration of [ 14 C] fingolimod, the major fingolimod-related components in blood, as judged from their contribution to the AUC up to 816 hours post-dose of total radiolabeled components, are fingolimod itself (23.3%), fingolimod-phosphate (10.3%), and inactive metabolites [M3 carboxylic acid metabolite (8.3%), M29 ceramide metabolite (8.9%), and M30 ceramide metabolite (7.3%)].
Elimination Fingolimod blood clearance is 6.3 ±
2.3L/h, and the average apparent terminal half-life (t 1/2 ) is 6 to 9 days. Blood levels of fingolimod-phosphate decline in parallel with those of fingolimod in the terminal phase, yielding similar half-lives for both. After oral administration, about 81% of the dose is slowly excreted in the urine as inactive metabolites.
Fingolimod and fingolimod-phosphate are not excreted intact in urine but are the major components in the feces with amounts of each representing less than 2.5% of the dose. Specific Populations Pediatric Patients The median fingolimod-phosphate (fingolimod-P) concentration in pediatric MS patients aged 10 to less than 18 years was 1.10 ng/mL, as compared to 1.35 ng/mL in adult MS patients. Geriatric Patients The mechanism for elimination and results from population pharmacokinetics suggest that dose adjustment would not be necessary in elderly patients.
However, clinical experience in patients aged above 65 years is limited. Gender Gender has no clinically significant influence on fingolimod and fingolimod-phosphate pharmacokinetics. Race The effects of race on fingolimod and fingolimod-phosphate pharmacokinetics cannot be adequately assessed due to a low number of patients who self-identified as Black or African American, Asian, or other races in the clinical program.
Renal Impairment In adult patients with severe renal impairment, fingolimod C max and AUC are increased by 32% and 43%, respectively, and fingolimod-phosphate C max and AUC are increased by 25% and 14%, respectively, with no change in apparent elimination half-life. Based on these findings, the TASCENSO ODT 0.5 mg dose is appropriate for use in adult patients with renal impairment. TASCENSO ODT 0.25 mg and 0.5 mg are appropriate for use in pediatric patients with renal impairment.
The systemic exposure of 2 metabolites (M2 and M3) is increased by 3-and 13-fold, respectively. The toxicity of these… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Heart Rate and Rhythm Fingolimod causes a transient reduction in heart rate and AV conduction at treatment initiation [see Warnings and Precautions (5.1) ] . Heart rate progressively increases after the first day, returning to baseline values within 1 month of the start of chronic treatment. Autonomic responses of the heart, including diurnal variation of heart rate and response to exercise, are not affected by fingolimod treatment.
Fingolimod treatment is not associated with a decrease in cardiac output. Potential to Prolong the QT Interval In a thorough QT interval study of doses of 1.25 or 2.5 mg fingolimod capsules at steady-state, when a negative chronotropic effect of fingolimod was still present, fingolimod treatment resulted in a prolongation of QTc, with the upper boundary of the 90% confidence interval (CI) of 14.0 msec. There is no consistent signal of increased incidence of QTc outliers, either absolute or change from baseline, associated with fingolimod treatment.
In MS studies, there was no clinically relevant prolongation of the QT interval, but patients at risk for QT prolongation were not included in clinical studies. Immune System Effects on Immune Cell Numbers in the Blood In a study in which 12 adult subjects received fingolimod 0.5 mg capsules daily, the lymphocyte count decreased to approximately 60% of baseline within 4 to 6 hours after the first dose. With continued daily dosing, the lymphocyte count continued to decrease over a 2-week period, reaching a nadir count of approximately 500 cells/mcL or approximately 30% of baseline.
In a placebo-controlled study in 1272 MS patients (of whom 425 received fingolimod 0.5 mg capsules daily and 418 received placebo), 18% (N = 78) of patients on fingolimod 0.5 mg reached a nadir of < 200 cells/mcL on at least 1 occasion. No patient on placebo reached a nadir of < 200 cells/mcL. Low lymphocyte counts are maintained with chronic daily dosing of fingolimod 0.5 mg daily.
Chronic fingolimod dosing leads to a mild decrease in the neutrophil count to approximately 80% of baseline. Monocytes are unaffected by fingolimod. Peripheral lymphocyte count increases are evident within days of stopping fingolimod treatment and typically normal counts are reached within 1 to 2 months.
Effect on Antibody Response Fingolimod reduces the immune response to vaccination, as evaluated in 2 studies. In the first study, the immunogenicity of keyhole limpet hemocyanin (KLH) and pneumococcal polysaccharide vaccine (PPV-23) immunization were assessed by IgM and IgG titers in a steady-state, randomized, placebo-controlled study in healthy adult volunteers. Compared to placebo, antigen-specific IgM titers were decreased by 91% and 25% in response to KLH and PPV-23, respectively, in subjects on fingolimod 0.5 mg capsules.
Similarly, IgG titers were decreased by 45% and 50%, in response to KLH and PPV-23, respectively, in subjects on fingolimod 0.5 mg daily compared to placebo. The responder rate for fingolimod 0.5 mg as measured by the number of subjects with a > 4-fold increase in KLH IgG was comparable to placebo and 25% lower for PPV-23 IgG, while the number of subjects with a > 4-fold increase in KLH and PPV-23 IgM was 75% and 40% lower, respectively, compared to placebo. The capacity to mount a skin delayed-type hypersensitivity reaction to Candida and tetanus toxoid was decreased by approximately 30% in subjects on fingolimod 0.5 mg daily, compared to placebo.
Immunologic responses were further decreased with fingolimod 1.25 mg (a dose higher than recommended in MS) [see Warnings and Precautions (5.2) ] . In the second study, the immunogenicity of Northern hemisphere seasonal influenza and tetanus toxoid vaccination was assessed in a 12-week steady-state, randomized, placebo-controlled study of fingolimod 0.5 mg capsules in adult multiple sclerosis patients (n = 136). The responder rate 3 weeks after vaccination, defined as seroconversion or a ≥ 4-fold increase in a… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of TASCENSO ODT is based on the relative bioavailability of TASCENSO ODT orally disintegrating tablets compared to fingolimod capsules in healthy adults [see Clinical Pharmacology (12.3) ]. The clinical studies described below were conducted using fingolimod capsules.
14.1Adults The efficacy of fingolimod was demonstrated in 2 studies that evaluated once-daily doses of fingolimod capsules 0.5 mg and 1.25 mg in patients with relapsing-remitting MS (RRMS). Both studies included patients who had experienced at least 2 clinical relapses during the 2 years prior to randomization or at least 1 clinical relapse during the 1 year prior to randomization and had an Expanded Disability Status Scale (EDSS) score from 0 to 5.5. Study 1 was a 2-year randomized, double-blind, placebo-controlled study in patients with RRMS who had not received any interferon-beta or glatiramer acetate for at least the previous 3 months and had not received any natalizumab for at least the previous 6 months.
Neurological evaluations were performed at screening, every 3 months and at time of suspected relapse. MRI evaluations were performed at screening, Month 6, Month 12, and Month 24. The primary endpoint was the annualized relapse rate.
Median age was 37 years, median disease duration was 6.7 years and median EDSS score at baseline was 2.0. Patients were randomized to receive fingolimod 0.5 mg (N = 425), 1.25 mg (N = 429), or placebo (N = 418) for up to 24 months. Median time on study drug was 717 days on 0.5 mg, 715 days on 1.25 mg, and 719 days on placebo.
The annualized relapse rate was significantly lower in patients treated with fingolimod than in patients who received placebo. The secondary endpoint was the time to 3-month confirmed disability progression as measured by at least a 1-point increase from baseline in EDSS (0.5-point increase for patients with baseline EDSS of 5.5) sustained for 3 months. Time to onset of 3-month confirmed disability progression was significantly delayed with fingolimod treatment compared to placebo.
The 1.25 mg dose resulted in no additional benefit over the fingolimod 0.5 mg dose. The results for this study are shown in Table 2 and Figure 1. Table 2: Clinical and MRI Results of Study 1 Fingolimod Capsules 0.5 mg Placebo p-value N = 425 N = 418 Clinical Endpoints Annualized relapse rate (primary endpoint) 0.18 0.40 < 0.001 Percentage of patients without relapse 70% 46% < 0.001 Hazard ratio § of disability progression (95% CI) 0.70 (0.52, 0.96)
0.02MRI Endpoint Mean (median) number of new or newly enlarging T2 lesions over 24 months 2.5 (0) 9.8 (5.0) < 0.001 Mean (median) number of T1 Gd-enhancing lesions at Month 24 0.2 (0) 1.1 (0) < 0.001 Abbreviation: CI, confidence interval. All analyses of clinical endpoints were intent-to-treat. MRI analysis used evaluable dataset. § Hazard ratio is an estimate of the relative risk of having the event of disability progression on fingolimod as compared to placebo.
Figure 1: Time to 3-Month Confirmed Disability Progression - Study 1 (ITT population) Study 2 was a 1-year randomized, double-blind, double-dummy, active-controlled study in patients with RRMS who had not received any natalizumab in the previous 6 months. Prior therapy with interferon-beta or glatiramer acetate up to the time of randomization was permitted. Neurological evaluations were performed at screening, every 3 months, and at the time of suspected relapses.
MRI evaluations were performed at screening and at Month 12. The primary endpoint was the annualized relapse rate. Median age was 36 years, median disease duration was 5.9 years, and median EDSS score at baseline was 2.0.
Patients were randomized to receive fingolimod capsules 0.5 mg (N = 431), 1.25 mg (N = 426), or interferon beta-1a, 30 mcg via the intramuscular route (IM) once-weekly (N = 435) for up to 12 months. Median time on study drug was 365 days on fingolimod 0.5 mg, 354 days on 1.25 mg, and 361 days on interferon beta-… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Oral carcinogenicity studies of fingolimod were conducted in mice and rats. In mice, fingolimod was administered at oral doses of 0, 0.025, 0.25, and 2.5 mg/kg/day for up to 2 years. The incidence of malignant lymphoma was increased in males and females at the mid and high dose.
The lowest dose tested (0.025 mg/kg/day) is less than the RHD of 0.5 mg/day on a body surface area (mg/m 2 ) basis. In rats, fingolimod was administered at oral doses of 0, 0.05, 0.15, 0.5, and 2.5 mg/kg/day. No increase in tumors was observed.
The highest dose tested (2.5 mg/kg/day) is approximately 50 times the RHD on a mg/m 2 basis. Fingolimod was negative in a battery of in vitro (Ames, mouse lymphoma thymidine kinase, chromosomal aberration in mammalian cells) and in vivo (micronucleus in mouse and rat) assays. When fingolimod was administered orally (0, 1, 3, and 10 mg/kg/day) to male and female rats prior to and during mating, and continuing to Day 7 of gestation in females, no effect on fertility was observed up to the highest dose tested (10 mg/kg), which is approximately 200 times the RHD on a mg/m 2 basis.
13.2Animal Toxicology and/or Pharmacology Lung toxicity was observed in 2 different strains of rats and in dogs and monkeys. The primary findings included increase in lung weight, associated with smooth muscle hypertrophy, hyperdistention of the alveoli, and/or increased collagen. Insufficient or lack of pulmonary collapse at necropsy, generally correlated with microscopic changes, was observed in all species.
In rats and monkeys, lung toxicity was observed at all oral doses tested in chronic studies. The lowest doses tested in rats (0.05 mg/kg/day in the 2-year carcinogenicity study) and monkeys (0.5 mg/kg/day in the 39-week toxicity study) are similar to and approximately 20 times the RHD on a mg/m 2 basis, respectively. In the 52-week oral study in monkeys, respiratory distress associated with ketamine administration was observed at doses of 3 and 10 mg/kg/day; the most affected animal became hypoxic and required oxygenation.
As ketamine is not generally associated with respiratory depression, this effect was attributed to fingolimod. In a subsequent study in rats, ketamine was shown to potentiate the bronchoconstrictive effects of fingolimod. The relevance of these findings to humans is unknown.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Oral carcinogenicity studies of fingolimod were conducted in mice and rats. In mice, fingolimod was administered at oral doses of 0, 0.025, 0.25, and 2.5 mg/kg/day for up to 2 years. The incidence of malignant lymphoma was increased in males and females at the mid and high dose.
The lowest dose tested (0.025 mg/kg/day) is less than the RHD of 0.5 mg/day on a body surface area (mg/m 2 ) basis. In rats, fingolimod was administered at oral doses of 0, 0.05, 0.15, 0.5, and 2.5 mg/kg/day. No increase in tumors was observed.
The highest dose tested (2.5 mg/kg/day) is approximately 50 times the RHD on a mg/m 2 basis. Fingolimod was negative in a battery of in vitro (Ames, mouse lymphoma thymidine kinase, chromosomal aberration in mammalian cells) and in vivo (micronucleus in mouse and rat) assays. When fingolimod was administered orally (0, 1, 3, and 10 mg/kg/day) to male and female rats prior to and during mating, and continuing to Day 7 of gestation in females, no effect on fertility was observed up to the highest dose tested (10 mg/kg), which is approximately 200 times the RHD on a mg/m 2 basis.
📄 Recent Major Changes ▾
Contraindications (removal) ( 4 ) 6/2026 Warnings and Precautions ( 5.8 , 5.11 ) 6/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 0.25 mg Tablet Carton containing Blisters Rx Only FOR ORAL USE ONLY NDC 70709-062-30 CYCLE PHARMA TASCENSO ODT ® (fingolimod) orally disintegrating tablets 0.25 mg Contains 30 tablets (3 blister cards of 10 tablets) PHARMACIST: Provide the accompanying Medication Guide to each patient. PRINCIPAL DISPLAY PANEL - 0.25 mg Tablet Blister Pack Carton
PRINCIPAL DISPLAY PANEL - 0.5 mg Tablet Carton containing Blisters Rx Only FOR ORAL USE ONLY NDC 70709-065-30 CYCLE PHARMA TASCENSO ODT ® (fingolimod) orally disintegrating tablets 0.5 mg Contains 30 tablets (3 blister cards of 10 tablets) PHARMACIST: Provide the accompanying Medication Guide to each patient. image description
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |