
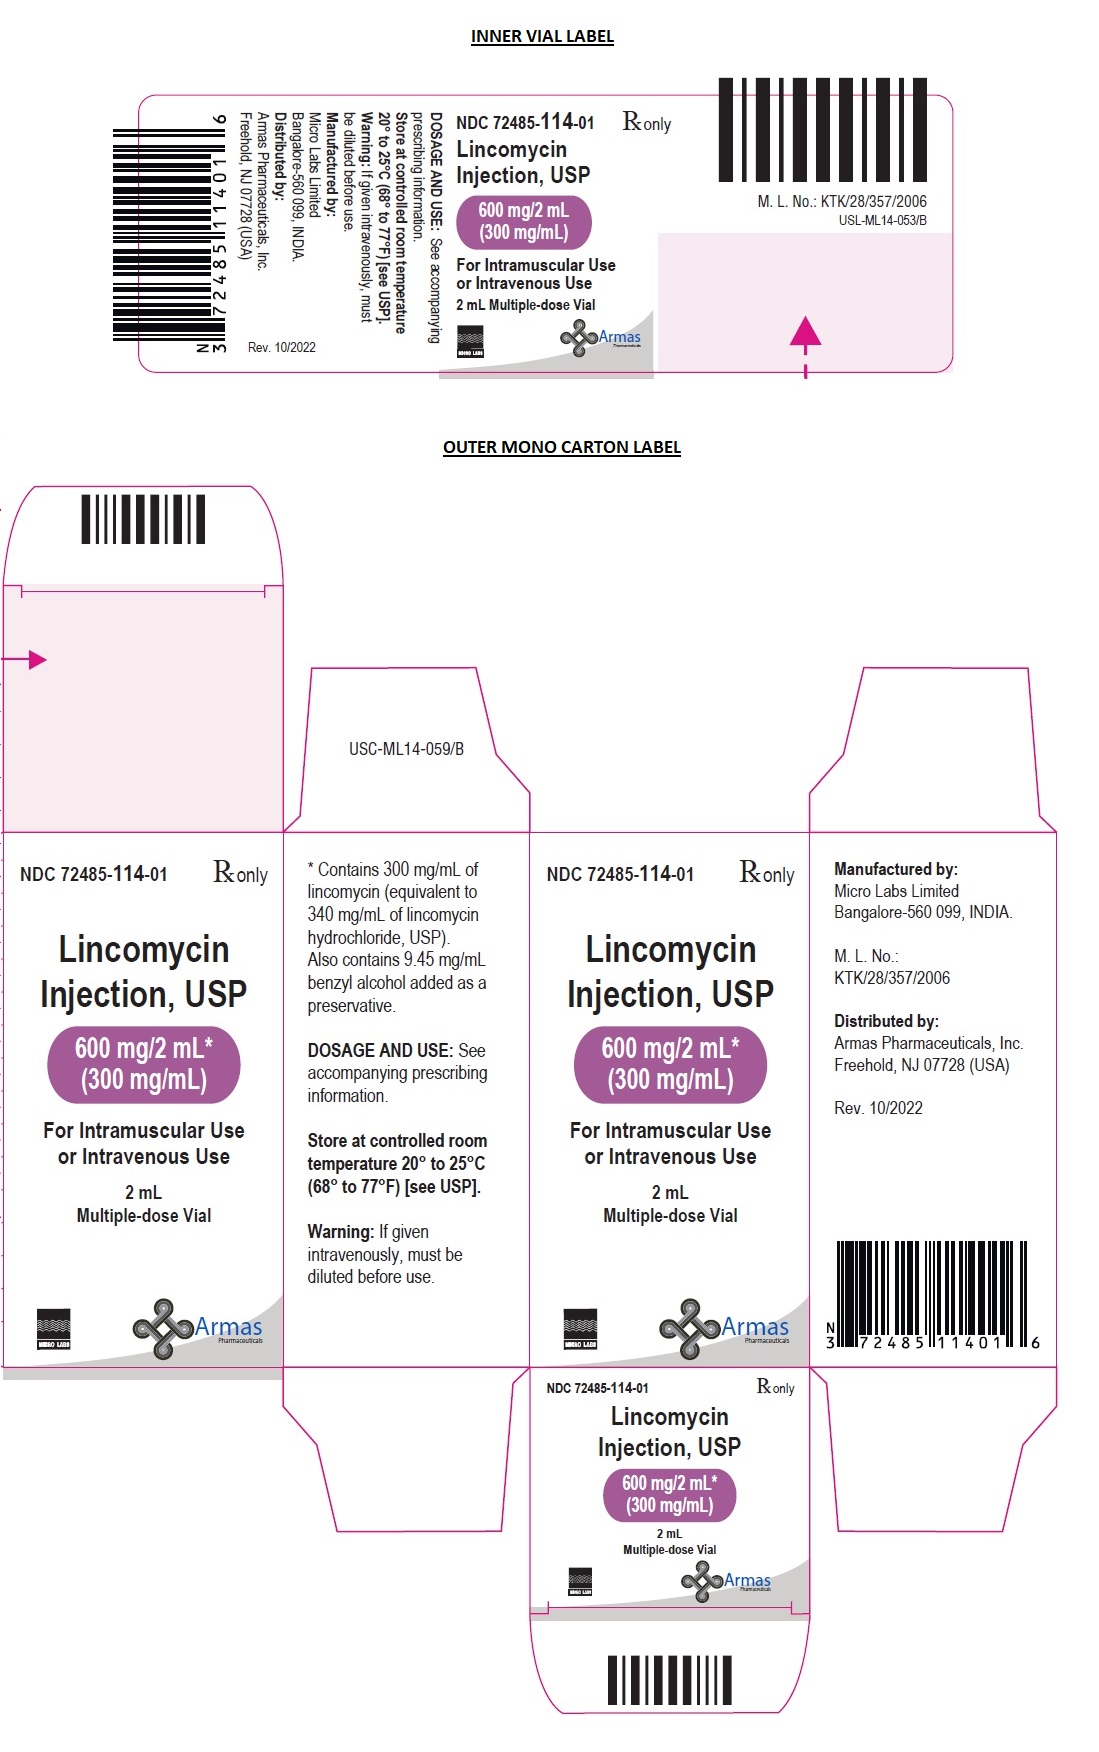
Lincomycin 600 mg/2mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Lincosamides class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lincomycin HCl — tap one for details:
Lincomycin HCl may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII LKG8494WBH
Benzyl alcohol is a clear liquid used as a preservative and solvent in medicines. It helps prevent bacterial and fungal growth and dissolves other ingredients to create uniform liquid formulations.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $2.57 | $5.13 / 2 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2010 | $4.234 / J2010 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lincocin 300 mg/mL 00009-0104-04 | Pharmacia | 1 vial | — | AP | FDA listed | — |
| Lincocin 300 mg/mL 00009-0107-04 | Pharmacia | 1 vial | — | AP | FDA listed | — |
| Lincomycin 3000 mg/10mL 00121-1035-55 | PAI | 10 vials | — | AP | FDA listed | — |
| Lincomycin 300 mg/mL 00404-9901-10 | Henry | 1 vial | — | AP | FDA listed | — |
| Lincomycin 300 mg/mL 25021-0193-02 | Sagent | 10 vials | — | AP | FDA listed | — |
| Lincomycin 300 mg/mL 39822-0350-02 | XGen | 10 vials | — | AP | FDA listed | — |
| Lincomycin 300 mg/mL 39822-0353-06 | XGen | 10 ml | — | AP | FDA listed | — |
| Lincomycin 300 mg/mL 42571-0374-75 | Micro | 1 vial | — | AP | FDA listed | — |
| lincomycin hydrochloride 300 mg/mL 68083-0478-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Lincomycin hydrochloride 300 mg/mL 68083-0479-01 | Gland | 1 vial | — | AP | FDA listed | — |
| lincomycin 300 mg/mL 70436-0034-82 | Slate | 10 vials | — | — | FDA listed | — |
| lincomycin 300 mg/mL 70436-0035-80 | Slate | 1 vial | — | — | FDA listed | — |
| Lincomycin 600 mg/2mLthis 72485-0114-01 | Armas | 1 vial | — | AP | FDA listed | — |
| Lincomycin 3000 mg/10mL 72485-0115-10 | Armas | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72485-0114-01 You're viewing this | 1 VIAL, MULTI-DOSE in 1 CARTON (72485-114-01) / 2 mL in 1 VIAL, MULTI-DOSE | 2023-05-05 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Clostridioides difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including lincomycin and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile. Because lincomycin therapy has been associated with severe colitis which may end fatally, it should be reserved for serious infections where less toxic antimicrobial agents are inappropriate, as described in the INDICATIONS AND USAGE section.
It should not be used in patients with nonbacterial infections such as most upper respiratory tract infections. C. diffficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibacterial use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial use not directed against C. difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibacterial treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Lincomycin injection is indicated in the treatment of serious infections due to susceptible strains of streptococci, pneumococci, and staphylococci. Its use should be reserved for penicillin-allergic patients or other patients for whom, in the judgment of the physician, a penicillin is inappropriate. Because of the risk of CDAD, as described in the BOXED WARNING , before selecting lincomycin the physician should consider the nature of the infection and the suitability of other alternatives.
Indicated surgical procedures should be performed in conjunction with antibacterial therapy. Lincomycin injection may be administered concomitantly with other antimicrobial agents when indicated. Lincomycin is not indicated in the treatment of minor bacterial infections or viral infections.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of lincomycin and other antibacterial drugs, lincomycin should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION If significant diarrhea occurs during therapy, lincomycin should be discontinued. (see BOXED WARNING ) INTRAMUSCULAR - Adults: Serious infections- 600 mg (2 mL) intramuscularly every 24 hours. More severe infections- 600 mg (2 mL) intramuscularly every 12 hours or more often.
Pediatric patients over 1 month of age: Serious infections- one intramuscular injection of 10 mg/kg (5 mg/lb) every 24 hours. More severe infections- one intramuscular injection of 10 mg/kg (5 mg/lb) every 12 hours or more often. INTRAVENOUS - Adults: The intravenous dose will be determined by the severity of the infection.
For serious infections doses of 600 mg of lincomycin (2 mL of lincomycin) to 1 gram are given every 8 to 12 hours. For more severe infections these doses may have to be increased. In life-threatening situations daily intravenous doses of as much as 8 grams have been given.
Intravenous doses are given on the basis of 1 gram of lincomycin diluted in not less than 100 mL of appropriate solution (see PHYSICAL COMPATIBILITIES ) and infused over a period of not less than one hour. Dose Vol. Diluent Time 600 mg 100 mL 1 hr 1 gram 100 mL 1 hr 2 grams 200 mL 2 hr 3 grams 300 mL 3 hr 4 grams 400 mL 4 hr These doses may be repeated as often as required to the limit of the maximum recommended daily dose of 8 grams of lincomycin.
Pediatric patients over 1 month of age: 10 to 20 mg/kg/day (5 to 10 mg/lb/day) depending on the severity of the infection may be infused in divided doses as described above for adults. NOTE: Severe cardiopulmonary reactions have occurred when lincomycin has been given at greater than the recommended concentration and rate (see PRECAUTIONS ). SUBCONJUNCTIVAL INJECTION - 0.25 mL (75 mg) injected subconjunctivally will result in ocular fluid concentrations of antibacterial (lasting for at least 5 hours) sufficient for most susceptible pathogens.
Patients with Renal Impairment When therapy with lincomycin is required in individuals with severe renal impairment, an appropriate dose is 25 to 30% of that recommended for patients with normally functioning kidneys (see PRECAUTIONS ). Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
⛔ Contraindications ▾
CONTRAINDICATIONS Lincomycin injection is contraindicated in patients previously found to be hypersensitive to lincomycin or clindamycin.
⚠️ Warnings ▾
WARNINGS See BOXED WARNING . Clostridioides difficile associated diarrhea Clostridioides difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including Lincomycin, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
Hypersensitivity Severe hypersensitivity reactions, including anaphylactic reactions and severe cutaneous adverse reactions (SCAR) such as Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), acute generalized exanthematous pustulosis (AGEP), and erythema multiforme (EM) have been reported in patients receiving lincomycin therapy. If an anaphylactic reaction or severe skin reaction occurs, lincomycin should be discontinued and appropriate therapy should be initiated. (see ADVERSE REACTIONS ) Benzyl Alcohol Toxicity in Pediatric Patients (Gasping Syndrome) Lincomycin injection contains benzyl alcohol as a preservative.
The preservative benzyl alcohol has been associated with serious adverse events, including the “gasping syndrome”, and death in pediatric patients. Although normal therapeutic doses of this product ordinarily deliver amounts of benzyl alcohol that are substantially lower than those reported in association with the “gasping syndrome”, the minimum amount of benzyl alcohol at which toxicity may occur is not known. The risk of benzyl alcohol toxicity depends on the quantity administered and the liver and kidneys’ capacity to detoxify the chemical.
Premature and low-birth weight infants may be more likely to develop toxicity. Inadequate for Use in Meningitis Although lincomycin appears to diffuse into cerebrospinal fluid, concentrations of lincomycin in the CSF may be inadequate for the treatment of meningitis.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions have been reported with the use of lincomycin. Gastrointestinal disorders Diarrhea, nausea, vomiting, glossitis, stomatitis, abdominal pain, abdominal discomfort † , anal pruritus Skin and subcutaneous tissue disorders Toxic epidermal necrolysis, Stevens-Johnson syndrome, acute generalized exanthematous pustulosis, dermatitis bullous, dermatitis exfoliative, erythema multiforme (see WARNINGS ) , rash, urticaria, pruritus Infections and infestations Vaginal infection, pseudomembranous colitis, Clostridioides difficile colitis (see WARNINGS ) Blood and lymphatic system disorders Pancytopenia, agranulocytosis, aplastic anemia, leukopenia, neutropenia, thrombocytopenic purpura Immune system disorders Anaphylactic reaction (see WARNINGS ), angioedema, serum sickness Hepatobiliary disorders Jaundice, liver function test abnormal, transaminases increased Renal and urinary disorders Renal impairment, oliguria, proteinuria, azotemia Cardiac disorders Cardio-respiratory arrest (see DOSAGE AND ADMINISTRATION ) Vascular disorders Hypotension (see DOSAGE AND ADMINISTRATION ), thrombophlebitis † Ear and labyrinth disorders Vertigo, tinnitus Neurologic disorder Headache, dizziness, somnolence General disorders and administration site conditions Injection site abscess sterile ‡ , injection site induration ‡ , injection site pain ‡ , injection site irritation ‡ † Event has been reported with intravenous injection. ‡ Reported with intramuscular injection.
To report SUSPECTED ADVERSE REACTIONS, contact Micro Labs USA, Inc. at 1-855-839-8195 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Lincomycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents; therefore, it should be used with caution in patients receiving such agents.
🤰 Pregnancy ▾
Pregnancy There are no adequate and well-controlled studies in pregnant women. Lincomycin Sterile Solution contains benzyl alcohol as a preservative. Benzyl alcohol can cross the placenta.
See WARNINGS . Lincomycin should be used during pregnancy only if clearly needed. Teratogenic Effects: In a study with 60 pregnant women, cord serum concentrations were approximately 25% of the maternal serum concentrations, indicating that lincomycin crosses the placenta, and no substantial accumulation occurred in the amniotic fluid.
Experience with 345 obstetrical patients receiving lincomycin revealed no ill effects related to pregnancy. There was no evidence of teratogenicity when lincomycin was administered in diet to pregnant Sprague Dawley rats during the period of major organogenesis at doses up to 5000 mg/kg (approximately 6 times the maximum recommended human dose [MRHD], respectively, based on body surface area comparison). Nonteratogenic Effects: Reproduction studies performed in rats administered oral lincomycin in diet for 2 weeks prior to mating, throughout pregnancy and lactation, revealed no adverse effects on survival of offspring from birth to weaning at doses up to 1000 mg/kg (1.2 times the MRHD based on body surface area comparison) up to 2 generations.
🧒 Pediatric Use ▾
Pediatric Use Lincomycin injection contains benzyl alcohol as a preservative. Benzyl alcohol has been associated with a fatal “Gasping Syndrome” in premature infants. See WARNINGS . Safety and effectiveness in pediatric patients below the age of one month have not been established. (see DOSAGE AND ADMINISTRATION )
🆘 Overdosage ▾
OVERDOSAGE Serum concentrations of lincomycin are not appreciably affected by hemodialysis and peritoneal dialysis.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Intramuscular administration of a single dose of 600 mg of lincomycin produces average peak serum concentrations of 11.6 mcg/mL at 60 minutes and maintains therapeutic concentrations for 17 to 20 hours for most susceptible gram-positive organisms. Urinary excretion after this dose ranges from 1.8 to 24.8 percent (mean: 17.3 percent). A two hour intravenous infusion of 600 mg of lincomycin achieves average peak serum concentrations of 15.9 mcg/mL and maintains therapeutic concentrations for 14 hours for most susceptible gram-positive organisms.
Urinary excretion ranges from 4.9 to 30.3 percent (mean: 13.8 percent). The biological half-life after intramuscular or intravenous administration is 5.4 ± 1.0 hours. The serum half-life of lincomycin may be prolonged in patients with severe renal impairment compared to patients with normal renal function.
In patients with hepatic impairment, serum half-life may be twofold longer than in patients with normal hepatic function. Hemodialysis and peritoneal dialysis are not effective in removing lincomycin from the serum. Tissue distribution studies indicate that bile is an important route of excretion.
Significant concentrations have been demonstrated in most body tissues. Although lincomycin appears to diffuse into cerebrospinal fluid (CSF), concentrations of lincomycin in the CSF appear inadequate for the treatment of meningitis. Microbiology: Mechanism of Action Lincomycin inhibits bacterial protein synthesis by binding to the 23S RNA of the 50S subunit of the bacterial ribosome.
Lincomycin is predominantly bacteriostatic in vitro . Resistance Cross resistance has been demonstrated between clindamycin and lincomycin. Resistance is most often due to methylation of specific nucleotides in the 23S RNA of the 50S ribosomal subunit, which can determine cross resistance to macrolides and streptogramins B (MLSB phenotype).
Macrolide-resistant isolates of these organisms should be tested for inducible resistance to lincomycin/clindamycin using the D-zone test or other appropriate method. Antimicrobial Activity Lincomycin has been shown to be active against most strains of the following bacteria both in vitro and in clinical infections: (see INDICATIONS AND USAGE ). Staphylococcus aureus Streptococcus pneumoniae The following in vitro data are available, but their clinical significance is unknown.
Lincomycin has been shown to be active in vitro against the following microorganisms; however, the safety and efficacy of lincomycin in treating clinical infections due to these organisms have not been established in adequate and well controlled trials. Gram-positive bacteria: Corynebacterium diphtheriae Streptococcus pyogenes Viridans group streptococci Anaerobic bacteria: Clostridium tetani Clostridium perfringens Susceptibility Testing For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Lincomycin Injection, USP is a sterile, clear, colorless to slightly yellow solution, having a slight odor. Free from any visible particles available in the following strength and package sizes: Unit of Sale Concentration NDC 72485-114-01 2 mL mono carton multiple-dose vial 600 mg/2 mL (300 mg/mL) Each mL of Lincomycin Injection, USP contains 300 mg lincomycin (equivalent to 340 mg lincomycin hydrochloride, USP); also benzyl alcohol, 9.45 mg added as preservative. Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP].
📋 Description ▾
DESCRIPTION Lincomycin injection, USP is a sterile solution containing lincomycin hydrochloride which is the monohydrated salt of lincomycin, a lincosamide antibacterial produced by the growth of a member of the lincolnensis group of Streptomyces lincolnensis (Fam. Streptomycetaceae ). The chemical name for lincomycin hydrochloride is Methyl 6,8-dideoxy-6-(1-methyl-trans-4-propyl-L2-pyrolidinecarboxamido)-1-thio-D-erythro-α-D-galacto-octopyranoside monohydrochloride monohydrate.
The molecular formula of lincomycin hydrochloride is C 18 H 34 N 2 O 6 S.HCl.H 2 O and the molecular weight is 461.01. The structural formula is represented below: Lincomycin hydrochloride is a white or practically white, crystalline powder. Its solutions are acid and are dextrorotatory.
Lincomycin hydrochloride is freely soluble in water; soluble in dimethylformamide and insoluble in acetone. Lincomycin Injection, USP contains lincomycin hydrochloride in a sterile, clear, colorless to slightly yellow solution with benzyl alcohol used as a preservative 9.45 mg/mL, and water for injection. Lincomycin injection, USP is a sterile solution for intramuscular and intravenous use.
Lincomycin injection, USP is supplied in 2 mL and 10 mL multiple-dose vials containing 300 mg/mL of lincomycin (equivalent to 340 mg/mL of lincomycin hydrochloride, USP). strc
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including lincomycin should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When lincomycin is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by lincomycin or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibacterial which usually ends when the antibacterial is discontinued. Sometimes after starting treatment with an antibacterial, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after taking the last dose of the antibacterial.
If this occurs, patients should contact their physician as soon as possible.