
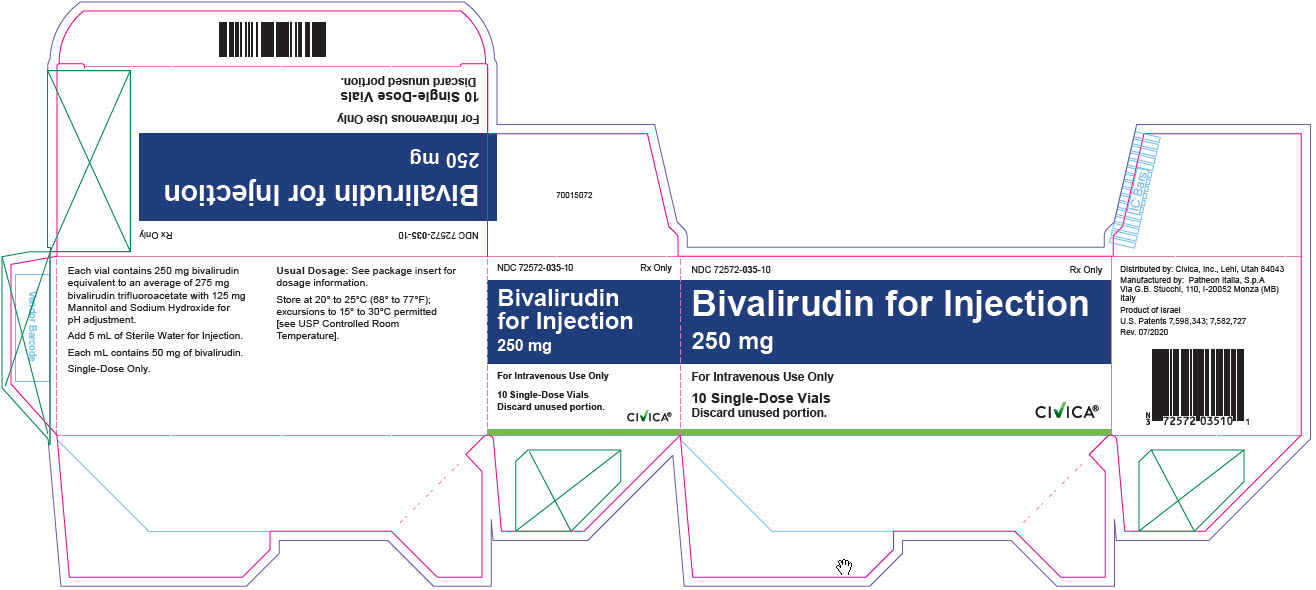
bivalirudin 250 mg Injection, Powder, Lyophilized, For Solution, 10 vials
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Direct Thrombin Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bivalirudin — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0583 | $0.166 / J0583 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bivalirudin 250 mg/5mL 16729-0275-67 | Accord | 10 vials | — | AP | FDA listed | — |
| Bivalirudin 250 mg 52958-0034-01 | Hainan | 10 vials | — | AP | FDA listed | — |
| Bivalirudin 250 mg 55111-0652-37 | Dr. | 10 vials | — | AP | FDA listed | — |
| Bivalirudin 250 mg 55150-0210-10 | Eugia | 10 vials | — | — | FDA listed | — |
| Bivalirudin 250 mg 63323-0562-15 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Bivalirudin 250 mg/5mL 67457-0256-10 | Mylan | 10 vials | — | AP | FDA listed | — |
| bivalirudin 250 mg 70436-0025-80 | Slate | 1 injection | — | AP | FDA listed | — |
| Bivalirudin 250 mg/5mL 71288-0427-11 | Meitheal | 10 vials | — | AP | FDA listed | — |
| bivalirudin 250 mgthis 72572-0035-10 | Civica, | 10 vials | — | AP | FDA listed | — |
| Bivalirudin 250 mg 83634-0400-10 | Avenacy, | 10 vials | — | AP | FDA listed | — |
| Bivalirudin 250 mg 70511-0142-50 | MAIA | 1 vial | — | — | FDA listed | — |
| Bivalirudin 250 mg 42023-0622-01 | Par | 1 vial | — | — | FDA listed | — |
| bivalirudin 250 mg 00781-3158-95 | Sandoz | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7582727 ↗ | Drug product | — | Jul 27, 2028 |
| US 7598343 ↗ | Drug product | — | Jul 27, 2028 |
| US 7582727*PED ↗ | Drug product | — | Jan 27, 2029 |
| US 7598343*PED ↗ | Drug product | — | Jan 27, 2029 |
Is there a generic version of BIVALIRUDIN 250 MG VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72572-0035-10 You're viewing this | 10 VIAL, SINGLE-USE in 1 CARTON (72572-035-10) / 1 INJECTION, POWDER, LYOPHILIZED, FOR SOLUTION in 1 VIAL, SINGLE-USE (72572-035-01) | 2020-12-21 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Bivalirudin for injection is indicated for use as an anticoagulant for use in patients undergoing percutaneous coronary intervention (PCI) including patients with heparin-induced thrombocytopenia and heparin-induced thrombocytopenia and thrombosis syndrome. Bivalirudin for injection is a direct thrombin inhibitor indicated for use as an anticoagulant in patients undergoing percutaneous coronary intervention (PCI) including patients with heparin-induced thrombocytopenia (HIT) or heparin-induced thrombocytopenia and thrombosis syndrome (HITTS).( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • The recommended dosage is a 0.75 mg/kg intravenous bolus dose followed immediately by a 1.75 mg/kg/h intravenous infusion for the duration of the procedure. Five minutes after the bolus dose has been administered, an activated clotting time (ACT) should be performed and an additional bolus dose of 0.3 mg/kg should be given if needed. • Extending duration of infusion post-procedure up to 4 hours should be considered in patients with ST segment elevation MI (STEMI). ( 2.1 )
2.1Recommended Dosage Bivalirudin has been studied only in patients receiving concomitant aspirin. The recommended dose of bivalirudin is an intravenous bolus dose of 0.75 mg/kg, followed immediately by an infusion of 1.75 mg/kg/h for the duration of the procedure. Five minutes after the bolus dose has been administered, an activated clotting time (ACT) should be performed and an additional bolus of 0.3 mg/kg should be given if needed.
Extended duration of infusion following PCI at 1.75 mg/kg/h for up to 4 hours post-procedure should be considered in patients with ST segment elevation MI (STEMI).
2.2Dose Adjustment in Renal Impairment Bolus Dose No reduction in the bolus dose is needed for any degree of renal impairment. Maintenance Infusion In patients with creatinine clearance less than 30mL/min (by Cockcroft Gault equation), reduce the infusion rate to 1 mg/kg/h. Monitor anticoagulant status in patients with renal impairment.
In patients on hemodialysis, reduce the infusion rate to 0.25 mg/kg/h [see Use in Specific Populations ( 8.6 ) , Clinical Pharmacology ( 12.3 )] .
2.3Instructions for Preparation and Administration Bivalirudin is intended for intravenous bolus injection and continuous infusion after reconstitution and dilution. Preparation Instructions for Bolus Injection and Continuous Infusion • To each 250 mg vial, add 5 mL of Sterile Water for Injection, USP. • Gently swirl until all material is dissolved. • Withdraw and discard 5 mL from a 50 mL infusion bag containing 5% Dextrose in Water or 0.9% Sodium Chloride for Injection. • Add the contents of the reconstituted vial to the infusion bag containing 5% Dextrose in Water or 0.9% Sodium Chloride for Injection to yield a final concentration of 5 mg/mL (e.g., 1 vial in 50 mL; 2 vials in 100 mL; 5 vials in 250 mL). • Adjust the dose to be administered according to the patient’s weight (see Table 1 ).
Table 1: Dosing Table Weight (kg) Using 5 mg/mL Concentration Bolus 0.75 mg/kg (mL) Infusion 1.75 mg/kg/h (mL/h) 43-47 7 16 48-52 7.5 17.5 53-57 8 19 58-62 9 21 63-67 10 23 68-72 10.5 24.5 73-77 11 26 78-82 12 28 83-87 13 30 88-92 13.5 31.5 93-97 14 33 98-102 15 35 103-107 16 37 108-112 16.5 38.5 113-117 17 40 118-122 18 42 123-127 19 44 128-132 19.5 45.5 133-137 20 47 138-142 21 49 143-147 22 51 148-152 22.5
52.5Drug Compatibilities No incompatibilities have been observed with administration sets. Do not administer the drugs listed in Table 2 in the same intravenous line with Bivalirudin. Table 2: Drugs Not for Administration in the Same Intravenous Line with Bivalirudin Alteplase Amiodarone HCl Amphotericin B Chlorpromazine HCl Diazepam Dobutamine Prochlorperazine Edisylate Reteplase Streptokinase Vancomycin HCl Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration.
Preparations of bivalirudin containing particulate matter should not be used. Reconstituted material will be a clear to slightly opalescent, colorless to slightly yellow solution.
2.4Storage after Reconstitution Do not freeze reconstituted or diluted Bivalirudin. Reconstituted material may be stored at 2° to 8°C for up to 24 hours. Diluted bivalirudin with a concentration of between 0.5 mg/mL and 5 mg/mL is stable at room temperature for up to 24 hours. Discard any unused portion of reconstituted solution remaining in the vial.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 250 mg of bivalirudin as a lyophilized powder in a single dose vial for reconstitution. Each vial contains 250 mg of bivalirudin equivalent to an average of 275 mg bivalirudin trifluoroacetate*. *The range of bivalirudin trifluoroacetate is 270 to 280 mg based on a range of trifluoroacetic acid composition of 1.7 to 2.6 equivalents . For injection: 250 mg of bivalirudin as a lyophilized powder in a single dose vial for reconstitution.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Bivalirudin is contraindicated in patients with: • Active major bleeding; • Hypersensitivity (e.g., anaphylaxis) to bivalirudin or its components [see Adverse Reactions (6.1) ] . • Active major bleeding ( 4 ) • Hypersensitivity to bivalirudin or its components ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Bleeding Events: Bivalirudin increases the risk of bleeding. ( 5.1 , 6.1 , 12.2 ) • Acute Stent Thrombosis: Increased incidence of acute stent thrombosis in STEMI patients undergoing primary PCI. ( 2.1 , 5.2 ) • Thrombotic Risk with Coronary Artery Brachytherapy: An increased risk of thrombus formation, including fatal outcomes, in gamma brachytherapy. ( 5.3 )
5.1Bleeding Events Bivalirudin increases the risk of bleeding [see Adverse Reactions ( 6.1 )] . An unexplained fall in blood pressure or hematocrit should lead to serious consideration of a hemorrhagic event and cessation of bivalirudin administration. Monitor patients receiving bivalirudin for signs and symptoms of bleeding. Monitor patients with disease states associated with an increased risk of bleeding more frequently for bleeding.
5.2Acute Stent Thrombosis in Patients with STEMI Undergoing PCI Acute stent thrombosis (AST) (less than 4 hours) has been observed at a greater frequency in bivalirudin treated patients (1.2%, 36/2889) compared to heparin treated patients (0.2%, 6/2911) with STEMI undergoing primary PCI. Among patients who experienced an AST, one fatality (0.03%) occurred in a bivalirudin treated patient and one fatality (0.03%) in a heparin treated patient. These patients have been managed by Target Vessel Revascularization (TVR).
Patients should remain for at least 24 hours in a facility capable of managing ischemic complications and should be carefully monitored following primary PCI for signs and symptoms consistent with myocardial ischemia.
5.3Thrombotic Risk with Coronary Artery Brachytherapy An increased risk of thrombus formation, including fatal outcomes, has been associated with the use of bivalirudin in gamma brachytherapy. If a decision is made to use bivalirudin during brachytherapy procedures, maintain meticulous catheter technique, with frequent aspiration and flushing, paying special attention to minimizing conditions of stasis within the catheter or vessels [see Adverse Reactions (6.3) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reaction (>2%) was bleeding. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc. at 1-800-525-8747 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In the BAT trials, 79 of the 2161 (3.7%) patients undergoing PCI for treatment of unstable angina and randomized to bivalirudin experienced major bleeding events, which consisted of intracranial bleeding, retroperitoneal bleeding, and clinically overt bleeding with a decrease in hemoglobin greater than 3 g/dL or leading to a transfusion of greater than 2 units of blood.
6.2Immunogenicity As with all peptides, there is potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease.
For these reasons, comparison of the incidence of antibodies to bivalirudin in the studies described below with the incidence of antibodies in other studies or to other products may be misleading. In in vitro studies, bivalirudin exhibited no platelet aggregation response against sera from patients with a history of HIT/HITTS. Among 494 subjects who received bivalirudin in clinical trials and were tested for antibodies, 2 subjects had treatment-emergent positive bivalirudin antibody tests.
Neither subject demonstrated clinical evidence of allergic or anaphylactic reactions and repeat testing was not performed. Nine additional patients who had initial positive tests were negative on repeat testing.
6.3Postmarketing Experience Because postmarketing adverse reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The following adverse reactions have been identified during post approval use of bivalirudin: fatal bleeding; hypersensitivity and allergic reactions including reports of anaphylaxis; lack of anticoagulant effect; thrombus formation during PCI with and without intracoronary brachytherapy, including reports of fatal outcomes; pulmonary hemorrhage; cardiac tamponade; and INR increased.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In clinical trials in patients undergoing PCI/ percutaneous transluminal coronary angioplasty (PTCA), coadministration of bivalirudin with heparin, warfarin, thrombolytics, or GPIs was associated with increased risks of major bleeding events compared to patients not receiving these concomitant medications. Heparin, warfarin, thrombolytics, or GPIs: Increased major bleeding risk with concomitant use. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Geriatric patients: Increased bleeding risk possible. ( 8.5 ) • Renal impairment: Reduce infusion dose and monitor ACT. ( 2.2 , 8.6 )
8.1Pregnancy Risk Summary There are no data available on use of bivalirudin in pregnant women to inform a drug-associated risk of adverse developmental outcomes. Reproduction studies in rats and rabbits administered subcutaneously doses up to 1.6 times and 3.2 times the maximum recommended human dose (MRHD) of 15 mg/kg/day based on body surface area (BSA) during organogenesis, respectively, revealed no evidence of fetal harm. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproductive studies have been performed in rats at subcutaneous doses up to 150 mg/kg/day (1.6 times the maximum recommended human dose based on body surface area) and rabbits at subcutaneous doses up to 150 mg/kg/day (3.2 times the maximum recommended human dose based on body surface area).
These studies revealed no harm to the fetus attributable to bivalirudin. At 500 mg/kg/day (equivalent to 5.4 times the maximum recommended human dose based on body surface area) subcutaneously, litter sizes and live fetuses in rats were reduced. Fetal skeletal variations were also noted.
Some of these changes could be attributed to maternal toxicity observed at high doses. There is no study covering the perinatal period because of the potential complications of drug-induced hemorrhage during delivery.
8.2Lactation Risk Summary It is not known whether bivalirudin is present in human milk. No data are available on the effects on the breastfed child or on milk production. Bivalirudin was administered to lactating rats in reproduction studies (see Data) .
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for bivalirudin and any potential adverse effects on the breastfed child from bivalirudin or from the underlying maternal condition. Data Animal Data Reproduction studies conducted in lactating female rats dosed subcutaneously daily with bivalirudin at doses up to 150 mg/kg/day (1.6 times the maximum recommended human dose, based on body surface area) from day 2 through day 20 of lactation revealed no adverse developmental outcomes to the pups.
8.4Pediatric Use The safety and effectiveness of bivalirudin in pediatric patients have not been established.
8.5Geriatric Use In studies of patients undergoing PCI, 44% were ≥65 years of age and 12% of patients were ≥75 years old. Elderly patients experienced more bleeding events than younger patients.
8.6Renal Impairment The disposition of bivalirudin was studied in PTCA patients with mild, moderate and severe renal impairment. The clearance of bivalirudin was reduced approximately 21% in patients with moderate and severe renal impairment and was reduced approximately 70% in dialysis-dependent patients [see Clinical Pharmacology (12.3) ] . Reduce the infusion dose of bivalirudin and monitor the anticoagulant status more frequently in patients with renal impairment creatinine clearance less than 30 mL/min (by Cockcroft Gault equation) [see Dosage and Administration (2.2) ] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no data available on use of bivalirudin in pregnant women to inform a drug-associated risk of adverse developmental outcomes. Reproduction studies in rats and rabbits administered subcutaneously doses up to 1.6 times and 3.2 times the maximum recommended human dose (MRHD) of 15 mg/kg/day based on body surface area (BSA) during organogenesis, respectively, revealed no evidence of fetal harm. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproductive studies have been performed in rats at subcutaneous doses up to 150 mg/kg/day (1.6 times the maximum recommended human dose based on body surface area) and rabbits at subcutaneous doses up to 150 mg/kg/day (3.2 times the maximum recommended human dose based on body surface area).
These studies revealed no harm to the fetus attributable to bivalirudin. At 500 mg/kg/day (equivalent to 5.4 times the maximum recommended human dose based on body surface area) subcutaneously, litter sizes and live fetuses in rats were reduced. Fetal skeletal variations were also noted.
Some of these changes could be attributed to maternal toxicity observed at high doses. There is no study covering the perinatal period because of the potential complications of drug-induced hemorrhage during delivery.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of bivalirudin in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In studies of patients undergoing PCI, 44% were ≥65 years of age and 12% of patients were ≥75 years old. Elderly patients experienced more bleeding events than younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Cases of overdose of up to 10 times the recommended bolus or continuous infusion dose of bivalirudin have been reported in clinical trials and in postmarketing reports. A number of the reported overdoses were due to failure to adjust the infusion dose of bivalirudin in persons with renal dysfunction including persons on hemodialysis [see Dosage and Administration (2.2) ] . Bleeding, as well as deaths due to hemorrhage, have been observed in some reports of overdose.
In cases of suspected overdosage, discontinue bivalirudin immediately and monitor the patient closely for signs of bleeding. There is no known antidote to bivalirudin. Bivalirudin is hemodialyzable [see Clinical Pharmacology (12.3) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bivalirudin directly inhibits thrombin by specifically binding both to the catalytic site and to the anion-binding exosite of circulating and clot-bound thrombin. Thrombin is a serine proteinase that plays a central role in the thrombotic process, acting to cleave fibrinogen into fibrin monomers and to activate Factor XIII to Factor XIIIa, allowing fibrin to develop a covalently cross-linked framework, which stabilizes the thrombus; thrombin also activates Factors V and VIII, promoting further thrombin generation, and activates platelets, stimulating aggregation and granule release.
The binding of bivalirudin to thrombin is reversible as thrombin slowly cleaves the bivalirudin-Arg 3 -Pro 4 bond, resulting in recovery of thrombin active site functions. In in vitro studies, bivalirudin inhibited both soluble (free) and clot-bound thrombin, was not neutralized by products of the platelet release reaction, and prolonged the activated partial thromboplastin time (aPTT), thrombin time (TT), and prothrombin time (PT) of normal human plasma in a concentration-dependent manner. The clinical relevance of these findings is unknown.
12.2Pharmacodynamics In healthy volunteers and patients (with ≥70% vessel occlusion undergoing routine PTCA), bivalirudin exhibited dose- and concentration-dependent anticoagulant activity as evidenced by prolongation of the ACT, aPTT, PT, and TT. Intravenous administration of bivalirudin produces an immediate anticoagulant effect. Coagulation times return to baseline approximately 1 hour following cessation of bivalirudin administration.
Bivalirudin also increases INR. Therefore, INR measurements made in bivalirudin treated patients may not be useful for determining the appropriate dose of warfarin. In 291 patients with ≥70% vessel occlusion undergoing routine PTCA, a positive correlation was observed between the dose of bivalirudin and the proportion of patients achieving ACT values of 300 sec or 350 sec.
At a bivalirudin dose of 1 mg/kg IV bolus plus 2.5 mg/kg/h IV infusion for 4 hours, followed by 0.2 mg/kg/h, all patients reached maximal ACT values greater than 300 sec.
12.3Pharmacokinetics Bivalirudin exhibits linear pharmacokinetics following IV administration to patients undergoing PTCA. In these patients, a mean steady state bivalirudin concentration of 12.3 ± 1.7 mcg/mL is achieved following an IV bolus of 1 mg/kg and a 4-hour 2.5 mg/kg/h IV infusion. Distribution Bivalirudin does not bind to plasma proteins (other than thrombin) or to red blood cells.
Elimination Bivalirudin has a half-life of 25 minutes in PTCA patients with normal renal function. The total body clearance of bivalirudin in PTCA patients with normal renal function is 3.4 mL/min/kg. Metabolism Bivalirudin is metabolized by proteolytic cleavage.
Excretion Bivalirudin undergoes glomerular filtration. Tubular secretion and tubular reabsorption are also implicated in the excretion of bivalirudin, although the extent is unknown. Specific Populations Patients with Renal Impairment Total body clearance was similar for PTCA patients with normal renal function and with mild renal impairment.
Clearance was reduced by 21% in patients with moderate and severe renal impairment with a half-life of 34 and 57 minutes, respectively. In dialysis patients, clearance was reduced by 70%, with a half-life of 3.5 hours. Approximately 25% bivalirudin is cleared by hemodialysis.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bivalirudin directly inhibits thrombin by specifically binding both to the catalytic site and to the anion-binding exosite of circulating and clot-bound thrombin. Thrombin is a serine proteinase that plays a central role in the thrombotic process, acting to cleave fibrinogen into fibrin monomers and to activate Factor XIII to Factor XIIIa, allowing fibrin to develop a covalently cross-linked framework, which stabilizes the thrombus; thrombin also activates Factors V and VIII, promoting further thrombin generation, and activates platelets, stimulating aggregation and granule release.
The binding of bivalirudin to thrombin is reversible as thrombin slowly cleaves the bivalirudin-Arg 3 -Pro 4 bond, resulting in recovery of thrombin active site functions. In in vitro studies, bivalirudin inhibited both soluble (free) and clot-bound thrombin, was not neutralized by products of the platelet release reaction, and prolonged the activated partial thromboplastin time (aPTT), thrombin time (TT), and prothrombin time (PT) of normal human plasma in a concentration-dependent manner. The clinical relevance of these findings is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Bivalirudin for injection is supplied as a sterile, lyophilized powder in single-dose, glass vials. Each vial contains 250 mg of bivalirudin equivalent to an average of 275 mg of bivalirudin trifluoroacetate*. *The range of bivalirudin trifluoroacetate is 270 to 280 mg based on a range of trifluoroacetic acid composition of 1.7 to 2.6 equivalents. NDC 72572-035-10 – Package of 10 – 250 mg Single-Dose Vials
16.2Storage Store bivalirudin for injection dosage units at 20° to 25°C (68° to 77°F); excursions to 15° to 30°C permitted [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Bivalirudin for injection contains bivalirudin, which is a specific and reversible direct thrombin inhibitor. Bivalirudin is a synthetic, 20 amino acid peptide, with the chemical name of D-phenylalanyl-L-prolyl-L-arginyl-L-prolyl-glycyl-glycyl-glycyl-glycyl-L-asparagyl-glycyl-L-aspartyl-L-phenylalanyl-L-glutamyl-L-glutamyl-L-isoleucyl-L-prolyl-L-glutamyl-L-glutamyl-L-tyrosyl-L-leucine. The active pharmaceutical ingredient is in the form of bivalirudin trifluoroacetate as a white to off-white powder.
The chemical name for bivalirudin trifluoroacetate is D-phenylalanyl-L-prolyl-L-arginyl-L-prolyl-glycyl-glycyl-glycyl-glycyl-L-asparagyl-glycyl-L-aspartyl-L-phenylalanyl-L-glutamyl-L-glutamyl-L-isoleucyl-L-prolyl-L-glutamyl-L-glutamyl-L-tyrosyl-L-leucine trifluoroacetate ( Figure 1 ). The molecular weight of bivalirudin is 2180 daltons (anhydrous free base peptide). Figure 1: Structure Formula for Bivalirudin Trifluoroacetate Bivalirudin for injection is supplied as a sterile white lyophilized cake, in single-dose vials.
Each vial contains 250 mg bivalirudin, equivalent to an average of 275 mg of bivalirudin trifluoroacetate * , 125 mg mannitol, and sodium hydroxide to adjust the pH to 5-6 (equivalent of approximately 12.5 mg sodium). When reconstituted with Sterile Water for Injection, the product yields a clear to opalescent, colorless to slightly yellow solution, pH 5-6. * The range of bivalirudin trifluoroacetate is 270 mg to 280 mg based on a range of trifluoroacetic acid composition of 1.7 to 2.6 equivalents. chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to watch carefully for any signs of bleeding or bruising and to report these to their health care provider when they occur. Distributed by: Civica, Inc., Lehi, Utah 84043 Manufactured by: Patheon Italia, S.p.A. Via G.B. Stucchi, 110 I-20052 Monza (MB), Italy U.S. Patents 7,598,343; 7,582,727