
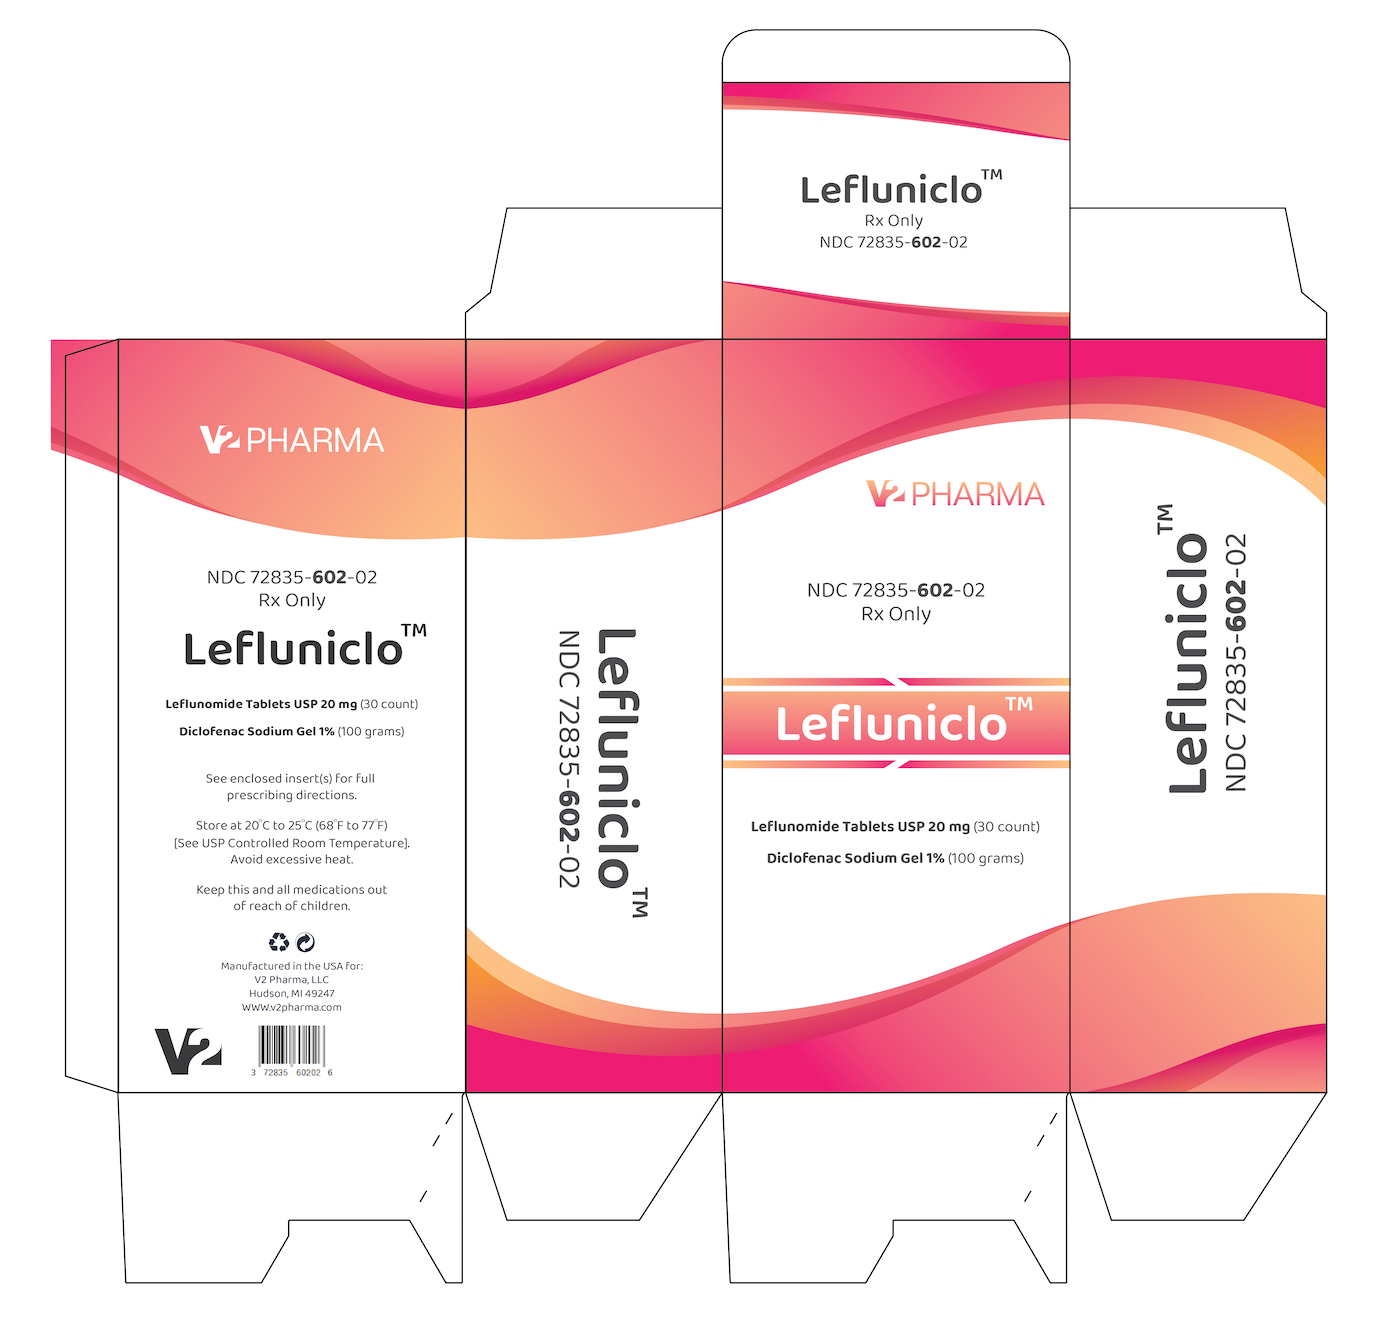
Lefluniclo Leflunomide and Diclofenac Sodium Gel Kit — NDC 72835-602-02 (Billing 72835-0602-02)
This is a package of Lefluniclo Leflunomide and Diclofenac Sodium Gel Kit from V2 Pharma, LLC, marketed since Jan 2023 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 72835-602-02 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 72835 labeler · 602 product · 02 package
- Package marketed since
- Jan 11, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 7283560202 6
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 084619
- GCN: 53964
- HICL (First Databank): 048836
- AHFS class code: 90:24.00.00
- RxCUI (RxNorm): 205285
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Antirheumatic Agent class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
This is a kit product containing leflunomide and diclofenac sodium gel. Leflunomide is a medication that functions as an immunosuppressant typically used to manage inflammatory joint conditions. Diclofenac sodium is a nonsteroidal anti-inflammatory drug (NSAID) commonly applied as a topical gel to reduce localized pain and inflammation. This product is marketed without an approved FDA application.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72835-0602-02 You're viewing this Main listing | 1 KIT in 1 CARTON * 1 BOTTLE in 1 CARTON / 30 TABLET, FILM COATED in 1 BOTTLE * 100 g in 1 TUBE | 2023-01-11 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lefluniclothis 72835-0602-02 | V2 | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
This is label-wide narrative text, not a normalized exact-product ingredient list. A label can cover multiple strengths or packages.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from V2 Pharma, LLC labeler code 72835
- Lidovyx Lidocaine 4% 40 mg/g Gel NDC 72835-447-01
- LMR Plus Lidocaine Kit NDC 72835-501-02
- Elemar Patch Lidocaine Kit NDC 72835-502-02
- Crysalo Methyl Salicylate, Menthol 11 g/100mL; 5 g/100mL Liquid NDC 72835-511-01
- Cobalefol VITAMIN 90 mg; 20 ug; 10.5 mg; 1.4 mg; 5'-PHOSPHATE 1.6 mg; 16.3 mg; 2.5 mg; 1700 ug; 10 ug Capsule NDC 72835-550-01
- Relivyx Plus Lidocaine Kit NDC 72835-555-02
- Matervia ascorbic acid, cholecalciferol, thiamine, pyridoxal-5-phosphate, folic acid, methylcobalamin, calcium citrate, iron, iodine 125 mg; 20 ug; 1.4 mg; 5-PHOSPHATE 2.5 mg; 1000 ug; 1000 ug; 200 mg; 13 mg; 150 ug Capsule NDC 72835-660-01
- Inflatherm Diclofenac Sodium and Menthol / Camphor Gel Kit NDC 72835-701-02
- Dermavyx Triamcinolone Acetonide Cream 0.1%, Transparent Dressing Kit NDC 72835-777-02
- Trionex Calcipotriene Cream, 0.005% and Transparent Dressing Kit NDC 72835-902-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYO-FETAL TOXICITY and HEPATOTOXICITY Embryo-Fetal Toxicity Leflunomide tablet is contraindicated for use in pregnant women because of the potential for fetal harm. Teratogenicity and embryo-lethality occurred in animals administered leflunomide at doses lower than the human exposure level. Exclude pregnancy before the start of treatment with leflunomide tablets in females of reproductive potential.
Advise females of reproductive potential to use effective contraception during leflunomide tablets treatment and during an accelerated drug elimination procedure after leflunomide tablets treatment. Stop leflunomide tablets and use an accelerated drug elimination procedure if the patient becomes pregnant. [see Contraindications (4), Warnings and Precautions (5.1, 5.3), Use in Special Populations (8.1, 8.3)], and Clinical Pharmacology (12.3)] Hepatotoxicity Severe liver injury, including fatal liver failure, has been reported in patients treated with leflunomide tablets.
Leflunomide tablet is contraindicated in patients with severe hepatic impairment. Concomitant use of leflunomide tablets with other potentially hepatotoxic drugs may increase the risk of liver injury. Patients with pre-existing acute or chronic liver disease, or those with serum alanine aminotransferase (ALT) >2xULN before initiating treatment, are at increased risk and should not be treated with leflunomide tablets.
Monitor ALT levels at least monthly for six months after starting leflunomide tablets, and thereafter every 6 to 8 weeks. If leflunomide-induced liver injury is suspected, stop leflunomide tablets treatment, start an accelerated drug elimination procedure, and monitor liver tests weekly until normalized. [see Contraindications (4), Warnings and Precautions (5.2, 5.3), Use in Special Populations (8.6)]
🎯 Indications and Usage ▾
INDICATION AND USAGE For the treatment of adults with active rheumatoid arthritis (RA). For the temporary relief of arthritis pain.
1 INDICATIONS AND USAGE Leflunomide tablets USP are indicated for the treatment of adults with active rheumatoid arthritis (RA).
Uses • for the temporary relief of arthritis pain ONLY in the following areas: • hand, wrist, elbow (upper body areas) • foot, ankle, knee (lower body areas) • this product may take up to 7 days to work for arthritis pain; it is not for immediate relief. If no pain relief in 7 days, stop use.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION SEE PRESCRIBING DIRECTIONS FOR EACH COMPONENT CONTAINED IN THIS KIT Take one leflunimide 20 mg once daily. The maximum recommended daily dosage is 20 mg once per day. Apply 2-4 grams of diclofenac 1% gel to treated area as needed up to 4 times per day. Do not usea on more than 2 body areas at the same time.
"These highlights do not include all the information needed to use" "see full prescribing information for" and "Initial U.S. Approval" Loading dosage for patients at low risk for leflunomide tablets -associated hepatotoxicity and leflunomide tablets-associated myelosuppression: 100 mg daily for 3 days (2.1) Maintenance dosage: 20 mg daily. (2.1) Maximum recommended daily dosage: 20 mg once daily.
(2.1) If 20 mg once daily is not tolerated, may decrease dosage to 10 mg once daily. (2.1) Screen patients for active and latent tuberculosis, pregnancy test (females), blood pressure, and laboratory tests before starting leflunomide tablets. (2.2)
2.1Recommended Dosage The recommended dosage of leflunomide tablets USP is 20 mg once daily. Treatment may be initiated with or without a loading dose, depending upon the patient's risk of leflunomide tablets USP -associated hepatotoxicity and leflunomide tablets -associated myelosuppression. The loading dosage provides steady-state concentrations more rapidly.
For patients who are at low risk for leflunomide tablets -associated hepatotoxicity and leflunomide tablets USP - associated myelosuppression the recommended leflunomide tablets USP loading dosage is 100 mg once daily for 3 days. Subsequently administer 20 mg once daily. For patients at high risk for leflunomide tablets USP -associated hepatotoxicity (e.g., those taking concomitant methotrexate) or leflunomide tablets -associated myelosuppression (e.g., patients taking concomitant immunosuppressants), the recommended leflunomide tablets USP dosage is 20 mg once daily without a loading dose [see Warnings and Precautions (5.2,5.4)].
The maximum recommended daily dosage is 20 mg once per day. Consider dosage reduction to 10 mg once daily for patients who are not able to tolerate 20 mg daily (i.e., for patients who experience any adverse events listed in Table 1). Monitor patients carefully after dosage reduction and after stopping therapy with leflunomide tablets, since the active metabolite of leflunomide, teriflunomide, is slowly eliminated from the plasma [see Clinical Pharmacology (12.3)].
After stopping leflunomide tablets treatment, an accelerated drug elimination procedure is recommended to reduce the plasma concentrations of the active metabolite, teriflunomide [see Warnings and Precautions (5.3)]. Without use of an accelerated drug elimination procedure, it may take up to 2 years to reach undetectable plasma teriflunomide concentrations after stopping leflunomide tablets [see Clinical Pharmacology (12.3)].
2.2Evaluation and Testing Prior to Starting leflunomide tablets USP Prior to starting leflunomide tablets treatment the following evaluations and tests are recommended:
Directions Use up to 21 days unless directed by your doctor Not for strains, sprains, bruises or sports injuries. This product has not been shown to work for these types of injuries. Daily Per Dose For your arthritis pain: • Use 4 times per day every day • Do not use on more than 2 body areas at the same time Use ENCLOSED DOSING CARD to measure a dose • For each upper body area (hand, wrist, or elbow) – Squeeze out 2.25 inches (2 grams) • For each lower body area (foot, ankle or knee) –Squeeze out 4.5 inches (4 grams) Read the enclosed User Guide for complete instructions: • use only as directed • do not use more than directed or for longer than directed • apply only to clean, dry skin that does not have any cuts, open wounds, infections or rashes • do not apply in same area as any other product • do not apply with external heat such as heating pad • do not apply a bandage over the treated area • store ENCLOSED DOSING CARD with… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 20 mg, supplied as Yellow colour, film coated, round shaped tablet, debossed with "L" on one side and "A5" on the other side
⛔ Contraindications ▾
CONTRADICTIONS Do not use if known hypersensitivity to any of the listed ingredients of any of the components included on the kit.
4 CONTRAINDICATIONS Leflunomide tablet is contraindicated in: Pregnant women. Leflunomide tablets may cause fetal harm. If a woman becomes pregnant while taking this drug, stop leflunomide tablets, apprise the patient of the potential hazard to the fetus, and begin a drug elimination procedure [see Warnings and Precautions (5.1 and 5.3) and Use in Specific Populations (8.1)].
Patients with severe hepatic impairment [see Warnings and Precautions (5.2)]. Patients with known hypersensitivity to leflunomide or any of the other components of leflunomide tablets. Known reactions include anaphylaxis [see Adverse Reactions (6.1)].
Patients being treated with teriflunomide [see Drug Interactions (7)]. Pregnancy. (4, 5.1,8.1) Severe hepatic impairment.
(4,5.2) Hypersensitivity to leflunomide tablets or any of its inactive components. (4) Current teriflunomide treatment. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS After stopping leflunomide tablets, it is recommended that an accelerated drug elimination procedure be used to reduce the plasma concentrations of the active metabolite, teriflunomide. (5.3) Severe infections (including sepsis), pancytopenia, agranulocytosis and thrombocytopenia: Stop leflunomide tablets and use accelerated elimination procedure. Do not start leflunomide tablets in patients with active infection.
Monitor CBCs during treatment with leflunomide tablets (5.4) Stevens-Johnson syndrome and toxic epidermal necrolysis: Stop leflunomide tablets and use accelerated elimination procedure. (5.5) Peripheral neuropathy: If patient develops symptoms consistent with peripheral neuropathy, evaluate patient and consider discontinuing leflunomide tablets. (5.7) Interstitial lung disease: May be fatal.
New onset or worsening symptoms may necessitate discontinuation of leflunomide tablets and initiation of accelerated elimination procedure. (5.8) Increased blood pressure: Monitor and treat. (5.10)
5.1Embryo-Fetal Toxicity Leflunomide tablets may cause fetal harm when administered to a pregnant woman. Teratogenicity and embryo-lethality occurred in animal reproduction studies with leflunomide at doses lower than the human exposure level [see Use in Specific Populations (8.1)]. Leflunomide tablet is contraindicated for use in pregnant women [see Contraindications (4)].
Exclude pregnancy before starting treatment with leflunomide tablets in females of reproductive potential [see Dosage and Administration (2.2)]. Advise females of reproductive potential to use effective contraception during leflunomide tablets treatment and during an accelerated drug elimination procedure after leflunomide tablets treatment [see Use in Specific Populations (8.3)]. If a woman becomes pregnant while taking leflunomide tablets, stop treatment with leflunomide tablets, apprise the patient of the potential risk to a fetus, and perform an accelerated drug elimination procedure to achieve non-detectable plasma concentrations of teriflunomide, the active metabolite of leflunomide [see Warnings and Precautions (5.3)].
Upon discontinuing leflunomide tablets, it is recommended that all females of reproductive potential undergo an accelerated drug elimination procedure. Women receiving leflunomide tablets treatment who wish to become pregnant must discontinue leflunomide tablets and undergo an accelerated drug elimination procedure, which includes verification that plasma concentrations of the active metabolite of leflunomide, teriflunomide, are less than 0.02 mg/L (0.02 mcg/mL). Based on animal data, human plasma concentrations of teriflunomide of less than 0.02 mg/L (0.02 mcg/mL) are expected to have minimal embryo-fetal risk [see Contraindications (4), Warnings and Precautions (5.3), and Use in Specific Populations (8.1)].
5.2Hepatotoxicity Severe liver injury, including fatal liver failure, has been reported in some patients treated with leflunomide tablets. Patients with pre-existing acute or chronic liver disease, or those with serum alanine aminotransferase (ALT) of greater than twice the upper limits of normal (>2xULN) before initiating treatment, should not be treated with leflunomide tablets. Use caution when leflunomide tablets are given with other potentially hepatotoxic drugs.
Monitoring of ALT levels is recommended at least monthly for six months after starting leflunomide tablets, and thereafter every 6 to 8 weeks. If ALT elevation > 3 fold ULN occurs, interrupt leflunomide tablets therapy and investigate the cause. If likely leflunomide tablets - induced, perform the accelerated drug elimination procedure and monitor liver tests weekly until normalized [see Warnings and Precautions (5.3)].
If leflunomide tablets -induced liver injury is unlikely because some other cause has been found, resumption of leflunomide tablets therapy may be considered. If leflunomide tablets and methotrexate are given concomitantly, follow… [Excerpted — this section continues on DailyMed.]
⚠️ Warnings ▾
Warnings For external use only Allergy alert: Diclofenac may cause a severe allergic reaction, especially in people allergic to aspirin. Symptoms may include: • hives • asthma (wheezing) • skin reddening • blisters • facial swelling • shock • rash If an allergic reaction occurs, stop use and seek medical help right away. Liver warning: This product contains diclofenac.
Liver damage may occur if you apply • more or for a longer time than directed • when using other drugs containing diclofenac Stomach bleeding warning: This product contains an NSAID, which may cause severe stomach bleeding. The chance is small but higher if you • are age 60 or older • have had stomach ulcers or bleeding problems • take a blood thinning (anticoagulant) or steroid drug • take other drugs containing prescription or nonprescription NSAIDs (aspirin, ibuprofen, naproxen, or others) • have 3 or more alcoholic drinks every day while using this product • apply more or for longer than directed Heart attack and stroke warning: NSAIDs, except aspirin, increase the risk of heart attack, heart failure, and stroke.
These can be fatal. The risk is higher if you use more than directed or for longer than directed. Do not use • if you have ever had an allergic reaction to any other pain reliever or to a fever reducer • for strains, sprains, bruises or sports injuries.
This product has not been shown to work for these types of injuries. • right before or after heart surgery • on more than 2 body areas at the same time • in the eyes, nose or mouth Ask a doctor before use if • you have problems or serious side effects from taking pain relievers or fever reducers • stomach bleeding warning applies to you • you have a history of stomach problems, such as heartburn • you have high blood pressure, heart disease, liver cirrhosis, kidney disease, asthma, or had a stroke • you are taking a diuretic • you are under age 18 years.
It is not known if this drug works or is safe in children under age 18 years. Ask a doctor or pharmacist before use if you are • under a doctor’s care for any serious condition • taking any other drug When using this product • avoid contact with eyes, nose, or mouth • if eye contact occurs, rinse thoroughly with water Stop use and ask a doctor if • pain gets worse or lasts more than 21 days • redness or swelling is present in the painful area • fever occurs • skin irritation occurs • any new symptoms appear. These could be signs of a serious condition. • you experience any of the following signs of stomach bleeding: • feel faint • have bloody or black stools • vomit blood • have stomach pain that does not get better • you have symptoms of heart problems or stroke: • chest pain • trouble breathing • leg swelling • weakness in one part or side of body • slurred speech If pregnant or breast-feeding, ask a health professional before use.
It is especially important not to use this product during the last 3 months of pregnancy unless definitely directed to do so by a doctor because it may cause problems in the unborn child or complications during delivery. Keep out of reach of children. If swallowed, get medical help or contact a Poison Control Center right away (1-800-222-1222).
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Hepatotoxicity [see Warnings and Precautions (5.2)] Immunosuppression [see Warnings and Precautions (5.4)] Bone marrow suppression [see Warnings and Precautions (5.4)] Stevens-Johnson syndrome and toxic epidermal necrolysis [see Warnings and Precautions (5.5)] Peripheral neuropathy [see Warnings and Precautions (5.7 )] Interstitial lung disease [see Warnings and Precautions (5.8)] The most commonly reported adverse reactions (≥10%) regardless of relation to leflunomide tablets treatment were diarrhea, respiratory infection, nausea, headache, rash, abnormal liver enzymes, dyspepsia.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceutical Inc. at 1-800-399-2561 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. In clinical studies (Trials 1, 2, and 3), 1,865 patients were treated with leflunomide tablets administered as either monotherapy or in combination with methotrexate or sulfasalazine. Patients ranged in age from 19 to 85 years, with an overall median age of 58 years.
The mean duration of RA was 6 years ranging from 0 to 45 years. Elevation of Liver Enzymes Treatment with leflunomide tablets was associated with elevations of liver enzymes, primarily ALT and AST, in a significant number of patients; these effects were generally reversible. Most transaminase elevations were mild (≤ 2-fold ULN) and usually resolved while continuing treatment.
Marked elevations (>3-fold ULN) occurred infrequently and reversed with dose reduction or discontinuation of treatment. Table 1 shows liver enzyme elevations seen with monthly monitoring in clinical trials Trial 1 and Trial 2. It was notable that the absence of folate use in Trial 3 was associated with a considerably greater incidence of liver enzyme elevation on methotrexate.
In a 6 month study of 263 patients with persistent active rheumatoid arthritis despite methotrexate therapy, and with normal LFTs, leflunomide tablets was administered to a group of 130 patients starting at 10 mg per day and increased to 20 mg as needed. An increase in ALT greater than or equal to three times the ULN was observed in 3.8% of patients compared to 0.8% in 133 patients continued on methotrexate with placebo. Most Common Adverse Reactions The most common adverse reactions in leflunomide tablets -treated patients with RA include diarrhea, elevated liver enzymes (ALT and AST), alopecia and rash.
Table 2 displays the most common adverse reactions in the controlled studies in patients with RA at one year (≥ 5% in any leflunomide tablets treatment group). Adverse events during a second year of treatment with leflunomide tablets in clinical trials were consistent with those observed during the first year of treatment and occurred at a similar or lower incidence. Less Common Adverse Reactions In addition, in controlled clinical trials, the following adverse events in the leflunomide tablets treatment group occurred at a higher incidence than in the placebo group.
These adverse events were deemed possibly related to the study drug. Blood and Lymphatic System: leukocytosis, thrombocytopenia; Cardiovascular: chest pain, palpitation, thrombophlebitis of the leg, varicose vein; Eye: blurred vision, eye disorder, papilledema, retinal disorder, retinal hemorrhage; Gastrointestinal: alkaline phosphatase increased, anorexia, bilirubinemia, flatulence, gamma-GT increased, salivary gland enlarged, sore throat, vomiting, dry mouth; General Disorders: malaise; Immune System: anaphylactic reaction; Infection: abscess, flu syndrome, vaginal moniliasis; Nervous System: dizziness, headache, somnolence; Respiratory Syste… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Following oral administration, leflunomide is metabolized to an active metabolite, teriflunomide, which is responsible for essentially all of leflunomide's in vivo activity. Drug interaction studies have been conducted with both leflunomide and with its active metabolite, teriflunomide, where the metabolite was directly administered to the test subjects. Effect of potent CYP and transporter inducers Leflunomide is metabolized by CYP450 metabolizing enzymes.
Concomitant use of leflunomide tablets and rifampin, a potent inducer of CYP and transporters, increased the plasma concentration of teriflunomide by 40%. However, when co-administered with the metabolite, teriflunomide, rifampin did not affect its pharmacokinetics. No dosage adjustment is recommended for leflunomide tablets when coadministered with rifampin.
Because of the potential for leflunomide tablets concentrations to continue to increase with multiple dosing, caution should be used if patients are to be receiving both leflunomide tablets and rifampin [see Clinical Pharmacology (12.3)]. Effect on CYP2C8 substrates Teriflunomide is an inhibitor of CYP2C8 in vivo. In patients taking leflunomide tablets, exposure of drugs metabolized by CYP2C8 (e.g., paclitaxel, pioglitazone, repaglinide, rosiglitazone) may be increased.
Monitor these patients and adjust the dose of the concomitant drug(s) metabolized by CYP2C8 as required [see Clinical Pharmacology (12.3)]. Effect on warfarin Coadministration of leflunomide tablets with warfarin requires close monitoring of the international normalized ratio (INR) because teriflunomide, the active metabolite of leflunomide tablets, may decrease peak INR by approximately 25%. Effect on oral contraceptives Teriflunomide may increase the systemic exposures of ethinylestradiol and levonorgestrel.
Consideration should be given to the type or dose of contraceptives used in combination with leflunomide tablets [see Clinical Pharmacology (12.3)]. Effect on CYP1A2 substrates Teriflunomide, the active metabolite of leflunomide tablets, may be a weak inducer of CYP1A2 in vivo. In patients taking leflunomide tablets, exposure of drugs metabolized by CYP1A2 (e.g., alosetron, duloxetine, theophylline, tizanidine) may be reduced.
Monitor these patients and adjust the dose of the concomitant drug(s) metabolized by CYP1A2 as required [see Clinical Pharmacology (12.3)]. Effect on organic anion transporter 3 (OAT3) substrates Teriflunomide inhibits the activity of OAT3 in vivo. In patients taking leflunomide tablets, exposure of drugs which are OAT3 substrates (e.g., cefaclor, cimetidine, ciprofloxacin, penicillin G, ketoprofen, furosemide, methotrexate, zidovudine) may be increased.
Monitor these patients and adjust the dose of the concomitant drug(s) which are OAT3 substrates as required [see Clinical Pharmacology (12.3)]. Effect on BCRP and organic anion transporting polypeptide B1 and B3 (OATP1B1/1B3) substrates Teriflunomide inhibits the activity of BCRP and OATP1B1/1B3 in vivo. For a patient taking leflunomide tablets, the dose of rosuvastatin should not exceed 10 mg once daily.
For other substrates of BCRP (e.g., mitoxantrone) and drugs in the OATP family (e.g., methotrexate, rifampin), especially HMG- Co reductase inhibitors (e.g., atorvastatin, nateglinide, pravastatin, repaglinide, and simvastatin), consider reducing the dose of these drugs and monitor patients closely for signs and symptoms of increased exposures to the drugs while patients are taking leflunomide tablets [see Clinical Pharmacology (12.3)]. Drugs metabolized by CYP2C8 and OAT3 transporters: Monitor patients because teriflunomide may increase exposure of these drugs.
(7) Teriflunomide may increase exposure of ethinylestradiol and levonorgestrel. Choose an appropriate oral contraceptive. (7) Drugs metabolized by CYP1A2: Monitor patients because teriflunomide may decrease exposure of these drugs.
(7) Warfarin: Monitor INR as teriflunomide may decrease INR. (7)… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Discontinue breastfeeding. ( 8.2 ) Safety and effectiveness in pediatric patients <12 years of age has not been established. ( 8.4 )
8.1Pregnancy Risk Summary Leflunomide tablet is contraindicated for use in pregnant women because of the potential for fetal harm. In animal reproduction studies, oral administration of leflunomide during organogenesis at a dose of 1/10 of and equivalent to the maximum recommended human dose (MRHD) based on AUC, respectively in rats and rabbits, caused teratogenicity (rats and rabbits) and embryo-lethality (rats) [see Data]. Pregnancy exposure registry data are not available at this time to inform the presence or absence of drug-associated risk with the use of leflunomide tablets during pregnancy.
The background risk of major birth defects and miscarriage for the indicated populations is unknown. The background risk in the U.S. general population of major birth defects is 2 to 4% and of miscarriage is 15 to 20% of clinically recognized pregnancies. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, stop treatment with leflunomide tablets, apprise the patient of the potential hazard to a fetus, and perform the accelerated drug elimination procedure to achieve teriflunomide concentrations of less than 0.02 mg/L (0.02 mcg/mL) [see Warnings and Precautions ( 5.3 )].
Clinical Considerations Fetal/Neonatal adverse reactions Lowering the plasma concentration of the active metabolite, teriflunomide, by instituting an accelerated drug elimination procedure as soon as pregnancy is detected may decrease the risk to the fetus from leflunomide tablets. The accelerated drug elimination procedure includes verification that the plasma teriflunomide concentration is less than 0.02 mg/L. [see Warnings and Precautions ( 5.3 ) and Clinical Pharmacology ( 12.3 )]. Data Animal Data In an embryofetal development study, pregnant rats administered leflunomide during organogenesis from gestation days 7 to 19 at a dose approximately 1/10 of the MRHD (on an AUC basis at a maternal oral dose of 15 mg/kg),teratogenic effects, most notably anophthalmia or microophthalmia and internal hydrocephalus, were observed.
Under these exposure conditions, Leflunomide also caused a decrease in the maternal body weight and an increase in embryolethality with a decrease in fetal body weight for surviving fetuses. In an embryofetal development study, pregnant rabbits administered leflunomide during organogenesis from gestation days 6 to 18 at a dose approximately equivalent to the MRHD (on an AUC basis at a maternal oral dose of 10 mg/kg), a teratogenic finding of fused, dysplastic sternebrae was observed. Leflunomide was not teratogenic in rats and rabbits at doses approximately 1/150 and 1/10 of the MRHD, respectively (on an AUC basis at maternal oral dose of 1 mg/kg in both rats and rabbits).
In a pre- and post-natal development study, when female rats were treated leflunomide at a dose that was approximately 1/100 of the MRHD (on an AUC basis at a maternal dose of 1.25 mg/kg) beginning 14 days before mating and continuing until the end of lactation, the offspring exhibited marked (greater than 90%) decreases in postnatal survival.
8.2Lactation Risk Summary Clinical lactation studies have not been conducted to assess the presence of leflunomide tablets in human milk, the effects of leflunomide tablets on the breastfed child, or the effects of leflunomide tablets on milk production. Because of the potential for serious adverse reactions in a breastfed infant from leflunomide tablets, advise a nursing woman to discontinue breastfeeding during treatment with leflunomide tablets.
8.3Females and Males of Reproductive Potential Leflunomide tablets may cause fetal harm when administered during pregnancy. Advise females of the potential risk to the fetus. Advise females to notify their healthcare provider immediately if pregnancy occurs or is suspected dur… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Leflunomide tablet is contraindicated for use in pregnant women because of the potential for fetal harm. In animal reproduction studies, oral administration of leflunomide during organogenesis at a dose of 1/10 of and equivalent to the maximum recommended human dose (MRHD) based on AUC, respectively in rats and rabbits, caused teratogenicity (rats and rabbits) and embryo-lethality (rats) [see Data]. Pregnancy exposure registry data are not available at this time to inform the presence or absence of drug-associated risk with the use of leflunomide tablets during pregnancy.
The background risk of major birth defects and miscarriage for the indicated populations is unknown. The background risk in the U.S. general population of major birth defects is 2 to 4% and of miscarriage is 15 to 20% of clinically recognized pregnancies. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, stop treatment with leflunomide tablets, apprise the patient of the potential hazard to a fetus, and perform the accelerated drug elimination procedure to achieve teriflunomide concentrations of less than 0.02 mg/L (0.02 mcg/mL) [see Warnings and Precautions ( 5.3 )].
Clinical Considerations Fetal/Neonatal adverse reactions Lowering the plasma concentration of the active metabolite, teriflunomide, by instituting an accelerated drug elimination procedure as soon as pregnancy is detected may decrease the risk to the fetus from leflunomide tablets. The accelerated drug elimination procedure includes verification that the plasma teriflunomide concentration is less than 0.02 mg/L. [see Warnings and Precautions ( 5.3 ) and Clinical Pharmacology ( 12.3 )]. Data Animal Data In an embryofetal development study, pregnant rats administered leflunomide during organogenesis from gestation days 7 to 19 at a dose approximately 1/10 of the MRHD (on an AUC basis at a maternal oral dose of 15 mg/kg),teratogenic effects, most notably anophthalmia or microophthalmia and internal hydrocephalus, were observed.
Under these exposure conditions, Leflunomide also caused a decrease in the maternal body weight and an increase in embryolethality with a decrease in fetal body weight for surviving fetuses. In an embryofetal development study, pregnant rabbits administered leflunomide during organogenesis from gestation days 6 to 18 at a dose approximately equivalent to the MRHD (on an AUC basis at a maternal oral dose of 10 mg/kg), a teratogenic finding of fused, dysplastic sternebrae was observed. Leflunomide was not teratogenic in rats and rabbits at doses approximately 1/150 and 1/10 of the MRHD, respectively (on an AUC basis at maternal oral dose of 1 mg/kg in both rats and rabbits).
In a pre- and post-natal development study, when female rats were treated leflunomide at a dose that was approximately 1/100 of the MRHD (on an AUC basis at a maternal dose of 1.25 mg/kg) beginning 14 days before mating and continuing until the end of lactation, the offspring exhibited marked (greater than 90%) decreases in postnatal survival.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of leflunomide tablets in pediatric patients have not been established. The safety and effectiveness of leflunomide tablets in the treatment of polyarticular course juvenile idiopathic arthritis (JIA) was evaluated in a single multicenter, double-blind, active-controlled trial in 94 pediatric patients (1:1 randomization) with polyarticular course juvenile idiopathic arthritis (JIA) as defined by the American College of Rheumatology (ACR). In this population, leflunomide tablets treatment was found not to be effective.
The safety of leflunomide tablets was studied in 74 patients with polyarticular course JIA ranging in age from 3 to 17 years (47 patients from the active-controlled study and 27 from an open-label safety and pharmacokinetic study). The most common adverse events included abdominal pain, diarrhea, nausea, vomiting, oral ulcers, upper respiratory tract infections, alopecia, rash, headache, and dizziness. Less common adverse events included anemia, hypertension, and weight loss.
Fourteen pediatric patients experienced ALT and/or AST elevations, nine between 1.2 and 3-fold the upper limit of normal, five between 3 and 8-fold the upper limit of normal.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in controlled clinical trials (Trials 1, 2, and 3) of leflunomide tablets, 234 subjects were 65 years and over [see Clinical Studies ( 14 )]. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. No dosage adjustment is needed in patients over 65.
🆘 Overdosage ▾
10 OVERDOSAGE There have been reports of chronic overdose in patients taking leflunomide tablets at daily dose up to five times the recommended daily dose and reports of acute overdose in adults and children. Adverse events were consistent with the safety profile for leflunomide tablets [See Adverse Reactions ( 6 )]. The most frequent adverse events observed were diarrhea, abdominal pain, leukopenia, anemia and elevated liver function tests.
In the event of a significant overdose or toxicity, perform an accelerated drug elimination procedure to accelerate elimination [see Warnings and Precautions ( 5.3 )]. Studies with both hemodialysis and CAPD (chronic ambulatory peritoneal dialysis) indicate that teriflunomide, the primary metabolite of leflunomide, is not dialyzable [See Clinical Pharmacology ( 12.3 )].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Leflunomide is an isoxazole immunomodulatory agent that inhibits dihydroorotate dehydrogenase (a mitochondrial enzyme involved in de novo pyrimidine synthesis) and has antiproliferative activity. Several in vivo and in vitro experimental models have demonstrated an anti-inflammatory effect.
12.3Pharmacokinetics Following oral administration, leflunomide is metabolized to an active metabolite, teriflunomide, which is responsible for essentially all of leflunomide's in vivo activity. Plasma concentrations of the parent drug, leflunomide, have been occasionally seen at very low concentrations. Studies of the pharmacokinetics of leflunomide have primarily examined the plasma concentrations of the active metabolite, teriflunomide.
Absorption Following oral administration, peak teriflunomide concentrations occurred between 6 to 12 hours after dosing. Due to the very long half-life of teriflunomide (18 to 19 days), a loading dose of 100 mg for 3 days was used in clinical studies to facilitate the rapid attainment of steady-state teriflunomide concentrations. Without a loading dose, it is estimated that attainment of steady- state plasma concentrations would require about two months of dosing.
The resulting plasma concentrations following both loading doses and continued clinical dosing indicate that plasma teriflunomide concentrations are dose proportional. Effect of Food Co-administration of leflunomide tablets with a high fat meal did not have a significant impact on teriflunomide plasma concentrations. Distribution Teriflunomide is extensively bound to plasma protein (>99%) and is mainly distributed in plasma.
The volume of distribution is 11 L after a single intravenous (IV) administration. Elimination Teriflunomide, the active metabolite of leflunomide, has a median half-life of 18 to 19 days in healthy volunteers. The elimination of teriflunomide can be accelerated by administration of cholestyramine or activated charcoal.
Without use of an accelerated drug elimination procedure, it may take up to 2 years to reach plasma teriflunomide concentrations of less than 0.02 mg/L, due to individual variation in drug clearance [see Warnings and Precautions ( 5.3 )]. After a single IV administration of the metabolite (teriflunomide), the total body clearance of teriflunomide was 30.5 mL/h. Metabolism In vitro inhibition studies in human liver microsomes suggest that cytochrome P450 (CYP) 1A2, 2C19 and 3A4 are involved in leflunomide metabolism.
In vivo , leflunomide is metabolized to one primary (teriflunomide) and many minor metabolites. In vitro , teriflunomide is not metabolized by CYP450 or flavin monoamine oxidase enzymes. The parent compound is rarely detectable in plasma.
Excretion Teriflunomide, the active metabolite of leflunomide, is eliminated by direct biliary excretion of unchanged drug as well as renal excretion of metabolites. Over 21 days, 60.1% of the administered dose is excreted via feces (37.5%) and urine (22.6%). After an accelerated elimination procedure with cholestyramine, an additional 23.1% was recovered (mostly in feces).
Studies with both hemodialysis and CAPD (chronic ambulatory peritoneal dialysis) indicate that teriflunomide is not dialyzable. Specific Populations Gender. Gender has not been shown to cause a consistent change in the in vivo pharmacokinetics of teriflunomide.
Smoking. A population based pharmacokinetic analysis of the clinical trial data indicates that smokers have a 38% increase in clearance over non-smokers; however, no difference in clinical efficacy was seen between smokers and nonsmokers. Drug Interaction Studies Drug interaction studies have been conducted with both leflunomide and with its active metabolite, teriflunomide, where the metabolite was directly administered to the test subjects.
The Potential Effect of Other Drugs on Leflunomide tablets Potent CYP and transporter inducers: Following concomitant administration of a single d… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Leflunomide is an isoxazole immunomodulatory agent that inhibits dihydroorotate dehydrogenase (a mitochondrial enzyme involved in de novo pyrimidine synthesis) and has antiproliferative activity. Several in vivo and in vitro experimental models have demonstrated an anti-inflammatory effect.
📦 How Supplied / Storage and Handling ▾
Store at 20°-25°C (68° to 77°F); Keep away from heat and flame. Protect from freezing. [See USP Controlled Room Temperature.] Protect from light.
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Leflunomide tablets USP; 10 mg and 20 mg Strength Quantity NDC Number Description 10 mg 30 count bottle packed in a monocarton 70748-129-06 White to off-white, round film coated tablet, debossed with "L" on one side and "A4" on the other side. 20 mg 30 count bottle packed in a monocarton 70748-130-06 Yellow colour, film coated, round shaped tablet, debossed with "L" on one side and "A5" on the other side. Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Protect from light.
📦 Storage and Handling ▾
Store at 20°-25°C (68° to 77°F); Keep away from heat and flame. Protect from freezing. [See USP Controlled Room Temperature.] Protect from light.
Other information • store at 20-25°C (68-77°F). Keep from freezing. • read all product information before using. Keep the dosing card, this carton and accompanying User Guide for important information.
🧪 Active Ingredient ▾
Active ingredient Diclofenac sodium (NSAID*) 1% (equivalent to 0.93% diclofenac) *nonsteroidal anti-inflammatory drug
🧪 Inactive Ingredients ▾
Inactive ingredients carbomer homopolymer Type C, cocoyl caprylocaprate, fragrance, isopropyl alcohol, mineral oil, polyoxyl 20 cetostearyl ether, propylene glycol, purified water, strong ammonia solution
🎯 Purpose ▾
Purpose Arthritis pain reliever
📋 Description ▾
LEFLUNICLO DESCRIPTION LEFFLUNICLO is supplied as 2 components in a kit: 1 BOTTLE OF LEFLUNOMIDE TABLETS USP; 20MG (30 TABLETS) White to off-white, round film coated tablet, debossed with "L" on one side and "A5" on the other side. 1 TUBE OF DICLOFENAC SODIUM (NSAID*) 1% (equivalent to 0.93% diclofenac), 100 g TUBE.
11 DESCRIPTION Leflunomide USP is a pyrimidine synthesis inhibitor. The chemical name for leflunomide is N-(4´-trifluoromethylphenyl)-5-methylisoxazole-4-carboxamide. It has an empirical formula C 12 H 9 F 3 N 2 O 2 , a molecular weight of 270.2 and the following structural formula: Leflunomide USP is available for oral administration as film coated tablets containing 10, 20 mg of active drug.
Combined with leflunomide are the following inactive ingredients: colloidal silicon dioxide, crospovidone, hypromellose, lactose monohydrate, magnesium stearate, corn starch, HPMC 2910/Hypromellose USP (6 mPas), Titanium Dioxide USP, Macrogol/PEG 6000 NF, Talc USP and Iron Oxide Yellow NF (20 mg tablet only). Image
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Embryo-Fetal Toxicity Advise females of reproductive potential Of the potential for fetal harm if leflunomide tablets are taken during pregnancy. To notify their healthcare provider immediately if a pregnancy occurs or is suspected. To use effective contraception during treatment with leflunomide tablets and until the active metabolite (teriflunomide) plasma concentration is verified to be less than 0.02 mg/L [see Warnings and Precautions ( 5.1 , 5.3 ), Use in Specific Populations ( 8.1 , 8.3 ), Clinical Pharmacology ( 12.3 )].
Lactation Advise nursing women to discontinue breastfeeding during treatment with leflunomide tablets [see Use in Specific Populations ( 8.2 )]. Advise patients of the possibility of rare, serious skin reactions. Instruct patients to promptly report if they develop a skin rash or mucous membrane lesions.
Advise patients of the potential hepatotoxic effects of leflunomide tablets and of the need for monitoring liver enzymes. Instruct patients to report if they develop symptoms such as unusual tiredness, abdominal pain or jaundice. Advise patients that they may develop a lowering of their blood counts and should have frequent hematologic monitoring.
This is particularly important for patients who are receiving other immunosuppressive therapy concurrently with leflunomide tablets, who have recently discontinued such therapy before starting treatment with leflunomide tablets, or who have had a history of a significant hematologic abnormality. Instruct patients to promptly report if they notice symptoms consistent with pancytopenia, such as easy bruising or bleeding, recurrent infections, fever, paleness or unusual tiredness. Inform patients about the early warning signs of interstitial lung disease and ask to promptly if these symptoms appear or worsen during therapy.
📄 Do Not Use ▾
Do not use • if you have ever had an allergic reaction to any other pain reliever or to a fever reducer • for strains, sprains, bruises or sports injuries. This product has not been shown to work for these types of injuries. • right before or after heart surgery • on more than 2 body areas at the same time • in the eyes, nose or mouth
📄 Ask a Doctor Before Use If ▾
Ask a doctor before use if • you have problems or serious side effects from taking pain relievers or fever reducers • stomach bleeding warning applies to you • you have a history of stomach problems, such as heartburn • you have high blood pressure, heart disease, liver cirrhosis, kidney disease, asthma, or had a stroke • you are taking a diuretic • you are under age 18 years. It is not known if this drug works or is safe in children under age 18 years.
📄 Ask a Doctor or Pharmacist Before Use If ▾
Ask a doctor or pharmacist before use if you are • under a doctor’s care for any serious condition • taking any other drug
📄 When Using This Product ▾
When using this product • avoid contact with eyes, nose, or mouth • if eye contact occurs, rinse thoroughly with water
📄 Stop Use and Ask a Doctor If ▾
Stop use and ask a doctor if • pain gets worse or lasts more than 21 days • redness or swelling is present in the painful area • fever occurs • skin irritation occurs • any new symptoms appear. These could be signs of a serious condition. • you experience any of the following signs of stomach bleeding: • feel faint • have bloody or black stools • vomit blood • have stomach pain that does not get better • you have symptoms of heart problems or stroke: • chest pain • trouble breathing • leg swelling • weakness in one part or side of body • slurred speech
🤰 If Pregnant or Breast-Feeding ▾
If pregnant or breast-feeding, ask a health professional before use. It is especially important not to use this product during the last 3 months of pregnancy unless definitely directed to do so by a doctor because it may cause problems in the unborn child or complications during delivery.
📄 Keep Out of Reach of Children ▾
Keep out of reach of children. If swallowed, get medical help or contact a Poison Control Center right away (1-800-222-1222).
📄 Questions or Comments ▾
Questions or comments? 1-800-719-9260
⚠️ Precautions ▾
PRECAUTIONS Keep this and all other medications out of the reach of children. Please read all precautions of each component within this kit. PREGNANCY If pregnant or breast feeding, ask a health professional before use.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following oral administration, leflunomide is metabolized to an active metabolite, teriflunomide, which is responsible for essentially all of leflunomide's in vivo activity. Plasma concentrations of the parent drug, leflunomide, have been occasionally seen at very low concentrations. Studies of the pharmacokinetics of leflunomide have primarily examined the plasma concentrations of the active metabolite, teriflunomide.
Absorption Following oral administration, peak teriflunomide concentrations occurred between 6 to 12 hours after dosing. Due to the very long half-life of teriflunomide (18 to 19 days), a loading dose of 100 mg for 3 days was used in clinical studies to facilitate the rapid attainment of steady-state teriflunomide concentrations. Without a loading dose, it is estimated that attainment of steady- state plasma concentrations would require about two months of dosing.
The resulting plasma concentrations following both loading doses and continued clinical dosing indicate that plasma teriflunomide concentrations are dose proportional. Effect of Food Co-administration of leflunomide tablets with a high fat meal did not have a significant impact on teriflunomide plasma concentrations. Distribution Teriflunomide is extensively bound to plasma protein (>99%) and is mainly distributed in plasma.
The volume of distribution is 11 L after a single intravenous (IV) administration. Elimination Teriflunomide, the active metabolite of leflunomide, has a median half-life of 18 to 19 days in healthy volunteers. The elimination of teriflunomide can be accelerated by administration of cholestyramine or activated charcoal.
Without use of an accelerated drug elimination procedure, it may take up to 2 years to reach plasma teriflunomide concentrations of less than 0.02 mg/L, due to individual variation in drug clearance [see Warnings and Precautions ( 5.3 )]. After a single IV administration of the metabolite (teriflunomide), the total body clearance of teriflunomide was 30.5 mL/h. Metabolism In vitro inhibition studies in human liver microsomes suggest that cytochrome P450 (CYP) 1A2, 2C19 and 3A4 are involved in leflunomide metabolism.
In vivo , leflunomide is metabolized to one primary (teriflunomide) and many minor metabolites. In vitro , teriflunomide is not metabolized by CYP450 or flavin monoamine oxidase enzymes. The parent compound is rarely detectable in plasma.
Excretion Teriflunomide, the active metabolite of leflunomide, is eliminated by direct biliary excretion of unchanged drug as well as renal excretion of metabolites. Over 21 days, 60.1% of the administered dose is excreted via feces (37.5%) and urine (22.6%). After an accelerated elimination procedure with cholestyramine, an additional 23.1% was recovered (mostly in feces).
Studies with both hemodialysis and CAPD (chronic ambulatory peritoneal dialysis) indicate that teriflunomide is not dialyzable. Specific Populations Gender. Gender has not been shown to cause a consistent change in the in vivo pharmacokinetics of teriflunomide.
Smoking. A population based pharmacokinetic analysis of the clinical trial data indicates that smokers have a 38% increase in clearance over non-smokers; however, no difference in clinical efficacy was seen between smokers and nonsmokers. Drug Interaction Studies Drug interaction studies have been conducted with both leflunomide and with its active metabolite, teriflunomide, where the metabolite was directly administered to the test subjects.
The Potential Effect of Other Drugs on Leflunomide tablets Potent CYP and transporter inducers: Following concomitant administration of a single dose of leflunomide tablets to subjects receiving multiple doses of rifampin, teriflunomide peak concentrations were increased (~40%) over those seen when leflunomide tablets was given alone [see Drug Interactions ( 7 )]. An in vivo interaction study with leflunomide tablets and cimetidine (non-specific weak CYP inhibitor) has demonstrated a… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of leflunomide tablets in the treatment of rheumatoid arthritis (RA) was demonstrated in three controlled trials showing reduction in signs and symptoms, and inhibition of structural damage. In two placebo controlled trials, efficacy was demonstrated for improvement in physical function. In these trials, efficacy was evaluated by: 1.
Reduction of signs and symptoms Relief of signs and symptoms was assessed using the American College of Rheumatology (ACR) 20 Responder Index, a composite of clinical, laboratory, and functional measures in rheumatoid arthritis. An "ACR20 Responder" is a patient who had ≥ 20% improvement in both tender and swollen joint counts and in 3 of the following 5 criteria: physician global assessment, patient global assessment, functional ability measure [Modified Health Assessment Questionnaire (MHAQ)], visual analog pain scale, and erythrocyte sedimentation rate or C-reactive protein.
An "ACR20 Responder at Endpoint" is a patient who completed the study and was an ACR20 Responder at the completion of the study. 2. Inhibition of structural damage Inhibition of structural damage compared to control was assessed using the Sharp Score, a composite score of X-ray erosions and joint space narrowing in hands/wrists and forefeet.
3. Improvement in physical function Improvement in physical function was assessed using the Health Assessment Questionnaire (HAQ) and the Medical Outcomes Survey Short Form (SF-36).In all leflunomide tablets trials, participants of at least 18 years of age and in ARA functional class of I, II or III received an initial loading dosage of 100 mg leflunomide per day for three days, followed by 20 mg per day thereafter. Exclusion criteria included patients with a history of hypersensitivity to the study medication; women who were pregnant or breast feeding and men or women of child bearing age and potential who had not received contraceptives for at least 4 weeks before entering the study and to be maintained throughout the study and for at least 6 months after discontinuing treatment; patients with a history of inflammatory disease, impaired renal function or liver impairment, cardiac failure, congenital or acquired immunodeficiency, impaired coagulation, or a history of recent major traumatic injury; patients taking intra-articular or systemic concomitant medications which could affect the safety and/or efficacy of the study medication.
Trial 1 Trial 1, a 2 year study, randomized 482 patients with active RA of at least 6 months duration to leflunomide 20 mg/day (n=182), methotrexate 7.5 mg/week increasing to 15 mg/week (n=182), or placebo (n=118). All patients received folate 1 mg BID. The primary analysis was at 52 weeks with blinded treatment to 104 weeks.
Overall, 235 of the 508 randomized treated patients (482 in primary data analysis and an additional 26 patients), continued into a second 12 months of double-blind treatment (98 leflunomide, 101 methotrexate, 36 placebo). Leflunomide dose continued at 20 mg/day and the methotrexate dose could be increased to a maximum of 20 mg/week. In total, 190 patients (83 leflunomide, 80 methotrexate, 27 placebo) completed 2 years of double-blind treatment.
Trial 2 Trial 2 randomized 358 patients with active RA to leflunomide 20 mg/day (n=133), sulfasalazine 2.0 g/day (n=133), or placebo (n=92). Treatment duration was 24 weeks. An extension of the study was an optional 6-month blinded continuation of Trial 2 without the placebo arm, resulting in a 12-month comparison of leflunomide and sulfasalazine.
Of the 168 patients who completed 12 months of treatment , 146 patients (87%) entered a 1-year extension study of double blind active treatment; (60 leflunomide, 60 sulfasalazine, 26 placebo/ sulfasalazine). Patients continued on the same daily dosage of leflunomide or sulfasalazine that they had been taking at the completion of Trial 2. A total of 121 patients (53 leflunomide, 47 sulfasalazine, 21 placebo/sulfasalazin… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of carcinogenicity was observed in a 2-year bioassay in rats at oral doses of leflunomide up to the maximally tolerated dose of 6 mg/kg (approximately 1/40 the maximum human teriflunomide systemic exposure based on AUC). However, male mice in a 2-year bioassay exhibited an increased incidence in lymphoma at an oral dose of 15 mg/kg, the highest dose studied (1.7 times the human teriflunomide exposure based on AUC). Female mice, in the same study, exhibited a dose-related increased incidence of bronchoalveolar adenomas and carcinomas combined beginning at 1.5 mg/kg (approximately 1/10 the human teriflunomide exposure based on AUC).
The significance of the findings in mice relative to the clinical use of leflunomide tablet is not known. Leflunomide was not mutagenic in the Ames assay, the unscheduled DNA synthesis assay, or in the HGPRT gene mutation assay. In addition, leflunomide was not clastogenic in the in vivo mouse micronucleus assay or in the in vivo Chinese hamster bone marrow cell cytogenic test.
However, 4-trifluoromethylaniline (TFMA), a minor metabolite of leflunomide, was mutagenic in the Ames assay and in the HGPRT gene mutation assay, and was clastogenic in the in vitro Chinese hamster cell chromosomal aberration assay. TFMA was not clastogenic in the in vivo mouse micronucleus assay or in the in vivo Chinese hamster bone marrow cell cytogenic test. Leflunomide had no effect on fertility or reproductive performance in either male or female rats at oral doses up to 4.0 mg/kg (approximately 1/30 the human teriflunomide exposure based on AUC) [see Use in Specific Populations ( 8.1 , 8.6 )].
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of carcinogenicity was observed in a 2-year bioassay in rats at oral doses of leflunomide up to the maximally tolerated dose of 6 mg/kg (approximately 1/40 the maximum human teriflunomide systemic exposure based on AUC). However, male mice in a 2-year bioassay exhibited an increased incidence in lymphoma at an oral dose of 15 mg/kg, the highest dose studied (1.7 times the human teriflunomide exposure based on AUC). Female mice, in the same study, exhibited a dose-related increased incidence of bronchoalveolar adenomas and carcinomas combined beginning at 1.5 mg/kg (approximately 1/10 the human teriflunomide exposure based on AUC).
The significance of the findings in mice relative to the clinical use of leflunomide tablet is not known. Leflunomide was not mutagenic in the Ames assay, the unscheduled DNA synthesis assay, or in the HGPRT gene mutation assay. In addition, leflunomide was not clastogenic in the in vivo mouse micronucleus assay or in the in vivo Chinese hamster bone marrow cell cytogenic test.
However, 4-trifluoromethylaniline (TFMA), a minor metabolite of leflunomide, was mutagenic in the Ames assay and in the HGPRT gene mutation assay, and was clastogenic in the in vitro Chinese hamster cell chromosomal aberration assay. TFMA was not clastogenic in the in vivo mouse micronucleus assay or in the in vivo Chinese hamster bone marrow cell cytogenic test. Leflunomide had no effect on fertility or reproductive performance in either male or female rats at oral doses up to 4.0 mg/kg (approximately 1/30 the human teriflunomide exposure based on AUC) [see Use in Specific Populations ( 8.1 , 8.6 )].
📄 Package Label / Principal Display Panel ▾
Lefluniclo Packaging The packaging for Lefluniclo is shown below Lefluniclo Packaging
About this NDC listing & data coverage
Listed without an FDA application
This product's marketing category indicates it is marketed without an approved FDA application (no NDA, ANDA, or BLA on file). Having an NDC does not by itself establish FDA approval — the NDC Directory is a listing system, not an approval decision. Approval-linked data such as Orange Book therapeutic-equivalence ratings therefore does not apply.
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |