
Lidocaine Hydrochloride 20 mg/mL Jelly
Other active recalls for Lidocaine Hydrochloride (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antiarrhythmic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's best to avoid using two lidocaine products at the same time unless your doctor says it's okay. When you use multiple products containing a local anesthetic, the total amount a...
- Can I use a lidocaine patch and a lidocaine cream at the same time?
- No — please don't do this. Heat significantly increases how much lidocaine is absorbed through your skin, which can push drug levels in your blood higher than they should be. Stick...
- Can I put a heating pad on the area where I applied a lidocaine patch?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.167 | $145.90 / 125 ml |
| Medicaid paysCMS SDUD · 12 mo | $1.29 | $160.70 / 125 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lidocaine Hydrochloride 20 mg/mL 76329-3013-05 | International | 25 vials | $0.704 | AT | Availability likely | save 40% |
| glydo 20 mg/mL 25021-0673-76 | Sagent | 10 syringes | $0.887 | AT | Availability likely | save 24% |
| Lidocaine Hydrochloride 20 mg/mL 76329-3011-05 | International | 25 vials | $1.167 | AT | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mLthis 76329-3012-05 | International | 25 vials | $1.167 | AT | Availability likely | — |
| Lidocaine Hydrochloride 20 mg/mL 00404-9898-10 | Henry | 1 vial | — | AT | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 00404-9899-20 | Henry | 1 vial | — | AT | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 00404-9900-05 | Henry | 1 vial | — | AT | FDA listed | — |
| First Aid Only Lidocaine Hydrochloride Analgesic Burn Gel 20 mg/g 00924-5004-00 | Acme | 3.5 g | — | — | FDA listed | — |
| First Aid Only Burn 20 mg/g 00924-5010-00 | Acme | 3.5 g | — | — | FDA listed | — |
| Burn 20 mg/g 43473-0048-01 | Nantong | 9 g | — | — | FDA listed | — |
| PO First Aid Series BURN 2 g/100g 43473-0062-01 | Nantong | 9 g | — | — | FDA listed | — |
| JJ Care BURN 2 g/100g 43473-0069-01 | Nantong | 9 g | — | — | FDA listed | — |
| Lightning X Burn Relief Gel 2 g/100g 43473-0121-01 | Nantong | 9 g | — | — | FDA listed | — |
| Medi-First Burn 20 mg/g 47682-0477-69 | Unifirst | 6 packets | — | — | FDA listed | — |
| Lidocaine Hci 20 mg/mL 51662-1389-01 | HF | 5 ml | — | AT | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 51662-1551-03 | HF | 25 pouches | — | AT | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 51662-1552-03 | HF | 25 pouches | — | AT | FDA listed | — |
| Burn Ease 2 g/100g 58228-2010-01 | ProStat | 25 packets | — | — | FDA listed | — |
| PROSTAT FIRST AID Burn Ease, 0.9g 2 g/100g 58228-2012-01 | ProStat | 25 packets | — | — | FDA listed | — |
| Burn Ease Cooling 2 g/100g 58228-2893-05 | ProStat | 2000 packets | — | — | FDA listed | — |
| Burn Ease 2 g/100g 58228-3831-02 | ProStat | 20 packets | — | — | FDA listed | — |
| Burn Ease 2 g/100g 58228-3832-02 | ProStat | 6 packets | — | — | FDA listed | — |
| PS-3866 Burn Ease, 0.9g 2 g/100g 58228-3866-01 | ProStat | 10 packets | — | — | FDA listed | — |
| PROSTAT FIRST AID Burn Ease, 0.9g 2 g/100g 58228-3867-01 | ProStat | 10 packets | — | — | FDA listed | — |
| Burn Ease, 3.5g 2 g/100g 58228-3883-01 | ProStat | 2000 packets | — | — | FDA listed | — |
| PS-3885 Burn Ease, 3.5g 2 g/100g 58228-3885-01 | ProStat | 6 packets | — | — | FDA listed | — |
| Burn Ease 2 g/100g 58228-6210-01 | Front | 25 packets | — | — | FDA listed | — |
| FL Burn Ease, 0.9g 2 g/100g 58228-6212-01 | ProStat | 25 packets | — | — | FDA listed | — |
| Burn Ease 3.5g 2 g/100g 58228-6231-01 | Front | 20 packets | — | — | FDA listed | — |
| Burn Ease 3.5g 2 g/100g 58228-6232-01 | Front | 6 packets | — | — | FDA listed | — |
| Burn Ease 3.5g 2 g/100g 58228-6283-01 | Front | 2000 packets | — | — | FDA listed | — |
| Lidoease 2% 20 mg/g 59088-0221-03 | PureTek | 28.35 g | — | — | FDA listed | — |
| Burn Jel 2 g/100mL 59898-0200-11 | Water-Jel | 24 bottles | — | — | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/g 61010-5000-00 | Safetec | 3.3 g | — | — | FDA listed | — |
| Aloe Ice Sunburn Relief 2 g/100mL 61477-0101-11 | Aloe | 60 ml | — | — | FDA listed | — |
| Regenecare Ha 20 mg/g 66977-0107-03 | MPM | 85 g | — | — | FDA listed | — |
| XeroBurn Burn Gel 2 g/100g 67777-0129-02 | Dynarex | 1728 packets | — | — | FDA listed | — |
| Burn Gel .02 g/g 69396-0106-09 | Trifecta | 144 packets | — | — | FDA listed | — |
| Redicare Burn Gel 20 mg/g 71105-0500-02 | Redicare | 15 packets | — | — | FDA listed | — |
| Jelcaine Sterile 20 mg/mL 71351-0025-30 | Brookfield | 30 ml | — | — | FDA listed | — |
| Lidocaine 20 mg/mL 72485-0611-10 | ARMAS | 1 tube | — | AT | FDA listed | — |
| Lidocaine Hydrochloride 20 mg/mL 76329-3015-05 | International | 25 vials | — | AT | FDA listed | — |
| Burn 20 mg/g 82942-1001-01 | J&A | 9 g | — | — | FDA listed | — |
| Lidomax 20 mg/g 85477-0304-07 | Oncora | 85 g | — | — | FDA listed | — |
| Collavera 20 mg/g 85477-0305-07 | Oncora | 28.33 g | — | — | FDA listed | — |
| Lidocaine Hydrochloride 2% 2 g/100g 87236-0015-35 | Aldermed | 25 packets | — | — | FDA listed | — |
| Lidocaine 20 mg/mL 70244-0039-01 | Sentiss | 1 tube | — | AT | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 76329-3012-05 You're viewing this | 25 VIAL, SINGLE-USE in 1 BOX (76329-3012-5) / 5 mL in 1 VIAL, SINGLE-USE | 1979-08-07 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE: Lidocaine Hydrochloride Jelly USP, 2% is indicated for prevention and control of pain in procedures involving the male and female urethra for topical treatment of painful urethritis, and as an anesthetic lubricant for endotracheal intubation (oral and nasal).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION: When Lidocaine Hydrochloride Jelly USP, 2% is used concomitantly with other products containing lidocaine, the total dose contributed by all formulations must be kept in mind. The dosage varies and depends upon the area to be anesthetized, vascularity of the tissues, individual tolerance, and the technique of anesthesia. The lowest dosage needed to provide effective anesthesia should be administered.
Dosages should be reduced for children and for elderly and debilitated patients. Although the incidence of adverse effects with Lidocaine Hydrochloride Jelly USP, 2% is quite low, caution should be exercised, particularly when employing large amounts, since the incidence of adverse effects is directly proportional to the total dose of local anesthetic agent administered. For Surface Anesthesia of the Male Adult Urethra Slowly instill approximately 15 mL (300 mg of lidocaine HCl) into the urethra or until the patient has a feeling of tension.
A penile clamp is then applied for several minutes at the corona. An additional dose of not more than 15 mL (300 mg) can be instilled for adequate anesthesia. Prior to sounding or cystoscopy, a penile clamp should be applied for 5 to 10 minutes to obtain adequate anesthesia.
A total dose of 30 mL (600 mg) is usually required to fill and dilate the male urethra. Prior to catheterization, smaller volumes of 5 to 10 mL (100 to 200 mg) are usually adequate for lubrication. For Surface Anesthesia of the Female Adult Urethra Slowly instill 3 to 5 mL (60 to 100 mg of lidocaine HCl) of the jelly into the urethra.
If desired, some jelly may be deposited on a cotton swab and introduced into the urethra. In order to obtain adequate anesthesia, several minutes should be allowed prior to performing urological procedures. Lubrication for Endotracheal Intubation Apply a moderate amount of jelly to the external surface of the endotracheal tube shortly before use.
Care should be taken to avoid introducing the product into the lumen of the tube. Do not use the jelly to lubricate endotracheal stylettes. See WARNINGS and ADVERSE REACTIONS concerning rare reports of inner lumen occlusion.
It is also recommended that use of endotracheal tubes with dried jelly on the external surface be avoided for lack of lubricating effect. MAXIMUM DOSAGE: No more than 600 mg of lidocaine hydrochloride should be given in any 12 hour period. Children It is difficult to recommend a maximum dose of any drug for children since this varies as a function of age and weight.
For children less than ten years who have a normal lean body mass and a normal lean body development, the maximum dose may be determined by the application of one of the standard pediatric drug formulas (e.g., Clark's rule). For example, in a child of five years weighing 50 lbs., the dose of lidocaine hydrochloride should not exceed 75–100 mg when calculated according to Clark's rule. In any case, the maximum amount of lidocaine administered should not exceed 4.5 mg / kg (2 mg / lb) of body weight.
⛔ Contraindications ▾
CONTRAINDICATIONS: Lidocaine is contraindicated in patients with a known history of hypersensitivity to local anesthetics of the amide type or to other components of Lidocaine Hydrochloride Jelly USP, 2%.
⚠️ Warnings ▾
WARNINGS: EXCESSIVE DOSAGE, OR SHORT INTERVALS BETWEEN DOSES, CAN RESULT IN HIGH PLASMA LEVELS AND SERIOUS ADVERSE EFFECTS. PATIENTS SHOULD BE INSTRUCTED TO STRICTLY ADHERE TO THE RECOMMENDED DOSAGE AND ADMINISTRATION GUIDELINES AS SET FORTH IN THIS PACKAGE INSERT. THE MANAGEMENT OF SERIOUS ADVERSE REACTIONS MAY REQUIRE THE USE OF RESUSCITATIVE EQUIPMENT, OXYGEN, AND OTHER RESUSCITATIVE DRUGS.
Lidocaine Hydrochloride Jelly USP, 2% should be used with extreme caution in the presence of sepsis or severely traumatized mucosa in the area of application, since under such conditions there is the potential for rapid systemic absorption. When used for endotracheal tube lubrication, care should be taken to avoid introducing the product into the lumen of the tube. Do not use the jelly to lubricate the endotracheal stylettes. lf allowed into the inner lumen, the jelly may dry on the inner surface leaving a residue which tends to clump with flexion, narrowing the lumen.
There have been rare reports in which this residue has caused the lumen to occlude (see ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION ). Methemoglobinemia Cases of methemoglobinemia have been reported in association with local anesthetic use. Although all patients are at risk for methemoglobinemia, patients with glucose-6-phosphate dehydrogenase deficiency, congenital or idiopathic methemoglobinemia, cardiac or pulmonary compromise, infants under 6 months of age, and concurrent exposure to oxidizing agents or their metabolites are more susceptible to developing clinical manifestations of the condition.
If local anesthetics must be used in these patients, close monitoring for symptoms and signs of methemoglobinemia is recommended. Signs of methemoglobinemia may occur immediately or may be delayed some hours after exposure, and are characterized by a cyanotic skin discoloration and/or abnormal coloration of the blood. Methemoglobin levels may continue to rise; therefore, immediate treatment is required to avert more serious central nervous system and cardiovascular adverse effects, including seizures, coma, arrhythmias, and death.
Discontinue Lidocaine Hydrochloride Jelly USP, 2% and any other oxidizing agents. Depending on the severity of the signs and symptoms, patients may respond to supportive care, i.e., oxygen therapy, hydration. A more severe clinical presentation may require treatment with methylene blue, exchange transfusion, or hyperbaric oxygen.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS: Adverse experiences following the administration of lidocaine are similar in nature to those observed with other amide local anesthetic agents. These adverse experiences are, in general, dose-related and may result from high plasma levels caused by excessive dosage or rapid absorption, or may result from a hypersensitivity, idiosyncrasy, or diminished tolerance on the part of the patient. Serious adverse experiences are generally systemic in nature.
The following types are those most commonly reported: There have been rare reports of endotracheal tube occlusion associated with the presence of dried jelly residue in the inner lumen of the tube (see WARNINGS and DOSAGE AND ADMINISTRATION ). Central Nervous System CNS manifestations are excitatory and/or depressant and may be characterized by lightheadedness, nervousness, apprehension, euphoria, confusion, dizziness, drowsiness, tinnitus, blurred or double vision, vomiting, sensations of heat, cold or numbness, twitching, tremors, convulsions, unconsciousness, respiratory depression and arrest.
The excitatory manifestations may be very brief or may not occur at all, in which case the first manifestation of toxicity may be drowsiness merging into unconsciousness and respiratory arrest. Drowsiness following the administration of lidocaine is usually an early sign of a high blood level of the drug and may occur as a consequence of rapid absorption. Cardiovascular system Cardiovascular manifestations are usually depressant and are characterized by bradycardia, hypotension, and cardiovascular collapse, which may lead to cardiac arrest.
Allergic Allergic reactions are characterized by cutaneous lesions, urticaria, edema or anaphylactoid reactions. Allergic reactions may occur as a result of sensitivity either to the local anesthetic agent or to other components in the formulation. Allergic reactions as a result of sensitivity to lidocaine are extremely rare and, if they occur, should be managed by conventional means.
The detection of sensitivity by skin testing is of doubtful value.
🔄 Drug Interactions ▾
Drug Interactions Patients who are administered local anesthetics are at increased risk of developing methemoglobinemia when concurrently exposed to the following drugs, which could include other local anesthetics: Examples of Drugs Associated with Methemoglobinemia: Class Examples Nitrates/Nitrites nitric oxide, nitroglycerin, nitroprusside, nitrous oxide Local anesthetics articaine, benzocaine, bupivacaine, lidocaine, mepivacaine, prilocaine, procaine, ropivacaine, tetracaine Antineoplastic Agents cyclophosphamide, flutamide, hydroxyurea, ifosfamide, rasburicase Antibiotics dapsone, nitrofurantoin, para-aminosalicylic acid, sulfonamides Antimalarials chloroquine, primaquine Anticonvulsants Phenobarbital, phenytoin, sodium valproate, Other drugs acetaminophen, metoclopramide, quinine, sulfasalazine
🤰 Pregnancy ▾
Use in Pregnancy Teratogenic Effects Teratogenic Effects: Pregnancy Category B. Reproduction studies for lidocaine have been performed in both rats and rabbits. There was no evidence of harm to the fetus at subcutaneous doses of up to 50 mg/kg lidocaine (300 mg/m 2 on a body surface area basis) in the rat model.
In the rabbit model, there was no evidence of harm to the fetus at a dose of 5 mg/kg, s.c. (60 mg/m 2 on a body surface area basis). Treatment of rabbits with 25 mg/kg (300 mg/m 2 ) produced evidence of maternal toxicity and evidence of delayed fetal development, including a non-significant decrease in fetal weight (7%) and an increase in minor skeletal anomalies (skull and sternebral defect, reduced ossification of the phalanges).
The effect of lidocaine on post-natal development was examined in rats by treating pregnant female rats daily subcutaneously at doses of 2, 10, and 50 mg/kg (12, 60, and 300 mg/m 2 ) from day 15 of pregnancy and up to 20 days post partum. No signs of adverse effects were seen either in dams or in the pups up to and including the dose of 10 mg/kg (60 mg/m 2 ); however, the number of surviving pups was reduced at 50 mg/kg (300 mg/m 2 ), both at birth and the duration of lactation period, the effect most likely being secondary to maternal toxicity.
No other effects on litter size, litter weight, abnormalities in the pups and physical developments of the pups were seen in this study. A second study examined the effects of lidocaine on post-natal development in the rat that included assessment of the pups from weaning to sexual maturity. Rats were treated for 8 months with 10 or 30 mg/kg, s.c. lidocaine (60 mg/m 2 and 180 mg/m 2 on a body surface area basis, respectively).
This time period encompassed 3 mating periods. There was no evidence of altered post-natal development in any offspring; however, both doses of lidocaine significantly reduced the average number of pups per litter surviving until weaning of offspring from the first 2 mating period. There are, however, no adequate and well-controlled studies in pregnant women.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Although, the safety and effectiveness of Lidocaine Hydrochloride Jelly USP, 2% in pediatric patients have not been established, a study of 19 premature neonates (gestational age <33 weeks) found no correlation between the plasma concentration of lidocaine or monoethylglycinexylidide and infant body weight when moderate amounts of lidocaine (i.e. 0.3 mL/kg of lidocaine gel 20 mg/ml) were used for lubricating both intranasal and endotracheal tubes. No neonate had plasma levels of lidocaine above 750 mcg/L.
Dosages in children should be reduced, commensurate with age, body weight, and physical condition. (See DOSAGE AND ADMINISTRATION .)
🆘 Overdosage ▾
OVERDOSAGE: Acute emergencies from local anesthetics are generally related to high plasma levels encountered during therapeutic use of local anesthetics (see ADVERSE REACTIONS , WARNINGS , and PRECAUTIONS .) Management of Local Anesthetic Emergencies The first consideration is prevention, best accomplished by careful and constant monitoring of cardiovascular and respiratory vital signs and the patient's state of consciousness after each local anesthetic administration. At the first sign of change, oxygen should be administered.
The first step in the management of convulsions consists of immediate attention to the maintenance of a patent airway and assisted or controlled ventilation with oxygen and a delivery system capable of permitting immediate positive airway pressure by mask. Immediately after the institution of these ventilatory measures, the adequacy of the circulation should be evaluated, keeping in mind that drugs used to treat convulsions sometimes depress the circulation when administered intravenously. Should convulsions persist despite adequate respiratory support and if the status of the circulation permits, small increments of an ultra-short acting barbiturate (such as thiopental or thiamylal) or a benzodiazepine (such as diazepam) may be administered intravenously.
The clinician should be familiar, prior to use of local anesthetics, with these anticonvulsant drugs. Supportive treatment of circulatory depression may require administration of intravenous fluids and when appropriate, a vasopressor as directed by the clinical situation (e.g. ephedrine). If not treated immediately, both convulsions and cardiovascular depression can result in hypoxia, acidosis, bradycardia, arrhythmias and cardiac arrest.
If cardiac arrest should occur, standard cardiopulmonary resuscitative measures should be instituted. Dialysis is of negligible value in the treatment of acute overdosage with lidocaine. The oral LD 50 of lidocaine hydrochloride in non-fasted female rats is 459 (346 to 773) mg / kg (as the salt) and 214 (159 to 324) mg / kg (as the salt) in fasted female rats.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY: Mechanism of action Lidocaine stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses, thereby effecting local anesthetic action. Onset of action The onset of action is 3 to 5 minutes. It is ineffective when applied to intact skin.
Hemodynamics Excessive blood levels may cause changes in cardiac output, total peripheral resistance, and mean arterial pressure. These changes may be attributable to a direct depressant effect of the local anesthetic agent on various components of the cardiovascular system. Pharmacokinetics and Metabolism Lidocaine may be absorbed following topical administration to mucous membranes, its rate and extent of absorption varies depending upon concentration and total dose administered, the specific site of application, and duration of exposure.
In general, the rate of absorption of local anesthetic agents following topical application occurs most rapidly after intratracheal administration. Lidocaine is also well-absorbed from the gastrointestinal tract, but little intact drug may appear in the circulation because of biotransformation in the liver. Lidocaine is metabolized rapidly by the liver, and metabolites and unchanged drug are excreted by the kidneys.
Biotransformation includes oxidative N-dealkylation, ring hydroxylation, cleavage of the amide linkage, and conjugation. N-dealkylation, a major pathway of biotransformation, yields the metabolites monoethylglycinexylidide and glycinexylidide. The pharmacological / toxicological actions of these metabolites are similar to, but less potent than, those of lidocaine.
Approximately 90% of lidocaine administered is excreted in the form of various metabolites, and less than 10% is excreted unchanged. The primary metabolite in urine is a conjugate of 4-hydroxy-2, 6-dimethylaniline. The plasma binding of lidocaine is dependent on drug concentration, and the fraction bound decreases with increasing concentration.
At concentrations of 1 to 4 mcg of free base per mL, 60 to 80 percent of lidocaine is protein bound. Binding is also dependent on the plasma concentration of the alpha-1-acid glycoprotein. Lidocaine crosses the blood-brain and placental barriers, presumably by passive diffusion.
Studies of lidocaine metabolism following intravenous bolus injections have shown that the elimination half-life of this agent is typically 1.5 to 2 hours. Because of the rapid rate at which lidocaine is metabolized, any condition that affects liver function may alter lidocaine kinetics. The half-life may be prolonged twofold or more in patients with liver dysfunction.
Renal dysfunction does not affect lidocaine kinetics but may increase the accumulation of metabolites. Factors such as acidosis and the use of CNS stimulants and depressants affect the CNS levels of lidocaine required to produce overt systemic effects. Objective adverse manifestations become increasingly apparent with increasing venous plasma levels above 6 mcg free base per mL.
In the rhesus monkey arterial blood levels of 18 to 21 mcg/mL have been shown to be the threshold for convulsive activity.
🧬 Mechanism of Action ▾
Mechanism of action Lidocaine stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses, thereby effecting local anesthetic action.
📦 How Supplied / Storage and Handling ▾
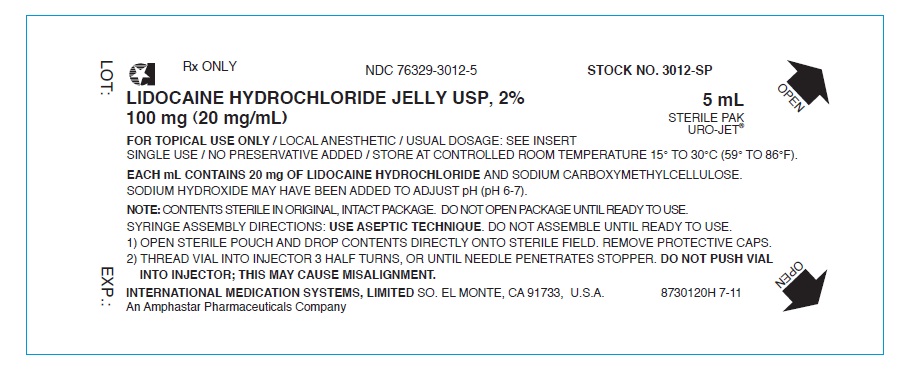
HOW SUPPLIED: Lidocaine Hydrochloride Jelly USP, 2% Box of 25 In unit use packages containing one single use vial and a URO-JET ® vial injector. Stock No. 5 mL size NDC 76329-3012-5 3012-SP 10 mL size NDC 76329-3013-5 3013-SP 20 mL size NDC 76329-3015-5 3015-SP In unit use packages containing one single use vial and a URO-JET ® AC (Anatomically Constricted) vial injector.
Box of 25 Stock No. 5 mL size NDC 76329-3011-5 3011-SP Syringe Assembly Directions Syringe Assembly Directions: USE ASEPTIC TECHNlQUE Do not assemble until ready to use. 1)Open sterile pouch and drop contents directly onto sterile field.
Remove protective caps. 2)Thread vial into injector 3 half turns, or until needle penetrates stopper.* DO NOT PUSH VIAL INTO INJECTOR; THIS MAY CAUSE MISALIGNMENT. 3)Remove cap and expel air.
Store at controlled room temperature 15° to 30°C (59° to 86°F). Figure Figure Figure
📋 Description ▾
DESCRIPTION Lidocaine Hydrochloride Jelly USP, 2% is a sterile aqueous product that contains a local anesthetic agent and is administered topically (see INDICATIONS AND USAGE for specific uses). Lidocaine Hydrochloride Jelly USP, 2% contains lidocaine hydrochloride which is chemically designated as acetamide, 2-(diethylamino)-N-(2,6-dimethylphenyl)-, monohydrochloride and has the following structural formula: Lidocaine Hydrochloride Jelly USP, 2% also contains sodium carboxymethylcellulose, and the resulting mixture maximizes contact with mucosa and provides lubrication for instrumentation.
The unused portion should be discarded after initial use. Composition of Lidocaine Hydrochloride Jelly USP, 2%: Each mL contains 20 mg of lidocaine HCI. The formulation also contains sodium carboxymethylcellulose and sodium hydroxide and/or hydrochloric acid to adjust pH between 6.0 to 7.0.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Inform patients that use of local anesthetics may cause methemoglobinemia, a serious condition that must be treated promptly. Advise patients or caregivers to seek immediate medical attention if they or someone in their care experience the following signs or symptoms: pale, gray, or blue colored skin (cyanosis); headache; rapid heart rate; shortness of breath; lightheadedness; or fatigue. When topical anesthetics are used in the mouth, the patient should be aware that the production of topical anesthesia may impair swallowing and thus enhance the danger of aspiration.
For this reason, food should not be ingested for 60 minutes following use of local anesthetic preparations in the mouth or throat area. This is particularly important in children because of their frequency of eating. Numbness of the tongue or buccal mucosa may enhance the danger of unintentional biting trauma.
Food and chewing gum should not be taken while the mouth or throat area is anesthetized.