
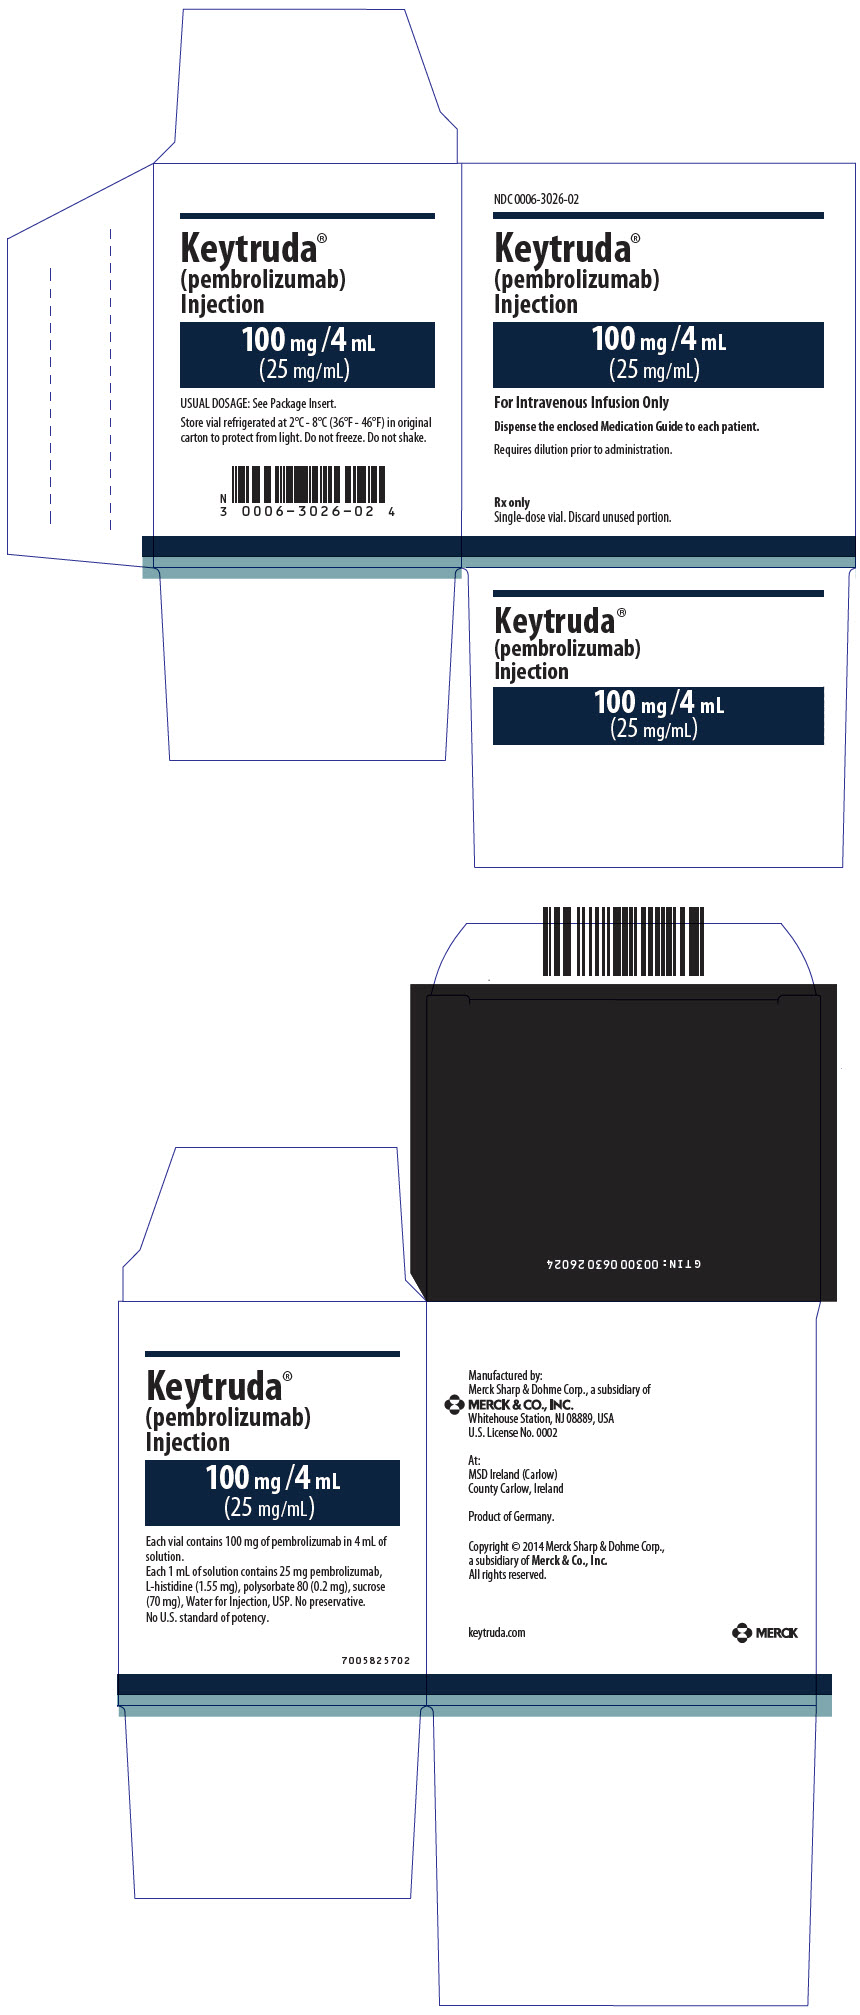
KEYTRUDA pembrolizumab 25 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Programmed Death Receptor-1 Blocking Antibody class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Pembrolizumab injection is used alone or with other drugs to treat a variety of solid tumor, soft tissue and blood cancers. Pembrolizumab injection is in a class of medications called monoclonal antibodies. It works by helping your immune system to slow or stop the growth of cancer cells.
Read the full MedlinePlus article ↗- Great question — it's a very different approach. Chemo directly attacks fast-growing cells, including cancer cells. Pembrolizumab is immunotherapy: it doesn't target the cancer its...
- What exactly is pembrolizumab and how is it different from regular chemotherapy?
- Each infusion takes about 30 minutes once it's running, though you'll spend extra time at the clinic for preparation and monitoring. Depending on your treatment plan, it's given ev...
- How often will I need to come in for infusions, and how long does each one take?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Pembrolizumab — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
1.55 mg / 1 mL
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
0.2 mg / 1 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
70 mg / 1 mL
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,282.81 | $10,262.50 / 8 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9271 | $60.645 / J9271 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Keytruda 25 mg/mLthis 00006-3026-04 | Merck | 2 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Sep 4, 2026 |
Is there a biosimilar for KEYTRUDA 100 MG/4 ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00006-3026-02 | 1 VIAL in 1 CARTON (0006-3026-02) / 4 mL in 1 VIAL (0006-3026-01) | 2015-01-15 | Active |
| 00006-3026-04 You're viewing this | 2 VIAL in 1 CARTON (0006-3026-04) / 4 mL in 1 VIAL (0006-3026-01) | 2019-08-01 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 68% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00006-3026-04?
What NDC number is used to bill for this package of KEYTRUDA pembrolizumab 25 mg/mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE KEYTRUDA is a programmed death receptor-1 (PD-1)-blocking antibody indicated: Melanoma for the treatment of patients with unresectable or metastatic melanoma. ( 1.1 ) for the adjuvant treatment of adult and pediatric (12 years and older) patients with Stage IIB, IIC, or III melanoma following complete resection. ( 1.1 ) Non-Small Cell Lung Cancer (NSCLC) in combination with pemetrexed and platinum chemotherapy, as first-line treatment of patients with metastatic nonsquamous NSCLC, with no EGFR or ALK genomic tumor aberrations.
( 1.2 ) in combination with carboplatin and either paclitaxel or paclitaxel protein-bound, as first-line treatment of patients with metastatic squamous NSCLC. ( 1.2 ) as a single agent for the first-line treatment of patients with NSCLC expressing PD-L1 [Tumor Proportion Score (TPS) ≥1%] as determined by an FDA-authorized test, with no EGFR or ALK genomic tumor aberrations, and is: Stage III where patients are not candidates for surgical resection or definitive chemoradiation, or metastatic. ( 1.2 , 2.1 ) as a single agent for the treatment of patients with metastatic NSCLC whose tumors express PD-L1 (TPS ≥1%) as determined by an FDA-authorized test, with disease progression on or after platinum-containing chemotherapy.
Patients with EGFR or ALK genomic tumor aberrations should have disease progression on FDA-approved therapy for these aberrations prior to receiving KEYTRUDA. ( 1.2 , 2.1 ) for the treatment of patients with resectable (tumors ≥4 cm or node positive) NSCLC in combination with platinum-containing chemotherapy as neoadjuvant treatment, and then continued as a single agent as adjuvant treatment after surgery. ( 1.2 ) as a single agent, for adjuvant treatment following resection and platinum-based chemotherapy for adult patients with Stage IB (T2a ≥4 cm), II, or IIIA NSCLC.
( 1.2 ) Malignant Pleural Mesothelioma (MPM) in combination with pemetrexed and platinum chemotherapy, as first-line treatment of adult patients with unresectable advanced or metastatic MPM. ( 1.3 ) Head and Neck Squamous Cell Cancer (HNSCC) for the treatment of adult patients with resectable locally advanced HNSCC whose tumors express PD-L1 [Combined Positive Score (CPS) ≥1] as determined by an FDA-authorized test, as a single agent as neoadjuvant treatment, continued as adjuvant treatment in combination with radiotherapy (RT) with or without cisplatin and then as a single agent.
( 1.4 ) in combination with platinum and FU for the first-line treatment of patients with metastatic or with unresectable, recurrent HNSCC. ( 1.4 ) as a single agent for the first-line treatment of patients with metastatic or with unresectable, recurrent HNSCC whose tumors express PD-L1 [Combined Positive Score (CPS) ≥1] as determined by an FDA-authorized test. ( 1.4 , 2.1 ) as a single agent for the treatment of patients with recurrent or metastatic HNSCC with disease progression on or after platinum-containing chemotherapy.
( 1.4 ) Classical Hodgkin Lymphoma (cHL) for the treatment of adult patients with relapsed or refractory cHL. ( 1.5 ) for the treatment of pediatric patients with refractory cHL, or cHL that has relapsed after 2 or more lines of therapy. ( 1.5 ) Primary Mediastinal Large B-Cell Lymphoma (PMBCL) for the treatment of adult and pediatric patients with refractory PMBCL, or who have relapsed after 2 or more prior lines of therapy.
( 1.6 ) Limitations of Use : KEYTRUDA is not recommended for treatment of patients with PMBCL who require urgent cytoreductive therapy. Urothelial Cancer in combination with enfortumab vedotin-ejfv, for the treatment of adult patients with locally advanced or metastatic urothelial cancer. ( 1.7 ) as a single agent for the treatment of patients with locally advanced or metastatic urothelial carcinoma who: are not eligible for any platinum-containing chemotherapy, or who have disease progression during or following platinum-containing chemotherapy or within 12 months of neoadjuvant…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Melanoma: 200 mg every 3 weeks or 400 mg every 6 weeks; 2 mg/kg (up to 200 mg) every 3 weeks for pediatrics. ( 2.2 ) NSCLC: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) MPM: 200 mg every 3 weeks or 400 mg every 6 weeks.
( 2.2 ) HNSCC: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) cHL or PMBCL: 200 mg every 3 weeks or 400 mg every 6 weeks for adults; 2 mg/kg (up to 200 mg) every 3 weeks for pediatrics. ( 2.2 ) Urothelial Cancer: 200 mg every 3 weeks or 400 mg every 6 weeks.
( 2.2 ) MSI-H or dMMR Cancer: 200 mg every 3 weeks or 400 mg every 6 weeks for adults; 2 mg/kg (up to 200 mg) every 3 weeks for pediatrics. ( 2.2 ) MSI-H or dMMR CRC: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) Gastric Cancer: 200 mg every 3 weeks or 400 mg every 6 weeks.
( 2.2 ) Esophageal Cancer: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) Cervical Cancer: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) HCC: 200 mg every 3 weeks or 400 mg every 6 weeks.
( 2.2 ) BTC: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) MCC: 200 mg every 3 weeks or 400 mg every 6 weeks for adults; 2 mg/kg (up to 200 mg) every 3 weeks for pediatrics. ( 2.2 ) RCC: 200 mg every 3 weeks or 400 mg every 6 weeks as a single agent in the adjuvant setting, or in the advanced setting with either: axitinib 5 mg orally twice daily or lenvatinib 20 mg orally once daily.
( 2.2 ) ccRCC: 200 mg every 3 weeks or 400 mg every 6 weeks in combination with belzutifan 120 mg orally once daily in the adjuvant setting. ( 2.2 ) Endometrial Carcinoma: 200 mg every 3 weeks or 400 mg every 6 weeks in combination with carboplatin and paclitaxel regardless of MMR or MSI status, or in combination with lenvatinib 20 mg orally once daily for pMMR or not MSI-H tumors, or as a single agent for MSI-H or dMMR tumors. ( 2.2 ) TMB-H Cancer: 200 mg every 3 weeks or 400 mg every 6 weeks for adults; 2 mg/kg (up to 200 mg) every 3 weeks for pediatrics.
( 2.2 ) cSCC: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) TNBC: 200 mg every 3 weeks or 400 mg every 6 weeks. ( 2.2 ) Ovarian cancer: 200 mg every 3 weeks or 400 mg every 6 weeks.
( 2.2 ) Administer KEYTRUDA as an intravenous infusion over 30 minutes after dilution. ( 2.4 ) See Full Prescribing Information for dosage modifications for adverse reactions and preparation and administration instructions. ( 2.3 , 2.4 )
2.1Patient Selection Information on FDA-authorized tests for patient selection is available at: http://www.fda.gov/CompanionDiagnostics . Patient Selection for Single-Agent Treatment Select patients for treatment with KEYTRUDA as a single agent based on the presence of positive PD-L1 expression in: Stage III NSCLC who are not candidates for surgical resection or definitive chemoradiation [see Clinical Studies (14.2) ] . metastatic NSCLC [see Clinical Studies (14.2) ]. first-line treatment of metastatic or unresectable, recurrent HNSCC [see Clinical Studies (14.4) ] . previously treated recurrent locally advanced or metastatic esophageal cancer [see Clinical Studies (14.11) ] . recurrent or metastatic cervical cancer with disease progression on or after chemotherapy [see Clinical Studies (14.12) ] .
For the MSI-H/dMMR indications, select patients for treatment with KEYTRUDA as a single agent based on MSI-H/dMMR status in tumor specimens [see Clinical Studies (14.8 , 14.9) ]. For the TMB-H indication, select patients for treatment with KEYTRUDA as a single agent based on TMB-H status in tumor specimens [see Clinical Studies (14.18) ]. Because subclonal dMMR mutations and microsatellite instability may arise in high-grade gliomas during temozolomide therapy, it is recommended to test for TMB-H, MSI-H, and dMMR in the primary tumor specimens obtained prior to initiation of temozolomide chemotherapy in patients with high-grade gliomas.
Additional Patient Selection Information for MSI-H or dMMR in Patients with non-CRC Solid Tumors Due to discordance between local tests and FDA-auth…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 100 mg/4 mL (25 mg/mL) clear to slightly opalescent, colorless to slightly yellow solution in a single-dose vial Injection: 100 mg/4 mL (25 mg/mL) solution in a single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Immune-Mediated Adverse Reactions ( 5.1 ) Immune-mediated adverse reactions, which may be severe or fatal, can occur in any organ system or tissue, including the following: immune-mediated pneumonitis, immune-mediated colitis, immune-mediated hepatitis, immune-mediated endocrinopathies, immune-mediated nephritis with renal dysfunction, immune-mediated dermatologic adverse reactions, and solid organ transplant rejection. Monitor for early identification and management. Evaluate liver enzymes, creatinine, and thyroid function at baseline and periodically during treatment.
Withhold or permanently discontinue based on severity and type of reaction. Infusion-related reactions: Interrupt, slow the rate of infusion, or permanently discontinue KEYTRUDA based on the severity of reaction. ( 5.2 ) Complications of allogeneic HSCT: Fatal and other serious complications can occur in patients who receive allogeneic HSCT before or after being treated with a PD-1/PD-L1 blocking antibody.
( 5.3 ) Treatment of patients with multiple myeloma with a PD-1 or PD-L1 blocking antibody in combination with a thalidomide analogue plus dexamethasone is not recommended outside of controlled clinical trials. ( 5.4 ) Embryo-Fetal toxicity: Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective method of contraception.
( 5.5 , 8.1 , 8.3 )
5.1Severe and Fatal Immune-Mediated Adverse Reactions KEYTRUDA is a monoclonal antibody that belongs to a class of drugs that bind to either the programmed death-receptor 1 (PD-1) or the PD-ligand 1 (PD-L1), blocking the PD-1/PD-L1 pathway, thereby removing inhibition of the immune response, potentially breaking peripheral tolerance and inducing immune-mediated adverse reactions. Important immune-mediated adverse reactions listed under WARNINGS AND PRECAUTIONS may not include all possible severe and fatal immune-mediated adverse reactions.
Immune-mediated adverse reactions, which may be severe or fatal, can occur in any organ system or tissue and can affect more than one body system simultaneously. Immune-mediated adverse reactions can occur at any time after starting treatment with a PD-1/PD-L1 blocking antibody. While immune-mediated adverse reactions usually manifest during treatment with PD-1/PD-L1 blocking antibodies, immune-mediated adverse reactions can also manifest after discontinuation of PD-1/PD-L1 blocking antibodies.
Early identification and management of immune-mediated adverse reactions are essential to ensure safe use of PD-1/PD-L1 blocking antibodies. Monitor patients closely for symptoms and signs that may be clinical manifestations of underlying immune-mediated adverse reactions. Evaluate liver enzymes, creatinine, and thyroid function at baseline and periodically during treatment.
For patients with TNBC treated with KEYTRUDA in the neoadjuvant setting, monitor blood cortisol at baseline, prior to surgery, and as clinically indicated. In cases of suspected immune-mediated adverse reactions, initiate appropriate workup to exclude alternative etiologies, including infection. Institute medical management promptly, including specialty consultation as appropriate.
Withhold or permanently discontinue KEYTRUDA depending on severity [see Dosage and Administration (2.3) ] . In general, if KEYTRUDA requires interruption or discontinuation, administer systemic corticosteroid therapy (1 to 2 mg/kg/day prednisone or equivalent) until improvement to Grade 1 or less. Upon improvement to Grade 1 or less, initiate corticosteroid taper and continue to taper over at least 1 month.
Consider administration of other systemic immunosuppressants in patients whose immune-mediated adverse reactions are not controlled with corticosteroid therapy. Toxicity management guidelines for adverse reactions that do not necessarily require systemic steroids (e.g., endocrinopathies and dermatologic reactions) are discussed below. Immune-Mediated Pneumoni…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling. Severe and fatal immune-mediated adverse reactions [see Warnings and Precautions (5.1) ] . Infusion-related reactions [see Warnings and Precautions (5.2) ].
Most common adverse reactions (reported in ≥20% of patients) were: KEYTRUDA as a single agent: fatigue, musculoskeletal pain, rash, diarrhea, pyrexia, cough, decreased appetite, pruritus, dyspnea, constipation, pain, abdominal pain, nausea, and hypothyroidism. ( 6.1 ) KEYTRUDA in combination with chemotherapy or chemoradiotherapy: fatigue/asthenia, nausea, constipation, diarrhea, decreased appetite, rash, vomiting, cough, dyspnea, pyrexia, alopecia, peripheral neuropathy, mucosal inflammation, stomatitis, headache, weight loss, abdominal pain, arthralgia, myalgia, insomnia, palmar-plantar erythrodysesthesia, urinary tract infection, hypothyroidism, radiation skin injury, dysphagia, dry mouth, and musculoskeletal pain.
( 6.1 ) KEYTRUDA in combination with chemotherapy and bevacizumab: peripheral neuropathy, alopecia, anemia, fatigue/asthenia, nausea, neutropenia, diarrhea, hypertension, thrombocytopenia, constipation, arthralgia, vomiting, urinary tract infection, rash, leukopenia, hypothyroidism, decreased appetite, pyrexia, epistaxis, decreased white blood cell count, and stomatitis. ( 6.1 ) KEYTRUDA in combination with axitinib: diarrhea, fatigue/asthenia, hypertension, hepatotoxicity, hypothyroidism, decreased appetite, palmar-plantar erythrodysesthesia, nausea, stomatitis/mucosal inflammation, dysphonia, rash, cough, and constipation.
( 6.1 ) KEYTRUDA in combination with lenvatinib: hypothyroidism, hypertension, fatigue, diarrhea, musculoskeletal disorders, nausea, decreased appetite, vomiting, stomatitis, weight loss, abdominal pain, urinary tract infection, proteinuria, constipation, headache, hemorrhagic events, palmar-plantar erythrodysesthesia, dysphonia, rash, hepatotoxicity, and acute kidney injury. ( 6.1 ) KEYTRUDA in combination with belzutifan (reported in ≥25% of patients): decreased hemoglobin, increased alanine aminotransferase, fatigue, increased aspartate aminotransferase, decreased lymphocytes, and increased alkaline phosphatase.
( 6.1 ) KEYTRUDA in combination with enfortumab vedotin-ejfv: rash, peripheral neuropathy, fatigue, pruritus, diarrhea, alopecia, weight loss, decreased appetite, dry eye, nausea, constipation, dysgeusia, and urinary tract infection. ( 6.1 ) KEYTRUDA in combination with sacituzumab govitecan-hziy: anemia, neutropenia, diarrhea, nausea, fatigue, alopecia, constipation, rash, vomiting, headache and abdominal pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described in the WARNINGS AND PRECAUTIONS reflect exposure to KEYTRUDA as a single agent in 2799 patients in three randomized, open-label, active-controlled trials (KEYNOTE-002, KEYNOTE-006, and KEYNOTE-010), which enrolled 912 patients with melanoma and 682 patients with NSCLC, and one single-arm trial (KEYNOTE-001), which enrolled 655 patients with melanoma and 550 patients with NSCLC.
In addition to the 2799 patients, certain subsections in the WARNINGS AND PRECAUTIONS describe adverse reactions observed with exposure to KEYTRUDA as a single agent in a randomized, placebo-controlled trial (KEYNOTE-091), which enrolled 580 patients with resected NSCLC, a non-randomized, open-label, multi-cohort trial (KEYNOTE-012), a non-randomized, open-label, single-cohort trial (KEYNOTE-055), and two randomized, open-label, active-controlled trials (KEYNOTE-040 and KEYNOTE-04…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on its mechanism of action, KEYTRUDA can cause fetal harm when administered to a pregnant woman. There are no available human data informing the risk of embryo-fetal toxicity. In animal models, the PD-1/PD-L1 signaling pathway is important in the maintenance of pregnancy through induction of maternal immune tolerance to fetal tissue (see Data ) .
Human IgG4 (immunoglobulins) are known to cross the placenta; therefore, pembrolizumab has the potential to be transmitted from the mother to the developing fetus. Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data Animal reproduction studies have not been conducted with KEYTRUDA to evaluate its effect on reproduction and fetal development. A literature-based assessment of the effects of the PD-1 pathway on reproduction demonstrated that a central function of the PD-1/PD-L1 pathway is to preserve pregnancy by maintaining maternal immune tolerance to the fetus. Blockade of PD-L1 signaling has been shown in murine models of pregnancy to disrupt tolerance to the fetus and to result in an increase in fetal loss; therefore, potential risks of administering KEYTRUDA during pregnancy include increased rates of abortion or stillbirth.
As reported in the literature, there were no malformations related to the blockade of PD-1 signaling in the offspring of these animals; however, immune-mediated disorders occurred in PD-1 knockout mice. Based on its mechanism of action, fetal exposure to pembrolizumab may increase the risk of developing immune-mediated disorders or of altering the normal immune response.
8.2Lactation Risk Summary There are no data on the presence of pembrolizumab in either animal or human milk or its effects on the breastfed child or on milk production. Maternal IgG is known to be present in human milk. The effects of local gastrointestinal exposure and limited systemic exposure in the breastfed child to KEYTRUDA are unknown.
Because of the potential for serious adverse reactions in breastfed children, advise women not to breastfeed during treatment with KEYTRUDA and for 4 months after the last dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating KEYTRUDA [see Use in Specific Populations (8.1) ]. Contraception KEYTRUDA can cause fetal harm when administered to a pregnant woman [see Warnings and Precautions (5.5) , Use in Specific Populations (8.1) ]. Advise females of reproductive potential to use effective contraception during treatment with KEYTRUDA and for 4 months after the last dose.
8.4Pediatric Use The safety and effectiveness of KEYTRUDA as a single agent have been established in pediatric patients with melanoma, cHL, PMBCL, MCC, MSI-H or dMMR cancer, and TMB-H cancer. Use of KEYTRUDA in pediatric patients for these indications is supported by evidence from adequate and well-controlled studies in adults with additional pharmacokinetic and safety data in pediatric patients [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.1 , 14.5 , 14.6 , 14.8 , 14.15 , 14.18) ] .
In KEYNOTE-051, 173 pediatric patients (65 pediatric patients aged 6 months to younger than 12 years and 108 pediatric patients aged 12 to 17 years) with advanced melanoma, lymphoma, or PD-L1 positive or MSI-H solid tumors received KEYTRUDA 2 mg/kg every 3 weeks. The median duration of exposure was 2.1 months (range: 1 day to 25 months). Adverse reactions that occurred at a ≥10% higher rate in pediatric patients when compared to adults included pyrexia (33%), vomiting (29%), headache (25%), abdominal pain (23%), decreased lymphocyte count (13%), and decreased white blood cell count…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action, KEYTRUDA can cause fetal harm when administered to a pregnant woman. There are no available human data informing the risk of embryo-fetal toxicity. In animal models, the PD-1/PD-L1 signaling pathway is important in the maintenance of pregnancy through induction of maternal immune tolerance to fetal tissue (see Data ) .
Human IgG4 (immunoglobulins) are known to cross the placenta; therefore, pembrolizumab has the potential to be transmitted from the mother to the developing fetus. Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data Animal reproduction studies have not been conducted with KEYTRUDA to evaluate its effect on reproduction and fetal development. A literature-based assessment of the effects of the PD-1 pathway on reproduction demonstrated that a central function of the PD-1/PD-L1 pathway is to preserve pregnancy by maintaining maternal immune tolerance to the fetus. Blockade of PD-L1 signaling has been shown in murine models of pregnancy to disrupt tolerance to the fetus and to result in an increase in fetal loss; therefore, potential risks of administering KEYTRUDA during pregnancy include increased rates of abortion or stillbirth.
As reported in the literature, there were no malformations related to the blockade of PD-1 signaling in the offspring of these animals; however, immune-mediated disorders occurred in PD-1 knockout mice. Based on its mechanism of action, fetal exposure to pembrolizumab may increase the risk of developing immune-mediated disorders or of altering the normal immune response.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of KEYTRUDA as a single agent have been established in pediatric patients with melanoma, cHL, PMBCL, MCC, MSI-H or dMMR cancer, and TMB-H cancer. Use of KEYTRUDA in pediatric patients for these indications is supported by evidence from adequate and well-controlled studies in adults with additional pharmacokinetic and safety data in pediatric patients [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.1 , 14.5 , 14.6 , 14.8 , 14.15 , 14.18) ] .
In KEYNOTE-051, 173 pediatric patients (65 pediatric patients aged 6 months to younger than 12 years and 108 pediatric patients aged 12 to 17 years) with advanced melanoma, lymphoma, or PD-L1 positive or MSI-H solid tumors received KEYTRUDA 2 mg/kg every 3 weeks. The median duration of exposure was 2.1 months (range: 1 day to 25 months). Adverse reactions that occurred at a ≥10% higher rate in pediatric patients when compared to adults included pyrexia (33%), vomiting (29%), headache (25%), abdominal pain (23%), decreased lymphocyte count (13%), and decreased white blood cell count (11%).
Laboratory abnormalities that occurred at a ≥10% higher rate in pediatric patients when compared to adults were leukopenia (30%), neutropenia (28%), thrombocytopenia (22%), and Grade 3 anemia (17%). The safety and effectiveness of KEYTRUDA in pediatric patients have not been established in the other approved indications [see Indications and Usage (1) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of 3781 patients with melanoma, NSCLC, HNSCC, or urothelial carcinoma who were treated with KEYTRUDA in clinical studies, 48% were 65 years and over and 17% were 75 years and over. No overall differences in safety or effectiveness were observed between elderly patients and younger patients. Of 389 adult patients with cHL who were treated with KEYTRUDA in clinical studies, 46 (12%) were 65 years and over.
Patients aged 65 years and over had a higher incidence of serious adverse reactions (50%) than patients aged younger than 65 years (24%). Clinical studies of KEYTRUDA in cHL did not include sufficient numbers of patients aged 65 years and over to determine whether effectiveness differs from that in younger patients. Of 506 adult patients with Stage IB (T2a ≥4 cm), II, or IIIA NSCLC following complete resection and platinum-based chemotherapy who were treated with KEYTRUDA in KEYNOTE-091, 242 (48%) were 65 years and over.
No overall differences in safety or effectiveness were observed between elderly patients and younger patients. Of 596 adult patients with TNBC who were treated with KEYTRUDA in combination with paclitaxel, paclitaxel protein-bound, or gemcitabine and carboplatin in KEYNOTE-355, 137 (23%) were 65 years and over. No overall differences in safety or effectiveness were observed between elderly patients and younger patients.
Of 221 adult patients with TNBC who were treated with KEYTRUDA in combination with sacituzumab govitecan-hziy in KEYNOTE-D19, 26% of patients were 65 years and over and 5% were 75 years and older. No overall differences in effectiveness were observed between elderly patients and younger patients. There was a higher rate of serious adverse reactions in patients aged 65 years or older (48%) compared with younger adult patients (34%).
Of 406 adult patients with endometrial carcinoma who were treated with KEYTRUDA in combination with lenvatinib in KEYNOTE-775, 201 (50%) were 65 years and over. No overall differences in safety or effectiveness were observed between elderly patients and younger patients. Of the 564 patients with locally advanced or metastatic urothelial cancer treated with KEYTRUDA in combination with enfortumab vedotin-ejfv, 44% (n=247) were 65-74 years and 26% (n=144) were 75 years or older.
No overall differences in effectiveness were observed between patients 65 years of age or older and younger patients. Patients 75 years of age or older treated with KEYTRUDA in combination with enfortumab vedotin-ejfv experienced a higher incidence of fatal adverse reactions than younger patients. The incidence of fatal adverse reactions was 4% in patients younger than 75 and 7% in patients 75 years or older.
Of the 570 patients with MIBC treated with KEYTRUDA in combination with enfortumab vedotin-ejfv, 45% (n=259) were 65-74 years and 22% (n=125) were 75 years or older. No overall differences in effectiveness were observed between patients 65 years of age or older and younger patients. Patients 75 years of age or older treated with KEYTRUDA in combination with enfortumab vedotin-ejfv experienced a higher incidence of fatal adverse reactions than younger patients.
The incidence of fatal adverse reactions was 3.6% in patients younger than 75 and 11% in patients 75 years or older. Of the 432 patients randomized to KEYTRUDA in combination with axitinib in the KEYNOTE-426 trial, 40% were 65 years or older. No overall difference in safety or efficacy was reported between patients who were ≥65 years of age and younger.
Of 294 adult patients with FIGO 2014 Stage III-IVA cervical cancer who were treated with KEYTRUDA in combination with CRT in KEYNOTE-A18, 42 (14%) were 65 years and over. No overall difference in safety was observed between patients ≥65 years of age and younger patients. Of 643 adult patients with ovarian cancer who were treated with KEYTRUDA in combination with paclitaxel with or without bevacizumab in KEYNOTE-B96, 236 (37%) were 65 years and over and 58 (9%) were 7…
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Binding of the PD-1 ligands, PD-L1 and PD-L2, to the PD-1 receptor found on T cells, inhibits T cell proliferation and cytokine production. Upregulation of PD-1 ligands occurs in some tumors and signaling through this pathway can contribute to inhibition of active T-cell immune surveillance of tumors. Pembrolizumab is a monoclonal antibody that binds to the PD-1 receptor and blocks its interaction with PD-L1 and PD-L2, releasing PD-1 pathway-mediated inhibition of the immune response, including the anti-tumor immune response.
In syngeneic mouse tumor models, blocking PD-1 activity resulted in decreased tumor growth. In syngeneic mouse tumor models, combination treatment of a PD-1 blocking antibody and kinase inhibitor lenvatinib decreased tumor-associated macrophages, increased activated cytotoxic T cells, and reduced tumor growth compared to either treatment alone.
12.2Pharmacodynamics There are no clinically significant exposure-response relationships for efficacy or safety at pembrolizumab dosages of 200 mg or 2 mg/kg every 3 weeks and 400 mg every 6 weeks regardless of cancer type based on observed data in adult patients with melanoma, cHL, and PMBCL.
12.3Pharmacokinetics The pharmacokinetics (PK) of pembrolizumab was characterized using a population PK analysis with concentration data collected from 2993 patients with various cancers who received pembrolizumab doses of 1 to 10 mg/kg every 2 weeks, 2 to 10 mg/kg every 3 weeks, or 200 mg every 3 weeks. Steady-state concentrations of pembrolizumab were reached by 16 weeks of repeated dosing with an every 3-week regimen and the systemic accumulation was 2.1-fold. The peak concentration (C max ), trough concentration (C min ), and area under the plasma concentration versus time curve at steady state (AUC ss ) of pembrolizumab increased dose proportionally in the dose range: of 2 to 10 mg/kg every 3 weeks.
Distribution The geometric mean value (CV%) for volume of distribution at steady state is
6.0L (20%). Elimination Pembrolizumab clearance (CV%) is approximately 23% lower [geometric mean, 195 mL/day (40%)] at steady state than that after the first dose [252 mL/day (37%)]; this decrease in clearance with time is not considered clinically important. The terminal half-life (t 1/2 ) is 22 days (32%).
Specific Populations The following factors had no clinically important effect on the CL of pembrolizumab: age (range: 15 to 94 years), sex, race (89% White), renal impairment (eGFR ≥15 mL/min/1.73 m 2 ), mild to moderate hepatic impairment (total bilirubin ≤3 times ULN and any AST), or tumor burden. The impact of severe hepatic impairment (total bilirubin >3 times ULN and any AST) on the pharmacokinetics of pembrolizumab is unknown. Pediatric Patients: Pembrolizumab concentrations with weight-based dosing at 2 mg/kg every 3 weeks in pediatric patients (10 months to 17 years) are comparable to those of adults at the same dose.
12.6Immunogenicity The observed incidence of anti-drug antibodies (ADA) is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of ADA in the studies described in this section with the incidence of ADA in other studies, including those of KEYTRUDA or of other pembrolizumab products. Trough levels of pembrolizumab interfere with the electrochemiluminescent (ECL) assay results; therefore, a subset analysis was performed in the KEYTRUDA-treated patients with a pembrolizumab concentration below the drug tolerance level of the ADA assay.
In clinical studies in patients treated with KEYTRUDA at a dosage of 2 mg/kg every 3 weeks, 200 mg every 3 weeks, or 10 mg/kg every 2 or 3 weeks, 27 (2.1%) of 1,289 evaluable patients tested positive for treatment-emergent anti-pembrolizumab antibodies of whom 6 (0.5%) patients had neutralizing antibodies against pembrolizumab. There were no identified clinically significant effects of ADA o…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Binding of the PD-1 ligands, PD-L1 and PD-L2, to the PD-1 receptor found on T cells, inhibits T cell proliferation and cytokine production. Upregulation of PD-1 ligands occurs in some tumors and signaling through this pathway can contribute to inhibition of active T-cell immune surveillance of tumors. Pembrolizumab is a monoclonal antibody that binds to the PD-1 receptor and blocks its interaction with PD-L1 and PD-L2, releasing PD-1 pathway-mediated inhibition of the immune response, including the anti-tumor immune response.
In syngeneic mouse tumor models, blocking PD-1 activity resulted in decreased tumor growth. In syngeneic mouse tumor models, combination treatment of a PD-1 blocking antibody and kinase inhibitor lenvatinib decreased tumor-associated macrophages, increased activated cytotoxic T cells, and reduced tumor growth compared to either treatment alone.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING KEYTRUDA injection (clear to slightly opalescent, colorless to slightly yellow solution): Carton containing one 100 mg/4 mL (25 mg/mL), single-dose vial (NDC 0006-3026-02) Carton containing two 100 mg/4 mL (25 mg/mL), single-dose vials (NDC 0006-3026-04) Store vials under refrigeration at 2°C to 8°C (36°F to 46°F) in original carton to protect from light. Do not freeze. Do not shake.
📦 Storage and Handling ▾
Store vials under refrigeration at 2°C to 8°C (36°F to 46°F) in original carton to protect from light. Do not freeze. Do not shake.
📋 Description ▾
11 DESCRIPTION Pembrolizumab is a programmed death receptor-1 (PD 1)-blocking antibody. Pembrolizumab is a humanized monoclonal IgG4 kappa antibody with an approximate molecular weight of 149 kDa. Pembrolizumab is produced in recombinant Chinese hamster ovary (CHO) cells.
KEYTRUDA (pembrolizumab) injection is a sterile, preservative-free, clear to slightly opalescent, colorless to slightly yellow solution for intravenous use. Each vial contains 100 mg of pembrolizumab in 4 mL of solution. Each 1 mL of solution contains 25 mg of pembrolizumab and is formulated in: L-histidine (1.55 mg), polysorbate 80 (0.2 mg), sucrose (70 mg), and Water for Injection, USP.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Immune-Mediated Adverse Reactions Inform patients of the risk of immune-mediated adverse reactions that may be severe or fatal, may occur after discontinuation of treatment, and may require corticosteroid treatment and interruption or discontinuation of KEYTRUDA. These reactions may include: Pneumonitis: Advise patients to contact their healthcare provider immediately for new or worsening cough, chest pain, or shortness of breath [see Warnings and Precautions (5.1) ] .
Colitis: Advise patients to contact their healthcare provider immediately for diarrhea or severe abdominal pain [see Warnings and Precautions (5.1) ] . Hepatitis: Advise patients to contact their healthcare provider immediately for jaundice, severe nausea or vomiting, or easy bruising or bleeding [see Warnings and Precautions (5.1) ] . Endocrinopathies: Advise patients to contact their healthcare provider immediately for signs or symptoms of adrenal insufficiency, hypophysitis, hypothyroidism, hyperthyroidism, or Type 1 diabetes mellitus [see Warnings and Precautions (5.1) ] .
Nephritis: Advise patients to contact their healthcare provider immediately for signs or symptoms of nephritis [see Warnings and Precautions (5.1) ] . Severe skin reactions: Advise patients to contact their healthcare provider immediately for any signs or symptoms of severe skin reactions, SJS or TEN [see Warnings and Precautions (5.1) ] . Other immune-mediated adverse reactions: Advise patients that immune-mediated adverse reactions can occur and may involve any organ system, and to contact their healthcare provider immediately for any new or worsening signs or symptoms [see Warnings and Precautions (5.1) ] .
Advise patients of the risk of solid organ transplant rejection and other transplant (including corneal graft) rejection. Advise patients to contact their healthcare provider immediately for signs or symptoms of organ transplant rejection and other transplant (including corneal graft) rejection [see Warnings and Precautions (5.1) ] . Infusion-Related Reactions Advise patients to contact their healthcare provider immediately for signs or symptoms of infusion-related reactions [see Warnings and Precautions (5.2) ] .
Complications of Allogeneic HSCT Advise patients of the risk of post-allogeneic hematopoietic stem cell transplantation complications [see Warnings and Precautions (5.3) ]. Embryo-Fetal Toxicity Advise females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.5) , Use in Specific Populations (8.1 , 8.3) ]. Advise females of reproductive potential to use effective contraception during treatment with KEYTRUDA and for 4 months after the last dose [see Warnings and Precautions (5.5) , Use in Specific Populations (8.1 , 8.3) ] .
Lactation Advise women not to breastfeed during treatment with KEYTRUDA and for 4 months after the last dose [see Use in Specific Populations (8.2) ] . Laboratory Tests Advise patients of the importance of keeping scheduled appointments for blood work or other laboratory tests [see Warnings and Precautions (5.1) ] .
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: July 2026 MEDICATION GUIDE KEYTRUDA ® (key-true-duh) (pembrolizumab) injection, for intravenous use What is the most important information I should know about KEYTRUDA?
KEYTRUDA is a medicine that may treat certain cancers by working with your immune system. KEYTRUDA can cause your immune system to attack normal organs and tissues in any area of your body and can affect the way they work. These problems can sometimes become severe or life-threatening and can lead to death.
You can have more than one of these problems at the same time. These problems may happen anytime during treatment or even after your treatment has ended. Call or see your healthcare provider right away if you develop any new or worsening signs or symptoms, including: Lung problems cough shortness of breath chest pain Intestinal problems diarrhea (loose stools) or more frequent bowel movements than usual stools that are black, tarry, sticky, or have blood or mucus severe stomach-area (abdomen) pain or tenderness Liver problems yellowing of your skin or the whites of your eyes severe nausea or vomiting pain on the right side of your stomach area (abdomen) dark urine (tea colored) bleeding or bruising more easily than normal Hormone gland problems headaches that will not go away or unusual headaches eye sensitivity to light eye problems rapid heartbeat increased sweating extreme tiredness weight gain or weight loss feeling more hungry or thirsty than usual urinating more often than usual hair loss feeling cold constipation your voice gets deeper dizziness or fainting changes in mood or behavior, such as decreased sex drive, irritability, or forgetfulness Kidney problems decrease in your amount of urine blood in your urine swelling of your ankles loss of appetite Skin problems rash itching skin blistering or peeling painful sores or ulcers in your mouth or in your nose, throat, or genital area fever or flu-like symptoms swollen lymph nodes Problems can also happen in other organs and tissues.
These are not all of the signs and symptoms of immune system problems that can happen with KEYTRUDA. Call or see your healthcare provider right away for any new or worsening signs or symptoms, which may include: chest pain, irregular heartbeat, shortness of breath, swelling of ankles confusion, sleepiness, memory problems, changes in mood or behavior, stiff neck, balance problems, tingling or numbness of the arms or legs double vision, blurry vision, sensitivity to light, eye pain, changes in eyesight persistent or severe muscle pain or weakness, muscle cramps low red blood cells, bruising Infusion reactions that can sometimes be severe or life-threatening.
Signs and symptoms of infusion reactions may include: chills or shaking itching or rash flushing shortness of breath or wheezing dizziness feeling like passing out fever back pain Rejection of a transplanted organ or tissue. Your healthcare provider should tell you what signs and symptoms you should report and monitor you depending on the type of organ or tissue transplant that you have had. Complications, including graft-versus-host-disease (GVHD), in people who have received a bone marrow (stem cell) transplant that uses donor stem cells (allogeneic).
These complications can be serious and can lead to death. These complications may happen if you underwent transplantation either before or after being treated with KEYTRUDA. Your healthcare provider will monitor you for these complications.
Getting medical treatment right away may help keep these problems from becoming more serious. Your healthcare provider will check you for these problems during treatment with KEYTRUDA. Your healthcare provider may treat you with corticosteroid or hormone replacement medicines.
Your healthcare provider may also need to delay or completely stop treatment with KEYTRUDA if you have severe side effects. What is KEYTRUDA? KEYTRUDA is a prescription med…