
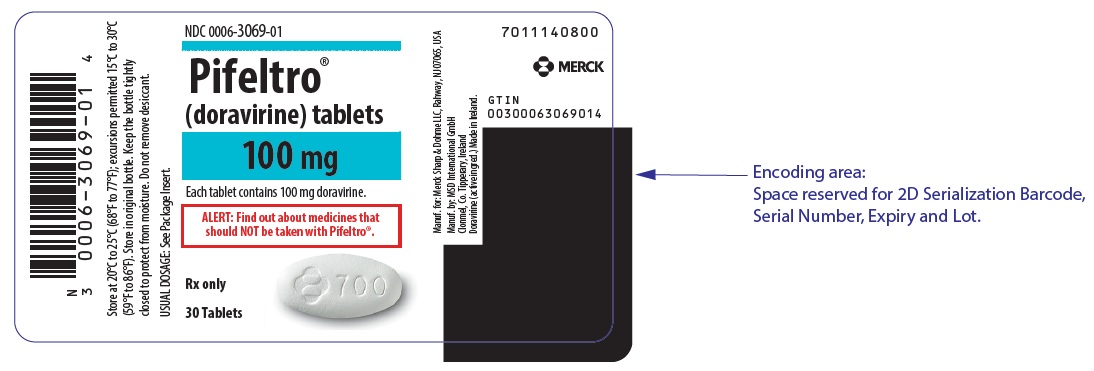
Pifeltro doravirine 100 mg Tablet, Film Coated, 30-count — NDC 0006-3069-01 (Billing 00006-3069-01)
This is a package of 30 tablets of Pifeltro doravirine 100 mg Tablet, Film Coated from Merck Sharp & Dohme LLC, marketed since Jul 2018 and currently FDA-listed; retail pharmacies pay about $60.79 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0006-3069-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0006 labeler · 3069 product · 01 package
- Package marketed since
- Jul 20, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 30 EA per package
- Barcode (UPC)
- 0300063069014
- Medicaid fills, this package
- 11,622 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078887
- GCN: 45294
- GPI-14 (Medi-Span): 12109025000320
- HICL (First Databank): 045216
- AHFS class code: 08:18.08.16
- RxCUI (RxNorm): 2055760
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus 1 Non-Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Pifeltro treats HIV-1 infection, but it does not cure HIV. It's always used together with other HIV medicines — never on its own. When taken consistently as part of a combination r...
- What exactly does Pifeltro treat, and will it cure my HIV?
- Good news — you can take Pifeltro with or without food, whichever works best for you. Studies show that food doesn't meaningfully change how much of the drug gets into your body. T...
- Can I take Pifeltro with food, or does it have to be on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Doravirine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $60.787 | $1,823.61 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $59.28 | $1,778.39 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $60.17 | $1,805.16 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00006-3069-01 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | 2018-07-20 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Pifeltro 100 mgthis 00006-3069-01 | Merck | 30 tablets | $60.787 | — | Availability likely | — |
| Pifeltro 100 mg 50090-6268-00 | A-S | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8486975 ↗ | Drug substance | U-2630 | Aug 30, 2032 |
| US 8486975 ↗ | Drug substance | U-2394 | Aug 30, 2032 |
| US 8486975 ↗ | Drug substance | U-3308 | Aug 30, 2032 |
Is there a generic version of PIFELTRO 100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Doravirine inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 6N003M473W
Hypromellose acetate succinate is a modified cellulose polymer that dissolves in the small intestine. It's used as a coating material to protect the medicine from stomach acid and control where and when the drug is released in the digestive tract.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Merck Sharp & Dohme LLC labeler code 00006
- Janumet Sitagliptin and Metformin Hydrochloride 50 mg; 500 mg Tablet, Film Coated NDC 0006-0575-03
- Janumet Sitagliptin and Metformin Hydrochloride 50 mg; 1000 mg Tablet, Film Coated NDC 0006-0577-03
- ZINPLAVA bezlotoxumab 25 mg/mL Injection, Solution NDC 0006-3025-00
- KEYTRUDA pembrolizumab 25 mg/mL Injection, Solution NDC 0006-3026-02
- EMEND FOSAPREPITANT DIMEGLUMINE 150 mg/5mL Injection, Powder, Lyophilized, For Solution NDC 0006-3061-00
- Emend aprepitant 125 mg Powder, For Suspension NDC 0006-3066-03
- Zepatier elbasvir and grazoprevir 50 mg; 100 mg Tablet, Film Coated NDC 0006-3074-02
- Prevymis Letermovir 240 mg Tablet, Film Coated NDC 0006-3075-02
- Prevymis Letermovir 480 mg Tablet, Film Coated NDC 0006-3076-02
- Isentress Raltegravir 600 mg Tablet, Film Coated NDC 0006-3080-01
- KEYTRUDA QLEX pembrolizumab and berahyaluronidase alfa-pmph 2000 U/mL; 165 mg/mL Injection, Solution NDC 0006-3083-01
- PRIMAXIN IV imipenem and cilastatin sodium 500 mg/100mL; 500 mg/100mL Injection, Powder, For Solution NDC 0006-3516-59
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE PIFELTRO ® is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients weighing at least 35 kg: with no prior antiretroviral treatment history; OR to replace the current antiretroviral regimen in those who are virologically-suppressed (HIV-1 RNA less than 50 copies per mL) on a stable antiretroviral regimen with no history of treatment failure and no known substitutions associated with resistance to doravirine [see Clinical Studies (14) ] .
PIFELTRO, a non-nucleoside reverse transcriptase inhibitor (NNRTI), is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients weighing at least 35 kg: with no prior antiretroviral treatment history, OR to replace the current antiretroviral regimen in those who are virologically-suppressed (HIV-1 RNA less than 50 copies per mL) on a stable antiretroviral regimen with no history of treatment failure and no known substitutions associated with resistance to doravirine.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dosage: One tablet taken orally once daily with or without food in adults and pediatric patients weighing at least 35 kg. ( 2.1 ) Dosage adjustment with rifabutin: One tablet taken twice daily (approximately 12 hours apart). ( 2.2 )
2.1Recommended Dosage The recommended dosage regimen of PIFELTRO in adults and pediatric patients weighing at least 35 kg is one 100 mg tablet taken orally once daily with or without food [see Clinical Pharmacology (12.3) ] .
2.2Dosage Adjustment with Rifabutin If PIFELTRO is co-administered with rifabutin, increase PIFELTRO dosage to one tablet twice daily (approximately 12 hours apart) for the duration of rifabutin co-administration [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS PIFELTRO film-coated tablets are white, oval-shaped tablets, debossed with the corporate logo and 700 on one side and plain on the other side. Each tablet contains 100 mg doravirine. Tablets: 100 mg doravirine. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS PIFELTRO is contraindicated when co-administered with drugs that are strong cytochrome P450 (CYP)3A enzyme inducers as significant decreases in doravirine plasma concentrations may occur, which may decrease the effectiveness of PIFELTRO [see Warnings and Precautions (5.2) , Drug Interactions (7.1) , and Clinical Pharmacology (12.3) ] . These drugs include, but are not limited to, the following: the anticonvulsants carbamazepine, oxcarbazepine, phenobarbital, phenytoin the androgen receptor inhibitor enzalutamide the antimycobacterials rifampin, rifapentine the cytotoxic agent mitotane St.
John's wort ( Hypericum perforatum) PIFELTRO is contraindicated when co-administered with drugs that are strong cytochrome P450 (CYP)3A enzyme inducers as significant decreases in doravirine plasma concentrations may occur, which may decrease the effectiveness of PIFELTRO. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Severe skin reactions, including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN), and Drug Rash with Eosinophilia and Systemic Symptoms (DRESS), have been reported. Discontinue PIFELTRO immediately if signs or symptoms of severe skin reactions develop. ( 5.1 ) Monitor for Immune Reconstitution Syndrome. ( 5.3 )
5.1Skin and Hypersensitivity Reactions Severe skin reactions, including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN), have been reported during the postmarketing experience with doravirine-containing regimens [see Adverse Reactions (6.2) ]. In addition, Drug Rash with Eosinophilia and Systemic Symptoms (DRESS syndrome) was reported in a clinical trial with a two-drug regimen containing doravirine. Discontinue PIFELTRO, and other medications known to be associated with severe skin reactions, immediately if a painful rash with mucosal involvement, a progressive severe rash, or a rash with constitutional symptoms, eosinophilia, lymphadenopathy, or other organ involvement develops.
Clinical status should be closely monitored, and appropriate therapy should be initiated.
5.2Risk of Adverse Reactions or Loss of Virologic Response Due to Drug Interactions The concomitant use of PIFELTRO and certain other drugs may result in known or potentially significant drug interactions, some of which may lead to loss of therapeutic effect of PIFELTRO and possible development of resistance [see Dosage and Administration (2.2) , Contraindications (4) and Drug Interactions (7.1) ]. See Table 6 for steps to prevent or manage these possible and known significant drug interactions, including dosing recommendations.
Consider the potential for drug interactions prior to and during PIFELTRO therapy, review concomitant medications during PIFELTRO therapy, and monitor for adverse reactions.
5.3Immune Reconstitution Syndrome Immune reconstitution syndrome has been reported in patients treated with combination antiretroviral therapy. During the initial phase of combination antiretroviral treatment, patients whose immune system responds may develop an inflammatory response to indolent or residual opportunistic infections (such as Mycobacterium avium infection, cytomegalovirus, Pneumocystis jirovecii pneumonia (PCP), or tuberculosis), which may necessitate further evaluation and treatment. Autoimmune disorders (such as Graves' disease, polymyositis, Guillain-Barré syndrome, and autoimmune hepatitis) have also been reported to occur in the setting of immune reconstitution; however, the time to onset is more variable and can occur many months after initiation of treatment.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Skin and Hypersensitivity Reactions [see Warnings and Precautions (5.1) ] Immune Reconstitution Syndrome [see Warnings and Precautions (5.3) ] Most common adverse reactions (incidence greater than or equal to 5%, all grades) are nausea, dizziness, headache, fatigue, diarrhea, abdominal pain, and abnormal dreams. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in Adults with No Antiretroviral Treatment History The safety assessment of PIFELTRO used in combination with other antiretroviral agents is based on Week 96 data from two Phase 3, randomized, international, multicenter, double-blind, active-controlled trials (DRIVE-FORWARD (Protocol 018) and DRIVE-AHEAD (Protocol 021)).
In DRIVE-FORWARD, 766 adult participants received either PIFELTRO 100 mg (n=383) or darunavir 800 mg + ritonavir 100 mg (DRV+r) (n=383) once daily, each in combination with emtricitabine/tenofovir disoproxil fumarate (FTC/TDF) or abacavir/lamivudine (ABC/3TC). By Week 96, 2% in the PIFELTRO group and 3% in the DRV+r group had adverse events leading to discontinuation of study medication. In DRIVE-AHEAD, 728 adult participants received either DELSTRIGO [doravirine (DOR)/3TC/TDF] (n=364) or efavirenz (EFV)/FTC/TDF once daily (n=364).
By Week 96, 3% in the DELSTRIGO group and 7% in the EFV/FTC/TDF group had adverse events leading to discontinuation of study medication. Adverse reactions reported in greater than or equal to 5% of participants in any treatment group in DRIVE-FORWARD and DRIVE-AHEAD are presented in Table 1. Table 1: Adverse Reactions Frequencies of adverse reactions are based on all adverse events attributed to trial drugs by the investigator.
(All Grades) Reported in ≥5% No adverse reactions of Grade 2 or higher (moderate or severe) occurred in ≥ 2% of participants treated with doravirine. of Participants in Any Treatment Group in Adults with No Antiretroviral Treatment History in DRIVE-FORWARD and DRIVE-AHEAD (Week 96) DRIVE-FORWARD DRIVE-AHEAD PIFELTRO+2 NRTIs NRTI = nucleoside reverse transcriptase inhibitor. Once Daily N=383 DRV+r+2 NRTIs Once Daily N=383 DELSTRIGO Once Daily N=364 EFV/FTC/TDF Once Daily N=364 NRTIs = FTC/TDF or ABC/3TC. Fatigue: includes fatigue, asthenia, malaise Abdominal Pain: includes abdominal discomfort, abdominal pain, abdominal pain lower, abdominal pain upper, epigastric discomfort Rash: includes rash, rash erythematous, rash generalized, rash macular, rash maculo-papular, rash papular, rash pruritic, rash pustular Nausea 7% 8% 5% 7% Headache 6% 3% 4% 5% Fatigue 6% 3% 4% 4% Diarrhea 6% 13% 4% 6% Abdominal Pain 5% 2% 1% 2% Dizziness 3% 2% 7% 32% Rash 2% 3% 2% 12% Abnormal Dreams 1% <1% 5% 10% Insomnia 1% 2% 4% 5% Somnolence 0% <1% 3% 7% The majority (77%) of adverse reactions associated with doravirine occurred at severity Grade 1 (mild).
Neuropsychiatric Adverse Events For DRIVE-AHEAD, the analysis of participants with neuropsychiatric adverse events by Week 48 is presented in Table 2. The proportion of participants who reported one or more neuropsychiatric adverse events was 24% and 57% in the DELSTRIGO and EFV/FTC/TDF groups, respectively. A statistically significantly lower proportion of DELSTRIGO-treated participants compared to EFV/FTC/TDF-treated participants reported neuropsychiatric adverse events by Week 48 in the three pre-specified categories of dizziness, sleep disorders and disturbances, and altered sensorium.
Table 2: DRIVE-AHEAD - Analysis of Participants with Neuropsychiatric Adverse Events A… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consult the full prescribing information prior to and during treatment for important potential drug-drug interactions. ( 4 , 5.2 , 7 )
7.1Effect of Other Drugs on PIFELTRO Co-administration of PIFELTRO with a CYP3A inducer decreases doravirine plasma concentrations, which may reduce PIFELTRO efficacy [see Contraindications (4) , Warnings and Precautions (5.2) , and Clinical Pharmacology (12.3) ] . Co-administration of PIFELTRO and drugs that are inhibitors of CYP3A may result in increased plasma concentrations of doravirine. Table 6 shows significant drug interactions with PIFELTRO.
Table 6: Drug Interactions with PIFELTRO This table is not all inclusive. Concomitant Drug Class: Drug Name Effect on Concentration Clinical Comment ↑ = increase, ↓ = decrease All other drug-drug interactions shown are anticipated based on the known metabolic and elimination pathways. Androgen Receptors enzalutamide ↓ doravirine Co-administration is contraindicated with enzalutamide.
At least a 4-week cessation period is recommended prior to initiation of PIFELTRO. Anticonvulsants carbamazepine oxcarbazepine phenobarbital phenytoin ↓ doravirine Co-administration is contraindicated with these anticonvulsants. At least a 4-week cessation period is recommended prior to initiation of PIFELTRO.
Antimycobacterials rifampin The interaction between PIFELTRO and the concomitant drug was evaluated in a clinical study. rifapentine ↓ doravirine Co-administration is contraindicated with rifampin or rifapentine . At least a 4-week cessation period is recommended prior to initiation of PIFELTRO. rifabutin ↓ doravirine Increase PIFELTRO dosage to one tablet twice daily when co-administered with rifabutin [see Dosage and Administration (2.2) ] . Cytotoxic Agents mitotane ↓ doravirine Co-administration is contraindicated with mitotane.
At least a 4-week cessation period is recommended prior to initiation of PIFELTRO. HIV Antiviral Agents efavirenz etravirine nevirapine ↓ doravirine Use with efavirenz, etravirine, or nevirapine is not recommended. Herbal Products St.
John's wort ↓ doravirine Co-administration is contraindicated with St. John's wort. At least a 4-week cessation period is recommended prior to initiation of PIFELTRO.
No clinically significant changes in concentration were observed for doravirine when co-administered with the following agents: dolutegravir, TDF, lamivudine, elbasvir and grazoprevir, ledipasvir and sofosbuvir, ritonavir, ketoconazole, aluminum hydroxide/magnesium hydroxide/simethicone containing antacid, pantoprazole, and methadone [see Clinical Pharmacology (12.3) ].
7.2Effect of PIFELTRO on Other Drugs No clinically significant changes in concentration were observed for the following agents when co-administered with doravirine: dolutegravir, lamivudine, TDF, elbasvir and grazoprevir, ledipasvir and sofosbuvir, atorvastatin, an oral contraceptive containing ethinyl estradiol and levonorgestrel, metformin, methadone, and midazolam [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatrics: Not recommended for patients weighing less than 35 kg. ( 8.4 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in individuals exposed to PIFELTRO during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary No adequate human data are available to establish whether or not PIFELTRO poses a risk to pregnancy outcomes.
In animal reproduction studies, no adverse developmental effects were observed when doravirine was administered at exposures ≥8 times the exposure in humans at the recommended human dose (RHD) of PIFELTRO ( see Data ). The background rate of major birth defects is 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in the clinically recognized pregnancies in the U.S. general population is 15-20%. Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates individuals and infants from the limited geographic area, and does not include outcomes for births that occurred at less than 20 weeks gestation.
Data Animal Data Doravirine was administered orally to pregnant rabbits (up to 300 mg/kg/day on gestation days (GD) 7 to 20) and rats (up to 450 mg/kg/day on GD 6 to 20 and separately from GD 6 to lactation/postpartum day 20). No significant toxicological effects on embryo-fetal (rats and rabbits) or pre/post-natal (rats) development were observed at exposures (AUC) approximately 9 times (rats) and 8 times (rabbits) the exposure in humans at the RHD. Doravirine was transferred to the fetus through the placenta in embryo-fetal studies, with fetal plasma concentrations of up to 40% (rabbits) and 52% (rats) that of maternal concentrations observed on GD 20.
8.2Lactation Risk Summary It is unknown whether doravirine is present in human milk, affects human milk production, or has effects on the breastfed infant. Doravirine is present in the milk of lactating rats ( see Data ). Potential risks of breastfeeding include: (1) HIV-1 transmission (in HIV-1-negative infants), (2) developing viral resistance (in HIV-1-positive infants), and (3) serious adverse reactions in a breastfed infant similar to those seen in adults.
Data Doravirine was excreted into the milk of lactating rats following oral administration (450 mg/kg/day) from GD 6 to lactation day 14, with milk concentrations approximately 1.5 times that of maternal plasma concentrations observed 2 hours post dose on lactation day 14.
8.4Pediatric Use The safety and efficacy of PIFELTRO for the treatment of HIV-1 infection have been established in pediatric patients weighing at least 35 kg [see Indications and Usage (1) and Dosage and Administration (2.1) ]. Use of PIFELTRO in this group is supported by evidence from adequate and well-controlled trials in adults and an open-label trial in virologically-suppressed or treatment-naïve pediatric participants 12 to less than 18 years of age. The safety, efficacy, and exposure of doravirine in these pediatric participants were similar to that in adults [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.3) ].
Safety and efficacy of PIFELTRO in pediatric patients weighing less than 35 kg have not been established.
8.5Geriatric Use Clinical trials of PIFELTRO did not include sufficient numbers of participants aged 65 years and over to determine whether they respond differently from younger participants. In general, caution should be exercised in the administration of PIFELTRO in elderly patients, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3)… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in individuals exposed to PIFELTRO during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary No adequate human data are available to establish whether or not PIFELTRO poses a risk to pregnancy outcomes.
In animal reproduction studies, no adverse developmental effects were observed when doravirine was administered at exposures ≥8 times the exposure in humans at the recommended human dose (RHD) of PIFELTRO ( see Data ). The background rate of major birth defects is 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in the clinically recognized pregnancies in the U.S. general population is 15-20%. Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates individuals and infants from the limited geographic area, and does not include outcomes for births that occurred at less than 20 weeks gestation.
Data Animal Data Doravirine was administered orally to pregnant rabbits (up to 300 mg/kg/day on gestation days (GD) 7 to 20) and rats (up to 450 mg/kg/day on GD 6 to 20 and separately from GD 6 to lactation/postpartum day 20). No significant toxicological effects on embryo-fetal (rats and rabbits) or pre/post-natal (rats) development were observed at exposures (AUC) approximately 9 times (rats) and 8 times (rabbits) the exposure in humans at the RHD. Doravirine was transferred to the fetus through the placenta in embryo-fetal studies, with fetal plasma concentrations of up to 40% (rabbits) and 52% (rats) that of maternal concentrations observed on GD 20.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of PIFELTRO for the treatment of HIV-1 infection have been established in pediatric patients weighing at least 35 kg [see Indications and Usage (1) and Dosage and Administration (2.1) ]. Use of PIFELTRO in this group is supported by evidence from adequate and well-controlled trials in adults and an open-label trial in virologically-suppressed or treatment-naïve pediatric participants 12 to less than 18 years of age. The safety, efficacy, and exposure of doravirine in these pediatric participants were similar to that in adults [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.3) ].
Safety and efficacy of PIFELTRO in pediatric patients weighing less than 35 kg have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of PIFELTRO did not include sufficient numbers of participants aged 65 years and over to determine whether they respond differently from younger participants. In general, caution should be exercised in the administration of PIFELTRO in elderly patients, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Doravirine is an antiretroviral drug [see Microbiology (12.4) ].
12.2Pharmacodynamics In a Phase 2 trial evaluating doravirine over a dose range of 0.25 to 2 times the recommended dose of PIFELTRO, (in combination with FTC/TDF) in participants living with HIV with no antiretroviral treatment history, no exposure-response relationship for efficacy was identified for doravirine. Cardiac Electrophysiology At a doravirine dose of 1200 mg, which provides approximately 4 times the peak concentration observed following the recommended dose of PIFELTRO, doravirine does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Doravirine pharmacokinetics are similar in healthy participants and participants living with HIV. Doravirine pharmacokinetics are provided in Table 7. Table 7: Pharmacokinetic Properties of Doravirine Parameter Doravirine Abbreviations: AUC=area under the time concentration curve; C max =maximum concentration; C 24 =concentration at 24 hours; T max time to C max ; V dss = volume of distribution at steady state, t 1/2 =elimination half-life; CL/F=apparent clearance; CL renal =apparent renal clearance General Steady State Exposure Doravirine 100 mg once daily to participants living with HIV , Presented as geometric mean (%CV: geometric coefficient of variation) AUC 0-24 (mcg∙h/mL) 16.1 (29) C max (mcg/mL) 0.962 (19) C 24 (mcg/mL) 0.396 (63) Time to Steady State (Days) 2 Accumulation Ratio 1.2 to
1.4Absorption Absolute Bioavailability 64% T max (h) 2 Effect of Food Geometric mean ratio [high-fat meal/fasting] and (90% confidence interval) for PK parameters. High fat meal is approximately 1,000 kcal, 50% fat. The effect of food is not clinically relevant. AUC Ratio 1.16 (1.06, 1.26) C max Ratio 1.03 (0.89, 1.19) C 24 Ratio 1.36 (1.19, 1.55) Distribution V dss (L) Based on IV dose
60.5Plasma Protein Binding 76% Elimination t 1/2 (h) 15 CL/F (mL/min) 106 (35.2) CL renal (mL/min) 9.3 (18.6) Metabolism Primary Pathway(s) CYP3A Excretion Major Route of Elimination Metabolism Urine (unchanged) 6% Biliary/Fecal (unchanged) Minor Specific Populations In adults, no clinically significant difference on the pharmacokinetics of doravirine were observed based on age (18 to 78 years of age), sex, and race/ethnicity, mild to severe renal impairment (creatinine clearance (CLcr) >15 mL/min, estimated by Cockcroft-Gault), or moderate hepatic impairment (Child-Pugh B).
The pharmacokinetics of doravirine in patients with end-stage renal disease or undergoing dialysis, or severe hepatic impairment (Child-Pugh C) is unknown. Patients with Renal Impairment In a study comparing 8 participants with severe renal impairment to 8 participants without renal impairment, the single dose exposure of doravirine was 43% higher in participants with severe renal impairment. In a population pharmacokinetic analysis, renal function did not have a clinically relevant effect on doravirine pharmacokinetics.
Doravirine has not been studied in patients with end-stage renal disease or in patients undergoing dialysis [see Use in Specific Populations (8.6) ] . Patients with Hepatic Impairment No clinically significant difference in the pharmacokinetics of doravirine was observed in participants with moderate hepatic impairment (Child-Pugh score B) compared to participants without hepatic impairment. Doravirine has not been studied in participants with severe hepatic impairment (Child-Pugh score C) [see Use in Specific Populations (8.7) ] .
Pediatric Patients Mean doravirine exposures were similar in 54 pediatric participants aged 12 to less than 18 years and weighing at least 35 kg who received doravirine or DELSTRIGO in IMPAACT 2014 (Protocol 027) relative to adults following administration of doravirine or DELSTRIGO (Table 8). For pediatric participants weighing ≥ 35 kg and < 45 kg who received doravirine 100 mg or DELSTRIGO, the population pharmacokinetic model-predicted mean C 24… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Doravirine is an antiretroviral drug [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each PIFELTRO tablet contains 100 mg of doravirine, is white, oval-shaped and film-coated, and is debossed with the corporate logo and 700 on one side and plain on the other side. Each bottle contains 30 tablets (NDC 0006-3069-01) with silica gel desiccant and is closed with a child-resistant closure. Store PIFELTRO in the original bottle.
Keep the bottle tightly closed to protect from moisture. Do not remove the desiccant. Store PIFELTRO at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store PIFELTRO in the original bottle. Keep the bottle tightly closed to protect from moisture. Do not remove the desiccant. Store PIFELTRO at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION PIFELTRO is a film-coated tablet containing doravirine for oral administration. Doravirine is an HIV-1 non-nucleoside reverse transcriptase inhibitor (NNRTI). Each tablet contains 100 mg of doravirine as the active ingredient.
The tablets include the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose acetate succinate, lactose monohydrate, magnesium stearate, and microcrystalline cellulose. The tablets are film coated with a coating material containing the following inactive ingredients: hypromellose, lactose monohydrate, titanium dioxide, and triacetin. The coated tablets are polished with carnauba wax.
The chemical name for doravirine is 3-chloro-5-[[1-[(4,5-dihydro-4-methyl-5-oxo-1 H -1,2,4-triazol-3-yl)methyl]-1,2-dihydro-2-oxo-4-(trifluoromethyl)-3-pyridinyl]oxy]benzonitrile. It has a molecular formula of C 17 H 11 ClF 3 N 5 O 3 and a molecular weight of 425.75. It has the following structural formula: Doravirine is practically insoluble in water.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Skin and Hypersensitivity Reactions Inform patients that severe skin reactions including Stevens-Johnson syndrome (SJS)/toxic epidermal necrolysis (TEN) and Drug Rash with Eosinophilia and Systemic Symptoms (DRESS) have been reported with doravirine-containing regimens. Advise patients to immediately contact their healthcare provider if they develop a rash.
Instruct patients to immediately stop taking PIFELTRO and seek medical attention if a painful rash with mucosal involvement or a rash with constitutional symptoms develops [see Warnings and Precautions (5.1) ] . Drug Interactions Inform patients that PIFELTRO may interact with certain other drugs; therefore, advise patients to report to their healthcare provider the use of any other prescription or nonprescription medication or herbal products, including St. John's wort [see Contraindications (4) , Warnings and Precautions (5.2) , and Drug Interactions (7.1) ] .
For patients concomitantly receiving rifabutin, take one tablet of PIFELTRO twice daily (approximately 12 hours apart) [see Dosage and Administration (2.2) ] . Immune Reconstitution Syndrome Inform patients that in some patients with advanced HIV infection (AIDS), signs and symptoms of inflammation from previous infections may occur soon after anti-HIV treatment is started. It is believed that these symptoms are due to an improvement in the body's immune response, enabling the body to fight infections that may have been present with no obvious symptoms.
Advise patients to inform their healthcare provider immediately of any symptoms of infection [see Warnings and Precautions (5.3) ]. Dosing Instructions Advise patients to take PIFELTRO every day at a regularly scheduled time with or without food. Inform patients that it is important not to miss or skip doses as it can result in development of resistance.
If a patient forgets to take PIFELTRO, tell the patient to take the missed dose right away, unless it is almost time for the next dose. Advise the patient not to take 2 doses at one time and to take the next dose at the regularly scheduled time. Pregnancy Registry Inform patients that there is an antiretroviral pregnancy registry to monitor fetal outcomes in pregnant individuals exposed to PIFELTRO [see Use in Specific Populations (8.1) ].
Lactation Inform individuals with HIV-1 infection that the potential risks of breastfeeding include: (1) HIV-1 transmission (in HIV-1–negative infants), (2) developing viral resistance (in HIV-1– positive infants), and (3) serious adverse reactions in a breastfed infant similar to those seen in adults [see Use in Specific Populations (8.2) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Doravirine pharmacokinetics are similar in healthy participants and participants living with HIV. Doravirine pharmacokinetics are provided in Table 7. Table 7: Pharmacokinetic Properties of Doravirine Parameter Doravirine Abbreviations: AUC=area under the time concentration curve; C max =maximum concentration; C 24 =concentration at 24 hours; T max time to C max ; V dss = volume of distribution at steady state, t 1/2 =elimination half-life; CL/F=apparent clearance; CL renal =apparent renal clearance General Steady State Exposure Doravirine 100 mg once daily to participants living with HIV , Presented as geometric mean (%CV: geometric coefficient of variation) AUC 0-24 (mcg∙h/mL) 16.1 (29) C max (mcg/mL) 0.962 (19) C 24 (mcg/mL) 0.396 (63) Time to Steady State (Days) 2 Accumulation Ratio 1.2 to
1.4Absorption Absolute Bioavailability 64% T max (h) 2 Effect of Food Geometric mean ratio [high-fat meal/fasting] and (90% confidence interval) for PK parameters. High fat meal is approximately 1,000 kcal, 50% fat. The effect of food is not clinically relevant. AUC Ratio 1.16 (1.06, 1.26) C max Ratio 1.03 (0.89, 1.19) C 24 Ratio 1.36 (1.19, 1.55) Distribution V dss (L) Based on IV dose
60.5Plasma Protein Binding 76% Elimination t 1/2 (h) 15 CL/F (mL/min) 106 (35.2) CL renal (mL/min) 9.3 (18.6) Metabolism Primary Pathway(s) CYP3A Excretion Major Route of Elimination Metabolism Urine (unchanged) 6% Biliary/Fecal (unchanged) Minor Specific Populations In adults, no clinically significant difference on the pharmacokinetics of doravirine were observed based on age (18 to 78 years of age), sex, and race/ethnicity, mild to severe renal impairment (creatinine clearance (CLcr) >15 mL/min, estimated by Cockcroft-Gault), or moderate hepatic impairment (Child-Pugh B).
The pharmacokinetics of doravirine in patients with end-stage renal disease or undergoing dialysis, or severe hepatic impairment (Child-Pugh C) is unknown. Patients with Renal Impairment In a study comparing 8 participants with severe renal impairment to 8 participants without renal impairment, the single dose exposure of doravirine was 43% higher in participants with severe renal impairment. In a population pharmacokinetic analysis, renal function did not have a clinically relevant effect on doravirine pharmacokinetics.
Doravirine has not been studied in patients with end-stage renal disease or in patients undergoing dialysis [see Use in Specific Populations (8.6) ] . Patients with Hepatic Impairment No clinically significant difference in the pharmacokinetics of doravirine was observed in participants with moderate hepatic impairment (Child-Pugh score B) compared to participants without hepatic impairment. Doravirine has not been studied in participants with severe hepatic impairment (Child-Pugh score C) [see Use in Specific Populations (8.7) ] .
Pediatric Patients Mean doravirine exposures were similar in 54 pediatric participants aged 12 to less than 18 years and weighing at least 35 kg who received doravirine or DELSTRIGO in IMPAACT 2014 (Protocol 027) relative to adults following administration of doravirine or DELSTRIGO (Table 8). For pediatric participants weighing ≥ 35 kg and < 45 kg who received doravirine 100 mg or DELSTRIGO, the population pharmacokinetic model-predicted mean C 24 of doravirine was comparable to that achieved in adults, whereas mean AUC 0-24 and C max of doravirine were 25% and 36% higher than adult values, respectively.
However, the predicted AUC 0-24 and C max increases are not considered clinically significant. Table 8: Steady State Pharmacokinetics for Doravirine Following Administration of Doravirine or DELSTRIGO in Pediatric Participants Living with HIV Aged 12 to Less than 18 Years and Weighing at Least 35 kg Parameter Presented as geometric mean (%CV: geometric coefficient of variation) Doravirine From population PK analysis (n=53 weighing ≥45 kg, n=1 weighing ≥35 kg to <45 kg) Abbreviations: AUC=area under the time concentr… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In a Phase 2 trial evaluating doravirine over a dose range of 0.25 to 2 times the recommended dose of PIFELTRO, (in combination with FTC/TDF) in participants living with HIV with no antiretroviral treatment history, no exposure-response relationship for efficacy was identified for doravirine. Cardiac Electrophysiology At a doravirine dose of 1200 mg, which provides approximately 4 times the peak concentration observed following the recommended dose of PIFELTRO, doravirine does not prolong the QT interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Clinical Trial Results in Adults with No Antiretroviral Treatment History The efficacy of PIFELTRO is based on the analyses of 96-week data from two randomized, multicenter, double-blind, active controlled Phase 3 trials (DRIVE-FORWARD, NCT02275780 and DRIVE-AHEAD, NCT02403674) in participants living with HIV with no antiretroviral treatment history (n=1494). In DRIVE-FORWARD, 766 participants were randomized and received at least 1 dose of either PIFELTRO once daily or darunavir 800 mg + ritonavir 100 mg (DRV+r) once daily each in combination with emtricitabine/tenofovir DF (FTC/TDF) or abacavir/lamivudine (ABC/3TC) selected by the investigator.
At baseline, the median age of participants was 33 years, 16% were female, 27% were Non-White, 4% had hepatitis B and/or C virus co-infection, 10% had a history of AIDS, 20% had HIV-1 RNA greater than 100,000 copies/mL, 86% had CD4+ T-cell count greater than 200 cells/mm 3 , 13% received ABC/3TC, and 87% received FTC/TDF; these characteristics were similar between treatment groups. In DRIVE-AHEAD, 728 participants were randomized and received at least 1 dose of either DELSTRIGO (DOR/3TC/TDF) or EFV 600 mg/FTC 200 mg/TDF 300 mg once daily.
At baseline, the median age of participants was 31 years, 15% were female, 52% were Non-White, 3% had hepatitis B or C co-infection, 14% had a history of AIDS, 21% had HIV-1 RNA greater than 100,000 copies/mL, and 88% had CD4+ T-cell count greater than 200 cells/mm 3 ; these characteristics were similar between treatment groups. Week 96 outcomes for DRIVE-FORWARD and DRIVE-AHEAD are provided in Table 10. Side-by-side tabulation is to simplify presentation; direct comparisons across trials should not be made due to differing trial designs.
In DRIVE-FORWARD, the mean CD4+ T-cell counts in the PIFELTRO and DRV+r groups increased from baseline by 224 and 207 cells/mm 3 , respectively. In DRIVE-AHEAD, the mean CD4+ T-cell counts in the DELSTRIGO and EFV/FTC/TDF groups increased from baseline by 238 and 223 cells/mm 3 , respectively. Table 10: Virologic Outcome in DRIVE-FORWARD and DRIVE-AHEAD at Week 96 in HIV-1 Adults with No Antiretroviral Treatment History Outcome DRIVE-FORWARD DRIVE-AHEAD PIFELTRO + 2 NRTIs Once Daily DRV+r + 2 NRTIs Once Daily DELSTRIGO Once Daily EFV/FTC/TDF Once Daily N=383 N=383 N=364 N=364 Note: NRTIs = FTC/TDF or ABC/3TC.
HIV-1 RNA <50 copies/mL 72% 65% 77% 74% Treatment Differences (95% CI) The 95% CIs for the treatment differences were calculated using stratum-adjusted Mantel-Haenszel method. 7.5% (1.0%, 14.1%) 3.8% (-2.4%, 10.0%) HIV-1 RNA ≥ 50 copies/mL Includes participants who discontinued study drug or study before Week 96 for lack or loss of efficacy and participants with HIV-1 RNA equal to or above 50 copies/mL in the Week 96 window. 17% 20% 15% 12% No Virologic Data at Week 96 Window 11% 15% 7% 14% Discontinued study due to AE or Death Includes participants who discontinued because of adverse event (AE) or death if this resulted in no virologic data in the Week 96 window.
2% 4% 3% 8% Discontinued study for Other Reasons Other Reasons include: lost to follow-up, non-compliance with study drug, physician decision, pregnancy, protocol deviation, screen failure, withdrawal by participant. 7% 9% 4% 5% On study but missing data in window 2% 3% 1% 1% Proportion (%) of Participants With HIV-1 RNA <50 copies/mL at Week 96 by Baseline and Demographic Category Gender Male 72% (N = 319) 67% (N = 326) 78% (N = 305) 73% (N = 311) Female 73% (N = 64) 54% (N = 57) 75% (N = 59) 75% (N = 53) Race White 78% (N = 280) 68% (N = 280) 80% (N = 176) 74% (N = 170) Non-White 58% (N = 103) 57% (N = 102) 76% (N = 188) 74% (N = 194) Ethnicity Does not include participants whose ethnicity or viral subtypes were unknown.
Hispanic or Latino 76% (N = 93) 63% (N = 86) 81% (N = 126) 77% (N = 119) Not Hispanic or Latino 71% (N = 284) 66% (N = 290) 76% (N = 238) 72% (N = 239) NRTI Background Therapy FTC/TDF 71% (N = 333) 64% (N =… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Doravirine was not carcinogenic in long-term oral carcinogenicity studies in mice and rats at exposures up to 6 and 7 times, respectively, the human exposures at the RHD. A statistically significant incidence of thyroid parafollicular cell adenoma and carcinoma seen only in female rats at the high dose was within the range observed in historical controls. Mutagenesis Doravirine was not genotoxic in a battery of in vitro or in vivo assays, including microbial mutagenesis, chromosomal aberration in Chinese hamster ovary cells, and in in vivo rat micronucleus assays.
Impairment of fertility There were no effects on fertility, mating performance or early embryonic development when doravirine was administered to rats at systemic exposures (AUC) approximately 7 times the exposure in humans at the RHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Doravirine was not carcinogenic in long-term oral carcinogenicity studies in mice and rats at exposures up to 6 and 7 times, respectively, the human exposures at the RHD. A statistically significant incidence of thyroid parafollicular cell adenoma and carcinoma seen only in female rats at the high dose was within the range observed in historical controls. Mutagenesis Doravirine was not genotoxic in a battery of in vitro or in vivo assays, including microbial mutagenesis, chromosomal aberration in Chinese hamster ovary cells, and in in vivo rat micronucleus assays.
Impairment of fertility There were no effects on fertility, mating performance or early embryonic development when doravirine was administered to rats at systemic exposures (AUC) approximately 7 times the exposure in humans at the RHD.
📄 Patient Package Insert ▾
Patient Information PIFELTRO ® (pih-FEL-tro) (doravirine) tablets What is PIFELTRO? PIFELTRO is a prescription medicine that is used together with other HIV-1 medicines to treat Human Immunodeficiency Virus-1 (HIV-1) infection in adults and children who weigh at least 77 pounds (35 kg): who have not received HIV-1 medicines in the past, or to replace their current HIV-1 medicines for people whose healthcare provider determines that they meet certain requirements. HIV-1 is the virus that causes Acquired Immune Deficiency Syndrome (AIDS).
It is not known if PIFELTRO is safe and effective in children who weigh less than 77 pounds (35 kg). Who should not take PIFELTRO? Do not take PIFELTRO if you take any of the following medicines: carbamazepine oxcarbazepine phenobarbital phenytoin enzalutamide rifampin rifapentine mitotane St.
John's wort Ask your healthcare provider or pharmacist if you are not sure if your medicine is one that is listed above. If you have taken any of the medicines in the past 4 weeks, talk to your healthcare provider or pharmacist before starting treatment with PIFELTRO. What should I tell my healthcare provider before treatment with PIFELTRO?
Before treatment with PIFELTRO, tell your healthcare provider about all of your medical conditions, including if you: are pregnant or plan to become pregnant. It is not known if PIFELTRO can harm your unborn baby. Tell your healthcare provider if you become pregnant during treatment with PIFELTRO.
Pregnancy Registry: There is a pregnancy registry for people who take PIFELTRO during pregnancy. The purpose of this registry is to collect information about the health of you and your baby. Talk to your healthcare provider about how you can take part in this registry. are breastfeeding or plan to breastfeed.
PIFELTRO may pass to your baby in your breast milk. Talk with your healthcare provider about the following risks to your baby from breastfeeding during treatment with PIFELTRO: the HIV-1 virus may pass to your baby if your baby does not have HIV-1 infection. the HIV-1 virus may become harder to treat if your baby has HIV-1 infection. your baby may get side effects from PIFELTRO. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
Some medicines interact with PIFELTRO . Keep a list of your medicines to show your healthcare provider and pharmacist. Tell your healthcare provider if you have taken rifabutin in the past 4 weeks.
You can ask your healthcare provider or pharmacist for a list of medicines that interact with PIFELTRO. Do not start taking a new medicine without telling your healthcare provider . Your healthcare provider can tell you if it is safe to take PIFELTRO with other medicines.
How do I take PIFELTRO? Take PIFELTRO every day exactly as your healthcare provider tells you to take it. Take PIFELTRO 1 time each day, at about the same time every day.
If you take the medicine rifabutin during treatment with PIFELTRO, take PIFELTRO 2 times each day, about 12 hours apart, as prescribed by your healthcare provider. You may not have enough doravirine in your blood if you take rifabutin during treatment with PIFELTRO. Take PIFELTRO with or without food.
Do not change your dose or stop taking PIFELTRO without talking to your healthcare provider. Stay under a healthcare provider's care when taking PIFELTRO. It is important that you do not miss or skip doses of PIFELTRO.
If you miss a dose of PIFELTRO, take it as soon as you remember. If it is almost time for your next dose, skip the missed dose and take the next dose at your regular time. Do not take 2 doses of PIFELTRO at the same time.
If you have any questions, call your healthcare provider or pharmacist. When your PIFELTRO supply starts to run low, get more from your healthcare provider or pharmacy. This is very important because the amount of virus in your blood may increase if the medicine is stopped for even a sho… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.1 ) 7/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 100 mg Bottle Label NDC 0006-3069-01 Pifeltro ® (doravirine) tablets 100 mg Each tablet contains 100 mg doravirine. ALERT: Find out about medicines that should NOT be taken with Pifeltro ® . Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 100 mg Bottle Label