
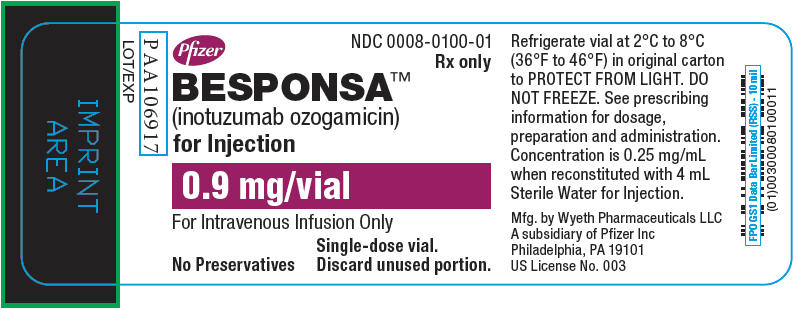
Besponsa inotuzumab ozogamicin .25 mg/mL Injection, Powder, Lyophilized, For Solution — NDC 0008-0100-01 (Billing 00008-0100-01)
This is a package of Besponsa inotuzumab ozogamicin .25 mg/mL Injection, Powder, Lyophilized, For Solution from Wyeth Pharmaceuticals LLC, a subsidiary of Pfizer Inc., marketed since Aug 2017 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0008-0100-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0008 labeler · 0100 product · 01 package
- Package marketed since
- Aug 18, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0008010001 1
- Medicaid fills, this package
- 36 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 077609
- GCN: 43664
- GPI-14 (Medi-Span): 21352640202130
- HICL (First Databank): 044438
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1942954
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the CD22-directed Immunoconjugate class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Inotuzumab ozogamicin injection is used to treat certain acute lymphoblastic leukemia (ALL; a type of cancer that begins in the white blood cells) in adults who have not responded to previous cancer treatments in adults and children 1 year of age and older. Inotuzumab ozogamicin injection is in a class of medications called monoclonal antibodies. It works by activating the immune system to destroy cancer cells.
Read the full MedlinePlus article ↗- It treats relapsed or refractory CD22-positive B-cell precursor acute lymphoblastic leukemia. That means leukemia that came back or didn't respond to earlier treatment. It's used i...
- It's given through an IV by your healthcare team, usually on Days 1, 8 and 15 of each cycle. You'll get medicines beforehand to reduce reactions, and you'll be watched for at least...
- Common ones include low blood counts, infections, fever, tiredness, nausea, vomiting, headache, belly pain and bleeding. Your team will check blood counts and liver tests regularly...
- Call about yellow skin or eyes, a swollen or painful belly, fast weight gain, fever or signs of infection, unusual bleeding, or a racing or irregular heartbeat. Also report any fev...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Inotuzumab Ozogamicin — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $15,538.43 | $62,153.73 / 4 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9229 | $2,873.103 / J9229 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00008-0100-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 4 mL in 1 VIAL, SINGLE-DOSE | 2017-08-18 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Besponsa .25 mg/mLthis 00008-0100-01 | Wyeth | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Aug 17, 2029 |
Is there a biosimilar for BESPONSA 0.9 MG VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Inotuzumab Ozogamicin Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 023C2WHX2V
Tromethamine is a chemical buffer that helps maintain the proper acidity level in liquid medicines. It neutralizes acids and stabilizes the solution so the medication remains effective and safe throughout its shelf life.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Wyeth Pharmaceuticals LLC, a subsidiary of Pfize... labeler code 00008
- North American Coral Snake Antivenin (Equine) Coral Snake (Micrurus Fulvius) Immune Globulin 250 [arb'U]/10mL Injection, Powder, For Solution NDC 0008-0423-03
- Effexor XR VENLAFAXINE HYDROCHLORIDE 150 mg Capsule, Extended Release NDC 0008-0836-21
- Protonix Delayed-Release PANTOPRAZOLE SODIUM 40 mg Tablet, Delayed Release NDC 0008-0841-81
- Protonix Delayed-Release PANTOPRAZOLE SODIUM 20 mg Tablet, Delayed Release NDC 0008-0843-81
- Protonix Delayed-Release PANTOPRAZOLE SODIUM 40 mg Granule, Delayed Release NDC 0008-0844-02
- Protonix I.V. PANTOPRAZOLE SODIUM 40 mg/10mL Injection, Powder, For Solution NDC 0008-0923-51
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HEPATOTOXICITY, INCLUDING HEPATIC VENO-OCCLUSIVE DISEASE (VOD) (ALSO KNOWN AS SINUSOIDAL OBSTRUCTION SYNDROME) and INCREASED RISK OF POST-HEMATOPOIETIC STEM CELL TRANSPLANT (HSCT) NON-RELAPSE MORTALITY WARNING: HEPATOTOXICITY, INCLUDING HEPATIC VENO-OCCLUSIVE DISEASE (VOD) (ALSO KNOWN AS SINUSOIDAL OBSTRUCTION SYNDROME) and INCREASED RISK OF POST- HEMATOPOIETIC STEM CELL TRANSPLANT (HSCT) NON-RELAPSE MORTALITY See full prescribing information for complete boxed warning. • Hepatotoxicity, including fatal and life-threatening VOD occurred in patients who received BESPONSA.
( 5.1 ) • A higher post-HSCT non-relapse mortality rate occurred in patients receiving BESPONSA ( 5.2 ) HEPATOTOXICITY, INCLUDING VOD • Hepatotoxicity, including fatal and life-threatening VOD occurred in patients with relapsed or refractory acute lymphoblastic leukemia (ALL) who received BESPONSA. The risk of VOD was greater in patients who underwent HSCT after BESPONSA treatment; use of HSCT conditioning regimens containing 2 alkylating agents and last total bilirubin level ≥ upper limit of normal (ULN) before HSCT were significantly associated with an increased risk of VOD. • Other risk factors for VOD in patients treated with BESPONSA included ongoing or prior liver disease, prior HSCT, increased age, later salvage lines, and a greater number of BESPONSA treatment cycles. • Elevation of liver tests may require dosing interruption, dose reduction, or permanent discontinuation of BESPONSA.
Permanently discontinue treatment if VOD occurs. If severe VOD occurs, treat according to standard medical practice [see Dosage and Administration (2.3) and Warnings and Precautions (5.1) ]. INCREASED RISK OF POST-HSCT NON-RELAPSE MORTALITY • There was higher post-HSCT non-relapse mortality rate in patients receiving BESPONSA, resulting in a higher Day 100 post-HSCT mortality rate [see Warnings and Precautions (5.2) ] .
🎯 Indications and Usage ▾
1. INDICATIONS AND USAGE BESPONSA is indicated for the treatment of relapsed or refractory CD22-positive B-cell precursor acute lymphoblastic leukemia (ALL) in adult and pediatric patients 1 year and older . BESPONSA is a CD22-directed antibody and cytotoxic drug conjugate indicated for the treatment of relapsed or refractory CD22-positive B-cell precursor acute lymphoblastic leukemia (ALL) in adult and pediatric patients 1 year and older. ( 1 )
⏱️ Dosage and Administration ▾
2. DOSAGE AND ADMINISTRATION • Administer by intravenous infusion only. (2.1) • Pre-medicate with a corticosteroid, antipyretic, and antihistamine prior to all infusions.
( 2.2 ) • Dosing regimens for Cycle 1 and subsequent cycles, depending on the response to treatment, are shown below. See full prescribing information for dosing details. ( 2 ) Day 1 Day 8 Day 15 Dosing regimen for Cycle 1 All patients: Dose 0.8 mg/m 2 0.5 mg/m 2 0.5 mg/m 2 Cycle length 21 days For patients who achieve a CR or a CRi, and/or to allow for recovery from toxicity, the cycle length may be extended up to 28 days (i.e., 7-day treatment-free interval starting on Day 21).
Dosing regimen for subsequent cycles depending on response to treatment Patients who have achieved a CR or CRi: Dose 0.5 mg/m 2 0.5 mg/m 2 0.5 mg/m 2 Cycle length 28 days Patients who have not achieved a CR or CRi: Dose 0.8 mg/m 2 0.5 mg/m 2 0.5 mg/m 2 Cycle length 28 days • See full prescribing information for instructions on reconstitution of lyophilized powder, and preparation and administration of reconstituted drug. ( 2.4 )
2.1Recommended Dosage • Pre-medicate before each dose [see Dosage and Administration (2.2) ] . • Administer by intravenous infusion only. • For the first cycle, the recommended total dose of BESPONSA for all patients is 1.8 mg/m 2 per cycle, administered as 3 divided doses on Day 1 (0.8 mg/m 2 ), Day 8 (0.5 mg/m 2 ), and Day 15 (0.5 mg/m 2 ). Cycle 1 is 3 weeks in duration, but may be extended to 4 weeks if the patient achieves a complete remission (CR) or complete remission with incomplete hematologic recovery (CRi), and/or to allow recovery from toxicity. • For subsequent cycles: • In patients who achieve a CR or CRi, the recommended total dose of BESPONSA is 1.5 mg/m 2 per cycle, administered as 3 divided doses on Day 1 (0.5 mg/m 2 ), Day 8 (0.5 mg/m 2 ), and Day 15 (0.5 mg/m 2 ).
Subsequent cycles are 4 weeks in duration. OR • In patients who do not achieve a CR or CRi, the recommended total dose of BESPONSA is 1.8 mg/m 2 per cycle given as 3 divided doses on Day 1 (0.8 mg/m 2 ), Day 8 (0.5 mg/m 2 ), and Day 15 (0.5 mg/m 2 ). Subsequent cycles are 4 weeks in duration.
Patients who do not achieve a CR or CRi within 3 cycles should discontinue treatment. • For patients proceeding to hematopoietic stem cell transplant (HSCT), the recommended duration of treatment with BESPONSA is 2 cycles. A third cycle may be considered for those patients who do not achieve CR or CRi and minimal residual disease (MRD) negativity after 2 cycles [see Warnings and Precautions (5.1) ] . • For patients not proceeding to HSCT, additional cycles of treatment, up to a maximum of 6 cycles, may be administered.
Table 1 shows the recommended dosing regimens. Table 1. Dosing Regimen for Cycle 1 and Subsequent Cycles Depending on Response to Treatment Abbreviations: CR=complete remission; CRi=complete remission with incomplete hematologic recovery.
Day 1 Day 8 +/- 2 days (maintain minimum of 6 days between doses). Day 15 Dosing regimen for Cycle 1 All patients: Dose Dose is based on the patient's body surface area (m 2 ). 0.8 mg/m 2 0.5 mg/m 2 0.5 mg/m 2 Cycle length 21 days For patients who achieve a CR or a CRi, and/or to allow for recovery from toxicity, the cycle length may be extended up to 28 days (i.e., 7-day treatment-free interval starting on Day 21).
Dosing regimen for subsequent cycles depending on response to treatment Patients who have achieved a CR CR is defined as < 5% blasts in the bone marrow and the absence of peripheral blood leukemic blasts, full recovery of peripheral blood counts (platelets ≥ 100 × 10 9 /L and absolute neutrophil counts [ANC] ≥ 1 × 10 9 /L) and resolution of any extramedullary disease. or CRi CRi is defined as < 5% blasts in the bone marrow and the absence of peripheral blood leukemic blasts, incomplete recovery of peripheral blood counts (platelets < 100 × 10 9 /L and/or ANC < 1 × 10 9 /L) and resolution of any extramedullary disease. : Dose 0.5… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3. DOSAGE FORMS AND STRENGTHS For injection: 0.9 mg as a white to off-white lyophilized powder in a single-dose vial for reconstitution and further dilution. For injection: 0.9 mg lyophilized powder in a single-dose vial for reconstitution and further dilution. ( 3 )
⛔ Contraindications ▾
4. CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5. WARNINGS AND PRECAUTIONS • Myelosuppression: Monitor complete blood counts; for signs and symptoms of infection; bleeding/hemorrhage; or other effects of myelosuppression during treatment; manage appropriately. ( 5.3 ) • Infusion related reactions: Monitor for infusion related reactions during and for at least 1 hour after infusion ends.
( 5.4 ) • QT interval prolongation: Obtain electrocardiograms (ECGs) and electrolytes at baseline and monitor during treatment. Monitor more frequently when using concomitant mediations known to prolong QT interval. ( 5.5 ) • Embryo-fetal toxicity: Can cause fetal harm.
Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. ( 5.6 , 8.1 , 8.3 )
5.1Hepatotoxicity, Including Hepatic Veno-occlusive Disease (VOD) (also known as Sinusoidal Obstruction Syndrome) BESPONSA can cause hepatotoxicity, including VOD. In adult patients in the INO-VATE ALL trial, hepatotoxicity, including severe, life-threatening, and sometimes fatal hepatic VOD occurred in 23/164 patients (14%) in the BESPONSA arm during or following treatment or following a HSCT after completion of treatment. VOD occurred up to 56 days after the final dose during treatment or during follow-up without an intervening HSCT.
The median time from subsequent HSCT to onset of VOD was 15 days (range: 3-57 days). In the BESPONSA arm, among the 79 patients who proceeded to a subsequent HSCT, VOD occurred in 18/79 patients (23%), and among all 164 patients treated, VOD occurred in 5/164 patients (3%) during study therapy or in follow-up without an intervening HSCT. The risk of VOD was greater in patients who underwent HSCT after BESPONSA treatment; use of HSCT conditioning regimens containing 2 alkylating agents (e.g., busulfan in combination with other alkylating agents) and last total bilirubin level greater than or equal to the ULN before HSCT are significantly associated with an increased risk of VOD.
Other risk factors for VOD in patients treated with BESPONSA included ongoing or prior liver disease, prior HSCT, increased age, later salvage lines, and a greater number of BESPONSA treatment cycles. Patients who have experienced prior VOD or have serious ongoing hepatic liver disease (e.g., cirrhosis, nodular regenerative hyperplasia, active hepatitis) are at an increased risk for worsening of liver disease, including developing VOD, following treatment with BESPONSA. In Study WI203581 (ITCC-059) VOD occurred in 8/53 (15%) of pediatric patients treated with single agent BESPONSA.
Among the 26 pediatric patients who underwent HSCT, VOD occurred in 5 (19%) patients [see Adverse Reactions (6.1) ] . Monitor closely for signs and symptoms of VOD including elevations in total bilirubin, hepatomegaly (which may be painful), rapid weight gain, and ascites. Due to the risk of VOD, for patients proceeding to HSCT, the recommended duration of treatment with BESPONSA is 2 cycles; a third cycle may be considered for those patients who do not achieve a CR or CRi and MRD negativity after 2 cycles [see Dosage and Administration (2.1) ] .
For patients who proceed to HSCT, monitor liver tests at least weekly during the first month post-HSCT, then less frequently thereafter, according to standard medical practice. In adult patients in the INO-VATE ALL trial, increases in liver test abnormalities occurred. Grade 3 or 4 AST, ALT, and total bilirubin abnormal liver tests occurred in 7/160 (4%), 7/161 (4%), and 8/161 patients (5%), respectively.
In pediatric patients in Study WI203581 (ITCC-059), liver test abnormalities occurred, with Grade 3 or 4 increases in AST, ALT, and blood bilirubin in 11/53 (21%), 11/53 (21%), and 5/53 (9%) of patients, respectively [see Adverse Reactions (6.1) ] . In all patients, monitor liver tests, including ALT, AST, total bilirubin, and alkaline phosphatase, prior to and following each dose of BESPONSA. Based on elevations of liver tests withhold, reduce dose, or permanently disco… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6. ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: • Hepatotoxicity, including hepatic VOD (also known as SOS) [see Warnings and Precautions (5.1) ] • Increased risk of post-transplant non-relapse mortality [see Warnings and Precautions (5.2) ] • Myelosuppression [see Warnings and Precautions (5.3) ] • Infusion related reactions [see Warnings and Precautions (5.4) ] • QT interval prolongation [see Warnings and Precautions (5.5) ] The most common (≥ 20%) adverse reactions, including laboratory abnormalities, in adult and pediatric patients are thrombocytopenia, pyrexia, neutropenia, infection, anemia, vomiting, leukopenia, hemorrhage, fatigue, nausea, febrile neutropenia, headache, transaminases increased, abdominal pain, and gamma-glutamyltransferase increased, and hyperbilirubinemia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Relapsed or Refractory B-cell Precursor ALL Adult Patients The safety of BESPONSA was evaluated in adult patients with relapsed or refractory B-cell precursor ALL in the INO-VATE ALL trial. The study was a randomized clinical study of BESPONSA (n=164) versus Investigator’s choice of chemotherapy (fludarabine + cytarabine + granulocyte colony-stimulating factor [FLAG], mitoxantrone + cytarabine [MXN/Ara-C], or high dose cytarabine [HIDAC]) (n=143) [see Clinical Studies (14) ] .
Of the 164 patients who received BESPONSA, the median age was 47 years (range: 18–78 years), 56% were male, 68% had received 1 prior treatment regimen for ALL, 31% had received 2 prior treatment regimens for ALL, 68% were White, 19% were Asian, and 2% were Black. In patients who received BESPONSA, the median duration of treatment was 8.9 weeks (range: 0.1–26.4 weeks), with a median of 3 treatment cycles started in each patient. In patients who received Investigator's choice of chemotherapy, the median duration of treatment was 0.9 weeks (range: 0.1–15.6 weeks), with a median of 1 treatment cycle started in each patient.
In patients who received BESPONSA, the most common (≥ 20%) adverse reactions were thrombocytopenia, neutropenia, infection, anemia, leukopenia, fatigue, hemorrhage, pyrexia, nausea, headache, febrile neutropenia, transaminases increased, abdominal pain, gamma-glutamyltransferase increased, and hyperbilirubinemia. In patients who received BESPONSA, the most common (≥ 2%) serious adverse reactions were infection, febrile neutropenia, hemorrhage, abdominal pain, pyrexia, VOD, and fatigue. In patients who received BESPONSA, the most common (≥ 2%) adverse reactions reported as the reason for permanent discontinuation were infection (6%), thrombocytopenia (2%), hyperbilirubinemia (2%), transaminases increased (2%), and hemorrhage (2%); the most common (≥ 5%) adverse reactions reported as the reason for dosing interruption were neutropenia (17%), infection (10%), thrombocytopenia (10%), transaminases increased (6%), and febrile neutropenia (5%); and the most common (≥ 1%) adverse reactions reported as the reason for dose reduction were neutropenia (1%), thrombocytopenia (1%), and transaminases increased (1%).
VOD was reported in 23/164 patients (14%) who received BESPONSA during or following treatment or following a HSCT after completion of treatment [see Warnings and Precautions (5.1) ]. Table 7 shows the adverse reactions with ≥ 10% incidence reported in patients with relapsed or refractory ALL who received BESPONSA or Investigator's choice of chemotherapy. Table 7.
Adverse Reactions With ≥ 10% Incidence Only adverse reactions with ≥ 10% incidence in the BESPONSA arm are inclu… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7. DRUG INTERACTIONS Drugs That Prolong the QT Interval Concomitant use of BESPONSA with drugs known to prolong the QT interval or induce Torsades de Pointes may increase the risk of a clinically significant QTc interval prolongation [see Clinical Pharmacology (12.2) ] . Discontinue or use alternative concomitant drugs that do not prolong QT/QTc interval while the patient is using BESPONSA.
When it is not feasible to avoid concomitant use of drugs known to prolong QT/QTc, obtain ECGs and electrolytes prior to the start of treatment, after initiation of any drug known to prolong QTc, and periodically monitor as clinically indicated during treatment [see Warnings and Precautions (5.5) ] .
👥 Use in Specific Populations ▾
8. USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on its mechanism of action and findings from animal studies [see Clinical Pharmacology (12.1) , Nonclinical Toxicology (13.1) ] , BESPONSA can cause embryo-fetal harm when administered to a pregnant woman . There are no available data on BESPONSA use in pregnant women to inform a drug-associated risk. In rat embryo-fetal development studies, inotuzumab ozogamicin caused embryo-fetal toxicity at maternal systemic exposures that were ≥ 0.4 times the exposure in patients at the maximum recommended dose, based on AUC [see Data ] .
Advise patients of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2–4% and 15–20%, respectively. Data Animal Data In embryo-fetal development studies in rats, pregnant animals received daily intravenous doses of inotuzumab ozogamicin up to 0.36 mg/m 2 during the period of organogenesis.
Embryo-fetal toxicities including increased resorptions and fetal growth retardation as evidenced by decreased live fetal weights and delayed skeletal ossification were observed at ≥ 0.11 mg/m 2 (approximately 2 times the exposure in patients at the maximum recommended dose, based on AUC). Fetal growth retardation also occurred at 0.04 mg/m 2 (approximately 0.4 times the exposure in patients at the maximum recommended dose, based on AUC). In an embryo-fetal development study in rabbits, pregnant animals received daily intravenous doses up to 0.15 mg/m 2 (approximately 3 times the exposure in patients at the maximum recommended dose, based on AUC) during the period of organogenesis.
At a dose of 0.15 mg/m 2 , slight maternal toxicity was observed in the absence of any effects on embryo‑fetal development.
8.2Lactation Risk Summary There are no data on the presence of inotuzumab ozogamicin or its metabolites in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with BESPONSA and for 2 months after the last dose.
8.3Females and Males of Reproductive Potential Based on its mechanism of action and findings from animal studies, BESPONSA can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating BESPONSA. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with BESPONSA and for 8 months after the last dose [see Nonclinical Toxicology (13.1) ] .
Males Advise males with female partners of reproductive potential to use effective contraception during treatment with BESPONSA and for 5 months after the last dose [see Nonclinical Toxicology (13.1) ] . Infertility Females Based on findings in animals, BESPONSA may impair fertility in females of reproductive potential [see Nonclinical Toxicology (13.1) ] . Males Based on findings in animals, BESPONSA may impair fertility in males of reproductive potential [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use The safety and effectiveness of BESPONSA in pediatric patients 1 year and older with relapsed or refractory CD22-positive B-cell precursor ALL have been established. The use of BESPONSA for this indication is supported by evidence of safety and effectiveness in Study WI203581 (ITCC-059) [see Adverse Reactions (6.1) , Clinical Studies (14.1) ] . The study included patients in the following age groups: 2 patients 1 year to < 2 years old, 10 patients 2 years to < 6 years old, 20 patients 6 years to < 12 years old, and 20 patients 12 years to < 17 years old.
Compared to adults, pediatric patients had a higher incidence of liver test abnormalities; with grade 3-4 increases in AST, ALT, and to… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action and findings from animal studies [see Clinical Pharmacology (12.1) , Nonclinical Toxicology (13.1) ] , BESPONSA can cause embryo-fetal harm when administered to a pregnant woman . There are no available data on BESPONSA use in pregnant women to inform a drug-associated risk. In rat embryo-fetal development studies, inotuzumab ozogamicin caused embryo-fetal toxicity at maternal systemic exposures that were ≥ 0.4 times the exposure in patients at the maximum recommended dose, based on AUC [see Data ] .
Advise patients of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2–4% and 15–20%, respectively. Data Animal Data In embryo-fetal development studies in rats, pregnant animals received daily intravenous doses of inotuzumab ozogamicin up to 0.36 mg/m 2 during the period of organogenesis.
Embryo-fetal toxicities including increased resorptions and fetal growth retardation as evidenced by decreased live fetal weights and delayed skeletal ossification were observed at ≥ 0.11 mg/m 2 (approximately 2 times the exposure in patients at the maximum recommended dose, based on AUC). Fetal growth retardation also occurred at 0.04 mg/m 2 (approximately 0.4 times the exposure in patients at the maximum recommended dose, based on AUC). In an embryo-fetal development study in rabbits, pregnant animals received daily intravenous doses up to 0.15 mg/m 2 (approximately 3 times the exposure in patients at the maximum recommended dose, based on AUC) during the period of organogenesis.
At a dose of 0.15 mg/m 2 , slight maternal toxicity was observed in the absence of any effects on embryo‑fetal development.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BESPONSA in pediatric patients 1 year and older with relapsed or refractory CD22-positive B-cell precursor ALL have been established. The use of BESPONSA for this indication is supported by evidence of safety and effectiveness in Study WI203581 (ITCC-059) [see Adverse Reactions (6.1) , Clinical Studies (14.1) ] . The study included patients in the following age groups: 2 patients 1 year to < 2 years old, 10 patients 2 years to < 6 years old, 20 patients 6 years to < 12 years old, and 20 patients 12 years to < 17 years old.
Compared to adults, pediatric patients had a higher incidence of liver test abnormalities; with grade 3-4 increases in AST, ALT, and total bilirubin in 21%, 21%, and 9%, respectively, in pediatric patients treated with BESPONSA compared to 4%, 4%, and 5% in adults. The safety and effectiveness of BESPONSA in patients < 1 year of age with relapsed or refractory CD22-positive B-cell precursor ALL have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the INO-VATE ALL trial, 30/164 patients (18%) treated with BESPONSA were ≥ 65 years of age. No differences in responses were identified between older and younger patients. Based on a population pharmacokinetic analysis in 765 patients, no adjustment to the starting dose is required based on age [see Clinical Pharmacology (12.3) ] .
🧬 Clinical Pharmacology ▾
12. CLINICAL PHARMACOLOGY
12.1Mechanism of Action Inotuzumab ozogamicin is a CD22-directed antibody drug conjugate (ADC). Inotuzumab recognizes human CD22. The small molecule, N-acetyl-gamma-calicheamicin, is a cytotoxic agent that is covalently attached to the antibody via a linker.
Nonclinical data suggest that the anticancer activity of inotuzumab ozogamicin is due to the binding of the ADC to CD22-expressing tumor cells, followed by internalization of the ADC-CD22 complex, and the intracellular release of N-acetyl-gamma-calicheamicin dimethylhydrazide via hydrolytic cleavage of the linker. Activation of N-acetyl-gamma-calicheamicin dimethylhydrazide induces double-strand DNA breaks, subsequently inducing cell cycle arrest and apoptotic cell death.
12.2Pharmacodynamics During the treatment period, the pharmacodynamic response to BESPONSA was characterized by the depletion of CD22-positive leukemic blasts. Cardiac Electrophysiology In a randomized clinical study in patients with relapsed or refractory ALL, increases in QTcF of ≥ 60 msec from baseline were measured in 4/162 patients (3%) in the BESPONSA arm and 3/124 patients (2%) in the Investigator's choice of chemotherapy arm. Increases in QTcF of > 500 msec were observed in none of the patients in the BESPONSA arm and 1/124 patients (1%) in the Investigator's choice of chemotherapy arm.
Central tendency analysis of the QTcF interval changes from baseline showed that the highest mean (upper bound of the 2-sided 90% CI) for QTcF was 15.3 (21.1) msec, which was observed at Cycle 4/Day 1/1 hour in the BESPONSA arm [see Warnings and Precautions (5.5) ].
12.3Pharmacokinetics The mean C max of inotuzumab ozogamicin was 308 ng/mL. The mean simulated total AUC per cycle was 100,000 ng∙h/mL. In patients with relapsed or refractory ALL, steady-state drug concentration was achieved by Cycle 4.
Following administration of multiple doses, a 5.3 times accumulation of inotuzumab ozogamicin was predicted by Cycle 4. Distribution N-acetyl-gamma-calicheamicin dimethylhydrazide is approximately 97% bound to human plasma proteins in vitro. In humans, the total volume of distribution of inotuzumab ozogamicin was approximately 12 L.
Elimination The pharmacokinetics of inotuzumab ozogamicin was well characterized by a 2-compartment model with linear and time-dependent clearance components. In 234 patients with relapsed or refractory ALL, the clearance of inotuzumab ozogamicin at steady state was 0.0333 L/h and the terminal half-life (t ½ ) was 12.3 days. Following administration of multiple doses, a 5.3 times accumulation of inotuzumab ozogamicin was predicted by Cycle 4.
Metabolism In vitro, N-acetyl-gamma-calicheamicin dimethylhydrazide was primarily metabolized via nonenzymatic reduction. In humans, N-acetyl-gamma-calicheamicin dimethylhydrazide serum levels were typically below the limit of quantitation. Specific Populations The effect of intrinsic factors on inotuzumab ozogamicin pharmacokinetics was assessed using a population pharmacokinetic analysis unless otherwise specified.
Age (18 to 92 years of age), sex, and race (Asian versus non-Asian [Caucasian, Black, and Unspecified]) had no clinically significant effect on the pharmacokinetics of inotuzumab ozogamicin. Body surface area was found to significantly affect inotuzumab ozogamicin disposition. BESPONSA is dosed based on body surface area [see Dosage and Administration (2.1) ].
Patients with Renal Impairment The clearance of inotuzumab ozogamicin in patients with mild renal impairment (creatinine clearance [CL cr; based on the Cockcroft-Gault formula] 60–89 mL/min; n=237), moderate renal impairment (CL cr 30–59 mL/min; n=122), or severe renal impairment (CL cr 15–29 mL/min; n=4) was similar to patients with normal renal function (CL cr ≥ 90 mL/min; n=402). The safety and efficacy of inotuzumab ozogamicin in patients with end stage renal disease with or without hemodialysis is unknown. Patients with Hepatic Impairment The clearanc… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Inotuzumab ozogamicin is a CD22-directed antibody drug conjugate (ADC). Inotuzumab recognizes human CD22. The small molecule, N-acetyl-gamma-calicheamicin, is a cytotoxic agent that is covalently attached to the antibody via a linker.
Nonclinical data suggest that the anticancer activity of inotuzumab ozogamicin is due to the binding of the ADC to CD22-expressing tumor cells, followed by internalization of the ADC-CD22 complex, and the intracellular release of N-acetyl-gamma-calicheamicin dimethylhydrazide via hydrolytic cleavage of the linker. Activation of N-acetyl-gamma-calicheamicin dimethylhydrazide induces double-strand DNA breaks, subsequently inducing cell cycle arrest and apoptotic cell death.
📦 How Supplied / Storage and Handling ▾
16. HOW SUPPLIED/STORAGE AND HANDLING How Supplied BESPONSA (inotuzumab ozogamicin) for injection is supplied as a white to off-white lyophilized powder in a single-dose vial for reconstitution and further dilution. Each vial delivers 0.9 mg inotuzumab ozogamicin.
Each carton (NDC 0008-0100-01) contains one single-dose vial. Storage and Handling Refrigerate (2-8°C; 36-46°F) BESPONSA vials and store in the original carton to protect from light. Do not freeze.
BESPONSA is a hazardous drug. Follow applicable special handling and disposal procedures. 1
📋 Description ▾
11. DESCRIPTION Inotuzumab ozogamicin is a CD22-directed antibody and cytotoxic-drug conjugate (ADC) consisting of 3 components: 1) the recombinant humanized immunoglobulin class G subtype 4 (IgG4) kappa antibody inotuzumab, specific for human CD22, 2) N-acetyl-gamma-calicheamicin that causes double-stranded DNA breaks, and 3) an acid-cleavable linker composed of the condensation product of 4-(4'-acetylphenoxy)-butanoic acid (AcBut) and 3-methyl-3-mercaptobutane hydrazide (known as dimethylhydrazide) that covalently attaches N-acetyl-gamma-calicheamicin to inotuzumab.
Inotuzumab ozogamicin has an approximate molecular weight of 160 kDa. The average number of calicheamicin derivative molecules conjugated to each inotuzumab molecule is approximately 6 with a distribution from 2–8. Inotuzumab ozogamicin is produced by chemical conjugation of the antibody and small molecule components.
The antibody is produced by mammalian (Chinese hamster ovary) cells, and the semisynthetic calicheamicin derivative is produced by microbial fermentation followed by synthetic modification. BESPONSA (inotuzumab ozogamicin) for injection is supplied as a sterile, white to off-white, preservative-free, lyophilized powder for intravenous administration. Each single-dose vial delivers 0.9 mg inotuzumab ozogamicin.
Inactive ingredients are polysorbate 80 (0.36 mg), sodium chloride (2.16 mg), sucrose (180 mg), and tromethamine (8.64 mg). After reconstitution with 4 mL of Sterile Water for Injection, USP, the final concentration is 0.25 mg/mL of inotuzumab ozogamicin with a deliverable volume of 3.6 mL (0.9 mg) and a pH of approximately 8.0. Chemical Structure
💬 Information for Patients ▾
17. PATIENT COUNSELING INFORMATION Hepatotoxicity, Including Hepatic Veno-occlusive Disease (VOD) (also known as Sinusoidal Obstruction Syndrome) Inform patients that liver problems, including severe, life-threatening, or fatal VOD, and increases in liver tests may develop during BESPONSA treatment. Inform patients that they should seek immediate medical advice if they experience symptoms of VOD, which may include elevated bilirubin, rapid weight gain, and abdominal swelling that may be painful.
Inform patients that they should carefully consider the benefit/risk of BESPONSA treatment if they have a prior history of VOD or serious ongoing liver disease [see Warnings and Precautions (5.1) ] . Increased Risk of Post-HSCT Non-Relapse Mortality Inform patients that there is an increased risk of post-HSCT non-relapse mortality after receiving BESPONSA, that the most common causes of post-HSCT non-relapse mortality included infection and VOD. Advise patients to report signs and symptoms of infection [see Warnings and Precautions (5.2) ] .
Myelosuppression Inform patients that decreased blood counts, which may be life-threatening, may develop during BESPONSA treatment and that complications associated with decreased blood counts may include infections, which may be life-threatening or fatal, and bleeding/hemorrhage events. Inform patients that signs and symptoms of infection, bleeding/hemorrhage, or other effects of decreased blood counts should be reported during treatment with BESPONSA [see Warnings and Precautions (5.3) ]. Infusion Related Reactions Advise patients to contact their health care provider if they experience symptoms such as fever, chills, rash, or breathing problems during the infusion of BESPONSA [see Warnings and Precautions (5.4) ] .
QT Interval Prolongation Inform patients of symptoms that may be indicative of significant QTc prolongation including dizziness, lightheadedness, and syncope. Advise patients to report these symptoms and the use of all medications to their healthcare provider [see Warnings and Precautions (5.5) ] . Embryo-Fetal Toxicity Advise males and females of reproductive potential to use effective contraception during BESPONSA treatment and for 5 and 8 months after the last dose, respectively [see Use in Specific Populations (8.3) ] .
Advise women to contact their healthcare provider if they become pregnant, or if pregnancy is suspected, during treatment with BESPONSA. Inform the patient of the potential risk to the fetus [see Warnings and Precautions (5.6) , Use in Specific Populations (8.1) ] . Lactation Advise women against breastfeeding while receiving BESPONSA and for 2 months after the last dose [see Use in Specific Populations (8.2) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The mean C max of inotuzumab ozogamicin was 308 ng/mL. The mean simulated total AUC per cycle was 100,000 ng∙h/mL. In patients with relapsed or refractory ALL, steady-state drug concentration was achieved by Cycle 4.
Following administration of multiple doses, a 5.3 times accumulation of inotuzumab ozogamicin was predicted by Cycle 4. Distribution N-acetyl-gamma-calicheamicin dimethylhydrazide is approximately 97% bound to human plasma proteins in vitro. In humans, the total volume of distribution of inotuzumab ozogamicin was approximately 12 L.
Elimination The pharmacokinetics of inotuzumab ozogamicin was well characterized by a 2-compartment model with linear and time-dependent clearance components. In 234 patients with relapsed or refractory ALL, the clearance of inotuzumab ozogamicin at steady state was 0.0333 L/h and the terminal half-life (t ½ ) was 12.3 days. Following administration of multiple doses, a 5.3 times accumulation of inotuzumab ozogamicin was predicted by Cycle 4.
Metabolism In vitro, N-acetyl-gamma-calicheamicin dimethylhydrazide was primarily metabolized via nonenzymatic reduction. In humans, N-acetyl-gamma-calicheamicin dimethylhydrazide serum levels were typically below the limit of quantitation. Specific Populations The effect of intrinsic factors on inotuzumab ozogamicin pharmacokinetics was assessed using a population pharmacokinetic analysis unless otherwise specified.
Age (18 to 92 years of age), sex, and race (Asian versus non-Asian [Caucasian, Black, and Unspecified]) had no clinically significant effect on the pharmacokinetics of inotuzumab ozogamicin. Body surface area was found to significantly affect inotuzumab ozogamicin disposition. BESPONSA is dosed based on body surface area [see Dosage and Administration (2.1) ].
Patients with Renal Impairment The clearance of inotuzumab ozogamicin in patients with mild renal impairment (creatinine clearance [CL cr; based on the Cockcroft-Gault formula] 60–89 mL/min; n=237), moderate renal impairment (CL cr 30–59 mL/min; n=122), or severe renal impairment (CL cr 15–29 mL/min; n=4) was similar to patients with normal renal function (CL cr ≥ 90 mL/min; n=402). The safety and efficacy of inotuzumab ozogamicin in patients with end stage renal disease with or without hemodialysis is unknown. Patients with Hepatic Impairment The clearance of inotuzumab ozogamicin in patients with mild hepatic impairment (total bilirubin ≤ ULN and AST > ULN, or total bilirubin > 1.0–1.5 × ULN and AST any level; n=150) was similar to patients with normal hepatic function (total bilirubin/AST ≤ ULN; n=611).
There is insufficient data in patients with moderate and severe hepatic impairment (total bilirubin >
1.5ULN). Pediatric Patients The exposure of inotuzumab ozogamicin increases with decreasing body size at the recommended dosage. There was an approximately 30% increase in AUC of inotuzumab ozogamicin in pediatric patients 1 year and older compared with adults.
Drug Interactions In vitro Effect of Metabolic Pathways and Transporter Systems on BESPONSA N-acetyl-gamma-calicheamicin dimethylhydrazide is a substrate of P-glycoprotein (P-gp). Effect of BESPONSA on Metabolic Pathways and Transporter Systems At clinically relevant concentrations, N-acetyl-gamma-calicheamicin dimethylhydrazide had a low potential to: • Inhibit cytochrome P450 (CYP 450) Enzymes : CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP3A4/5. • Induce CYP450 Enzymes : CYP1A2, CYP2B6, and CYP3A4. • Inhibit UGT Enzymes : UGT1A1, UGT1A4, UGT1A6, UGT1A9, and UGT2B7. • Inhibit Drug Transporters : P-gp, breast cancer resistance protein (BCRP), organic anion transporter (OAT)1 and OAT3, organic cation transporter (OCT)2, and organic anion transporting polypeptide (OATP)1B1 and OATP1B3.
At clinically relevant concentrations, inotuzumab ozogamicin had a low potential to: • Inhibit CYP450 Enzymes : CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP3A4/5. • Induce CYP450 Enzyme… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics During the treatment period, the pharmacodynamic response to BESPONSA was characterized by the depletion of CD22-positive leukemic blasts. Cardiac Electrophysiology In a randomized clinical study in patients with relapsed or refractory ALL, increases in QTcF of ≥ 60 msec from baseline were measured in 4/162 patients (3%) in the BESPONSA arm and 3/124 patients (2%) in the Investigator's choice of chemotherapy arm. Increases in QTcF of > 500 msec were observed in none of the patients in the BESPONSA arm and 1/124 patients (1%) in the Investigator's choice of chemotherapy arm.
Central tendency analysis of the QTcF interval changes from baseline showed that the highest mean (upper bound of the 2-sided 90% CI) for QTcF was 15.3 (21.1) msec, which was observed at Cycle 4/Day 1/1 hour in the BESPONSA arm [see Warnings and Precautions (5.5) ].
🔬 Clinical Studies ▾
14. CLINICAL STUDIES Relapsed or Refractory ALL INO-VATE ALL Study – Adult Patients The safety and efficacy of BESPONSA were evaluated in INO-VATE ALL (NCT01564784) a randomized (1:1), open‑label, international, multicenter study in patients with relapsed or refractory ALL. Patients were stratified at randomization based on duration of first remission (< 12 months or ≥ 12 months, salvage treatment (Salvage 1 or 2) and patient age at randomization (< 55 or ≥ 55 years).
Eligible patients were ≥ 18 years of age with Philadelphia chromosome-negative or Philadelphia chromosome-positive relapsed or refractory B-cell precursor ALL. All patients were required to have ≥ 5% bone marrow blasts and to have received 1 or 2 previous induction chemotherapy regimens for ALL. Patients with Philadelphia chromosome-positive B-cell precursor ALL were required to have disease that failed treatment with at least 1 tyrosine kinase inhibitor and standard chemotherapy.
Table 1 shows the dosing regimen used to treat patients. Among all 326 patients who were randomized to receive BESPONSA (N=164) or Investigator's choice of chemotherapy (N=162), 215 patients (66%) had received 1 prior treatment regimen for ALL and 108 patients (33%) had received 2 prior treatment regimens for ALL. The median age was 47 years (range: 18–79 years), 276 patients (85%) had Philadelphia chromosome-negative ALL, 206 patients (63%) had a duration of first remission < 12 months, and 55 patients (17%) had undergone a HSCT prior to receiving BESPONSA or Investigator's choice of chemotherapy.
The two treatment groups were generally balanced with respect to the baseline demographics and disease characteristics. All evaluable patients had B-cell precursor ALL that expressed CD22, with ≥ 90% of evaluable patients exhibiting ≥ 70% leukemic blast CD22 positivity prior to treatment, as assessed by flow cytometry performed at a central laboratory. The efficacy of BESPONSA was established on the basis of CR, the duration of CR, and proportion of MRD-negative CR (< 1 × 10 -4 of bone marrow nucleated cells by flow cytometry) in the first 218 patients randomized.
CR, duration of remission (DoR), and MRD results in the initial 218 randomized patients were consistent with those seen in all 326 randomized patients. Among the initial 218 randomized patients, 64/88 (73%) and 21/88 (24%) of responding patients per EAC achieved CR/CRi in Cycles 1 and 2, respectively, in the BESPONSA arm, and 29/32 (91%) and 1/32 (3%) of responding patients per EAC achieved a CR/CRi in Cycles 1 and 2, respectively, in the Investigator's choice of chemotherapy arm. Table 11 shows the efficacy results from this study.
Table 11. Efficacy Results in Patients With Relapsed or Refractory B-Cell Precursor ALL Who Received BESPONSA or Investigator's Choice of Chemotherapy (FLAG, MXN/Ara-C, or HIDAC) CR CR, per EAC, was defined as < 5% blasts in the bone marrow and the absence of peripheral blood leukemic blasts, full recovery of peripheral blood counts (platelets ≥ 100 × 10 9 /L and absolute neutrophil counts [ANC] ≥ 1 × 10 9 /L) and resolution of any extramedullary disease. CRi CRi, per EAC, was defined as < 5% blasts in the bone marrow and the absence of peripheral blood leukemic blasts, incomplete recovery of peripheral blood counts (platelets < 100 × 10 9 /L and/or ANC < 1 × 10 9 /L) and resolution of any extramedullary disease.
CR/CRi , BESPONSA (N=109) HIDAC, FLAG, or MXN/Ara-C (N=109) BESPONSA (N=109) HIDAC, FLAG or MXN/Ara-C (N=109) BESPONSA (N=109) HIDAC, FLAG, or MXN/Ara-C (N=109) Abbreviations: CI=confidence interval; CR=complete remission; CRi=complete remission with incomplete hematologic recovery; DoR=duration of remission; EAC=Endpoint Adjudication Committee; FLAG=fludarabine + cytarabine + granulocyte colony-stimulating factor; HIDAC=high-dose cytarabine; HR=hazard ratio; MRD=minimal residual disease; MXN/AraC=mitoxantrone + cytarabine; N/n=number of patients; OS=overall survival; PFS=progression-free surviv… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13. NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Formal carcinogenicity studies have not been conducted with inotuzumab ozogamicin. In toxicity studies, rats were dosed weekly for 4 or 26 weeks with inotuzumab ozogamicin at doses up to 4.1 mg/m 2 and 0.73 mg/m 2 , respectively. After 26 weeks of dosing, rats developed hepatocellular adenomas in the liver at 0.73 mg/m 2 (approximately 2 times the exposure in patients at the maximum recommended dose, based on AUC).
Inotuzumab ozogamicin was clastogenic in vivo in the bone marrow of male mice that received single doses ≥ 1.1 mg/m 2 . This is consistent with the known induction of DNA breaks by calicheamicin. N-acetyl-gamma-calicheamicin dimethylhydrazide (the cytotoxic agent released from inotuzumab ozogamicin) was mutagenic in an in vitro bacterial reverse mutation (Ames) assay.
In a female fertility and early embryonic development study, female rats were administered daily intravenous doses of inotuzumab ozogamicin up to 0.11 mg/m 2 for 2 weeks before mating through Day 7 of pregnancy. An increase in the proportion of resorptions and decrease in the number of viable embryos and gravid uterine weights were observed at the 0.11 mg/m 2 dose level (approximately 2 times the exposure in patients at the maximum recommended dose, based on AUC). Additional findings in female reproductive organs occurred in repeat-dose toxicology studies and included decreased ovarian and uterine weights, and ovarian and uterine atrophy.
Findings in male reproductive organs occurred in repeat-dose toxicology studies and included decreased testicular weights, testicular degeneration, hypospermia, and prostatic and seminal vesicle atrophy. Testicular degeneration and hypospermia were nonreversible following a 4-week nondosing period. In the chronic studies of 26-weeks duration, adverse effects on reproductive organs occurred at ≥ 0.07 mg/m 2 in male rats and at 0.73 mg/m 2 in female monkeys [see Use in Specific Populations (8.3) ] .
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Formal carcinogenicity studies have not been conducted with inotuzumab ozogamicin. In toxicity studies, rats were dosed weekly for 4 or 26 weeks with inotuzumab ozogamicin at doses up to 4.1 mg/m 2 and 0.73 mg/m 2 , respectively. After 26 weeks of dosing, rats developed hepatocellular adenomas in the liver at 0.73 mg/m 2 (approximately 2 times the exposure in patients at the maximum recommended dose, based on AUC).
Inotuzumab ozogamicin was clastogenic in vivo in the bone marrow of male mice that received single doses ≥ 1.1 mg/m 2 . This is consistent with the known induction of DNA breaks by calicheamicin. N-acetyl-gamma-calicheamicin dimethylhydrazide (the cytotoxic agent released from inotuzumab ozogamicin) was mutagenic in an in vitro bacterial reverse mutation (Ames) assay.
In a female fertility and early embryonic development study, female rats were administered daily intravenous doses of inotuzumab ozogamicin up to 0.11 mg/m 2 for 2 weeks before mating through Day 7 of pregnancy. An increase in the proportion of resorptions and decrease in the number of viable embryos and gravid uterine weights were observed at the 0.11 mg/m 2 dose level (approximately 2 times the exposure in patients at the maximum recommended dose, based on AUC). Additional findings in female reproductive organs occurred in repeat-dose toxicology studies and included decreased ovarian and uterine weights, and ovarian and uterine atrophy.
Findings in male reproductive organs occurred in repeat-dose toxicology studies and included decreased testicular weights, testicular degeneration, hypospermia, and prostatic and seminal vesicle atrophy. Testicular degeneration and hypospermia were nonreversible following a 4-week nondosing period. In the chronic studies of 26-weeks duration, adverse effects on reproductive organs occurred at ≥ 0.07 mg/m 2 in male rats and at 0.73 mg/m 2 in female monkeys [see Use in Specific Populations (8.3) ] .
📚 References ▾
15. REFERENCES 1. OSHA Hazardous Drugs. OSHA. https://www.osha.gov/hazardous-drugs
📄 Recent Major Changes ▾
Indications and Usage (1) 3/2024 Dosage and Administration, Instructions for Reconstitution, Dilution and Administration (2.4) 3/2024 Warnings and Precautions, Hepatotoxicity, Including Hepatic Veno-occlusive Disease (VOD) (also known as Sinusoidal Obstruction Syndrome) (5.1) 3/2024 Warnings and Precautions, Increased Risk of Post-Transplant Non-Relapse Mortality (5.2) 3/2024 Warnings and Precautions, Myelosuppression (5.3) 3/2024 Warnings and Precautions, Infusion Related Reactions (5.4) 3/2024 Warnings and Precautions, QT Interval Prolongation (5.5) 3/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 0.9 mg Vial Label Pfizer NDC 0008-0100-01 Rx only BESPONSA ™ (inotuzumab ozogamicin) for Injection 0.9 mg/vial For Intravenous Infusion Only No Preservatives Single-dose vial. Discard unused portion. PRINCIPAL DISPLAY PANEL - 0.9 mg Vial Label
PRINCIPAL DISPLAY PANEL - 0.9 mg Vial Carton Pfizer NDC 0008-0100-01 BESPONSA™ (inotuzumab ozogamicin) for Injection 0.9 mg/vial For Intravenous Infusion Only Reconstitution and dilution required. No Preservatives One Single-Dose Vial. Discard unused portion. Rx only PRINCIPAL DISPLAY PANEL - 0.9 mg Vial Carton
Medicaid utilization & spend
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |