
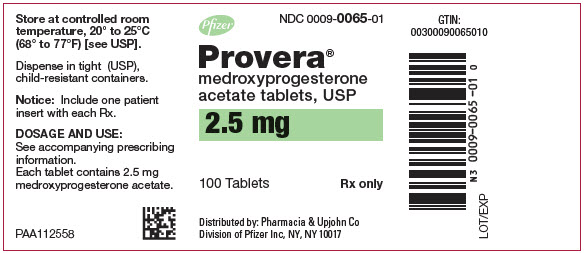
Provera medroxyprogesterone acetate 10 mg Tablet, 100-count
Other active recalls for Medroxyprogesterone Acetate (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Medroxyprogesterone is used to treat abnormal menstruation (periods) or irregular vaginal bleeding. Medroxyprogesterone is also used to bring on a normal menstrual cycle in women who menstruated normally in the past but have not menstruated for at least 6 months and who are not pregnant or undergoing menopause (change of life). Medroxyprogesterone is also used to prevent overgrowth of the lining of the uterus (womb) and may decrease the risk of cancer of the uterus in patients who are taking estrogen. Medroxyprogesterone is in a class of medications called progestins. It works by stopping the...
Read the full MedlinePlus article ↗- It depends on the form. The injectable versions — like Depo-Provera — are mainly used for birth control, and one of them (Depo-subQ Provera 104, the under-the-skin shot) is also ap...
- What exactly is medroxyprogesterone used for — is it just birth control?
- Irregular bleeding and spotting are very common, especially in the first few months. As you continue using the shot, many women find their periods become lighter and less frequent...
- What should I expect to happen to my periods on the birth control shot?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Medroxyprogesterone Acetate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 776XM7047L
Calcium stearate is a white powder derived from stearic acid and calcium. It works as a lubricant and glidant to help the medicine flow smoothly during manufacturing and prevent ingredients from sticking to equipment.
-
UNII J2B2A4N98G
Lactose is a natural sugar derived from milk. In medications, it serves as a filler and binder to add bulk and help hold tablet or capsule ingredients together during manufacturing.
-
UNII T5L8T28FGP
Mineral oil is a clear, odorless liquid derived from crude oil. It acts as a lubricant and emollient in medications, helping pills slide smoothly during manufacturing and aiding moisture retention in topical products.
-
UNII X045WJ989B
Sorbic acid is a preservative derived from berries that prevents mold, yeast, and bacterial growth in medicines. It keeps the product stable and safe during storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $5.05 | $505.30 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Medroxyprogesterone Acetate 10 mg 00555-0779-02 | Teva | 100 tablets | $0.148 | AB | Availability likely | — |
| medroxyprogesterone acetate 10 mg 59762-0056-01 | Mylan | 100 tablets | $0.148 | AB | Availability likely | — |
| Medroxyprogesterone Acetate 10 mg 60687-0105-21 | American | 30 tablets | $0.148 | AB | Availability likely | — |
| Provera 10 mgthis 00009-0051-01 | Pharmacia | 100 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 50090-0166-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 51655-0520-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone 10 mg 54348-0805-05 | PharmPak, | 5 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 55289-0160-05 | PD-Rx | 5 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 63187-0382-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 63629-2612-01 | Bryant | 10 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 63629-8824-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 68071-4132-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 68788-9899-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| Medroxyprogesterone Acetate 10 mg 70518-3070-01 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00009-0051-01 You're viewing this | 100 TABLET in 1 BOTTLE (0009-0051-01) | 2020-07-20 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR DISORDERS, BREAST CANCER AND PROBABLE DEMENTIA FOR ESTROGEN PLUS PROGESTIN THERAPY Cardiovascular Disorders and Probable Dementia Estrogen plus progestin therapy should not be used for the prevention of cardiovascular disease or dementia. (See CLINICAL STUDIES and WARNINGS, Cardiovascular Disorders and Probable Dementia .) The Women's Health Initiative (WHI) estrogen plus progestin substudy reported an increased risk of deep vein thrombosis (DVT), pulmonary embolism (PE), stroke and myocardial infarction (MI) in postmenopausal women (50 to 79 years of age) during 5.6 years of treatment with daily oral conjugated estrogens (CE) [0.625 mg] combined with medroxyprogesterone acetate (MPA) [2.5 mg], relative to placebo.
(See CLINICAL STUDIES and WARNINGS, Cardiovascular Disorders . ) The WHI Memory Study (WHIMS) estrogen plus progestin ancillary study reported an increased risk of developing probable dementia in postmenopausal women 65 years of age or older during 4 years of treatment with daily CE (0.625 mg) combined with MPA (2.5 mg), relative to placebo. It is unknown whether this finding applies to younger postmenopausal women. (See CLINICAL STUDIES and WARNINGS, Probable Dementia and PRECAUTIONS, Geriatric Use .) Breast Cancer The WHI estrogen plus progestin substudy demonstrated an increased risk of invasive breast cancer.
(See CLINICAL STUDIES and WARNINGS, Malignant Neoplasm, Breast Cancer . ) In the absence of comparable data, these risks should be assumed to be similar for other doses of CE and MPA, and other combinations and dosage forms of estrogens and progestins. Progestins with estrogens should be prescribed at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman.
What is the most important information I should know about PROVERA (a progestin hormone)? • Do not use estrogens with progestins to prevent heart disease, heart attacks, strokes, or dementia (decline in brain function). • Using estrogens with progestins may increase your chance of getting heart attacks, strokes, breast cancer, and blood clots. • Using estrogens with progestins may increase your chance of getting dementia, based on a study of women age 65 years or older. • You and your healthcare provider should talk regularly about whether you still need treatment with PROVERA.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE PROVERA tablets are indicated for the treatment of secondary amenorrhea and abnormal uterine bleeding due to hormonal imbalance in the absence of organic pathology, such as fibroids or uterine cancer. They are also indicated for use in the prevention of endometrial hyperplasia in nonhysterectomized postmenopausal women who are receiving daily oral conjugated estrogens 0.625 mg tablets.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Secondary Amenorrhea PROVERA tablets may be given in dosages of 5 or 10 mg daily for 5 to 10 days. A dose for inducing an optimum secretory transformation of an endometrium that has been adequately primed with either endogenous or exogenous estrogen is 10 mg of PROVERA daily for 10 days. In cases of secondary amenorrhea, therapy may be started at any time.
Progestin withdrawal bleeding usually occurs within three to seven days after discontinuing PROVERA therapy. Abnormal Uterine Bleeding Due to Hormonal Imbalance in the Absence of Organic Pathology Beginning on the calculated 16th or 21st day of the menstrual cycle, 5 or 10 mg of PROVERA may be given daily for 5 to 10 days. To produce an optimum secretory transformation of an endometrium that has been adequately primed with either endogenous or exogenous estrogen, 10 mg of PROVERA daily for 10 days beginning on the 16th day of the cycle is suggested.
Progestin withdrawal bleeding usually occurs within three to seven days after discontinuing therapy with PROVERA. Patients with a past history of recurrent episodes of abnormal uterine bleeding may benefit from planned menstrual cycling with PROVERA. Reduction of Endometrial Hyperplasia in Postmenopausal Women Receiving Daily 0.625 mg Conjugated Estrogens When estrogen is prescribed for a postmenopausal woman with a uterus, a progestin should also be initiated to reduce the risk of endometrial cancer.
A woman without a uterus does not need progestin. Use of estrogen, alone or in combination with a progestin, should be with the lowest effective dose and for the shortest duration consistent with treatment goals and risks for the individual woman. Patients should be re-evaluated periodically as clinically appropriate (for example, 3 to 6 month intervals) to determine if treatment is still necessary (see WARNINGS ).
For women who have a uterus, adequate diagnostic measures, such as endometrial sampling, when indicated, should be undertaken to rule out malignancy in cases of undiagnosed persistent or recurring abnormal vaginal bleeding. PROVERA tablets may be given in dosages of 5 or 10 mg daily for 12 to 14 consecutive days per month, in postmenopausal women receiving daily 0.625 mg conjugated estrogens, either beginning on the 1st day of the cycle or the 16th day of the cycle. Patients should be started at the lowest dose.
The lowest effective dose of PROVERA has not been determined.
⛔ Contraindications ▾
CONTRAINDICATIONS PROVERA is contraindicated in women with any of the following conditions: 1. Undiagnosed abnormal genital bleeding. 2.
Known, suspected, or history of breast cancer. 3. Known or suspected estrogen- or progesterone-dependent neoplasia.
4. Active DVT, PE, or a history of these conditions 5. Active arterial thromboembolic disease (for example, stroke and MI), or a history of these conditions.
6. Known anaphylactic reaction or angioedema to PROVERA. 7.
Known liver impairment or disease. 8. Known or suspected pregnancy.
⚠️ Warnings ▾
WARNINGS See BOXED WARNINGS . 1. Cardiovascular Disorders An increased risk of PE, DVT, stroke, and MI has been reported with estrogen plus progestin therapy.
Should any of these events occur or be suspected, estrogen plus progestin therapy should be discontinued immediately. Risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (VTE) (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus) should be managed appropriately. a. Stroke In the WHI estrogen plus progestin substudy, a statistically significant increased risk of stroke was reported in women 50 to 79 years of age receiving CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 per 10,000 women-years).
(See CLINICAL STUDIES .) The increase in risk was demonstrated after the first year and persisted. Should a stroke occur or be suspected, estrogen plus progestin therapy should be discontinued immediately. b. Coronary Heart Disease In the WHI estrogen plus progestin substudy, there was a statistically non-significant increased risk of CHD events reported in women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (41 versus 34 per 10,000 women-years).
An increase in relative risk was demonstrated in year 1, and a trend toward decreasing relative risk was reported in years 2 through 5. In postmenopausal women with documented heart disease (n = 2,763, average 66.7 years of age), in a controlled clinical trial of secondary prevention of cardiovascular disease (Heart and Estrogen/Progestin Replacement Study [HERS]), treatment with daily CE (0.625 mg) plus MPA (2.5mg) demonstrated no cardiovascular benefit. During an average follow-up of 4.1 years, treatment with CE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established coronary heart disease.
There were more CHD events in the CE plus MPA-treated group than in the placebo group in year 1, but not during the subsequent years. Two thousand three hundred and twenty-one (2,321) women from the original HERS trial agreed to participate in an open label extension of HERS, HERS II. Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years overall.
Rates of CHD events were comparable among women in the CE plus MPA group and the placebo group in HERS, HERS II, and overall. c. Venous Thromboembolism In the WHI estrogen plus progestin substudy, a statistically significant 2-fold greater rate of VTE (DVT and PE) was reported in women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (35 versus 17 per 10,000 women-years). Statistically significant increases in risk for both DVT (26 versus 13 per 10,000 women-years) and PE (18 versus 8 per 10,000 women-years) were also demonstrated.
The increase in VTE risk was demonstrated during the first year and persisted. (See CLINICAL STUDIES . ) Should a VTE occur or be suspected, estrogen plus progestin therapy should be discontinued immediately. If feasible, estrogens plus progestins should be discontinued at least 4 to 6 weeks before surgery of the type associated with an increased risk of thromboembolism, or during periods of prolonged immobilization.
2. Malignant Neoplasms a. Breast Cancer The WHI substudy of daily CE (0.625 mg)-alone provided information about breast cancer in estrogen-alone users.
In the WHI estrogen-alone substudy, after an average follow-up of 7.1 years, daily CE-alone was not associated with an increased risk of invasive breast cancer [relative risk (RR) 0.80] compared to placebo (see CLINICAL STUDIES ). After a mean follow-up of 5.6 years, the estrogen plus progestin substudy reported an increased risk of invasive breast cancer in women who took daily CE plus MPA. In this substudy, prior use of estrogen-alone or estrogen plus progestin ther…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS See BOXED WARNINGS , WARNINGS , and PRECAUTIONS . Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The following adverse reactions have been reported in women taking PROVERA tablets, without concomitant estrogens treatment: 1.
Genitourinary system Abnormal uterine bleeding (irregular, increase, decrease), change in menstrual flow, breakthrough bleeding, spotting, amenorrhea, changes in cervical erosion and cervical secretions. 2. Breasts Breast tenderness, mastodynia or galactorrhea has been reported.
3. Cardiovascular Thromboembolic disorders including thrombophlebitis and pulmonary embolism have been reported. 4.
Gastrointestinal Nausea, cholestatic jaundice. 5. Skin Sensitivity reactions consisting of urticaria, pruritus, edema and generalized rash have occurred.
Acne, alopecia and hirsutism have been reported. 6. Eyes Neuro-ocular lesions, for example, retinal thrombosis, and optic neuritis.
7. Central nervous system Mental depression, insomnia, somnolence, dizziness, headache, nervousness. 8.
Miscellaneous Hypersensitivity reactions (for example, anaphylaxis and anaphylactoid reactions, angioedema), rash (allergic) with and without pruritus, change in weight (increase or decrease), pyrexia, edema/fluid retention, fatigue, decreased glucose tolerance. The following adverse reactions have been reported with estrogen plus progestin therapy. 1.
Genitourinary system Abnormal uterine bleeding/spotting, or flow; breakthrough bleeding; spotting; dysmenorrheal/pelvic pain; increase in size of uterine leiomyomata; vaginitis, including vaginal candidiasis; change in amount of cervical secretion; changes in cervical ectropion; ovarian cancer; endometrial hyperplasia; endometrial cancer. 2. Breasts Tenderness, enlargement, pain, nipple discharge, galactorrhea; fibrocystic breast changes; breast cancer.
3. Cardiovascular Deep and superficial venous thrombosis; pulmonary embolism; thrombophlebitis; myocardial infarction; stroke; increase in blood pressure. 4.
Gastrointestinal Nausea, vomiting; abdominal cramps, bloating; cholestatic jaundice; increased incidence of gallbladder disease; pancreatitis; enlargement of hepatic hemangiomas. 5. Skin Chloasma or melasma that may persist when drug is discontinued; erythema multiforme; erythema nodosum; hemorrhagic eruption; loss of scalp hair; hirsutism; pruritus, rash.
6. Eyes Retinal vascular thrombosis, intolerance to contact lenses. 7.
Central nervous system Headache; migraine; dizziness; mental depression; chorea; nervousness; mood disturbances; irritability; exacerbation of epilepsy, dementia. 8. Miscellaneous Increase or decrease in weight; reduced carbohydrate tolerance; aggravation of porphyria; edema; arthalgias; leg cramps; changes in libido; urticaria, angioedema, anaphylactoid/anaphylactic reactions; hypocalcemia; exacerbation of asthma; increased triglycerides.
🔄 Drug / Laboratory Test Interactions ▾
C. Drug-Laboratory Test Interactions The following laboratory results may be altered by the use of estrogen plus progestin therapy: 1. Accelerated prothrombin time, partial thromboplastin time, and platelet aggregation time; increased platelet count; increased factors II, VII antigen, VIII antigen, VIII coagulant activity, IX, X, XII, VII-X complex, II-VII-X complex, and beta-thromboglobulin; decreased levels of anti-factor Xa and antithrombin III, decreased antithrombin III activity; increased levels of fibrinogen and fibrinogen activity; increased plasminogen antigen and activity.
2. Increased thyroid-binding globulin (TBG) levels leading to increased circulating total thyroid hormone levels as measured by protein-bound iodine (PBI), T4 levels (by column or by radioimmunoassay) or T3 levels by radioimmunoassay, T3 resin uptake is decreased, reflecting the elevated TBG. Free T4 and free T3 concentrations are unaltered.
Women on thyroid replacement therapy may require higher doses of thyroid hormone. 3. Other binding proteins may be elevated in serum, for example, corticosteroid binding globulin (CBG), sex hormone binding globulin (SHBG) leading to increased circulating corticosteroid and sex steroids, respectively.
Free hormone concentrations, such as testosterone and estradiol, may be decreased. Other plasma proteins may be increased (angiotensinogen/renin substrate, alpha-1-antitrypsin, ceruloplasmin). 4.
Increased plasma high-density lipoprotein (HDL) and HDL2 cholesterol subfraction concentrations, reduced low-density lipoprotein (LDL) cholesterol concentration, increased triglycerides levels. 5. Impaired glucose tolerance.
🤰 Pregnancy ▾
E. Pregnancy PROVERA should not be used during pregnancy. (See CONTRAINDICATIONS .) There may be increased risks for hypospadias, clitoral enlargement and labial fusion in children whose mothers are exposed to PROVERA during the first trimester of pregnancy. However, a clear association between these conditions with use of PROVERA has not been established.
🧒 Pediatric Use ▾
G. Pediatric Use PROVERA tablets are not indicated in children. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
H. Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing PROVERA alone to determine whether those over 65 years of age differ from younger subjects in their response to PROVERA alone. The Women's Health Initiative Studies In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age.
(See CLINICAL STUDIES .) The Women's Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen-alone or estrogen plus progestin when compared to placebo. (See WARNINGS, Probable Dementia .) Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women. (See WARNINGS, Probable Dementia .)
🆘 Overdosage ▾
OVERDOSAGE Overdosage of estrogen plus progestin therapy may cause nausea and vomiting, breast tenderness, dizziness, abdominal pain, drowsiness/fatigue and withdrawal bleeding may occur in women. Treatment of overdose consists of discontinuation of CE plus MPA together with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Medroxyprogesterone acetate (MPA) administered orally or parenterally in the recommended doses to women with adequate endogenous estrogen, transforms proliferative into secretory endometrium. Androgenic and anabolic effects have been noted, but the drug is apparently devoid of significant estrogenic activity. While parenterally administered MPA inhibits gonadotropin production, which in turn prevents follicular maturation and ovulation, available data indicate that this does not occur when the usually recommended oral dosage is given as single daily doses.
Pharmacokinetics The pharmacokinetics of MPA were determined in 20 postmenopausal women following a single-dose administration of eight PROVERA 2.5 mg tablets or a single administration of two PROVERA 10 mg tablets under fasting conditions. In another study, the steady-state pharmacokinetics of MPA were determined under fasting conditions in 30 postmenopausal women following daily administration of one PROVERA 10 mg tablet for 7 days. In both studies, MPA was quantified in serum using a validated gas chromatography-mass spectrometry (GC-MS) method.
Estimates of the pharmacokinetic parameters of MPA after single and multiple doses of PROVERA tablets were highly variable and are summarized in Table 1. Table 1. Mean (SD) Pharmacokinetic Parameters for Medroxyprogesterone Acetate (MPA) Tablet Strength C max (ng/mL) T max (h) Auc 0–(∞) (ng∙h/mL) t 1/2 (h) Vd/f (L) CL/f (mL/min) Single Dose 2 × 10 mg 1.01 (0.599) 2.65 (1.41) 6.95 (3.39) 12.1 (3.49) 78024 (47220) 64110 (42662) 8 × 2.5 mg 0.805 (0.413) 2.22 (1.39) 5.62 (2.79) 11.6 (2.81) 62748 (40146) 74123 (35126) Multiple Dose 10 mg Following Day 7 dose 0.71 (0.35) 2.83 (1.83) 6.01 (3.16) 16.6 (15.0) 40564 (38256) 41963 (38402) A.
Absorption: No specific investigation on the absolute bioavailability of MPA in humans has been conducted. MPA is rapidly absorbed from the gastrointestinal tract, and maximum MPA concentrations are obtained between 2 to 4 hours after oral administration. Administration of PROVERA with food increases the bioavailability of MPA.
A 10 mg dose of PROVERA, taken immediately before or after a meal, increased MPA C max (50 to 70%) and AUC (18 to 33%). The half-life of MPA was not changed with food. B.
Distribution: MPA is approximately 90% protein bound, primarily to albumin; no MPA binding occurs with sex hormone binding globulin. C. Metabolism: Following oral dosing, MPA is extensively metabolized in the liver via hydroxylation, with subsequent conjugation and elimination in the urine.
D. Excretion: Most MPA metabolites are excreted in the urine as glucuronide conjugates with only minor amounts excreted as sulfates. E.
Specific Populations Hepatic Insufficiency MPA is almost exclusively eliminated via hepatic metabolism. In 14 patients with advanced liver disease, MPA disposition was significantly altered (reduced elimination). In patients with fatty liver, the mean percent dose excreted in the 24-hour urine as intact MPA after a 10 mg or 100 mg dose was 7.3% and 6.4%, respectively.
Renal Insufficiency The effect of renal impairment on the pharmacokinetics of PROVERA has not been studied. F. Drug Interactions Medroxyprogesterone acetate (MPA) is metabolized in-vitro primarily by hydroxylation via the CYP3A4.
Specific drug-drug interaction studies evaluating the clinical effects with CYP3A4 inducers or inhibitors on MPA have not been conducted. Inducers and/or inhibitors of CYP3A4 may affect the metabolism of MPA.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED PROVERA Tablets are available in the following strengths and package sizes: 2.5 mg tablets (scored, round, orange, imprinted PROVERA 2.5) Bottles of 100: NDC 0009-0065-01 5 mg tablets (scored, round, blue, imprinted PROVERA 5) Bottles of 100: NDC 0009-0287-01 10 mg tablets (scored, round, white, imprinted PROVERA 10) Bottles of 100: NDC 0009-0051-01 Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP]. "Keep out of reach of children"
📦 Storage and Handling ▾
Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP]. "Keep out of reach of children"
📋 Description ▾
DESCRIPTION PROVERA ® tablets contain medroxyprogesterone acetate, which is a derivative of progesterone. It is a white to off-white, odorless crystalline powder, stable in air, melting between 200 and 210°C. It is freely soluble in chloroform, soluble in acetone and in dioxane, sparingly soluble in alcohol and in methanol, slightly soluble in ether, and insoluble in water.
The chemical name for medroxyprogesterone acetate is pregn-4-ene-3, 20-dione, 17-(acetyloxy)-6-methyl-, (6α)-. The structural formula is: Each PROVERA tablet for oral administration contains 2.5 mg, 5 mg or 10 mg of medroxyprogesterone acetate and the following inactive ingredients: Calcium stearate, corn starch, lactose, mineral oil, sucrose and talc. The 2.5 mg tablets also contain: FD&C Yellow No.
6. The 5 mg tablets also contain: FD&C Blue No.2 – Aluminum Lake. Chemical Structure
💬 Information for Patients ▾
B. Patient Information Physicians are advised to discuss the Patient Information leaflet with women for whom they prescribe PROVERA. There may be an increased risk of minor birth defects in children whose mothers are exposed to progestins during the first trimester of pregnancy.
The possible risk to the male baby is hypospadias, a condition in which the opening of the penis is on the underside rather than the tip of the penis. This condition occurs naturally in approximately 5 to 8 per 1000 male births. The risk may be increased with exposure to PROVERA.
Enlargement of the clitoris and fusion of the labia may occur in female babies. However, a clear association between hypospadias, clitoral enlargement and labial fusion with use of PROVERA has not been established. Inform the patient of the importance of reporting exposure to PROVERA in early pregnancy.