
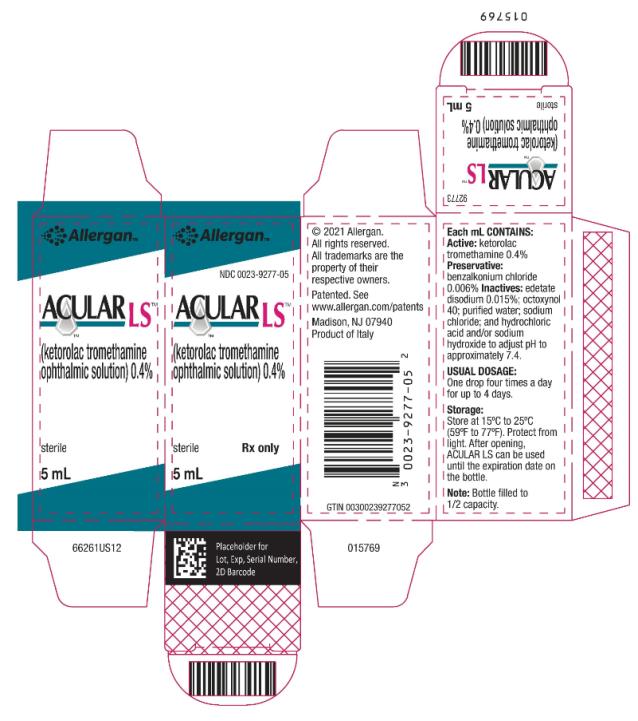
ACULAR LS Ketorolac Tromethamine 4 mg/mL Solution/ Drops
Other active recalls for Ketorolac Tromethamine (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ophthalmic ketorolac is used to treat itchy eyes caused by allergies. It also is used to treat swelling and redness (inflammation) that can occur after cataract surgery. Ketorolac is in a class of medications called nonsteroidal anti-inflammatory drugs (NSAIDs). It works by stopping the release of substances that cause allergy symptoms and inflammation.
Read the full MedlinePlus article ↗- That's actually how ketorolac has to be used — the rules say treatment must always start with an injection, either into a vein or a muscle. The oral tablets are only for continuing...
- Why did my doctor give me a shot first instead of just pills?
- Ketorolac is actually quite hard on your stomach, kidneys, and cardiovascular system when used beyond 5 days — the risks of serious bleeding, ulcers, and other complications go up...
- Why can I only take this for 5 days? My pain might last longer than that.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ketorolac Tromethamine — tap one for details:
Ketorolac Tromethamine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 9T1C662FKS
A synthetic detergent and emulsifier derived from octylphenol. It helps blend water and oil-based ingredients together and improves how the medicine disperses in the body, commonly used in injectable and topical formulations.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $54.526 | $272.63 / 5 ml |
| Medicaid paysCMS SDUD · 12 mo | $57.57 | $287.87 / 5 ml |
| Medicare drug plans payPart D · Q2 2026 | $55.72 | $278.61 / 5 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ketorolac Tromethamine 4 mg/mL 60758-0773-05 | Pacific | 1 bottle | $12.710 | — | Availability likely | save 77% |
| Acular Ls 4 mg/mLthis 00023-9277-05 | Allergan, | 1 bottle | $54.526 | — | Availability likely | — |
| Ketorolac Tromethamine 4 mg/mL 50090-3550-00 | A-S | 1 bottle | — | — | FDA listed | — |
| Ketorolac Tromethamine 4 mg/mL 65862-0775-05 | Aurobindo | 1 bottle | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8008338 ↗ | Drug substance | U-1181 | May 24, 2027 |
| US 8008338*PED ↗ | Drug product | — | Nov 24, 2027 |
Is there a generic version of ACULAR LS 0.4% OPHTH SOL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00023-9277-05 You're viewing this | 1 BOTTLE, DROPPER in 1 CARTON (0023-9277-05) / 5 mL in 1 BOTTLE, DROPPER | 2003-08-19 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ACULAR LS ophthalmic solution is indicated for the reduction of ocular pain and burning/stinging following corneal refractive surgery. ACULAR LS ophthalmic solution is a nonsteroidal, anti-inflammatory drug (NSAID) indicated for the reduction of ocular pain and burning/stinging following corneal refractive surgery. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION One drop of ACULAR LS should be applied in the operated eye 4 times per day as needed for pain and burning/stinging for up to 4 days following corneal refractive surgery. ( 2.1 )
2.1Recommended Dosing The recommended dose of ACULAR LS ophthalmic solution is one drop four times a day in the operated eye as needed for pain and burning/stinging for up to 4 days following corneal refractive surgery.
2.2Use With Other Topical Ophthalmic Medications ACULAR LS has been safely administered in conjunction with other topical ophthalmic medications such as alpha-agonists, antibiotics, beta-blockers, carbonic anhydrase inhibitors, cycloplegics, and mydriatics. Drops should be administered at least 5 minutes apart.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ophthalmic solution containing ketorolac tromethamine 0.4% (4 mg/mL). Ophthalmic solution containing ketorolac tromethamine 0.4% (4 mg/mL). ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ACULAR LS ophthalmic solution is contraindicated in patients with previously demonstrated hypersensitivity to any of the ingredients in the formulation [see Adverse Reactions ( 6.1 )] . Hypersensitivity to any component of this product. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Delayed healing ( 5.1 ) Cross-sensitivity or hypersensitivity ( 5.2 ) Increased bleeding time due to interference with thrombocyte aggregation ( 5.3 ) Corneal effects including keratitis ( 5.4 )
5.1Delayed Healing Topical nonsteroidal anti-inflammatory drugs (NSAIDs) may slow or delay healing. Topical corticosteroids are also known to slow or delay healing. Concomitant use of topical NSAIDs and topical steroids may increase the potential for healing problems.
5.2Cross-Sensitivity or Hypersensitivity There is the potential for cross-sensitivity to acetylsalicylic acid, phenylacetic acid derivatives, and other NSAIDs. There have been reports of bronchospasm or exacerbation of asthma associated with the use of ketorolac tromethamine ophthalmic solution in patients who have either a known hypersensitivity to aspirin/non-steroidal anti-inflammatory drugs or a past medical history of asthma. Therefore, caution should be used when treating individuals who have previously exhibited sensitivities to these drugs.
5.3Increased Bleeding Time With some NSAIDs, there exists the potential for increased bleeding time due to interference with thrombocyte aggregation. There have been reports that ocularly applied nonsteroidal anti-inflammatory drugs may cause increased bleeding of ocular tissues (including hyphemas) in conjunction with ocular surgery. It is recommended that ACULAR LS ophthalmic solution be used with caution in patients with known bleeding tendencies or who are receiving other medications, which may prolong bleeding time.
5.4Corneal Effects Use of topical NSAIDs may result in keratitis. In some susceptible patients, continued use of topical NSAIDs may result in epithelial breakdown, corneal thinning, corneal erosion, corneal ulceration, or corneal perforation. These events may be sight threatening.
Patients with evidence of corneal epithelial breakdown should immediately discontinue use of topical NSAIDs and should be closely monitored for corneal health. Postmarketing experience with topical NSAIDs suggests that patients with complicated ocular surgeries, corneal denervation, corneal epithelial defects, diabetes mellitus, ocular surface diseases (e.g., dry eye syndrome), rheumatoid arthritis, or repeat ocular surgeries within a short period of time may be at increased risk for corneal adverse events which may become sight threatening.
Topical NSAIDs should be used with caution in these patients. Postmarketing experience with topical NSAIDs also suggests that use more than 1 day prior to surgery or use beyond 14 days post-surgery may increase patient risk for the occurrence and severity of corneal adverse events.
5.5Risk of Contamination Do not allow the tip of the bottle to contact the eye or surrounding structures because this could cause the tip to become contaminated by common bacteria known to cause ocular infections. Serious damage to the eye and subsequent loss of vision may result from using contaminated solutions.
5.6Contact Lens Wear ACULAR LS should not be administered while wearing contact lenses.
🤒 Adverse Reactions ▾
6 A DVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Delayed Healing [ see Warnings and Precautions (5.1) ] Cross-Sensitivity or Hypersensitivity [ see Warnings and Precautions (5.2) ] Increased Bleeding Time [ see Warnings and Precautions (5.3) ] Corneal Effects [ see Warnings and Precautions (5.4) ] The most common adverse reactions occurring in 1 - 5% of patients included conjunctival hyperemia, corneal infiltrates, headache, ocular edema and ocular pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AbbVie at 1-800-678-1605 or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most frequently reported adverse reactions for ACULAR LS ophthalmic solution occurring in approximately 1 to 5% of the overall study population were conjunctival hyperemia, corneal infiltrates, headache, ocular edema, and ocular pain.
The most frequent adverse reactions reported with the use of ketorolac tromethamine ophthalmic solutions have been transient stinging and burning on instillation. These reactions were reported by up to 40% of patients participating in clinical trials. Other adverse reactions occurring approximately in 1 to 10% of the time during treatment with other ketorolac tromethamine ophthalmic solutions included allergic reactions (including eye swelling, eyelid edema, and hyperemia), corneal edema, iritis, ocular inflammation, ocular irritation, superficial keratitis, and superficial ocular infections.
Other adverse reactions reported rarely with the use of ketorolac tromethamine ophthalmic solutions included: corneal ulcer, eye dryness, and visual disturbance (blurry vision).
6.2Postmarketing Experience The following adverse reactions have been identified during postmarketing use of ketorolac tromethamine ophthalmic solutions in clinical practice. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. The reactions, which have been chosen for inclusion due to either their seriousness, frequency of reporting, possible causal connection to topical ketorolac tromethamine ophthalmic solutions or a combination of these factors, include bronchospasm or exacerbation of asthma, corneal erosion, corneal perforation, corneal thinning and corneal melt, and epithelial breakdown [see Warnings and Precautions ( 5.2 , 5.4 )] .
👥 Use in Specific Populations ▾
8 U SE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate or well-controlled studies with ACULAR LS in pregnant women. No evidence of teratogenicity has been observed in rats or rabbits with ACULAR LS at clinically relevant doses. 8. 2 Lactation Risk Summary It is not known whether ketorolac when given topically is present in human milk. Because many drugs are excreted in human milk, caution should be exercised when ACULAR LS is administered to a nursing woman.
8.4Pediatric Use Safety and effectiveness of ketorolac tromethamine in pediatric patients below the age of 3 have not been established.
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and other adult patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate or well-controlled studies with ACULAR LS in pregnant women. No evidence of teratogenicity has been observed in rats or rabbits with ACULAR LS at clinically relevant doses.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of ketorolac tromethamine in pediatric patients below the age of 3 have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and other adult patients.
🧬 Clinical Pharmacology ▾
12 C LINICAL PHARMACOLOGY
12.1Mechanism of Action Ketorolac tromethamine is a nonsteroidal anti-inflammatory drug which, when administered systemically, has demonstrated analgesic, anti-inflammatory, and anti-pyretic activity. The mechanism of its action is thought to be due to its ability to inhibit prostaglandin biosynthesis.
12.3Pharmacokinetics One drop of 0.5% ketorolac tromethamine ophthalmic solution was instilled into one eye and one drop of vehicle into the other eye TID in 26 healthy subjects. Five of 26 subjects had detectable concentrations of ketorolac in their plasma (range 11 to 23 ng/mL) at day 10 during topical ocular treatment. Two drops of 0.5% ketorolac tromethamine ophthalmic solution instilled into the eyes of patients 12 hours and 1 hour prior to cataract extraction achieved a mean ketorolac concentration of 95 ng/mL in the aqueous humor of 8 of 9 eyes tested (range 40 to 170 ng/mL).
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ketorolac tromethamine is a nonsteroidal anti-inflammatory drug which, when administered systemically, has demonstrated analgesic, anti-inflammatory, and anti-pyretic activity. The mechanism of its action is thought to be due to its ability to inhibit prostaglandin biosynthesis.
📦 How Supplied / Storage and Handling ▾
16 H OW SUPPLIED/STORAGE AND HANDLING ACULAR LS (ketorolac tromethamine ophthalmic solution) 0.4% is supplied sterile, in white opaque plastic LDPE bottles with white droppers, with a gray high impact polystyrene (HIPS) caps as follows: 5 mL in 10 mL bottle NDC 0023-9277-05 Storage: Store at 15 o C to 25 o C (59 o F to 77 o F). Protect from light. After opening, ACULAR LS can be used until the expiration date on the bottle.
📋 Description ▾
11 D ESCRIPTION ACULAR LS (ketorolac tromethamine ophthalmic solution) 0.4% is a member of the pyrrolo-pyrrole group of nonsteroidal anti-inflammatory drugs (NSAIDs) for ophthalmic use. Its chemical name is (±)-5-Benzoyl-2,3-dihydro-1 H -pyrrolizine-1-carboxylic acid, compound with 2-amino-2-(hydroxymethyl)-1,3-propanediol (1:1), and its molecular weight is 376.40. Its molecular formula is C 19 H 24 N 2 O 6 and it has the following structure: ACULAR LS ophthalmic solution is supplied as a sterile isotonic aqueous 0.4% solution, with a pH of approximately 7.4.
ACULAR LS ophthalmic solution contains a racemic mixture of R-(+) and S-(-)- ketorolac tromethamine. Ketorolac tromethamine may exist in three crystal forms. All forms are equally soluble in water.
The pKa of ketorolac is 3.5. This white to off-white crystalline substance discolors on prolonged exposure to light. The osmolality of ACULAR LS ophthalmic solution is 290 mOsmol/kg.
Each mL of ACULAR LS ophthalmic solution contains: Active: ketorolac tromethamine 0.4%. Preservative : benzalkonium chloride 0.006%. Inactives : edetate disodium 0.015%; octoxynol 40; purified water; sodium chloride; and hydrochloric acid and/or sodium hydroxide to adjust pH.
Chemical Structure
💬 Information for Patients ▾
17 P ATIENT COUNSELING INFORMATION Slow or Delayed Healing Inform patients of the possibility that slow or delayed healing may occur while using nonsteroidal anti-inflammatory drugs (NSAIDs). Avoiding Contamination of the Product Instruct patients to avoid allowing the tip of the bottle to contact the eye or surrounding structures because this could cause the tip to become contaminated by common bacteria known to cause ocular infections. Serious damage to the eye and subsequent loss of vision may result from using contaminated solutions.
Contact Lens Wear Advise patients that ACULAR LS ophthalmic solution should not be administered while wearing contact lenses. Intercurrent Ocular Conditions Advise patients that if they develop an intercurrent ocular condition (e.g., trauma or infection) or have ocular surgery, they should immediately seek their physician’s advice concerning the continued use of ACULAR LS. Concomitant Topical Ocular Therapy Advise patients that if more than one topical ophthalmic medication is being used, the medicines should be administered at least 5 minutes apart.
Distributed by: AbbVie Inc. North Chicago, IL 60064 © 2024 AbbVie. All rights reserved.
ACULAR LS and its design are trademarks of Allergan, Inc., an AbbVie company. V2.1USPI9277 Shape Description automatically generated