
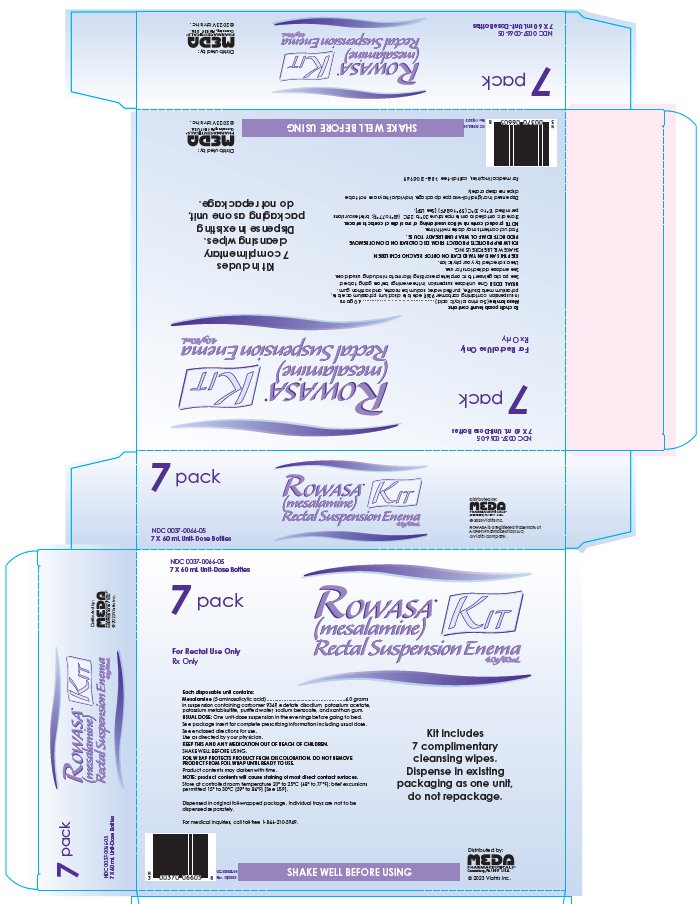
Rowasa mesalamine 4 g/60mL Suspension
Other active recalls for Mesalamine (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Aminosalicylate class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Rectal mesalamine is used to treat ulcerative colitis (a condition which causes swelling and sores in the lining of the colon [large intestine] and rectum), proctitis (swelling in the rectum), and proctosigmoiditis (swelling in the rectum and sigmoid colon [last section of the colon]). Rectal mesalamine is in a class of medications called anti-inflammatory agents. It works by stopping the body from producing a certain substance that may cause inflammation.
Read the full MedlinePlus article ↗- Mesalamine works to reduce inflammation directly in the lining of your colon or rectum. Depending on which product you've been prescribed, it can help bring an active flare of ulce...
- What exactly is mesalamine supposed to do for me?
- It really does matter, and they're not interchangeable. The form your doctor chose depends on where in your bowel the inflammation is. Rectal suppositories (like CANASA) treat infl...
- There are so many different forms — pills, enemas, suppositories. Does it matter which one I use?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mesalamine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII HHT01ZNK31
Carbomer Homopolymer Type B is a synthetic polymer made from acrylic acid. It absorbs water and forms a gel, so it's used in medicines as a thickener, suspending agent, and to help create a smooth texture in creams, gels, and lotions.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII M911911U02
Potassium acetate is a salt derived from potassium and acetic acid. It acts as a buffer to help maintain the medicine's pH balance and may also serve as an electrolyte source in liquid formulations.
-
UNII 65OE787Q7W
Potassium metabisulfite is a chemical salt used as a preservative and antioxidant in medicines and foods. It helps prevent spoilage and discoloration by protecting the product from oxidation and microbial growth.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $483.91 | $812,960.40 / 1680 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mesalamine 4 g/60mL 21922-0045-47 | Encube | 7 bottles | $0.097 | AB | Availability likely | — |
| Mesalamine 4 g/60mL 62559-0420-07 | ANI | 7 bottles | $0.097 | AB | Availability likely | — |
| Mesalamine 4 g/60mL 70954-0301-20 | ANI | 7 bottles | $0.097 | AB | Availability likely | — |
| Mesalamine 4 g/60mL 45802-0098-28 | Padagis | 28 bottles | $0.179 | AB | Availability likely | — |
| Mesalamine 45802-0923-41 | Padagis | 1 kit | $135.189 | AB | Availability likely | — |
| Mesalamine 45802-0929-49 | Padagis | 1 kit | $135.189 | AB | Availability likely | — |
| sfRowasa Sulfite-Free Formulation 4 g/60mL 00037-0022-07 | Viatris | 7 bottles | — | AB | Discontinued | — |
| Rowasa 4 g/60mLthis 00037-0066-03 | Viatris | 28 bottles | — | AB | FDA listed | — |
| Mesalamine 63629-8678-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Mesalamine 63629-8679-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Mesalamine 4 g/60mL 72162-2302-02 | Bryant | 7 bottles | — | AB | FDA listed | — |
| Mesalamine 4 g/60mL 84725-0002-03 | KLM | 7 bottles | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7645801 ↗ | Drug substance | — | Jul 24, 2027 |
Is there a generic version of ROWASA 4 GM/60 ML ENEMA KIT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00037-0066-03 You're viewing this | 28 BOTTLE, DISPENSING in 1 CARTON (0037-0066-03) / 60 mL in 1 BOTTLE, DISPENSING (0037-0066-06) | 2016-03-24 | Active |
| 00037-0066-05 | 7 BOTTLE, DISPENSING in 1 CARTON (0037-0066-05) / 60 mL in 1 BOTTLE, DISPENSING (0037-0066-06) | 2016-03-24 | Active |
Pack size FAQ
What quantity is in NDC 00037-0066-03?
What NDC number is used to bill for this package of Rowasa mesalamine 4 g/60mL Suspension?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ROWASA is indicated for the treatment of active mild to moderate distal ulcerative colitis, proctosigmoiditis or proctitis in adults. ROWASA is an aminosalicylate indicated for treatment of active mild to moderate distal ulcerative colitis, proctosigmoiditis or proctitis in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Evaluate renal function before initiating therapy with ROWASA [see Warnings and Precautions (5.1) ]. Recommended Dosage The recommended dosage is one rectal instillation (4 grams) once a day, preferably at bedtime, and retained for approximately eight hours for 3 to 6 weeks depending on symptoms and sigmoidoscopic findings. Administration Instructions • Shake the bottle to ensure the suspension is homogeneous. • Remove the protective sheath from the applicator tip. • Assume the correct body position: o Lie on the left side with the lower leg extended and the upper right leg flexed forward for balance. o Alternatively, sit in the knee to chest position. • Gently insert the applicator tip in the rectum pointing toward the umbilicus. • Steadily squeeze the bottle to discharge the medication. • Remain in the position for at least 30 minutes.
Administer at bedtime with the objective of retaining it all night. • Drink an adequate amount of fluids during treatment [see Warnings and Precautions (5.7) ] . • Evaluate renal function prior to initiation of ROWASA and periodically while on therapy. ( 2 , 5.1 ) • The recommended dosage is one rectal instillation (4 grams) once a day, preferably at bedtime, and retained for approximately eight hours for 3 to 6 weeks depending on symptoms and sigmoidoscopic findings. ( 2 ) • Drink an adequate amount of fluids.
( 2 . 5.7 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Rectal Suspension: 4 g/60 mL enema bottle; off-white to tan colored suspension Rectal Suspension: 4 g/60 mL enema bottle ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ROWASA is contraindicated in patients with known or suspected hypersensitivity to salicylates, aminosalicylates, sulfites or any other component of this medication [see Warnings and Precautions (5.3) ] . Known or suspected hypersensitivity to salicylates, aminosalicylates, sulfites or any other of the ingredients in ROWASA. ( 4 , 5.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypersensitivity Reactions : Sulfite-related reactions (ROWASA contains potassium metabisulfite) and sulfasalazine-associated reactions (myocarditis and pericarditis) can occur; evaluate patients immediately and discontinue ROWASA if a hypersensitivity reaction is suspected. ( 5.3 ) • Renal Impairment : Assess renal function at the beginning of treatment and periodically during treatment. Evaluate the risks and benefits of ROWASA in patients with known renal impairment or taking nephrotoxic drug.
Discontinue ROWASA if renal function deteriorates while on therapy. ( 5.1 , 7.1 ) • Mesalamine-Induced Acute Intolerance Syndrome : Discontinue treatment if acute intolerance syndrome (cramping, acute abdominal pain, bloody diarrhea, sometimes fever, headache and rash) is suspected. ( 5.2 ) • Hepatic Failure : Evaluate the risks and benefits of using ROWASA in patients with known liver impairment.
( 5.4 ) • Severe Cutaneous Adverse Reactions : Discontinue at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation. ( 5.5 ) • Photosensitivity : Avoid sun exposure if pre-existing skin conditions. ( 5.6 ) • Nephrolithiasis : Cases of nephrolithiasis have been reported with the use of mesalamine.
Mesalamine-containing stones are undetectable by standard radiography or computed tomography (CT). Ensure adequate hydration during treatment. ( 5.7 ) • Interference with Laboratory Tests : Mesalamine may lead to elevated urinary normetanephrine test results.
( 5.8 ) • Intracranial Hypertension : If an unusual headache or visual disturbance occurs during treatment, immediately discontinue treatment and refer patient for further evaluation. ( 5.9 )
5.1Hypersensitivity Reactions Sulfite-Related Reactions ROWASA contains potassium metabisulfite, a sulfite that may cause allergic-type reactions including anaphylactic symptoms and life-threatening or less severe asthmatic episodes in certain susceptible people. The overall prevalence of sulfite sensitivity in the general population is unknown but probably low. Sulfite sensitivity is seen more frequently in asthmatic or in atopic nonasthmatic persons.
Epinephrine is the preferred treatment for serious allergic or emergency situations even though epinephrine injection contains sodium or potassium metabisulfite with the above-mentioned potential liabilities. The alternatives to using epinephrine in a life-threatening situation may not be satisfactory. The presence of a sulfite(s) in epinephrine injection should not deter the administration of the drug for treatment of serious allergic or other emergency situations.
Sulfasalazine-Associated Reactions Hypersensitivity reactions have been reported in patients taking sulfasalazine. Some patients may have a similar reaction to ROWASA or to other compounds that contain or are converted to mesalamine. As with sulfasalazine, mesalamine-induced hypersensitivity reactions may present as internal organ involvement, including myocarditis, pericarditis, nephritis, hepatitis, pneumonitis and hematologic abnormalities.
Evaluate patients immediately if signs or symptoms of a hypersensitivity reaction are present. Discontinue ROWASA if an alternative etiology for the signs and symptoms cannot be established.
5.2Renal Impairment Renal impairment, including minimal change disease, acute and chronic interstitial nephritis, and renal failure have been reported in patients given ROWASA or other products that contain mesalamine or are converted to mesalamine. In animal studies, the kidney was the principal organ of mesalamine toxicity [see Nonclinical Toxicology (13.2) ] . Evaluate the risks and benefits of using ROWASA in patients with known renal impairment or a history of renal disease or taking concomitant nephrotoxic drugs.
Evaluate renal function in all patients prior to initiation and periodically while on ROWASA therapy. Discontinue ROWASA if renal function deteri…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Hypersensitivity reactions [see Warnings and Precautions (5.1) ] • Renal impairment [see Warnings and Precautions (5.2) ] • Mesalamine-induced acute intolerance syndrome [see Warnings and Precautions (5.3) ] • Hepatic failure [see Warnings and Precautions (5.4) ] • Severe cutaneous adverse reactions [see Warnings and Precautions (5.5) ] • Photosensitivity [see Warnings and Precautions (5.6) ] • Nephrolithiasis [see Warnings and Precautions (5.7) ] • Intracranial Hypertension [see Warnings and Precautions (5.9) ] Most common adverse reactions (≥1%) are: gas/flatulence, flu, fever, leg/joint pain, hemorrhoids, rectal pain and hair loss.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Meda Pharmaceuticals Inc at 1-866-210-5949 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Table 1: Adverse Reactions reported in 1% or more of ROWASA-treated patients and greater than placebo in Clinical Trials of ROWASA in Adult Patients with Ulcerative Colitis, Proctosigmoiditis or Proctitis Adverse Reaction ROWASA (N=815) % Placebo (N=128) % Gas/Flatulence 6 4 Flu 5 1 Fever 3 0 Leg/Joint pain 2 1 Hemorrhoids 1 1 Rectal pain 1 0 Hair loss 1 0
6.2Postmarketing Experience The following adverse reactions have been identified during post‑approval use of mesalamine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiac Disorders: myocarditis, pericarditis [see Warnings and Precautions (5.1) ] Gastrointestinal Disorders: pancreatitis Hematologic Disorders: agranulocytosis, aplastic anemia, eosinophilia, leukopenia, neutropenia, pancytopenia, thrombocytopenia Hepatic Disorders: elevated liver enzymes, hepatic failure [see Warnings and Precautions (5.4) ] Immune System Disorders: vasculitis Nervous System: intracranial hypertension Renal and Urinary Disorders: acute renal failure, chronic renal failure, interstitial nephritis, nephrogenic diabetes insipidus, nephrolithiasis, nephrotoxicity [see Warnings and Precautions (5.2) , (5.7) ] • Urine discoloration occurring ex-vivo caused by contact of mesalamine including inactive metabolite, with surfaces or water treated with hypochlorite-containing bleach Reproductive System and Breast Disorders: reversible oligospermia Respiratory, Thoracic, and Mediastinal Disorders: fibrosing alveolitis, pleurisy/pleuritis Skin and Subcutaneous Tissue Disorders: AGEP, DRESS, SJS/TEN [see Warnings and Precautions (5.5) ]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Nephrotoxic Agents including Non-Steroidal Anti-inflammatory Drugs (NSAIDs) : Increased risk of nephrotoxicity; monitor for changes in renal function and mesalamine-related adverse reactions. ( 7.1 ) • Azathioprine or 6-Mercaptopurine : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 7.2 )
7.1Nephrotoxic Agents, Including Non-Steroidal Anti-Inflammatory Drugs The concurrent use of mesalamine with known nephrotoxic agents, including non‑steroidal anti‑inflammatory drugs (NSAIDs), may increase the risk of nephrotoxicity. Monitor patients taking nephrotoxic drugs for changes in renal function and mesalamine-related adverse reactions [see Warnings and Precautions (5.2) ] .
7.2Azathioprine or 6-Mercaptopurine The concurrent use of mesalamine with azathioprine or 6‑mercaptopurine and/or any other drugs known to cause myelotoxicity may increase the risk for blood disorders, bone marrow failure, and associated complications. If concomitant use of ROWASA and azathioprine or 6-mercaptopurine cannot be avoided, monitor blood tests, including complete blood cell counts and platelet counts.
7.3Interference with Urinary Normetanephrine Measurements Use of ROWASA may lead to spuriously elevated test results when measuring urinary normetanephrine by liquid chromatography with electrochemical detection [see Warnings and Precautions (5.8) ] . Consider an alternative, selective assay for normetanephrine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 8.5 )
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ) . There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations ) . In animal reproduction studies, rats and rabbits administered mesalamine during organogenesis at oral doses up to 5 and 8 times the maximum recommended human dose, respectively, did not reveal any evidence of harm to the embryo or the fetus (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies and case series on the use of mesalamine, the active moiety of ROWASA, during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk in major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, and maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies have been performed with mesalamine in rats and rabbits during organogenesis at oral doses up to 5 and 8 times respectively, the maximum recommended human dose, and have revealed no evidence of harm to the embryo or the fetus.
8.2Lactation Risk Summary Data from published literature report the presence of mesalamine and its metabolite, N‑acetyl‑5‑aminosalicylic acid in human milk in small amounts with relative infant doses (RID) of 0.1% or less for mesalamine (see Data ) . There are case reports of diarrhea observed in breastfed infants exposed to mesalamine (see Clinical Considerations ) . There is no information on the effects of mesalamine on milk production.
The lack of clinical data during lactation precludes a clear determination of the risk of ROWASA to an infant during lactation; therefore, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ROWASA and any potential adverse effects on the breastfed child from ROWASA or from the underlying maternal condition. Clinical Considerations Advise the caregiver to monitor the breastfed infant for diarrhea. Data In published lactation studies, maternal mesalamine doses from various oral and rectal formulations and products ranged from 500 mg to 4.8 g daily.
The average concentration of mesalamine in milk ranged from non‑detectable to 0.5 mg/L. The average concentration of N‑acetyl‑5-aminosalicylic acid in milk ranged from 0.2 to 9.3 mg/L. Based on these concentrations, estimated infant daily d…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ) . There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations ) . In animal reproduction studies, rats and rabbits administered mesalamine during organogenesis at oral doses up to 5 and 8 times the maximum recommended human dose, respectively, did not reveal any evidence of harm to the embryo or the fetus (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies and case series on the use of mesalamine, the active moiety of ROWASA, during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk in major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, and maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies have been performed with mesalamine in rats and rabbits during organogenesis at oral doses up to 5 and 8 times respectively, the maximum recommended human dose, and have revealed no evidence of harm to the embryo or the fetus.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of ROWASA did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. Reports from uncontrolled clinical studies and postmarketing reporting systems suggested a higher incidence of blood dyscrasias (i.e., agranulocytosis, neutropenia and pancytopenia) in patients receiving mesalamine-containing products such as ROWASA who were 65 years or older compared to younger adult patients, which may also be associated with ulcerative colitis, use of interacting drugs, or reduced renal function.
Consider monitoring complete blood cell counts and platelet counts in patients 65 years and over during treatment with ROWASA. In general, consider the greater frequency of decreased hepatic, renal, or cardiac function, and of concurrent disease or other drug therapy in patients 65 years and over when prescribing ROWASA.
🆘 Overdosage ▾
10 OVERDOSAGE ROWASA is an aminosalicylate, and symptoms of salicylate toxicity include nausea, vomiting and abdominal pain, tachypnea, hyperpnea, tinnitus, and neurologic symptoms (headache, dizziness, confusion, seizures). Severe salicylate intoxication may lead to electrolyte and blood pH imbalance and potentially to other organ (e.g., renal and liver) involvement. There is no specific antidote for mesalamine overdose; however, conventional therapy for salicylate toxicity may be beneficial in the event of acute overdosage and may include gastrointestinal tract decontamination to prevent further absorption.
Correct fluid and electrolyte imbalance by the administration of appropriate intravenous therapy and maintain adequate renal function.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of 5-ASA (mesalamine) is not fully understood, but appears to be a topical anti-inflammatory effect on colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase pathways (i.e., prostanoids), and through the lipoxygenase pathways (i.e., leukotrienes and hydroxyeicosatetraenoic acids) is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
12.2Pharmacodynamics The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of mesalamine have not been fully characterized.
12.3Pharmacokinetics Absorption Mesalamine administered rectally as ROWASA is poorly absorbed from the colon and is excreted principally in the feces during subsequent bowel movements. The extent of absorption is dependent upon the retention time of the drug product, and there is considerable individual variation. Under clinical conditions patients demonstrated plasma levels 10 to 12 hours post mesalamine administration of 2 mcg/mL, about two-thirds of which was the N-acetyl metabolite.
In addition, steady state plasma levels demonstrated a lack of accumulation of either parent drug or N-acetyl metabolite during repeated daily rectal administrations. Distribution Other than the kidney, the organ distribution and other bioavailability characteristics of absorbed mesalamine in man are not known. The poor colonic absorption of rectally administered mesalamine is substantiated by the low serum concentration of 5-ASA and N-acetyl-5-ASA seen in ulcerative colitis patients after dosage with mesalamine.
Elimination Metabolism It is known that the compound undergoes acetylation but whether this process takes place at colonic or systemic sites has not been elucidated. Excretion Whatever the metabolic site, most of the absorbed mesalamine is excreted in the urine as the N-acetyl-5-ASA metabolite. At steady state, approximately 10 to 30% of the daily 4-gram dose can be recovered in cumulative 24-hour urine collections.
While the elimination half-life of mesalamine is short (0.5 to 1.5 hours), the acetylated metabolite exhibits a half-life of 5 to 10 hours.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of 5-ASA (mesalamine) is not fully understood, but appears to be a topical anti-inflammatory effect on colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase pathways (i.e., prostanoids), and through the lipoxygenase pathways (i.e., leukotrienes and hydroxyeicosatetraenoic acids) is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ROWASA ® (mesalamine) rectal suspension is an off-white to tan colored suspension. Each disposable enema bottle contains 4 grams of mesalamine in 60 mL aqueous suspension. Enema bottles are supplied in boxed, foil-wrapped trays as follows: NDC 0037-0066-01 ..................
Professional Sample NDC 0037-0066-05 .................. Carton of 7 Bottles NDC 0037-0066-14 .................. Carton of 14 Bottles NDC 0037-0066-03 ..................
Carton of 28 Bottles ROWASA ® (mesalamine) rectal suspension is for rectal use only. Storage Store at controlled room temperature 20°C to 25°C (68°F to 77°F); Excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Once the foil wrapped unit of seven bottles is opened, all enemas should be used promptly as directed by your physician.
Contents of enemas removed from the foil pouch may darken with time. Slight darkening will not affect potency, however, enemas with dark brown contents should be discarded.
📋 Description ▾
11 DESCRIPTION The active ingredient in ROWASA ® (mesalamine) Rectal Suspension Enema, a disposable (60 mL) unit, is mesalamine, also known as 5-aminosalicylic acid (5-ASA). Chemically, mesalamine is 5-amino-2-hydroxybenzoic acid. The empirical formula is C 7 H 7 NO 3 , representing a molecular weight of 153.14.
The structural formula is: ROWASA is supplied as a suspension for rectal administration. Each rectal suspension enema unit contains 4 grams of mesalamine. The inactive ingredients are carbomer 934P, edetate disodium, potassium acetate, potassium metabisulfite, purified water and xanthan gum.
Sodium benzoate is added as a preservative. The disposable unit consists of an applicator tip protected by a polyethylene cover and lubricated with USP white petrolatum. The unit has a one-way valve to prevent back flow of the dispensed product.
ROWASA Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Instructions for Use ). Renal Impairment Inform patients that ROWASA may decrease their renal function, especially if they have known renal impairment or are taking nephrotoxic drugs, and periodic monitoring of renal function will be performed while they are on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Warnings and Precautions (5.1) ] .
Mesalamine-Induced Acute Intolerance Syndrome and Other Hypersensitivity Reactions Instruct patients to stop taking ROWASA and report to their healthcare provider if they experience new or worsening symptoms of acute intolerance syndrome (cramping, abdominal pain, bloody diarrhea, fever, headache, and rash) or other symptoms suggestive of mesalamine-induced hypersensitivity [see Warnings and Precautions (5.2 , 5.3) ] . Hepatic Failure Advise patients with known liver disease to contact their healthcare provider if they experience signs or symptoms of worsening liver function [see Warnings and Precautions (5.4) ] .
Severe Cutaneous Adverse Reactions Inform patients of the signs and symptoms of severe cutaneous adverse reactions. Instruct patients to stop taking ROWASA and report to their healthcare provider at first appearance of a severe cutaneous adverse reaction or other sign of hypersensitivity [see Warnings and Precautions (5.5) ] . Photosensitivity Advise patients with pre-existing skin conditions to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors [see Warnings and Precautions (5.7) ] .
Nephrolithiasis Instruct patients to drink an adequate amount of fluids during treatment in order to minimize the risk of kidney stone formation and to contact their healthcare provider if they experience signs or symptoms of a kidney stone (e.g., severe side or back pain, blood in the urine) [see Warnings and Precautions (5.7) ] . Blood Disorders Inform elderly patients and those taking azathioprine or 6-mercaptopurine of the risk for blood disorders and the need for periodic monitoring of complete blood cell counts and platelet counts while on therapy.
Advise patients to complete all blood tests ordered by their healthcare provider [see Drug Interactions (7.2) , Use in Specific Populations (8.5) ] . Intracranial Hypertension Instruct patients to discontinue ROWASA and immediately report to their healthcare provider if unusual headache or visual disturbances occur [see Warnings and Precautions (5.9) ] . Administration Advise patients that ROWASA will cause staining of direct contact surfaces, including but not limited to fabrics, flooring, painted surfaces, marble, granite, vinyl, and enamel.
Administer the product in a suitable location. Instruct patients: • Shake the bottle to ensure the suspension is homogeneous. • Remove the protective sheath from the applicator tip. • Lie on the left side with the lower leg extended and the upper right leg flexed forward for balance. Alternatively, alternative is the knee-chest position. • Gently insert the applicator tip in the rectum pointing toward the umbilicus. • Steadily squeeze the bottle to discharge the medication. • Administer at bedtime with the objective of retaining it all night. • Drink an adequate amount of fluids during treatment [see Warnings and Precautions (5.7) ] . • Advise patients that urine may become discolored reddish-brown while taking ROWASA when it comes in contact with surfaces or water treated with hypochlorite-containing bleach.
If discolored urine is observed, advise patients to observe their urine flow. Report to the healthcare provider only if urine is discolored on leaving the body, before contact with any surface or water (e.g., in the toilet). IN-003606-X11 Rev. x/202x Distributed by: MEDA PHARMACEUTICALS Canonsburg, PA 15317 U.S.A. © 2026 Viatris Inc.
ROWASA is a registered trademark of Alaven Pharmaceutical LLC, a Viatris Company. For M…