
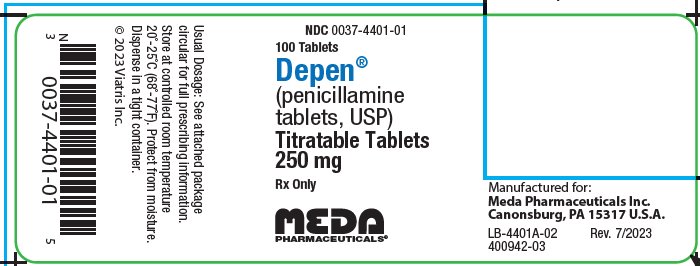
Depen Penicillamine 250 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antirheumatic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Penicillamine is used to treat Wilson's disease (an inherited condition that causes copper to build up in the body and may result in serious symptoms) and cystinuria (an inherited condition which can lead to kidney stones). It is also used in combination with other treatments to treat severe rheumatoid arthritis (a condition in which the body's immune system attacks its own joints, causing pain, swelling, and loss of function) that did not get better after treatment with other medications. Penicillamine is in a class of medications called heavy metal antagonists. It works to treat Wilson's dis...
Read the full MedlinePlus article ↗- That's one of the most important parts of staying safe on penicillamine. This drug can affect your bone marrow and reduce blood cell counts — sometimes severely — and it can also c...
- Why does my doctor keep ordering so many blood tests while I'm on this medication?
- Unfortunately, no — even a small snack matters here. Food, milk, antacids, and iron all significantly reduce how much penicillamine your body absorbs, and they can even inactivate...
- Why do I have to take it on an empty stomach? Can I just take it with a small snack?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Penicillamine — tap one for details:
Penicillamine may be associated with lower levels of 5 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $74.42 | $7,441.54 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Depen 250 mgthis 00037-4401-01 | Viatris | 100 tablets | — | AB | FDA listed | — |
| penicillamine 250 mg 00254-2000-01 | Par | 100 tablets | — | AB | FDA listed | — |
| Penicillamine 250 mg 70748-0153-01 | Lupin | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00037-4401-01 You're viewing this | 100 TABLET in 1 BOTTLE (0037-4401-01) | 1978-11-30 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Physicians planning to use penicillamine should thoroughly familiarize themselves with its toxicity, special dosage considerations, and therapeutic benefits. Penicillamine should never be used casually. Each patient should remain constantly under the close supervision of the physician. Patients should be warned to report promptly any symptoms suggesting toxicity.
🎯 Indications and Usage ▾
INDICATIONS DEPEN is indicated in the treatment of Wilson’s disease, cystinuria, and in patients with severe, active rheumatoid arthritis who have failed to respond to an adequate trial of conventional therapy. Available evidence suggests that DEPEN is not of value in ankylosing spondylitis. Wilson’s Disease - Wilson’s disease (hepatolenticular degeneration) results from the interaction of an inherited defect and an abnormality in copper metabolism.
The metabolic defect, which is the consequence of the autosomal inheritance of one abnormal gene from each parent, manifests itself in a greater positive copper balance than normal. As a result, copper is deposited in several organs and appears eventually to produce pathologic effects most prominently seen in the brain, where degeneration is widespread; in the liver, where fatty infiltration, inflammation, and hepatocellular damage progress to postnecrotic cirrhosis; in the kidney, where tubular and glomerular dysfunction results; and in the eye, where characteristic corneal copper deposits are known as Kayser-Fleischer rings.
Two types of patients require treatment for Wilson’s disease: (1) the symptomatic, and (2) the asymptomatic in whom it can be assumed the disease will develop in the future if the patient is not treated. Diagnosis, suspected on the basis of family or individual history, physical examination, or a low serum concentration of ceruloplasmin*, is confirmed by the demonstration of Kayser-Fleischer rings or, particularly in the asymptomatic patient, by the quantitative demonstration in a liver biopsy specimen of a concentration of copper in excess of 250 mcg/g dry weight.
Treatment has two objectives: (1) to minimize dietary intake and absorption of copper. (2) to promote excretion of copper deposited in tissues. The first objective is attained by a daily diet that contains no more than one or two milligrams of copper.
Such a diet should exclude, most importantly, chocolate, nuts, shellfish, mushrooms, liver, molasses, broccoli, and cereals enriched with copper, and be composed to as great an extent as possible of foods with a low copper content. Distilled or demineralized water should be used if the patient’s drinking water contains more than 0.1 mg of copper per liter. For the second objective, a copper chelating agent is used.
In symptomatic patients, this treatment usually produces marked neurologic improvement, fading of Kayser-Fleischer rings, and gradual amelioration of hepatic dysfunction and psychic disturbances. Clinical experience to date suggests that life is prolonged with the above regimen. Noticeable improvement may not occur for one to three months.
Occasionally, neurologic symptoms become worse during initiation of therapy with DEPEN. Despite this, the drug should not be discontinued permanently. Although temporary interruption may result in clinical improvement of the neurological symptoms, it carries an increased risk of developing a sensitivity reaction upon resumption of therapy (See WARNINGS ). * For quantitative test for serum ceruloplasmin see: Morell, A.G.; Windsor, J.; Sternlieb, I; Scheinberg, I.H.: Measurement of the concentration of ceruloplasmin in serum by determination of its oxidase activity, in “Laboratory Diagnosis of Liver Disease,” F.W.
Sunderman; F.W. Sunderman, Jr., (eds.), St. Louis, Warren H.
Green, Inc., 1968, pp. 193-195. Treatment of asymptomatic patients has been carried out for over ten years.
Symptoms and signs of the disease appear to be prevented indefinitely if daily treatment with DEPEN can be continued. Cystinuria - Cystinuria is characterized by excessive urinary excretion of the dibasic amino acids, arginine, lysine, ornithine, and cystine, and the mixed disulfide of cysteine and homocysteine. The metabolic defect that leads to cystinuria is inherited as an autosomal, recessive trait.
Metabolism of the affected amino acids is influenced by at least two abnormal factors: (1) defective gastrointestinal absorption a…
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION In all patients receiving penicillamine, it is important that DEPEN be given on an empty stomach, at least one hour before meals or two hours after meals, and at least one hour apart from any other drug, food, or milk. Because penicillamine increases the requirement for pyridoxine, patients may require a daily supplement of pyridoxine (see PRECAUTIONS ). Wilson’s Disease - Optimal dosage can be determined by measurement of urinary copper excretion and the determination of free copper in the serum.
The urine must be collected in copper-free glassware, and should be quantitatively analyzed for copper before and soon after initiation of therapy with DEPEN. Determination of 24-hour urinary copper excretions is of greatest value in the first week of therapy with penicillamine. In the absence of any drug reaction, a dose between 0.75 and 1.5 g that results in an initial 24-hour cupriuresis of over 2 mg should be continued for about three months, by which time the most reliable method of monitoring maintenance treatment is the determination of free copper in the serum.
This equals the difference between quantitatively determined total copper and ceruloplasmin-copper. Adequately treated patients will usually have less than 10 mcg free copper/dL of serum. It is seldom necessary to exceed a dosage of 2 g/day.
If the patient is intolerant to therapy with DEPEN, alternative treatment is trientine hydrochloride. In patients who cannot tolerate as much as 1 g/day initially, initiating dosage with 250 mg/day, and increasing gradually to the requisite amount, gives closer control of the effects of the drug and may help to reduce the incidence of adverse reactions. Cystinuria - It is recommended that DEPEN be used along with conventional therapy.
By reducing urinary cystine, it decreases crystalluria and stone formation. In some instances, it has been reported to decrease the size of, and even to dissolve, stones already formed. The usual dosage of DEPEN in the treatment of cystinuria is 2 g/day for adults, with a range of 1 to 4 g/day.
For pediatric patients, dosage can be based on 30 mg/kg/day. The total daily amount should be divided into four doses. If four equal doses are not feasible, give the larger portion at bedtime.
If adverse reactions necessitate a reduction in dosage, it is important to retain the bedtime dose. Initiating dosage with 250 mg/day, and increasing gradually to the requisite amount, gives closer control of the effects of the drug and may help to reduce the incidence of adverse reactions. In addition to taking DEPEN, patients should drink copiously.
It is especially important to drink about a pint of fluid at bedtime and another pint once during the night when urine is more concentrated and more acid than during the day. The greater the fluid intake, the lower the required dosage of DEPEN. Dosage must be individualized to an amount that limits cystine excretion to 100-200 mg/day in those with no history of stones, and below 100 mg/day in those who have had stone formation and/or pain.
Thus, in deter-mining dosage, the inherent tubular defect, the patient’s size, age, and rate of growth, and his diet and water intake all must be taken into consideration. The standard nitroprusside cyanide test has been reported useful as a qualitative measure of the effective dose*: * Lotz, M., Potts, J.T. and Bartter, F.C.: BritMed J 2 : 521, August 28, 1965 (in Medical Memoranda). Add 2 mL of freshly prepared 5 percent sodium cyanide to 5 mL of a 24-hour aliquot of protein-free urine and let stand ten minutes.
Add 5 drops of freshly prepared 5 percent sodium nitroprusside and mix. Cystine will turn the mixture magenta. If the result is negative, it can be assumed that cystine excretion is less than 100 mg/g creatinine.
Although penicillamine is rarely excreted unchanged, it also will turn the mixture magenta. If there is any question as to which substance is causing the reaction, a ferric chloride test can be…
⛔ Contraindications ▾
CONTRAINDICATIONS Except for treatment of Wilson’s disease or certain cases of cystinuria, use of penicillamine during pregnancy is contraindicated (See WARNINGS ). Although breast milk studies have not been reported in animals or humans, mothers on therapy with penicillamine should not nurse their infants. Patients with a history of penicillamine-related aplastic anemia or agranulocytosis should not be restarted on penicillamine (see WARNINGS and ADVERSE REACTIONS ).
Because of its potential for causing renal damage, penicillamine should not be administered to rheumatoid arthritis patients with a history or other evidence of renal insufficiency.
⚠️ Warnings ▾
WARNINGS The use of penicillamine has been associated with fatalities due to certain diseases, such as aplastic anemia, agranulocytosis, thrombocytopenia, Goodpasture’s syndrome, and myasthenia gravis. Because of the potential for serious hematological and renal adverse reactions to occur at any time, routine urinalysis, white and differential blood cell count, hemoglobin determination, and direct platelet count must be done every two weeks for at least the first six months of penicillamine therapy and monthly thereafter.
Patients should be instructed to report promptly the development of signs and symptoms of granulocytopenia and/or thrombocytopenia such as fever, sore throat, chills, bruising, or bleeding. The above laboratory studies should then be promptly repeated. Leukopenia and thrombocytopenia have been reported to occur in up to five percent of patients during penicillamine therapy.
Leukopenia is of the granulocytic series and may or may not be associated with an increase in eosinophils. A confirmed reduction in WBC below 3500 per cubic mL mandates discontinuance of penicillamine therapy. Thrombocytopenia may be on an idiosyncratic basis with decreased or absent megakaryocytes in the marrow, when it is part of an aplastic anemia.
In other cases the thrombocytopenia is presumably on an immune basis since the number of megakaryocytes in the marrow has been reported to be normal or sometimes increased. The development of a platelet count below 100,000 per cubic mL, even in the absence of clinical bleeding, requires at least temporary cessation of penicillamine therapy. A progressive fall in either platelet count or WBC in three successive determinations, even though values are still within the normal range, likewise requires at least temporary cessation.
Proteinuria and/or hematuria may develop during therapy and may be warning signs of membranous glomerulopathy which can progress to a nephrotic syndrome. Close observation of these patients is essential. In some patients the proteinuria disappears with continued therapy; in others penicillamine must be discontinued.
When a patient develops proteinuria or hematuria the physician must ascertain whether it is a sign of drug-induced glomerulopathy or is unrelated to penicillamine. Rheumatoid arthritis patients who develop moderate degrees of proteinuria may be continued cautiously on penicillamine therapy, provided that quantitative 24-hour urinary protein determinations are obtained at intervals of one to two weeks. Penicillamine dosage should not be increased under these circumstances.
Proteinuria which exceeds 1 g/24 hours, or proteinuria which is progressively increasing requires either discontinuance of the drug or a reduction in the dosage. In some patients, proteinuria has been reported to clear following reduction in dosage. In rheumatoid arthritis patients, penicillamine should be discontinued if unexplained gross hematuria or persistent microscopic hematuria develops.
In patients with Wilson’s disease or cystinuria the risks of continued penicillamine therapy in patients manifesting potentially serious urinary abnormalities must be weighed against the expected therapeutic benefits. When penicillamine is used in cystinuria, an annual x-ray for renal stones is advised. Cystine stones form rapidly, sometimes in six months.
Up to one year or more may be required for any urinary abnormalities to disappear after penicillamine has been discontinued. Because of rare reports of intrahepatic cholestasis and toxic hepatitis, liver function tests are recommended every six months for the duration of therapy. Goodpasture’s syndrome has occurred rarely.
The development of abnormal urinary findings associated with hemoptysis and pulmonary infiltrates on x-ray requires immediate cessation of penicillamine. Obliterative bronchiolitis has been reported rarely. The patient should be cautioned to report immediately pulmonary symptoms such as exertional dyspnea, unexplained cough, or wh…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS To report SUSPECTED ADVERSE REACTIONS, contact Viatris at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. Penicillamine is a drug with a high incidence of untoward reactions, some of which are potentially fatal. Therefore, it is mandatory that patients receiving penicillamine therapy remain under close medical supervision throughout the period of drug administration (see WARNINGS and PRECAUTIONS ).
Reported incidences (%) for the most commonly occurring adverse reactions in rheumatoid arthritis patients are noted, based on 17 representative clinical trials reported in the literature (1270 patients). Allergic - Generalized pruritus, early and late rashes (5%), pemphigus (see WARNINGS ), and drug eruptions which may be accompanied by fever, arthralgia, or lymphadenopathy have occurred (see WARNINGS and PRECAUTIONS ). Some patients may show a lupus erythematosus-like syndrome similar to drug-induced lupus produced by other pharmacological agents (see PRECAUTIONS ).
Urticaria and exfoliative dermatitis have occurred. Thyroiditis has been reported; hypoglycemia in association with anti-insulin antibodies has been reported. These reactions are extremely rare.
Some patients may develop a migratory polyarthralgia, often with objective synovitis (see DOSAGE AND ADMINISTRATION ). Gastrointestinal - Anorexia, epigastric pain, nausea, vomiting, or occasional diarrhea may occur (17%). Isolated cases of reactivated peptic ulcer have occurred, as have hepatic dysfunction and pancreatitis.
Intrahepatic cholestasis and toxic hepatitis have been reported rarely. There have been a few reports of increased serum alkaline phosphatase, lactic dehydrogenase, and positive cephalin flocculation and thymol turbidity tests. Some patients may report a blunting, diminution, or total loss of taste perception (12%); or may develop oral ulcerations.
Although rare, cheilosis, glossitis, and gingivo-stomatitis have been reported (see PRECAUTIONS ). Gastrointestinal side effects are usually reversible following cessation of therapy. Hematological - Penicillamine can cause bone marrow depression (see WARNINGS ).
Leukopenia (2%) and thrombocytopenia (4%) have occurred. Fatalities have been reported as a result of thrombocytopenia, agranulocytosis, aplastic anemia, and sideroblastic anemia. Thrombotic thrombocytopenic purpura, hemolytic anemia, red cell aplasia, monocytosis, leukocytosis, eosinophilia, and thrombocytosis have also been reported.
Renal - Patients on penicillamine therapy may develop proteinuria (6%) and/or hematuria which, in some, may progress to the development of the nephrotic syndrome as a result of an immune complex membranous glomerulopathy (see WARNINGS ). Central Nervous System - Tinnitus, optic neuritis, and peripheral sensory and motor neuropathies (including polyradiculoneuropathy, i.e., Guillain-Barre Syndrome) have been reported. Muscular weakness may or may not occur with the peripheral neuropathies.
Neuromuscular - Myasthenia gravis (see WARNINGS ). Other - Adverse reactions that have been reported rarely include thrombophlebitis; hyperpyrexia (see PRECAUTIONS ); falling hair or alopecia; lichen planus; polymyositis; dermatomyositis; mammary hyperplasia; elastosis perforans serpiginosa; toxic epidermal necrolysis; anetoderma (cutaneous macular atrophy); and Goodpasture’s syndrome, a severe and ultimately fatal glomerulonephritis associated with intra-alveolar hemorrhage (see WARNINGS ). Fatal renal vasculitis has also been reported.
Allergic alveolitis, obliterative bronchiolitis, interstitial pneumonitis, and pulmonary fibrosis have been reported in patients with severe rheumatoid arthritis, some of whom were receiving penicillamine. Bronchial asthma also has been reported. Increased skin friability, excessive wrinkling of skin, and development of small, white papules at venipuncture and surgical sites have been reported (see PRECAUTIONS ).
The chelating action of the drug may cau…
🤰 Pregnancy ▾
Use In Pregnancy Penicillamine has been shown to be teratogenic in rats when given in doses 6 times higher than the highest dose recommended for human use (based on a standard weight of 50 kg). Skeletal defects, cleft palates, and fetal toxicity (resorptions) have been reported. There are no controlled studies on the use of penicillamine in pregnant women.
Although normal outcomes have been reported, characteristic congenital cutis laxa and associated birth defects have been reported in infants born of mothers who received therapy with penicillamine during pregnancy. Penicillamine should be used in women of childbearing potential only when the expected benefits outweigh the possible hazards. Women on therapy with penicillamine who are of childbearing potential should be apprised of this risk, advised to report promptly any missed menstrual periods or other indications of possible pregnancy, and followed closely for early recognition of pregnancy.
Wilson’s Disease - Reported experience* shows that continued treatment with penicillamine throughout pregnancy protects the mother against relapse of the Wilson’s disease, and that discontinuation of penicillamine has deleterious effects on the mother. If penicillamine is administered during pregnancy to patients with Wilson’s disease, it is recommended that the daily dosage be limited to 1 g. If cesarean section is planned, the daily dosage should be limited to 250 mg during the last six weeks of pregnancy and post-operatively until wound healing is complete.
Cystinuria - If possible, penicillamine should not be given during pregnancy to women with cystinuria (see CONTRAINDICATIONS ). There are reports of women with cystinuria on therapy with penicillamine who gave birth to infants with generalized connective tissue defects who died following abdominal surgery. If stones continue to form in these patients, the benefits of therapy to the mother must be evaluated against the risk to the fetus.
Rheumatoid Arthritis - Penicillamine should not be administered to rheumatoid arthritis patients who are pregnant (see CONTRAINDICATIONS ) and should be discontinued promptly in patients in whom pregnancy is suspected or diagnosed. There is a report that a woman with rheumatoid arthritis treated with less than one gram a day of penicillamine during pregnancy gave birth (cesarean delivery) to an infant with growth retardation, flattened face with broad nasal bridge, low set ears, short neck with loose skin folds, and unusually lax body skin.
🧒 Pediatric Use ▾
Pediatric Use The efficacy of DEPEN in pediatric patients with juvenile rheumatoid arthritis has not been established.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Penicillamine is a chelating agent recommended for the removal of excess copper in patients with Wilson’s disease. From in vitro studies which indicate that one atom of copper combines with two molecules of penicillamine, it would appear that one gram of penicillamine should be followed by the excretion of about 200 milligrams of copper; however, the actual amount excreted is about one percent of this. Penicillamine also reduces excess cystine excretion in cystinuria.
This is done, at least in part, by disulfide interchange between penicillamine and cystine, resulting in formation of penicillamine-cysteine disulfide, a substance that is much more soluble than cystine and is excreted readily. Penicillamine interferes with the formation of cross-links between tropocollagen molecules and cleaves them when newly formed. The mechanism of action of penicillamine in rheumatoid arthritis is unknown, although it appears to suppress disease activity.
Unlike cytotoxic immunosuppressants, penicillamine markedly lowers IgM rheumatoid factor but produces no significant depression in absolute levels of serum immunoglobulins. Also unlike cytotoxic immunosuppressants, which act on both, penicillamine in vitro depresses T-cell activity but not B-cell activity. In vitro , penicillamine dissociates macroglobulins (rheumatoid factor) although the relationship of the activity to its effect in rheumatoid arthritis is not known.
In rheumatoid arthritis, the onset of therapeutic response to DEPEN may not be seen for two or three months. In those patients who respond, however, the first evidence of suppression of symptoms such as pain, tenderness, and swelling usually is generally apparent within three months. The optimum duration of therapy has not been determined.
If remissions occur, they may last from months to years but usually require continued treatment (see DOSAGE AND ADMINISTRATION ). In all patients receiving penicillamine, it is important that DEPEN be given on an empty stomach, at least one hour before meals or two hours after meals, and at least one hour apart from any other drug, food or milk. This permits maximum absorption and reduces the likelihood of inactivation by metal binding in the gastrointestinal tract.
Methodology for determining the bioavailability of penicillamine is not available; however, penicillamine is known to be a very soluble substance.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Depen® (penicillamine tablets, USP) Titratable Tablets: 250 mg functionally scored, oval, white tablets coded with 37-4401; available in bottles of 100 (NDC 0037-4401-01). Storage: Store at controlled room temperature 20°–25°C (68°–77°F). Protect from moisture.
Dispense in a tight container. To report SUSPECTED ADVERSE REACTIONS, contact Viatris at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. ©2025 Viatris, Inc. DEPEN is a registered trademark of Meda Pharmaceuticals Inc., a Viatris company.
Distributed by: Viatris Specialty LLC Morgantown, WV 26505 U.S.A. 201114-01 Rev. 9/2025 VS:SOV:DEPT:R1
📋 Description ▾
DESCRIPTION Penicillamine is 3-mercapto-D-valine, a disease modifying antirheumatic drug. It is a white or practically white, crystalline powder, freely soluble in water, slightly soluble in alcohol, and insoluble in ether, acetone, benzene, and carbon tetrachloride. Although its configuration is D, it is levorotatory as usually measured: The empirical formula is C 5 H 11 NO 2 S, giving it a molecular weight of 149.21.
The structural formula is: It reacts readily with formaldehyde or acetone to form a thiazolidine-carboxylic acid. Depen ® (penicillamine tablets, USP) Titratable Tablets for oral administration contain 250 mg of penicillamine. Other ingredients (inactive): edetate disodium, hypromellose, lactose, magnesium stearate, magnesium trisilicate, polyethylene glycol, povidone, starch, and stearic acid.
Drug Configuration Structural Formula