
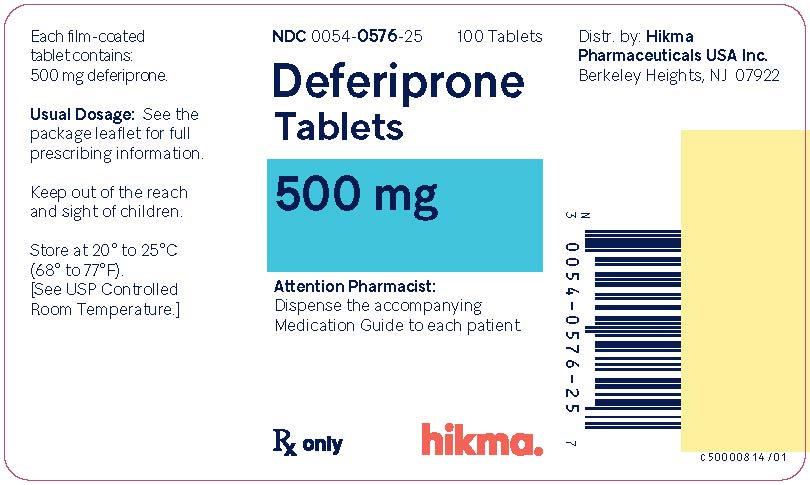
Deferiprone 500 mg Tablet, Coated, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Iron Chelator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Deferiprone is used to remove excess iron in the body in adults and children 3 years of age and older who have thalassemia (an inherited condition that causes a low number of red blood cells). It is also used to remove excess iron in adults and children 3 years of age and older with sickle cell disease (an inherited blood disease) or other types of anemia (a lower than normal number of red blood cells). Deferiprone is in a class of medications called iron chelators. It works by attaching to iron in the body so that it can be excreted (removed from the body).
Read the full MedlinePlus article ↗- Your body has built up too much iron from the blood transfusions you've needed. That extra iron can slowly damage organs like your heart and liver. Deferiprone works by latching on...
- What exactly is deferiprone doing in my body?
- Deferiprone can cause a serious drop in white blood cells — the cells that fight infection. This is the biggest risk with the medication, and it can happen without warning symptoms...
- Why do I need so many blood tests while taking this?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Deferiprone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U076Q6Q621
Polyethylene glycol 1000 is a synthetic compound made from ethylene oxide. It serves as a solvent, lubricant, and humectant in medicines, helping dissolve active ingredients and improve how the product flows and feels.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $46.70 | $4,669.62 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $40.13 | $4,012.85 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Deferiprone 500 mgthis 00054-0576-25 | Hikma | 100 tablets | — | AB | FDA listed | — |
| Deferiprone 500 mg 51672-4196-01 | Sun | 100 tablets | — | AB | FDA listed | — |
| Deferiprone 500 mg 75907-0349-01 | DR. | 100 tablets | — | AB | FDA listed | — |
| Deferiprone 500 mg 73190-0095-01 | AvKARE | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00054-0576-25 You're viewing this | 100 TABLET, COATED in 1 BOTTLE (0054-0576-25) | 2021-06-03 | Active |
| 00054-0576-28 | 300 TABLET, COATED in 1 BOTTLE (0054-0576-28) | 2021-06-03 | Discontinued by firm |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 00054-0576-25?
What is the difference between NDC 00054-0576-25 and NDC 00054-0576-28?
What NDC number is used to bill for this package of Deferiprone 500 mg Tablet, Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: AGRANULOCYTOSIS AND NEUTROPENIA • Deferiprone tablets can cause agranulocytosis that can lead to serious infections and death. Neutropenia may precede the development of agranulocytosis. [see Warnings and Precautions ( 5.1 )] • Measure the absolute neutrophil count (ANC) before starting deferiprone tablets therapy and monitor regularly while on therapy. • Interrupt deferiprone tablets therapy if neutropenia develops. [see Warnings and Precautions ( 5.1 )] • Interrupt deferiprone tablets if infection develops, and monitor the ANC more frequently. [see Warnings and Precautions ( 5.1 )] • Advise patients taking deferiprone tablets to report immediately any symptoms indicative of infection. [see Warnings and Precautions ( 5.1 )] WARNING: AGRANULOCYTOSIS AND NEUTROPENIA See full prescribing information for complete boxed warning. • Deferiprone tablets can cause agranulocytosis that can lead to serious infections and death.
Neutropenia may precede the development of agranulocytosis. ( 5.1 ) • Measure the absolute neutrophil count (ANC) before starting deferiprone tablets and monitor regularly while on therapy. ( 5.1 ) • Interrupt deferiprone tablets therapy if neutropenia develops.
( 5.1 ) • Interrupt deferiprone tablets if infection develops and monitor the ANC more frequently. ( 5.1 ) • Advise patients taking deferiprone tablets to report immediately any symptoms indicative of infection. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Deferiprone tablets are indicated for the treatment of transfusional iron overload in adult patients with thalassemia syndromes when current chelation therapy is inadequate. Limitations of Use: • Safety and effectiveness have not been established for the treatment of transfusional iron overload in patients with myelodysplastic syndrome or in patients with Diamond Blackfan anemia. Pediatric use information is approved for Chiesi USA, Inc.’s FERRIPROX ® (deferiprone) tablets.
However, due to Chiesi USA, Inc.’s marketing exclusivity rights, this drug product is not labeled with that information. Deferiprone tablets are an iron chelator indicated for the treatment of transfusional iron overload in adult patients with thalassemia syndromes when current chelation therapy is inadequate. ( 1 ) Limitations of Use: Safety and effectiveness have not been established for the treatment of transfusional iron overload in patients with myelodysplastic syndrome or in patients with Diamond Blackfan anemia.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Deferiprone Tablets are available in a 500 mg formulation. ( 2.1 ) • To prevent medication errors, before prescribing and dispensing, ensure that the tablet formulation is appropriate for the dosing regimen. Each tablet has distinct identifying characteristics.
( 2.1 , 3 ) • Deferiprone Tablets (three times a day), 500 mg: o Starting oral dosage: 75 mg/kg/day (actual body weight) in three divided doses ( 2.4 ) o Maximum oral dosage: 99 mg/kg/day (actual body weight) in three divided doses ( 2.4 )
2.1Important Dosage and Administration Information Deferiprone Tablets are available in a 500 mg formulation. • Deferiprone Tablets - 500 mg - given three times a day [see Dosage and Administration ( 2.4 )] To prevent medication errors, before prescribing and dispensing, ensure that the tablet formulation is appropriate for the dosing regimen. Each tablet has distinct identifying characteristics [see Dosage Forms and Strengths ( 3 )] . Monitoring for Safety: Due to the risk of agranulocytosis, monitor ANC before and during deferiprone tablets therapy.
Test ANC prior to start of deferiprone tablets therapy and monitor on the following schedule during treatment: • First six months of therapy: Monitor ANC weekly; • Next six months of therapy: Monitor ANC once every two weeks; • After one year of therapy: Monitor ANC every two to four weeks (or at the patient’s blood transfusion interval in patients that have not experienced an interruption due to any decrease in ANC [see Warnings and Precautions ( 5.1 )] . Due to the risk of hepatic transaminase elevations, monitor ALT before and monthly during deferiprone tablets therapy [see Warnings and Precautions ( 5.2 )] .
Due to the risk of zinc deficiency, monitor zinc levels before and regularly during deferiprone tablets therapy [see Warnings and Precautions ( 5.3 )] .
2.4Recommended Dosage for 500 mg Deferiprone Tablets (three times a day) for Adult Patients with Transfusional Iron Overload due to Thalassemia Syndromes Starting Dosage for Three Times a Day Tablets: The recommended starting oral dosage of deferiprone tablets (three times a day) is 75 mg/kg/day (actual body weight), in three divided doses per day. Table 5 describes the number of deferiprone tablets (three times a day) needed to achieve the 75 mg/kg/day total starting dosage. Round dose to the nearest 250 mg (half-tablet).
Table 5: Number of Deferiprone 500 mg Tablets (three times a day) Needed to Achieve the Total Starting Daily Dosage of 75 mg/kg dose (rounded to the nearest half-tablet) Body Weight (kg) Morning Midday Evening 20 1 1 1 30 1.5 1.5 1.5 40 2 2 2 50 2.5 2.5 2.5 60 3 3 3 70 3.5 3.5 3.5 80 4 4 4 90 4.5 4.5
4.5To minimize gastrointestinal upset when first starting therapy, dosing can start at 45 mg/kg/day and increase weekly by 15 mg/kg/day increments until the full prescribed dose is achieved. Dosage Adjustments Tailor dosage adjustments for deferiprone tablets (three times a day) to the individual patient’s response and therapeutic goals (maintenance or reduction of body iron burden). The maximum oral dosage is 99 mg/kg/day (actual body weight), in three divided doses per day.
Table 6 describes the number of deferiprone tablets (three times a day) needed to achieve the 99 mg/day total maximum daily dosage. Table 6: Number of Deferiprone 500 mg Tablets (three times a day) Needed to Achieve the Maximum Total Daily Dosage of 99 mg/kg dose (rounded to the nearest half-tablet) Body Weight (kg) Morning Midday Evening 20 1.5 1 1.5 30 2 2 2 40 3 2 3 50 3.5 3 3.5 60 4 4 4 70 5 4.5 4.5 80 5.5 5 5.5 90 6 6 6 Pediatric use information is approved for Chiesi USA, Inc.’s FERRIPROX ® (deferiprone) tablets.
However, due to Chiesi USA, Inc.’s marketing exclusivity rights, this drug product is not labeled with that information.
2.5Monitoring Ferritin Levels to Assess Efficacy Monitor serum ferritin concentration every two to three months to assess the effect of deferiprone tablets on body iron stores…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • Tablets: 500 mg film-coated, modified capsule shaped, white to off-white with functional scoring and debossed with 54 [score] 422 on one side and plain on the other. • Tablets (three times a day): 500 mg film-coated tablets with functional scoring ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Deferiprone tablets are contraindicated in patients with known hypersensitivity to deferiprone or to any of the excipients in the formulations. The following reactions have been reported in association with the administration of deferiprone: Henoch-Schönlein purpura; urticaria; and periorbital edema with skin rash [see Adverse Reactions ( 6.2 )] . Hypersensitivity to deferiprone or to any of the excipients in the formulations. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Liver Enzyme Elevations: Monitor monthly and discontinue for persistent elevations. ( 5.2 ) • Zinc Deficiency: Monitor during therapy and supplement for deficiency. ( 5.3 ) • Embryo-Fetal Toxicity: Can cause fetal harm. ( 5.4 )
5.1Agranulocytosis and Neutropenia Fatal agranulocytosis can occur with deferiprone tablets use. Deferiprone tablets can also cause neutropenia, which may foreshadow agranulocytosis. Measure the absolute neutrophil count (ANC) before starting deferiprone tablets therapy and monitor it regularly while on therapy [see Dosage and Administration ( 2.1 )] .
Reduction in the frequency of ANC monitoring should be considered on an individual patient basis, according to the health care provider’s assessment of the patient’s understanding of the risk minimization measures required during therapy. Interrupt deferiprone tablets therapy if neutropenia develops (ANC < 1.5 x 10 9 /L). Interrupt deferiprone tablets if infection develops and monitor the ANC frequently.
Advise patients taking deferiprone tablets to immediately interrupt therapy and report to their physician if they experience any symptoms indicative of infection. The incidence of agranulocytosis was 1% of patients in pooled clinical trials of 642 patients with thalassemia syndromes. The mechanism of deferiprone-associated agranulocytosis is unknown.
Agranulocytosis and neutropenia usually resolve upon discontinuation of deferiprone tablets, but there have been reports of agranulocytosis leading to death. Implement a plan to monitor for and to manage agranulocytosis and neutropenia prior to initiating deferiprone tablets treatment. For agranulocytosis (ANC < 0.2 x 10 9 /L) and severe neutropenia (0.2 x 10 9 /L ≤ ANC < 0.5 x 10 9 /L): Consider hospitalization and other management as clinically appropriate.
Do not resume deferiprone tablets in patients who have developed agranulocytosis unless potential benefits outweigh potential risks. Do not rechallenge patients who have developed neutropenia with deferiprone tablets unless potential benefits outweigh potential risks. For neutropenia (ANC < 1.5 x 10 9 /L and ≥ 0.5 x 10 9 /L): Instruct the patient to immediately discontinue deferiprone tablets and all other medications with a potential to cause neutropenia.
Obtain a complete blood cell (CBC) count, including a white blood cell (WBC) count corrected for the presence of nucleated red blood cells, an absolute neutrophil count (ANC), and a platelet count daily until recovery (ANC ≥ 1.5 x 10 9 /L).
5.2Liver Enzyme Elevations In pooled clinical trials, 7.5% of 642 patients with thalassemia syndromes treated with deferiprone tablets developed increased ALT values. Four (0.62%) deferiprone tablet-treated subjects discontinued the drug due to increased serum ALT levels and 1 (0.16%) due to an increase in both ALT and AST. Monitor serum ALT values monthly during therapy with deferiprone tablets and consider interruption of therapy if there is a persistent increase in the serum transaminase levels [see Dosage and Administration ( 2.1 )] .
5.3Zinc Deficiency Decreased plasma zinc concentrations have been observed on deferiprone tablets therapy. Monitor plasma zinc annually, and supplement in the event of a deficiency [see Dosage and Administration ( 2.1 )] .
5.4Embryo-Fetal Toxicity Based on findings from animal reproduction studies and evidence of genotoxicity, deferiprone tablets can cause fetal harm when administered to a pregnant woman. The available data on the use of deferiprone tablets in pregnant women are insufficient to inform risk. In animal studies, administration of deferiprone during the period of organogenesis resulted in embryo-fetal death and malformations at doses lower than equivalent human clinical doses.
Advise pregnant women and females of reproductive potential of the potential risk to the fetus [see Use in Specific Populations ( 8.1 )] . Advise females of reproductive potential to use an effective method of con…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described below and elsewhere in the labeling: • Agranulocytosis and Neutropenia [see Warnings and Precautions ( 5.1 )] • Liver Enzyme Elevations [see Warnings and Precautions ( 5.2 )] • Zinc Deficiency [see Warnings and Precautions ( 5.3 )] • The most common adverse reactions in patients with thalassemia (incidence ≥ 6%) are nausea, vomiting, abdominal pain, arthralgia, ALT increased and neutropenia. ( 5.1 , 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-800-962-8364 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The following adverse reaction information represents the pooled data collected from single arm or active-controlled clinical trials with deferiprone tablets (three times a day). Thalassemia Syndromes: The safety of deferiprone tablets was evaluated in the pooled clinical trial database [see Clinical Studies ( 14.1 )] .
Patients received deferiprone tablets (three times a day). Deferiprone tablets were administered orally three times a day (total daily dose either 50, 75, or 99 mg/kg), N=642. Among 642 patients receiving deferiprone tablets, 492 (76.6%) were exposed for 6 months or longer and 365 (56.9%) were exposed for greater than one year.
The median age of patients who received deferiprone tablets was 19 years (range 1, 77 years); 50.2% female; 71.2% White, 17.8% Asian, 9.2% Unknown, 1.2% Multi-racial and 0.6% Black. The most serious adverse reaction reported in clinical trials with deferiprone tablets was agranulocytosis [see Warnings and Precautions ( 5.1 )] . The most common adverse reactions (≥6%) reported during clinical trials were nausea, vomiting, abdominal pain, arthralgia, alanine aminotransferase increased and neutropenia.
The table below lists the adverse drug reactions that occurred in at least 1% of patients treated with deferiprone tablets in clinical trials in patients with thalassemia syndromes. Table 7: Adverse reactions occurring in ≥ 1% of deferiprone tablets-treated patients with thalassemia syndromes Body System Adverse Reaction (N=642) % Patients BLOOD AND LYMPHATIC SYSTEM DISORDERS Neutropenia Neutropenia includes events of severe neutropenia (ANC ≥ 0.2 x 10 9 /L and < 0.5 x 10 9 /L). 7 Agranulocytosis Agranulocytosis (ANC < 0.2 x 10 9 /L) 1 GASTROINTESTINAL DISORDERS Nausea 13 Abdominal pain/discomfort 10 Vomiting 10 Diarrhea 3 Dyspepsia 2 INVESTIGATIONS Alanine aminotransferase increased 7 Weight increased 2 Aspartate aminotransferase increased 1 METABOLISM AND NUTRITION DISORDERS Increased appetite 4 Decreased appetite 1 MUSCULOSKELETAL AND CONNECTIVE TISSUE DISORDERS Arthralgia 10 Back pain 2 Pain in extremity 2 Arthropathy 1 NERVOUS SYSTEM DISORDERS Headache 2 Gastrointestinal symptoms such as nausea, vomiting, and abdominal pain were the most frequent adverse reactions reported by patients participating in clinical trials and led to the discontinuation of deferiprone tablets therapy in 1.6% of patients.
Chromaturia (reddish/brown discoloration of the urine) is a result of the excretion of iron in the urine.
6.2Postmarketing Experience The following additional adverse reactions have been reported in patients receiving deferiprone tablets. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or to establish a causal relationship to drug exposure. Blood and lymphatic system disorders: thrombocytosis, pancytopenia.
Cardiac disorders: atrial fibrillation, cardiac failure. Congenital, familial and genetic disorders: hypospadias. Eye disorders: diplopia, papilledema, retinal toxicity.
G…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Drugs Associated with Neutropenia or Agranulocytosis: Avoid co-administration. If co-administration is unavoidable, closely monitor the absolute neutrophil count. ( 7.1 ) • UGT1A6 Inhibitors: Avoid co-administration. ( 7.2 ) • Polyvalent Cations: Allow at least a 4-hour interval between administration of deferiprone tablets and drugs or supplements containing polyvalent cations (e.g., iron, aluminum, or zinc). ( 2.2 , 7.2 )
7.1Drugs Associated with Neutropenia or Agranulocytosis Avoid co-administration of deferiprone tablets with other drugs known to be associated with neutropenia or agranulocytosis. If co-administration is unavoidable, closely monitor the absolute neutrophil count [see Warnings and Precautions ( 5.1 )] .
7.2Effect of Other Drugs on Deferiprone Tablets UDP-Glucuronosyltransferases (UGTs): Avoid use of UGT1A6 inhibitors (e.g., diclofenac, probenecid, or silymarin (milk thistle)) with deferiprone tablets [see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 )] . Polyvalent Cations: Deferiprone has the potential to bind polyvalent cations (e.g., iron, aluminum, and zinc); allow at least a 4-hour interval between deferiprone tablets and other medications (e.g., antacids), or supplements containing these polyvalent cations [see Dosage and Administration ( 2.2 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary: In animal reproduction studies, oral administration of deferiprone to pregnant rats and rabbits during organogenesis at doses 33% and 49%, respectively, of the maximum recommended human dose (MRHD) resulted in structural abnormalities, embryo-fetal mortality and alterations to growth ( see Data ). The limited available data from deferiprone use in pregnant women are insufficient to inform a drug-associated risk of major birth defects and miscarriage. Based on evidence and developmental toxicity in animal studies, deferiprone tablets can cause fetal harm when administered to a pregnant woman.
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and of miscarriage is 2-4% and 15-20%, respectively. Data: Human Data: Post-marketing data available from 39 pregnancies of deferiprone-treated patients and 10 pregnancies of partners of deferiprone-treated patients are as follows: Of the 39 pregnancies in deferiprone-treated patients, 23 resulted in healthy newborns, 6 ended in spontaneous abortion, 9 had unknown outcomes, and 1 infant was born with anal atresia, nephroptosis, ventricular septal defect, hemivertebra and urethral fistula.
Of the 10 pregnancies in partners of deferiprone-treated patients, 5 resulted in healthy newborns, 1 resulted in a healthy newborn with slight hypospadias, 1 was electively terminated, 1 resulted in the intrauterine death of twins, and 2 had unknown outcomes. Animal Data: During organogenesis, pregnant rats and rabbits received deferiprone at oral doses of 0, 30, 80 or 200 mg/kg/day, and 0, 10, 50, or 150 mg/kg/day, respectively. The daily dose was administered as two equal divided doses approximately 7 hours apart.
Doses of 200 mg/kg/day in rats and 150 mg/kg/day in rabbits, approximately 33% and 49% of the MRHD, respectively, resulted in increased post-implantation loss and reduced fetal weights in the presence of maternal toxicity (reduced maternal body weight and body weight gain in both rats and rabbits; abnormal large placenta at low incidence in rats). The 200 mg/kg/day dose in rats resulted in external, visceral and skeletal fetal malformations, such as cranial malformations, cleft palate, limb malrotation, anal atresia, internal hydrocephaly, anophthalmia, and fused bones.
The dose of 150 mg/kg/day in rabbits resulted in external fetal malformations (partially opened eyes) and minor blood vessel and skeletal variations. In rats, malformations including micrognathia and persistent ductus arteriosus could be observed in the absence of maternal toxicity at doses equal to or greater than 30 and 80 mg/kg/day, approximately 5% and 13% of the MHRD, respectively.
8.2Lactation Risk Summary: There is no information regarding the presence of deferiprone in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, including the potential for tumorigenicity shown for deferiprone in animal studies, advise patients that breastfeeding is not recommended during treatment with deferiprone tablets, and for at least 2 weeks after the last dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing: Pregnancy testing is recommended for females of reproductive potential prior to initiating deferiprone tablets. Contraception: Females: Deferiprone tablets can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )] . Advise female patients of reproductive potential to use effective contraception during treatment with deferiprone tablets…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary: In animal reproduction studies, oral administration of deferiprone to pregnant rats and rabbits during organogenesis at doses 33% and 49%, respectively, of the maximum recommended human dose (MRHD) resulted in structural abnormalities, embryo-fetal mortality and alterations to growth ( see Data ). The limited available data from deferiprone use in pregnant women are insufficient to inform a drug-associated risk of major birth defects and miscarriage. Based on evidence and developmental toxicity in animal studies, deferiprone tablets can cause fetal harm when administered to a pregnant woman.
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and of miscarriage is 2-4% and 15-20%, respectively. Data: Human Data: Post-marketing data available from 39 pregnancies of deferiprone-treated patients and 10 pregnancies of partners of deferiprone-treated patients are as follows: Of the 39 pregnancies in deferiprone-treated patients, 23 resulted in healthy newborns, 6 ended in spontaneous abortion, 9 had unknown outcomes, and 1 infant was born with anal atresia, nephroptosis, ventricular septal defect, hemivertebra and urethral fistula.
Of the 10 pregnancies in partners of deferiprone-treated patients, 5 resulted in healthy newborns, 1 resulted in a healthy newborn with slight hypospadias, 1 was electively terminated, 1 resulted in the intrauterine death of twins, and 2 had unknown outcomes. Animal Data: During organogenesis, pregnant rats and rabbits received deferiprone at oral doses of 0, 30, 80 or 200 mg/kg/day, and 0, 10, 50, or 150 mg/kg/day, respectively. The daily dose was administered as two equal divided doses approximately 7 hours apart.
Doses of 200 mg/kg/day in rats and 150 mg/kg/day in rabbits, approximately 33% and 49% of the MRHD, respectively, resulted in increased post-implantation loss and reduced fetal weights in the presence of maternal toxicity (reduced maternal body weight and body weight gain in both rats and rabbits; abnormal large placenta at low incidence in rats). The 200 mg/kg/day dose in rats resulted in external, visceral and skeletal fetal malformations, such as cranial malformations, cleft palate, limb malrotation, anal atresia, internal hydrocephaly, anophthalmia, and fused bones.
The dose of 150 mg/kg/day in rabbits resulted in external fetal malformations (partially opened eyes) and minor blood vessel and skeletal variations. In rats, malformations including micrognathia and persistent ductus arteriosus could be observed in the absence of maternal toxicity at doses equal to or greater than 30 and 80 mg/kg/day, approximately 5% and 13% of the MHRD, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of deferiprone tablets have not been established in pediatric patients with chronic iron overload due to blood transfusions who are less than 8 years of age. Pediatric use information is approved for Chiesi USA, Inc.’s FERRIPROX ® (deferiprone) tablets. However, due to Chiesi USA, Inc.’s marketing exclusivity rights, this drug product is not labeled with that information .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of deferiprone did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE No cases of acute overdose have been reported. There is no specific antidote to deferiprone tablets overdose. Neurological disorders such as cerebellar symptoms, diplopia, lateral nystagmus, psychomotor slowdown, hand movements and axial hypotonia have been observed in children treated with 2.5 to 3 times the recommended dose for more than one year. The neurological disorders progressively regressed after deferiprone discontinuation.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Deferiprone is a chelating agent with an affinity for ferric ions (iron III). Deferiprone binds with ferric ions to form neutral 3:1 (deferiprone:iron) complexes that are stable at physiological pH.
12.2Pharmacodynamics No clinical studies were performed to assess the relationship between the dose of deferiprone and the amount of iron eliminated from the body. Cardiac Electrophysiology: At the maximum approved recommended dose, deferiprone does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Deferiprone Tablets, 500 mg: The mean C max and AUC of deferiprone was 20 mcg/mL and 50 mcg∙h/mL, respectively, in healthy subjects. The dose proportionality of deferiprone over the approved recommended dosage range is unknown. Absorption: Deferiprone appeared in the blood within 5 to 10 minutes after oral administration.
Peak serum concentration of deferiprone was reached approximately 1 to 2 hours after a single dose. Effect of Food: No clinically significant differences in the pharmacokinetics of deferiprone were observed following administration with food. Elimination: The elimination half-life of deferiprone is approximately 2 hours.
Metabolism: Deferiprone is metabolized primarily by UGT1A6. The major metabolite of deferiprone is the 3- O -glucuronide, which lacks iron binding capability. Excretion: Following oral administration, 75% to 90% of the administered dose was recovered in urine (primarily as metabolite) in the first 24 hours.
Specific Populations: No clinically significant differences in the pharmacokinetics of deferiprone were observed based on sex, race/ethnicity, body weight, mild to severe (eGFR 15 to 89 mL/min/1.73 m 2 ) renal impairment, or mild (Child Pugh Class A) to moderate (Child Pugh Class B) hepatic impairment. The effect of age, including geriatric or pediatric populations, end stage renal disease or severe (Child Pugh Class C) hepatic impairment on the pharmacokinetics of deferiprone is unknown. Drug Interaction Studies: In Vitro Studies: UGT1A6 Inhibitors: Phenylbutazone (UGT1A6 inhibitor) decreased glucuronidation of deferiprone by up to 78%.
Polyvalent Cations: Deferiprone has the potential to bind polyvalent cations (e.g., iron, aluminum, and zinc).
🧬 Mechanism of Action ▾
12.1Mechanism of Action Deferiprone is a chelating agent with an affinity for ferric ions (iron III). Deferiprone binds with ferric ions to form neutral 3:1 (deferiprone:iron) complexes that are stable at physiological pH.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Deferiprone Tablets, 500 mg: Deferiprone tablets are white to off-white, modified capsule shaped, biconvex, film coated tablets, debossed with 54 [score] 422 on one side and plain on the other side. They are provided in a 100 count and 300 count HDPE bottle with a child-resistant cap. NDC 0054-0576-25: Bottle of 100 Tablets NDC 0054-0576-28: Bottle of 300 Tablets Storage: Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Deferiprone tablets contain 500 mg deferiprone (3-hydroxy-1,2-dimethylpyridin-4-one), a synthetic, orally active, iron-chelating agent. The molecular formula for deferiprone is C 7 H 9 NO 2 and its molecular weight is 139.15 g/mol. Deferiprone has the following structural formula: Deferiprone is a white crystalline powder.
It is slightly soluble in deionized water and has a melting point range of 271°C - 273°C. Deferiprone Tablets, 500 mg: White to off-white, modified capsule shaped, biconvex, film coated tablet, debossed with 54 [score] 422 on one side and plain on the other. The tablets can be broken in half along the score line.
Each tablet contains 500 mg deferiprone and the following inactive ingredients: Tablet core: colloidal silicon dioxide, crospovidone, magnesium stearate, microcrystalline cellulose; Coating: hypromellose, polyethylene glycol, polysorbate 80, and titanium dioxide. deferiprone-chem-structure.jpg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide) • Instruct patients and their caregivers to store deferiprone tablets at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. • Deferiprone Tablets, 500 mg: Store in the originally supplied bottle, closed tightly to protect from moisture. Advise patients to take the first dose of deferiprone in the morning, the second dose at midday, and the third dose in the evening.
Clinical experience suggests that taking deferiprone tablets with meals may reduce nausea. Embryo-Fetal toxicity: Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.4 ) and Use in Specific Populations ( 8.1 )] .
Advise female patients of reproductive potential to use effective contraception during treatment with deferiprone tablets and for at least six months after the last dose [see Use in Specific Populations ( 8.1 , 8.3 )] . Advise males with female partners of reproductive potential to use effective contraception during treatment with deferiprone and for at least three months after the last dose [see Use in Specific Populations ( 8.3 ) and Nonclinical Toxicology ( 13.1 )] . Lactation: Advise females not to breastfeed during treatment with deferiprone tablets and for at least 2 weeks after the last dose [see Use in Specific Populations ( 8.2 )] .
Distributed by: Hikma Pharmaceuticals USA Inc. Berkeley Heights, NJ 07922 C50000816/06 Revised May 2025
💬 Medication Guide ▾
Medication Guide Deferiprone (de fer’ i prone) Tablets What is the most important information I should know about deferiprone tablets? Deferiprone tablets can cause serious side effects, including a very low white blood cell count. One type of white blood cell that is important for fighting infections is called a neutrophil.
If your neutrophil count is low (neutropenia), you may be at risk of developing a serious infection that can lead to death. Neutropenia is common with deferiprone tablets and can become severe in some people. Severe neutropenia is known as agranulocytosis.
If you develop agranulocytosis, you will be at risk of developing serious infections that can lead to death. Your healthcare provider will do a blood test before you start deferiprone tablets and regularly during treatment to check your neutrophil count. If you develop neutropenia, your healthcare provider should check your blood counts every day until your white blood cell count improves.
Your healthcare provider may temporarily stop treatment with deferiprone tablets if you develop neutropenia or infection. Stop taking deferiprone tablets and call your healthcare provider or get medical help right away if you develop any of these symptoms of infection: • fever • sore throat or mouth sores • flu-like symptoms • chills and severe shaking It is important for you to have your white blood cell count checked within 24 hours of developing symptoms of an infection to see if you have severe neutropenia (agranulocytosis).
Do not delay getting medical care if you are unable to reach your healthcare provider. See “What are the possible side effects of deferiprone tablets?” for more information about side effects. What are deferiprone tablets?
Deferiprone tablets are a prescription medicine used to treat iron overload from blood transfusions in adults with thalassemia syndromes when current iron removal (chelation) therapy does not work well enough. It is not known if deferiprone tablets are safe and effective to treat iron overload due to blood transfusions: • in people with myelodysplastic syndrome or Diamond Blackfan anemia • in children less than 8 years of age Do not take deferiprone tablets if you are allergic to deferiprone or any of the ingredients in deferiprone tablets.
See the end of this Medication Guide for a complete list of ingredients in deferiprone tablets. Before taking deferiprone tablets, tell your healthcare provider about all of your medical conditions, including if you: • have liver problems • are pregnant or plan to become pregnant. Deferiprone tablets can harm your unborn baby.
You should avoid becoming pregnant during treatment with deferiprone tablets. Tell your healthcare provider right away if you become pregnant or think you may be pregnant during treatment with deferiprone tablets. Females who are able to become pregnant: o Your healthcare provider should do a pregnancy test before you start treatment with deferiprone tablets. o You should use effective birth control during treatment with deferiprone tablets and for at least 6 months after the last dose.
Males with female partners who are able to become pregnant: o You should use effective birth control during treatment with deferiprone tablets and for at least 3 months after the last dose. • are breastfeeding or plan to breastfeed. It is not known if deferiprone passes into your breast milk. Do not breastfeed during treatment with deferiprone tablets and for at least 2 weeks after the last dose.
Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins and herbal supplements. How should I take deferiprone tablets? • Take deferiprone tablets exactly as your healthcare provider tells you. • Your healthcare provider will prescribe deferiprone tablets based on your body weight. • Your healthcare provider will check your body iron level during treatment with deferiprone tablets and may change your dose if needed. Your…