
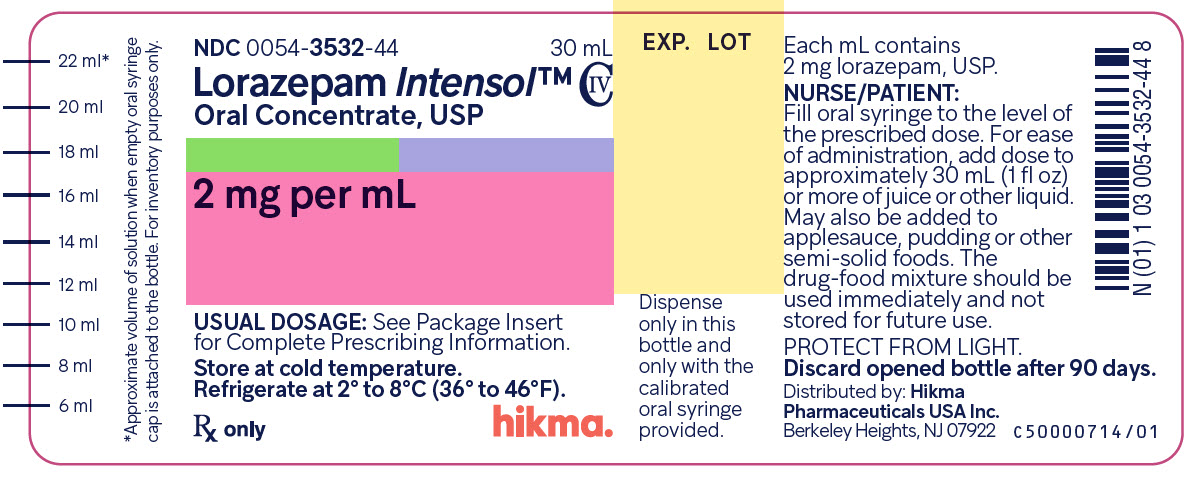
Lorazepam 2 mg/mL Solution, Concentrate — NDC 0054-3532-44 (Billing 00054-3532-44)
This is a package of Lorazepam 2 mg/mL Solution, Concentrate from Hikma Pharmaceuticals USA Inc., marketed since Jun 1991 and currently FDA-listed; retail pharmacies pay about $0.6863 per mL (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0054-3532-44 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0054 labeler · 3532 product · 44 package
- Package marketed since
- Jun 28, 1991
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0054353244 1
- Medicaid fills, this package
- 3,232 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Lorazepam (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016363
- GCN: 19601
- GPI-14 (Medi-Span): 57100060001320
- HICL (First Databank): 004846
- AHFS class code: 28:12.08.00
- RxCUI (RxNorm): 311376
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Lorazepam is used to relieve anxiety and treat insomnia. Lorazepam is in a class of medications called benzodiazepines. It works by slowing activity in the brain to allow for relaxation.
Read the full MedlinePlus article ↗- It depends on the form. Tablets and the oral liquid are for anxiety disorders or short-term anxiety relief. The injection is used in the hospital for status epilepticus and for sed...
- Take it exactly as your prescriber directs. If you use the liquid concentrate, mix it into water, juice, applesauce or pudding with the supplied dropper, then use it all right away...
- No, avoid alcohol. Opioids with lorazepam can cause extreme sleepiness, slowed breathing, coma and death. Tell me about every medicine you take so we can check for problems.
- Can I drink alcohol or take opioids with it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lorazepam — tap one for details:
Lorazepam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.686 | $20.59 / 30 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.7581 | $22.74 / 30 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.7606 | $22.82 / 30 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00054-3532-44 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 30 mL in 1 BOTTLE | 1991-06-28 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lorazepam 2 mg/mLthis 00054-3532-44 | Hikma | 1 bottle | $0.686 | AA | Availability likely | — |
| Lorazepam 2 mg/mL 00121-0770-01 | Pharmaceutical | 1 bottle | $0.686 | AA | Availability likely | — |
| Lorazepam 2 mg/mL 62135-0549-43 | Chartwell | 30 ml | $0.686 | — | Availability likely | — |
| Lorazepam 2 mg/mL 65162-0687-84 | Amneal | 30 ml | $0.686 | AA | Availability likely | — |
| Lorazepam 2 mg/mL 68000-0108-05 | American | 50 syringes | — | AA | FDA listed | — |
| Lorazepam 2 mg/mL 68000-0107-05 | American | 50 syringes | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Hikma Pharmaceuticals USA Inc. labeler code 00054
- Diphenoxylate Hydrochloride and Atropine Sulfate 2.5 mg/5mL; .025 mg/5mL Solution NDC 0054-3194-46
- Fluticasone Propionate 50 ug Spray, Metered NDC 0054-3270-99
- Furosemide 10 mg/mL Solution NDC 0054-3294-46
- Furosemide 40 mg/5mL Solution NDC 0054-3298-63
- Lidocaine Viscous Lidocaine Hydrochloride 20 mg/mL Solution NDC 0054-3500-49
- Lidocaine Hydrochloride 40 mg/mL Solution NDC 0054-3505-47
- Meperidine Hydrochloride 50 mg/5mL Solution NDC 0054-3545-63
- Methadone Hydrochloride 10 mg/mL Concentrate NDC 0054-3553-44
- Methadone Hydrochloride 5 mg/5mL Solution NDC 0054-3555-63
- Methadone Hydrochloride 10 mg/5mL Solution NDC 0054-3556-63
- Midazolam Hydrochloride 2 mg/mL Syrup NDC 0054-3566-99
- Naproxen 125 mg/5mL Suspension NDC 0054-3630-63
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS • Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation (see WARNINGS and PRECAUTIONS ). • The use of benzodiazepines, including lorazepam, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes. Before prescribing lorazepam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (see WARNINGS ). • The continued use of benzodiazepines, including lorazepam, may lead to clinically significant physical dependence.
The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose. Abrupt discontinuation or rapid dosage reduction of lorazepam after continued use may precipitate acute withdrawal reactions, which can be life-threatening. To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage ( DOSAGE AND ADMINISTRATION and WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Lorazepam is indicated for the management of anxiety disorders or for the short-term relief of the symptoms of anxiety or anxiety associated with depressive symptoms. Anxiety or tension associated with the stress of everyday life usually does not require treatment with an anxiolytic. The effectiveness of lorazepam in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies.
The physician should periodically reassess the usefulness of the drug for the individual patient.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Proper Use of an Intensol ™ An Intensol is a concentrated oral solution as compared to standard oral liquid medications. It is recommended that an Intensol be mixed with liquid or semi-solid food such as water, juices, soda or soda-like beverages, applesauce and puddings. Use only the calibrated oral syringe provided with this product.
Draw into the syringe the amount prescribed for a single dose. Then push the plunger on the syringe to add the contents into a liquid or semi-solid food. Stir the liquid or food gently for a few seconds.
The Intensol formulation blends quickly and completely. The entire amount of the mixture, of drug and liquid or drug and food, should be consumed immediately. Do not store for future use.
Lorazepam is administered orally. For optimal results, dose, frequency of administration, and duration of therapy should be individualized according to patient response. The usual range is 2 mg/day to 6 mg/day given in divided doses, the largest dose being taken before bedtime, but the daily dosage may vary from 1 mg/day to 10 mg/day.
For anxiety, most patients require an initial dose of 2 mg/day to 3 mg/day given two times a day or three times a day. For insomnia due to anxiety or transient situational stress, a single daily dose of 2 mg to 4 mg may be given, usually at bedtime. For elderly or debilitated patients, an initial dosage of 1 mg/day to 2 mg/day in divided doses is recommended, to be adjusted as needed and tolerated.
The dosage of lorazepam should be increased gradually when needed to help avoid adverse effects. When higher dosage is indicated, the evening dose should be increased before the daytime doses. Discontinuation or Dosage Reduction of Lorazepam To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage.
If a patient develops withdrawal reactions, consider pausing the taper or increasing the dosage to the previous tapered dosage level. Subsequently decrease the dosage more slowly (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE: Dependence ).
⛔ Contraindications ▾
CONTRAINDICATIONS Lorazepam is contraindicated in patients with: • hypersensitivity to benzodiazepines or to any components of the formulation. • acute narrow-angle glaucoma.
⚠️ Warnings ▾
WARNINGS Risks from Concomitant Use with Opioids Concomitant use of benzodiazepines, including lorazepam, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe lorazepam concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. In patients already receiving an opioid analgesic, prescribe a lower initial dose of lorazepam than indicated in the absence of an opioid and titrate based on clinical response. If an opioid is initiated in a patient already taking lorazepam, prescribe a lower initial dose of the opioid and titrate based upon clinical response.
Advise both patients and caregivers about the risks of respiratory depression and sedation when lorazepam is used with opioids. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see PRECAUTIONS: Drug Interactions ). Abuse, Misuse, and Addiction The use of benzodiazepines, including lorazepam, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death (see DRUG ABUSE AND DEPENDENCE: Abuse ). Before prescribing lorazepam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (e.g., using a standardized screening tool).
Use of lorazepam, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of lorazepam along with monitoring for signs and symptoms of abuse, misuse, and addiction. Prescribe the lowest effective dosage; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug. If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
Dependence and Withdrawal Reactions To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage (a patient-specific plan should be used to taper the dose) (see DOSAGE AND ADMINISTRATION: Discontinuation or Dosage Reduction of Lorazepam ). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines, including lorazepam, may lead to clinically significant physical dependence.
Abrupt discontinuation or rapid dosage reduction of lorazepam after continued use, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures) (see DRUG ABUSE AND DEPENDENCE: Dependence ) . Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months (see DRUG ABUSE AND DEPENDENCE: Dependence ). Pre-existing depression may emerge or worsen during use of benzodiazepines including lorazepam.
Lorazepam is not recommended for use in patients w… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Most adverse reactions to benzodiazepines, including CNS effects and respiratory depression, are dose dependent, with more severe effects occurring with high doses. In a sample of about 3,500 patients treated for anxiety, the most frequent adverse reaction to lorazepam was sedation (15.9%), followed by dizziness (6.9%), weakness (4.2%), and unsteadiness (3.4%). The incidence of sedation and unsteadiness increased with age.
Other adverse reactions to benzodiazepines, including lorazepam are fatigue, drowsiness, amnesia, memory impairment, confusion, disorientation, depression, unmasking of depression, disinhibition, euphoria, suicidal ideation/attempt, ataxia, asthenia, extrapyramidal symptoms, convulsions/seizures, tremor, vertigo, eye-function/visual disturbance (including diplopia and blurred vision), dysarthria/slurred speech, change in libido, impotence, decreased orgasm; headache, coma; respiratory depression, apnea, worsening of sleep apnea, worsening of obstructive pulmonary disease; gastrointestinal symptoms including nausea, change in appetite, constipation, jaundice, increase in bilirubin, increase in liver transaminases, increase in alkaline phosphatase; hypersensitivity reactions, anaphylactoid reactions; dermatological symptoms, allergic skin reactions, alopecia; syndrome of inappropriate antidiuretic hormone (SIADH), hyponatremia; thrombocytopenia, agranulocytosis, pancytopenia; hypothermia; and autonomic manifestations.
Paradoxical reactions, including anxiety, excitation, agitation, hostility, aggression, rage, sleep disturbances/insomnia, sexual arousal, and hallucinations may occur. Small decreases in blood pressure and hypotension may occur but are usually not clinically significant, probably being related to the relief of anxiety produced by lorazepam. To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-800-962-8364 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🤰 Pregnancy ▾
Pregnancy Pregnancy Exposure Registry There is a pregnancy registry that monitors pregnancy outcomes in women exposed to psychiatric medications, including lorazepam, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychiatric Medications at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/pregnancyregistry/. Risk Summary Neonates born to mothers using benzodiazepines late in pregnancy have been reported to experience symptoms of sedation and/or neonatal withdrawal (see WARNINGS: Neonatal Sedation and Withdrawal Syndrome and Clinical Considerations ).
Available data from published observational studies of pregnant women exposed to benzodiazepines do not report a clear association with benzodiazepines and major birth defects (see Data) . The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Benzodiazepines cross the placenta and may produce respiratory depression, hypotonia and sedation in neonates. Monitor neonates exposed to lorazepam during pregnancy or labor for signs of sedation, respiratory depression, hypotonia, and feeding problems.
Monitor neonates exposed to lorazepam during pregnancy for signs of withdrawal. Manage these neonates accordingly (see WARNINGS: Neonatal Sedation and Withdrawal Syndrome ). Data Human Data Published data from observational studies on the use of benzodiazepines during pregnancy do not report a clear association with benzodiazepines and major birth defects.
Although early studies reported an increased risk of congenital malformations with diazepam and chlordiazepoxide, there was no consistent pattern noted. In addition, the majority of more recent case-control and cohort studies of benzodiazepine use during pregnancy, which were adjusted for confounding exposures to alcohol, tobacco and other medications, have not confirmed these findings. Animal Data Reproductive studies in animals were performed in mice, rats, and two strains of rabbits.
Occasional anomalies (reduction of tarsals, tibia, metatarsals, malrotated limbs, gastroschisis, malformed skull, and microphthalmia) were seen in drug-treated rabbits without relationship to dosage. Although all of these anomalies were not present in the concurrent control group, they have been reported to occur randomly in historical controls. At doses of 40 mg/kg and higher, there was evidence of fetal resorption and increased fetal loss in rabbits which was not seen at lower doses.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of lorazepam generally were not adequate to determine whether subjects aged 65 and over respond differently than younger subjects; however, the incidence of sedation and unsteadiness was observed to increase with age (see ADVERSE REACTIONS ). Age does not appear to have a significant effect on lorazepam kinetics (see CLINICAL PHARMACOLOGY ). Clinical circumstances, some of which may be more common in the elderly, such as hepatic or renal impairment, should be considered.
Greater sensitivity (e.g., sedation) of some older individuals cannot be ruled out. In general, dose selection for an elderly patient should be cautious, and lower doses may be sufficient in these patients (see DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE Overdosage of benzodiazepines is characterized by central nervous system depression ranging from drowsiness to coma. In mild to moderate cases, symptoms can include drowsiness, confusion, dysarthria, lethargy, hypnotic state, diminished reflexes, ataxia, and hypotonia. Rarely, paradoxical or disinhibitory reactions (including agitation, irritability, impulsivity, violent behavior, confusion, restlessness, excitement, and talkativeness) may occur.
In severe overdosage cases, patients may develop respiratory depression and coma. Overdosage of benzodiazepines in combination with other CNS depressants (including alcohol and opioids) may be fatal (see WARNINGS: Abuse, Misuse, and Addiction ). Markedly abnormal (lowered or elevated) blood pressure, heart rate, or respiratory rate raise the concern that additional drugs and/or alcohol are involved in the overdosage.
In managing benzodiazepine overdosage, employ general supportive measures, including intravenous fluids and airway management. Flumazenil, a specific benzodiazepine receptor antagonist indicated for the complete or partial reversal of the sedative effects of benzodiazepines in the management of benzodiazepine overdosage, can lead to withdrawal and adverse reactions, including seizures, particularly in the context of mixed overdosage with drugs that increase seizure risk (e.g., tricyclic and tetracyclic antidepressants) and in patients with long-term benzodiazepine use and physical dependency.
The risk of withdrawal seizures with flumazenil use may be increased in patients with epilepsy. Flumazenil is contraindicated in patients who have received a benzodiazepine for control of a potentially life-threatening condition (e.g., status epilepticus). If the decision is made to use flumazenil, it should be used as an adjunct to, not as a substitute for, supportive management of benzodiazepine overdosage.
See the flumazenil injection Prescribing Information. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Lorazepam Intensol ™ Oral Concentrate, USP The 2 mg per mL oral concentrate is supplied as a clear colorless solution. NDC 0054-3532-44: Bottle of 30 mL with calibrated syringe (graduations 0.05 mL on the syringe). PROTECT FROM LIGHT Store at cold temperature.
Refrigerate at 2° to 8°C (36° to 46°F) Dispense only in the bottle and only with the calibrated oral syringe provided. Discard opened bottle after 90 days . Distributed by: Hikma Pharmaceuticals USA Inc.
Berkeley Heights, NJ 07922 C50000716/01 Revised January 2023
📋 Description ▾
DESCRIPTION Lorazepam, an antianxiety agent, has the chemical formula, 7-chloro-5-( o -chlorophenyl)-1,3-dihydro-3-hydroxy-2 H -1,4-benzodiazepin-2-one: C 15 H 10 Cl 2 N 2 O 2 MW: 321.16 Lorazepam, USP is a white or a practically white powder almost insoluble in water. Each mL of Lorazepam Intensol ™ for oral administration contains 2 mg of lorazepam. The inactive ingredients present are polyethylene glycol and propylene glycol. lorazepam structural formula
💬 Information for Patients ▾
Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when lorazepam is used with opioids and not to use such drugs concomitantly unless supervised by a healthcare provider. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see WARNINGS: Risks from Concomitant Use of Opioids and PRECAUTIONS: Drug Interactions ).
Abuse, Misuse, and Addiction Inform patients that the use of lorazepam even at recommended doses, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances. Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug (see WARNINGS: Abuse, Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE ).
Withdrawal Reactions Inform patients that the continued use of lorazepam may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of lorazepam may precipitate acute withdrawal reactions, which can be life-threatening. Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of lorazepam may require a slow taper (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE ).
Pregnancy Advise pregnant females that use of lorazepam late in pregnancy can result in sedation (respiratory depression, lethargy, hypotonia) and/or withdrawal symptoms (hyperreflexia, irritability, restlessness, tremors, inconsolable crying, and feeding difficulties) in newborns (see WARNINGS: Neonatal Sedation and Withdrawal Syndrome and PRECAUTIONS: Pregnancy ). Instruct patients to inform their healthcare provider if they are pregnant. Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lorazepam during pregnancy (see PRECAUTIONS: Pregnancy ).
Nursing Instruct patients to notify their healthcare provider if they are breastfeeding or intend to breastfeed. Instruct breastfeeding patients using lorazepam to monitor infants for excessive sedation, poor feeding and poor weight gain, and to seek medical attention if they notice these signs (see PRECAUTIONS: Nursing Mothers ).
💬 Medication Guide ▾
Medication Guide Lorazepam Intensol™ Oral Concentrate, USP, CIV (lor A ze pam) What is the most important information I should know about lorazepam? • Lorazepam is a benzodiazepine medicine. Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma and death. Get emergency help right away if any of the following happens: • shallow or slowed breathing • breathing stops (which may lead to the heart stopping) • excessive sleepiness (sedation) Do not drive or operate heavy machinery until you know how taking lorazepam with opioids affects you. • Risk of abuse, misuse, and addiction.
There is a risk of abuse, misuse, and addiction with benzodiazepines including lorazepam which can lead to overdose and serious side effects including coma and death. o Serious side effects including coma and death have happened in people who have abused or misused benzodiazepines, including lorazepam. These serious side effects may also include delirium, paranoia, suicidal thoughts or actions, seizures, and difficulty breathing. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these serious side effects. o You can develop an addiction even if you take lorazepam exactly as prescribed by your healthcare provider. o Take lorazepam exactly as your healthcare provider prescribed. o Do not share your lorazepam with other people. o Keep lorazepam in a safe place and away from children. • Physical dependence and withdrawal reactions.
Lorazepam can cause physical dependence and withdrawal reactions. o Do not suddenly stop taking lorazepam. Stopping lorazepam suddenly can cause serious and life-threatening side effects, including, unusual movements, responses or expressions, seizures, sudden and severe mental or nervous system changes, depression, seeing or hearing things that others do not see or hear, an extreme increase in activity or talking, losing touch with reality, and suicidal thoughts or actions. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these symptoms. o Some people who suddenly stop benzodiazepines have symptoms that can last for several weeks to more than 12 months, including anxiety, trouble remembering, learning, or concentrating, depression, problems sleeping, feeling like insects are crawling under your skin, weakness, shaking, muscle twitching, burning or prickling feeling in your hands, arms, legs or feet, and ringing in your ears. o Physical dependence is not the same as drug addiction.
Your healthcare provider can tell you more about the differences between physical dependence and drug addiction. • Do not take more lorazepam than prescribed or take lorazepam for longer than prescribed. What is lorazepam? • Lorazepam is a prescription medicine used: o to treat anxiety disorders o for the short-term relief of the symptoms of anxiety or anxiety that can happen with symptoms of depression • Lorazepam is a federal controlled substance (C-IV) because it can be abused or lead to dependence. Keep lorazepam in a safe place to prevent misuse and abuse.
Selling or giving away lorazepam may harm others, and is against the law. Tell your healthcare provider if you have abused or been dependent on alcohol, prescription medicines or street drugs. • It is not known if lorazepam is safe and effective for use in children less than 12 years of age. • It is not known if lorazepam is safe and effective for use for longer than 4 months. Do not take lorazepam if you: • are allergic to lorazepam, other benzodiazepines, or any of the ingredients in Lorazepam Intensol ™ Oral Concentrate.
See the end of this Medication Guide for a complete list of ingredients in Lorazepam Intensol ™ Oral Concentrate. Before you take lorazepam, tell your healthcare provider about all your medical conditions, including if you: •… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS In patients with depression, a possibility for suicide should be borne in mind; benzodiazepines should not be used in such patients without adequate antidepressant therapy. Lorazepam should be used with caution in patients with compromised respiratory function (e.g., COPD, sleep apnea syndrome). Elderly or debilitated patients may be more susceptible to the sedative effects of lorazepam.
Therefore, these patients should be monitored frequently and have their dosage adjusted carefully according to patient response; the initial dosage should not exceed 2 mg. Paradoxical reactions have been occasionally reported during benzodiazepine use. Such reactions may be more likely to occur in children and the elderly.
Should these occur, use of the drug should be discontinued. The usual precautions for treating patients with impaired renal or hepatic function should be observed. As with all benzodiazepines, the use of lorazepam may worsen hepatic encephalopathy; therefore, lorazepam should be used with caution in patients with severe hepatic insufficiency and/or encephalopathy.
Dosage for patients with severe hepatic insufficiency should be adjusted carefully according to patient response; lower doses may be sufficient in such patients. In patients where gastrointestinal or cardiovascular disorders coexist with anxiety, it should be noted that lorazepam has not been shown to be of significant benefit in treating the gastrointestinal or cardiovascular component. Esophageal dilation occurred in rats treated with lorazepam for more than one year at 6 mg/kg/day.
The no-effect dose was 1.25 mg/kg/day (approximately 6 times the maximum human therapeutic dose of 10 mg per day). The effect was reversible only when the treatment was withdrawn within two months of first observation of the phenomenon. The clinical significance of this is unknown.
However, use of lorazepam for prolonged periods and in geriatric patients requires caution, and there should be frequent monitoring for symptoms of upper GI disease. Safety and effectiveness of lorazepam in children of less than 12 years have not been established. Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide).
Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when lorazepam is used with opioids and not to use such drugs concomitantly unless supervised by a healthcare provider. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see WARNINGS: Risks from Concomitant Use of Opioids and PRECAUTIONS: Drug Interactions ). Abuse, Misuse, and Addiction Inform patients that the use of lorazepam even at recommended doses, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances.
Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug (see WARNINGS: Abuse, Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE ). Withdrawal Reactions Inform patients that the continued use of lorazepam may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of lorazepam may precipitate acute withdrawal reactions, which can be life-threatening.
Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of lorazepam may require a slow taper (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE ). Pregnancy Advise pregnant females that use of… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Risk Summary Lorazepam is present in breast milk. There are reports of sedation, poor feeding and poor weight gain in infants exposed to benzodiazepines through breast milk. The effects of lorazepam on milk production are unknown.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for lorazepam and any potential adverse effects on the breastfed infant from lorazepam or from the underlying maternal condition. Clinical Considerations Infants exposed to lorazepam through breast milk should be monitored for sedation, poor feeding and poor weight gain.
🔬 Clinical Studies ▾
CLINICAL PHARMACOLOGY Studies in healthy volunteers show that in single high doses lorazepam has a tranquilizing action on the central nervous system with no appreciable effect on the respiratory or cardiovascular systems. Lorazepam is readily absorbed with an absolute bioavailability of 90 percent. Peak concentrations in plasma occur approximately two hours following administration.
The peak plasma level of lorazepam from a 2 mg dose is approximately 20 ng/mL. The mean half-life of unconjugated lorazepam in human plasma is about 12 hours and for its major metabolite, lorazepam glucuronide, about 18 hours. At clinically relevant concentrations, lorazepam is approximately 85% bound to plasma proteins.
Lorazepam is rapidly conjugated at its 3-hydroxy group into lorazepam glucuronide which is then excreted in the urine. Lorazepam glucuronide has no demonstrable central nervous system (CNS) activity in animals. The plasma levels of lorazepam are proportional to the dose given.
There is no evidence of accumulation of lorazepam on administration up to 6 months. Studies comparing young and elderly subjects have shown that advancing age does not have a significant effect on the pharmacokinetics of lorazepam. However, in one study involving single intravenous doses of 1.5 mg to 3 mg of lorazepam injection, mean total body clearance of lorazepam decreased by 20% in 15 elderly subjects of 60 to 84 years of age compared to that in 15 younger subjects of 19 to 38 years of age.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Controlled Substance Lorazepam is a Schedule IV controlled substance. Abuse Lorazepam is a benzodiazepine and a CNS depressant with a potential for abuse and addiction. Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects.
Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a healthcare provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Even taking benzodiazepines as prescribed may put patients at risk for abuse and misuse of their medication. Abuse and misuse of benzodiazepines may lead to addiction. Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death.
Benzodiazepines are often sought by individuals who abuse drugs and other substances, and by individuals with addictive disorders (see WARNINGS: Abuse, Misuse, and Addiction ). The following adverse reactions have occurred with benzodiazepine abuse and/or misuse: abdominal pain, amnesia, anorexia, anxiety, aggression, ataxia, blurred vision, confusion, depression, disinhibition, disorientation, dizziness, euphoria, impaired concentration and memory, indigestion, irritability, muscle pain, slurred speech, tremors, and vertigo.
The following severe adverse reactions have occurred with benzodiazepine abuse and/or misuse: delirium, paranoia, suicidal ideation and behavior, seizures, coma, breathing difficulty, and death. Death is more often associated with polysubstance use (especially benzodiazepines with other CNS depressants such as opioids and alcohol). Dependence Physical Dependence Lorazepam may produce physical dependence from continued therapy.
Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Abrupt discontinuation or rapid dosage reduction of benzodiazepines or administration of flumazenil, a benzodiazepine antagonist, may precipitate acute withdrawal reactions, including seizures, which can be life-threatening. Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages (i.e., higher and/or more frequent doses) and those who have had longer durations of use (see WARNINGS: Dependence and Withdrawal Reactions ) .
To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage (see DOSAGE AND ADMINISTRATION: Discontinuation or Dosage Reduction of Lorazepam and WARNINGS ) . Acute Withdrawal Signs and Symptoms Acute withdrawal signs and symptoms associated with benzodiazepines have included abnormal involuntary movements, anxiety, blurred vision, depersonalization, depression, derealization, dizziness, fatigue, gastrointestinal adverse reactions (e.g., nausea, vomiting, diarrhea, weight loss, decreased appetite), headache, hyperacusis, hypertension, irritability, insomnia, memory impairment, muscle pain and stiffness, panic attacks, photophobia, restlessness, tachycardia, and tremor.
More severe acute withdrawal signs and symptoms, including life-threatening reactions, have included catatonia, convulsions, delirium tremens, depression, hallucinations, man… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 0054- 3532 -44 Lorazepam Intensol ™ Oral Concentrate, USP, CIV 2 mg per mL Rx only lorazepam intensol bottle label image