
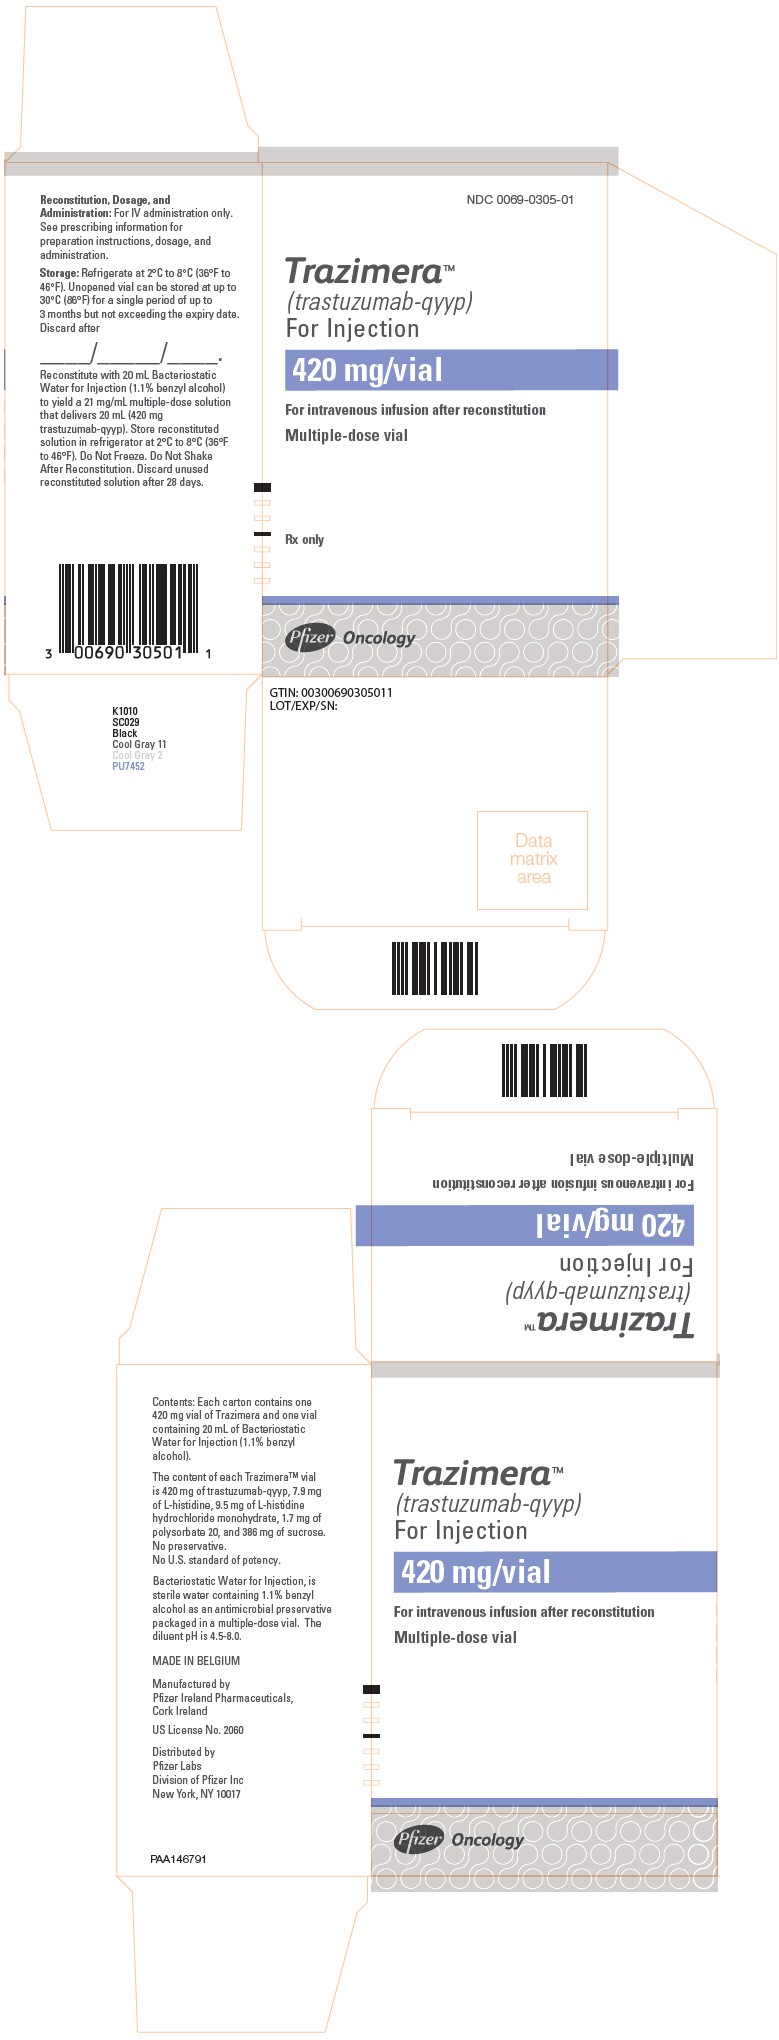
Trazimera trastuzumab-qyyp Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the HER2/neu Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Trastuzumab injection is used to treat certain types of breast and stomach cancers. Trastuzumab is in a class of medications called monoclonal antibodies. It works by stopping the growth of cancer cells.
Read the full MedlinePlus article ↗- Trastuzumab is used for more than just breast cancer. It treats HER2-positive breast cancer — both early-stage (after surgery) and metastatic (spread) breast cancer. It's also appr...
- What exactly is trastuzumab used for — is it just for breast cancer?
- No, trastuzumab is not a pill. It's given as an IV infusion — a drip into a vein — at your cancer center or infusion clinic. Your very first infusion is given slowly over 90 minute...
- How will I receive this medication? Do I take it as a pill?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,301.97 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · Q5116 | $13.033 / Q5116 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Trazimerathis 00069-0305-01 | Pfizer | 1 kit | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
6 biosimilars are FDA-licensed for this reference biologic — see the list below. (Biologics have no small-molecule generics.)
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Mar 11, 2031 |
Is there a biosimilar for TRAZIMERA 420 MG VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00069-0305-01 You're viewing this | 1 KIT in 1 KIT (0069-0305-01) * 20 mL in 1 VIAL, MULTI-DOSE (0069-0306-01) * 20 mL in 1 VIAL (0069-0307-01) | 2020-02-24 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOMYOPATHY, INFUSION REACTIONS, EMBRYO-FETAL TOXICITY, and PULMONARY TOXICITY WARNING: CARDIOMYOPATHY, INFUSION REACTIONS, EMBRYO-FETAL TOXICITY, and PULMONARY TOXICITY See full prescribing information for complete boxed warning Cardiomyopathy: Trastuzumab products can result in subclinical and clinical cardiac failure manifesting as CHF, and decreased LVEF, with greatest risk when administered concurrently with anthracyclines. Evaluate cardiac function prior to and during treatment. Discontinue TRAZIMERA for cardiomyopathy.
( 2.5 , 5.1 ) Infusion Reactions, Pulmonary Toxicity: Discontinue TRAZIMERA for anaphylaxis, angioedema, interstitial pneumonitis, or acute respiratory distress syndrome. ( 5.2 , 5.4 ) Embryo-Fetal Toxicity: Exposure to trastuzumab products during pregnancy can result in oligohydramnios, in some cases complicated by pulmonary hypoplasia and neonatal death. Advise patients of these risks and the need for effective contraception.
( 5.3 , 8.1 , 8.3 ) Cardiomyopathy Administration of trastuzumab products can result in sub-clinical and clinical cardiac failure. The incidence and severity was highest in patients receiving trastuzumab with anthracycline-containing chemotherapy regimens. Evaluate left ventricular function in all patients prior to and during treatment with TRAZIMERA.
Discontinue TRAZIMERA treatment in patients receiving adjuvant therapy and withhold TRAZIMERA in patients with metastatic disease for clinically significant decrease in left ventricular function [see Dosage and Administration (2.5) and Warnings and Precautions (5.1) ] . Infusion Reactions; Pulmonary Toxicity Administration of trastuzumab products can result in serious and fatal infusion reactions and pulmonary toxicity. Symptoms usually occur during or within 24 hours of administration of trastuzumab products.
Interrupt TRAZIMERA infusion for dyspnea or clinically significant hypotension. Monitor patients until symptoms completely resolve. Discontinue TRAZIMERA for anaphylaxis, angioedema, interstitial pneumonitis, or acute respiratory distress syndrome [see Warnings and Precautions (5.2 , 5.4 )] .
Embryo-Fetal Toxicity Exposure to trastuzumab products during pregnancy can result in oligohydramnios and oligohydramnios sequence manifesting as pulmonary hypoplasia, skeletal abnormalities, and neonatal death. Advise patients of these risks and the need for effective contraception [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1 , 8.3 )].
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TRAZIMERA is a HER2/neu receptor antagonist indicated in adults for: • The treatment of HER2-overexpressing breast cancer. ( 1.1 , 1.2 ) • The treatment of HER2-overexpressing metastatic gastric or gastroesophageal junction adenocarcinoma. ( 1.3 ) Select patients for therapy based on an FDA-approved companion diagnostic for a trastuzumab product. ( 1 , 2.2 )
1.1Adjuvant Breast Cancer TRAZIMERA is indicated in adults for adjuvant treatment of HER2-overexpressing node positive or node negative (ER/PR negative or with one high risk feature [see Clinical Studies (14.1) ] ) breast cancer • as part of a treatment regimen consisting of doxorubicin, cyclophosphamide, and either paclitaxel or docetaxel • as part of a treatment regimen with docetaxel and carboplatin • as a single agent following multi-modality anthracycline based therapy. Select patients for therapy based on an FDA-approved companion diagnostic for a trastuzumab product [see Dosage and Administration (2.2) ] .
1.2Metastatic Breast Cancer TRAZIMERA is indicated in adults: • In combination with paclitaxel for first-line treatment of HER2-overexpressing metastatic breast cancer • As a single agent for treatment of HER2-overexpressing breast cancer in patients who have received one or more chemotherapy regimens for metastatic disease. Select patients for therapy based on an FDA-approved companion diagnostic for a trastuzumab product [see Dosage and Administration (2.2) ].
1.3Metastatic Gastric Cancer TRAZIMERA is indicated in adults, in combination with cisplatin and capecitabine or 5-fluorouracil, for the treatment of patients with HER2-overexpressing metastatic gastric or gastroesophageal junction adenocarcinoma who have not received prior treatment for metastatic disease. Select patients for therapy based on an FDA-approved companion diagnostic for a trastuzumab product [see Dosage and Administration (2.2) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For intravenous (IV) infusion only. Do not administer as an intravenous push or bolus. TRAZIMERA has different dosage and administration instructions than subcutaneous trastuzumab products.
( 2.3 ) Do not substitute TRAZIMERA (trastuzumab-qyyp) for or with ado-trastuzumab emtansine or fam-trastuzumab deruxtecan. ( 2.3 ) Perform HER2 testing using FDA-approved tests by laboratories with demonstrated proficiency. ( 1 , 2.2 ) Adjuvant Treatment of HER2-Overexpressing Breast Cancer ( 2.2 ) Administer at either: • Initial dose of 4 mg/kg over 90 minutes intravenous infusion, then 2 mg/kg over 30 minutes intravenous infusion weekly for 12 weeks (with paclitaxel or docetaxel) or 18 weeks (with docetaxel and carboplatin).
One week after the last weekly dose of TRAZIMERA, administer 6 mg/kg as an intravenous infusion over 30 to 90 minutes every three weeks to complete a total of 52 weeks of therapy, or • Initial dose of 8 mg/kg over 90 minutes intravenous infusion, then 6 mg/kg over 30 to 90 minutes intravenous infusion every three weeks for 52 weeks. Metastatic HER2-Overexpressing Breast Cancer ( 2.3 ) • Initial dose of 4 mg/kg as a 90 minutes intravenous infusion followed by subsequent weekly doses of 2 mg/kg as 30 minutes intravenous infusions.
Metastatic HER2-Overexpressing Gastric Cancer ( 2.3 ) • Initial dose of 8 mg/kg over 90 minutes intravenous infusion, followed by 6 mg/kg over 30 to 90 minutes intravenous infusion every 3 weeks.
2.1Evaluation and Testing Before Initiating TRAZIMERA Assess left ventricular ejection fraction (LVEF) prior to initiation of TRAZIMERA and at regular intervals during treatment [see Boxed Warning , Dosage and Administration (2.5) and Warnings and Precautions (5.1) ] . Verify the pregnancy status of females of reproductive potential prior to the initiation of TRAZIMERA [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1 , 8.3) ].
2.2Patient Selection Select patients based on HER2 protein overexpression or HER2 gene amplification in tumor specimens [see Indications and Usage (1) and Clinical Studies (14) ] . Assessment of HER2 protein overexpression and HER2 gene amplification should be performed using FDA-approved tests specific for breast or gastric cancers by laboratories with demonstrated proficiency. Information on the FDA-approved tests for the detection of HER2 protein overexpression and HER2 gene amplification is available at: http://www.fda.gov/CompanionDiagnostics .
Assessment of HER2 protein overexpression and HER2 gene amplification in metastatic gastric cancer should be performed using FDA-approved tests specifically for gastric cancers due to differences in gastric vs. breast histopathology, including incomplete membrane staining and more frequent heterogeneous expression of HER2 seen in gastric cancers. Improper assay performance, including use of suboptimally fixed tissue, failure to utilize specified reagents, deviation from specific assay instructions, and failure to include appropriate controls for assay validation, can lead to unreliable results.
2.3Recommended Dosage • TRAZIMERA is for intravenous infusion only. Do not administer as an intravenous push or bolus. • TRAZIMERA has different dosage and administration instructions than subcutaneous trastuzumab products. • Do not mix TRAZIMERA with other drugs. • Do not substitute TRAZIMERA (trastuzumab-qyyp) for or with ado-trastuzumab emtansine or fam-trastuzumab deruxtecan. Adjuvant Treatment of Breast Cancer Administer according to one of the following doses and schedules for a total of 52 weeks of TRAZIMERA therapy: During and following paclitaxel, docetaxel, or docetaxel and carboplatin: • Initial dose of 4 mg/kg as an intravenous infusion over 90 minutes then at 2 mg/kg as an intravenous infusion over 30 minutes weekly during chemotherapy for the first 12 weeks (paclitaxel or docetaxel) or 18 weeks (docetaxel and carboplatin). • One week following the last weekly dose of TRAZIME…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • For injection: 150 mg of TRAZIMERA as a white lyophilized powder in a single-dose vial. • For injection: 420 mg of TRAZIMERA as a white lyophilized powder in a multiple-dose vial. • For Injection: 150 mg lyophilized powder in a single-dose vial for reconstitution. ( 3 ) • For Injection: 420 mg lyophilized powder in a multiple-dose vial for reconstitution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. • None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Exacerbation of Chemotherapy-Induced Neutropenia. ( 5.5 , 6.1 )
5.1Cardiomyopathy Trastuzumab products can cause left ventricular cardiac dysfunction, arrhythmias, hypertension, disabling cardiac failure, cardiomyopathy, and cardiac death [see Boxed Warning ] . Trastuzumab products can also cause asymptomatic decline in left ventricular ejection fraction (LVEF). There is a 4 to 6 fold increase in the incidence of symptomatic myocardial dysfunction among patients receiving trastuzumab products as a single agent or in combination therapy compared with those not receiving trastuzumab products.
The highest absolute incidence occurs when a trastuzumab product is administered with an anthracycline. Withhold TRAZIMERA for ≥ 16% absolute decrease in LVEF from pre-treatment values or an LVEF value below institutional limits of normal and ≥ 10% absolute decrease in LVEF from pretreatment values [see Dosage and Administration (2.5) ] . The safety of continuation or resumption of trastuzumab products in patients with trastuzumab product-induced left ventricular cardiac dysfunction has not been studied.
Patients who receive anthracycline after stopping trastuzumab products may also be at increased risk of cardiac dysfunction [see Drug Interactions (7) and Clinical Pharmacology (12.3) ] . Cardiac Monitoring Conduct thorough cardiac assessment, including history, physical examination, and determination of LVEF by echocardiogram or MUGA scan. The following schedule is recommended: • Baseline LVEF measurement immediately prior to initiation of TRAZIMERA • LVEF measurements every 3 months during and upon completion of TRAZIMERA • Repeat LVEF measurement at 4 week intervals if TRAZIMERA is withheld for significant left ventricular cardiac dysfunction [see Dosage and Administration (2.5) ] • LVEF measurements every 6 months for at least 2 years following completion of TRAZIMERA as a component of adjuvant therapy.
In NSABP B31, 15% (158/1031) of patients discontinued trastuzumab due to clinical evidence of myocardial dysfunction or significant decline in LVEF after a median follow-up duration of 8.7 years in the AC-TH (anthracycline, cyclophosphamide, paclitaxel, and trastuzumab) arm. In HERA (one-year trastuzumab treatment), the number of patients who discontinued trastuzumab due to cardiac toxicity at 12.6 months median duration of follow-up was 2.6% (44/1678). In BCIRG006, a total of 2.9% (31/1056) of patients in the TCH (docetaxel, carboplatin, trastuzumab) arm (1.5% during the chemotherapy phase and 1.4% during the monotherapy phase) and 5.7% (61/1068) of patients in the AC-TH arm (1.5% during the chemotherapy phase and 4.2% during the monotherapy phase) discontinued trastuzumab due to cardiac toxicity.
Among 64 patients receiving adjuvant chemotherapy (NSABP B31 and NCCTG N9831) who developed congestive heart failure (CHF), one patient died of cardiomyopathy, one patient died suddenly without documented etiology, and 33 patients were receiving cardiac medication at last follow-up. Approximately 24% of the surviving patients had recovery to a normal LVEF (defined as ≥ 50%) and no symptoms on continuing medical management at the time of last follow-up. Incidence of congestive heart failure is presented in Table 1.
The safety of continuation or resumption of trastuzumab products in patients with trastuzumab product-induced left ventricular cardiac dysfunction has not been studied. Table 1: Incidence of Congestive Heart Failure in Adjuvant Breast Cancer Studies Incidence of Congestive Heart Failure % (n) Study Regimen Trastuzumab Control NSABP B31 & NCCTG N9831 Median follow-up duration for NSABP B31 & NCCTG N9831 combined was 8.3 years in the AC→paclitaxel+trastuzumab arm. AC Anthracycline (doxorubicin) and cyclophosphamide. → Paclitaxel+Trastuzumab 3.2% (64/2000) Includes 1 patient with fatal cardiomyopathy and 1 patient with sudden death without documented etiology.
1.3% (21/1655) HERA Includes NYHA II-IV and car…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: • Cardiomyopathy [see Warnings and Precautions (5.1) ] • Infusion Reactions [see Warnings and Precautions (5.2) ] • Embryo-Fetal Toxicity [see Warnings and Precautions (5.3) ] • Pulmonary Toxicity [see Warnings and Precautions (5.4) ] • Exacerbation of Chemotherapy-Induced Neutropenia [see Warnings and Precautions (5.5) ] Adjuvant Breast Cancer • Most common adverse reactions (≥ 5%) are headache, diarrhea, nausea, and chills.
( 6.1 ) Metastatic Breast Cancer • Most common adverse reactions (≥ 10%) are fever, chills, headache, infection, congestive heart failure, insomnia, cough, and rash. ( 6.1 ) Metastatic Gastric Cancer • Most common adverse reactions (≥ 10%) are neutropenia, diarrhea, fatigue, anemia, stomatitis, weight loss, upper respiratory tract infections, fever, thrombocytopenia, mucosal inflammation, nasopharyngitis, and dysgeusia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 and www.Pfizer.com or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most common adverse reactions in patients receiving trastuzumab products in the adjuvant and metastatic breast cancer setting are fever, nausea, vomiting, infusion reactions, diarrhea, infections, increased cough, headache, fatigue, dyspnea, rash, neutropenia, anemia, and myalgia.
Adverse reactions requiring interruption or discontinuation of trastuzumab product treatment include CHF, significant decline in left ventricular cardiac function, severe infusion reactions, and pulmonary toxicity [see Dosage and Administration (2.5) ] . In the metastatic gastric cancer setting, the most common adverse reactions (≥ 10%) that were increased (≥ 5% difference) in the trastuzumab arm as compared to the chemotherapy alone arm were neutropenia, diarrhea, fatigue, anemia, stomatitis, weight loss, upper respiratory tract infections, fever, thrombocytopenia, mucosal inflammation, nasopharyngitis, and dysgeusia.
The most common adverse reactions which resulted in discontinuation of treatment on the trastuzumab-containing arm in the absence of disease progression were infection, diarrhea, and febrile neutropenia. Adjuvant Breast Cancer The information below reflects exposure to one-year trastuzumab therapy across three randomized, open-label studies, NSABP B31, NCCTG N9831, and HERA, with (n = 3678) or without (n = 3363) trastuzumab in the adjuvant treatment of breast cancer. HERA Table 3 reflects exposure to trastuzumab in 1678 patients in HERA; the median treatment duration was 51 weeks and median number of infusions was 18 [see Clinical Studies (14.1) ].
Table 3: Adverse Reactions (≥ 1%) in HERA (All Grades) The incidence of Grade 3 or higher adverse reactions was < 1% in both arms for each listed term. Adverse Reactions Trastuzumab (n = 1678) % Observation (n = 1708) % Nervous System Headache 10 3 Paresthesia 2
0.6 Musculoskeletal Arthralgia 8 6 Back pain 5 3 Myalgia 4 1 Bone pain 3 2 Muscle spasm 3
0.2 Infections Nasopharyngitis 8 3 Urinary tract infection 3
0.8Gastrointestinal Diarrhea 7 1 Nausea 6 1 Vomiting 3.5
0.6 Constipation 2 1 Dyspepsia 2
0.5 Upper abdominal pain 2 1 General Pyrexia 6
0.4Peripheral edema 5 2 Chills 5 0 Asthenia 4.5 2 Influenza-like illness 2
0.2 Respiratory Thoracic Mediastinal Cough 5 2 Influenza 4
0.5 Dyspnea 3 2 URI 3 1 Rhinitis 2
0.4 Pharyngolaryngeal pain 2
0.5 Sinusitis 2
0.3 Epistaxis 2
0.06Cardiac Hypertension 4 2 Dizziness 4 2 Ejection fraction decreased 3.5
0.6 Palpitations 3
0.7Cardiac arrhythmias Higher level grouping term. 3 1 Cardiac failure (congestive) 2
0.3 Skin & Subcutaneous Tissue Rash 4
0.6 Nai…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Anthracyclines Patients who receive anthracycline after stopping trastuzumab products may be at increased risk of cardiac dysfunction because of trastuzumab products estimated long washout period [see Clinical Pharmacology (12.3) ] . If possible, avoid anthracycline-based therapy for up to 7 months after stopping trastuzumab products. If anthracyclines are used, closely monitor the patient's cardiac function.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and Males of Reproductive Potential: Verify the pregnancy status of females prior to initiation of TRAZIMERA. ( 8.3 )
8.1Pregnancy Risk Summary Trastuzumab products can cause fetal harm when administered to a pregnant woman. In post-marketing reports and published literature, use of trastuzumab products during pregnancy resulted in cases of oligohydramnios and of oligohydramnios sequence, manifesting as pulmonary hypoplasia, skeletal abnormalities, and neonatal death (see Data ) . Apprise the patient of the potential risks to a fetus.
There are clinical considerations if a trastuzumab product is used in a pregnant woman or if a patient becomes pregnant within 7 months following the last dose of a trastuzumab product (see Clinical Considerations ). The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Monitor women who received TRAZIMERA during pregnancy or within 7 months prior to conception for oligohydramnios. If oligohydramnios occurs, perform fetal/neonatal testing that is appropriate for gestational age and consistent with community standards of care. Data Human Data In post-marketing reports and published literature, use of trastuzumab products during pregnancy resulted in cases of oligohydramnios and of oligohydramnios sequence.
Fetal manifestations included pulmonary hypoplasia, skeletal abnormalities and neonatal death. These case reports described oligohydramnios in pregnant women who received trastuzumab either alone or in combination with chemotherapy. In most reported cases, amniotic fluid index increased after trastuzumab was stopped.
In reported cases where trastuzumab therapy was resumed after amniotic index improved, oligohydramnios recurred. Animal Data In studies where trastuzumab was administered to pregnant cynomolgus monkeys during the period of organogenesis at doses up to 25 mg/kg given twice weekly (up to 25 times the recommended weekly human dose of 2 mg/kg), trastuzumab crossed the placental barrier during the early (Gestation Days 20 to 50) and late (Gestation Days 120 to 150) phases of gestation. The resulting concentrations of trastuzumab in fetal serum and amniotic fluid were approximately 33% and 25%, respectively, of those present in the maternal serum but were not associated with adverse developmental effects.
8.2Lactation Risk Summary There is no information regarding the presence of trastuzumab products in human milk, the effects on the breastfed infant, or the effects on milk production. Published data suggest human IgG is present in human milk but does not enter the neonatal and infant circulation in substantial amounts. Trastuzumab was present in the milk of lactating cynomolgus monkeys but not associated with neonatal toxicity (see Data ).
Consider the developmental and health benefits of breastfeeding along with the mother's clinical need for TRAZIMERA treatment and any potential adverse effects on the breastfed child from TRAZIMERA or from the underlying maternal condition. This consideration should also take into account the trastuzumab product wash out period of 7 months [see Clinical Pharmacology (12.3) ]. Data In lactating cynomolgus monkeys, trastuzumab was present in breast milk at about 0.3% of maternal serum concentrations after pre-(beginning Gestation Day 120) and post-partum (through Post-partum Day 28) doses of 25 mg/kg administered twice weekly (25 times the recommended weekly human dose of 2 mg/kg of trastuzumab products).
Infant monkeys with detectable serum levels of trastuzumab did not exhibit any adverse effects on growth or development from birth to 1 month of age.
8.3 Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Trastuzumab products can cause fetal harm when administered to a pregnant woman. In post-marketing reports and published literature, use of trastuzumab products during pregnancy resulted in cases of oligohydramnios and of oligohydramnios sequence, manifesting as pulmonary hypoplasia, skeletal abnormalities, and neonatal death (see Data ) . Apprise the patient of the potential risks to a fetus.
There are clinical considerations if a trastuzumab product is used in a pregnant woman or if a patient becomes pregnant within 7 months following the last dose of a trastuzumab product (see Clinical Considerations ). The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Monitor women who received TRAZIMERA during pregnancy or within 7 months prior to conception for oligohydramnios. If oligohydramnios occurs, perform fetal/neonatal testing that is appropriate for gestational age and consistent with community standards of care. Data Human Data In post-marketing reports and published literature, use of trastuzumab products during pregnancy resulted in cases of oligohydramnios and of oligohydramnios sequence.
Fetal manifestations included pulmonary hypoplasia, skeletal abnormalities and neonatal death. These case reports described oligohydramnios in pregnant women who received trastuzumab either alone or in combination with chemotherapy. In most reported cases, amniotic fluid index increased after trastuzumab was stopped.
In reported cases where trastuzumab therapy was resumed after amniotic index improved, oligohydramnios recurred. Animal Data In studies where trastuzumab was administered to pregnant cynomolgus monkeys during the period of organogenesis at doses up to 25 mg/kg given twice weekly (up to 25 times the recommended weekly human dose of 2 mg/kg), trastuzumab crossed the placental barrier during the early (Gestation Days 20 to 50) and late (Gestation Days 120 to 150) phases of gestation. The resulting concentrations of trastuzumab in fetal serum and amniotic fluid were approximately 33% and 25%, respectively, of those present in the maternal serum but were not associated with adverse developmental effects.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of TRAZIMERA in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Trastuzumab has been administered to 386 patients who were 65 years of age or over (253 in the adjuvant treatment and 133 in metastatic breast cancer treatment settings). The risk of cardiac dysfunction was increased in geriatric patients as compared to younger patients in both those receiving treatment for metastatic disease in H0648g and H0649g, or adjuvant therapy in NSABP B31 and NCCTG N9831. Limitations in data collection and differences in study design of the 4 studies of trastuzumab in adjuvant treatment of breast cancer preclude a determination of whether the toxicity profile of trastuzumab in older patients is different from younger patients.
The reported clinical experience is not adequate to determine whether the efficacy improvements (ORR, TTP, OS, DFS) of trastuzumab treatment in older patients is different from that observed in patients < 65 years of age for metastatic disease and adjuvant treatment. In ToGA (metastatic gastric cancer), of the 294 patients treated with trastuzumab, 108 (37%) were 65 years of age or older, while 13 (4.4%) were 75 and over. No overall differences in safety or effectiveness were observed.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The HER2 (or c-erbB2) proto-oncogene encodes a transmembrane receptor protein of 185 kDa, which is structurally related to the epidermal growth factor receptor. Trastuzumab products have been shown, in both in vitro assays and in animals, to inhibit the proliferation of human tumor cells that overexpress HER2. Trastuzumab products are mediators of antibody-dependent cellular cytotoxicity (ADCC).
In vitro , trastuzumab product-mediated ADCC has been shown to be preferentially exerted on HER2 overexpressing cancer cells compared with cancer cells that do not overexpress HER2.
12.2Pharmacodynamics Trastuzumab product exposure-response relationships and the time course of pharmacodynamic responses are not fully characterized. Cardiac Electrophysiology The effects of trastuzumab on electrocardiographic (ECG) endpoints, including QTc interval duration, were evaluated in patients with HER2 positive solid tumors. Trastuzumab had no clinically relevant effect on the QTc interval duration and there was no apparent relationship between serum trastuzumab concentrations and change in QTcF interval duration in patients with HER2 positive solid tumors.
12.3Pharmacokinetics The pharmacokinetics of trastuzumab were evaluated in a pooled population pharmacokinetic (PK) model analysis of 1,582 subjects with primarily breast cancer and metastatic gastric cancer (MGC) receiving intravenous trastuzumab. Total trastuzumab clearance increases with decreasing concentrations due to parallel linear and non-linear elimination pathways. Although the average trastuzumab exposure was higher following the first cycle in breast cancer patients receiving the once every three weeks schedule compared to the weekly schedule of trastuzumab, the average steady-state exposure was essentially the same at both dosages.
The average trastuzumab exposure following the first cycle and at steady state as well as the time to steady state was higher in breast cancer patients compared to MGC patients at the same dosage; however, the reason for this exposure difference is unknown. Additional predicted trastuzumab exposure and PK parameters following the first trastuzumab cycle and at steady state exposure are described in Tables 7 and 8, respectively. Population PK based simulations indicate that following discontinuation of trastuzumab, concentrations in at least 95% of breast cancer patients and MGC patients will decrease to approximately 3% of the population predicted steady-state trough serum concentration (approximately 97% washout) by 7 months [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1 , 8.3) ] .
Table 7: Population Predicted Cycle 1 PK Exposures (Median with 5 th to 95 th Percentiles) in Breast Cancer and MGC Patients Schedule Primary tumor type N C min (µg/mL) C max (µg/mL) AUC 0-21 days (µg.day/mL) 8 mg/kg + 6 mg/kg q3w Breast cancer 1195 29.4 (5.8 to 59.5) 178 (117 to 291) 1373 (736 to 2245) MGC 274 23.1 (6.1 to 50.3) 132 (84.2 to 225) 1109 (588 to 1938) 4 mg/kg + 2 mg/kg qw Breast cancer 1195 37.7 (12.3 to 70.9) 88.3 (58 to 144) 1066 (586 to 1754) Table 8: Population Predicted Steady State PK Exposures (Median with 5 th to 95 th Percentiles) in Breast Cancer and MGC Patients Schedule Primary tumor type N C min,ss Steady-state trough serum concentration of trastuzumab.
(µg/mL) C max,ss Maximum steady-state serum concentration of trastuzumab. (µg/mL) AUC ss, 0-21 days (µg.day/mL) Time to steady-state (week) Total CL range at steady-state (L/day) 8 mg/kg + 6 mg/kg q3w Breast cancer 1195 47.4 (5 to 115) 179 (107 to 309) 1794 (673 to 3618) 12 0.173 to 0.283 MGC 274 32.9 (6.1 to 88.9) 131 (72.5 to 251) 1338 (557 to 2875) 9 0.189 to 0.337 4 mg/kg + 2 mg/kg qw Breast cancer 1195 66.1 (14.9 to 142) 109 (51.0 to 209) 1765 (647 to 3578) 12 0.201 to 0.244 Specific Populations Based on a population pharmacokinetic analysis, no clinically significant differences were observed in the pharmacokinetics…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The HER2 (or c-erbB2) proto-oncogene encodes a transmembrane receptor protein of 185 kDa, which is structurally related to the epidermal growth factor receptor. Trastuzumab products have been shown, in both in vitro assays and in animals, to inhibit the proliferation of human tumor cells that overexpress HER2. Trastuzumab products are mediators of antibody-dependent cellular cytotoxicity (ADCC).
In vitro , trastuzumab product-mediated ADCC has been shown to be preferentially exerted on HER2 overexpressing cancer cells compared with cancer cells that do not overexpress HER2.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING 420 mg Multiple-dose vial TRAZIMERA (trastuzumab-qyyp) for injection 420 mg/vial is supplied in a multiple-dose vial as a sterile, white lyophilized powder. Each carton contains one multiple-dose vial of TRAZIMERA and one vial (20 mL) of Bacteriostatic Water for Injection (BWFI) containing 1.1% benzyl alcohol as a preservative. NDC 0069-0305-01.
150 mg Single-dose vial TRAZIMERA (trastuzumab-qyyp) for injection 150 mg/vial is supplied in a single-dose vial as a sterile, white lyophilized powder. Each carton contains one single-dose vial of TRAZIMERA. NDC 0069-0308-01.
Store TRAZIMERA vials in the refrigerator at 2°C to 8°C (36°F to 46°F) in the original carton to protect from light. If needed, unopened TRAZIMERA vials may be removed from the refrigerator and stored at room temperature up to 30°C (86°F) for a single period of up to 3 months in the original carton to protect from light. Once removed from the refrigerator, do not return to the refrigerator and discard after 3 months or by the expiration date stamped on the vial, whichever occurs first.
Write the revised expiration date in the space provided on the carton labeling.
📋 Description ▾
11 DESCRIPTION Trastuzumab-qyyp is a humanized IgG1 kappa monoclonal antibody that selectively binds with high affinity to the extracellular domain of the human epidermal growth factor receptor 2 protein, HER2. Trastuzumab-qyyp is produced by recombinant DNA technology in a mammalian cell (Chinese Hamster Ovary) culture. TRAZIMERA (trastuzumab-qyyp) for injection is a sterile, white, preservative-free lyophilized powder with a cake-like appearance, for intravenous administration.
Each multiple-dose vial of TRAZIMERA delivers 420 mg trastuzumab-qyyp, 7.9 mg L-histidine, 9.5 mg L-histidine HCl monohydrate, 1.7 mg polysorbate 20, and 386 mg sucrose. Reconstitution with 20 mL of the appropriate diluent (BWFI or SWFI) yields a solution containing 21 mg/mL trastuzumab-qyyp that delivers 20 mL (420 mg trastuzumab-qyyp), at a pH of approximately 6. If TRAZIMERA is reconstituted with SWFI without preservative, the reconstituted solution is considered single-dose.
Each single-dose vial of TRAZIMERA delivers 150 mg trastuzumab-qyyp, 2.8 mg L-histidine, 3.4 mg L-histidine HCl monohydrate, 0.6 mg polysorbate 20, and 138 mg sucrose. Reconstitution with 7.4 mL of SWFI yields a solution containing 21 mg/mL trastuzumab-qyyp that delivers 7.15 mL (150 mg trastuzumab-qyyp), at a pH of approximately 6.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Cardiomyopathy • Advise patients to contact a health care professional immediately for any of the following: new onset or worsening shortness of breath, cough, swelling of the ankles/legs, swelling of the face, palpitations, weight gain of more than 5 pounds in 24 hours, dizziness or loss of consciousness [see Boxed Warning ] . Embryo-Fetal Toxicity • Advise pregnant women and females of reproductive potential that TRAZIMERA exposure during pregnancy or within 7 months prior to conception can result in fetal harm.
Advise female patients to contact their healthcare provider with a known or suspected pregnancy [see Use in Specific Populations (8.1) ] . • Advise females of reproductive potential to use effective contraception during treatment and for 7 months following the last dose of TRAZIMERA [see Use in Specific Populations (8.3) ] .