
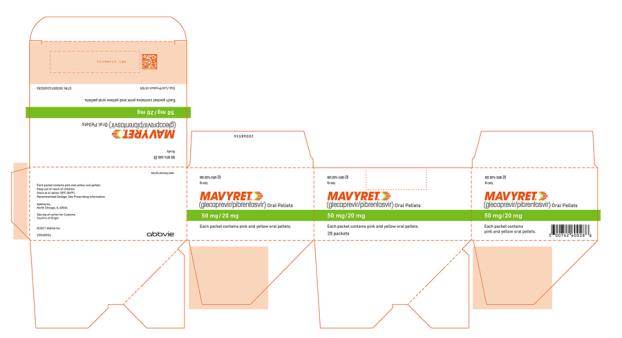
Mavyret Glecaprevir and Pibrentasvir 20 mg; 50 mg Pellet — NDC 0074-2600-28 (Billing 00074-2600-28)
This is a package of Mavyret Glecaprevir and Pibrentasvir 20 mg; 50 mg Pellet from AbbVie Inc., marketed since Jun 2021 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0074-2600-28 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0074 labeler · 2600 product · 28 package
- Package marketed since
- Jun 22, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0074260028 6
- Medicaid fills, this package
- 28 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 082438
- GCN: 49863
- HICL (First Databank): 044453
- AHFS class code: 08:18.40.20
- RxCUI (RxNorm): 1940703
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 8, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Hepatitis C Virus NS3/4A Protease Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 8, 2026
Clinical
The combination of glecaprevir and pibrentasvir is used to treat certain types of chronic (long-term) hepatitis C infection (swelling of the liver caused by a virus) in adults and children 3 years of age and older. It is also used to treat certain types of chronic hepatitis C infection in adults and children 3 years of age and older who have already received another medication to treat their hepatitis C infection. Glecaprevir is in a class of medications called HCV NS3/4A protease inhibitors. It works by decreasing the amount of hepatitis C virus (HCV) in the body. Pibrentasvir is in a class o...
Read the full MedlinePlus article ↗- It treats hepatitis C virus infection, genotypes 1 to 6, in adults and children 3 and older. It can be used if you have no cirrhosis or compensated cirrhosis. Your doctor picks the...
- Take it once a day with food. Tablets are swallowed together at the same time. For younger children, the pellets are sprinkled on soft, sticky food and swallowed without chewing. F...
- Most people have mild ones like headache, tiredness and nausea. Diarrhea and itching can happen too. Call your doctor if you notice yellow skin or eyes, belly swelling, confusion,...
- Treating hepatitis C can reactivate hepatitis B if you have it now or had it before. That can cause serious liver injury. Testing lets your doctor monitor or treat hepatitis B.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $88.51 | $2,478.30 / 28 pellets |
| Medicare drug plans payPart D · Q2 2026 | $96.00 | $2,688.11 / 28 pellets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00074-2600-28 You're viewing this Main listing | 1 PACKET in 1 CARTON / 28 PELLET in 1 PACKET | 2021-06-22 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mavyret 20 mg/1; 50 mgthis 00074-2600-28 | AbbVie | 1 packet | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 9, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
Our estimate: December 2036 about 10 years away
How sure: Probable. More likely than not, but it can still move.
Why then: A patent that protects the brand runs out. After that, approved generics can be sold.
See the full forecast for generic Mavyret →🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10286029 ↗ | Method of use | U-4206 | Mar 14, 2034 |
| US 10039754 ↗ | Method of use | U-4206 | Jun 10, 2030 |
| US 10028937 ↗ | Method of use | U-4206 | Jun 10, 2030 |
| US 9586978 ↗ | Method of use | U-4206 | Nov 6, 2030 |
| US 8648037 ↗ | Drug substance | U-4206 | Jan 19, 2032 |
| US 9586978 ↗ | Method of use | U-3238 | Nov 6, 2030 |
| US 8648037 ↗ | Drug substance | U-3238 | Jan 19, 2032 |
| US 10028937 ↗ | Method of use | U-3238 | Jun 10, 2030 |
| US 10039754 ↗ | Method of use | U-3238 | Jun 10, 2030 |
| US 10286029 ↗ | Method of use | U-3238 | Mar 14, 2034 |
| US 8937150 ↗ | Drug substance | — | May 18, 2032 |
| US 9321807 ↗ | Drug substance | — | Jun 5, 2035 |
| US RE48923 ↗ | Drug substance | — | May 8, 2035 |
| US RE48923*PED ↗ | Drug product | — | Nov 8, 2035 |
| US 10028937*PED ↗ | Drug product | — | Dec 10, 2030 |
| US 10039754*PED ↗ | Drug product | — | Dec 10, 2030 |
| US 9586978*PED ↗ | Drug product | — | May 6, 2031 |
| US 8648037*PED ↗ | Drug product | — | Jul 19, 2032 |
| US 10286029*PED ↗ | Drug product | — | Sep 14, 2034 |
| US 8937150*PED ↗ | Drug product | — | Nov 18, 2032 |
| US 9321807*PED ↗ | Drug product | — | Dec 5, 2035 |
| Code | What it grants | Expires |
|---|---|---|
| I-967 | New indication (3-year) | Jun 10, 2028 |
| ODE-372 | Orphan Drug Exclusivity (7-year) | Jun 10, 2028 |
| PED | Pediatric Exclusivity (+6 months) | Dec 10, 2028 |
Is there a generic version of MAVYRET 50-20 MG PELLET PACKET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 9, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Glecaprevir and Pibrentasvir inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII RT9P9S09QI
Propylene glycol monocaprylate is a synthetic compound made by combining propylene glycol with a fatty acid. It acts as an emulsifier and surfactant to help mix oil and water-based ingredients together in medicines and improve how the body absorbs the active drug.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII O03S90U1F2
A synthetic compound combining vitamin E with polyethylene glycol and succinic acid. It acts as a solubilizer and antioxidant in medicines, helping dissolve poorly water-soluble drugs and prevent degradation of active ingredients.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from AbbVie Inc. labeler code 00074
- Rinvoq Upadacitinib 1 mg/mL Solution NDC 0074-2320-01
- adalimumab 40 mg/.8mL Injection, Solution NDC 0074-2330-00
- Norvir Ritonavir 100 mg Tablet, Film Coated NDC 0074-2340-30
- Lupron Depot-PED leuprolide acetate Kit NDC 0074-2440-03
- Humira Adalimumab Kit NDC 0074-2540-01
- Ibrutinib 420 mg Tablet NDC 0074-2585-99
- Mavyret Glecaprevir and Pibrentasvir 100 mg; 40 mg Tablet, Film Coated NDC 0074-2625-01
- Ibrutinib 140 mg Capsule NDC 0074-2628-99
- Kaletra Lopinavir and Ritonavir 100 mg; 25 mg Tablet, Film Coated NDC 0074-3008-60
- Duopa Carbidopa and Levodopa 20 mg/mL; 4.63 mg/mL Suspension NDC 0074-3012-07
- Gengraf Cyclosporine 25 mg Capsule NDC 0074-3108-32
- Gengraf Cyclosporine 100 mg Capsule NDC 0074-3109-32
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF HEPATITIS B VIRUS REACTIVATION IN PATIENTS COINFECTED WITH HCV AND HBV Test all patients for evidence of current or prior hepatitis B virus (HBV) infection before initiating treatment with MAVYRET. HBV reactivation has been reported in HCV/HBV coinfected patients who were undergoing or had completed treatment with HCV direct-acting antivirals and were not receiving HBV antiviral therapy. Some cases have resulted in fulminant hepatitis, hepatic failure, and death.
Monitor HCV/HBV coinfected patients for hepatitis flare or HBV reactivation during HCV treatment and post-treatment follow-up. Initiate appropriate patient management for HBV infection as clinically indicated [see Warnings and Precautions ( 5.1 )] . WARNING: RISK OF HEPATITIS B VIRUS REACTIVATION IN PATIENTS COINFECTED WITH HCV AND HBV See full prescribing information for complete boxed warning.
Hepatitis B virus (HBV) reactivation has been reported, in some cases resulting in fulminant hepatitis, hepatic failure, and death. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE MAVYRET is indicated for the treatment of adult and pediatric patients 3 years and older with acute or chronic hepatitis C virus (HCV) genotype 1, 2, 3, 4, 5 or 6 infection without cirrhosis or with compensated cirrhosis (Child-Pugh A). MAVYRET is indicated for the treatment of adult and pediatric patients 3 years and older with HCV genotype 1 infection, who previously have been treated with a regimen containing an HCV NS5A inhibitor or an NS3/4A protease inhibitor (PI), but not both [see Dosage and Administration ( 2.2 ) and Clinical Studies ( 14 )].
MAVYRET is a fixed-dose combination of glecaprevir, a hepatitis C virus (HCV) NS3/4A protease inhibitor, and pibrentasvir, an HCV NS5A inhibitor, and is indicated for the treatment of adult and pediatric patients 3 years and older with acute or chronic HCV genotype (GT) 1, 2, 3, 4, 5 or 6 infection without cirrhosis or with compensated cirrhosis (Child-Pugh A). MAVYRET is indicated for the treatment of adult and pediatric patients 3 years and older with HCV genotype 1 infection, who previously have been treated with a regimen containing an HCV NS5A inhibitor or an NS3/4A protease inhibitor, but not both.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Testing Prior to the Initiation of Therapy: Test all patients for HBV infection by measuring HBsAg and anti-HBc. ( 2.1 ) See recommended treatment duration for patients 3 years and older in tables below. ( 2.2 ) Treatment-Naïve Patients 1 HCV Genotype Treatment Duration No Cirrhosis Compensated Cirrhosis (Child-Pugh A) 1, 2, 3, 4, 5, or 6 8 weeks 8 weeks Treatment-naïve patients are those who have not received treatment for the current infection.
Treatment-Experienced Patients 1 Treatment Duration HCV Genotype Patients Previously Treated With a Regimen Containing: No Cirrhosis Compensated Cirrhosis (Child-Pugh A) 1 An NS5A inhibitor 2 without prior treatment with an NS3/4A protease inhibitor (PI) 16 weeks 16 weeks An NS3/4A PI 3 without prior treatment with an NS5A inhibitor 12 weeks 12 weeks 1, 2, 4, 5, or 6 PRS 4 8 weeks 12 weeks 3 PRS 4 16 weeks 16 weeks Treatment-experienced patients are those who previously received treatment for the current infection. Treated with prior regimens containing ledipasvir and sofosbuvir or daclatasvir with (peg) interferon and ribavirin.
Treated with prior regimens containing simeprevir and sofosbuvir, or simeprevir, boceprevir, or telaprevir with (peg) interferon and ribavirin. PRS=Prior treatment experience with regimens containing (peg) interferon, ribavirin, and/or sofosbuvir, but no prior treatment experience with an HCV NS3/4A PI or NS5A inhibitor. Recommended dosage in adults: Three tablets taken at the same time orally once daily (total daily dose: glecaprevir 300 mg and pibrentasvir 120 mg) with food.
( 2.3 ) Recommended dosage in pediatric patients 3 years and older: Pediatric Patients 3 Years to Less than 12 Years Old: Dosing is based on weight. Refer to Table 3 of the full prescribing information for specific dosing guidelines based on body weight. ( 2.4 ) Instructions for Use should be followed for preparation and administration of MAVYRET oral pellets.
( 2.5 ) Pediatric Patients 12 Years of Age and Older, or Pediatric Patients Weighing at Least 45 kg: three tablets taken at the same time orally once daily (total daily dose: glecaprevir 300 mg and pibrentasvir 120 mg) with food. ( 2.4 ) HCV/HIV-1 co-infection and patients with any degree of renal impairment: Follow the dosage recommendations in the tables above. ( 2.2 ) Liver or Kidney Transplant Recipients: MAVYRET is recommended for 12 weeks in patients 3 years and older who are liver or kidney transplant recipients.
A 16-week treatment duration is recommended in genotype 1-infected patients who are NS5A inhibitor-experienced without prior treatment with an NS3/4A PI or in genotype 3-infected patients who are PRS treatment-experienced. ( 2.6 )
2.1Testing Prior to the Initiation of Therapy Test all patients for evidence of current or prior HBV infection by measuring hepatitis B surface antigen (HBsAg) and hepatitis B core antibody (anti-HBc) before initiating HCV treatment with MAVYRET [see Warnings and Precautions ( 5.1 ) ] .
2.2Recommended Treatment Duration in Patients 3 Years and Older Tables 1 and 2 provide the recommended MAVYRET treatment duration based on the patient population in HCV mono-infected and HCV/HIV-1 co-infected patients with compensated liver disease (with or without cirrhosis) and with or without renal impairment including patients receiving dialysis [see Contraindications ( 4 ) and Clinical Studies ( 14 )] . Refer to Drug Interactions ( 7 ) for dosage recommendations for concomitant HIV-1 antiviral drugs. Table 1.
Recommended Duration for Treatment-Naïve Patients 1 HCV Genotype Treatment Duration No Cirrhosis Compensated Cirrhosis (Child-Pugh A) 1, 2, 3, 4, 5, or 6 8 weeks 8 weeks 1. Treatment-naïve patients are those who have not received treatment for the current infection. Table 2.
Recommended Duration for Treatment-Experienced Patients 1 Treatment Duration HCV Genotype Patients Previously Treated with a Regimen Containing: No Cirrhosis Compensated Cirrhosis (Child-Pugh A)… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS MAVYRET is available as tablets or pellets for oral use. Tablets: pink, oblong-shaped, film-coated, and debossed with “NXT” on one side. Each tablet contains 100 mg glecaprevir and 40 mg of pibrentasvir.
Oral pellets: pink and yellow coated pellets in unit-dose packets. Each packet contains 50 mg glecaprevir and 20 mg pibrentasvir. Tablets: 100 mg glecaprevir and 40 mg pibrentasvir.
( 3 ) Oral Pellets: 50 mg glecaprevir and 20 mg pibrentasvir. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS MAVYRET is contraindicated in patients with moderate or severe hepatic impairment (Child-Pugh B or C) or those with any history of prior hepatic decompensation [see Warnings and Precautions ( 5.2 ), Use in Specific Populations ( 8.7 ) and Clinical Pharmacology ( 12.3 )] . MAVYRET is contraindicated with atazanavir or rifampin [see Drug Interaction ( 7.3 ) and Clinical Pharmacology ( 12.3 )] . Patients with moderate or severe hepatic impairment (Child-Pugh B or C) or those with any history of prior hepatic decompensation.
( 4 , 5.2 ) Coadministration with atazanavir or rifampin. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of Hepatitis B Virus Reactivation: Test all patients for evidence of current or prior HBV infection before initiation of HCV treatment. Monitor HCV/HBV coinfected patients for HBV reactivation and hepatitis flare during HCV treatment and post-treatment follow-up. Initiate appropriate patient management for HBV infection as clinically indicated.
( 5.1 ) Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease: Hepatic decompensation/failure, including fatal outcomes, have been reported mostly in patients with cirrhosis and baseline moderate or severe liver impairment (Child-Pugh B or C). Monitor for clinical and laboratory evidence of hepatic decompensation. Discontinue MAVYRET in patients who develop evidence of hepatic decompensation/failure.
( 5.2 )
5.1Risk of Hepatitis B Virus Reactivation in Patients Coinfected with HCV and HBV Hepatitis B virus (HBV) reactivation has been reported in HCV/HBV coinfected patients who were undergoing or had completed treatment with HCV direct-acting antivirals, and who were not receiving HBV antiviral therapy. Some cases have resulted in fulminant hepatitis, hepatic failure and death. Cases have been reported in patients who are HBsAg positive and also in patients with serologic evidence of resolved HBV infection (i.e., HBsAg negative and anti-HBc positive).
HBV reactivation has also been reported in patients receiving certain immunosuppressant or chemotherapeutic agents; the risk of HBV reactivation associated with treatment with HCV direct-acting antivirals may be increased in these patients. HBV reactivation is characterized as an abrupt increase in HBV replication manifesting as a rapid increase in serum HBV DNA level. In patients with resolved HBV infection reappearance of HBsAg can occur.
Reactivation of HBV replication may be accompanied by hepatitis, i.e., increase in aminotransferase levels and, in severe cases, increases in bilirubin levels, liver failure, and death can occur. Test all patients for evidence of current or prior HBV infection by measuring HBsAg and anti- HBc before initiating HCV treatment with MAVYRET. In patients with serologic evidence of HBV infection, monitor for clinical and laboratory signs of hepatitis flare or HBV reactivation during HCV treatment with MAVYRET and during post-treatment follow-up.
Initiate appropriate patient management for HBV infection as clinically indicated.
5.2Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease Postmarketing cases of hepatic decompensation/failure, including those with fatal outcomes, have been reported in patients treated with HCV NS3/4A protease inhibitor-containing regimens, including MAVYRET. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The majority of patients with severe outcomes had evidence of advanced liver disease with moderate or severe hepatic impairment (Child-Pugh B or C) prior to initiating therapy with MAVYRET, including some patients reported as having compensated cirrhosis with mild liver impairment (Child-Pugh A) at baseline but with a prior decompensation event (i.e., prior history of ascites, variceal bleeding, encephalopathy).
Rare cases of hepatic decompensation/failure were reported in patients without cirrhosis or with compensated cirrhosis (Child-Pugh A); many of these patients had evidence of portal hypertension. Events also occurred in patients taking a concomitant medication not recommended for coadministration, or in patients with confounding factors such as serious liver-related medical or surgical comorbidities. Cases typically occurred within the first 4 weeks of treatment (median of 27 days).
In patients with compensated cirrhosis (Child-Pugh A) or evidence of advanced liver disease such as portal hypertension, perform hepatic labo… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS In subjects receiving MAVYRET, the most commonly reported adverse reactions (greater than 10%) are headache and fatigue. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AbbVie Inc. at 1-800-633-9110 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of MAVYRET cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Overall Adverse Reactions in Subjects with Chronic HCV Infection without Cirrhosis or with Compensated Cirrhosis (Child-Pugh A) The adverse reactions data for MAVYRET in subjects without cirrhosis or with compensated cirrhosis (Child-Pugh A) were derived from nine registrational Phase 2 and 3 trials which evaluated approximately 2,300 adults infected with genotype 1, 2, 3, 4, 5, or 6 HCV who received MAVYRET for 8, 12 or 16 weeks [see Clinical Studies ( 14 ) ] .
The overall proportion of subjects who permanently discontinued treatment due to adverse reactions was 0.1% for subjects who received MAVYRET for 8, 12 or 16 weeks. The most common adverse reactions, all grades, observed in greater than or equal to 5% of subjects receiving 8, 12, or 16 weeks of treatment with MAVYRET were headache (13%), fatigue (11%), and nausea (8%). In subjects receiving MAVYRET who experienced adverse reactions, 80% had an adverse reaction of mild severity (Grade 1).
One subject experienced a serious adverse reaction. Adverse reactions (type and severity) were similar for subjects receiving MAVYRET for 8, 12 or 16 weeks. The type and severity of adverse reactions in subjects with compensated cirrhosis (Child-Pugh A) were similar to those seen in subjects without cirrhosis.
Adverse Reactions in Subjects with Chronic HCV Infection without Cirrhosis ENDURANCE-2 Among 302 treatment-naïve or PRS treatment-experienced, HCV genotype 2-infected adults without cirrhosis enrolled in ENDURANCE-2, adverse reactions (all intensity) occurring in at least 5% of subjects treated with MAVYRET for 12 weeks are presented in Table 4 . In subjects treated with MAVYRET for 12 weeks, 32% reported an adverse reaction, of which 98% had adverse reactions of mild or moderate severity. No subjects treated with MAVYRET or placebo in ENDURANCE-2 permanently discontinued treatment due to an adverse drug reaction.
Table 4. Adverse Reactions Reported in ≥5% of Treatment-Naïve and PRS-Experienced Adults without Cirrhosis Receiving MAVYRET for 12 Weeks in ENDURANCE-2 Adverse Reaction MAVYRET 12 Weeks (N = 202) % Placebo 12 Weeks (N = 100) % Headache 9 6 Nausea 6 2 Diarrhea 5 2 ENDURANCE-3 Among 505 treatment-naïve, HCV genotype 3-infected adults without cirrhosis enrolled in ENDURANCE-3, adverse reactions (all intensity) occurring in at least 5% of subjects treated with MAVYRET for 8 or 12 weeks are presented in Table 5 . In subjects treated with MAVYRET, 45% reported an adverse reaction, of which 99% had adverse reactions of mild or moderate severity.
The proportion of subjects who permanently discontinued treatment due to adverse reactions was 0%, < 1% and 1% for the MAVYRET 8-week arm, MAVYRET 12 week arm and DCV + SOF arm, respectively. Table 5. Adverse Reactions Reported in ≥5% of Treatment-Naïve Adults without Cirrhosis Receiving MAVYRET for 8 Weeks or 12 Weeks in ENDURANCE-3 Adverse Reaction MAVYRET* 8 Weeks (N = 157) % MAVYRET 12 Weeks (N = 233) % DCV 1 + SOF 2 12 Weeks (N = 115) % Headache 16 17 15 Fatigue 11 14 12 Nausea 9 12 12 Diarrhea 7 3 3 1 DCV=daclatasvir 2 SOF=sofosbuvir * The 8-week arm was a non-randomized treatment arm.
Adverse Reactions in Subjects with Chronic HCV Infection with Compensated Cirrhosis (Child-Pugh A) The safety of MAVYRET in HCV GT 1, 2, 3, 4, 5, or 6 subjects with compensated cirrhosis is based on data from 288 adults from the Phase 2/3 registrational trials treated with MAVYRET for 12 or… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Carbamazepine, efavirenz, and St. John’s wort may decrease concentrations of glecaprevir and pibrentasvir. Coadministration of carbamazepine, efavirenz containing regimens, and St.
John’s wort with MAVYRET is not recommended. ( 5.3 ) Clearance of HCV infection with direct-acting antivirals may lead to changes in hepatic function, which may impact safe and effective use of concomitant medications. Frequent monitoring of relevant laboratory parameters (INR or blood glucose) and dose adjustments of certain concomitant medications may be necessary.
( 7.3 ) Medication- Assisted Treatment (MAT) for Opioid Use Disorder. ( 7.4 ) Consult the full prescribing information prior to and during treatment for potential drug interactions. ( 4 , 7 , 12.3 )
7.1Mechanisms for the Potential Effect of MAVYRET on Other Drugs Glecaprevir and pibrentasvir are inhibitors of P-glycoprotein (P-gp), breast cancer resistance protein (BCRP), and organic anion transporting polypeptide (OATP) 1B1/3. Coadministration with MAVYRET may increase plasma concentration of drugs that are substrates of P-gp, BCRP, OATP1B1 or OATP1B3. Glecaprevir and pibrentasvir are weak inhibitors of cytochrome P450 (CYP) 3A, CYP1A2, and uridine glucuronosyltransferase (UGT) 1A1.
7.2Mechanisms for the Potential Effect of Other Drugs on MAVYRET Glecaprevir and pibrentasvir are substrates of P-gp and/or BCRP. Glecaprevir is a substrate of OATP1B1/3. Coadministration of MAVYRET with drugs that inhibit hepatic P-gp, BCRP, or OATP1B1/3 may increase the plasma concentrations of glecaprevir and/or pibrentasvir.
Coadministration of MAVYRET with drugs that induce P-gp/CYP3A may decrease glecaprevir and pibrentasvir plasma concentrations. Carbamazepine, phenytoin, efavirenz, and St. John’s wort may significantly decrease plasma concentrations of glecaprevir and pibrentasvir, leading to reduced therapeutic effect of MAVYRET.
The use of these agents with MAVYRET is not recommended [see Warnings and Precautions ( 5.3 ) and Clinical Pharmacology ( 12.3 )] .
7.3Established and Other Potential Drug Interactions Clearance of HCV infection with direct-acting antivirals may lead to changes in hepatic function, which may impact the safe and effective use of concomitant medications. For example, altered blood glucose control resulting in serious symptomatic hypoglycemia has been reported in diabetic patients in postmarketing case reports and published epidemiological studies. Management of hypoglycemia in these cases required either discontinuation or dose modification of concomitant medications used for diabetes treatment.
Frequent monitoring of relevant laboratory parameters (e.g. International Normalized Ratio [INR] in patients taking warfarin, blood glucose levels in diabetic patients) or drug concentrations of concomitant medications such as CYP P450 substrates with a narrow therapeutic index (e.g. certain immunosuppressants) is recommended to ensure safe and effective use. Dose adjustments of concomitant medications may be necessary.
Table 6 provides the effect of MAVYRET on concentrations of coadministered drugs and the effect of coadministered drugs on glecaprevir and pibrentasvir [see Contraindications ( 4 ) , Warnings and Precautions ( 5.3 ) , and Clinical Pharmacology ( 12.3 ) ] . All interaction studies were performed in adults. Table 6.
Potentially Significant Drug Interactions Identified in Drug Interaction Studies Concomitant Drug Class: Drug Name Effect on Concentration Clinical Comments Antiarrhythmics: Digoxin ↑ digoxin Measure serum digoxin concentrations before initiating MAVYRET. Reduce digoxin concentrations by decreasing the dose by approximately 50% or by modifying the dosing frequency and continue monitoring. Anticoagulants: Dabigatran etexilate ↑ dabigatran If MAVYRET and dabigatran etexilate are coadministered, refer to the dabigatran etexilate prescribing information for dabigatran etexilate dose modifications in combination with P-gp inhibitors in the… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary No adequate human data are available to establish whether or not MAVYRET poses a risk to pregnancy outcomes. In animal reproduction studies, no adverse developmental effects were observed when the components of MAVYRET were administered separately during organogenesis at exposures up to 53 times (rats; glecaprevir) or 51 and 1.5 times (mice and rabbits, respectively; pibrentasvir) the human exposures at the recommended dose of MAVYRET (see Data ) . No definitive conclusions regarding potential developmental effects of glecaprevir could be made in rabbits, since the highest achieved glecaprevir exposure in this species was only 7% (0.07 times) of the human exposure at the recommended dose.
There were no effects with either compound in rodent pre/post-natal developmental studies in which maternal systemic exposures (AUC) to glecaprevir and pibrentasvir were approximately 47 and 74 times, respectively, the exposure in humans at the recommended dose (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Glecaprevir Glecaprevir was administered orally to pregnant rats (up to 120 mg/kg/day) and rabbits (up to 60 mg/kg/day) during the period of organogenesis (gestation days (GD) 6 to 18, and GD 7 to 19, respectively). No adverse embryo-fetal effects were observed in rats at dose levels up to 120 mg/kg/day (53 times the exposures in humans at the recommended human dose (RHD)). In rabbits, the highest glecaprevir exposure achieved was 7% (0.07 times) of the exposure in humans at RHD.
As such, data in rabbits during organogenesis are not available for glecaprevir systemic exposures at or above the exposures in humans at the RHD. In the pre/post-natal developmental study in rats, glecaprevir was administered orally (up to 120 mg/kg/day) from GD 6 to lactation day 20. No effects were observed at maternal exposures 47 times the exposures in humans at the RHD.
Pibrentasvir Pibrentasvir was administered orally to pregnant mice and rabbits (up to 100 mg/kg/day) during the period of organogenesis (GD 6 to 15, and GD 7 to 19, respectively). No adverse embryo-fetal effects were observed at any studied dose level in either species. The systemic exposures at the highest doses were 51 times (mice) and 1.5 times (rabbits) the exposures in humans at the RHD.
In the pre/post-natal developmental study in mice, pibrentasvir was administered orally (up to 100 mg/kg/day) from GD 6 to lactation day 20. No effects were observed at maternal exposures approximately 74 times the exposures in humans at the RHD.
8.2Lactation Risk Summary It is not known whether the components of MAVYRET are excreted in human breast milk, affect human milk production, or have effects on the breastfed infant. When administered to lactating rodents, the components of MAVYRET were present in milk, without effect on growth and development observed in the nursing pups (see Data ) . The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for MAVYRET and any potential adverse effects on the breastfed child from MAVYRET or from the underlying maternal condition.
Data No significant effects of glecaprevir or pibrentasvir on growth and post-natal development were observed in nursing pups at the highest doses tested (120 mg/kg/day for glecaprevir and 100 mg/kg/day for pibrentasvir). Maternal systemic exposure (AUC) to glecaprevir and pibrentasvir was approximately 47 or 74 times the exposure in humans at the RHD. Systemic exposure in nursing pups on post-natal day 14 was approximately 0.6 to 2.2 % of the maternal exposure for glecaprevir and approximately one quarter to one third of the maternal exposure for pibrentasvir.
Glecaprevir or… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary No adequate human data are available to establish whether or not MAVYRET poses a risk to pregnancy outcomes. In animal reproduction studies, no adverse developmental effects were observed when the components of MAVYRET were administered separately during organogenesis at exposures up to 53 times (rats; glecaprevir) or 51 and 1.5 times (mice and rabbits, respectively; pibrentasvir) the human exposures at the recommended dose of MAVYRET (see Data ) . No definitive conclusions regarding potential developmental effects of glecaprevir could be made in rabbits, since the highest achieved glecaprevir exposure in this species was only 7% (0.07 times) of the human exposure at the recommended dose.
There were no effects with either compound in rodent pre/post-natal developmental studies in which maternal systemic exposures (AUC) to glecaprevir and pibrentasvir were approximately 47 and 74 times, respectively, the exposure in humans at the recommended dose (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Glecaprevir Glecaprevir was administered orally to pregnant rats (up to 120 mg/kg/day) and rabbits (up to 60 mg/kg/day) during the period of organogenesis (gestation days (GD) 6 to 18, and GD 7 to 19, respectively). No adverse embryo-fetal effects were observed in rats at dose levels up to 120 mg/kg/day (53 times the exposures in humans at the recommended human dose (RHD)). In rabbits, the highest glecaprevir exposure achieved was 7% (0.07 times) of the exposure in humans at RHD.
As such, data in rabbits during organogenesis are not available for glecaprevir systemic exposures at or above the exposures in humans at the RHD. In the pre/post-natal developmental study in rats, glecaprevir was administered orally (up to 120 mg/kg/day) from GD 6 to lactation day 20. No effects were observed at maternal exposures 47 times the exposures in humans at the RHD.
Pibrentasvir Pibrentasvir was administered orally to pregnant mice and rabbits (up to 100 mg/kg/day) during the period of organogenesis (GD 6 to 15, and GD 7 to 19, respectively). No adverse embryo-fetal effects were observed at any studied dose level in either species. The systemic exposures at the highest doses were 51 times (mice) and 1.5 times (rabbits) the exposures in humans at the RHD.
In the pre/post-natal developmental study in mice, pibrentasvir was administered orally (up to 100 mg/kg/day) from GD 6 to lactation day 20. No effects were observed at maternal exposures approximately 74 times the exposures in humans at the RHD.
🧒 Pediatric Use ▾
8.4Pediatric Use No dosage adjustment of MAVYRET is required in pediatric patients 12 years and older or weighing at least 45 kg. The recommended dosage of MAVYRET in pediatric patients 3 to less than 12 years of age is based on weight [see Dosage and Administration ( 2.2 , 2.4 ) , Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14.10 ) ] . The safety, efficacy, and pharmacokinetics of MAVYRET in HCV GT1, 2, 3, or 4 infected pediatric patients 3 years and older is based on data from an open-label trial in 127 subjects with chronic HCV infection, without cirrhosis, and aged 3 years to less than 18 years who were either treatment-naïve (n=114) or treatment-experienced (n=13) and received MAVYRET for 8, 12 or 16 weeks (DORA-Part 1 and Part 2).
The adverse reactions observed in subjects 3 years to less than 18 years of age were consistent with those observed in clinical trials of MAVYRET in adults with chronic HCV infection with the exception of vomiting, rash and abdominal pain upper which were observed more frequently in pediatric subjects less than 12 years of age compared to adults [see Adverse Reactions ( 6.1 ) ] . The efficacy results observed in this trial were consistent with those observed in clinical trials of MAVYRET in adults [see Clinical Studies ( 14.10 ) ] .
Use of MAVYRET in pediatric patients with acute HCV infection is supported by extrapolation of safety and efficacy data from adult patients with acute HCV infection and adult and pediatric patients with chronic HCV infection. It is expected that adult and pediatric patients with acute HCV infection have similar disease response to treatment. No clinically meaningful differences in MAVYRET exposures are expected among pediatric patients with acute HCV infection and pediatric patients with chronic HCV infection [see Clinical Pharmacology ( 12.3 )].
In pediatric patients with cirrhosis, history of a kidney and/or liver transplant, or HCV GT5 or 6 infection, the safety and efficacy of MAVYRET are supported by the comparable glecaprevir and pibrentasvir exposures observed between pediatric subjects and adults [see Clinical Pharmacology ( 12.3 ) ] . The safety and effectiveness of MAVYRET in children less than 3 years of age have not been studied.
🧓 Geriatric Use ▾
8.5Geriatric Use In clinical trials of MAVYRET in subjects with chronic HCV infection, 328 subjects were age 65 years and over (14% of the total number of subjects in the Phase 2 and 3 clinical trials), and 47 (2%) subjects were age 75 and over. In a clinical trial of MAVYRET in subjects with acute HCV infection, 16 subjects were age 65 years and over (6%), and 1 (0.3%) subject was age 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger subjects.
No dosage adjustment of MAVYRET is warranted in geriatric patients [see Clinical Pharmacology ( 12.3 ) ] .
🆘 Overdosage ▾
10 OVERDOSAGE In case of overdose, the patient should be monitored for any signs and symptoms of toxicities. Appropriate symptomatic treatment should be instituted immediately. Glecaprevir and pibrentasvir are not significantly removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Mechanism of Action MAVYRET is a fixed-dose combination of glecaprevir and pibrentasvir, which are direct-acting antiviral agents against the hepatitis C virus [see Microbiology ( 12.4 ) ] .
12.2Pharmacodynamics Cardiac Electrophysiology The effect of doses up to glecaprevir 600 mg (2 times the recommended dosage) with doses up to pibrentasvir 240 mg (2 times the recommended dosage) on QTc interval was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT study. At 20-fold of glecaprevir and 5-fold of pibrentasvir therapeutic concentrations, the glecaprevir and pibrentasvir combination does not prolong the QTc interval to any clinically relevant extent.
12.3Pharmacokinetics The pharmacokinetic properties of the components of MAVYRET in healthy subjects are provided in Table 7 . The steady-state pharmacokinetic parameters of glecaprevir and pibrentasvir in subjects with chronic HCV infection without cirrhosis are provided in Table 8 . For pellets relative to tablets in healthy adult subjects under non-fasting conditions, geometric mean ratios (GMRs) of glecaprevir and pibrentasvir C max were 0.664 and 1.137, AUC inf were 0.795 and 1.219, and C 24 (concentrations at 24 hours post-dose) were 0.917 and 1.174.
These differences were not considered clinically significant. Table 7. Pharmacokinetic Properties of the Components of MAVYRET in Healthy Subjects Glecaprevir Pibrentasvir Absorption T max (h) a of tablets 5.0
5.0T max (h) a of oral pellets 3.0
5.0Effect of meal (relative to fasting) b on tablets ↑ 83-163% ↑ 40-53% Effect of meal (relative to fasting) b on oral pellets ↑ 131-167% ↑ 56-114% Distribution % Bound to human plasma proteins 97.5 >99.9 Blood-to-plasma ratio 0.57
0.62Elimination t 1/2 (h) 6 13 Metabolism secondary, None CYP3A Major route of excretion biliary-fecal biliary-fecal % of dose excreted in urine c 0.7 0 % of dose excreted in feces c 92.1 96.6 a. Median T max following single doses of glecaprevir and pibrentasvir in healthy subjects. b. Mean systemic exposures with low/moderate to high fat meals. c.
Single dose administration of radiolabeled glecaprevir or pibrentasvir in mass balance studies. Table 8. Steady-State Pharmacokinetic Parameters of Glecaprevir and Pibrentasvir Following Administration of MAVYRET in Subjects with Chronic HCV In f ection without Cirrhosis Pharmacokinetic Parameter Glecaprevir b Pibrentasvir c C max (ng/mL) a 597 (114) 110 (49) AUC 24,ss (ng•h/mL) a 4800 (122) 1430 (57) C trough,ss (ng/mL) a 13.0 (334) 18.9 (92) a Geometric mean (%CV) of individual-estimated C max , AUC 24,ss and C trough,ss values b Relative to healthy subjects, glecaprevir C max was 51% lower, AUC 24,ss was similar (10% difference), and C trough,ss was 157% higher in subjects without cirrhosis with chronic HCV infection c Relative to healthy subjects, pibrentasvir C max was 63% lower, AUC 24,ss was 34% lower, and C trough,ss was 37% lower in subjects without cirrhosis with chronic HCV infection No clinically meaningful differences in glecaprevir and pibrentasvir exposures are expected among adult patients with acute HCV infection and adult patients with chronic HCV infection.
Specific Populations Pediatric Patients The pharmacokinetics of glecaprevir and pibrentasvir were determined in pediatric subjects with chronic HCV infection who were 3 years of age and older receiving a daily dose of MAVYRET as described below in Table 9 . GMRs of glecaprevir and pibrentasvir C max and AUC 24 in pediatrics vs. adults with chronic HCV infection ranged from 1.58-2.68 and 0.965-1.64, respectively. GMRs of glecaprevir C trough ranged from 0.292-0.954 and GMRs of pibrentasvir C trough ranged from 0.794-1.93.
All pediatric glecaprevir and pibrentasvir PK parameter values fell within the range observed in adult subjects. These differences were not considered clinically significant. No clinically meaningful differences in glecaprevir and pibrentasvir exposures are… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Mechanism of Action MAVYRET is a fixed-dose combination of glecaprevir and pibrentasvir, which are direct-acting antiviral agents against the hepatitis C virus [see Microbiology ( 12.4 ) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING MAVYRET Tablets Configuration Content Package Size NDC Monthly carton (blister pack) 4 weekly cartons 7 daily blisters/carton 3 tablets/blister 84 tablets 0074-2625-04 Monthly carton (wallet) 4 weekly cartons 7 daily wallets/carton 3 tablets/wallet 84 tablets 0074-2625-28 8-Week Carton 2 monthly cartons 4 weekly cartons/monthly carton 7 daily wallets/carton 3 tablets/wallet 168 tablets 0074-2625-56 Bottle 84 tablets 0074-2625-84 MAVYRET tablets are pink-colored, film-coated, oblong biconvex shaped, debossed with “NXT” on one side.
Store at or below 30°C (86°F). MAVYRET Oral Pellets MAVYRET oral pellets are dispensed in child-resistant unit-dose packets in cartons. Each carton contains 28 packets.
Each packet contains 50 mg glecaprevir/20 mg pibrentasvir pink and yellow oral pellets. The NDC number is 0074-2600-28. Store at or below 30°C (86°F).
📋 Description ▾
11 DESCRIPTION MAVYRET contains glecaprevir, a HCV NS3/4A PI, and pibrentasvir a HCV NS5A inhibitor. MAVYRET is available as a fixed dose combination tablet or coated pellets in unit-dose packets for oral administration. Glecaprevir/Pibrentasvir Film-Coated Immediate Release Tablets Each tablet contains 100 mg of glecaprevir and 40 mg of pibrentasvir.
Glecaprevir and pibrentasvir are presented as a co-formulated, fixed-dose combination, immediate release bilayer tablet. The tablet contains the following inactive ingredients: colloidal silicon dioxide, copovidone (type K 28), croscarmellose sodium, hypromellose 2910, iron oxide red, lactose monohydrate, polyethylene glycol 3350, propylene glycol monocaprylate (type II), sodium stearyl fumarate, titanium dioxide, and vitamin E (tocopherol) polyethylene glycol succinate. The tablets do not contain gluten.
Glecaprevir/Pibrentasvir Coated Oral Pellets MAVYRET oral pellets are small, pink and yellow and supplied in unit-dose packets for oral administration. Each unit-dose of MAVYRET oral pellets in packets contains 50 mg glecaprevir and 20 mg pibrentasvir and the following inactive ingredients: colloidal silicon dioxide, copovidone (type K 28), croscarmellose sodium, hypromellose 2910, iron oxide red, iron oxide yellow, lactose monohydrate, polyethylene glycol/macrogol 3350, propylene glycol monocaprylate (type II), sodium stearyl fumarate, titanium dioxide, vitamin E (tocopherol) polyethylene glycol succinate.
The oral pellets do not contain gluten. Glecaprevir drug substance: The chemical name of glecaprevir is (3a R ,7 S ,10 S ,12 R ,21 E ,24a R )-7- tert -butyl- N -{(1 R ,2 R )-2-(difluoromethyl)-1-[(1-methylcyclopropane-1-sulfonyl)carbamoyl]cyclopropyl}-20,20-difluoro-5,8-dioxo-2,3,3a,5,6,7,8,11,12,20,23,24a-dodecahydro-1 H ,10 H -9,12-methanocyclopenta[18,19][1,10,17,3,6]trioxadiazacyclononadecino[11,12- b ]quinoxaline-10-carboxamide hydrate. The molecular formula is C 38 H 46 F 4 N 6 O 9 S (anhydrate) and the molecular weight for the drug substance is 838.87 g/mol (anhydrate).
The strength of glecaprevir is based on anhydrous glecaprevir. Glecaprevir is a white to off-white crystalline powder with a solubility of less than 0.1 to 0.3 mg/mL across a pH range of 2–7 at 37°C and is practically insoluble in water, but is sparingly soluble in ethanol. Glecaprevir has the following molecular structure: Pibrentasvir drug substance: The chemical name of pibrentasvir is Methyl {(2 S ,3 R )-1-[(2 S )-2-{5-[(2 R ,5 R )-1-{3,5-difluoro-4-[4-(4-fluorophenyl)piperidin-1-yl]phenyl}-5-(6-fluoro-2-{(2 S )-1-[ N -(methoxycarbonyl)- O -methyl-L-threonyl]pyrrolidin-2-yl}-1 H -benzimidazol-5-yl)pyrrolidin-2-yl]-6-fluoro-1 H -benzimidazol-2-yl}pyrrolidin-1-yl]-3-methoxy-1-oxobutan-2-yl}carbamate.
The molecular formula is C 57 H 65 F 5 N 10 O 8 and the molecular weight for the drug substance is 1113.18 g/mol. Pibrentasvir is a white to off-white to light yellow crystalline powder with a solubility of less than 0.1 mg/mL across a pH range of 1–7 at 37°C and is practically insoluble in water, but is freely soluble in ethanol. Pibrentasvir has the following molecular structure: Glecaprevir Pibrentasvir
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Risk of Hepatitis B Virus Reactivation in Patients Coinfected with HCV and HBV Inform patients that HBV reactivation can occur in patients coinfected with HBV during or after treatment of HCV infection. Advise patients to tell their healthcare provider if they have a history of hepatitis B virus infection [see Warnings and Precautions ( 5.1 ) ] .
Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease Advise patients to seek medical evaluation immediately for symptoms of worsening liver problems such as nausea, tiredness, yellowing of the skin or white part of the eyes, bleeding or bruising more easily than normal, confusion, loss of appetite, diarrhea, dark or brown urine, dark or bloody stool, swelling of the stomach area (abdomen) or pain in the upper right side of the stomach area, sleepiness, or vomiting of blood [see Warnings and Precautions ( 5.2 )] .
Drug Interactions Inform patients that MAVYRET may interact with some drugs; therefore, patients should be advised to report to their healthcare provider the use of any prescription, non-prescription medication or herbal products [see Contraindications ( 4 ) , Warnings and Precautions ( 5.3 ) and Drug Interactions ( 7 ) ] . Administration For MAVYRET oral pellets, advise patients or caregivers to read and follow the Instructions for Use for preparing the correct dose [see Dosage and Administration ( 2.4 , 2.5 )] . Inform patients it is important to take all three tablets at the same time once daily with food as directed.
Inform patients that it is important not to miss or skip doses and to take MAVYRET for the duration that is recommended by the physician [see Dosage and Administration ( 2.2 ) ] . If a dose is missed and it is: Less than 18 hours from the usual time that MAVYRET should have been taken – advise the patient to take the dose as soon as possible and then to take the next dose at the usual time. More than 18 hours from the usual time that MAVYRET should have been taken – advise the patient not to take the missed dose and to take the next dose at the usual time.
Manufactured by AbbVie Inc., North Chicago, IL 60064 MAVYRET and its design are trademarks of AbbVie Inc. © 2025 AbbVie Inc. All rights reserved. 20092779
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetic properties of the components of MAVYRET in healthy subjects are provided in Table 7 . The steady-state pharmacokinetic parameters of glecaprevir and pibrentasvir in subjects with chronic HCV infection without cirrhosis are provided in Table 8 . For pellets relative to tablets in healthy adult subjects under non-fasting conditions, geometric mean ratios (GMRs) of glecaprevir and pibrentasvir C max were 0.664 and 1.137, AUC inf were 0.795 and 1.219, and C 24 (concentrations at 24 hours post-dose) were 0.917 and 1.174.
These differences were not considered clinically significant. Table 7. Pharmacokinetic Properties of the Components of MAVYRET in Healthy Subjects Glecaprevir Pibrentasvir Absorption T max (h) a of tablets 5.0
5.0T max (h) a of oral pellets 3.0
5.0Effect of meal (relative to fasting) b on tablets ↑ 83-163% ↑ 40-53% Effect of meal (relative to fasting) b on oral pellets ↑ 131-167% ↑ 56-114% Distribution % Bound to human plasma proteins 97.5 >99.9 Blood-to-plasma ratio 0.57
0.62Elimination t 1/2 (h) 6 13 Metabolism secondary, None CYP3A Major route of excretion biliary-fecal biliary-fecal % of dose excreted in urine c 0.7 0 % of dose excreted in feces c 92.1 96.6 a. Median T max following single doses of glecaprevir and pibrentasvir in healthy subjects. b. Mean systemic exposures with low/moderate to high fat meals. c.
Single dose administration of radiolabeled glecaprevir or pibrentasvir in mass balance studies. Table 8. Steady-State Pharmacokinetic Parameters of Glecaprevir and Pibrentasvir Following Administration of MAVYRET in Subjects with Chronic HCV In f ection without Cirrhosis Pharmacokinetic Parameter Glecaprevir b Pibrentasvir c C max (ng/mL) a 597 (114) 110 (49) AUC 24,ss (ng•h/mL) a 4800 (122) 1430 (57) C trough,ss (ng/mL) a 13.0 (334) 18.9 (92) a Geometric mean (%CV) of individual-estimated C max , AUC 24,ss and C trough,ss values b Relative to healthy subjects, glecaprevir C max was 51% lower, AUC 24,ss was similar (10% difference), and C trough,ss was 157% higher in subjects without cirrhosis with chronic HCV infection c Relative to healthy subjects, pibrentasvir C max was 63% lower, AUC 24,ss was 34% lower, and C trough,ss was 37% lower in subjects without cirrhosis with chronic HCV infection No clinically meaningful differences in glecaprevir and pibrentasvir exposures are expected among adult patients with acute HCV infection and adult patients with chronic HCV infection.
Specific Populations Pediatric Patients The pharmacokinetics of glecaprevir and pibrentasvir were determined in pediatric subjects with chronic HCV infection who were 3 years of age and older receiving a daily dose of MAVYRET as described below in Table 9 . GMRs of glecaprevir and pibrentasvir C max and AUC 24 in pediatrics vs. adults with chronic HCV infection ranged from 1.58-2.68 and 0.965-1.64, respectively. GMRs of glecaprevir C trough ranged from 0.292-0.954 and GMRs of pibrentasvir C trough ranged from 0.794-1.93.
All pediatric glecaprevir and pibrentasvir PK parameter values fell within the range observed in adult subjects. These differences were not considered clinically significant. No clinically meaningful differences in glecaprevir and pibrentasvir exposures are expected among pediatric patients with acute HCV infection and pediatric patients with chronic HCV infection.
The pharmacokinetics of glecaprevir and pibrentasvir have not been established in children less than 3 years of age. Table 9. Pharmacokinetic Parameters of Glecaprevir (GLE) and Pibrentasvir (PIB) in Pediatric Subjects with Chronic HCV Infection Age and Weight (kg) N Total Daily Dose of GLE/PIB (mg) PK Parameter Geometric Mean (%CV) GLE PIB 12 to < 18 years, ≥ 45 kg 14 300/120 AUC 24 (ng•h/mL) 4790 (72) 1380 (40) C max (ng/mL) 1040 (86) 174 (36) C trough (ng/mL) 3.79 (82) 15.0 (61) 9 to < 12 years, 30 to < 45 kg 13 250/100 AUC 24 (ng•h/mL) 7870 (209) 2200 (99) C max (ng/mL) 1370 (169) 225 (72) C trough (ng/mL… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology The effect of doses up to glecaprevir 600 mg (2 times the recommended dosage) with doses up to pibrentasvir 240 mg (2 times the recommended dosage) on QTc interval was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT study. At 20-fold of glecaprevir and 5-fold of pibrentasvir therapeutic concentrations, the glecaprevir and pibrentasvir combination does not prolong the QTc interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Description of Clinical Trials Table 12 summarizes the clinical trials conducted to support the effectiveness of MAVYRET in subjects with HCV genotype 1, 2, 3, 4, 5 or 6 infection and compensated liver disease (including Child-Pugh A cirrhosis) according to treatment history and cirrhosis status. Table 12. Clinical Trials Conducted with MAVYRET in Subjects with HCV Genotype 1, 2, 3, 4, 5 or 6 Infection and Compensated Liver Disease Genotype (GT) Clinical Trial (NCT Number) Treatment Duration* Clinical Trials of Chronic HCV Infection TN and PRS-TE Subjects without Cirrhosis GT1** ENDURANCE-1 (NCT02604017) MAVYRET for 8 (n=351) or 12 weeks (n=352) GT2 SURVEYOR-2 (NCT02243293) MAVYRET for 8 weeks (n=197) GT3 ENDURANCE-3 (NCT02640157) MAVYRET for 8 (n=157) or 12 weeks (n=233) sofosbuvir + daclatasvir for 12 weeks (n=115) SURVEYOR-2 MAVYRET for 16 (PRS-TE only) weeks (n=22) GT4, 5, 6 ENDURANCE-5,6 (NCT02966795) MAVYRET for 8 weeks (GT5 n=20; GT6 n=55) SURVEYOR-2 MAVYRET for 8 weeks (GT4 n=46; GT5 n=2; GT6 n=10) GT1, 2, 3, 6 VOYAGE-1 (NCT03222583) MAVYRET for 8 (n=356) or 16 weeks (n=6; GT3 PRS-TE only) TN and PRS-TE Subjects with Compensated Cirrhosis GT1, 2, 4, 5, 6 EXPEDITION-1 (NCT02642432) MAVYRET for 12 weeks (n=146) GT1, 2, 3, 4, 5, 6 EXPEDITION-8 (NCT03089944) MAVYRET for 8 weeks (n=343) (TN only) GT3 SURVEYOR-2 MAVYRET for 16 weeks (PRS-TE only) (n=47) GT5, 6 ENDURANCE-5,6 MAVYRET for 12 weeks (GT 5 n=3; GT 6 n=6) GT1, 2, 3, 4, 6 VOYAGE-2 (NCT03235349) MAVYRET for 12 (n=157) or 16 weeks (n=3; GT3 PRS-TE only) Subjects with CKD Stage 4 and 5 without Cirrhosis or with Compensated Cirrhosis GT1-6 EXPEDITION-4 (NCT02651194) MAVYRET for 12 weeks (n=104) NS5A Inhibitor or PI-Experienced Subjects without Cirrhosis or with Compensated Cirrhosis GT1 MAGELLAN-1 (NCT02446717) MAVYRET for 12 (n=25) or 16 weeks (n=17) HCV/HIV-1 Co-Infected Subjects without Cirrhosis or with Compensated Cirrhosis GT1, 2, 3, 4, 6 EXPEDITION-2 (NCT02738138) MAVYRET for 8 (n=137) or 12 weeks (n=16) Liver or Kidney Transplant Recipients without Cirrhosis GT1, 2, 3, 4, 6 MAGELLAN-2 (NCT02692703) MAVYRET for 12 weeks (n=100) Adolescent Subjects (12 to less than 18 years) GT1, 2, 3, 4** DORA (Part 1) (NCT03067129) MAVYRET for 8 (n=44) or 16 weeks (n=3) Pediatric Subjects (3 to less than 12 years) GT1, 2, 3, 4** DORA (Part 2) (NCT03067129) MAVYRET for 8 (n=78), 12 (n=1), or 16 weeks (n=1) Clinical Trial of Acute HCV Infection GT1, 2, 3, 4** M20-350 (NCT04903626) MAVYRET for 8 weeks (n=286) TN=treatment naïve; PI=protease inhibitor; CKD=chronic kidney disease PRS-TE= defined as prior treatment experience with regimens containing (peg)interferon, ribavirin, and/or sofosbuvir, but no prior treatment experience with an HCV NS3/4A PI or NS5A inhibitor. * Treatment durations for some trial arms shown in this table do not reflect recommended dosing for the respective genotypes, prior treatment history, and/or cirrhosis status.
For recommended dosing in adults and pediatric patients 3 years and older [see Dosage and Administration ( 2.2 , 2.3 , 2.4 ) ] . ** ENDURANCE-1 included 33 subjects co-infected with HIV-1. DORA included 3 subjects co-infected with HIV-1. M20-350 included 142 subjects co-infected with HIV-1.
Serum HCV RNA values were measured during the clinical trials using the Roche COBAS AmpliPrep/COBAS TaqMan HCV test (version 2.0) with a lower limit of quantification (LLOQ) of 15 IU/mL (except for SURVEYOR-2 which used the Roche COBAS TaqMan real-time reverse transcriptase-PCR (RT-PCR) assay v. 2.0 with an LLOQ of 25 IU/mL). The primary endpoint across all clinical trials was sustained virologic response (SVR12), defined as HCV RNA less than LLOQ at 12 weeks after the end of treatment.
Relapse was defined as HCV RNA ≥ LLOQ after end-of-treatment response among subjects who completed treatment. Subjects with missing HCV RNA data, such as those who discontinued due to an adverse event, subject withdrawal or were lost to follow-up, were… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis and Mutagenesis Glecaprevir and pibrentasvir were not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes and in vivo rodent micronucleus assays. Carcinogenicity studies with glecaprevir and pibrentasvir have not been conducted. Impairment of Fertility No effects on mating, female or male fertility, or early embryonic development were observed in rodents at up to the highest dose tested.
Systemic exposures (AUC) to glecaprevir and pibrentasvir were approximately 63 and 102 times higher, respectively, than the exposure in humans at the recommended dose.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis and Mutagenesis Glecaprevir and pibrentasvir were not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes and in vivo rodent micronucleus assays. Carcinogenicity studies with glecaprevir and pibrentasvir have not been conducted. Impairment of Fertility No effects on mating, female or male fertility, or early embryonic development were observed in rodents at up to the highest dose tested.
Systemic exposures (AUC) to glecaprevir and pibrentasvir were approximately 63 and 102 times higher, respectively, than the exposure in humans at the recommended dose.
📄 Patient Package Insert ▾
Patient Information MAVYRET ® (MAV-ih-reht) (glecaprevir and pibrentasvir) tablets MAVYRET ® (MAV-ih-reht) (glecaprevir and pibrentasvir) oral pellets What is the most important information I should know about MAVYRET? MAVYRET can cause serious side effects, including: Hepatitis B virus reactivation. Before starting treatment with MAVYRET, your healthcare provider will do blood tests to check for hepatitis B virus infection.
If you have ever had hepatitis B virus infection, the hepatitis B virus could become active again during or after treatment for hepatitis C virus with MAVYRET. Hepatitis B virus that becomes active again (called reactivation) may cause serious liver problems including liver failure and death. Your healthcare provider will monitor you if you are at risk for hepatitis B virus reactivation during treatment and after you stop taking MAVYRET.
For more information about side effects, see the section “What are the possible side effects of MAVYRET?” What is MAVYRET? MAVYRET is a prescription medicine used to treat adults and children 3 years of age and older with: acute (recently infected) or chronic (lasting a long time) hepatitis C virus (HCV) genotypes 1, 2, 3, 4, 5 or 6 infection without cirrhosis or with compensated cirrhosis. HCV genotype 1 infection who have been previously treated with a regimen that contained an HCV NS5A inhibitor or an NS3/4A protease inhibitor (PI), but not both.
MAVYRET contains the 2 medicines: glecaprevir and pibrentasvir. It is not known if MAVYRET is safe and effective in children under 3 years of age. Do not take MAVYRET if you : have certain liver problems also take any of the following medicines: ○ atazanavir ○ rifampin Before taking MAVYRET, tell your healthcare provider about all of your medical conditions, including if you: have had hepatitis B virus infection have liver problems other than hepatitis C virus infection have HIV-1 infection have had a liver or a kidney transplant are pregnant or plan to become pregnant.
It is not known if MAVYRET will harm your unborn baby. are breastfeeding or plan to breastfeed. It is not known if MAVYRET passes into your breast milk. Talk to your healthcare provider about the best way to feed your baby during treatment with MAVYRET.
Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. MAVYRET and other medicines may affect each other. This can cause you to have too much or not enough MAVYRET or other medicines in your body.
This may affect the way MAVYRET or your other medicines work or may cause side effects. Keep a list of your medicines to show your healthcare provider and pharmacist. You can ask your healthcare provider or pharmacist for a list of medicines that interact with MAVYRET.
Do not start taking a new medicine without telling your healthcare provider. Your healthcare provider can tell you if it is safe to take MAVYRET with other medicines. How should I take MAVYRET?
Take MAVYRET exactly as your healthcare provider tells you to take it. Do not change your dose unless your healthcare provider tells you to. Do not stop taking MAVYRET without first talking with your healthcare provider.
Do not miss or skip doses of MAVYRET during treatment. Take MAVYRET with food. For adults, adolescents 12 years and older, or children weighing at least 99 pounds (45 kg), the usual dose of MAVYRET is 3 tablets at the same time each day.
For children 3 years to less than 12 years of age and weighing less than 99 pounds (45 kg), your child’s healthcare provider will prescribe the right dose of MAVYRET oral pellets based on your child’s body weight. If your child’s healthcare provider prescribes MAVYRET oral pellets for your child, see “ How should I give MAVYRET oral pellets to my child ?” If you miss a dose of MAVYRET and it is: Less than 18 hours from the time you usually take MAVYRET, take the missed dose with food as soon as possible. Then take you… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE MAVYRET ® (MAV-ih-reht) (glecaprevir and pibrentasvir) pellets for oral use INSTRUCTIONS FOR USE INSTRUCTIONS FOR USE
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 6/2025 Dosage and Administration ( 2.2 ) 6/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0074-2625-04 Rx only MAVYRET ® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg. This carton contains 21 tablets packaged as follows: 7 daily blisters for 1 week of treatment. Each daily blister contains 3 tablets.
MON TUE WED THU FRI SAT SUN Track your daily treatment by pushing in the tab above after removing each pack from carton. NDC 0074-2625-04 Rx only MAVYRET® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg. This carton contains 21 tablets packaged as follows: 7 daily blisters for 1 week of treatment.
Each daily blister contains 3 tablets. MON TUE WED THU FRI SAT SUN Track your daily treatment by pushing in the tab above after removing each pack from carton.
PRINCIPAL DISPLAY PANEL NDC 0074-2625-04 4-WEEK SUPPLY Rx only M AVYRET ® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg. This monthly carton contains 84 tablets packaged as follows: 4 weekly cartons of therapy. Each weekly carton contains 21 tablets in 7 daily blisters of 3 tablets each.
NDC 0074-2625-04 4-WEEK SUPPLY Rx only MAVYRET® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg. This monthly carton contains 84 tablets packaged as follows: 4 weekly cartons of therapy. Each weekly carton contains 21 tablets in 7 daily blisters of 3 tablets each.
PRINCIPAL DISPLAY PANEL NDC 0074-2625-28 Rx only M avyret ® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg. This carton contains 21 tablets packaged as follows: 7 wallets for 1 week of treatment. Each wallet contains 3 tablets.
MON TUE WED THU FRI SAT SUN Track your daily treatment by pushing in the tab above after removing each pack from carton. NDC 0074-2625-28 Rx only Mavyret® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg. This carton contains 21 tablets packaged as follows: 7 wallets for 1 week of treatment.
Each wallet contains 3 tablets. MON TUE WED THU FRI SAT SUN Track your daily treatment by pushing in the tab above after removing each pack from carton.
PRINCIPAL DISPLAY PANEL NDC 0074-2625-28 Rx only 4-WEEK SUPPLY Mavyret ® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg This monthly carton contains 84 tablets packaged as follows: 4 weekly cartons of therapy. Each weekly carton contains 21 tablets in 7 wallets of 3 tablets each. NDC 0074-2625-28 Rx only 4-WEEK SUPPLY Mavyret® (glecaprevir and pibrentasvir) 100mg / 40mg Each tablet contains glecaprevir and pibrentasvir 100mg / 40mg This monthly carton contains 84 tablets packaged as follows: 4 weekly cartons of therapy.
Each weekly carton contains 21 tablets in 7 wallets of 3 tablets each.
PRINCIPAL DISPLAY PANEL NDC 0074-2600-28 Rx only MAVYRET ® (glecaprevir/pibrentasivir) Oral Pellets 50 mg/20 mg Each packet contains pink and yellow oral pellets. 28 packets PRINCIPAL DISPLAY PANEL NDC 0074-2600-28 Rx only MAVYRET® (glecaprevir/pibrentasivir) Oral Pellets 50 mg/20 mg Each packet contains pink and yellow oral pellets. 28 packets
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |