
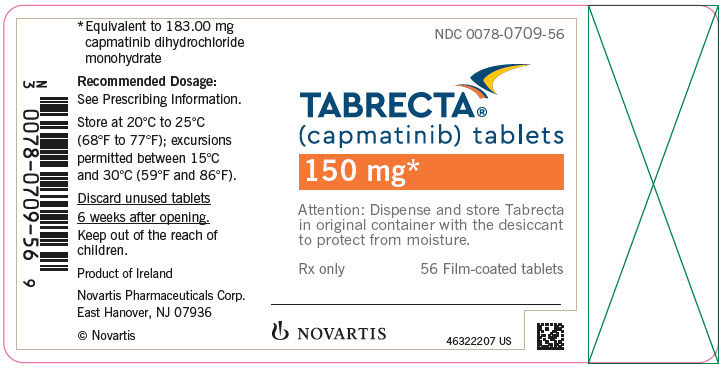
Tabrecta capmatinib 150 mg Tablet, Film Coated, 56-count — NDC 0078-0709-56 (Billing 00078-0709-56)
This is a package of 56 tablets of Tabrecta capmatinib 150 mg Tablet, Film Coated from Novartis Pharmaceuticals Corporation, marketed since May 2020 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0078-0709-56 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0078 labeler · 0709 product · 56 package
- Package marketed since
- May 6, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 56 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0078070956 9
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 081014
- GCN: 48012
- GPI-14 (Medi-Span): 21533716200320
- HICL (First Databank): 046519
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2362234
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Capmatinib is used to treat a certain type of non-small cell lung cancer (NSCLC) that has spread to other parts of the body. Capmatinib is in a class of medications called kinase inhibitors. It works by blocking the action of an abnormal protein that signals cancer cells to multiply. This helps slow or stop the spread of cancer cells.
Read the full MedlinePlus article ↗- It treats metastatic non-small cell lung cancer in adults. It is only for tumors with a MET exon 14 skipping mutation, which an FDA-approved test finds. If you're taking it, your d...
- Take your tablets by mouth twice a day, with or without food. Swallow them whole and don't crush, chew or break them. If you miss a dose or vomit, skip it and take the next one at...
- The most common are swelling, nausea, muscle and joint pain, tiredness, vomiting, shortness of breath, cough and low appetite. Tell your care team if these bother you. Your doctor...
- Call if you have new or worsening cough, fever or trouble breathing, since these can signal serious lung inflammation. Also call for signs of an allergic reaction, like rash, itchi...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Capmatinib Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $205.00 | $11,479.80 / 56 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00078-0709-56 You're viewing this Main listing | 56 TABLET, FILM COATED in 1 BOTTLE | 2020-05-06 | — | Active |
| 00078-0709-94 0078-0709-94 | 56 TABLET, FILM COATED in 1 BOTTLE Sample | 2020-05-06 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00078-0709-94?
What NDC number is used to bill for this package of Tabrecta capmatinib 150 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tabrecta 150 mgthis 00078-0709-56 | Novartis | 56 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12084449 ↗ | Method of use | U-2813 | Nov 19, 2027 |
| US 12084449 ↗ | Method of use | U-2813 | Nov 19, 2027 |
| US 8901123 ↗ | Method of use | U-2813 | May 20, 2029 |
| US 8901123 ↗ | Method of use | U-2813 | May 20, 2029 |
| US 8420645 ↗ | Drug substance | — | Jun 5, 2031 |
| US 10596178 ↗ | Drug product | — | Jul 22, 2035 |
| US 7767675 ↗ | Drug substance | — | Nov 19, 2032 |
| US 8420645 ↗ | Drug substance | — | Jun 5, 2031 |
| US 10596178 ↗ | Drug product | — | Jul 22, 2035 |
| US 8461330 ↗ | Drug substance | — | Nov 19, 2027 |
| US 8461330 ↗ | Drug substance | — | Nov 19, 2027 |
| US 7767675 ↗ | Drug substance | — | Nov 19, 2032 |
| US 12208101 ↗ | Drug product | — | Jul 22, 2035 |
| US 12208101 ↗ | Drug product | — | Jul 22, 2035 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-291 | Orphan Drug Exclusivity (7-year) | May 6, 2027 |
| ODE-291 | Orphan Drug Exclusivity (7-year) | May 6, 2027 |
Is there a generic version of TABRECTA 150 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Capmatinib inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Novartis Pharmaceuticals Corporation labeler code 00078
- Zykadia ceritinib 150 mg Tablet, Film Coated NDC 0078-0694-48
- ENTRESTO Sacubitril and Valsartan 97 mg; 103 mg Tablet, Film Coated NDC 0078-0696-20
- Promacta eltrombopag olamine 25 mg Powder, For Suspension NDC 0078-0697-61
- Rydapt 25 mg Capsule, Liquid Filled NDC 0078-0698-19
- Piqray alpelisib 200 mg Tablet NDC 0078-0701-84
- Piqray alpelisib 150 mg Tablet NDC 0078-0708-02
- Jadenu deferasirox 180 mg Granule NDC 0078-0713-15
- PIQRAY alpelisib Kit NDC 0078-0715-02
- Tabrecta capmatinib 200 mg Tablet, Film Coated NDC 0078-0716-56
- Jadenu deferasirox 360 mg Granule NDC 0078-0720-15
- Jadenu deferasirox 90 mg Granule NDC 0078-0727-15
- Betoptic S betaxolol hydrochloride 2.8 mg/mL Suspension/ Drops NDC 0078-0729-10
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TABRECTA is indicated for the treatment of adult patients with metastatic non-small cell lung cancer (NSCLC) whose tumors have a mutation that leads to mesenchymal-epithelial transition (MET) exon 14 skipping as detected by an FDA-approved test. TABRECTA is a kinase inhibitor indicated for the treatment of adult patients with metastatic non-small cell lung cancer (NSCLC) whose tumors have a mutation that leads to mesenchymal-epithelial transition (MET) exon 14 skipping as detected by an FDA-approved test.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Select patients for treatment with TABRECTA based on presence of a mutation that leads to MET exon 14 skipping. ( 2.1 ) Recommended Dosage : 400 mg orally twice daily with or without food. ( 2.2 )
2.1Patient Selection Select patients for treatment with TABRECTA based on the presence of a mutation that leads to MET exon 14 skipping in tumor or plasma specimens [see Clinical Studies (14)] . If a mutation that leads to MET exon 14 skipping is not detected in a plasma specimen, test tumor tissue if feasible. Information on FDA-approved tests is available at: http://www.fda.gov/CompanionDiagnostics .
2.2Recommended Dosage The recommended dosage of TABRECTA is 400 mg orally twice daily with or without food. Swallow TABRECTA tablets whole. Do not break, crush or chew the tablets. If a patient misses or vomits a dose, instruct the patient not to make up the dose, but to take the next dose at its scheduled time.
2.3Dosage Modifications for Adverse Reactions The recommended dose reductions for the management of adverse reactions are listed in Table 1. Table 1: Recommended TABRECTA Dose Reductions for Adverse Reactions Dose reduction Dose and schedule First 300 mg orally twice daily Second 200 mg orally twice daily Permanently discontinue TABRECTA in patients who are unable to tolerate 200 mg orally twice daily. The recommended dosage modifications of TABRECTA for adverse reactions are provided in Table 2.
Table 2: Recommended TABRECTA Dosage Modifications for Adverse Reactions Abbreviations: ALT, alanine aminotransferase; AST, aspartate aminotransferase; ILD, interstitial lung disease; ULN, upper limit of normal. Grading according to Common Terminology Criteria for Adverse Events (CTCAE) version 5.0. Adverse reaction Severity Dosage modification Interstitial Lung Disease (ILD)/Pneumonitis [see Warnings and Precautions (5.1)] Any grade Permanently discontinue TABRECTA.
Increased ALT and/or AST without increased total bilirubin [see Warnings and Precautions (5.2)] Grade 3 Withhold TABRECTA until recovery to baseline ALT/AST. If recovered to baseline within 7 days, then resume TABRECTA at the same dose; otherwise resume TABRECTA at a reduced dose. Grade 4 Permanently discontinue TABRECTA.
Increased ALT and/or AST with increased total bilirubin in the absence of cholestasis or hemolysis [see Warnings and Precautions (5.2)] ALT and/or AST greater than 3 times ULN with total bilirubin greater than 2 times ULN Permanently discontinue TABRECTA. Increased total bilirubin without concurrent increased ALT and/or AST [see Warnings and Precautions (5.2)] Grade 2 Withhold TABRECTA until recovery to baseline bilirubin. If recovered to baseline within 7 days, then resume TABRECTA at the same dose; otherwise resume TABRECTA at a reduced dose.
Grade 3 Withhold TABRECTA until recovery to baseline bilirubin. If recovered to baseline within 7 days, then resume TABRECTA at a reduced dose; otherwise permanently discontinue TABRECTA. Grade 4 Permanently discontinue TABRECTA.
Increased lipase or amylase [see Warnings and Precautions (5.3)] Grade 3 Withhold TABRECTA until ≤ Grade 2 or baseline. If recovered to baseline or ≤ Grade 2 within 14 days, resume TABRECTA at a reduced dose; otherwise permanently discontinue TABRECTA. Grade 4 Permanently discontinue TABRECTA.
Pancreatitis [see Warnings and Precautions (5.3)] Grade 3 or Grade 4 Permanently discontinue TABRECTA. Hypersensitivity [see Warnings and Precautions (5.4)] All Grades If hypersensitivity is suspected based on clinical judgment, withhold TABRECTA until resolution of the event. Permanently discontinue TABRECTA in patients who develop serious hypersensitivity reactions.
Other adverse reactions [see Adverse Reactions (6.1)] Grade 2 Maintain dose level. If intolerable, consider withholding TABRECTA until resolved, then resume TABRECTA at a reduced dose. Grade 3 Withhold TABRECTA until resolved, then resume TABRECTA at a reduced dose.
Grade 4 Permanently discontinue TABRECTA… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 150 mg: pale orange brown, ovaloid, curved film-coated with beveled edges, unscored, debossed with ‘DU’ on one side and ‘NVR’ on the other side 200 mg: yellow, ovaloid, curved film-coated with beveled edges, unscored, debossed with ‘LO’ on one side and ‘NVR’ on the other side Tablets: 150 mg and 200 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Interstitial Lung Disease (ILD)/Pneumonitis : Monitor for new or worsening pulmonary symptoms indicative of ILD/pneumonitis. Permanently discontinue TABRECTA in patients with ILD/pneumonitis. ( 2.3 , 5.1 ) Hepatotoxicity : Monitor liver function tests.
Withhold, dose reduce, or permanently discontinue TABRECTA based on severity. ( 2.3 , 5.2 ) Pancreatic Toxicity : Monitor amylase and lipase levels. Withhold, dose reduce, or permanently discontinue TABRECTA based on severity.
( 2.3 , 5.3 ) Hypersensitivity Reactions : Withhold or permanently discontinue TABRECTA based on severity. ( 2.3 , 5.4 ) Risk of Photosensitivity : May cause photosensitivity reactions. Advise patients to limit direct ultraviolet exposure.
( 5.5 ) Embryo-Fetal Toxicity : Can cause fetal harm. Advise patients of the potential risk to a fetus and to use effective contraception. ( 5.6 , 8.1 , 8.3 )
5.1Interstitial Lung Disease (ILD)/Pneumonitis ILD/pneumonitis, which can be fatal, occurred in patients treated with TABRECTA [see Adverse Reactions (6.1)] . ILD/pneumonitis occurred in 4.8% of patients treated with TABRECTA in GEOMETRY mono-1, with 1.9% of patients experiencing Grade 3 ILD/pneumonitis and one patient experiencing death (0.3%). Nine patients (2.4%) discontinued TABRECTA due to ILD/pneumonitis.
The median time-to-onset of Grade 3 or higher ILD/pneumonitis was 1.8 months (range: 0.2 months to 1.7 years). Monitor for new or worsening pulmonary symptoms indicative of ILD/pneumonitis (e.g., dyspnea, cough, fever). Immediately withhold TABRECTA in patients with suspected ILD/pneumonitis and permanently discontinue if no other potential causes of ILD/pneumonitis are identified [see Dosage and Administration (2.3)] .
5.2Hepatotoxicity Hepatotoxicity occurred in patients treated with TABRECTA [see Adverse Reactions (6.1)] . Increased alanine aminotransferase (ALT)/aspartate aminotransferase (AST) occurred in 15% of patients treated with TABRECTA in GEOMETRY mono-1. Grade 3 or 4 increased ALT/AST occurred in 7% of patients.
Three patients (0.8%) discontinued TABRECTA due to increased ALT/AST. The median time-to-onset of Grade 3 or higher increased ALT/AST was 1.8 months (range: 0.5 to 46.4 months). Monitor liver function tests (including ALT, AST, and total bilirubin) prior to the start of TABRECTA, every 2 weeks during the first 3 months of treatment, then once a month or as clinically indicated, with more frequent testing in patients who develop increased transaminases or bilirubin.
Based on the severity of the adverse reaction, withhold, dose reduce, or permanently discontinue TABRECTA [see Dosage and Administration (2.3)] .
5.3Pancreatic Toxicity Elevations in amylase and lipase levels occurred in patients treated with TABRECTA [see Adverse Reactions (6.1)] . Increased amylase/lipase occurred in 14% of patients treated with TABRECTA in GEOMETRY mono-1. Grade 3 and 4 increased amylase/lipase occurred in 7% and 1.9% of patients, respectively.
Three patients (0.8%) discontinued TABRECTA due to increased amylase/lipase. The median time-to-onset of Grade 3 or higher increased amylase/lipase was 2 months (range: 0.03 to 31.1 months). Pancreatitis (Grade 3) occurred in one patient (0.3%); TABRECTA was permanently discontinued for this event.
Monitor amylase and lipase at baseline and regularly during treatment with TABRECTA. Based on the severity of the adverse reaction, temporarily withhold, dose reduce, or permanently discontinue TABRECTA [see Dosage and Administration (2.3)] .
5.4Hypersensitivity Reactions Serious hypersensitivity reactions occurred in patients treated with TABRECTA in clinical trials other than GEOMETRY mono-1 [see Adverse Reactions (6.1)] . Signs and symptoms of hypersensitivity included pyrexia, chills, pruritus, rash, decreased blood pressure, nausea and vomiting. Based on the severity of the adverse reaction, temporarily withhold or permanently discontinue TABRECTA [see Dosage and Administration (2.3)] .… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: ILD/Pneumonitis [see Warnings and Precautions (5.1)] Hepatotoxicity [see Warnings and Precautions (5.2)] Pancreatic Toxicity [see Warnings and Precautions (5.3)] Hypersensitivity reactions [see Warnings and Precautions (5.4)] The most common adverse reactions (≥ 20%) are edema, nausea, musculoskeletal pain, fatigue, vomiting, dyspnea, cough, and decreased appetite. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Novartis Pharmaceuticals Corporation at 1-888-669-6682 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Metastatic Non-Small Cell Lung Cancer The safety of TABRECTA was evaluated in GEOMETRY mono-1 [see Clinical Studies (14)] . Patients received TABRECTA 400 mg orally twice daily until disease progression or unacceptable toxicity (N = 373).
Among patients who received TABRECTA, 37% were exposed for at least 6 months and 22% were exposed for at least one year. Serious adverse reactions occurred in 53% of patients who received TABRECTA. Serious adverse reactions in ≥ 2% of patients included dyspnea (7%), pneumonia (7%), pleural effusion (4.3%), musculoskeletal pain (3.8%), general physical health deterioration (2.9%), ILD/pneumonitis (2.7%), edema (2.4%), and vomiting (2.4%).
Fatal adverse reactions occurred in 0.5% of patients who received TABRECTA, including pneumonitis (0.3%) and death, not otherwise specified (0.3%). Permanent discontinuation of TABRECTA due to an adverse reaction occurred in 17% of patients. The most frequent adverse reactions (≥ 1%) leading to permanent discontinuation of TABRECTA were ILD/pneumonitis (2.4%), edema (2.4%), fatigue (1.3%), and pneumonia (1.1%).
Dose interruptions due to an adverse reaction occurred in 57% of patients who received TABRECTA. Adverse reactions requiring dosage interruption in > 2% of patients who received TABRECTA included edema, increased blood creatinine, nausea, increased lipase, vomiting, increased ALT, dyspnea, pneumonia, fatigue, increased amylase, increased AST, musculoskeletal pain, abdominal pain, and increased blood bilirubin. Dose reductions due to an adverse reaction occurred in 26% of patients who received TABRECTA.
Adverse reactions requiring dosage reductions in > 2% of patients who received TABRECTA included edema, increased ALT and increased blood creatinine. The most common adverse reactions (≥ 20%) in patients who received TABRECTA were edema, nausea, musculoskeletal pain, fatigue, vomiting, dyspnea, cough, and decreased appetite. Table 3 summarizes the adverse reactions in GEOMETRY mono-1.
Table 3: Adverse Reactions (≥ 10%) in Patients Who Received TABRECTA in GEOMETRY mono-1 a Edema includes edema peripheral, generalized edema, face edema, edema, localized edema, edema genital, eyelid edema, peripheral swelling, scrotal edema, and penile edema. b Musculoskeletal pain includes arthralgia, back pain, bone pain, musculoskeletal chest pain, musculoskeletal pain, myalgia, neck pain, non-cardiac chest pain, pain in extremity, pain in jaw, spinal pain. c Fatigue includes fatigue and asthenia. d Pyrexia includes pyrexia and body temperature increased. e Cough includes cough, upper airway cough syndrome, and productive cough. f Pneumonia includes pneumonia aspiration, pneumonia, pneumonia influenzal, pneumonia bacterial, lower respiratory tract infection, and lung abscess. g Rash includes rash, dermatitis acneiform, rash maculo-papular, eczema, erythema multiforme, rash macular, dermatitis, rash erythematous, rash pustular, dermatitis bullous, and rash vesicular. h Dizziness includes dizziness, vertigo, and vertigo positional.
Adverse reactions TA… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong and Moderate CYP3A Inducers : Avoid concomitant use. ( 7.1 )
7.1Effect of Other Drugs on TABRECTA Strong CYP3A Inhibitors Coadministration of TABRECTA with a strong CYP3A inhibitor increased capmatinib exposure, which may increase the incidence and severity of adverse reactions of TABRECTA [see Clinical Pharmacology (12.3)] . Closely monitor patients for adverse reactions during coadministration of TABRECTA with strong CYP3A inhibitors. Strong and Moderate CYP3A Inducers Coadministration of TABRECTA with a strong CYP3A inducer decreased capmatinib exposure.
Coadministration of TABRECTA with a moderate CYP3A inducer may also decrease capmatinib exposure. Decreases in capmatinib exposure may decrease TABRECTA anti-tumor activity [see Clinical Pharmacology (12.3)] . Avoid coadministration of TABRECTA with strong and moderate CYP3A inducers.
7.2Effect of TABRECTA on Other Drugs CYP1A2 Substrates Coadministration of TABRECTA increased the exposure of a CYP1A2 substrate, which may increase the adverse reactions of these substrates [see Clinical Pharmacology (12.3)] . If coadministration is unavoidable between TABRECTA and CYP1A2 substrates where minimal concentration changes may lead to serious adverse reactions, decrease the CYP1A2 substrate dosage in accordance with the approved prescribing information. P-glycoprotein (P-gp) and Breast Cancer Resistance Protein (BCRP) Substrates Coadministration of TABRECTA increased the exposure of a P-gp substrate and a BCRP substrate, which may increase the adverse reactions of these substrates [see Clinical Pharmacology (12.3)] .
If coadministration is unavoidable between TABRECTA and P-gp or BCRP substrates where minimal concentration changes may lead to serious adverse reactions, decrease the P-gp or BCRP substrate dosage in accordance with the approved prescribing information. MATE1 and MATE2K Substrates Coadministration of TABRECTA may increase the exposure of MATE1 and MATE2K substrates, which may increase the adverse reactions of these substrates [see Clinical Pharmacology (12.3)] . If coadministration is unavoidable between TABRECTA and MATE1 or MATE2K substrates where minimal concentration changes may lead to serious adverse reactions, decrease the MATE1 or MATE2K substrate dosage in accordance with the approved prescribing information.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1)] , TABRECTA can cause fetal harm when administered to a pregnant woman. There are no available data on TABRECTA use in pregnant women. Oral administration of capmatinib to pregnant rats and rabbits during the period of organogenesis resulted in malformations at maternal exposures less than the human exposure based on AUC at the 400 mg twice daily clinical dose ( see Data ).
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In rats, maternal toxicity (reduced body weight gain and food consumption) occurred at 30 mg/kg/day (approximately 1.4 times the human exposure based on AUC at the 400 mg twice daily clinical dose).
Fetal effects included reduced fetal weights, irregular/incomplete ossification, and increased incidences of fetal malformations (e.g., abnormal flexure/inward malrotation of hindpaws/forepaws, thinness of forelimbs, lack of/reduced flexion at the humerus/ulna joints, and narrowed or small tongue) at doses of ≥ 10 mg/kg/day (approximately 0.6 times the human exposure based on AUC at the 400 mg twice daily clinical dose). In rabbits, no maternal effects were detected at doses up to 60 mg/kg/day (approximately 1.5 times the human exposure based on AUC at the 400 mg twice daily clinical dose).
Fetal effects included small lung lobe at ≥ 5 mg/kg/day (approximately 0.016 times the human exposure based on AUC at the 400 mg twice daily clinical dose), and reduced fetal weights, irregular/incomplete ossification and increased incidences of fetal malformations (e.g., abnormal flexure/malrotation of hindpaws/forepaws, thinness of forelimbs/hindlimbs, lack of/reduced flexion at the humerus/ulna joints, small lung lobes, narrowed or small tongue) at the dose of 60 mg/kg/day.
8.2Lactation Risk Summary There are no data on the presence of capmatinib or its metabolites in either human or animal milk or its effects on the breastfed child or on milk production. Because of the potential for serious adverse reactions in breastfed children, advise women not to breastfeed during treatment with TABRECTA and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential Based on animal data, TABRECTA can cause malformations at doses less than the human exposure based on AUC at the 400 mg twice daily clinical dose [see Use in Specific Populations (8.1)] . Pregnancy Testing Verify pregnancy status for females of reproductive potential prior to starting treatment with TABRECTA. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with TABRECTA and for 1 week after the last dose.
Males Advise males with female partners of reproductive potential to use effective contraception during treatment with TABRECTA and for 1 week after the last dose.
8.4Pediatric Use Safety and effectiveness of TABRECTA in pediatric patients have not been established.
8.5Geriatric Use In GEOMETRY mono-1, 61% of the 373 patients were 65 years or older and 18% were 75 years or older. No overall differences in the safety or effectiveness were observed between these patients and younger patients.
8.6Renal Impairment No dosage adjustment is recommended in patients with mild (baseline creatinine clearance [CLcr] 60 to 89 mL/min by Cockcroft-Gault) or moderate renal impairment (CLcr 30 to 59 mL/min) [see Clinical Pharmacology (12.3)] . TABRECTA has not been studied in patients with severe renal impairment (CLcr 15 to 29 mL/min).
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1)] , TABRECTA can cause fetal harm when administered to a pregnant woman. There are no available data on TABRECTA use in pregnant women. Oral administration of capmatinib to pregnant rats and rabbits during the period of organogenesis resulted in malformations at maternal exposures less than the human exposure based on AUC at the 400 mg twice daily clinical dose ( see Data ).
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In rats, maternal toxicity (reduced body weight gain and food consumption) occurred at 30 mg/kg/day (approximately 1.4 times the human exposure based on AUC at the 400 mg twice daily clinical dose).
Fetal effects included reduced fetal weights, irregular/incomplete ossification, and increased incidences of fetal malformations (e.g., abnormal flexure/inward malrotation of hindpaws/forepaws, thinness of forelimbs, lack of/reduced flexion at the humerus/ulna joints, and narrowed or small tongue) at doses of ≥ 10 mg/kg/day (approximately 0.6 times the human exposure based on AUC at the 400 mg twice daily clinical dose). In rabbits, no maternal effects were detected at doses up to 60 mg/kg/day (approximately 1.5 times the human exposure based on AUC at the 400 mg twice daily clinical dose).
Fetal effects included small lung lobe at ≥ 5 mg/kg/day (approximately 0.016 times the human exposure based on AUC at the 400 mg twice daily clinical dose), and reduced fetal weights, irregular/incomplete ossification and increased incidences of fetal malformations (e.g., abnormal flexure/malrotation of hindpaws/forepaws, thinness of forelimbs/hindlimbs, lack of/reduced flexion at the humerus/ulna joints, small lung lobes, narrowed or small tongue) at the dose of 60 mg/kg/day.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of TABRECTA in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In GEOMETRY mono-1, 61% of the 373 patients were 65 years or older and 18% were 75 years or older. No overall differences in the safety or effectiveness were observed between these patients and younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Capmatinib is a kinase inhibitor that targets MET, including the mutant variant produced by exon 14 skipping. MET exon 14 skipping results in a protein with a missing regulatory domain that reduces its negative regulation leading to increased downstream MET signaling. Capmatinib inhibited cancer cell growth driven by a mutant MET variant lacking exon 14 at clinically achievable concentrations and demonstrated anti-tumor activity in murine tumor xenograft models derived from human lung tumors with either a mutation leading to MET exon 14 skipping or MET amplification.
Capmatinib inhibited the phosphorylation of MET triggered by binding of hepatocyte growth factor or by MET amplification, as well as MET-mediated phosphorylation of downstream signaling proteins and proliferation and survival of MET-dependent cancer cells.
12.2Pharmacodynamics Exposure-Response Capmatinib exposure-response relationships and the time course of pharmacodynamics response are unknown. Cardiac Electrophysiology No large mean increase in QTc (i.e. > 20 ms) was detected following treatment with TABRECTA at the recommended dosage of 400 mg orally twice daily.
12.3Pharmacokinetics Capmatinib exposure (AUC 0-12h and C max ) increased approximately proportionally over a dose range of 200 mg (0.5 times the recommended dosage) to 400 mg. Capmatinib reached steady-state by day 3 following twice daily dosing, with a mean (% coefficient of variation [%CV]) accumulation ratio of 1.5 (41%). Absorption After administration of TABRECTA 400 mg orally in patients with cancer, capmatinib peak plasma concentrations (C max ) were reached in approximately 1 to 2 hours (T max ).
The absorption of capmatinib after oral administration is estimated to be greater than 70%. Effect of Food A high-fat meal (containing approximately 1000 calories and 50% fat) in healthy subjects increased capmatinib AUC 0-INF by 46% with no change in C max compared to under fasted conditions. A low-fat meal (containing approximately 300 calories and 20% fat) in healthy subjects had no clinically meaningful effect on capmatinib exposure.
When capmatinib was administered at 400 mg orally twice daily in cancer patients, exposure (AUC 0-12h ) was similar after administration of capmatinib with food and under fasted conditions. Distribution Capmatinib plasma protein binding is 96%, independent of capmatinib concentration. The apparent mean volume of distribution at steady-state is 164 L.
The blood-to-plasma ratio was 1.5, but decreased at higher concentrations to 0.9. Elimination The effective elimination half-life of capmatinib is 6.5 hours. The mean (%CV) steady-state apparent clearance of capmatinib is 24 L/hr (82%).
Metabolism Capmatinib is primarily metabolized by CYP3A4 and aldehyde oxidase. Excretion Following a single oral administration of radiolabeled-capmatinib to healthy subjects, 78% of the total radioactivity was recovered in feces with 42% as unchanged and 22% was recovered in urine with negligible as unchanged. Specific Populations No clinically significant effects on the pharmacokinetic parameters of capmatinib were identified for the following covariates assessed: age (26 to 90 years), sex, race (White, Asian, Native American, Black, unknown), body weight (35 to 131 kg), mild to moderate renal impairment (baseline CLcr 30 to 89 mL/min by Cockcroft-Gault) and mild, moderate or severe hepatic impairment (Child-Pugh classification).
The effect of severe renal impairment (baseline CLcr 15 to 29 mL/min) on capmatinib pharmacokinetics has not been studied. Drug Interaction Studies Clinical Studies and Model-Informed Approaches Strong CYP3A Inhibitors: Coadministration with itraconazole (a strong CYP3A inhibitor) increased capmatinib AUC 0-INF by 42% with no change in capmatinib C max . Strong CYP3A Inducers: Coadministration with rifampicin (a strong CYP3A inducer) decreased capmatinib AUC 0-INF by 67% and decreased C max by 56%.
Moderate C… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Capmatinib is a kinase inhibitor that targets MET, including the mutant variant produced by exon 14 skipping. MET exon 14 skipping results in a protein with a missing regulatory domain that reduces its negative regulation leading to increased downstream MET signaling. Capmatinib inhibited cancer cell growth driven by a mutant MET variant lacking exon 14 at clinically achievable concentrations and demonstrated anti-tumor activity in murine tumor xenograft models derived from human lung tumors with either a mutation leading to MET exon 14 skipping or MET amplification.
Capmatinib inhibited the phosphorylation of MET triggered by binding of hepatocyte growth factor or by MET amplification, as well as MET-mediated phosphorylation of downstream signaling proteins and proliferation and survival of MET-dependent cancer cells.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied TABRECTA (capmatinib) 150 mg and 200 mg tablets Strength Description Tablets per bottle NDC number 150 mg Pale orange brown, ovaloid, curved film-coated tablet with beveled edges, unscored, debossed with ‘DU’ on one side and ‘NVR’ on the other side. 56 0078-0709-56 200 mg Yellow, ovaloid, curved film-coated tablet with beveled edges, unscored, debossed with ‘LO’ on one side and ‘NVR’ on the other side. 56 0078-0716-56 Storage Dispense in the original package with the desiccant cartridge.
Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature]. Protect from moisture. Discard any unused TABRECTA remaining after 6 weeks of first opening the bottle.
📋 Description ▾
11 DESCRIPTION Capmatinib is a kinase inhibitor. The chemical name is 2-Fluoro- N -methyl-4-[7-(quinolin-6-ylmethyl)imidazo[1,2- b ][1,2,4]triazin-2-yl]benzamide—hydrogen chloride—water (1/2/1). The molecular formula for capmatinib dihydrochloride monohydrate is C 23 H 21 Cl 2 FN 6 O 2 .
The relative molecular mass is 503.36 g/mol for the dihydrochloride monohydrate salt and 412.43 g/mol for the free base. The chemical structure for capmatinib dihydrochloride monohydrate is shown below: Capmatinib dihydrochloride monohydrate is a yellow powder with a pKa 1 of 0.9 (calculated) and pKa 2 of 4.5 (experimentally). Capmatinib dihydrochloride monohydrate is slightly soluble in acidic aqueous solutions at pH 1 and 2 and of further decreasing solubility towards neutral condition.
The log of the distribution coefficient (n-octanol/acetate buffer pH 4.0) is 1.2. TABRECTA is supplied for oral use as ovaloid, curved film-coated tablets with beveled edges, unscored containing 150 mg (pale orange brown color) or 200 mg (yellow color) capmatinib (equivalent to 183.00 mg or 244.00 mg respectively of capmatinib dihydrochloride monohydrate). Each tablet strength contains colloidal silicon dioxide; crospovidone; magnesium stearate; mannitol; microcrystalline cellulose; povidone; and sodium lauryl sulfate as inactive ingredients.
The 150 mg tablet coating contains ferric oxide, red; ferric oxide, yellow; ferrosoferric oxide; hypromellose; polyethylene glycol (PEG) 4000; talc; and titanium dioxide. The 200 mg tablet coating contains ferric oxide, yellow; hypromellose; polyethylene glycol (PEG) 4000; talc; and titanium dioxide. capmatinib dihydrochloride monohydrate structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Interstitial Lung Disease (ILD)/Pneumonitis Inform patients of the risks of severe or fatal ILD/pneumonitis. Advise patients to immediately contact their healthcare provider for new or worsening respiratory symptoms [see Warnings and Precautions (5.1)] .
Hepatotoxicity Inform patients that they will need to undergo lab tests to monitor liver function. Advise patients to immediately contact their healthcare provider for signs and symptoms of liver dysfunction [see Warnings and Precautions (5.2)] . Pancreatic Toxicity Inform patients that they will need to undergo lab tests to monitor pancreatic function.
Advise patients to immediately contact their healthcare provider for signs and symptoms of pancreatitis [see Warnings and Precautions (5.3)] . Hypersensitivity Reactions Inform patients that there is a risk of hypersensitivity reactions with TABRECTA. Advise patients to stop taking TABRECTA and immediately contact their healthcare provider for signs and symptoms of hypersensitivity [see Warnings and Precautions (5.4)] .
Risk of Photosensitivity Inform patients that there is a potential risk of photosensitivity reactions with TABRECTA. Advise patients to limit direct ultraviolet exposure by using sunscreen or protective clothing during treatment with TABRECTA [see Warnings and Precautions (5.5)] . Embryo-Fetal Toxicity Advise pregnant women of the potential risk to a fetus.
Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.6), Use in Specific Populations (8.1)] . Advise females of reproductive potential to use effective contraception during treatment with TABRECTA and for 1 week after the last dose [see Use in Specific Populations (8.3)] . Advise males with female partners of reproductive potential to use effective contraception during treatment with TABRECTA and for 1 week after the last dose [see Use in Specific Populations (8.3)] .
Drug Interactions Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products [see Drug Interactions (7)] . Lactation Advise women not to breastfeed during treatment with TABRECTA and for 1 week after the last dose [see Use in Specific Populations (8.2)] . Distributed by: Novartis Pharmaceuticals Corporation East Hanover, New Jersey 07936 © Novartis T2024-19
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Capmatinib exposure (AUC 0-12h and C max ) increased approximately proportionally over a dose range of 200 mg (0.5 times the recommended dosage) to 400 mg. Capmatinib reached steady-state by day 3 following twice daily dosing, with a mean (% coefficient of variation [%CV]) accumulation ratio of 1.5 (41%). Absorption After administration of TABRECTA 400 mg orally in patients with cancer, capmatinib peak plasma concentrations (C max ) were reached in approximately 1 to 2 hours (T max ).
The absorption of capmatinib after oral administration is estimated to be greater than 70%. Effect of Food A high-fat meal (containing approximately 1000 calories and 50% fat) in healthy subjects increased capmatinib AUC 0-INF by 46% with no change in C max compared to under fasted conditions. A low-fat meal (containing approximately 300 calories and 20% fat) in healthy subjects had no clinically meaningful effect on capmatinib exposure.
When capmatinib was administered at 400 mg orally twice daily in cancer patients, exposure (AUC 0-12h ) was similar after administration of capmatinib with food and under fasted conditions. Distribution Capmatinib plasma protein binding is 96%, independent of capmatinib concentration. The apparent mean volume of distribution at steady-state is 164 L.
The blood-to-plasma ratio was 1.5, but decreased at higher concentrations to 0.9. Elimination The effective elimination half-life of capmatinib is 6.5 hours. The mean (%CV) steady-state apparent clearance of capmatinib is 24 L/hr (82%).
Metabolism Capmatinib is primarily metabolized by CYP3A4 and aldehyde oxidase. Excretion Following a single oral administration of radiolabeled-capmatinib to healthy subjects, 78% of the total radioactivity was recovered in feces with 42% as unchanged and 22% was recovered in urine with negligible as unchanged. Specific Populations No clinically significant effects on the pharmacokinetic parameters of capmatinib were identified for the following covariates assessed: age (26 to 90 years), sex, race (White, Asian, Native American, Black, unknown), body weight (35 to 131 kg), mild to moderate renal impairment (baseline CLcr 30 to 89 mL/min by Cockcroft-Gault) and mild, moderate or severe hepatic impairment (Child-Pugh classification).
The effect of severe renal impairment (baseline CLcr 15 to 29 mL/min) on capmatinib pharmacokinetics has not been studied. Drug Interaction Studies Clinical Studies and Model-Informed Approaches Strong CYP3A Inhibitors: Coadministration with itraconazole (a strong CYP3A inhibitor) increased capmatinib AUC 0-INF by 42% with no change in capmatinib C max . Strong CYP3A Inducers: Coadministration with rifampicin (a strong CYP3A inducer) decreased capmatinib AUC 0-INF by 67% and decreased C max by 56%.
Moderate CYP3A Inducers: Coadministration with efavirenz (a moderate CYP3A inducer) was predicted to decrease capmatinib AUC 0-12h by 44% and decrease C max by 34%. Proton Pump Inhibitors: Coadministration with rabeprazole (a proton pump inhibitor) decreased capmatinib AUC 0-INF by 25% and decreased C max by 38%. Substrates of CYP Enzymes: Coadministration of capmatinib increased caffeine (a CYP1A2 substrate) AUC 0-INF by 134% with no change in its C max .
Coadministration of capmatinib had no clinically meaningful effect on exposure of midazolam (a CYP3A substrate). P-gp Substrates: Coadministration of capmatinib increased digoxin (a P-gp substrate) AUC 0-INF by 47% and increased C max by 74%. BCRP Substrates: Coadministration of capmatinib increased rosuvastatin (a BCRP substrate) AUC 0-INF by 108% and increased C max by 204%.
In Vitro Studies Transporter Systems: Capmatinib is a substrate of P-gp, but not a substrate of BCRP or MRP2. Capmatinib reversibly inhibits MATE1 and MATE2K, but does not inhibit OATP1B1, OATP1B3, OCT1, OAT1, OAT3, or MRP2.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Exposure-Response Capmatinib exposure-response relationships and the time course of pharmacodynamics response are unknown. Cardiac Electrophysiology No large mean increase in QTc (i.e. > 20 ms) was detected following treatment with TABRECTA at the recommended dosage of 400 mg orally twice daily.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Metastatic NSCLC with a Mutation that Leads to MET Exon 14 Skipping The efficacy of TABRECTA was evaluated in GEOMETRY mono-1, a multicenter, non-randomized, open-label, multi-cohort study (NCT02414139). Eligible patients were required to have NSCLC with a mutation that leads to MET exon 14 skipping, epidermal growth factor receptor (EGFR) wild-type and anaplastic lymphoma kinase (ALK) negative status, and at least one measurable lesion as defined by Response Evaluation Criteria in Solid Tumors (RECIST) version 1.1.
Patients with symptomatic CNS metastases, clinically significant uncontrolled cardiac disease, or who received treatment with any MET or hepatocyte growth factor (HGF) inhibitor were not eligible for the study. Out of the first 97 patients enrolled in GEOMETRY mono-1 following the central confirmation of MET exon 14 skipping by a RNA-based clinical trial assay, 78 patient samples were retested with the FDA-approved FoundationOne ® CDx (22 treatment-naïve and 56 previously treated patients) to detect mutations that lead to MET exon 14 skipping.
Out of 78 samples retested with FoundationOne ® CDx, 73 samples were evaluable (20 treatment-naïve and 53 previously treated patients), 72 (20 treatment-naïve and 52 previously treated patients) of which were confirmed to have a mutation that leads to MET exon 14 skipping, demonstrating an estimated positive percentage agreement of 99% (72/73) between the clinical trial assay and the FDA-approved assay. Patients received TABRECTA 400 mg orally twice daily until disease progression or unacceptable toxicity. The major efficacy outcome measure was overall response rate (ORR) as determined by a Blinded Independent Review Committee (BIRC) according to RECIST 1.1.
An additional efficacy outcome measure was duration of response (DOR) by BIRC. The efficacy population included 60 treatment-naïve patients and 100 previously treated patients. The median age was 71 years (range: 48 to 90 years); 61% female; 77% White; 25% had Eastern Cooperative Oncology Group (ECOG) Performance Status (PS) 0 and 74% had ECOG PS 1; 61% never smoked; 83% had adenocarcinoma; and 16% had CNS metastases.
Among previously treated patients, 81% received one, 16% received two and 3% received three prior lines of systemic therapy. Amongst previously treated patients, 86% received prior platinum-based chemotherapy. Efficacy results are presented in Table 5.
Table 5: Efficacy Results for Treatment-Naïve and Previously Treated Patients in GEOMETRY mono-1 Abbreviations: CI, confidence interval; NE, not estimable. a Blinded Independent Review Committee (BIRC) review. b Confirmed response. c Clopper and Pearson exact binomial 95% CI. d Based on Kaplan-Meier estimate. Efficacy parameters Treatment-naïve N = 60 Previously treated N = 100 Overall response rate a,b (95% CI) c 68% (55, 80) 44% (34, 54) Complete response 5% 0 Partial response 63% 44% Duration of response (DOR) a Median (months) (95% CI) d 16.6 (8.4, 22.1) 9.7 (5.6, 13.0) Patients % with DOR ≥ 12 months 49% 36%
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies were not conducted with capmatinib. Capmatinib was not mutagenic in an in vitro bacterial reverse mutation assay and did not cause chromosomal aberrations in an in vitro chromosome aberration assay in human peripheral blood lymphocytes. Capmatinib was not clastogenic in an in vivo bone marrow micronucleus test in rats.
Dedicated fertility studies were not conducted with capmatinib. No effects on male and female reproductive organs occurred in general toxicology studies conducted in rats and monkeys at doses resulting in exposures of up to approximately 3.6 times the human exposure based on AUC at the 400 mg twice daily clinical dose.
13.2Animal Toxicology and/or Pharmacology In rats, capmatinib administration resulted in vacuolation of white matter of the brain in both 4- and 13-week studies at doses ≥ 2.2 times the human exposure (AUC) at the 400 mg twice daily clinical dose. In some cases, the brain lesions were associated with early death and/or convulsions or tremors. Concentrations of capmatinib in the brain tissue of rats was approximately 9% of the corresponding concentrations in plasma.
In vitro and in vivo assays demonstrated that capmatinib has some potential for photosensitization; however, the no-observed-adverse-effect level for in vivo photosensitization was 30 mg/kg/day (C max of 14000 ng/mL), about 2.9 times the human C max at the 400 mg twice daily clinical dose.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies were not conducted with capmatinib. Capmatinib was not mutagenic in an in vitro bacterial reverse mutation assay and did not cause chromosomal aberrations in an in vitro chromosome aberration assay in human peripheral blood lymphocytes. Capmatinib was not clastogenic in an in vivo bone marrow micronucleus test in rats.
Dedicated fertility studies were not conducted with capmatinib. No effects on male and female reproductive organs occurred in general toxicology studies conducted in rats and monkeys at doses resulting in exposures of up to approximately 3.6 times the human exposure based on AUC at the 400 mg twice daily clinical dose.
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: March 2025 PATIENT INFORMATION TABRECTA ® (ta brek tah) (capmatinib) tablets What is TABRECTA?
TABRECTA is a prescription medicine used to treat adults with a kind of lung cancer called non-small cell lung cancer (NSCLC) that: has spread to other parts of the body (metastatic), and whose tumors have an abnormal mesenchymal epithelial transition (MET) gene. Your healthcare provider will perform a test to make sure that TABRECTA is right for you. It is not known if TABRECTA is safe and effective in children.
Before taking TABRECTA, tell your healthcare provider about all of your medical conditions, including if you: have or have had lung or breathing problems other than your lung cancer have or have had liver problems have or have had pancreatic problems are pregnant or plan to become pregnant. TABRECTA can harm your unborn baby. Females who are able to become pregnant: Your healthcare provider should do a pregnancy test before you start your treatment with TABRECTA.
You should use effective birth control during treatment and for 1 week after your last dose of TABRECTA. Talk to your healthcare provider about birth control choices that might be right for you during this time. Tell your healthcare provider right away if you become pregnant or think you may be pregnant during treatment with TABRECTA.
Males who have female partners who can become pregnant: You should use effective birth control during treatment and for 1 week after your last dose of TABRECTA. are breastfeeding or plan to breastfeed. It is not known if TABRECTA passes into your breast milk. Do not breastfeed during treatment and for 1 week after your last dose of TABRECTA.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. How should I take TABRECTA? Take TABRECTA exactly as your healthcare provider tells you.
Take TABRECTA 2 times a day with or without food. Swallow TABRECTA tablets whole. Do not break, crush, or chew TABRECTA tablets.
Do not change your dose or stop taking TABRECTA unless your healthcare provider tells you to. If you miss or vomit a dose of TABRECTA, do not make up the dose. Take your next dose at your regular scheduled time.
What should I avoid while taking TABRECTA? Your skin may be sensitive to the sun (photosensitivity) during treatment with TABRECTA. Use sunscreen or wear clothes that cover your skin during your treatment with TABRECTA to limit direct sunlight exposure.
What are the possible side effects of TABRECTA? TABRECTA may cause serious side effects, including: Lung or breathing problems. TABRECTA may cause inflammation of the lungs that can cause death.
Tell your healthcare provider right away if you develop any new or worsening symptoms, including: ◦ cough ◦ fever ◦ trouble breathing or shortness of breath Liver problems. TABRECTA may cause abnormal liver blood test results. Your healthcare provider will do blood tests to check your liver function before you start treatment and during treatment with TABRECTA.
Tell your healthcare provider right away if you develop any signs and symptoms of liver problems, including: ◦ your skin or the white part of your eyes turns yellow (jaundice) ◦ dark or “tea-colored” urine ◦ light-colored stools (bowel movements) ◦ confusion ◦ tiredness ◦ loss of appetite for several days or longer ◦ nausea and vomiting ◦ pain, aching, or tenderness on the right side of your stomach-area (abdomen) ◦ weakness ◦ swelling in your stomach-area Pancreas problems . TABRECTA may cause increases in your blood amylase and/or lipase levels that may indicate a problem with your pancreas.
Your healthcare provider will do blood tests to check your pancreatic function before you start treatment and during treatment with TABRECTA. Tell your healthcare provider right away if you develop any signs and symptoms of pancreas problems, inclu… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0078-0709-56 TABRECTA ® (capmatinib) tablets 150 mg * Attention: Dispense and store Tabrecta in original container with the desiccant to protect from moisture. Rx only 56 Film-coated tablets NOVARTIS PRINCIPAL DISPLAY PANEL NDC 0078-0709-56 TABRECTA® (capmatinib) tablets 150 mg* Attention: Dispense and store Tabrecta in original container with the desiccant to protect from moisture. Rx only 56 Film-coated tablets NOVARTIS
PRINCIPAL DISPLAY PANEL NDC 0078-0716-56 TABRECTA ® (capmatinib) tablets 200 mg * Attention: Dispense and store Tabrecta in original container with the desiccant to protect from moisture. Rx only 56 Film-coated tablets NOVARTIS PRINCIPAL DISPLAY PANEL NDC 0078-0716-56 TABRECTA® (capmatinib) tablets 200 mg* Attention: Dispense and store Tabrecta in original container with the desiccant to protect from moisture. Rx only 56 Film-coated tablets NOVARTIS
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |