
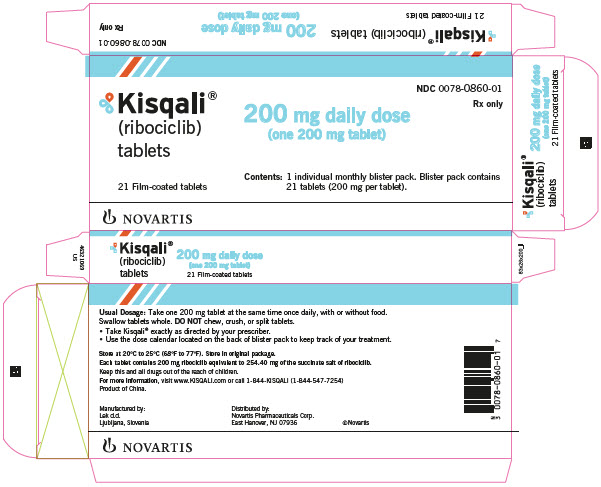
KISQALI ribociclib 200 mg Tablet, Film Coated, 21-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ribociclib is used in combination with another medication to treat a certain type of hormone receptor–positive (depends on hormones such as estrogen to grow) advanced breast cancer that has spread to other parts of the body or has not improved or has worsened after treatment with other therapies. Ribociclib is also used in combination with another medication to treat a certain type of hormone receptor–positive, early breast cancer in people who have already been treated with surgery, radiation, and/or chemotherapy. Ribociclib is in a class of medications called kinase inhibitors. It works by b...
Read the full MedlinePlus article ↗- Kisqali works by blocking proteins your cancer cells rely on to keep dividing. Think of it as throwing a wrench into the cancer's copy machine. It's always given alongside a hormon...
- What exactly is Kisqali supposed to do for my breast cancer?
- The most common things people notice are fatigue, nausea, headaches, and a drop in blood cell counts that your doctor will track with regular blood tests. Hair thinning or loss hap...
- I'm worried about side effects — what should I actually expect day to day?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ribociclib Succinate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 1DI56QDM62
A natural fatty substance from soybeans that helps mix oil and water-based ingredients together. It acts as an emulsifier and lubricant in medicines to improve texture and help the product break down properly in your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $358.76 | $7,533.97 / 21 tablets |
| Medicare drug plans payPart D · Q2 2026 | $348.49 | $7,318.32 / 21 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Kisqali 200 mg 00078-0874-63 | Novartis | 21 tablets | $289.717 | — | Availability likely | — |
| Kisqali 200 mg 00078-0867-42 | Novartis | 14 tablets | $346.947 | — | Availability likely | — |
| Kisqali 200 mgthis 00078-0860-01 | Novartis | 21 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8962630 ↗ | Method of use | U-1981 | Dec 9, 2029 |
| US 8962630 ↗ | Method of use | U-2356 | Dec 9, 2029 |
| US 8962630 ↗ | Method of use | U-2355 | Dec 9, 2029 |
| US 9868739 ↗ | Method of use | U-2355 | Nov 9, 2031 |
| US 9868739 ↗ | Method of use | U-2356 | Nov 9, 2031 |
| US 9416136 ↗ | Method of use | U-2355 | Aug 20, 2029 |
| US 9416136 ↗ | Method of use | U-2356 | Aug 20, 2029 |
| US 9416136 ↗ | Method of use | U-1981 | Aug 20, 2029 |
| US 9868739 ↗ | Method of use | U-3999 | Nov 9, 2031 |
| US 9416136 ↗ | Method of use | U-3999 | Aug 20, 2029 |
| US 8962630 ↗ | Method of use | U-3999 | Dec 9, 2029 |
| US 12544379 ↗ | Method of use | U-3975 | Aug 7, 2034 |
| US 12544380 ↗ | Method of use | U-4404 | Aug 7, 2034 |
| US 12544380 ↗ | Method of use | U-4405 | Aug 7, 2034 |
| US 9868739 ↗ | Method of use | U-1981 | Nov 9, 2031 |
| US 9868739 ↗ | Method of use | U-3975 | Nov 9, 2031 |
| US 9416136 ↗ | Method of use | U-3266 | Aug 20, 2029 |
| US 9416136 ↗ | Method of use | U-3265 | Aug 20, 2029 |
| US 8962630 ↗ | Method of use | U-3265 | Dec 9, 2029 |
| US 8962630 ↗ | Method of use | U-3266 | Dec 9, 2029 |
| US 9868739 ↗ | Method of use | U-3265 | Nov 9, 2031 |
| US 9868739 ↗ | Method of use | U-3266 | Nov 9, 2031 |
| US 9416136 ↗ | Method of use | U-3975 | Aug 20, 2029 |
| US 8962630 ↗ | Method of use | U-3975 | Dec 9, 2029 |
| US 9193732 ↗ | Drug substance | — | Nov 9, 2031 |
| US 12064434 ↗ | Drug product | — | Apr 14, 2036 |
| US 12419894 ↗ | Drug product | — | Apr 14, 2036 |
| US 8415355 ↗ | Drug substance | — | Mar 13, 2031 |
| US 8685980 ↗ | Drug substance | — | May 25, 2030 |
| US 10799506 ↗ | Drug product | — | Apr 14, 2036 |
| US 8324225 ↗ | Drug substance | — | Jun 17, 2028 |
| US 8685980*PED ↗ | Drug product | — | Nov 25, 2030 |
| US 8415355*PED ↗ | Drug product | — | Sep 13, 2031 |
| US 8324225*PED ↗ | Drug product | — | Dec 17, 2028 |
| US 8962630*PED ↗ | Drug product | — | Jun 9, 2030 |
| US 9193732*PED ↗ | Drug product | — | May 9, 2032 |
| US 9416136*PED ↗ | Drug product | — | Feb 20, 2030 |
| US 9868739*PED ↗ | Drug product | — | May 9, 2032 |
| US 10799506*PED ↗ | Drug product | — | Oct 14, 2036 |
| US 12064434*PED ↗ | Drug product | — | Oct 14, 2036 |
| US 12419894*PED ↗ | Drug product | — | Oct 14, 2036 |
| US 12544379*PED ↗ | Drug product | — | Feb 7, 2035 |
| US 12544380*PED ↗ | Drug product | — | Feb 7, 2035 |
| Code | What it grants | Expires |
|---|---|---|
| I-950 | New indication (3-year) | Sep 17, 2027 |
| PED | Pediatric Exclusivity (+6 months) | Mar 17, 2028 |
Is there a generic version of KISQALI 200 MG DAILY DOSE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00078-0860-01 You're viewing this | 1 BLISTER PACK in 1 CARTON (0078-0860-01) / 21 TABLET, FILM COATED in 1 BLISTER PACK | 2017-03-13 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE KISQALI is a kinase inhibitor indicated: in combination with an aromatase inhibitor for the adjuvant treatment of adults with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative stage II and III early breast cancer at high risk of recurrence. ( 1 ) for the treatment of adults with HR-positive, HER2-negative advanced or metastatic breast cancer in combination with: an aromatase inhibitor as initial endocrine-based therapy; or fulvestrant as initial endocrine-based therapy or following disease progression on endocrine therapy.
( 1 )
1.1Early Breast Cancer KISQALI is indicated in combination with an aromatase inhibitor for the adjuvant treatment of adults with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative stage II and III early breast cancer at high risk of recurrence.
1.2Advanced or Metastatic Breast Cancer KISQALI is indicated for the treatment of adults with HR-positive, HER2-negative advanced or metastatic breast cancer in combination with: an aromatase inhibitor as initial endocrine-based therapy; or fulvestrant as initial endocrine-based therapy or following disease progression on endocrine therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION KISQALI tablets are taken orally with or without food in combination with an aromatase inhibitor or fulvestrant. ( 2 ) Early Breast Cancer Recommended starting dose: 400 mg orally (two 200 mg tablets) taken once daily with or without food for 21 consecutive days followed by 7 days off treatment. ( 2.1 ) Advanced or Metastatic Breast Cancer Recommended starting dose: 600 mg orally (three 200 mg tablets) taken once daily with or without food for 21 consecutive days followed by 7 days off treatment.
( 2.1 ) Dose interruption, reduction, and/or discontinuation may be required based on individual safety and tolerability. ( 2.2 )
2.1Recommended Dosage Important Administration Instructions KISQALI can be taken with or without food [see Clinical Pharmacology (12.3)] . Pre/perimenopausal women, or men, treated with the combination KISQALI plus an aromatase inhibitor or fulvestrant, should be treated with a luteinizing hormone-releasing hormone (LHRH) agonist according to current clinical practice standards. Patients should take their dose of KISQALI at approximately the same time each day, preferably in the morning.
If the patient vomits after taking the dose, or misses a dose, no additional dose should be taken that day. The next prescribed dose should be taken at the usual time. KISQALI tablets should be swallowed whole (tablets should not be chewed, crushed or split prior to swallowing).
No tablet should be ingested if it is broken, cracked, or otherwise not intact. Early Breast Cancer The recommended dosage of KISQALI is 400 mg (two 200 mg film-coated tablets) taken orally, once daily for 21 consecutive days followed by 7 days off in 28-day treatment cycles. KISQALI should be given in combination with an aromatase inhibitor.
Refer to the Full Prescribing Information for the recommended dosage of the aromatase inhibitor. In patients with early breast cancer, treatment with KISQALI should continue for 3 years or until disease recurrence or unacceptable toxicity occurs. Advanced or Metastatic Breast Cancer The recommended dosage of KISQALI is 600 mg (three 200 mg film-coated tablets) taken orally, once daily for 21 consecutive days followed by 7 days off in 28-day treatment cycles.
KISQALI should be given in combination with endocrine therapy (fulvestrant or an aromatase inhibitor). Refer to the Full Prescribing Information for the recommended dose of endocrine therapy.
2.2Dose Modifications Dose Modifications for Adverse Reactions The recommended dose modifications for adverse reactions are listed in Table 1. Table 1: Recommended Dose Modification for Adverse Reactions Level KISQALI Dose Number of tablets Early breast cancer Starting dose 400 mg/day two 200 mg tablets Dose reduction 200 mg/day * one 200 mg tablet Advanced or metastatic breast cancer Starting dose 600 mg/day three 200 mg tablets First dose reduction 400 mg/day two 200 mg tablets Second dose reduction 200 mg/day * one 200 mg tablet *If dose reduction below 200 mg/day is required, discontinue KISQALI.
Tables 2, 3, 4, 5, 6, and 7 summarize recommendations for dose interruption, reduction, or discontinuation of KISQALI in the management of specific adverse reactions. Dose modification of KISQALI is recommended based on individual patient safety and tolerability. Table 2: Dose Modification and Management for Interstitial Lung Disease/Pneumonitis Grade 1 (asymptomatic) Grade 2 (symptomatic) Grade 3 (severe symptomatic) or 4 (life-threatening) ILD/Pneumonitis [see Warnings and Precautions (5.1)] No dose interruption or adjustment is required.
Initiate appropriate medical therapy and monitor as clinically indicated. Dose interruption until recovery to Grade ≤ 1 then consider resuming KISQALI at the next lower dose level*. If Grade 2 recurs, discontinue KISQALI.
Discontinue KISQALI. Abbreviation: ILD, interstitial lung disease. Grading according to Common Terminology Criteria for Adverse Events (CTCAE) version 4.03. *An individualized benefit-risk…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablet: 200 mg ribociclib (equivalent to 254.40 mg ribociclib succinate). Film coated, light greyish violet, round, curved with beveled edges, debossed with “RIC” on one side and “NVR” on the other side. Tablets: 200 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Interstitial Lung Disease (ILD)/Pneumonitis: Severe, life threatening, or fatal ILD/pneumonitis can occur with KISQALI treatment. Monitor for pulmonary symptoms indicative of ILD/pneumonitis. Interrupt and evaluate patients with new or worsening respiratory symptoms suspected to be due to ILD/pneumonitis.
Permanently discontinue KISQALI in patients with recurrent symptomatic or severe ILD/pneumonitis. ( 2.2 , 5.1 ) Severe Cutaneous Adverse Reactions (SCARs): SCARs including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug-reaction with eosinophilia and systemic symptoms (DRESS) can occur with KISQALI treatment. Permanently discontinue KISQALI in patients with SCARs or other life-threatening cutaneous reactions.
( 2.2 , 5.2 ) QT Interval Prolongation: KISQALI has been shown to prolong the QT interval in a concentration-dependent manner. Monitor electrocardiograms (ECGs) and electrolytes prior to initiation of treatment with KISQALI. Repeat ECGs at approximately Day 14 of the first cycle, and as clinically indicated.
Monitor electrolytes at the beginning of each cycle for 6 cycles, and as clinically indicated. Avoid using KISQALI with drugs known to prolong QT interval and/or strong CYP3A inhibitors. ( 2.2 , 5.3 , 7.1 , 7.4 ) Increased QT Prolongation with Concomitant Use of Tamoxifen: KISQALI is not indicated for concomitant use with tamoxifen.
( 5.4 ) Hepatotoxicity: Increases in serum transaminase and bilirubin levels have been observed. Perform liver function tests (LFTs) before initiating treatment with KISQALI. Monitor LFTs every 2 weeks for the first 2 cycles, at the beginning of each subsequent 4 cycles, and as clinically indicated.
( 2.2 , 5.5 ) Neutropenia: Perform complete blood count (CBC) before initiating therapy with KISQALI. Monitor CBC every 2 weeks for the first 2 cycles, at the beginning of each subsequent 4 cycles, and as clinically indicated. ( 2.2 , 5.6 ) Embryo-Fetal Toxicity: Can cause fetal harm.
Advise females of reproductive potential of potential risk to a fetus and to use effective contraception during therapy. ( 5.7 , 8.1 , 8.3 )
5.1Interstitial Lung Disease/Pneumonitis Severe, life-threatening, or fatal interstitial lung disease (ILD) and/or pneumonitis can occur in patients treated with KISQALI and other CDK 4/6 inhibitors. In patients with early breast cancer (NATALEE) who received 400 mg KISQALI plus a non-steroidal aromatase inhibitor (NSAI), 1.5% of patients had ILD/pneumonitis (Grade 1-2). In patients with advanced or metastatic breast cancer (MONALEESA-2, MONALEESA-3, MONALEESA-7), 1.6% of patients had ILD/pneumonitis (any Grade, 0.4% had Grade 3-4, and 0.1% had a fatal outcome).
Additional cases of ILD/pneumonitis have occurred in the postmarketing setting, some resulting in death [see Adverse Reactions (6.2)] . Monitor patients for pulmonary symptoms indicative of ILD/pneumonitis which may include hypoxia, cough, and dyspnea. In patients who have new or worsening respiratory symptoms suspected to be due to ILD or pneumonitis, interrupt KISQALI immediately and evaluate the patient.
Permanently discontinue KISQALI in patients with severe ILD/pneumonitis or any recurrent symptomatic ILD/pneumonitis [see Dosage and Administration (2.2)] .
5.2Severe Cutaneous Adverse Reactions Severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug-induced hypersensitivity syndrome (DiHS)/drug reaction with eosinophilia and systemic symptoms (DRESS) can occur in patients treated with KISQALI [see Adverse Reactions (6.2)] . If signs or symptoms of severe cutaneous reactions occur, interrupt KISQALI until the etiology of the reaction has been determined [see Dosage and Administration (2.2)] . Early consultation with a dermatologist is recommended to ensure greater diagnostic accuracy and appropriate management.
If SJS, TEN, or DiHS/DRESS is confirmed, permanently discontinue KISQALI. Do…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Interstitial Lung Disease/Pneumonitis [see Warnings and Precautions (5.1)] Severe Cutaneous Adverse Reactions [see Warnings and Precautions (5.2)] QT Interval Prolongation [see Warnings and Precautions (5.3, 5.4)] Hepatotoxicity [see Warnings and Precautions (5.5)] Neutropenia [see Warnings and Precautions (5.6)] In patients with early breast cancer, the most common (incidence ≥ 20%) adverse reactions, including laboratory abnormalities, are lymphocytes decreased, leukocytes decreased, neutrophils decreased, hemoglobin decreased, alanine aminotransferase increased, aspartate aminotransferase increased, infections, creatinine increased, platelets decreased, headache, nausea, and fatigue.
( 6 ) In patients with advanced or metastatic breast cancer, the most common (incidence ≥ 20%) adverse reactions, including laboratory abnormalities, are leukocytes decreased, neutrophils decreased, hemoglobin decreased, lymphocytes decreased, aspartate aminotransferase increased, gamma glutamyl transferase increased, alanine aminotransferase increased, infections, nausea, creatinine increased, fatigue, platelets decreased, diarrhea, vomiting, headache, constipation, alopecia, cough, rash, back pain, and glucose serum decreased.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Novartis Pharmaceuticals Corporation at 1-888-669-6682 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described in WARNINGS AND PRECAUTIONS reflect exposure to KISQALI plus non-steroidal aromatase inhibitor (NSAI) in 2526 patients with early breast cancer (NATALEE), of whom 51% completed 36 months of KISQALI treatment.
The most common (≥ 20%) adverse reactions, including laboratory abnormalities, were lymphocytes decreased (97%), leukocytes decreased (95%), neutrophils decreased (94%), hemoglobin decreased (47%), alanine aminotransferase increased (45%), aspartate aminotransferase increased (44%), infections (37%), creatinine increased (33%), platelets decreased (28%), headache (23%), nausea (23%), and fatigue (22%). In addition, the pooled safety population described in the WARNINGS AND PRECAUTIONS reflects exposure to KISQALI in 1065 patients with advanced or metastatic breast cancer (MONALEESA-2, MONALEESA-3, MONALEESA-7), of whom 76% were exposed for 6 months or longer, and 62% were exposed for greater than one year.
The most common (≥ 20%) adverse reactions, including laboratory abnormalities, were leukocytes decreased (95%), neutrophils decreased (93%), hemoglobin decreased (68%), lymphocytes decreased (66%), aspartate aminotransferase increased (55%), gamma-glutamyl transferase increased (53%), alanine aminotransferase increased (52%), infections (47%), nausea (47%), creatinine increased (42%), fatigue (35%), platelets decreased (34%), diarrhea (33%), vomiting (29%), headache (27%), constipation (25%), alopecia (25%), cough (24%), rash (24%), back pain (24%), and glucose serum decreased (20%).
NATALEE: KISQALI in Combination with a Non-steroidal Aromatase Inhibitor as Adjuvant Treatment Adults with HR-positive, HER2-negative Stage II and III Early Breast Cancer at High Risk of Recurrence The safety of KISQALI was evaluated in NATALEE, a clinical trial of 5101 patients who received KISQALI plus NSAI or NSAI alone, with or without goserelin [see Clinical Studies (14)] . The median duration of exposure to KISQALI was 33 months. Serious adverse reactions occurred in 14% of patients who received KISQALI.
Serious adverse reactions in > 0.5% of patients who received KISQALI included COVID-19 (1.1%), pneumonia (0.8%), and pulmonary embolism (0.6%). Fa…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A Inhibitors: Avoid concomitant use of KISQALI with strong CYP3A inhibitors. If strong inhibitors cannot be avoided, reduce KISQALI dose. ( 2.2 , 7.1 ) CYP3A4 Inducers: Avoid concomitant use of KISQALI with strong CYP3A inducers.
( 7.2 ) CYP3A Substrates: The dose of CYP3A substrates may need to be reduced when given concurrently with KISQALI. ( 7.3 ) Drugs Known to Prolong QT Interval: Avoid concomitant use of drugs known to prolong QT interval, such as anti-arrhythmic medicines. ( 7.4 )
7.1Drugs That May Increase Ribociclib Plasma Concentrations CYP3A4 Inhibitors Coadministration of strong CYP3A inhibitors increases ribociclib exposure [see Clinical Pharmacology (12.3)] . Increased ribociclib concentrations may increase the incidence and severity of adverse reactions, including QTcF prolongation [see Warnings and Precautions (5.3)] . Avoid concomitant use of strong CYP3A inhibitors with KISQALI and consider alternative concomitant medications with less potential for CYP3A inhibition.
In patients with early breast cancer, if coadministration of KISQALI with a strong CYP3A inhibitor cannot be avoided, reduce the dose of KISQALI to 200 mg once daily. In patients with advanced or metastatic breast cancer, if coadministration of KISQALI with a strong CYP3A inhibitor cannot be avoided, reduce the dose of KISQALI to 400 mg once daily [see Dosage and Administration (2.2)] .
7.2Drugs That May Decrease Ribociclib Plasma Concentrations CYP3A Inducers Coadministration of strong CYP3A inducers decreases the plasma exposure of ribociclib [see Clinical Pharmacology (12.3)] . Avoid concomitant use of strong CYP3A inducers and consider an alternate concomitant medication with no or minimal potential to induce CYP3A.
7.3Effect of KISQALI on Other Drugs CYP3A Substrates Coadministration of sensitive CYP3A4 substrates with multiple doses of KISQALI increases the substrate exposure [see Clinical Pharmacology (12.3)] . For CYP3A substrates where minimal increases in the concentration may increase CYP3A substrate adverse reactions, monitor for increased adverse reactions of the CYP3A substrate during treatment with KISQALI. The dose of the sensitive CYP3A substrate may need to be reduced as KISQALI can increase its exposure.
7.4Drugs That Prolong the QT Interval Avoid coadministration of KISQALI with products with a known potential to prolong QT interval, such as antiarrhythmic drugs and other drugs that are known to prolong the QT interval. If concomitant use cannot be avoided, monitor ECG when initiating, during concomitant use, and as clinically indicated [see Warnings and Precautions (5.3), Clinical Pharmacology (12.2)] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and the mechanism of action, KISQALI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)] . There are no available human data informing the drug-associated risk. In animal reproduction studies, administration of ribociclib to pregnant animals during organogenesis resulted in increased incidences of post implantation loss and reduced fetal weights in rats and increased incidences of fetal abnormalities in rabbits at exposures 0.6 or 1.5 times the exposure in humans, respectively, at the highest recommended dose of 600 mg/day based on AUC (see Data) .
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. However, the background risk of major birth defects is 2%-4% and of miscarriage is 15%-20% of clinically recognized pregnancies in the U.S. general population.
Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of ribociclib up to 1000 mg/kg/day and 60 mg/kg/day, respectively, during the period of organogenesis. In rats, 300 mg/kg/day resulted in reduced maternal body weight gain and reduced fetal weights accompanied by skeletal changes related to the lower fetal weights. There were no significant effects on embryo-fetal viability or fetal morphology at 50 or 300 mg/kg/day.
In rabbits at doses ≥ 30 mg/kg/day, there were adverse effects on embryo-fetal development, including increased incidences of fetal abnormalities (malformations and external, visceral, and skeletal variants) and fetal growth (lower fetal weights). These findings included reduced/small lung lobes, additional vessel on the descending aorta, additional vessel on the aortic arch, small eyes, diaphragmatic hernia, absent accessory lobe or (partly) fused lung lobes, reduced/small accessory lung lobe, extra/rudimentary 13 th ribs, misshapen hyoid bone, bent hyoid bone alae, and reduced number of phalanges in the pollex.
There was no evidence of increased incidence of embryo-fetal mortality. There was no maternal toxicity observed at 30 mg/kg/day. At 300 mg/kg/day in rats and 30 mg/kg/day in rabbits, the maternal systemic exposures (AUC) were approximately 0.6 and 1.5 times, respectively, the exposure in patients at the highest recommended dose of 600 mg/day.
8.2Lactation Risk Summary It is not known if ribociclib is present in human milk. There are no data on the effects of ribociclib on the breastfed infant or on milk production. Ribociclib and its metabolites readily passed into the milk of lactating rats.
Because of the potential for serious adverse reactions in breastfed infants from KISQALI, advise lactating women not to breastfeed while taking KISQALI and for at least 3 weeks after the last dose. Data In lactating rats administered a single dose of 50 mg/kg, exposure to ribociclib was 3.56-fold higher in milk compared to maternal plasma.
8.3Females and Males of Reproductive Potential Based on animal studies and mechanism of action, KISQALI can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)] . Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to starting treatment with KISQALI. Contraception Females Advise females of reproductive potential to use effective contraception (methods that result in less than 1% pregnancy rates) during treatment with KISQALI and for at least 3 weeks after the last dose.
Infertility Males Based on animal studies, KISQALI may impair fertility in males of reproductive potential [see Nonclinical Toxicology (13.1)] .
8.4Pediatric Use The safety and effectiveness of KISQALI in pediatric patients have not been established. The safety and efficacy of KISQALI in combination with chemotherapy was assessed but not establishe…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and the mechanism of action, KISQALI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)] . There are no available human data informing the drug-associated risk. In animal reproduction studies, administration of ribociclib to pregnant animals during organogenesis resulted in increased incidences of post implantation loss and reduced fetal weights in rats and increased incidences of fetal abnormalities in rabbits at exposures 0.6 or 1.5 times the exposure in humans, respectively, at the highest recommended dose of 600 mg/day based on AUC (see Data) .
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. However, the background risk of major birth defects is 2%-4% and of miscarriage is 15%-20% of clinically recognized pregnancies in the U.S. general population.
Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of ribociclib up to 1000 mg/kg/day and 60 mg/kg/day, respectively, during the period of organogenesis. In rats, 300 mg/kg/day resulted in reduced maternal body weight gain and reduced fetal weights accompanied by skeletal changes related to the lower fetal weights. There were no significant effects on embryo-fetal viability or fetal morphology at 50 or 300 mg/kg/day.
In rabbits at doses ≥ 30 mg/kg/day, there were adverse effects on embryo-fetal development, including increased incidences of fetal abnormalities (malformations and external, visceral, and skeletal variants) and fetal growth (lower fetal weights). These findings included reduced/small lung lobes, additional vessel on the descending aorta, additional vessel on the aortic arch, small eyes, diaphragmatic hernia, absent accessory lobe or (partly) fused lung lobes, reduced/small accessory lung lobe, extra/rudimentary 13 th ribs, misshapen hyoid bone, bent hyoid bone alae, and reduced number of phalanges in the pollex.
There was no evidence of increased incidence of embryo-fetal mortality. There was no maternal toxicity observed at 30 mg/kg/day. At 300 mg/kg/day in rats and 30 mg/kg/day in rabbits, the maternal systemic exposures (AUC) were approximately 0.6 and 1.5 times, respectively, the exposure in patients at the highest recommended dose of 600 mg/day.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of KISQALI in pediatric patients have not been established. The safety and efficacy of KISQALI in combination with chemotherapy was assessed but not established in an open-label, dose-finding multicenter study (Study CLEE011Q12101; NCT05429502) in 12 patients, including 9 pediatric patients aged 4 to <17 years with relapsed or refractory neuroblastoma and other solid tumors. The study was terminated early due to dose-limiting toxicities (DLTs) preventing the identification of a safe dosing regimen for the investigational combination.
DLTs included neutropenia, anemia, thrombocytopenia, ventricular tachycardia, respiratory failure, and infection. Ribociclib exposures in pediatric patients aged 1 to < 17 years were within the range of values previously observed in adults based on body surface area.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 2549 adults with early breast cancer who received KISQALI in NATALEE, 407 patients (16%) were ≥ 65 years of age and 123 patients (2.4%) were ≥ 75 years of age. No overall differences in safety or effectiveness of KISQALI were observed between older and younger adults with early breast cancer. Of 334 patients with advanced or metastatic breast cancer who received KISQALI in MONALEESA-2, 150 patients (45%) were ≥ 65 years of age and 35 patients (11%) were ≥ 75 years of age.
Of 484 patients with advanced or metastatic breast cancer who received KISQALI in MONALEESA-3, 226 patients (47%) were ≥ 65 years of age and 65 patients (14%) were ≥ 75 years of age. Of 248 patients with advanced or metastatic breast cancer who received KISQALI in MONALEESA-7, no patients were ≥ 65 years of age. No overall differences in safety or effectiveness of KISQALI were observed between older and younger adults with advanced or metastatic breast cancer.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ribociclib is an inhibitor of cyclin-dependent kinase (CDK) 4 and 6. These kinases are activated upon binding to D-cyclins and are downstream of signaling pathways which lead to cell cycle progression and cellular proliferation. The cyclin D-CDK4/6 complex regulates cell cycle progression through phosphorylation of the retinoblastoma protein (pRb).
In vitro , ribociclib decreased pRb phosphorylation, resulting in arrest in the G1 phase of the cell cycle and reduced proliferation in breast cancer-derived models. In vivo , treatment with single agent ribociclib in a rat xenograft model with human tumor cells led to decreased tumor volumes, which correlated with inhibition of pRb phosphorylation. In studies using patient-derived estrogen receptor positive breast cancer xenograft models, combination of ribociclib and antiestrogen (e.g., letrozole) therapies resulted in increased tumor growth inhibition compared to each drug alone.
Additionally, the combination of ribociclib and fulvestrant resulted in tumor growth inhibition in an estrogen receptor positive breast cancer xenograft model.
12.2Pharmacodynamics The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of KISQALI have not been fully characterized in patients. Cardiac Electrophysiology A concentration-QT analysis of the data in patients with breast cancer treated with KISQALI at doses ranging from 50 to 1200 mg (0.083 to 2 times of the approved recommended high dose) suggested that ribociclib causes concentration-dependent increases in QTcF interval [see Warnings and Precautions (5.3, 5.4)] .
In patients with early breast cancer, the estimated mean QTcF interval change from baseline for the KISQALI 400 mg in combination with non-steroidal aromatase inhibitor (NSAI) was 10.0 ms (90% CI: 8.0, 11.9) at the mean steady-state C max [see Warnings and Precautions (5.3, 5.4)] . In patients with advanced or metastatic breast cancer the estimated mean QTcF interval change from baseline for the KISQALI 600 mg in combination with aromatase inhibitors or fulvestrant was 22.0 ms (90% CI: 20.6, 23.4) and 23.7 ms (90% CI: 22.3, 25.1), respectively, and was 34.7 ms (90% CI: 31.6, 37.8) in combination with tamoxifen at the mean steady-state C max [see Warnings and Precautions (5.3, 5.4)] .
12.3Pharmacokinetics Ribociclib exhibited over-proportional increases in exposure (C max and AUC) across the dose range of 50 mg to 1200 mg (0.083 to 2 times of the approved recommended high dose) following both single dose and repeated doses of KISQALI. Following repeated 600 mg once daily administration, steady-state was generally achieved after 8 days and ribociclib accumulated with a mean accumulation ratio of 2.5 (range, 0.97 to 6.4), and mean (coefficient of variation (CV%)) steady-state ribociclib C max was 1820 (62%) ng/mL and AUC was 23800 (66%) ng*h/mL.
Absorption The T max following KISQALI administration was between 1 and 4 hours. The mean absolute bioavailability of ribociclib after a single oral dose of 600 mg was 65.8%. Food Effect: Compared to the fasted state, oral administration of a single 600 mg dose of KISQALI tablet with a high-fat, high-calorie meal (approximately 800 to 1000 calories with ~50% calories from fat, ~35% calories from carbohydrates, and ~15% calories from protein) had no clinically meaningful differences in ribociclib C max or AUC inf .
Distribution Ribociclib protein binding in vitro was approximately 70% and independent of concentration (10 to 10,000 ng/mL). The mean in vivo blood-to-plasma ratio was 1.04. The apparent volume of distribution at steady-state (Vss/F) was 1090 L.
Metabolism Ribociclib undergoes extensive hepatic metabolism mainly via CYP3A4 in humans. Following oral administration of a single 600 mg dose of radio-labeled ribociclib to humans, the primary metabolic pathways for ribociclib involved oxidation (dealkylation, C and/or N-oxygenation,…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ribociclib is an inhibitor of cyclin-dependent kinase (CDK) 4 and 6. These kinases are activated upon binding to D-cyclins and are downstream of signaling pathways which lead to cell cycle progression and cellular proliferation. The cyclin D-CDK4/6 complex regulates cell cycle progression through phosphorylation of the retinoblastoma protein (pRb).
In vitro , ribociclib decreased pRb phosphorylation, resulting in arrest in the G1 phase of the cell cycle and reduced proliferation in breast cancer-derived models. In vivo , treatment with single agent ribociclib in a rat xenograft model with human tumor cells led to decreased tumor volumes, which correlated with inhibition of pRb phosphorylation. In studies using patient-derived estrogen receptor positive breast cancer xenograft models, combination of ribociclib and antiestrogen (e.g., letrozole) therapies resulted in increased tumor growth inhibition compared to each drug alone.
Additionally, the combination of ribociclib and fulvestrant resulted in tumor growth inhibition in an estrogen receptor positive breast cancer xenograft model.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING KISQALI (ribociclib) Tablets Each film-coated tablet contains 200 mg of ribociclib free base. Light greyish violet, round, curved with beveled edge, debossed with “RIC” on one side and “NVR” on the other side; available in: Carton of 3 blister packs (63 tablets total) – each blister pack contains a 7-day supply of 21 tablets (200 mg per tablet) (600 mg daily dose). NDC 0078-0874-63 Carton of 3 blister packs (42 tablets total) – each blister pack contains a 7-day supply of 14 tablets (200 mg per tablet) (400 mg daily dose).
NDC 0078-0867-42 Carton of 1 blister pack (21 tablets total) – each blister pack contains a 21-day supply of 21 tablets (200 mg per tablet) (200 mg daily dose). NDC 0078-0860-01 Store at room temperature at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F). Store in the original blister package in order to protect from moisture.
📋 Description ▾
11 DESCRIPTION KISQALI (ribociclib) is a kinase inhibitor. The chemical name of ribociclib succinate is: Butanedioic acid—7-cyclopentyl- N , N -dimethyl-2-{[5-(piperazin-1-yl) pyridin-2-yl]amino}-7 H -pyrrolo[2,3- d ]pyrimidine-6-carboxamide (1/1). Ribociclib succinate is a light yellow to yellowish brown crystalline powder.
The molecular formula for ribociclib succinate is C 23 H 30 N 8 O·C 4 H 6 O 4 and the molecular weight is 552.64 g/mol (Free base: 434.55 g/mol). The chemical structure of ribociclib is shown below: KISQALI film-coated tablets are supplied for oral use and contain 200 mg of ribociclib free base (equivalent to 254.40 mg ribociclib succinate). The tablets also contain colloidal silicon dioxide, crospovidone, hydroxypropylcellulose, magnesium stearate and microcrystalline cellulose.
The film-coating contains iron oxide black, iron oxide red, lecithin (soya), polyvinyl alcohol (partially hydrolysed), talc, titanium dioxide, and xanthan gum as inactive ingredients. The Following chemical structure of KISQALI film-coated tablets are supplied for oral administration and contain 200 mg of ribociclib free base (equivalent to 254.40 mg ribociclib succinate). The tablets also contain colloidal silicon dioxide, crospovidone, hydroxypropylcellulose, magnesium stearate and microcrystalline cellulose.
The film-coating contains iron oxide black, iron oxide red, lecithin (soya), polyvinyl alcohol (partially hydrolysed), talc, titanium dioxide, and xanthan gum as inactive ingredients.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Interstitial Lung Disease/Pneumonitis Advise patients to immediately report new or worsening respiratory symptoms [see Warnings and Precautions (5.1)] . Severe Cutaneous Adverse Reactions Inform patients of the signs and symptoms of severe cutaneous adverse reactions (e.g., skin pain/burning, rapidly-spreading skin rash, and/or mucosal lesions accompanied by fever or flu-like symptoms).
Advise patients to contact their healthcare provider immediately if they develop signs and symptoms of severe cutaneous adverse reactions [see Warnings and Precautions (5.2)] . QT Prolongation Inform patients of the signs and symptoms of QT prolongation. Advise patients to contact their healthcare provider immediately for signs or symptoms of QT prolongation [see Warnings and Precautions (5.3, 5.4)] .
Hepatobiliary Toxicity Inform patients of the signs and symptoms of hepatobiliary toxicity. Advise patients to contact their healthcare provider immediately for signs or symptoms of hepatobiliary toxicity [see Warnings and Precautions (5.5)] . Neutropenia Advise patients of the possibility of developing neutropenia and to immediately contact their healthcare provider should they develop a fever, particularly in association with any suggestion of infection [see Warnings and Precautions (5.6)] .
Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.7), Use in Specific Populations (8.1)] . Advise females of reproductive potential to use effective contraception during KISQALI therapy and for at least 3 weeks after the last dose [see Use in Specific Populations (8.3)] .
Lactation Advise lactating women not to breastfeed during treatment with KISQALI and for at least 3 weeks after the last dose [see Use in Specific Populations (8.2)] . Drug Interactions Inform patients to avoid strong CYP3A inhibitors, strong CYP3A inducers, and drugs known to prolong the QT interval [see Drug Interactions (7.1, 7.2, 7.4)] . Dosing Instruct patients to take the doses of KISQALI at approximately the same time every day and to swallow whole (do not chew, crush, or split them prior to swallowing) [see Dosage and Administration (2.1)] .
If patient vomits or misses a dose, advise the patient to take the next prescribed dose at the usual time [see Dosage and Administration (2.1)] . Advise the patient that KISQALI may be taken with or without food [see Dosage and Administration (2.1)] . Distributed by: Novartis Pharmaceuticals Corporation East Hanover, New Jersey 07936 © Novartis T2026-21