
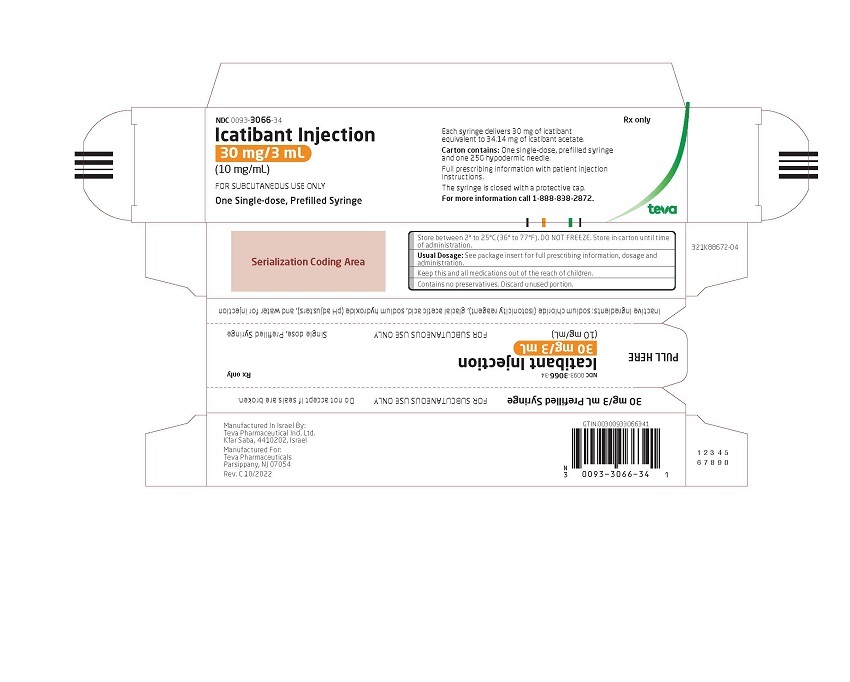
Icatibant 10 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Bradykinin B2 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Q40Q9N063P
Acetic acid is a weak organic acid commonly used in medicines as a buffer and pH adjuster. It helps maintain the proper acidity level to ensure the drug remains stable and effective in its formulation.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $836.31 | $2,508.92 / 3 ml |
| Medicare drug plans payPart D · Q2 2026 | $1,238.64 | $3,715.91 / 3 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Icatibant 10 mg/mLthis 00093-3066-34 | Teva | 1 syringe | — | AP | FDA listed | — |
| Icatibant 30 mg/3mL 24201-0207-01 | Hikma | 1 syringe | — | AP | FDA listed | — |
| Icatibant 30 mg/3mL 46708-0654-03 | Alembic | 1 syringe | — | AP | FDA listed | — |
| Firazyr 30 mg/3mL 54092-0702-01 | Takeda | 1 syringe | — | AP | FDA listed | — |
| Icatibant 30 mg/3mL 55150-0351-01 | Eugia | 1 syringe | — | AP | FDA listed | — |
| Icatibant 30 mg/3mL 62332-0654-03 | Alembic | 1 syringe | — | AP | FDA listed | — |
| Icatibant 10 mg/mL 63323-0574-86 | Fresenius | 1 syringe | — | AP | FDA listed | — |
| Icatibant 30 mg/3mL 69097-0664-34 | Cipla | 1 syringe | — | AP | FDA listed | — |
| Sajazir 30 mg/3mL 70709-0013-01 | Cycle | 1 syringe | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00093-3066-34 You're viewing this | 1 SYRINGE in 1 CARTON (0093-3066-34) / 3 mL in 1 SYRINGE | 2019-07-15 | Active |
| 00093-3066-93 | 3 CARTON in 1 BOX (0093-3066-93) / 1 SYRINGE in 1 CARTON (0093-3066-19) / 3 mL in 1 SYRINGE | 2019-07-15 | Active |
This pack accounts for about 28% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 00093-3066-34?
What NDC number is used to bill for this package of Icatibant 10 mg/mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Icatibant Injection is indicated for the treatment of acute attacks of hereditary angioedema (HAE) in adults 18 years of age and older. Icatibant Injection is a bradykinin B2 receptor antagonist indicated for treatment of acute attacks of hereditary angioedema (HAE) in adults 18 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION 30 mg injected subcutaneously in the abdominal area. ( 2.1 ) If response is inadequate or symptoms recur, additional injections of 30 mg may be administered at intervals of at least 6 hours. ( 2.1 ) Do not administer more than 3 injections in 24 hours. ( 2.1 ) Patients may self-administer upon recognition of an HAE attack. ( 2.2 )
2.1Recommended Dosing The recommended dose of Icatibant Injection is 30 mg administered by subcutaneous (SC) injection in the abdominal area. Additional doses may be administered at intervals of at least 6 hours if response is inadequate or if symptoms recur. No more than 3 doses may be administered in any 24 hour period.
2.2Administration Instructions Icatibant Injection should be inspected visually for particulate matter and discoloration prior to administration. The drug solution should be clear and colorless. Do not administer if the product contains particulates or is discolored.
Attach the provided 25 gauge needle to the syringe hub and screw on securely. Do not use a different needle. Disinfect the injection site and administer icatibant by subcutaneous injection over at least 30 seconds.
Patients may self-administer Icatibant Injection upon recognition of symptoms of an HAE attack after training under the guidance of a healthcare professional [see Patient Counseling Information ( 17 )] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Icatibant Injection is supplied in a prefilled syringe delivering 30 mg icatibant. Each syringe delivers 3 mL solution with a concentration of 10 mg per mL. Injection: 10 mg per mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Laryngeal attacks: Following treatment of laryngeal attacks with icatibant, advise patients to seek immediate medical attention. ( 5.1 )
5.1Laryngeal Attacks Given the potential for airway obstruction during acute laryngeal HAE attacks, patients should be advised to seek medical attention in an appropriate healthcare facility immediately in addition to treatment with icatibant.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most commonly reported adverse reactions were injection site reactions, which occurred in almost all patients (97%) in clinical trials. Other common adverse reactions occurring in greater than 1% of patients included pyrexia, transaminase increase, dizziness, and rash. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience The safety of icatibant was evaluated in three controlled trials that included 223 patients who received icatibant 30 mg (n=113), placebo (n=75), or comparator (n=38). The mean age at study entry was 38 years (range 18 to 83 years), 64% were female, and 95% were white. The data described below represent adverse reactions observed from the two placebo-controlled trials, consisting of 77 patients who received icatibant at a dose of 30 mg SC, and 75 who received placebo.
The most frequently reported adverse reactions (occurring in greater than 1% of patients and at a higher rate with icatibant versus placebo) are shown in Table 1. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Table 1: Adverse Reactions Observed in >1% of Patients with Acute Attacks of HAE and at a Higher Rate with Icatibant versus Placebo in the Placebo-controlled Trials a Icatibant (N=77) Placebo (N=75) System Organ Class Preferred Term Subjects (%) Subjects (%) General disorders and administration site conditions Injection site reaction b 75 (97) 25 (33) Pyrexia 3 (4) 0 Investigations Transaminase increased 3 (4) 0 Nervous system disorders Dizziness 2 (3) 1 (1) a Events occurring within 14 days of study drug administration b Injection site bruising, Injection site hematoma, Injection site burning, Injection site erythema, Injection site hypoesthesia, Injection site irritation, Injection site numbness, Injection site edema, Injection site pain, Injection site pressure sensation, Injection site pruritus, Injection site swelling, Injection site urticaria, and Injection site warmth The third trial was active-controlled and was comprised of 35 patients who received icatibant 30 mg and 38 patients who received the comparator.
Adverse reactions for icatibant were similar in nature and frequency to those reported in Table 1. In all three controlled trials, patients were eligible for treatment of subsequent attacks in an open-label extension. Patients were treated with Icatibant Injection 30 mg and could receive up to 3 doses of Icatibant Injection 30 mg administered at least 6 hours apart for each attack.
A total of 225 patients were treated with 1,076 doses of 30 mg Icatibant Injection for 987 attacks of acute HAE. Adverse reactions similar in nature and frequency were observed to those seen in the controlled phase of the trials. Other adverse reactions reported included rash, nausea, and headache in patients exposed to Icatibant Injection.
The safety of self-administration was evaluated in a separate, open-label trial in 56 patients with HAE. In this trial, the safety profile of Icatibant Injection in patients who self-administered Icatibant Injection was similar in nature and frequency to that of patients whose therapy was administered by healthcare professionals.
6.2Immunogenicity Across repeated treatment in the controlled trials, 4 patients tested positive for anti-icatibant antibodies. Three of these patients had subsequent tests which were negative. No hypersensitivity or anaphylactic reactions were reported with icatibant. No association between anti-icatibant antibodies and efficacy was observed.
6.3Postmarketing Experience The following adverse reactions have been identified during post approval use of icatibant: urticaria. Because these events are reported voluntarily from a population of uncertai…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1ACE Inhibitors Icatibant is a bradykinin B2 receptor antagonist and thereby has the potential to have a pharmacodynamic interaction with ACE inhibitors where icatibant may attenuate the antihypertensive effect of ACE inhibitors. Clinical trials to date have excluded subjects taking ACE inhibitors.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Elderly patients demonstrate increased systemic exposure to icatibant. Differences in efficacy and safety between elderly and younger patients have not been identified. ( 8.5 )
8.1Pregnancy Risk Summary Available data from published literature and the pharmacovigilance database with icatibant use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, icatibant, administered by the subcutaneous route during the period of organogenesis, did not cause structural abnormalities in rats or rabbits; however, premature birth and abortion were observed in rabbits at doses approximately 0.025 times the maximum recommended human dose (MRHD) and higher.
Decreased embryofetal survival was observed in rabbits at a subcutaneous dose that was 13 times the MRHD. In a pre- and post-natal development study in rats, delayed parturition was observed at subcutaneous doses 0.5 times the MRHD and higher, which resulted in deaths of dams at doses 2 times the MRHD and higher. Fetal death and early pup deaths were observed with doses 2 times the MRHD ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In an embryo-fetal development study with rats that received icatibant from gestation days 7 to 18, there was no evidence of any treatment-related structural abnormalities or effects on embryo-fetal survival with maternal doses up to 2.7 times the MRHD (on a mg/m 2 basis with maternal subcutaneous doses up to 25 mg/kg/day). In a fertility and early embryonic development study with rats, icatibant increased preimplantation loss at a dose that was 7 times the MRHD (on an AUC basis at a maternal dose of 10 mg/kg/day).
In an embryo-fetal development study with rabbits that received icatibant from gestation days 7 to 18, premature birth and abortion rates increased at doses approximately 0.025 times the MRHD and higher (on a mg/m 2 basis at maternal subcutaneous doses of 0.1 mg/kg and higher). Icatibant treatment resulted in dose-related decreases of total implantations and total number of live fetuses as well as dose-related increases of percent pre-implantation loss at a dose that was 13 times the MRHD (on an AUC basis with a maternal subcutaneous dose of 10 mg/kg/day).
There was no evidence of any treatment-related structural abnormalities with maternal doses up to 13 times the MRHD (on an AUC basis with maternal subcutaneous doses up to 10 mg/kg/day). In a pre- and post-natal development study in the rat, dams received icatibant by the subcutaneous route at doses of 1, 3, and 10 mg/kg/day from gestation day 6 to post-partum (PPD) day 20. Delayed parturition was observed at doses 0.5 times the MRHD and higher (on an AUC basis with maternal subcutaneous doses of 1 mg/kg/day and higher), which resulted in deaths of dams at doses 2 times the MRHD and higher (on an AUC basis with maternal subcutaneous doses of 3 mg/kg/day and higher).
Fetal death and increased pup deaths through PPD 4 were observed with doses 2 times the MRHD (on an AUC with a maternal subcutaneous dose of 3 mg/kg/day and higher). Impairment of pup righting reflex and decreased pup hair growth were also observed at 7 times the MRHD (on an AUC basis with a maternal dose of 10 mg/kg). Icatibant and the M2 metabolite were found in maternal milk following subcutaneous administration of icatibant.
The no effect dose for F1 pups was identified at a dose 0.5 times the MRHD (on an AUC basis with a maternal subcutaneous dose of 1 mg/kg/day). A no effect dose was not identified for F 0 maternal toxicity.
8.2 Lact…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published literature and the pharmacovigilance database with icatibant use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, icatibant, administered by the subcutaneous route during the period of organogenesis, did not cause structural abnormalities in rats or rabbits; however, premature birth and abortion were observed in rabbits at doses approximately 0.025 times the maximum recommended human dose (MRHD) and higher.
Decreased embryofetal survival was observed in rabbits at a subcutaneous dose that was 13 times the MRHD. In a pre- and post-natal development study in rats, delayed parturition was observed at subcutaneous doses 0.5 times the MRHD and higher, which resulted in deaths of dams at doses 2 times the MRHD and higher. Fetal death and early pup deaths were observed with doses 2 times the MRHD ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In an embryo-fetal development study with rats that received icatibant from gestation days 7 to 18, there was no evidence of any treatment-related structural abnormalities or effects on embryo-fetal survival with maternal doses up to 2.7 times the MRHD (on a mg/m 2 basis with maternal subcutaneous doses up to 25 mg/kg/day). In a fertility and early embryonic development study with rats, icatibant increased preimplantation loss at a dose that was 7 times the MRHD (on an AUC basis at a maternal dose of 10 mg/kg/day).
In an embryo-fetal development study with rabbits that received icatibant from gestation days 7 to 18, premature birth and abortion rates increased at doses approximately 0.025 times the MRHD and higher (on a mg/m 2 basis at maternal subcutaneous doses of 0.1 mg/kg and higher). Icatibant treatment resulted in dose-related decreases of total implantations and total number of live fetuses as well as dose-related increases of percent pre-implantation loss at a dose that was 13 times the MRHD (on an AUC basis with a maternal subcutaneous dose of 10 mg/kg/day).
There was no evidence of any treatment-related structural abnormalities with maternal doses up to 13 times the MRHD (on an AUC basis with maternal subcutaneous doses up to 10 mg/kg/day). In a pre- and post-natal development study in the rat, dams received icatibant by the subcutaneous route at doses of 1, 3, and 10 mg/kg/day from gestation day 6 to post-partum (PPD) day 20. Delayed parturition was observed at doses 0.5 times the MRHD and higher (on an AUC basis with maternal subcutaneous doses of 1 mg/kg/day and higher), which resulted in deaths of dams at doses 2 times the MRHD and higher (on an AUC basis with maternal subcutaneous doses of 3 mg/kg/day and higher).
Fetal death and increased pup deaths through PPD 4 were observed with doses 2 times the MRHD (on an AUC with a maternal subcutaneous dose of 3 mg/kg/day and higher). Impairment of pup righting reflex and decreased pup hair growth were also observed at 7 times the MRHD (on an AUC basis with a maternal dose of 10 mg/kg). Icatibant and the M2 metabolite were found in maternal milk following subcutaneous administration of icatibant.
The no effect dose for F1 pups was identified at a dose 0.5 times the MRHD (on an AUC basis with a maternal subcutaneous dose of 1 mg/kg/day). A no effect dose was not identified for F 0 maternal toxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients below the age of 18 years have not been established. Juvenile Toxicity Data Subcutaneous daily administration of icatibant to young rats during the juvenile period of development (postnatal days 22 to 70) delayed the sexual maturation of male reproductive tissues (atrophy of testes and epididymides) at exposures approximating one-third or greater the MRHD on a mg/m 2 basis. Impaired fertility and reproductive performance were also observed in male rats at the end of the postnatal treatment period at exposures approximating the MRHD or greater on a mg/m 2 basis.
No effects were observed in females at exposures approximating 3-fold the MRHD on a mg/m 2 basis. The observed tissue findings in males were consistent with those seen in sexually mature rats and dogs and are attributed to antagonism of the bradykinin B2 receptor and subsequent effects on gonadotropins. The observed effects may be a consequence of daily icatibant administration.
Toxicity to the testis did not occur in dogs treated twice a week for 9 months [see Carcinogenesis, Mutagenesis, Impairment of Fertility ( 13.1 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of icatibant did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Elderly patients are likely to have increased systemic exposure to icatibant compared to younger (18 to 45 years) patients [see Clinical Pharmacology ( 12.3 )] . Since other reported clinical experience has not identified differences in efficacy and safety between elderly and younger patients, no dose adjustment is recommended.
🆘 Overdosage ▾
10 OVERDOSAGE In a clinical study evaluating a 90 mg dose (30 mg in each of 3 subcutaneous sites), the adverse event profile was similar to that seen with 30 mg administered in a single subcutaneous site. In another clinical study, a dose of 3.2 mg/kg administered intravenously (approximately 8 times the therapeutic dose for HAE) caused erythema, itching and hypotension in healthy subjects. No therapeutic intervention was necessary.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Icatibant is a competitive antagonist selective for the bradykinin B2 receptor, with an affinity similar to bradykinin. Hereditary angioedema is caused by an absence or dysfunction of C1-esterase-inhibitor, a key regulator of the Factor XII/kallikrein proteolytic cascade that leads to bradykinin production. Bradykinin is a vasodilator which is thought to be responsible for the characteristic HAE symptoms of localized swelling, inflammation, and pain.
Icatibant inhibits bradykinin from binding the B2 receptor and thereby treats the clinical symptoms of an acute, episodic attack of HAE.
12.2Pharmacodynamics Following bradykinin challenge, intravenous administration of icatibant caused dose and time-dependent inhibition of development of bradykinin-induced hypotension, vasodilation, and reflex tachycardia in healthy young subjects. Icatibant intravenous doses of 0.4 and 0.8 mg/kg infused over 4 hours inhibited response to bradykinin challenge for 6 to 8 hours following completion of the infusion. Based on exposure-response analysis, a subcutaneous dose of 30 mg icatibant is predicted to be effective against bradykinin challenge for at least 6 hours.
The clinical significance of these findings is unknown. The effect of icatibant 30 and 90 mg following a single subcutaneous injection on QTc interval was evaluated in a randomized, placebo-, and active-controlled (moxifloxacin 400 mg) four-period crossover thorough QT study in 72 healthy subjects. In a study with demonstrated ability to detect small effects, the upper bound of the one-sided 95% confidence interval for the largest placebo adjusted, baseline-corrected QTc based on individual correction method (QTcI) was below 10 ms, the threshold for regulatory concern.
The dose of 90 mg is adequate to represent the high exposure clinical scenario.
12.3Pharmacokinetics The pharmacokinetics of icatibant has been characterized in studies using both intravenous and subcutaneous administration to healthy subjects and patients. The pharmacokinetic profile of icatibant in patients with HAE is similar to that in healthy subjects. The absolute bioavailability of icatibant following a 30 mg subcutaneous dose is approximately 97%.
Following subcutaneous administration of a single 30 mg dose of icatibant to healthy subjects (N=96), a mean (± standard deviation) maximum plasma concentration (C max ) of 974 ± 280 ng/mL was observed after approximately 0.75 hours. The mean area under the concentration-time curve (AUC 0-∞ ) after a single 30 mg dose was 2165 ± 568 ng•hr/mL, with no evidence of accumulation of icatibant following three 30 mg doses administered 6 hours apart. Following subcutaneous administration, plasma clearance was 245 ± 58 mL/min with a mean elimination half-life of 1.4 ± 0.4 hours and volume of distribution at steady state (V ss ) of 29.0 ±
8.7L. Icatibant is extensively metabolized by proteolytic enzymes to inactive metabolites that are primarily excreted in the urine, with less than 10% of the dose eliminated as unchanged drug. Icatibant is not degraded by oxidative metabolic pathways, is not an inhibitor of major cytochrome P450 (CYP) isoenzymes (CYP 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, and 3A4) and is not an inducer of CYP 1A2 and 3A4.
Special populations Hepatic Impairment The pharmacokinetic parameters of icatibant were found to be generally comparable between healthy subjects (n=8) and mild to moderate (Child Pugh scores of 5 to 8) hepatic impaired patients (n=8) following a dose of 0.15 mg/kg/day as continuous intravenous infusion over 3 days. In a separate study, icatibant clearance in subjects with a wide range of hepatic impairment (Child-Pugh scores of 7 to 15) was similar to that in healthy subjects. No dose adjustment is necessary for patients with impairment of hepatic function [see Use in Specific Populations ( 8.6 )] .
Renal Impairment Since renal clearance of icatibant is a minor eliminating pathway, renal…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Icatibant is a competitive antagonist selective for the bradykinin B2 receptor, with an affinity similar to bradykinin. Hereditary angioedema is caused by an absence or dysfunction of C1-esterase-inhibitor, a key regulator of the Factor XII/kallikrein proteolytic cascade that leads to bradykinin production. Bradykinin is a vasodilator which is thought to be responsible for the characteristic HAE symptoms of localized swelling, inflammation, and pain.
Icatibant inhibits bradykinin from binding the B2 receptor and thereby treats the clinical symptoms of an acute, episodic attack of HAE.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Icatibant Injection is supplied as a single-dose, prefilled syringe for subcutaneous administration. Each syringe delivers 3 mL of a sterile solution of icatibant 30 mg (as icatibant acetate). Each glass syringe has a bromobutyl plunger stopper, which is not made of latex natural rubber.
Icatibant Injection is available in cartons containing one single-dose, prefilled syringe and one 25 G Luer lock needle. NDC 0093-3066-34. Icatibant Injection is also available in a pack containing 3 cartons; each carton contains one single-dose, prefilled syringe and one 25 G Luer lock needle.
NDC 0093-3066-93.
16.2Storage and Handling Store between 2° to 25°C (36° to 77°F). Do not freeze. Store in carton until time of administration. Keep this and all medications out of the reach of children.
📋 Description ▾
11 DESCRIPTION Icatibant is a synthetic decapeptide with five non-proteinogenic amino acids. The chemical structure of icatibant acetate is presented in Figure 1. Figure 1 Chemical Structure Chemical name: D-Arginyl-L-arginyl-L-prolyl-L[(4R)-4-hydroxyprolyl]-glycyl-L[3-(2-thienyl)alanyl]-L‑seryl-D-(1,2,3,4-tetrahydroisoquinolin-3-ylcarbonyl)-L[(3aS,7aS)-octahydroindol-2-ylcarbonyl]-L‑arginine, acetate salt Icatibant Injection is provided as a sterile, isotonic, and buffered solution of icatibant acetate in a single-dose, prefilled syringe for subcutaneous administration.
Each mL of the solution contains 10 mg of icatibant (free base) which is equivalent to 11.38 mg of icatibant acetate. Each prefilled syringe delivers 3 mL of solution equivalent to a 30 mg icatibant dose. The solution is clear and colorless.
The solution also contains sodium chloride (isotonicity reagent), glacial acetic acid (pH adjuster), sodium hydroxide (pH adjuster) and water for injection with a pH of approximately 5.5. The solution does not contain preservatives. Pharmacological class: Icatibant is a bradykinin B2 receptor antagonist.
1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
17.1Information for Patients Patients may self-administer Icatibant Injection upon recognition of an HAE attack after training under the guidance of a healthcare professional. Patients with laryngeal symptoms should seek medical attention immediately in an appropriate healthcare facility after administration of Icatibant Injection [see Warnings and Precautions ( 5.1 )] . Injection site reactions are reported in most patients after administration of Icatibant Injection.
Other adverse reactions reported after administration of Icatibant Injection include pyrexia, increase in transaminases, dizziness, and rash [see Adverse Reactions ( 6.1 )] . Tiredness, drowsiness, and dizziness have been reported following the use of Icatibant Injection. Patients should be advised not to drive or use machinery if they feel tired or dizzy.
Manufactured In Israel By: Teva Pharmaceutical Ind. Ltd. Kfar Saba, 4410202, Israel Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev.
C 2/2024