
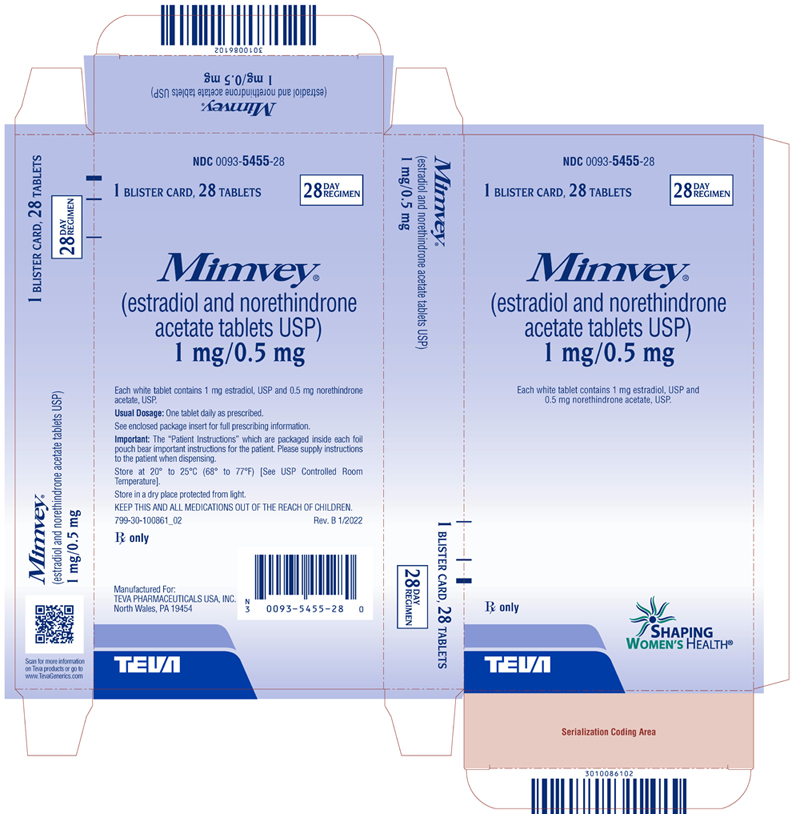
Mimvey Estradiol and Norethindrone Acetate 1 mg; .5 mg Tablet, Film Coated, 28-count
Past resolved recalls for this product (2)
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Radioactive Diagnostic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Great question. The estradiol (the estrogen part) is what actually relieves your hot flashes, night sweats, and vaginal dryness by replacing the estrogen your body stopped making a...
- What exactly is this medicine doing for me — why do I need both an estrogen and a progestin?
- Most women notice things like breast tenderness, some spotting or light bleeding, headaches, or nausea — especially in the first few months. Those are common and usually settle dow...
- What are the most important side effects I should actually watch out for?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.641 | $17.95 / 28 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.9306 | $26.06 / 28 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.36 | $37.97 / 28 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Estradiol and Norethindrone Acetate 1 mg/1; .5 mg 50742-0657-28 | Ingenus | 28 tablets | $0.641 | AB | Availability likely | — |
| Estradiol / Norethindrone Acetate 1 mg/1; .5 mg 51991-0474-28 | Breckenridge | 28 tablets | $0.641 | AB | Availability likely | — |
| Abigale 1 mg/1; .5 mg 70700-0330-85 | Xiromed | 84 tablets | $0.641 | AB | Availability likely | — |
| Mimvey 1 mg/1; .5 mgthis 00093-5455-28 | Teva | 28 tablets | $0.641 | AB | Availability likely | — |
| Etyqa 1 mg/1; .5 mg 59651-0424-28 | Aurobindo | 28 tablets | — | — | FDA listed | — |
| Estradiol / Norethindrone Acetate 1 mg/1; .5 mg 50090-8003-00 | A-S | 28 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00093-5455-28 You're viewing this | 1 BLISTER PACK in 1 CARTON (0093-5455-28) / 28 TABLET, FILM COATED in 1 BLISTER PACK | $0.6409 / ea | $17.94 | 2010-06-02 | Active |
| 00093-5455-42 | 5 BLISTER PACK in 1 CARTON (0093-5455-42) / 28 TABLET, FILM COATED in 1 BLISTER PACK | $0.6409 / ea | $89.72 | 2010-06-02 | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.6409 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00093-5455-28?
What NDC number is used to bill for this package of Mimvey Estradiol and Norethindrone Acetate 1 mg; .5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR DISORDERS, PROBABLE DEMENTIA, BREAST CANCER, and ENDOMETRIAL CANCER Estrogen Plus Progestin Therapy Cardiovascular Disorders and Probable Dementia The Women’s Health Initiative (WHI) estrogen plus progestin substudy reported increased risks of deep vein thrombosis (DVT), pulmonary embolism (PE), stroke and myocardial infarction (MI) in postmenopausal women (50 to 79 years of age) during 5.6 years of treatment with daily oral conjugated estrogen (CE) [0.625 mg] combined with medroxyprogesterone acetate (MPA) [2.5 mg], relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.5 )] .
The WHI Memory Study (WHIMS) estrogen plus progestin ancillary study of the WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 4 years of treatment with daily CE (0.625 mg) combined with MPA (2.5 mg), relative to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.6 )] . Do not use estrogen plus progestogen therapy for the prevention of cardiovascular disease or dementia [see Warnings and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.5 , 14.6 )] .
Breast Cancer The WHI estrogen plus progestin substudy also demonstrated an increased risk of invasive breast cancer [see Warnings and Precautions ( 5.2 ), and Clinical Studies ( 14.5 )] . Only daily oral 0.625 mg CE and 2.5 mg MPA were studied in the estrogen plus progestin substudy of the WHI. Therefore, the relevance of the WHI findings regarding adverse cardiovascular events, dementia and breast cancer to lower CE plus other MPA doses, other routes of administration, or other estrogen plus progestogen products is not known.
Without such data, it is not possible to definitively exclude these risks or determine the extent of these risks for other products. Discuss with your patient the benefits and risks of estrogen plus progestogen therapy, taking into account her individual risk profile. Prescribe estrogens with or without progestogens at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman.
Estrogen-Alone Therapy Endometrial Cancer There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens. Adding a progestogen to estrogen therapy has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Adequate diagnostic measures, including directed or random endometrial sampling when indicated, should be undertaken to rule out malignancy in postmenopausal women with undiagnosed persistent or recurring abnormal genital bleeding [see Warnings and Precautions ( 5.2 )] .
Cardiovascular Disorders and Probable Dementia The WHI estrogen-alone substudy reported increased risks of stroke and DVT in postmenopausal women (50 to 79 years of age) during 7.1 years of treatment with daily oral CE (0.625 mg)-alone, relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.5 )] . The WHIMS estrogen-alone ancillary study of the WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 5.2 years of treatment with daily CE (0.625 mg)-alone, relative to placebo.
It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.6 )] . Do not use estrogen-alone therapy for the prevention of cardiovascular disease or dementia [see Warnings and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.5 , 14.6 )] . Only daily oral 0.625 mg CE was studied in the estrogen-alone substudy of the WHI.
Therefore, the relevance of the WHI findings regarding adverse cardiovascular events and dementia to lower CE doses, other routes of a…
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mimvey is indicated for: Mimvey is an estrogen and progestin combination indicated in a woman with a uterus for: Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause ( 1.1 ) Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause ( 1.2 ) Limitations of Use: When prescribing solely for the treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause, first consider the use of topical vaginal products. Prevention of Postmenopausal Osteoporosis ( 1.3 ) Limitations of Use: When prescribing solely for the prevention of postmenopausal osteoporosis, first consider the use of non-estrogen medications.
Consider estrogen therapy only for women at significant risk of osteoporosis.
1.1 Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause
1.2Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause Limitation of Use When prescribing solely for the treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause, first consider the use of topical vaginal products.
1.3Prevention of Postmenopausal Osteoporosis Limitation of Use When prescribing solely for the prevention of postmenopausal osteoporosis, first consider the use of non-estrogen medications. Consider estrogen therapy only for women at significant risk of osteoporosis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Use estrogen-alone, or in combination with a progestogen, at the lowest effective dose and the shortest duration consistent with treatment goals and risks for the individual woman. Reevaluate postmenopausal women periodically as clinically appropriate to determine whether treatment is still necessary. Take a single Mimvey 1 mg/0.5 mg tablet orally once daily for the Treatment of Moderate to severe Vasomotor Symptoms due to Menopause and for the Prevention of Postmenopausal Osteoporosis ( 2.1 , 2.3 ) Mimvey 1 mg/0.5 mg tablets are taken orally once daily for the Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause ( 2.2 )
2.1Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause Take a single Mimvey tablet orally once daily for the treatment of moderate to severe vasomotor symptoms due to menopause. Mimvey 1 mg/0.5 mg
2.2Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause Take a single Mimvey tablet orally once daily for the treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause. Mimvey 1 mg/0.5 mg
2.3Prevention of Postmenopausal Osteoporosis Take a single Mimvey tablet orally once daily for the prevention of postmenopausal osteoporosis. Mimvey 1 mg/0.5 mg
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Mimvey tablets are available in one strength: Each tablet of Mimvey (estradiol and norethindrone acetate tablets, USP) 1 mg/0.5 mg contains 1 mg of estradiol and 0.5 mg of norethindrone acetate. The tablets are white, round, biconvex, film-coated, unscored tablets debossed with stylized b on one side and 34 on the other side. Mimvey (estradiol and norethindrone acetate) 1 mg/0.5 mg tablet ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Mimvey is contraindicated in women with any of the following conditions: Undiagnosed abnormal genital bleeding [see Warnings and Precautions ( 5.2 )] Breast cancer or history of breast cancer [see Warnings and Precautions ( 5.2 )] Estrogen-dependent neoplasia [see Warnings and Precautions ( 5.2 )] Active DVT, PE, or history of these conditions [see Warnings and Precautions ( 5.1 )] Active arterial thromboembolic disease (for example, stroke and MI), or a history of these conditions [see Warnings and Precautions ( 5.1 )] Known anaphylactic reaction, angioedema, or hypersensitivity to Mimvey Hepatic impairment or disease Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders Undiagnosed abnormal genital bleeding ( 4 ) Breast cancer or a history of breast cancer ( 4 , 5.2 ) Estrogen-dependent neoplasia ( 4 , 5.2 ) Active DVT, PE, or history of these conditions ( 4 , 5.1 ) Active arterial thromboembolic disease (for example, stroke and MI), or a history of these conditions ( 4 , 5.1 ) Known anaphylactic reaction, angioedema, or hypersensitivity to Mimvey ( 4 ) Hepatic impairment or disease ( 4 , 5.10 ) Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Estrogens increase the risk of gall bladder disease ( 5.4 ) Discontinue estrogen if severe hypercalcemia, loss of vision, severe hypertriglyceridemia or cholestatic jaundice occurs ( 5.5 , 5.6 , 5.9 , 5.10 ) Monitor thyroid function in women on thyroid replacement therapy ( 5.11 , 5.18 )
5.1Cardiovascular Disorders Increased risks of PE, DVT, stroke and MI are reported with estrogen plus progestin therapy. Increased risks of stroke and DVT are reported with estrogen-alone therapy. Immediately discontinue estrogen with or without progestogen therapy if any of these occur or is suspected.
Manage appropriately any risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (VTE) (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus). Stroke The WHI estrogen plus progestin substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 strokes per 10,000 women-years) [see Clinical Studies ( 14.5 )] .
The increase in risk was demonstrated after the first year and persisted. 1 Immediately discontinue estrogen with or without progestogen therapy if a stroke occurs or is suspected. The WHI estrogen-alone substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg)-alone compared to women in the same age group receiving placebo (45 versus 33 strokes per 10,000 women-years, respectively).
The increase in risk was demonstrated in year 1 and persisted [see Clinical Studies ( 14.5 )] . Immediately discontinue estrogen-alone therapy if a stroke occurs or is suspected. Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving CE (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years).
1 Coronary Heart Disease The WHI estrogen plus progestin substudy reported an increased risk (not statistically significant) of coronary heart disease (CHD) events (defined as nonfatal MI, silent MI, or CHD death) in those women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (41 versus 34 per 10,000 women-years). 1 An increase in relative risk was demonstrated in year 1, and a trend toward decreasing relative risk was reported in years 2 through 5 [see Clinical Studies ( 14.5 )] .
The WHI estrogen-alone substudy reported no overall effect on CHD events in women receiving estrogen-alone compared to placebo 2 [see Clinical Studies ( 14.5 )] . Subgroup analyses of women 50 to 59 years of age, who were less than 10 years since menopause, suggest a reduction (not statistically significant) in CHD events in those women receiving daily CE (0.625 mg)-alone compared to placebo (8 versus 16 per 10,000 women-years). 1 In postmenopausal women with documented heart disease (n=2,763), average 66.7 years of age, in a controlled clinical trial of secondary prevention of cardiovascular disease (Heart and Estrogen/Progestin Replacement Study; HERS), treatment with daily CE (0.625 mg plus MPA (2.5 mg) demonstrated no cardiovascular benefit.
During an average follow-up of 4.1 years, treatment with CE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established CHD. There were more CHD events in the CE plus MPA- treated group than in the placebo group in year 1, but not during the subsequent years. Two thousand three hundred twenty-one (2,321) women from the original HERS trial agreed to participate in an open label extension of HERS, HERS II.
Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years overall. Rates of CHD events were comparable among women in the CE plus MPA group and the placebo group…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: Cardiovascular Disorders [see Boxed Warning , Warnings and Precautions ( 5.1 )] Malignant Neoplasms [see Boxed Warning , Warnings and Precautions ( 5.2 )] The most common adverse reactions (incidence ≥ 5 percent) with Mimvey tablets are: back pain, headache, pain in the extremity, nausea, diarrhea, gastroenteritis, insomnia, emotional lability, upper respiratory tract infection, sinusitis, nasopharyngitis, weight increase, breast pain, post-menopausal bleeding, uterine fibroid vaginal hemorrhage, ovarian cyst, endometrial thickening, viral infection, moniliasis genital, and accidental injury.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse reactions reported with estradiol and norethindrone acetate 1 mg/0.5 mg by investigators during clinical trials regardless of causality assessment are shown in Table 1. TABLE 1 ALL TREATMENT-EMERGENT ADVERSE REACTIONS REGARDLESS OF RELATIONSHIP REPORTED AT A FREQUENCY OF ≥ 5 PERCENT WITH ESTRADIOL AND NORETHINDRONE ACETATE 1 MG/0.5 MG Endometrial Hyperplasia Study (12-Months) Vasomotor Symptoms Study (3-Months) Osteoporosis Study (2-Years) Estradiol and Norethindrone Acetate 1 mg/0.5 mg (n=295) 1 mg E 2 (n=296) Estradiol and Norethindrone Acetate 1 mg/0.5 mg (n=29) Placebo (n=34) Estradiol and Norethindrone Acetate 1 mg/0.5 mg (n=47) Placebo (n=48) Body as a Whole Back Pain 6% 5% 3% 3% 6% 4% Headache 16% 16% 17% 18% 11% 6% Digestive System Nausea 3% 5% 10% 0% 11% 0% Gastroenteritis 2% 2% 0% 0% 6% 4% Nervous System Insomnia 6% 4% 3% 3% 0% 8% Emotional Lability 1% 1% 0% 0% 6% 0% Respiratory System Upper Respiratory Tract Infection 18% 15% 10% 6% 15% 19% Sinusitis 7% 11% 7% 0% 15% 10% Metabolic and Nutritional Weight Increase 0% 0% 0% 0% 9% 6% Urogenital System Breast Pain 24% 10% 21% 0% 17% 8% Post-Menopausal Bleeding 5% 15% 10% 3% 11% 0% Uterine Fibroid 5% 4% 0% 0% 4% 8% Ovarian Cyst 3% 2% 7% 0% 0% 8% Resistance Mechanism Infection Viral 4% 6% 0% 3% 6% 6% Moniliasis Genital 4% 7% 0% 0% 6% 0% Secondary Terms Injury Accidental 4% 3% 3% 0% 17%* 4%* Other Events 2% 3% 3% 0% 6% 4% * including one upper extremity fracture in each group Adverse reactions reported with estradiol and norethindrone acetate 0.5 mg/0.1 mg by investigators during clinical trials regardless of causality assessment are shown in Table 2.
TABLE 2 ALL TREATMENT-EMERGENT ADVERSE REACTIONS REGARDLESS OF RELATIONSHIP REPORTED AT A FREQUENCY OF ≥ 5 PERCENT WITH ESTRADIOL AND NORETHINDRONE ACETATE
0.5MG/0.1 MG Estradiol and Norethindrone Acetate 0.5 mg/0.1 mg (n=194) Placebo (n=200) Body as a Whole Back Pain Headache Pain in extremity 10% 22% 5% 4% 19% 4% Digestive System Nausea Diarrhea 5% 6% 4% 6% Respiratory System Nasopharyngitis 21% 18% Urogenital System Endometrial thickening Vaginal hemorrhage 10% 26% 4% 12%
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of estradiol and norethindrone acetate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Genitourinary System Changes in vaginal bleeding pattern and abnormal withdrawal bleeding or flow; breakthrough bleeding; spotting; dysmenorrhea, increase in size of uterine leiomyomata; vaginitis, including vaginal candidiasis; change in amount of cervical secretion; changes in cervical ectropion; pre-menstrual-like syndrome; cystitis-like syndrome; ovarian cancer; endometrial hyperplasia; endometrial…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Coadministration of estradiol with norethindrone acetate did not elicit any apparent influence on the pharmacokinetics of norethindrone acetate. Similarly, no relevant interaction of norethindrone acetate on the pharmacokinetics of estradiol was found within the NETA dose range investigated in a single dose study. Estradiol In-vitro and in-vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4).
Therefore, inducers or inhibitors of CYP3A4 may affect estrogen drug metabolism. Inducers of CYP3A4 such as St. John's wort ( Hypericum perforatum ) preparations, phenobarbital, carbamazepine, and rifampin may reduce plasma concentrations of estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile.
Inhibitors of CYP3A4 such as erythromycin, clarithromycin, ketoconazole, itraconazole, ritonavir and grapefruit juice may increase plasma concentrations of estrogens and result in adverse reactions. Norethindrone Acetate Drugs or herbal products that induce or inhibit cytochrome P-450 enzymes, including CYP3A4, may decrease or increase the serum concentrations of norethindrone. Inducers and/or inhibitors of CYP3A4 may affect estrogen drug metabolism and decrease or increase the estrogen plasma concentration.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Estradiol and norethindrone acetate tablets are not indicated for use in pregnancy. There are no data with the use of estradiol and norethindrone acetate in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalities and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogen and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary Estrogens plus progestogens are present in human milk and can reduce milk production in breastfeeding women. This reduction can occur at any time but is less likely to occur once breastfeeding is well established. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for estradiol and norethindrone acetate and any potential adverse effects on the breastfed child from estradiol and norethindrone acetate or from the underlying maternal condition.
8.4Pediatric Use Estradiol and norethindrone acetate are not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing estradiol and norethindrone acetate to determine whether those over 65 years of age differ from younger subjects in their response to estradiol and norethindrone acetate. The Women’s Health Initiative Studies In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Clinical Studies ( 14.5 )] .
In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.5 )] . The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen plus progestin or estrogen-alone when compared to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Estradiol and norethindrone acetate tablets are not indicated for use in pregnancy. There are no data with the use of estradiol and norethindrone acetate in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalities and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogen and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Estradiol and norethindrone acetate are not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing estradiol and norethindrone acetate to determine whether those over 65 years of age differ from younger subjects in their response to estradiol and norethindrone acetate. The Women’s Health Initiative Studies In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Clinical Studies ( 14.5 )] .
In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.5 )] . The Women’s Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen plus progestin or estrogen-alone when compared to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of estrogen plus progestogen may cause nausea, vomiting, breast tenderness, abdominal pain, drowsiness and fatigue, and withdrawal bleeding may occur in women. Treatment of overdose consists of discontinuation of Mimvey therapy with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate-conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH), and FSH through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women. Progestin compounds enhance cellular differentiation and generally oppose the actions of estrogens by decreasing estrogen receptor levels, increasing local metabolism of estrogens to less active metabolites, or inducing gene products that blunt cellular responses to estrogen. Progestins exert their effects in target cells by binding to specific progesterone receptors that interact with progesterone response elements in target genes.
Progesterone receptors have been identified in the female reproductive tract, breast, pituitary, hypothalamus, and central nervous system.
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to estradiol and norethindrone acetate tablets nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
12.3Pharmacokinetics Absorption Estradiol Estradiol is absorbed through the gastrointestinal tract. Following oral administration of estradiol and norethindrone acetate tablets, peak plasma estradiol concentrations are reached within 5 to 8 hours. The oral bioavailability of estradiol following administration of estradiol and norethindrone acetate 1 mg/0.5 mg when compared to a combination oral solution is 53%.
Administration of estradiol and norethindrone acetate 1 mg/0.5 mg with food did not modify the bioavailability of estradiol. Norethindrone Acetate After oral administration, norethindrone acetate is absorbed and transformed to norethindrone. Norethindrone reaches a peak plasma concentration within 0.5 to 1.5 hours after the administration of estradiol and norethindrone acetate tablets.
The oral bioavailability of norethindrone following administration of estradiol and norethindrone acetate 1 mg/0.5 mg when compared to a combination oral solution is 100%. Administration of estradiol and norethindrone acetate 1 mg/0.5 mg with food increases norethindrone AUC 0-72 by 19% and decreases C max by 36%. The pharmacokinetic parameters of estradiol (E 2 ), estrone (E 1 ), and norethindrone (NET) following oral administration of 1 estradiol and norethindrone acetate 1 mg/0.5 mg or 2 estradiol and norethindrone acetate 0.5 mg/0.1 mg tablet(s) to healthy postmenopausal women are summarized in Table 3.
TABLE 3 PHARMACOKINETIC PARAMETERS AFTER ADMINISTRATION OF 1 TABLET OF ESTRADIOL AND NORETHINDRONE ACETATE 1 MG/0.5 MG OR 2 TABLETS OF ESTRADIOL AND NORETHINDRONE ACETATE
0.5MG/0.1 MG TO HEALTHY POSTMENOPAUSAL WOMEN 1 x Estradiol and Norethindrone Acetate 1 mg/0.5 mg (n=24) Mean a (%CV) b 2 x Estradiol and…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate-conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH), and FSH through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women. Progestin compounds enhance cellular differentiation and generally oppose the actions of estrogens by decreasing estrogen receptor levels, increasing local metabolism of estrogens to less active metabolites, or inducing gene products that blunt cellular responses to estrogen. Progestins exert their effects in target cells by binding to specific progesterone receptors that interact with progesterone response elements in target genes.
Progesterone receptors have been identified in the female reproductive tract, breast, pituitary, hypothalamus, and central nervous system.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Mimvey ® (estradiol and norethindrone acetate tablets, USP) 1 mg/0.5 mg is available as white, round, biconvex, film-coated, unscored tablet, debossed with stylized b on one side and 34 on the other side. Available in blister cards of 28 tablets: 1 blister card per carton (NDC 0093-5455-28) 5 blister cards per carton (NDC 0093-5455-42)
16.2Storage and Handling Store in a dry place protected from light. Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
📦 Storage and Handling ▾
16.2Storage and Handling Store in a dry place protected from light. Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Mimvey ® (estradiol and norethindrone acetate tablets, USP) 1 mg/0.5 mg is a single tablet for oral administration containing 1 mg of estradiol, USP and 0.5 mg of norethindrone acetate, USP and the following inactive ingredients: colloidal silicon dioxide, copovidone, corn starch, hypromellose, lactose monohydrate, magnesium stearate, polyethylene glycol, polysorbate 80, and titanium dioxide. Estradiol (E 2 ), an estrogen, is a white or almost white crystalline powder. Its chemical name is estra-1, 3, 5 (10)-triene-3, 17β-diol hemihydrate.
The structural formula of E 2 is as follows: Estradiol, USP C 18 H 24 O 2 , 1 / 2 H 2 O M.W. 281.4 Norethindrone acetate (NETA), a progestin, is a white or yellowish-white crystalline powder. Its chemical name is 17β-acetoxy-19-nor-17α-pregn-4-en-20-yn-3-one.
The structural formula of NETA is as follows: Norethindrone Acetate, USP C 22 H 28 O 3 M.W. 340.5 Estradiol Structure Norethindrone Acetate Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise women to read the FDA-approved patient labeling (Patient Information) Vaginal Bleeding Inform postmenopausal women to report any vaginal bleeding to their healthcare provider as soon as possible [see Warnings and Precautions ( 5.2 )] . Possible Serious Adverse Reactions with Estrogen Plus Progestogen Therapy Inform postmenopausal women of possible serious adverse reactions of estrogen plus progestogen therapy including Cardiovascular Disorders, Malignant Neoplasms, and Probable Dementia [see Warnings and Precautions ( 5.1 , 5.2 , 5.3 )] .
Possible Common Adverse Reactions with Estrogen Plus Progestogen Therapy Inform postmenopausal women of possible less serious but common adverse reactions of estrogen plus progestogen therapy such as headache, breast pain and tenderness, nausea and vomiting. Manufactured For: Teva Pharmaceuticals USA, Inc. North Wales, PA 19454 Rev.
H 5/2024