
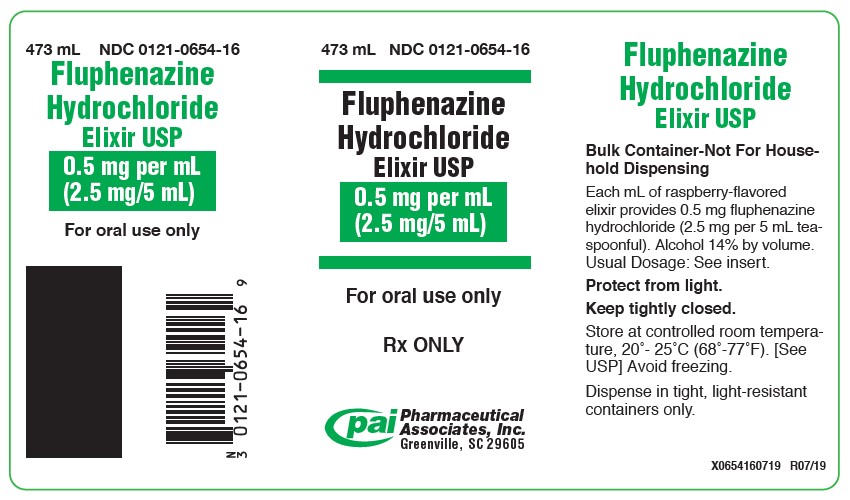
Fluphenazine Hydrochloride .5 mg/mL Elixir, 473 mL
Other active recalls for Fluphenazine Hydrochloride (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phenothiazine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Fluphenazine is an antipsychotic medication used to manage psychotic disorders — most commonly schizophrenia. It's available as tablets, an oral liquid, and injections. The long-ac...
- Fluphenazine Decanoate Injection is chemically designed to release slowly after a single shot, so one injection can keep working for up to four weeks or even longer. The regular ta...
- How is the long-acting injection different from the tablets or regular shot?
- The most common side effects involve movement — things like muscle stiffness, a restless, fidgety feeling, or tremors. These can often be managed by adjusting your dose or adding a...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.4689 | $221.79 / 473 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fluphenazine Hydrochloride .5 mg/mLthis 00121-0654-16 | PAI | 473 ml | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00121-0654-02 | 60 mL in 1 BOTTLE (0121-0654-02) | 2010-08-31 | Active |
| 00121-0654-16 You're viewing this | 473 mL in 1 BOTTLE (0121-0654-16) | 2010-08-31 | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 00121-0654-16?
What is the difference between NDC 00121-0654-16 and NDC 00121-0654-02?
What NDC number is used to bill for this package of Fluphenazine Hydrochloride .5 mg/mL Elixir?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of seventeen placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear.
Fluphenazine Hydrochloride Elixir USP is not approved for the treatment of patients with dementia-related psychosis ( see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Fluphenazine hydrochloride elixir is indicated in the management of manifestations of psychotic disorders. Fluphenazine hydrochloride has not been shown effective in the management of behavioral complications in patients with mental retardation.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Depending on the severity and duration of symptoms, total daily dosage for adult psychotic patients may range initially from 2.5 to 10.0 mg and should be divided and given at six- to eight-hour intervals. The smallest amount that will produce the desired results must be carefully determined for each individual, since optimal dosage levels of this potent drug may vary from patient to patient. In general, the oral dose has been found to be approximately two to three times the parenteral dose of fluphenazine.
Treatment is best instituted with a low initial dosage, which may be increased, if necessary, until the desired clinical effects are achieved. Therapeutic effect is often achieved with doses under 20 mg daily. Patients remaining severely disturbed or inadequately controlled may require upward titration of dosage.
Daily doses up to 40 mg may be necessary; controlled clinical studies have not been performed to demonstrate safety of prolonged administration of such doses. When symptoms are controlled, dosage can generally be reduced gradually to daily maintenance doses of 1 or 5 mg, often given as a single daily dose. Continued treatment is needed to achieve maximum therapeutic benefits; further adjustments in dosage may be necessary during the course of therapy to meet the patient's requirements.
For psychotic patients who have been stabilized on a fixed daily dosage of orally administered fluphenazine hydrochloride dosage forms, conversion to the long-acting injectable fluphenazine decanoate may be indicated (see package insert for fluphenazine decanoate injection for conversion information). For geriatric patients, the suggested starting dose is 1 to 2.5 mg daily, adjusted according to the response of the patient. Fluphenazine hydrochloride injection is useful when psychotic patients are unable or unwilling to take oral therapy.
⛔ Contraindications ▾
CONTRAINDICATIONS Phenothiazines are contraindicated in patients with suspected or established subcortical brain damage, in patients receiving large doses of hypnotics, and in comatose or severely depressed states. The presence of blood dyscrasia or liver damage precludes the use of fluphenazine hydrochloride. Fluphenazine hydrochloride is contraindicated in patients who have shown hypersensitivity to fluphenazine; cross sensitivity to phenothiazine derivatives may occur.
⚠️ Warnings ▾
WARNINGS Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Fluphenazine Hydrochloride Elixir USP is not approved for the treatment of patients with dementia-related psychosis ( see BOXED WARNING ). Tardive Dyskinesia Tardive dyskinesia, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements may develop in patients treated with neuroleptic (antipsychotic) drugs.
Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of neuroleptic treatment, which patients are likely to develop the syndrome. Whether neuroleptic drug products differ in their potential to cause tardive dyskinesia is unknown. Both the risk of developing the syndrome and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of neuroleptic drugs administered to the patient increase.
However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses. There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if neuroleptic treatment is withdrawn. Neuroleptic treatment, itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and thereby may possibly mask the underlying disease process.
The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown. Given these considerations, neuroleptics should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic neuroleptic treatment should generally be reserved for patients who suffer from a chronic illness that, 1) is known to respond to neuroleptic drugs, and, 2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate.
In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically. If signs and symptoms of tardive dyskinesia appear in a patient on neuroleptics, drug discontinuation should be considered.
However, some patients may require treatment despite the presence of the syndrome. (For further information about the description of tardive dyskinesia and its clinical detection, please refer to the sections on PRECAUTIONS, Information for Patients and ADVERSE REACTIONS, Tardive Dyskinesia .) Neuroleptic Malignant Syndrome (NMS) A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) has been reported in association with antipsychotic drugs. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmias).
The diagnostic evaluation of patients with this syndrome is complicated. In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.) and untreated or inadequately treated extrapyramidal signs and symptoms. Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever and primary central nervous system pathology.
The management of NMS should include: 1) immediate discontinuation of antipsychotic drugs and other drugs not essential to concurrent therapy; 2) intensive symptomatic treatment and medical monitoring; and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no gen…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Central Nervous System The side effects most frequently reported with phenothiazine compounds are extrapyramidal symptoms including pseudoparkinsonism, dystonia, dyskinesia, akathisia, oculogyric crises, opisthotonos, and hyperreflexia. Most often these extrapyramidal symptoms are reversible; however, they may be persistent (see below). With any given phenothiazine derivative, the incidence and severity of such reactions depend more on individual patient sensitivity than on other factors, but dosage level and patient age are also determinants.
Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs.
An elevated risk of acute dystonia is observed in males and younger age groups. Extrapyramidal reactions may be alarming, and the patient should be forewarned and reassured. These reactions can usually be controlled by administration of antiparkinsonian drugs such as Benztropine Mesylate or Intravenous Caffeine and Sodium Benzoate Injection, and by subsequent reduction in dosage.
Tardive Dyskinesia See WARNINGS. The syndrome is characterized by involuntary choreoathetoid movements which variously involve the tongue, face, mouth, lips, or jaw (e.g., protrusion of the tongue, puffing of cheeks, puckering of the mouth, chewing movements), trunk and extremities. The severity of the syndrome and the degree of impairment produced vary widely.
The syndrome may become clinically recognizable either during treatment, upon dosage reduction, or upon withdrawal of treatment. Early detection of tardive dyskinesia is important. To increase the likelihood of detecting the syndrome at the earliest possible time, the dosage of neuroleptic drug should be reduced periodically (if clinically possible) and the patient observed for signs of the disorder.
This maneuver is critical, since neuroleptic drugs may mask the signs of the syndrome. Other CNS Effects Occurrences of neuroleptic malignant syndrome (NMS) have been reported in patients on neuroleptic therapy (see WARNINGS, Neuroleptic Malignant Syndrome). Leukocytosis, elevated CPK, liver function abnormalities, and acute renal failure may also occur with NMS.
Drowsiness or lethargy, if they occur, may necessitate a reduction in dosage; the induction of a catatonic-like state has been known to occur with dosages of fluphenazine far in excess of the recommended amounts. As with other phenothiazine compounds, reactivation or aggravation of psychotic processes may be encountered. Phenothiazine derivatives have been known to cause, in some patients, restlessness, excitement, or bizarre dreams.
Autonomic Nervous System Hypertension and fluctuation in blood pressure have been reported with fluphenazine hydrochloride. Hypotension has rarely presented a problem with fluphenazine. However, patients with pheochromocytoma, cerebral vascular or renal insufficiency, or a severe cardiac reserve deficiency (such as mitral insufficiency) appear to be particularly prone to hypotensive reactions with phenothiazine compounds, and should therefore be observed closely when the drug is administered.
If severe hypotension should occur, supportive measures including the use of intravenous vasopressor drugs should be instituted immediately. Levarterenol Bitartrate Injection is the most suitable drug for this purpose; epinephrine should not be used since phenothiazine derivatives have been found to reverse its action, resulting in a further lowering of blood pressure. Autonomic reactions including nausea and loss of appetite, salivation, polyuria, perspiration, dry…
🤰 Pregnancy ▾
Usage In Pregnancy Non-teratogenic Effects Neonates exposed to antipsychotic drugs, during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
Fluphenazine hydrochloride should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The safety for the use of this drug during pregnancy has not been established; therefore, the possible hazards should be weighed against the potential benefits when administering this drug to pregnant patients.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Fluphenazine hydrochloride has activity at all levels of the central nervous system as well as on multiple organ systems. The mechanism whereby its therapeutic action is exerted is unknown.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Fluphenazine Hydrochloride Elixir USP 0.5 mg/mL (2.5 mg per 5 mL teaspoonful), available as an orange-colored, raspberry flavored elixir and is supplied in the following sizes: 60 mL bottle with calibrated dropper NDC 0121-0654-02 473 mL bottle NDC 0121-0654-16 Storage Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature]. Avoid freezing. Dispense in tight, light-resistant containers only.
📦 Storage and Handling ▾
Storage Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature]. Avoid freezing. Dispense in tight, light-resistant containers only.
📋 Description ▾
DESCRIPTION Fluphenazine hydrochloride is a trifluoromethyl phenothiazine derivative intended for the management of schizophrenia. Fluphenazine hydrochloride is described chemically as 4-[3-[2-(Trifluoromethyl)phenothiazin-10-yl]propyl]-1-piperazineethanol dihydrochloride and its molecular formula is C 22 H 26 F 3 N 3 OS • 2HCl. The structural formula is shown below: Each mL of fluphenazine hydrochloride elixir for oral administration, contains 0.5 mg fluphenazine hydrochloride and alcohol 14% (v/v).
Inactive ingredients: colorant (FD&C Yellow No. 6), flavor, glycerin, purified water, sodium benzoate, and sucrose. The pH range is 5.3 to 5.8.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Given the likelihood that some patients exposed chronically to neuroleptics will develop tardive dyskinesia, it is advised that all patients in whom chronic use is contemplated be given, if possible, full information about this risk. The decision to inform patients and/or their guardians must obviously take into account the clinical circumstances and the competency of the patient to understand the information provided.