
Valium diazepam 5 mg Tablet, 500-count — NDC 0140-0005-14 (Billing 00140-0005-14)
This is a package of 500 tablets of Valium diazepam 5 mg Tablet from Roche Laboratories Inc., marketed since Nov 1963 and currently FDA-listed, this package's marketing is listed to end Dec 2027.
NDC database record
One package, one record: these facts belong to NDC 0140-0005-14 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0140 labeler · 0005 product · 14 package
- Package marketed since
- Nov 15, 1963
- Package marketing ended
- Dec 9, 2027
- Sample package
- No — commercial package
- Billing quantity
- 500 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0140000514 6
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003768
- GCN: 14222
- GPI-14 (Medi-Span): 57100040000310
- HICL (First Databank): 001615
- AHFS class code: 28:12.08.00
- RxCUI (RxNorm): 104699
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Diazepam is used to relieve anxiety, control agitation caused by alcohol withdrawal, control muscle spasms and stiffness caused by certain nerve disorders, and to control seizures. Diazepam is in a class of medications called benzodiazepines. It works by calming abnormal overactivity in the brain.
Read the full MedlinePlus article ↗- It depends on the form. Tablets and oral solution are used for anxiety, alcohol withdrawal symptoms, muscle spasm, and as an add-on for seizure disorders. Valtoco nasal spray and r...
- No. Alcohol adds to the sedation and can slow your breathing. Avoid it while on diazepam.
- This combination is risky. It can cause extreme sleepiness, slowed breathing, coma, and death. Tell your prescriber about every opioid you take.
- Is it safe with my opioid pain medicine?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Diazepam — tap one for details:
Diazepam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00140-0005-01 0140-0005-01 Main listing | 1 BOTTLE, PLASTIC in 1 CARTON / 100 TABLET in 1 BOTTLE, PLASTIC | 1963-11-15 | Dec 9, 2027 | Active |
| 00140-0005-14 You're viewing this | 1 BOTTLE, PLASTIC in 1 CARTON / 500 TABLET in 1 BOTTLE, PLASTIC | 1963-11-15 | Dec 9, 2027 | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00140-0005-01?
What NDC number is used to bill for this package of Valium diazepam 5 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diazepam 5 mg 00172-3926-60 | Teva | 100 tablets | $0.028 | AB | Availability likely | — |
| Diazepam 5 mg 00378-0345-01 | Mylan | 100 tablets | $0.028 | AB | Availability likely | — |
| Diazepam 5 mg 51079-0285-20 | Mylan | 100 tablets | $0.028 | AB | Availability likely | — |
| Diazepam 5 mg 59651-0653-01 | Aurobindo | 100 tablets | $0.028 | AB | Availability likely | — |
| Diazepam 5 mg 62135-0787-90 | Chartwell | 90 tablets | $0.028 | — | Availability likely | — |
| Valium 5 mgthis 00140-0005-14 | Roche | 500 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 11534-0203-01 | Sunrise | 100 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 43063-0970-04 | PD-Rx | 4 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 48433-0028-20 | Safecor | 100 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 50090-1913-00 | A-S | 15 tablets | — | AB | Discontinued | — |
| Diazepam 5 mg 50090-2249-00 | A-S | 2 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 55154-5554-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 58118-3926-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 61919-0409-02 | Direct_Rx | 2 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 63187-0173-01 | Proficient | 1 tablet | — | AB | FDA listed | — |
| Diazepam 5 mg 63629-1523-00 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 67046-0943-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 68071-3682-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 68071-3686-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 68071-4770-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 68071-4922-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 68788-8466-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 70518-1713-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 71335-1584-00 | Bryant | 120 tablets | — | AB | Discontinued | — |
| Diazepam 5 mg 71335-2239-00 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 71610-0270-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 76420-0315-00 | ASCLEMED | 1000 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 76420-0533-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 80425-0496-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Diazepam 5 mg 87441-0026-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Valium 5 mg 80725-0005-01 | Waylis | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Diazepam inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 776XM7047L
Calcium stearate is a white powder derived from stearic acid and calcium. It works as a lubricant and glidant to help the medicine flow smoothly during manufacturing and prevent ingredients from sticking to equipment.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Roche Laboratories Inc. labeler code 00140
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation (see WARNINGS and PRECAUTIONS ). The use of benzodiazepines, including VALIUM, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes.
Before prescribing VALIUM and throughout treatment, assess each patient's risk for abuse, misuse, and addiction (see WARNINGS ) . The continued use of benzodiazepines, including VALIUM, may lead to clinically significant physical dependence. The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose.
Abrupt discontinuation or rapid dosage reduction of VALIUM after continued use may precipitate acute withdrawal reactions, which can be life-threatening. To reduce the risk of withdrawal reactions, use a gradual taper to discontinue VALIUM or reduce the dosage (see DOSAGE AND ADMINISTRATION and WARNINGS ) .
🎯 Indications and Usage ▾
INDICATIONS Valium is indicated for the management of anxiety disorders or for the short-term relief of the symptoms of anxiety. Anxiety or tension associated with the stress of everyday life usually does not require treatment with an anxiolytic. In acute alcohol withdrawal, Valium may be useful in the symptomatic relief of acute agitation, tremor, impending or acute delirium tremens and hallucinosis.
Valium is a useful adjunct for the relief of skeletal muscle spasm due to reflex spasm to local pathology (such as inflammation of the muscles or joints, or secondary to trauma), spasticity caused by upper motor neuron disorders (such as cerebral palsy and paraplegia), athetosis, and stiff-man syndrome. Oral Valium may be used adjunctively in convulsive disorders, although it has not proved useful as the sole therapy. The effectiveness of Valium in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies.
The physician should periodically reassess the usefulness of the drug for the individual patient.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Dosage should be individualized for maximum beneficial effect. While the usual daily dosages given below will meet the needs of most patients, there will be some who may require higher doses. In such cases dosage should be increased cautiously to avoid adverse effects.
ADULTS: USUAL DAILY DOSE: Management of Anxiety Disorders and Relief of Symptoms of Anxiety. Depending upon severity of symptoms—2 mg to 10 mg, 2 to 4 times daily Symptomatic Relief in Acute Alcohol Withdrawal. 10 mg, 3 or 4 times during the first 24 hours, reducing to 5 mg, 3 or 4 times daily as needed Adjunctively for Relief of Skeletal Muscle Spasm.
2 mg to 10 mg, 3 or 4 times daily Adjunctively in Convulsive Disorders. 2 mg to 10 mg, 2 to 4 times daily Geriatric Patients, or in the presence of debilitating disease. 2 mg to 2.5 mg, 1 or 2 times daily initially; increase gradually as needed and tolerated PEDIATRIC PATIENTS: Because of varied responses to CNS-acting drugs, initiate therapy with lowest dose and increase as required.
Not for use in pediatric patients under 6 months. 1 mg to 2.5 mg, 3 or 4 times daily initially; increase gradually as needed and tolerated Discontinuation or Dosage Reduction of Valium To reduce the risk of withdrawal reactions, use a gradual taper to discontinue Valium or reduce the dosage. If a patient develops withdrawal reactions, consider pausing the taper or increasing the dosage to the previous tapered dosage level.
Subsequently decrease the dosage more slowly (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE: Dependence ).
⛔ Contraindications ▾
CONTRAINDICATIONS Valium is contraindicated in patients with a known hypersensitivity to diazepam and, because of lack of sufficient clinical experience, in pediatric patients under 6 months of age. Valium is also contraindicated in patients with myasthenia gravis, severe respiratory insufficiency, severe hepatic insufficiency, and sleep apnea syndrome. It may be used in patients with open-angle glaucoma who are receiving appropriate therapy, but is contraindicated in acute narrow-angle glaucoma.
⚠️ Warnings ▾
WARNINGS Risks from Concomitant Use with Opioids Concomitant use of benzodiazepines, including Valium, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe Valium concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. In patients already receiving an opioid analgesic, prescribe a lower initial dose of Valium than indicated in the absence of an opioid and titrate based on clinical response. If an opioid is initiated in a patient already taking Valium, prescribe a lower initial dose of the opioid and titrate based upon clinical response.
Advise both patients and caregivers about the risks of respiratory depression and sedation when Valium is used with opioids. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see PRECAUTIONS: Drug Interactions ). Abuse, Misuse, and Addiction The use of benzodiazepines, including Valium, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death (see DRUG ABUSE AND DEPENDENCE: Abuse ). Before prescribing Valium and throughout treatment, assess each patient's risk for abuse, misuse, and addiction (e.g., using a standardized screening tool).
Use of Valium, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of Valium along with monitoring for signs and symptoms of abuse, misuse, and addiction. Prescribe the lowest effective dosage; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug. If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
Dependence and Withdrawal Reactions To reduce the risk of withdrawal reactions, use a gradual taper to discontinue Valium or reduce the dosage (a patient-specific plan should be used to taper the dose) (see DOSAGE AND ADMINISTRATION: Discontinuation or Dosage Reduction of Valium ). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines, including Valium, may lead to clinically significant physical dependence.
Abrupt discontinuation or rapid dosage reduction of Valium after continued use, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures) (see DRUG ABUSE AND DEPENDENCE: Dependence ). Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months (see DRUG ABUSE AND DEPENDENCE: Dependence ). Valium is not recommended in the treatment of psychotic patients and should not be employed instead of appropriate treatment.
Since Valium has a central nervous system depressant effect,… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Side effects most commonly reported were drowsiness, fatigue, muscle weakness, and ataxia. The following have also been reported: Central Nervous System : confusion, depression, dysarthria, headache, slurred speech, tremor, vertigo Gastrointestinal System : constipation, nausea, gastrointestinal disturbances Special Senses : blurred vision, diplopia, dizziness Cardiovascular System : hypotension Psychiatric and Paradoxical Reactions : stimulation, restlessness, acute hyperexcited states, anxiety, agitation, aggressiveness, irritability, rage, hallucinations, psychoses, delusions, increased muscle spasticity, insomnia, sleep disturbances, and nightmares.
Inappropriate behavior and other adverse behavioral effects have been reported when using benzodiazepines. Should these occur, use of the drug should be discontinued. They are more likely to occur in children and in the elderly.
Urogenital System : incontinence, changes in libido, urinary retention Skin and Appendages : skin reactions Laboratories : elevated transaminases and alkaline phosphatase Other : changes in salivation, including dry mouth, hypersalivation Antegrade amnesia may occur using therapeutic dosages, the risk increasing at higher dosages. Amnestic effects may be associated with inappropriate behavior. Minor changes in EEG patterns, usually low-voltage fast activity, have been observed in patients during and after Valium therapy and are of no known significance.
Because of isolated reports of neutropenia and jaundice, periodic blood counts and liver function tests are advisable during long-term therapy. Postmarketing Experience Injury, Poisoning and Procedural Complications There have been reports of falls and fractures in benzodiazepine users. The risk is increased in those taking concomitant sedatives (including alcohol), and in the elderly.
🔄 Drug Interactions ▾
Drug Interactions Opioids The concomitant use of benzodiazepines and opioids increases the risk of respiratory depression because of actions at different receptor sites in the CNS that control respiration. Benzodiazepines interact at GABA A sites and opioids interact primarily at mu receptors. When benzodiazepines and opioids are combined, the potential for benzodiazepines to significantly worsen opioid-related respiratory depression exists.
Limit dosage and duration of concomitant use of benzodiazepines and opioids, and monitor patients closely for respiratory depression and sedation. Centrally Acting Agents If Valium is to be combined with other centrally acting agents, careful consideration should be given to the pharmacology of the agents employed particularly with compounds that may potentiate or be potentiated by the action of Valium, such as phenothiazines, antipsychotics, anxiolytics/sedatives, hypnotics, anticonvulsants, narcotic analgesics, anesthetics, sedative antihistamines, narcotics, barbiturates, MAO inhibitors and other antidepressants.
Alcohol Concomitant use with alcohol is not recommended due to enhancement of the sedative effect. Antacids Diazepam peak concentrations are 30% lower when antacids are administered concurrently. However, there is no effect on the extent of absorption.
The lower peak concentrations appear due to a slower rate of absorption, with the time required to achieve peak concentrations on average 20 - 25 minutes greater in the presence of antacids. However, this difference was not statistically significant. Compounds Which Inhibit Certain Hepatic Enzymes There is a potentially relevant interaction between diazepam and compounds which inhibit certain hepatic enzymes (particularly cytochrome P450 3A and 2C19).
Data indicate that these compounds influence the pharmacokinetics of diazepam and may lead to increased and prolonged sedation. At present, this reaction is known to occur with cimetidine, ketoconazole, fluvoxamine, fluoxetine, and omeprazole. Phenytoin There have also been reports that the metabolic elimination of phenytoin is decreased by diazepam.
🤰 Pregnancy ▾
Pregnancy Category D (see WARNINGS: Pregnancy ).
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients below the age of 6 months have not been established.
🧓 Geriatric Use ▾
Geriatric Use In elderly patients, it is recommended that the dosage be limited to the smallest effective amount to preclude the development of ataxia or oversedation (2 mg to 2.5 mg once or twice daily, initially to be increased gradually as needed and tolerated). Extensive accumulation of diazepam and its major metabolite, desmethyldiazepam, has been noted following chronic administration of diazepam in healthy elderly male subjects. Metabolites of this drug are known to be substantially excreted by the kidney, and the risk of toxic reactions may be greater in patients with impaired renal function.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
OVERDOSAGE Overdose of benzodiazepines is usually manifested by central nervous system depression ranging from drowsiness to coma. In mild cases, symptoms include drowsiness, confusion, and lethargy. In more serious cases, symptoms may include ataxia, diminished reflexes, hypotonia, hypotension, respiratory depression, coma (rarely), and death (very rarely).
Overdose of benzodiazepines in combination with other CNS depressants (including alcohol) may be fatal and should be closely monitored. Management of Overdosage Following overdose with oral benzodiazepines, general supportive measures should be employed including the monitoring of respiration, pulse, and blood pressure. Vomiting should be induced (within 1 hour) if the patient is conscious.
Gastric lavage should be undertaken with the airway protected if the patient is unconscious. Intravenous fluids should be administered. If there is no advantage in emptying the stomach, activated charcoal should be given to reduce absorption.
Special attention should be paid to respiratory and cardiac function in intensive care. General supportive measures should be employed, along with intravenous fluids, and an adequate airway maintained. Should hypotension develop, treatment may include intravenous fluid therapy, repositioning, judicious use of vasopressors appropriate to the clinical situation, if indicated, and other appropriate countermeasures.
Dialysis is of limited value. As with the management of intentional overdosage with any drug, it should be considered that multiple agents may have been ingested. Flumazenil, a specific benzodiazepine-receptor antagonist, is indicated for the complete or partial reversal of the sedative effects of benzodiazepines and may be used in situations when an overdose with a benzodiazepine is known or suspected.
Prior to the administration of flumazenil, necessary measures should be instituted to secure airway, ventilation and intravenous access. Flumazenil is intended as an adjunct to, not as a substitute for, proper management of benzodiazepine overdose. Patients treated with flumazenil should be monitored for resedation, respiratory depression and other residual benzodiazepine effects for an appropriate period after treatment.
The prescriber should be aware of a risk of seizure in association with flumazenil treatment, particularly in long-term benzodiazepine users and in cyclic antidepressant overdose. Caution should be observed in the use of flumazenil in epileptic patients treated with benzodiazepines. The complete flumazenil package insert, including CONTRAINDICATIONS , WARNINGS , and PRECAUTIONS , should be consulted prior to use.
Withdrawal symptoms of the barbiturate type have occurred after the discontinuation of benzodiazepines (see DRUG ABUSE AND DEPENDENCE ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Diazepam is a benzodiazepine that exerts anxiolytic, sedative, muscle-relaxant, anticonvulsant and amnestic effects. Most of these effects are thought to result from a facilitation of the action of gamma aminobutyric acid (GABA), an inhibitory neurotransmitter in the central nervous system. Pharmacokinetics Absorption After oral administration >90% of diazepam is absorbed and the average time to achieve peak plasma concentrations is 1 – 1.5 hours with a range of 0.25 to 2.5 hours.
Absorption is delayed and decreased when administered with a moderate fat meal. In the presence of food mean lag times are approximately 45 minutes as compared with 15 minutes when fasting. There is also an increase in the average time to achieve peak concentrations to about 2.5 hours in the presence of food as compared with 1.25 hours when fasting.
This results in an average decrease in C max of 20% in addition to a 27% decrease in AUC (range 15% to 50%) when administered with food. Distribution Diazepam and its metabolites are highly bound to plasma proteins (diazepam 98%). Diazepam and its metabolites cross the blood-brain and placental barriers and are also found in breast milk in concentrations approximately one tenth of those in maternal plasma (days 3 to 9 post-partum).
In young healthy males, the volume of distribution at steady-state is 0.8 to
1.0L/kg. The decline in the plasma concentration-time profile after oral administration is biphasic. The initial distribution phase has a half-life of approximately 1 hour, although it may range up to >3 hours.
Metabolism Diazepam is N-demethylated by CYP3A4 and 2C19 to the active metabolite N-desmethyldiazepam, and is hydroxylated by CYP3A4 to the active metabolite temazepam. N-desmethyldiazepam and temazepam are both further metabolized to oxazepam. Temazepam and oxazepam are largely eliminated by glucuronidation.
Elimination The initial distribution phase is followed by a prolonged terminal elimination phase (half-life up to 48 hours). The terminal elimination half-life of the active metabolite N-desmethyldiazepam is up to 100 hours. Diazepam and its metabolites are excreted mainly in the urine, predominantly as their glucuronide conjugates.
The clearance of diazepam is 20 to 30 mL/min in young adults. Diazepam accumulates upon multiple dosing and there is some evidence that the terminal elimination half-life is slightly prolonged. Pharmacokinetics in Special Populations Children In children 3 - 8 years old the mean half-life of diazepam has been reported to be 18 hours.
Newborns In full term infants, elimination half-lives around 30 hours have been reported, with a longer average half-life of 54 hours reported in premature infants of 28 - 34 weeks gestational age and 8 - 81 days post-partum. In both premature and full term infants the active metabolite desmethyldiazepam shows evidence of continued accumulation compared to children. Longer half-lives in infants may be due to incomplete maturation of metabolic pathways.
Geriatric Elimination half-life increases by approximately 1 hour for each year of age beginning with a half-life of 20 hours at 20 years of age. This appears to be due to an increase in volume of distribution with age and a decrease in clearance. Consequently, the elderly may have lower peak concentrations, and on multiple dosing higher trough concentrations.
It will also take longer to reach steady-state. Conflicting information has been published on changes of plasma protein binding in the elderly. Reported changes in free drug may be due to significant decreases in plasma proteins due to causes other than simply aging.
Hepatic Insufficiency In mild and moderate cirrhosis, average half-life is increased. The average increase has been variously reported from 2-fold to 5-fold, with individual half-lives over 500 hours reported. There is also an increase in volume of distribution, and average clearance decreases by almost half.
Mean half-life is also prolonged w… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED For oral administration, Valium is supplied as round, flat-faced scored tablets with V-shaped perforation and beveled edges. Valium is available as follows: 2 mg, white - bottles of 100 (NDC 0140-0004-01); 5 mg, yellow - bottles of 100 (NDC 0140-0005-01) and 500 (NDC 0140-0005-14); 10 mg, blue - bottles of 100 (NDC 0140-0006-01) and 500 (NDC 0140-0006-14). Engraved on tablets: 2 mg—2 VALIUM ® (front) ROCHE (twice on scored side) 5 mg—5 VALIUM ® (front) ROCHE (twice on scored side) 10 mg—10 VALIUM ® (front) ROCHE (twice on scored side) Storage Store at room temperature 59º to 86ºF (15º to 30ºC).
Dispense in tight, light-resistant containers as defined in USP/NF.
📦 Storage and Handling ▾
Storage Store at room temperature 59º to 86ºF (15º to 30ºC). Dispense in tight, light-resistant containers as defined in USP/NF.
📋 Description ▾
DESCRIPTION Valium (diazepam) is a benzodiazepine derivative. The chemical name of diazepam is 7-chloro-1,3-dihydro-1-methyl-5-phenyl-2H-1,4-benzodiazepin-2-one. It is a colorless to light yellow crystalline compound, insoluble in water.
The empirical formula is C 16 H 13 ClN 2 O and the molecular weight is 284.75. The structural formula is as follows: Valium is available for oral administration as tablets containing 2 mg, 5 mg or 10 mg diazepam. In addition to the active ingredient diazepam, each tablet contains the following inactive ingredients: anhydrous lactose, corn starch, pregelatinized starch and calcium stearate with the following dyes: 5-mg tablets contain FD&C Yellow No.
6 and D&C Yellow No. 10; 10-mg tablets contain FD&C Blue No. 1.
Valium 2-mg tablets contain no dye. Chemical Structure
💬 Information for Patients ▾
Information for Patients Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when Valium is used with opioids and not to use such drugs concomitantly unless supervised by a health care provider. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see WARNINGS: Risks from Concomitant Use with Opioids and PRECAUTIONS: Drug Interactions ).
Abuse, Misuse, and Addiction Inform patients that the use of Valium, even at recommended dosages, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances. Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug (see WARNINGS: Abuse, Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE ).
Withdrawal Reactions Inform patients that the continued use of Valium may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of Valium may precipitate acute withdrawal reactions, which can be life-threatening. Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of Valium may require a slow taper (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE ).
Patients should be advised against the simultaneous ingestion of alcohol and other CNS-depressant drugs during Valium therapy. As is true of most CNS-acting drugs, patients receiving Valium should be cautioned against engaging in hazardous occupations requiring complete mental alertness, such as operating machinery or driving a motor vehicle.
💬 Medication Guide ▾
MEDICATION GUIDE VALIUM (VAL-ee-um) (diazepam) tablets, C-IV This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: February/2021 What is the most important information I should know about VALIUM?
VALIUM is a benzodiazepine medicine. Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system (CNS) depressants (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma and death. Get emergency help right away if any of the following happens: Shallow or slowed breathing, Breathing stops (which may lead to the heart stopping), Excessive sleepiness (sedation).
Do not drive or operate heavy machinery until you know how taking VALIUM with opioids affects you. Risk of abuse, misuse, and addiction. There is a risk of abuse, misuse, and addiction with benzodiazepines, including VALIUM, which can lead to overdose and serious side effects including coma and death.
Serious side effects including coma and death have happened in people who have abused or misused benzodiazepines, including VALIUM. These serious side effects may also include delirium, paranoia, suicidal thoughts or actions, seizures, and difficulty breathing. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these serious side effects.
You can develop an addiction even if you take VALIUM exactly as prescribed by your healthcare provider. Take VALIUM exactly as your healthcare provider prescribed. Do not share your VALIUM with other people.
Keep VALIUM in a safe place and away from children. Physical dependence and withdrawal reactions. VALIUM can cause physical dependence and withdrawal reactions.
Do not suddenly stop taking VALIUM. Stopping VALIUM suddenly can cause serious and life- threatening side effects, including, unusual movements, responses, or expressions, seizures, sudden and severe mental or nervous system changes, depression, seeing or hearing things that others do not see or hear, an extreme increase in activity or talking, losing touch with reality, and suicidal thoughts or actions. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these symptoms.
Some people who suddenly stop benzodiazepines have symptoms that can last for several weeks to more than 12 months, including, anxiety, trouble remembering, learning, or concentrating, depression, problems sleeping, feeling like insects are crawling under your skin, weakness, shaking, muscle twitching, burning or prickling feeling in your hands, arms, legs or feet, and ringing in your ears. Physical dependence is not the same as drug addiction. Your healthcare provider can tell you more about the differences between physical dependence and drug addiction.
Do not take more VALIUM than prescribed or take VALIUM for longer than prescribed. What is VALIUM? VALIUM is a prescription medicine used: to treat anxiety disorders for the short-term relief of the symptoms of anxiety to relieve the symptoms of alcohol withdrawal including agitation, shakiness (tremor), sudden and severe mental or nervous system changes (delirium tremens) and seeing or hearing things that others do not see or hear (hallucinations) along with other medicines for the relief of muscle spasms along with other medicines to treat seizure disorders VALIUM is a federal controlled substance (C-IV) because it contains diazepam that can be abused or lead to dependence.
Keep VALIUM in a safe place to prevent misuse and abuse. Selling or giving away VALIUM may harm others, and is against the law. Tell your healthcare provider if you have abused or been dependent on alcohol, prescription medicines or street drugs.
It is not known if VALIUM is safe and effective in children under 6 months of age. It is not known if VALIUM is safe and effective for use longer than 4 months. Do not take VALIUM if you: are allergic to diazepam or any of the ingredients in… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS General If Valium is to be combined with other psychotropic agents or anticonvulsant drugs, careful consideration should be given to the pharmacology of the agents to be employed - particularly with known compounds that may potentiate the action of diazepam, such as phenothiazines, narcotics, barbiturates, MAO inhibitors and other antidepressants (see Drug Interactions ). The usual precautions are indicated for severely depressed patients or those in whom there is any evidence of latent depression or anxiety associated with depression, particularly the recognition that suicidal tendencies may be present and protective measures may be necessary.
Psychiatric and paradoxical reactions are known to occur when using benzodiazepines (see ADVERSE REACTIONS ). Should this occur, use of the drug should be discontinued. These reactions are more likely to occur in children and the elderly.
A lower dose is recommended for patients with chronic respiratory insufficiency, due to the risk of respiratory depression. Benzodiazepines should be used with extreme caution in patients with a history of alcohol or drug abuse (see DRUG ABUSE AND DEPENDENCE ). In debilitated patients, it is recommended that the dosage be limited to the smallest effective amount to preclude the development of ataxia or oversedation (2 mg to 2.5 mg once or twice daily, initially, to be increased gradually as needed and tolerated).
Some loss of response to the effects of benzodiazepines may develop after repeated use of Valium for a prolonged time. Information for Patients Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when Valium is used with opioids and not to use such drugs concomitantly unless supervised by a health care provider.
Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see WARNINGS: Risks from Concomitant Use with Opioids and PRECAUTIONS: Drug Interactions ). Abuse, Misuse, and Addiction Inform patients that the use of Valium, even at recommended dosages, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances.
Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug (see WARNINGS: Abuse, Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE ). Withdrawal Reactions Inform patients that the continued use of Valium may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of Valium may precipitate acute withdrawal reactions, which can be life-threatening.
Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of Valium may require a slow taper (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE ). Patients should be advised against the simultaneous ingestion of alcohol and other CNS-depressant drugs during Valium therapy.
As is true of most CNS-acting drugs, patients receiving Valium should be cautioned against engaging in hazardous occupations requiring complete mental alertness, such as operating machinery or driving a motor vehicle. Drug Interactions Opioids The concomitant use of benzodiazepines and opioids increases the risk of respiratory depression because of actions at different receptor sites in the CNS that control respiration. Benzodiazepines interact at GABA A sites and opioids interact primarily at mu receptors.
Whe… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption After oral administration >90% of diazepam is absorbed and the average time to achieve peak plasma concentrations is 1 – 1.5 hours with a range of 0.25 to 2.5 hours. Absorption is delayed and decreased when administered with a moderate fat meal. In the presence of food mean lag times are approximately 45 minutes as compared with 15 minutes when fasting.
There is also an increase in the average time to achieve peak concentrations to about 2.5 hours in the presence of food as compared with 1.25 hours when fasting. This results in an average decrease in C max of 20% in addition to a 27% decrease in AUC (range 15% to 50%) when administered with food. Distribution Diazepam and its metabolites are highly bound to plasma proteins (diazepam 98%).
Diazepam and its metabolites cross the blood-brain and placental barriers and are also found in breast milk in concentrations approximately one tenth of those in maternal plasma (days 3 to 9 post-partum). In young healthy males, the volume of distribution at steady-state is 0.8 to
1.0L/kg. The decline in the plasma concentration-time profile after oral administration is biphasic. The initial distribution phase has a half-life of approximately 1 hour, although it may range up to >3 hours.
Metabolism Diazepam is N-demethylated by CYP3A4 and 2C19 to the active metabolite N-desmethyldiazepam, and is hydroxylated by CYP3A4 to the active metabolite temazepam. N-desmethyldiazepam and temazepam are both further metabolized to oxazepam. Temazepam and oxazepam are largely eliminated by glucuronidation.
Elimination The initial distribution phase is followed by a prolonged terminal elimination phase (half-life up to 48 hours). The terminal elimination half-life of the active metabolite N-desmethyldiazepam is up to 100 hours. Diazepam and its metabolites are excreted mainly in the urine, predominantly as their glucuronide conjugates.
The clearance of diazepam is 20 to 30 mL/min in young adults. Diazepam accumulates upon multiple dosing and there is some evidence that the terminal elimination half-life is slightly prolonged. Pharmacokinetics in Special Populations Children In children 3 - 8 years old the mean half-life of diazepam has been reported to be 18 hours.
Newborns In full term infants, elimination half-lives around 30 hours have been reported, with a longer average half-life of 54 hours reported in premature infants of 28 - 34 weeks gestational age and 8 - 81 days post-partum. In both premature and full term infants the active metabolite desmethyldiazepam shows evidence of continued accumulation compared to children. Longer half-lives in infants may be due to incomplete maturation of metabolic pathways.
Geriatric Elimination half-life increases by approximately 1 hour for each year of age beginning with a half-life of 20 hours at 20 years of age. This appears to be due to an increase in volume of distribution with age and a decrease in clearance. Consequently, the elderly may have lower peak concentrations, and on multiple dosing higher trough concentrations.
It will also take longer to reach steady-state. Conflicting information has been published on changes of plasma protein binding in the elderly. Reported changes in free drug may be due to significant decreases in plasma proteins due to causes other than simply aging.
Hepatic Insufficiency In mild and moderate cirrhosis, average half-life is increased. The average increase has been variously reported from 2-fold to 5-fold, with individual half-lives over 500 hours reported. There is also an increase in volume of distribution, and average clearance decreases by almost half.
Mean half-life is also prolonged with hepatic fibrosis to 90 hours (range 66 - 104 hours), with chronic active hepatitis to 60 hours (range 26 - 76 hours), and with acute viral hepatitis to 74 hours (range 49 - 129). In chronic active hepatitis, clearance is decreased by almost half.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Controlled Substance Valium contains diazepam, a Schedule IV controlled substance. Abuse Valium is a benzodiazepine and a CNS depressant with a potential for abuse and addiction. Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects.
Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Even taking benzodiazepines as prescribed may put patients at risk for abuse and misuse of their medication. Abuse and misuse of benzodiazepines may lead to addiction. Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death.
Benzodiazepines are often sought by individuals who abuse drugs and other substances, and by individuals with addictive disorders (see WARNINGS: Abuse, Misuse, and Addiction ). The following adverse reactions have occurred with benzodiazepine abuse and/or misuse: abdominal pain, amnesia, anorexia, anxiety, aggression, ataxia, blurred vision, confusion, depression, disinhibition, disorientation, dizziness, euphoria, impaired concentration and memory, indigestion, irritability, muscle pain, slurred speech, tremors, and vertigo.
The following severe adverse reactions have occurred with benzodiazepine abuse and/or misuse: delirium, paranoia, suicidal ideation and behavior, seizures, coma, breathing difficulty, and death. Death is more often associated with polysubstance use (especially benzodiazepines with other CNS depressants such as opioids and alcohol). Dependence Physical Dependence Valium may produce physical dependence from continued therapy.
Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Abrupt discontinuation or rapid dosage reduction of benzodiazepines or administration of flumazenil, a benzodiazepine antagonist, may precipitate acute withdrawal reactions, including seizures, which can be life-threatening. Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages (i.e., higher and/or more frequent doses), those who have had longer durations of use (see WARNINGS: Dependence and Withdrawal Reactions ).
To reduce the risk of withdrawal reactions, use a gradual taper to discontinue Valium or reduce the dosage (see DOSAGE and ADMINISTRATION: Discontinuation or Dosage Reduction of Valium and WARNINGS: Dependence and Withdrawal Reactions ). Acute Withdrawal Signs and Symptoms Acute withdrawal signs and symptoms associated with benzodiazepines have included abnormal involuntary movements, anxiety, blurred vision, depersonalization, depression, derealization, dizziness, fatigue, gastrointestinal adverse reactions (e.g., nausea, vomiting, diarrhea, weight loss, decreased appetite), headache, hyperacusis, hypertension, irritability, insomnia, memory impairment, muscle pain and stiffness, panic attacks, photophobia, restlessness, tachycardia, and tremor.
More severe acute withdrawal signs and symptoms, including life-threatening reactions, have included catatonia, convulsions, delirium tremen… [Excerpted — this section continues on DailyMed.]
🔒 Controlled Substance ▾
Controlled Substance Valium contains diazepam, a Schedule IV controlled substance.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility In studies in which mice and rats were administered diazepam in the diet at a dose of 75 mg/kg/day (approximately 6 and 12 times, respectively, the maximum recommended human dose [MRHD=1 mg/kg/day] on a mg/m 2 basis) for 80 and 104 weeks, respectively, an increased incidence of liver tumors was observed in males of both species. The data currently available are inadequate to determine the mutagenic potential of diazepam. Reproduction studies in rats showed decreases in the number of pregnancies and in the number of surviving offspring following administration of an oral dose of 100 mg/kg/day (approximately 16 times the MRHD on a mg/m 2 basis) prior to and during mating and throughout gestation and lactation.
No adverse effects on fertility or offspring viability were noted at a dose of 80 mg/kg/day (approximately 13 times the MRHD on a mg/m 2 basis).
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 2 mg Tablet Bottle Label NDC 0140-0004-01 Valium ® (diazepam) CIV 2 mg Each tablet contains 2 mg diazepam. Rx only 100 tablets Roche 10185528 PRINCIPAL DISPLAY PANEL - 2 mg Tablet Bottle Label
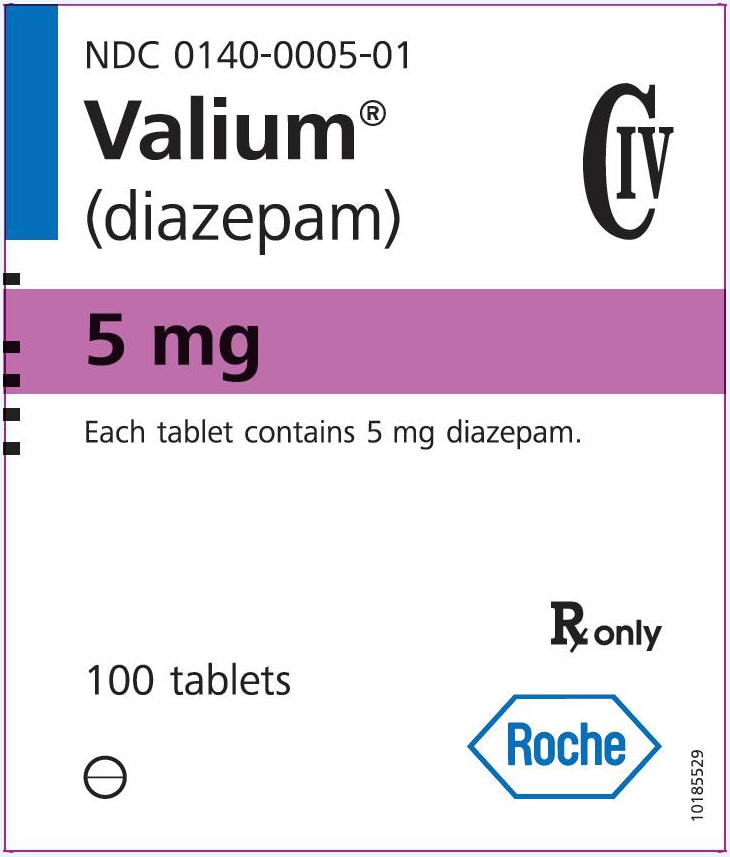
PRINCIPAL DISPLAY PANEL - 5 mg Tablet Bottle Label NDC 0140-0005-01 Valium ® (diazepam) CIV 5 mg Each tablet contains 5 mg diazepam. Rx only 100 tablets Roche 10185529 PRINCIPAL DISPLAY PANEL - 5 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg Tablet Bottle Label NDC 0140-0006-01 Valium ® (diazepam) CIV 10 mg Each tablet contains 10 mg diazepam. Rx only 100 tablets Roche 10185530 PRINCIPAL DISPLAY PANEL - 10 mg Tablet Bottle Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |