
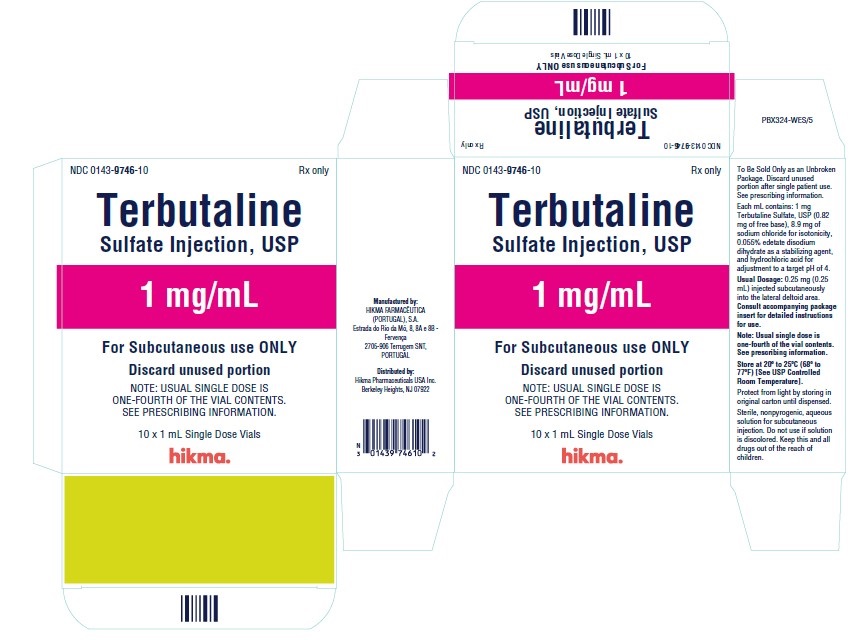
Terbutaline Sulfate 1 mg/mL Injection, 10 vials
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Selective beta-2-adrenoreceptor agonists class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Terbutaline injection is used to treat wheezing, shortness of breath, coughing, and chest tightness caused by asthma, chronic bronchitis, and emphysema. Terbutaline is in a class of medications called beta agonists. It works by relaxing and opening the airways, making it easier to breathe.
Read the full MedlinePlus article ↗- Terbutaline is a bronchodilator — it relaxes and opens up the airways in your lungs. It's approved to prevent and relieve bronchospasm (that tight, wheezy feeling when your airways...
- The injection form works quite fast — you can notice an improvement in airflow within about 5 minutes, with a more significant benefit kicking in within 15 minutes. The tablet form...
- The most common things people notice are shakiness (tremor), nervousness, headache, dizziness, and a faster or pounding heartbeat. These are usually temporary and tend to settle do...
- What side effects should I expect — and which ones should make me call my doctor?
Patient education
Supplement & herbal interactions
Terbutaline may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $9.85 | $98.47 / 10 vials |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J3105 | $2.820 / J3105 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Terbutaline Sulfate 1 mg/mL 00143-9375-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Terbutaline Sulfate 1 mg/mLthis 00143-9746-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Terbutaline Sulfate 1 mg/mL 00404-9962-01 | Henry | 1 vial | — | AP | FDA listed | — |
| Terbutaline Sulfate 1 mg/mL 63323-0665-01 | Fresenius | 25 vials | — | AP | FDA listed | — |
| Terbutaline Sulfate 1 mg/mL 71872-7080-01 | Medical | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00143-9746-10 You're viewing this | 10 VIAL in 1 CARTON (0143-9746-10) / 1 mL in 1 VIAL (0143-9746-01) | 2009-05-20 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: PROLONGED TOCOLYSIS Terbutaline sulfate has not been approved and should not be used for prolonged tocolysis (beyond 48-72 hours). In particular, terbutaline sulfate should not be used for maintenance tocolysis in the outpatient or home setting. Serious adverse reactions, including death, have been reported after administration of terbutaline sulfate to pregnant women.
In the mother, these adverse reactions include increased heart rate, transient hyperglycemia, hypokalemia, cardiac arrhythmias, pulmonary edema and myocardial ischemia. Increased fetal heart rate and neonatal hypoglycemia may occur as a result of maternal administration (see CONTRAINDICATIONS: Prolonged Tocolysis ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Terbutaline Sulfate Injection, USP is indicated for the prevention and reversal of bronchospasm in patients 12 years of age and older with asthma and reversible bronchospasm associated with bronchitis and emphysema.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Vials should be used only for subcutaneous administration and not intravenous infusion. Sterility and accurate dosing cannot be assured if the vials are not used in accordance with DOSAGE AND ADMINISTRATION . Discard unused portion after single patient use.
The usual subcutaneous dose of terbutaline sulfate injection is 0.25 mg injected into the lateral deltoid area. If significant clinical improvement does not occur within 15 to 30 minutes, a second dose of 0.25 mg may be administered. If the patient then fails to respond within another 15 to 30 minutes, other therapeutic measures should be considered.
The total dose within 4 hours should not exceed 0.5 mg. Note: Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
⛔ Contraindications ▾
CONTRAINDICATIONS 1. Prolonged Tocolysis Terbutaline sulfate has not been approved and should not be used for prolonged tocolysis (beyond 48-72 hours). In particular, terbutaline sulfate should not be used for maintenance tocolysis in the outpatient or home setting (see BOXED WARNING: Prolonged Tocolysis ).
2. Hypersensitivity Terbutaline sulfate injection is contraindicated in patients known to be hypersensitive to sympathomimetic amines or any component of this drug product.
⚠️ Warnings ▾
WARNINGS Deterioration of Asthma Asthma may deteriorate acutely over a period of hours or chronically over several days or longer. If the patient needs more doses of terbutaline sulfate than usual, this may be a marker of destabilization of asthma and requires reevaluation of the patient and treatment regimen, giving special consideration to the possible need for anti‑inflammatory treatment, e.g., corticosteroids. Use of Anti-Inflammatory Agents The use of beta-adrenergic agonist bronchodilators alone may not be adequate to control asthma in many patients.
Early consideration should be given to adding anti‑inflammatory agents, e.g., corticosteroids. Cardiovascular Effects Terbutaline sulfate, like all other beta-adrenergic agonists, can produce a clinically significant cardiovascular effect in some patients as measured by pulse rate, blood pressure, and/or symptoms. Although such effects are uncommon after administration of terbutaline sulfate at recommended doses, if they occur, the drug may need to be discontinued.
In addition, beta‑agonists have been reported to produce electrocardiogram (ECG) changes, such as flattening of the T wave, prolongation of the QTc interval, and ST segment depression. The clinical significance of these findings is unknown. Therefore, terbutaline sulfate, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias, and hypertension.
Seizures There have been rare reports of seizures in patients receiving terbutaline; seizures did not recur in these patients after the drug was discontinued.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions observed with terbutaline sulfate injection are similar to those commonly seen with other sympathomimetic agents. All these reactions are transient in nature and usually do not require treatment. The following table compares adverse reactions seen in patients treated with terbutaline sulfate injection (0.25 mg and 0.5 mg), with those seen in patients treated with epinephrine injection (0.25 mg and 0.5 mg), during eight double-blind crossover studies involving a total of 214 patients.
Incidence (%) of Adverse Reactions Terbutaline (%) Epinephrine (%) 0.25 mg N = 77 0.5 mg N = 205 0.25 mg N = 153 0.5 mg N = 61 Reaction Central Nervous System Tremor 7.8 38.0 16.3
18.0Nervousness 16.9 30.7 8.5
31.1Dizziness 1.3 10.2 7.8
3.3Headache 7.8 8.8 3.3
9.8Drowsiness 11.7 9.8 14.4
8.2Cardiovascular Palpitations 7.8 22.9 7.8
29.5Tachycardia 1.3 1.5 2.6
0.0Respiratory Dyspnea 0.0 2.0 2.0
0.0Chest discomfort 1.3 1.5 2.6
0.0Gastrointestinal Nausea/vomiting 1.3 3.9 1.3
11.5Systemic Weakness 1.3 0.5 2.6
1.6Flushed feeling 0.0 2.4 1.3
0.0Sweating 0.0 2.4 0.0
0.0Pain at injection site 2.6 0.5 2.6
1.6Note: Some patients received more than one dosage strength of terbutaline sulfate and epinephrine. In addition, there were reports of anxiety, muscle cramps, and dry mouth (< 0.5%). There have been rare reports of elevations in liver enzymes and of hypersensitivity vasculitis with terbutaline administration.
To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-877-845-0689, or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
Drug Interactions The concomitant use of terbutaline sulfate injection with other sympathomimetic agents is not recommended, since the combined effect on the cardiovascular system may be deleterious to the patient. Monoamine Oxidase Inhibitors or Tricyclic Antidepressants: Terbutaline should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants, or within 2 weeks of discontinuation of such agents, since the action of terbutaline on the vascular system may be potentiated.
Beta-Blockers: Beta-adrenergic receptor blocking agents not only block the pulmonary effect of beta-agonists, such as terbutaline sulfate injection, but may produce severe bronchospasm in asthmatic patients. Therefore, patients with asthma should not normally be treated with beta‑blockers. However, under certain circumstances, e.g., as prophylaxis after myocardial infarction, there may be no acceptable alternatives to the use of beta-adrenergic blocking agents in patients with asthma.
In this setting, cardioselective betablockers could be considered, although they should be administered with caution. Diuretics: The ECG changes and/or hypokalemia that may result from the administration of nonpotassium-sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of beta-agonists with nonpotassium-sparing diuretics.
🤰 Pregnancy ▾
Pregnancy -Teratogenic Effects There are no adequate and well-controlled studies of terbutaline sulfate in pregnant women. Published animal studies show that rat offspring exhibit alterations in behavior and brain development, including decreased cellular proliferation and differentiation when dams were treated subcutaneously with terbutaline during the late stage of pregnancy and lactation period. Terbutaline exposures in rat dams were approximately 24 to 48 times the common human dose in adults of 2-4 mg/day, on a mg/m 2 basis.
Terbutaline sulfate has not been approved and should not be used for prolonged tocolysis (beyond 48-72 hours). In particular, terbutaline sulfate should not be used for maintenance tocolysis in the outpatient or home setting. Serious adverse reactions, including death, have been reported after administration of terbutaline sulfate to pregnant women.
In the mother, these adverse reactions include increased heart rate, transient hyperglycemia, hypokalemia, cardiac arrhythmias, pulmonary edema and myocardial ischemia. Increased fetal heart rate and neonatal hypoglycemia may occur as a result of maternal administration (see BOXED WARNING: Prolonged Tocolysis and CONTRAINDICATIONS: Prolonged Tocolysis ). In animal embryofetal developmental studies, no teratogenic effects were observed in offspring when pregnant rats and rabbits received terbutaline sulfate at oral doses up to 50 mg/kg/day, approximately 810 and 1,600 times, respectively, the maximum recommended daily subcutaneous dose for adults, on a mg/m 2 basis.
Terbutaline sulfate should be used during pregnancy only if the potential benefits justify the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Terbutaline sulfate injection is not recommended for patients under the age of 12 years because of insufficient clinical data to establish safety and effectiveness.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of terbutaline sulfate injection did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE The median sc lethal dose of terbutaline sulfate in mature rats was approximately 165 mg/kg (approximately 2,700 times the maximum recommended daily sc dose for adults on a mg/m 2 basis). The median sc lethal dose of terbutaline sulfate in young rats was approximately 2,000 mg/kg (approximately 32,000 times the maximum recommended daily sc dose for adults on a mg/m 2 basis). The expected symptoms with overdosage are those of excessive beta-adrenergic stimulation and/or occurrence or exaggeration of any of the symptoms listed under ADVERSE REACTIONS , e.g., seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats per minute, arrhythmias, nervousness, headache, tremor, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, and insomnia.
Hypokalemia may also occur. There is no specific antidote. Treatment consists of discontinuation of terbutaline sulfate injection together with appropriate symptomatic therapy.
The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of terbutaline sulfate injection.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Terbutaline sulfate injection is a beta-adrenergic receptor agonist. In vitro and in vivo pharmacologic studies have demonstrated that terbutaline exerts a preferential effect on beta 2 ‑adrenergic receptors. While it is recognized that beta 2 -adrenergic receptors are the predominant receptors in bronchial smooth muscle, data indicate that there is a population of beta 2 -receptors in the human heart, existing in a concentration between 10% to 50%.
The precise function of these receptors has not been established (see WARNINGS ). Controlled clinical studies in patients given terbutaline subcutaneously have not revealed a preferential beta 2 -adrenergic effect. The pharmacologic effects of beta-adrenergic agonists, including terbutaline, are at least in part attributable to stimulation through beta-adrenergic receptors of intracellular adenyl cyclase, the enzyme which catalyzes the conversion of adenosine triphosphate (ATP) to cyclic 3’,5’-adenosine monophosphate (cAMP).
Increased cAMP levels are associated with relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells. Controlled clinical studies have shown that terbutaline sulfate injection relieves bronchospasm in acute and chronic obstructive pulmonary disease by significantly increasing pulmonary flow rates (e.g., an increase of 15% or more in FEV 1 ). After subcutaneous administration of 0.25 mg of terbutaline sulfate injection, a measurable change in expiratory flow rate usually occurs within 5 minutes, and a clinically significant increase in FEV 1 occurs within 15 minutes.
The maximum effect usually occurs within 30 to 60 minutes, and clinically significant bronchodilator activity may continue for 1.5 to 4 hours. The duration of clinically significant improvement is comparable to that observed with equimilligram doses of epinephrine. Preclinical Studies in laboratory animals (minipigs, rodents, and dogs) have demonstrated the occurrence of cardiac arrhythmias and sudden death (with histological evidence of myocardial necrosis) when beta-agonists and methylxanthines are administered concurrently.
The clinical significance of these findings is unknown. Pharmacokinetics Subcutaneous administration of 0.5 mg of terbutaline sulfate to 17 healthy, adult, male subjects resulted in mean (SD) peak plasma terbutaline concentration of 9.6 (3.6) ng/mL, which was observed at a median (range) time of 0.5 (0.08 to 1.0) hours after dosing. The mean (SD) AUC (0 to 48) and total body clearance values were 29.4 (14.2) hr•ng/mL, and 311 (112) mL/min respectively.
The terminal half-life was determined in 9 of the 17 subjects and had a mean (SD) of 5.7 (2.0) hours. After subcutaneous administration of 0.25 mg of terbutaline sulfate to two male subjects, peak terbutaline serum concentrations of 5.2 and 5.3 ng/mL were observed at about 20 minutes after dosing. Elimination half-life of the drug in 10 of 14 patients was approximately 2.9 hours after subcutaneous administration, but longer elimination half-lives (between 6 to 14 hours) were found in the other 4 patients.
About 90% of the drug was excreted in the urine at 96 hours after subcutaneous administration, with about 60% of this being unchanged drug. It appears that the sulfate conjugate is a major metabolite of terbutaline and urinary excretion is the primary route of elimination.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Terbutaline Sulfate Injection, USP, 1 mg/mL, is supplied at a volume of 1 mL contained in a 2 mL amber glass vial. Each vial contains 1 mg of terbutaline sulfate per 1 mL of solution; 0.25 mL of solution will provide the usual clinical dose of 0.25 mg. NDC 0143-9746-10 Carton of 10 vials.
Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Protect from light by storing vials in original carton until dispensed. Do not use if solution is discolored.
Discard unused portion after single patient use. Manufactured by: HIKMA FARMACÊUTICA (PORTUGAL), S.A.. Estrada do Rio da Mó, nº 8, 8A e 8B - Fervença, 2705 – 906 Terrugem SNT, PORTUGAL Distributed by: Hikma Pharmaceuticals USA Inc.
Berkeley Heights, NJ 07922 Revised: February 2021 PIN217-WES/4
📋 Description ▾
DESCRIPTION Terbutaline Sulfate, USP, the active ingredient of Terbutaline Sulfate Injection, USP, is a beta‑adrenergic agonist bronchodilator available as a sterile, nonpyrogenic, aqueous solution in vials, for subcutaneous administration. Each milliliter of solution contains 1 mg of Terbutaline Sulfate, USP (0.82 mg of the free base), sodium chloride for isotonicity, 0.055% edetate disodium dihydrate as a stabilizing agent, and hydrochloric acid for adjustment to a target pH of 4. Terbutaline sulfate is (±)-α-[( tert ‑butylamino) methyl]-3,5-dihydroxybenzyI alcohol sulfate (2:1) (salt).
The molecular formula is (C 12 H 19 N0 3 ) 2 •H 2 SO 4 and the structural formula is: Terbutaline Sulfate, USP is a white to gray-white crystalline powder. It is odorless or has a faint odor of acetic acid. It is soluble in water and in 0.1N hydrochloric acid, slightly soluble in methanol, and insoluble in chloroform.
Its molecular weight is 548.65. Terbutaline Sulfate structure